


Product Monograph - Mint-Nadolol
CLINICAL TRIALS
A double-blinded, randomized, balanced, two-treatment, two-period, two-sequence, single-dose, crossover, oral bioequivalence study of MINT-NADOLOL 80 mg tablets (Mint Pharmaceuticals Inc.) and NADOLOL 80 mg tablets (AA Pharma Inc.) was performed in 47 healthy, adult, Asian male human subjects under fasting conditions. The pharmacokinetic data from the 40 subjects who completed the study are summarized in the following table.
SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILITY DATA
Nadolol (1 x 80 mg) From measured data Geometric Mean Arithmetic Mean (CV %) | ||||
|---|---|---|---|---|
| Parameter | Test* | Reference† | % Ratio of Geometric Means | 90% Confidence Interval |
AUCT (ng∙hr/mL) | 3321.44 3530.82 (33.67) | 3153.70 3297.58 (29.40) | 105.3 | 96.0 – 115.5 |
AUCI (ng∙hr/mL) | 3414.81 3626.07 (33.29) | 3236.55 3381.90 (29.23) | 105.5 | 96.3 – 115.6 |
Cmax (ng/mL) | 258.60 291.24 (51.90) | 246.86 275.73 (52.35) | 104.8 | 90.5 – 121.2 |
Tmax§ (hr) | 3.00 (1.50 – 8.00) | 3.17 (0.50 – 6.00) | ||
T½€ (hr) | 13.68 (12.16) | 13.69 (13.10) | ||
*MINT-NADOLOL (nadolol) 80 mg tablets (Mint Pharmaceuticals Inc.)
† NADOLOL (nadolol) 80 mg tablets (AA PHARMA INC.) were purchased in Canada.
§Expressed as the median (range) only.
€Expressed as the arithmetic mean (CV%) only.
INDICATIONS
Angina:
MINT-NADOLOL (nadolol) is indicated for prophylaxis of angina pectoris.
Hypertension:
MINT-NADOLOL is indicated in patients with mild or moderate hypertension. MINT-NADOLOL is usually used in combination with other drugs, particularly a thiazide diuretic. However, it may be tried alone as an initial agent in those patients in whom, in the judgment of the physician, treatment should be started with a beta-blocker rather than a diuretic.
The combination of nadolol with a diuretic has been found to be compatible and generally more effective than nadolol alone. In a few cases where peripheral vasodilators were used with nadolol, no evidence of incompatibility was seen.
MINT-NADOLOL is not recommended for the emergency treatment of hypertensive crises.
CONTRAINDICATIONS
Allergic rhinitis, bronchospasm (including bronchial asthma), or severe chronic obstructive pulmonary disease (see PRECAUTIONS).
Sinus bradycardia.
Second and third degree A-V block.
Right ventricular failure secondary to pulmonary hypertension.
Congestive heart failure (see WARNINGS).
Cardiogenic shock.
Anesthesia with agents that produce myocardial depression, e.g. ether.
Hypersensitivity to nadolol.
WARNINGS
Cardiac Failure:
Special cautions should be exercised when administering MINT-NADOLOL (nadolol) to patients with a history of heart failure. Sympathetic stimulation is a vital component supporting circulatory function in congestive heart failure, and inhibition with beta blockade always carries a potential hazard of further depressing myocardial contractility and precipitating cardiac failure. In patients without a history of cardiac failure, continued depression of the myocardium over a period of time can, in some cases, lead to cardiac failure. Therefore, at the first sign or symptom of impending cardiac failure during MINT-NADOLOL therapy, patients should be fully digitalized, and/or given a diuretic, and the response observed closely.
Nadolol acts selectively without blocking the inotropic action of digitalis on the heart muscle. However, the positive inotropic action of digitalis may be reduced by the negative inotropic effect of nadolol when the two drugs are used concomitantly. The effects of nadolol and digitalis are additive in depressing A-V conduction. If cardiac failure continues despite adequate digitalization and diuretic therapy MINT-NADOLOL therapy should be discontinued (see WARNING below).
Abrupt Cessation of Therapy with MINT-NADOLOL:
Patients with angina should be warned against abrupt discontinuation of MINT-NADOLOL. There have been reports of severe exacerbation of angina, and of myocardial infarction or ventricular arrhythmias occurring in patients with angina pectoris, following abrupt discontinuation of beta- blocker therapy. The last two complications may occur with or without preceding exacerbation of angina pectoris. Therefore, when discontinuation of MINT-NADOLOL is planned in patients with angina pectoris, the dosage should be gradually reduced over a period of about 2 weeks and the patient should be carefully observed. The same frequency of administration should be maintained.
In situations of greater urgency, MINT-NADOLOL therapy should be discontinued stepwise and under conditions of closer observation. If angina markedly worsens or acute coronary insufficiency develops, it is recommended that treatment with MINT-NADOLOL be reinstituted promptly, at least temporarily.
Various skin rashes and conjunctival xerosis have been reported with beta-blockers including nadolol. A severe syndrome (oculo-muco-cutaneous syndrome) whose signs include conjunctivitis sicca and psoriasiform rashes, otitis and sclerosing serositis has occurred with the chronic use of one
beta-adrenergic-blocking agent (practolol). This syndrome has not been observed with nadolol or any other such agent. However, physicians should be alert to the possibility of such reactions and should discontinue treatment in the event that they occur.
Severe sinus bradycardia due to unopposed vagal activity occurs in approximately 3% of patients following administration of nadolol. In such cases, dosage should be reduced or the use of intravenous atropine could be considered; if no improvement is seen, intravenous isoproterenol should be considered
In patients with thyrotoxicosis, nadolol may give a false impression of improvement by diminishing peripheral manifestations of hyperthyroidism without improving thyroid function; therefore, abrupt withdrawal may be followed by an exacerbation of the symptoms of hyperthyroidism, including
thyroid storm.
PRECAUTIONS
MINT-NADOLOL (nadolol) should be administered with caution to patients prone to non-allergic bronchospasm (e.g., chronic bronchitis, emphysema) since it may block bronchodilation produced by endogenous and exogenous catecholamine stimulation of beta receptors.
There may be increased difficulty in treating an allergic type reaction in patients on beta-blockers. In these patients, the reaction may be more severe due to pharmacologic effects of the beta-blockers and problems with fluid changes. Epinephrine should be administered with caution since it may not have its usual effects in the treatment of anaphylaxis. On the one hand, larger doses of epinephrine may be needed to overcome the bronchospasm, while on the other those doses can be associated with excessive alpha-adrenergic stimulation with consequent hypertension, reflex bradycardia and heart block and possible potentiation of bronchospasm. Alternatives to the use of large doses of epinephrine include vigorous supportive care such as fluids and the use of beta-agonists including parenteral salbutamol or isoproterenol to overcome bronchospasm and norepinephrine to overcome hypotension.
MINT-NADOLOL should be administered with caution to patients subject to spontaneous hypoglycemia, or to diabetic patients (especially those with labile diabetes) who are receiving insulin or oral hypoglycemic agents. Beta-adrenergic blockers may mask the premonitory signs and symptoms of acute hypoglycemia. As beta-blockade also reduces the release of insulin in response to hyperglycemia, it may be necessary to adjust the dosage of anti-diabetic drugs.
MINT-NADOLOL dosage should be individually adjusted when used concomitantly with other antihypertensive agents (see DOSAGE AND ADMINISTRATION).
Patients receiving catecholamine-depleting drugs, such as reserpine and guanethidine, should be closely monitored if MINT-NADOLOL is administered concomitantly. The added catecholamine blocking action of nadolol may produce an excessive reduction of the resting sympathetic nervous activity.
Concomitant use of fingolimod with beta blockers may potentiate bradycardic effects and is not recommended. Where such coadministration is considered necessary, appropriate monitoring at treatment initiation, i.e. at least overnight monitoring, is recommended.
Suitable laboratory tests should be carried out at appropriate intervals and caution should be observed in patients with impaired renal or hepatic function. Since nadolol is excreted mainly by the kidneys, dosage reduction may be necessary when renal insufficiency is present.
In Patients Undergoing Elective or Emergency Surgery:
The management of patients being treated with beta-blockers and undergoing elective or emergency surgery is controversial. Although beta-adrenergic-receptor blockade impairs the ability of the heart to respond to beta-adrenergically-mediated reflex stimuli, abrupt discontinuation of therapy with MINT-NADOLOL may be followed by severe complications (see WARNINGS). Some patients receiving beta-adrenergic-blocking agents have been subject to protracted severe hypotension during anesthesia. Difficulty in restarting and maintaining the heart beat has also been reported.
For these reasons, in patients with angina undergoing elective surgery, MINT-NADOLOL should be withdrawn gradually following the recommendation given under Abrupt Cessation of Therapy (see WARNINGS). The available evidence suggests that the clinical and physiologic effects of beta- blockade induced by nadolol are essentially absent 5 days after cessation of therapy.
In emergency surgery, since nadolol is a competitive inhibitor of beta-adrenergic-receptor agonists, its effects may be reversed, if necessary, by sufficient doses of such agonists as isoproterenol or
levarterenol.
Usage in Pregnancy and Nursing Mothers:
Since nadolol has not been studied in human pregnancy, the drug should not be given to pregnant women. The use of any drug in patients of child-bearing potential requires that the anticipated benefit be weighed against possible hazards.
When given to pregnant rats, nadolol readily crossed the placental barrier. Nadolol was found to be concentrated in the milk of lactating rats. Information in humans is lacking. Therefore, the use of this drug in lactating women is not recommended.
Usage in Children:
There is no experience with nadolol in the treatment of pediatric age groups.
ADVERSE REACTIONS
The most serious adverse reactions encountered are congestive heart failure, A-V block and bronchospasm.
The most common adverse reactions reported are severe bradycardia (3%), dizziness (3%), fatigue (2%), hypotension (1%), congestive heart failure (1%), and cold sensations (1%).
Adverse reactions, grouped by system are as follows:
Cardiovascular:
- Congestive heart failure, pulmonary edema, cardiac enlargement. Rhythm or conduction disturbances including A-V block, bigeminy and Adams-Stokes syndrome.
- Chest pain
- Severe bradycardia
- Hypotension, orthostatic hypotension, and syncope.
- Peripheral vascular insufficiency including intermittent claudication and cold extremities
- Edema
Respiratory:
- Bronchospasm
- Dyspnea
- Cough
Central Nervous System:
- Dizziness
- Depression, anxiety, nervousness, irritability, and hallucinations
- Lethargy, fatigue
- Sleep disturbances including insomnia and nightmares
- Paresthesia
- Headache
- Tinnitus Slurred speech
Gastrointestinal:
- Abdominal pain or pressure
- Nausea, vomiting, diarrhea, constipation, and flatulence
- Gastritis
- Anorexia
Dermatological (See WARNINGS):
- Rash
- Pruritus
- Dry skin
Ophthalmologic:
- Conjunctivitis
- Blurred vision
- Dry eyes
Miscellaneous:
- Impotence, decreased libido
- Enlarged thyroid
- Nasal stuffiness, dry mouth, sweating
- Weight gain
Clinical Laboratory:
The following parameters have most frequently been found to be outside the normal range: serum triglycerides, blood glucose, serum potassium, SGOT, SGPT, LDH, BUN.
SYMPTOMS AND TREATMENT OF OVERDOSAGE
The most common signs to be expected with overdosage of a beta-adrenergic blocking agent are bradycardia, congestive heart failure, hypotension, bronchospasm, and hypoglycemia.
If overdosage occurs, in all cases therapy with MINT-NADOLOL (nadolol) should be discontinued and the patient observed closely. In addition, if required, the following therapeutic measures are suggested:
- 1. Bradycardia: Atropine or another anticholinergic drug.
- 2. Heart Block:(second or third degree): Isoproterenol or transvenous cardiac pacemaker.
- 3.
Congestive Heart Failure:
Conventional therapy.
- 4.
Hypotension (depending on associated factors):
Epinephrine rather than isoproterenol or norepinephrine may be useful in addition to atropine and digitalis (see precautions concerning the use of epinephrine in beta-blocked patients).
- 5. Bronchospasm: Aminophylline or isoproterenol.
- 6.
Hypoglycemia:
Intravenous glucose.
It should be remembered that nadolol is a competitive antagonist of isoproterenol and hence large doses of isoproterenol can be expected to reverse many of the effects of excessive doses of nadolol. However, the complications of excess isoproterenol should not be overlooked.
DOSAGE AND ADMINISTRATION
It is recommended that MINT-NADOLOL (nadolol) be administered as a single daily dose. MINT-NADOLOL may be administered without regard to meals since the presence of food
If you think you have taken too much MINT-NADOLOL, contact your healthcare professional, hospital emergency department or regional Poison Control Centre immediately, even if there are no symptoms.
in the gastrointestinal tract does not affect the rate or extent of nadolol absorption.
MINT-NADOLOL dosage must always be adjusted to the individual needs of the patient, in accordance with the following guidelines:
Angina Pectoris:
MINT-NADOLOL treatment should be initiated with doses of 80 mg daily. If an adequate response is not observed after one week, dosage may be increased by 80 mg increments at weekly intervals, until a satisfactory response is achieved. The maximum recommended daily dose is 240 mg. Patients stabilized on 80 mg daily might be tried on 40 mg daily as this dose has been found to be effective in some cases.
The value and safety of doses above 240 mg daily in angina pectoris have not been established.
Hypertension:
MINT-NADOLOL treatment should be initiated with doses of 80 mg daily. If an adequate response is not observed after one week, dosage may be increased by 80 mg increments at weekly intervals, until a satisfactory response is achieved. The maximum recommended daily dose is 320 mg, although most patients respond to 240 mg or less. The value and safety of doses above 320 mg daily have not been established.
AVAILABILITY
40 mg tablets: Round, white to off white, biconvex tablets, debossed MN above the break line, 40 below the break line on one side and pain on the other side. Available in bottles of 100 tablets.
80 mg tablets: Round, white to off white, biconvex tablets, debossed MN above the break line, 80 below the break line on one side and pain on the other side. Available in bottles of 100 tablets.
Storage:
Store tightly closed, at 15°C – 30°C. Keep out of reach and sight of children.
PHARMACOLOGY
Chemistry:
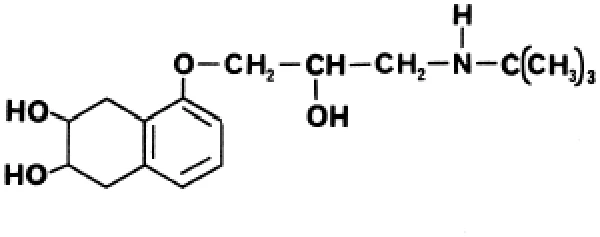
Molecular Formula: C17H27NO4
Molecular Weight: 309.41g/mol
Chemical Name: 2,3-cis-1,2,3,4-tetrahydro-5-(2-hydroxy-3-(tert-butylamino)propoxy)-2,3- naphthalenediol.
Description:
Nadolol is a white to off-white crystalline powder, freely soluble in 95% ethanol and dilute acids (pH 2.0); slightly soluble in chloroform and insoluble in acetone, benzene, ethyl ether, hexane, propylene glycol and aqueous buffers (pH 7.0-9.0).
Pharmacokinetics:
The principle details of the human pharmacokinetics of nadolol may be found under ACTIONS. Mean minimum serum concentrations at steady state were approximately 28, 70, and 131 ng/mL at doses of 80, 160 and 240 mg daily, respectively.
After intravenous administration 73% of the dose was excreted via the kidneys and about 23% via the gastrointestinal tract, the latter of biliary origin.
In dog studies, the highest concentrations of nadolol were present in the kidneys, lungs and heart.
Effects on the Cardiovascular System:
Animal studies in vitro and in vivo showed nadolol to be an antagonist of the beta-stimulatory effects of catecholamines and to consistently block isoproterenol-induced tachycardia and vasodepression in anesthetized dogs and cats, as well as in unanesthetized monkeys and spontaneously hypertensive rats.
Nadolol possesses no significant intrinsic sympathomimetic or membrane-stabilizing (quinidine-like) activities.
In human studies, nadolol has been shown to inhibit the effects of both isoproterenol- and exercise- induced tachycardia at doses as low as 10 mg. Maximum inhibition was seen at 60-90 minutes and 3-8 hours respectively. Significant inhibition of exercise induced increases in double product (heart rate x blood pressure) persisted for at least 26 hours following single oral doses of 40-160 mg.
The iv administration of 0.3-10 ug/kg of nadolol to normotensive male volunteers produced reductions in peripheral plasma renin activity. A similar effect was also seen in hypertensive patients.
A study of the effects of nadolol on human cardiac electrophysiology and hemodynamics showed that nadolol reduces cardiac output without affecting stroke volume.
Studies involving guinea pig atria, papillary muscle of cats, anesthetized. dogs, and unanesthetized atherosclerotic rabbits indicated that nadolol produces little direct myocardial depression in doses much greater than those required to produce complete beta-blockade. However, in other studies involving anesthetized dogs and cats, intravenous infusions of 0.05-1 mg/kg (dogs) and 0.1 to 10 mg/kg (cats) produced decreases in heart rate from 15 to 30% and 23 to 45% respectively.
In studies to determine the effect of intravenous nadolol on excitability, refractoriness, and conduction velocity of both atrial and ventricular tissue in anesthetized dogs, nadolol produced prolongation of ventricular refractoriness and depression of conduction through the A-V node.
In anesthetized dogs, intravenous doses of 0.03-1.0 mg/kg nadolol prevented ECG changes caused by coronary artery occlusion. Exacerbation of these changes by isoproterenol were similarly prevented.
Results from human studies have shown that nadolol possesses some anti-arrhythmic activity.
In a limited trial involving 11 hypertensive patients uncontrolled by diuretic alone, addition of nadolol to the regimen caused a significant increase (9.5%) in mean PAH clearance (effective renal plasma flow) and a 21% decrease in mean renovascular resistance after 16 weeks of combination therapy.
Significant reduction in blood pressure and heart rate occurred. No significant changes were observed in plasma volume, serum creatinine or creatinine clearance.
Similar findings were reported following intravenous doses of nadolol to both hypertensive and normal subjects fed a low sodium diet.
Effects of Respiratory Function:
Studies of the effects of intravenous doses of nadolol on bronchial-airway resistance and on histamine- induced bronchial constriction in anesthetized cats indicated that nadolol increased bronchial-airway resistance. Histamine-induced increases of bronchial-airway resistance were dose dependent and potentiated slightly by nadolol.
In normal male volunteers, both forced vital capacity (FVC) and forced expiratory volume in one second (FEV1.0) decreased after ingestion of 80 mg of nadolol and to a lesser extent after a 120 mg dose.
Other Effects:
A 60 mg daily dose of nadolol for 7 days produced a slightly faster initial rate of disappearance of glucose from the serum following glucose loading in six patients with moderate hypertension or cardiac arrhythmia. Mean insulin responses at 1 and 2 hours after ingestion of the glucose load were decreased approximately 30-35% by nadolol. Nadolol had no significant effect on fasting serum glucose or insulin levels.
TOXICOLOGY
Acute Toxicity:
Animal
Species Sex Oral LD50 (mg/kg)
Albino
Mice* F 3213
M 3774
M/F 3530
Albino Rats** M/ F >5000
*6 groups, each with 5 animals/sex were treated with nadolol at logarithmically spaced doses.
**Single group of 5 animals/sex were treated with the test article at a maximum single dose of 5000 mg/kg.
Mortality generally occurred over a 4-hour period post dosing in mice and one male rat died during the first four-hour period post dosing.
Toxicity was generally characterized by weakness, slight tremors, labored breathing, piloerection, and reduced motor activity in mice. In rats, toxicity was characterized by ptosis, hunched back, piloerection, ataxia, ocular discharge, and reduced motor activity.
Necropsy of animals succumbing during the study generally demonstrated reddening of the lungs and stomach mucosa. Animals sacrificed after completion of the study generally demonstrated no meaningful tissue abnormality.
Acute Oral Interaction Study:
Nadolol was administered orally to mice in combination with: hydralazine hydrochloride, hydrochlorothiazide, digoxin, furosemide, norethindrone/mestranol, quinidine sulfate, nitroglycerin, lithium carbonate or methyldopa.
Under the conditions of the study, there was no evidence of toxicity potentiation of nadolol with any of the nine marketed compounds. Signs of toxicity observed with nadolol alone or in combination with quinidine sulfate, hydralazine hydrochloride, furosemide, methyldopa, or lithium carbonate were ataxia and convulsion.
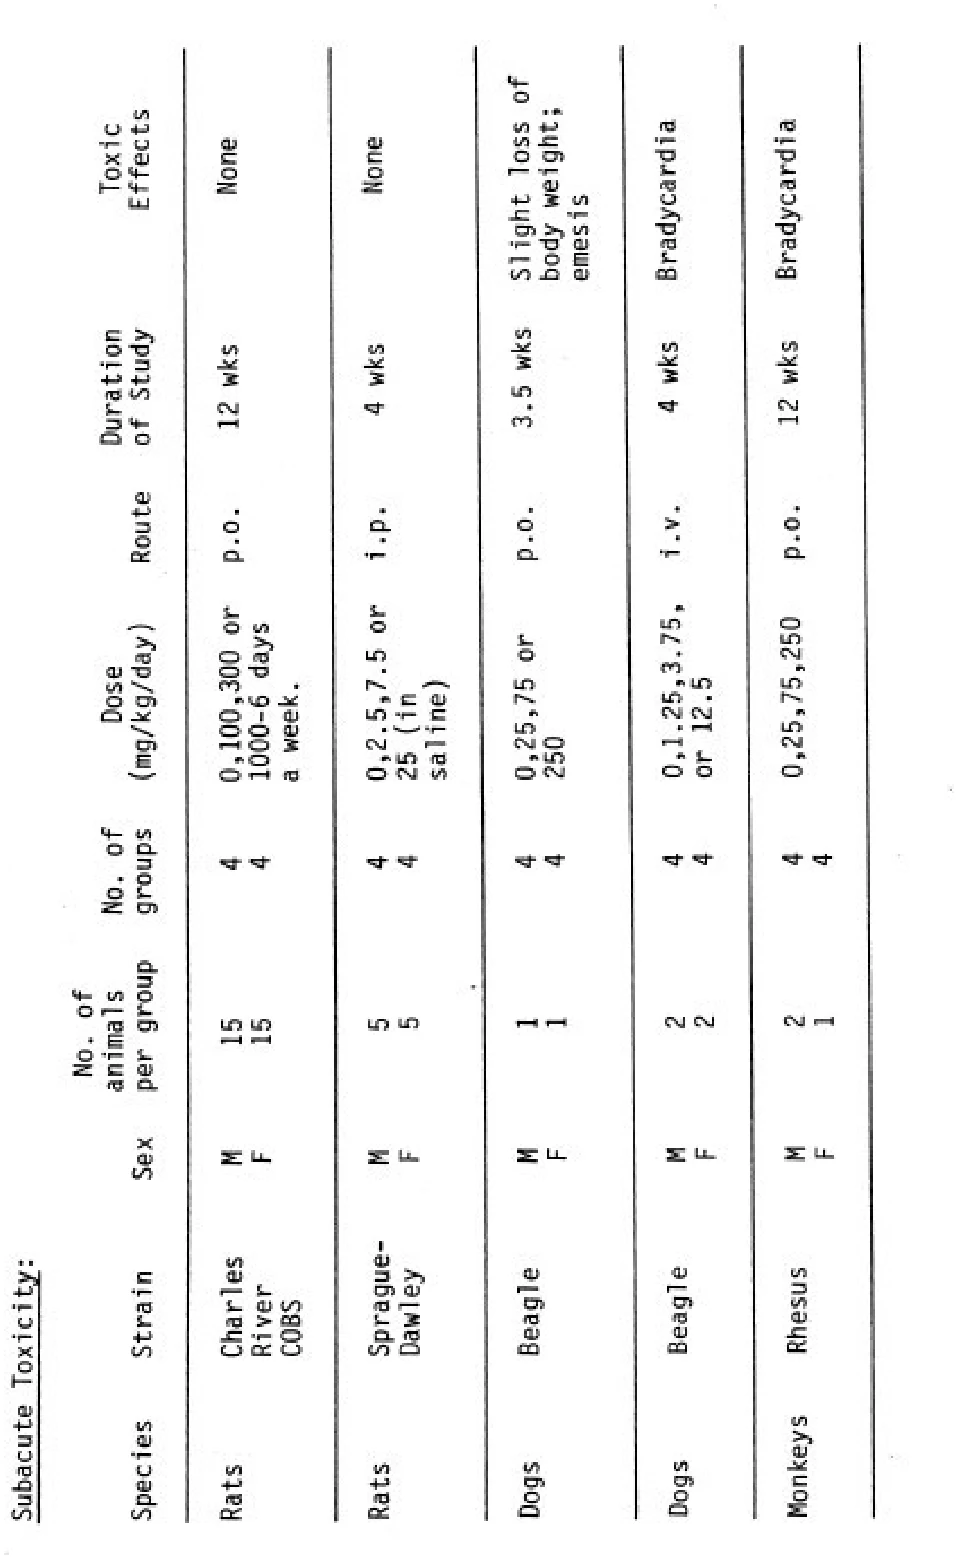
Carcinogenicity Studies:
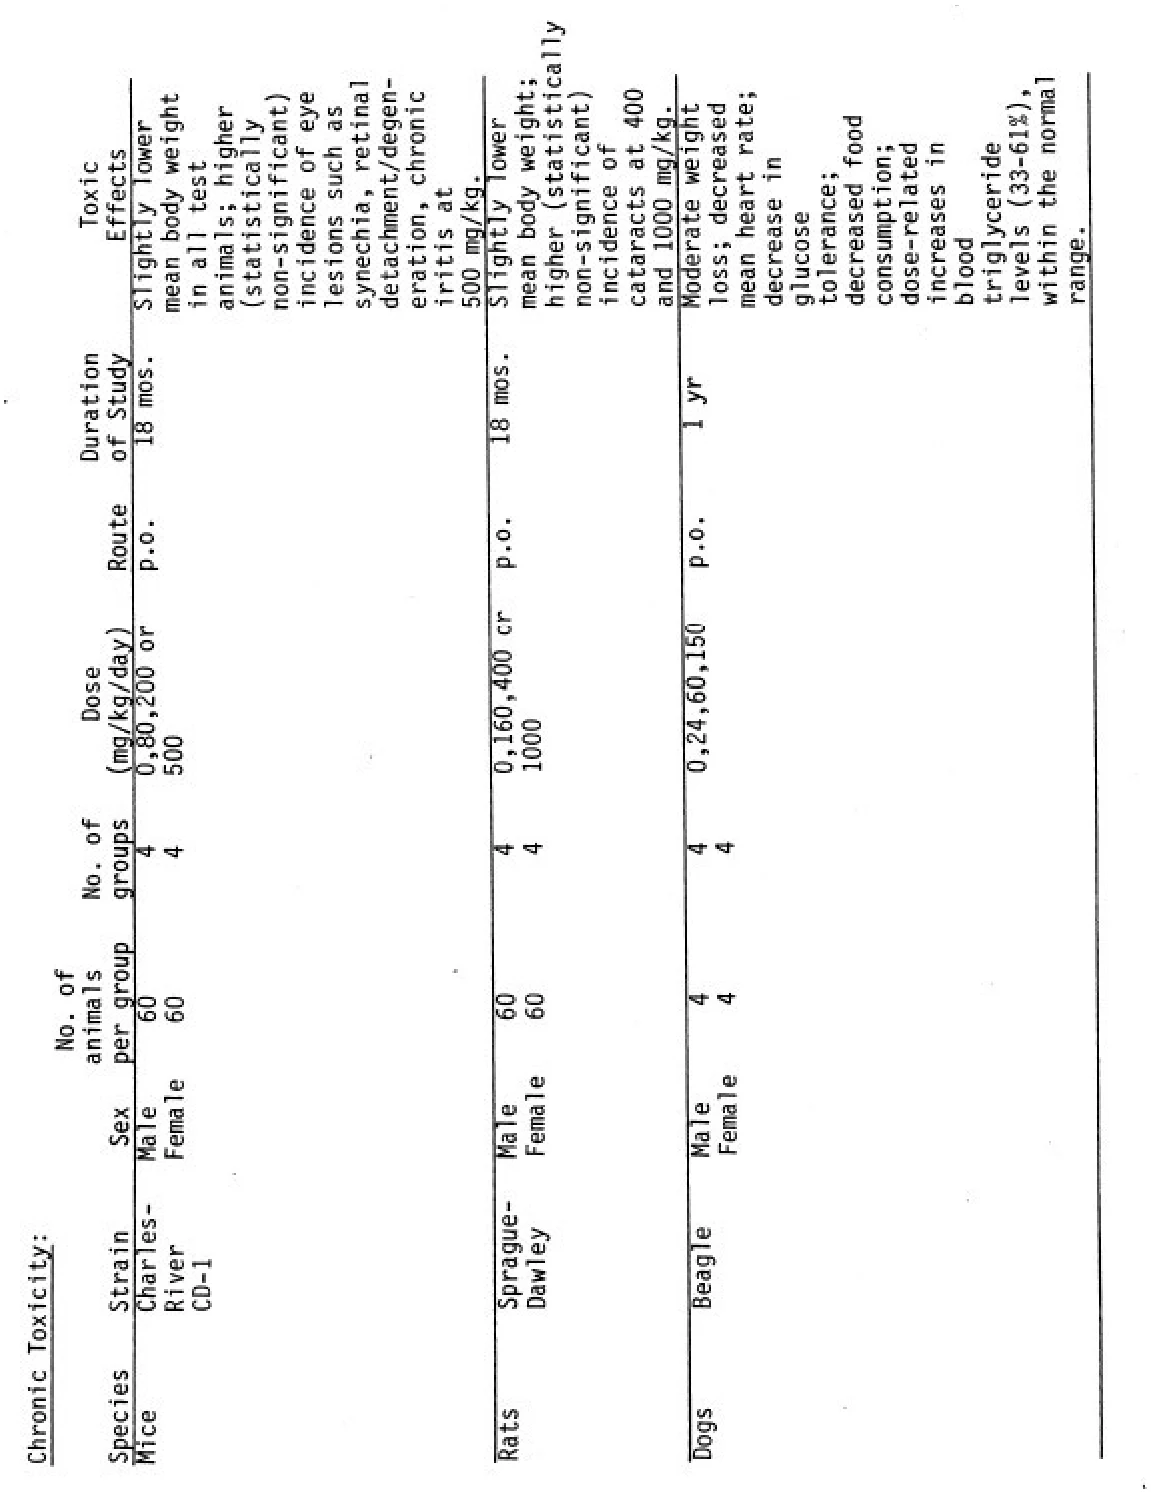
Nadolol was administered to 3 groups of 60 male and 60 female Charles River CD Sprague-Dawley rats at dietary levels of 160, 400 and 1000 mg/kg/day, for 18 months. A similar study was conducted in 3 groups of 60 male and 60 female Charles River CD-1 mice. Doses of 80, 200 or 500 mg/kg/day were given in the diet for 18 months.
Under the conditions of testing, nadolol did not influence the development of tumors.
Teratology Studies:
Rats: Doses of 100 or 300 mg/kg/day were administered orally to male rats for 10 weeks, and to female rats for
2 weeks before mating. Half of the females were dosed until day 13 or 14 of gestation; the remaining females were dosed through gestation and 21 days of lactation. Nadolol had no effect on gestation or on viability of the newborn at birth and at 4 days.
Rats, Hamsters: When administered orally to pregnant rats and hamsters, doses of 100 or 300 mg/kg did not affect fetal development or induce teratogenic changes in the offspring.
Rabbits: When daily doses of 100 or 300 mg/kg were administered orally to Small Russian rabbits from day 6 through day 18 of gestation, nadolol was found to be embryo and fetotoxic, although no teratogenic changes were seen in any of the viable offspring.
Similar effects were noted when pregnant New Zealand and White rabbits were administered daily doses of 100 mg/kg on days 7 through 18 of gestation. These effects were not, however, seen in Small Russian rabbits at dose levels of 25 or 50 mg/kg.
Rats: Total daily doses of 300, 900 or 1800 mg/kg of nadolol were given to rats from day 15 of gestation through to day 21 of lactation. At these dose levels, nadolol did not have any significant adverse effects on pregnant rats or their offspring.
BIBLIOGRAPHY
- 1. Dreyfuss J, Brannick LJ, Vukovich RA, Shaw JM, Willard DA: Metabolic studies in patients with nadolol: oral and intravenous administration. J. Clin. Pharmacol. 1977; 17: 300-307.
- 2. Evans DB, Peschka MT, Lee RJ, Laffan RJ: Antiarrhythmic action of nadolol, a beta-adrenergic receptor blocking agent. Eur J Pharmacol 1976; 35: 17-27.
- 3. Gibson JK, Gelband H, Bassett AL: Possible basis of antiarrhythmic action of a new beta- adrenergic blocking compound (nadolol). Am J Cardiol 1976; 37: 138.
- 4. Gi bson J K , Gel band H , Basset t A L: Ef f ect s of SQ 11725 on t he electrophysiology of isolated mammalian cardiac tissue. Pharmacologist 1974; 16: 201.
- 5. Griffith DL: Effects of diuretics on nadolol bioavailability. Clin Res 1977; 25: 549A.
- 6. Lee G, De Maria AN, Miller RR, Joye JA, Baker L, Jameson L, Low R, Mason DT: Comparative effects of nadolol and propranolol on cardiac and peripheral circulatory function in patients with coronary artery disease. Clin Res 1978; 26: 100A.
- 7. Lee RJ, Evans DB, Baky SH, Laffan RJ: Pharmacology of nadolol (SQ 11, 725), a beta- adrenergic antagonist lacking direct myocardial depression. Eur J Pharmacol 1975; 33: 371-382.
- 8. LeWinter MM, Curtis G, Shabetai R, Verba J, Bloomquist J, Engler R: Comparison of the effects of a new beta-adrenergic blocking agent (nadolol) and propranolol on left ventricular performance in patients with prior myocardial infarction. Clin Res 1978: 26: 101A.
- 9.
Morales-Aquilera A, Valle JR: Neuromuscular transmission blockade produced by propranolol
and 2,3-cis-1,2,3,4-tetrahydro-5-(2-hydroxy-3-(tert-butylamino)propoxy)-2-3-
naphthalenediol (SQ 11, 725). Fed Proc 1974; 33: 579.
- 10. McKinstry DN, Vukovich RA, Willard DA: Effects of beta-adrenergic blockade with nadolol and propranolol on glucose and lipid metabolism in man. Clin Res 1977; 25: 548A.
- 11. Miller LA, Crawford MH, O'Rourke RA: Nadolol compared to propranolol for treating chronic stable angina pectoris. Chest 1984; 86: 189-193.
- 12. Prager G: Angina Pectoris: effective therapy once daily. J Int Med Res 1979; 7: 39-44.
- 13. Peschka M, Evans DB, Laffan RJ: Antiarrhythmic activity of SQ 11725, a potent non- depressant beta-adrenergic blocking agent. Fed Proc 1973; 32: 780.
- 14. Shaw JM, Dreyfuss J: Placental transfer in rats of the beta-adrenergic blocking agent, nadolol, and its excretion in milk. Fed Proc 1976; 35: 365.
- 15.
Turner GG, Nelson RR, Nordstrom LA, Diefenthal HC, Gobel FL: Comparative effect of nadolol and
- propranolol on exercise tolerance in patients with angina pectoris. Br Heart J 1978; 40: 1361-1370.
- 16. Vukovich R, Dreyfuss J, Brannick LJ, Herrera J, Willard D: Pharmacologic and metabolic studies with a new beta-adrenergic blocking agent, nadolol. Clin Res 1976; 24: 513A.
- 17. Vukovich R, Sasahara A, Sanchez-Zambrano S, Belko J: Beta blockade with nadolol in patient with congestive heart failure. Lancet 1978; 1: 162-163.
- 18. Vukovich RA, Sasahara A, Zombrano P, Belko J, Godin P, Brannick L: Anti-arrhythmic effects of a new beta-adrenergic blocking agent, nadolol. Clin Pharmacol Ther 1976; 19: 118.
- 19. Wong KK, Dreyfuss J, Shaw JM, Ross JJ Jr., Schreiber EC: A beta-blocking agent (SQ 11725) that is not metabolized extensively by dogs and monkeys. Pharmacologist 1973; 15: 245.
- 20. PrNadolol (Nadolol) Tablets 40 mg, 80 mg, and 160 mg, Control no # 190672, Product Monograph, AA Pharma Inc. Canada, Inc. (June 24, 2016).