


Product Monograph - Otulfi
Recent Major Label Changes
Not Applicable
Table Of Contents
Certain sections or subsections that are not applicable at the time of the preparation of the most recent authorized product monograph are not listed.
Recent Major Label Changes .................................................................................................... 2
Table Of Contents .................................................................................................................... 2
Part 1: Health Professional Information ................................................................................... 4
- 1.
Indications ................................................................................................................... 4
1.1 Pediatrics ................................................................................................................. 5
1.2 Geriatrics ................................................................................................................. 5
- 2. Contraindications ......................................................................................................... 5
- 4.
Dosage And Administration ......................................................................................... 5
4.1 Dosing Considerations ............................................................................................. 5
4.2 Recommended Dose and Dosage Adjustment ......................................................... 5
4.4 Administration ......................................................................................................... 8
4.5 Missed Dose ............................................................................................................. 9
- 5. Overdose...................................................................................................................... 9
- 6. Dosage Forms, Strengths, Composition and Packaging ............................................... 10
- 7.
Warnings and Precautions .......................................................................................... 11
Carcinogenesis and Genotoxicity .................................................................................... 12
7.1 Special Populations ................................................................................................ 14
7.1.2 Breastfeeding ......................................................................................................... 14
7.1.3 Pediatrics ................................................................................................................ 15
7.1.4 Geriatrics ................................................................................................................ 15
- 8.
Adverse Reactions ...................................................................................................... 15
8.1 Adverse Reaction Overview ................................................................................... 15
8.2 Clinical Trial Adverse Reactions.............................................................................. 15
8.2.1 Clinical Trial Adverse Reactions – Pediatrics ..................................................... 22
8.3 Less Common Clinical Trial Adverse Reactions....................................................... 22
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data .................................................................................................. 23
8.5 Post-Market Adverse Reactions ............................................................................. 23
- 9.
Drug Interactions ....................................................................................................... 23
9.2 Drug Interactions Overview ................................................................................... 23
9.3 Drug-Behaviour Interactions .................................................................................. 24
9.4 Drug-Drug Interactions .......................................................................................... 24
9.5 Drug-Food Interactions .......................................................................................... 24
9.6 Drug-Herb Interactions .......................................................................................... 24
9.7 Drug-Laboratory Test Interactions ......................................................................... 24
- 10.
Clinical Pharmacology ................................................................................................ 25
10.1 Mechanism of Action ............................................................................................. 25
10.2 Pharmacodynamics ................................................................................................ 25
10.3 Pharmacokinetics ................................................................................................... 26
10.4 Immunogenicity ..................................................................................................... 29
- 11. Storage, Stability And Disposal ................................................................................... 29
- 12. Special Handling Instructions ..................................................................................... 29
Part 2: Scientific Information ................................................................................................. 30
- 13. Pharmaceutical Information ....................................................................................... 30
- 14.
Clinical Trials .............................................................................................................. 30
14.1 Clinical Trials by Indication ..................................................................................... 30
- 15. Microbiology .............................................................................................................. 60
- 16. Non-Clinical Toxicology .............................................................................................. 60
- 17. Supporting Product Monographs ............................................................................... 63
Patient Medication Information ............................................................................................ 64
Patient Medication Information ............................................................................................ 79
Part 1: Health Professional Information
Ustekinumab administered subcutaneously will be referred to throughout the Product Monograph as OTULFI (ustekinumab injection).
Ustekinumab administered through intravenous infusion will be referred to throughout the Product Monograph as OTULFI I.V. (ustekinumab for injection).
OTULFI (ustekinumab injection) and OTULFI I.V. (ustekinumab for injection) is a biosimilar biologic drug (biosimilar) to PrSTELARA® (ustekinumab injection) and Pr STELARA® I.V (ustekinumab injection). A biosimilar is a biologic drug that was granted authorization based on a demonstration of similarity to a version previously authorized in Canada, known as the reference biologic drug.
1. Indications
Indications have been granted on the basis of similarity between OTULFI/OTULFI I.V. and the reference biologic drug Stelara/Stelara I.V.
OTULFI/OTULFI I.V. (ustekinumab) should be used only by physicians who have sufficient knowledge of plaque psoriasis, psoriatic arthritis, Crohn’s disease, and/or ulcerative colitis and who have fully familiarized themselves with the efficacy/safety profile of the drug.
Plaque Psoriasis
OTULFI (ustekinumab) is indicated for:
- the treatment of chronic moderate to severe plaque psoriasis in adult patients who are candidates for phototherapy or systemic therapy
- the treatment of chronic moderate to severe plaque psoriasis in pediatric patients (6-17 years of age) who are inadequately controlled by, or are intolerant to, other systemic therapies or phototherapies (see 1.1 Pediatrics)
Psoriatic Arthritis
OTULFI (ustekinumab) is indicated for the treatment of adult patients with active psoriatic arthritis. OTULFI can be used alone or in combination with methotrexate (MTX).
Crohn’s Disease
OTULFI/OTULFI I.V. (ustekinumab) is indicated for the treatment of adult patients with moderately to severely active Crohn’s disease, who have had an inadequate response, loss of response to, or were intolerant to either immunomodulators or one or more tumour necrosis factor-alpha (TNFα) antagonists, or have had an inadequate response, intolerance or demonstrated dependence on corticosteroids.
Ulcerative Colitis
OTULFI/OTULFI I.V. (ustekinumab) is indicated for the treatment of adult patients with moderately to severely active ulcerative colitis who have had an inadequate response with, lost response to, or were intolerant to either conventional therapy or a biologic or have medical contraindications to such therapies.
1.1 Pediatrics
Pediatrics (6-17 years of age): OTULFI (ustekinumab) is indicated for the treatment of chronic moderate to severe plaque psoriasis in pediatric patients (children and adolescents) from 6 to 17 years of age, who are inadequately controlled by, or are intolerant to, other systemic therapies or phototherapies.
The safety and efficacy of OTULFI has not been established in pediatric patients with plaque psoriasis <6 years of age. Pediatric studies of OTULFI have not been conducted. The safety and efficacy of OTULFI in pediatric patients with psoriatic arthritis, Crohn’s disease, and ulcerative colitis have not been established (see 7.1.3 Pediatrics and 14.4 Clinical Trials - Reference Biologic Drug, Pediatric Plaque Psoriasis (6 to 17 years of age)).
1.2 Geriatrics
Geriatrics (>65 years of age): No major age-related differences in clearance or volume of distribution were observed in clinical studies. Although no overall differences in safety and efficacy were observed between older and younger patients in clinical studies in approved indications, the number of patients aged 65 and over is not sufficient to determine whether they respond differently from younger patients (see 7.1.4 Geriatrics).
2. Contraindications
OTULFI/OTULFI I.V. is contraindicated in patients who are hypersensitive to ustekinumab or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container (see 7 WARNINGS AND PRECAUTIONS, Sensitivity/Resistance, Hypersensitivity Reactions and 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING).
OTULFI/OTULFI I.V. is contraindicated in patients with severe infections such as sepsis, tuberculosis and opportunistic infections (see 7 WARNINGS AND PRECAUTIONS, General, Infections).
4. Dosage And Administration
4.1 Dosing Considerations
OTULFI/OTULFI I.V. (ustekinumab) is intended for use under the guidance and supervision of a physician.
The KabiCare Clinic Network has been established to facilitate the administration of OTULFI. This network consists of clinics located across Canada that are staffed by qualified healthcare professionals specially trained in the administration of OTULFI. Contact your doctor if you have any questions. Information about the KabiCare Infusion Network can be obtained by contacting KabiCare at: 1-888-304-2034 or info@kabicare.ca.
4.2 Recommended Dose and Dosage Adjustment
Plaque Psoriasis
For the treatment of plaque psoriasis, OTULFI is administered by subcutaneous injection.
Adults
The recommended dose of OTULFI is 45 mg administered at Weeks 0 and 4, then every 12 weeks thereafter. Alternatively, 90 mg may be used in patients with a body weight greater than 100 kg. In patients weighing >100 kg, both 45 mg and 90 mg were shown to be efficacious. However, 90 mg was efficacious in a higher percentage of these patients than the 45 mg dose.
For patients who inadequately respond to dosing every 12 weeks, consideration may be given to treating as often as every 8 weeks.
Consideration should be given to discontinuing treatment in patients who have shown no response up to 12 weeks of treatment.
Re-treatment with a dosing regimen of Weeks 0 and 4 followed by 12-week dosing after interruption of therapy has been shown to be safe and effective (see 14.4 Reference Biologic Drug, Plaque Psoriasis – Adults, Efficacy of retreatment).
Pediatrics (6 to 17 years of age)
The recommended dose of OTULFI based on body weight is shown below (Table 1). OTULFI should be administered at Weeks 0 and 4, then every 12 weeks thereafter.
Consideration should be given to discontinuing treatment in patients who have shown no response up to 12 weeks of treatment.
Table 1 Recommended dose of OTULFI for pediatric psoriasis
| Weight | Recommended Dose | Dosage Form |
|---|---|---|
| <60 Kga | 0.75 mg/Kg* | vial |
| ≥60 to ≤100 kg | 45 mg | prefilled syringe, vial |
| >100 Kgb | 90 mg | prefilled syringe |
* To calculate the volume of injection (mL) for patients <60 kg, use the following formula: body weight (kg) x 0.0083 (mL/kg). The calculated volume should be rounded to the nearest 0.01 mL and administered using a 1 mL graduated syringe. A 45 mg vial is available for pediatric patients who need to receive less than the full 45 mg dose. a For patients with body weight <60 kg, use the vial presentation only b There were only 3 patients aged 12 to 17 years, with a body weight >100 kg in the study | ||
Table 2 Injection volumes of OTULFI for pediatric psoriasis patients <60 Kg
| Body weight at time of dosing (kg) | Dose (mg) | Volume of injection (mL) |
|---|---|---|
| Body weight at time of dosing (kg) | Dose (mg) | Volume of injection (mL) |
| 15 | 11.3 | 0.12 |
| 16 | 12.0 | 0.13 |
| 17 | 12.8 | 0.14 |
| 18 | 13.5 | 0.15 |
| 19 | 14.3 | 0.16 |
| 20 | 15.0 | 0.17 |
| 21 | 15.8 | 0.17 |
| 22 | 16.5 | 0.18 |
| 23 | 17.3 | 0.19 |
| 24 | 18.0 | 0.20 |
| 25 | 18.8 | 0.21 |
| 26 | 19.5 | 0.22 |
| 27 | 20.3 | 0.22 |
| 28 | 21.0 | 0.23 |
| 29 | 21.8 | 0.24 |
| 30 | 22.5 | 0.25 |
| 31 | 23.3 | 0.26 |
| 32 | 24.0 | 0.27 |
| 33 | 24.8 | 0.27 |
| 34 | 25.5 | 0.28 |
| 35 | 26.3 | 0.29 |
| 36 | 27.0 | 0.30 |
| 37 | 27.8 | 0.31 |
| 38 | 28.5 | 0.32 |
| 39 | 29.3 | 0.32 |
| 40 | 30.0 | 0.33 |
| 41 | 30.8 | 0.34 |
| 42 | 31.5 | 0.35 |
| 43 | 32.3 | 0.36 |
| 44 | 33.0 | 0.37 |
| 45 | 33.8 | 0.37 |
| 46 | 34.5 | 0.38 |
| 47 | 35.3 | 0.39 |
| 48 | 36.0 | 0.40 |
| 49 | 36.8 | 0.41 |
| 50 | 37.5 | 0.42 |
| 51 | 38.3 | 0.42 |
| 52 | 39.0 | 0.43 |
| 53 | 39.8 | 0.44 |
| 54 | 40.5 | 0.45 |
| 55 | 41.3 | 0.46 |
| 56 | 42.0 | 0.46 |
| 57 | 42.8 | 0.47 |
| 58 | 43.5 | 0.48 |
| 59 | 44.3 | 0.49 |
Psoriatic Arthritis – Adults
For the treatment of psoriatic arthritis, OTULFI is administered by subcutaneous injection. The recommended dose of OTULFI is 45 mg administered at Weeks 0 and 4, then every 12 weeks thereafter. Alternatively, 90 mg may be used in patients with a body weight greater than 100 kg.
Crohn’s Disease and Ulcerative Colitis – Adults
Intravenous induction dosing
In patients with Crohn’s disease and ulcerative colitis, the recommended induction treatment regimen is a single intravenous (IV) tiered dose of OTULFI I.V. based on body weight (Table 3) (see 4.4 Administration, Intravenous Infusion (Crohn’s Disease and Ulcerative Colitis)).
Table 3 Initial dosing of OTULFI I.V.
| Body Weight of Patient at the time of dosing | Dose a | Number of 130 mg OTULFI I.V. vials |
|---|---|---|
| ≤55 kg | 260 mg | 2 |
| >55 kg to ≤85 kg | 390 mg | 3 |
| >85 kg | 520 mg | 4 |
a Recommended dose (approximately 6 mg/kg)
Subcutaneous maintenance dosing
The recommended maintenance dose of OTULFI is 90 mg administered subcutaneously. The first subcutaneous dose should be given at week 8 following the intravenous induction dose. Subsequent doses should be given every 8 weeks thereafter.
In some patients, (e.g., those with low inflammatory burden) a single dose OTULFI I.V. followed by 90 mg subcutaneous dosing 8 weeks later, then every 12 weeks thereafter may be considered at the discretion of the treating physician. Patients should have their dose frequency adjusted to every 8 weeks if inadequate response occurs. Consideration should be given to discontinuing treatment in patients who show no evidence of therapeutic benefit 16 weeks after the IV induction dose (see 14 CLINICAL TRIALS).
Immunomodulators and/or corticosteroids may be continued during treatment with OTULFI/OTULFI I.V. In patients who have responded to treatment with OTULFI/OTULFI I.V. corticosteroids may be reduced or discontinued in accordance with standard of care.
If therapy is interrupted, resumption of treatment with subcutaneous dosing every 8 weeks is safe and effective.
Special Populations
Renal Insufficiency
Specific studies have not been conducted in patients with renal insufficiency.
Hepatic Insufficiency
Specific studies have not been conducted in patients with hepatic insufficiency.
4.4 Administration
Subcutaneous Administration
OTULFI is supplied as 45 mg and 90 mg pre-filled syringes and 45 mg single-use vials. In pediatric patients, it is recommended that OTULFI be administered by a health care provider. A patient may self-inject with OTULFI if a physician determines that it is appropriate after proper training in subcutaneous injection technique and disposal (see PATIENT MEDICATION INFORMATION, How to take OTULFI).
Prior to subcutaneous administration, visually inspect the solution for particulate matter and discolouration. The product is clear to slightly opalescent, colourless to light brownish-yellow and may contain a few small translucent or white particles of protein. This appearance is not unusual for proteinaceous solutions. The product should not be used if solution is discoloured or cloudy, or if other particulate matter is present. OTULFI does not contain preservatives; therefore, any unused product remaining in the vial or syringe should not be used.
Patients should be instructed to inject the prescribed amount of OTULFI according to the directions provided in the PATIENT MEDICATION INFORMATION Section.
Intravenous Infusion (Crohn’s Disease and Ulcerative Colitis)
OTULFI I.V. is supplied in a 130 mg vial. The solution is clear, colourless to light brownish-yellow with a pH of approximately 6.0. Intravenous infusion of OTULFI I.V. should be administered by qualified health care professionals.
Instructions for dilution of OTULFI I.V. (130 mg vial) Crohn’s disease and ulcerative colitis
OTULFI I.V. must be diluted and prepared for IV infusion by a healthcare professional using aseptic technique.
- 1. Calculate the dose and the number of OTULFI I.V. vials needed based on patient’s body weight (see Table 3). Each 26 ml vial of OTULFI I.V. contains 130 mg of ustekinumab.
- 2. Withdraw, and then discard a volume of the 0.9% w/v sodium chloride solution from the 250 ml infusion bag equal to the volume of OTULFI I.V. to be added. (26 mL for each vial of OTULFI I.V. needed, for 2 vials - discard 52 mL, for 3 vials - discard 78 mL, for 4 vials - discard 104 mL). Alternatively, a 250 mL infusion bag containing 0.45% w/v sodium chloride solution may be used.
- 3. Withdraw 26 mL of OTULFI I.V. from each vial needed and add it to the 250 ml infusion bag. The final volume in the infusion bag should be 250 ml. Gently mix.
- 4. Visually inspect the diluted solution before administration. Do not use if visibly opaque particles, discolouration or foreign particles are observed.
- 5. Infuse the diluted solution over a period of at least one hour. Once diluted, the infusion should be completed within eight hours of the dilution in the infusion bag.
- 6. Use only an infusion set with an in-line, sterile, non-pyrogenic, low protein-binding filter (pore size 0.2 micrometer).
- 7. Do not infuse OTULFI I.V. concomitantly in the same intravenous line with other agents.
- 8. OTULFI I.V. does not contain preservatives. Each vial is for single use only and any unused medicinal product should be disposed of in accordance with local requirements.
If necessary, the diluted infusion solution may be stored at room temperature. The infusion should be completed within 8 hours of the dilution in the infusion bag. Do not freeze. Discard any unused portion of the infusion solution.
4.5 Missed Dose
Patients who miss their scheduled dose of OTULFI/OTULFI I.V., should be advised to contact their healthcare provider for guidance.
5. Overdose
Single doses up to 6 mg/kg intravenously have been administered in clinical studies without dose limiting toxicity. In case of overdosage, it is recommended that the patient be monitored for any signs or symptoms of adverse reactions or effects and appropriate symptomatic treatment be instituted immediately.
For the most recent information in the management of a suspected drug overdose, contact your regional poison control centre or Health Canada’s toll-free number, 1-844 POISON-X (1-844-764-7669).
6. Dosage Forms, Strengths, Composition and Packaging
To help ensure the traceability of biologic products, including biosimilars, health professionals should recognise the importance of recording both the brand name and the non-proprietary (active ingredient) name as well as other product-specific identifiers such as the Drug Identification Number (DIN) and the batch/lot number of the product supplied.
Table 4 Dosage Forms, Strengths and Composition
OTULFI/OTULFI I.V. (ustekinumab) is supplied in the following presentations:
OTULFI
Pre-filled Syringe:
- 45 mg / 0.5 mL
- 90 mg / mL
Single-use Vial:
- 45 mg / 0.5 mL
OTULFI I.V.
Single use Vial:
- 130 mg / 26 mL
OTULFI: 45 mg Pre-filled Syringe/Vial or 90 mg Pre-filled Syringe
OTULFI is supplied as a single use, sterile solution for subcutaneous injection in a Type 1 glass syringe with a fixed 29G, half-inch needle and rigid needle shield. The syringe is fitted with a needle safety
Route of Administration | Dosage Form / Strength / Composition | Non-medicinal Ingredients |
Subcutaneous Injection | Sterile solution in single-use pre-filled syringe 45 mg / 0.5 mL, 90 mg / mL or 45 mg / 0.5 mL vial | Hydrochloric acid, L-histidine, polysorbate 80, sucrose, and water for injection. |
Intravenous Infusion | Sterile solution in single-use vial 130 mg / 26 mL (5 mg / mL) | EDTA disodium salt dihydrate, L-histidine and L-histidine hydrochloride monohydrate, L-methionine, polysorbate 80, sucrose and water for injection. |
device. OTULFI is also supplied as a sterile solution for subcutaneous injection in a single- use (Type 1) glass vial.
The solution is clear to slightly opalescent, colourless to light brownish-yellow with a pH of approximately
6.0. Each mL of OTULFI contains 90 mg of ustekinumab. OTULFI does not contain preservatives.
There are two strengths of OTULFI available: 45 mg of ustekinumab in 0.5 mL and 90 mg of ustekinumab in 1 mL.
OTULFI is available in single unit packaging presentations.
OTULFI I.V.: 130 mg Vial
OTULFI I.V., 130 mg vial, is supplied as a sterile solution for intravenous infusion in a single use (Type 1) glass vial. The solution is clear to slightly opalescent, colourless to light brownish-yellow with a pH of approximately 6.0. Each mL of OTULFI I.V. contains 5 mg of ustekinumab. OTULFI I.V. does not contain preservatives. OTULFI I.V. is available in one strength, 130 mg in 26 mL, and packaged as 1 single use vial.
7. Warnings and Precautions
General
Infections
Ustekinumab is a selective immunomodulator and may have the potential to increase the risk of infections and reactivate latent infections.
Ustekinumab should not be given to patients with any clinically important active infection. If a patient develops a serious infection they should be closely monitored and ustekinumab should not be administered until the infection resolves or is adequately treated. Caution should be exercised when considering the use of ustekinumab in patients with a chronic infection or a history of recurrent infection. Patients should be instructed to seek medical advice if signs or symptoms suggestive of an infection occur.
Prior to initiating treatment with ustekinumab, patients should be evaluated for tuberculosis infection. Ustekinumab should not be given to patients with active tuberculosis. Treatment of latent tuberculosis infection should be initiated prior to administering ustekinumab. Anti-tuberculosis therapy should also be considered prior to initiation of ustekinumab in patients with a past history of latent or active tuberculosis in whom an adequate course of treatment cannot be confirmed. In clinical studies, patients with latent tuberculosis who were concurrently treated with isoniazid did not develop tuberculosis. Patients receiving ustekinumab should be monitored closely for signs and symptoms of active tuberculosis during and after treatment.
In clinical studies, serious bacterial, fungal, and viral infections were observed in subjects receiving ustekinumab. Serious infections requiring hospitalization occurred in the psoriasis, psoriatic arthritis, Crohn’s disease and ulcerative colitis development programs. In the psoriasis and psoriatic arthritis programs serious infections included diverticulitis, cellulitis, pneumonia, appendicitis, cholecystitis and sepsis. In the Crohn’s disease program, serious infections included anal abscess, gastroenteritis, pneumonia and sepsis. Other clinically important infections included listeria meningitis and ophthalmic herpes which were reported in one patient each. In the ulcerative colitis program, serious infections included gastroenteritis and pneumonia (see 8 ADVERSE REACTIONS).
Carcinogenesis and Genotoxicity
Malignancies
Ustekinumab is a selective immunomodulator. Immunomodulating agents have the potential to increase the risk of malignancy. Some patients who received ustekinumab in clinical studies developed malignancies (see 8.2 Clinical Trial Adverse Reactions, Malignancies).
Ustekinumab has not been studied in patients with a history of malignancy. Caution should be exercised when considering the use of ustekinumab in patients with a history of malignancy or when considering continuing treatment in patients who develop a malignancy.
All patients, in particular those greater than 60 years of age, those with a medical history of prolonged immunosuppressant therapy or those with a history of PUVA treatment, should be monitored for the appearance of skin cancer (see 8 ADVERSE REACTIONS).
Hepatic/Biliary/Pancreatic
Specific studies have not been conducted in patients with hepatic insufficiency.
Immune
Immunization
It is recommended that live viral or bacterial vaccines not be given concurrently with ustekinumab. No data are available on the secondary transmission of infection by live vaccines in patients receiving ustekinumab. Caution is advised when administering some live vaccines to household contacts of patients receiving ustekinumab because of the potential risk for shedding from the household contact and transmission to the patient. Patients receiving ustekinumab may receive concurrent inactivated or non-live vaccinations (see 9.4 Drug-Drug Interactions, Live Vaccines).
Prior to initiating therapy with ustekinumab, patients should receive all immunizations appropriate for age as recommended by current immunization guidelines. Long term treatment with ustekinumab does not appear to suppress the immune response to pneumococcal polysaccharide or tetanus vaccines polysaccharide or tetanus vaccines. During the long-term extension of a Phase 3 psoriasis study (PHOENIX 2), patients treated with ustekinumab for at least 3.5 years mounted similar antibody responses to both pneumococcal polysaccharide and tetanus vaccines as a non-systemically treated psoriasis control group. Similar proportions of patients developed protective levels of anti-pneumococcal and anti-tetanus antibodies and antibody titers were similar among ustekinumab-treated and control patients. However, non-live vaccinations received during a course of ustekinumab may not elicit an immune response sufficient to prevent disease.
Infant exposure in utero
For infants exposed in utero to ustekinumab, a six-month waiting period following birth is recommended before the administration of live vaccines. Administration of a live vaccine prior to 6 months of age may be considered if ustekinumab serum levels are undetectable in the infant, or the benefit of the vaccination clearly outweighs the risk of administration of live vaccines to the infant (see 7 WARNINGS AND PRECAUTIONS, Immune, Immunization).
Concomitant immunosuppressive therapy
In the Phase 3 psoriasis studies, the safety and efficacy of ustekinumab in combination with immunosuppressive agents or phototherapy have not been evaluated. In the Phase 3 psoriatic arthritis studies, concomitant methotrexate did not appear to influence the safety of ustekinumab. In Crohn’s disease and ulcerative colitis studies, concomitant use of immunomodulators (6-mercaptopurine (6-MP), azathioprine (AZA), MTX) or corticosteroids did not appear to influence the overall safety of ustekinumab. Caution should be exercised when considering concomitant use of immunosuppressive agents and ustekinumab or when transitioning from other biologic agents (see 9 DRUG-DRUG INTERACTIONS, Immunosuppressants).
Immunotherapy
Ustekinumab has not been evaluated in patients who have undergone allergy immunotherapy. Ustekinumab may affect allergy immunotherapy. Caution should be exercised in patients receiving or who have received allergy immunotherapy particularly for anaphylaxis.
Neurologic
Reversible Posterior Leukoencephalopathy Syndrome
One case of reversible posterior leukoencephalopathy syndrome (RPLS) was observed during the clinical development programs which included 6709 ustekinumab-treated subjects. The subject, who had received 12 doses of ustekinumab over approximately two and a half years, presented with headache, seizures and confusion in the setting of alcohol abuse. No additional ustekinumab injections were administered and the subject fully recovered with appropriate treatment.
RPLS is a neurological disorder, which is not caused by demyelination or a known infectious agent. RPLS can present with headache, seizures, confusion and visual disturbances. Conditions with which it has been associated include preeclampsia, acute hypertension, cytotoxic agents, immunosuppressive therapy and alcohol abuse. Fatal outcomes have been reported.
If RPLS is suspected, administer appropriate treatment and discontinue OTULFI/OTULFI I.V.
Renal
Specific studies have not been conducted in patients with renal insufficiency.
Reproductive Health: Female and Male Potential
Fertility
Women of Childbearing Potential: It is not known whether ustekinumab can affect reproductive potential. Women of childbearing potential initiating treatment with ustekinumab should use effective methods of contraception and should receive preconception counselling before planning a pregnancy in accordance with disease specific clinical guidelines. Ustekinumab remains in the circulation for approximately 15 weeks after treatment. In clinical trials, women of childbearing potential were required to use effective methods of contraception during treatment and for at least 15 weeks after treatment (see 7.1.1 Pregnant Women).
Sensitivity/Resistance
Hypersensitivity Reactions
Systemic
In post-marketing experience, serious allergic reactions, including anaphylaxis and angioedema, have been reported. If an anaphylactic or other serious allergic reaction occurs, institute appropriate therapy and discontinue administration of OTULFI/OTULFI I.V. (see 8 ADVERSE REACTIONS).
Respiratory
Cases of allergic alveolitis and eosinophilic pneumonia have been reported during post-approval use of ustekinumab. Clinical presentations included cough, dyspnoea, and interstitial infiltrates following one to three doses. Serious outcomes have included respiratory failure and prolonged hospitalisation. Improvement has been reported after discontinuation of ustekinumab and also, in some cases, administration of corticosteroids. If infection has been excluded and diagnosis is confirmed, discontinue ustekinumab and institute appropriate treatment.
7.1 Special Populations
7.1.1 Pregnancy
There is no evidence from animal studies of teratogenicity, birth defects or developmental delays at dose levels up to approximately 45-fold higher than the highest equivalent dose intended to be administered to patients with psoriasis and psoriatic arthritis (see 16 NON-CLINICAL TOXICOLOGY , Reproductive and Developmental Toxicology). However, animal reproductive and developmental studies are not always predictive of human response.
While it is known that human IgG antibodies, like ustekinumab, cross the placenta, no adequate and well-controlled studies have been conducted with ustekinumab in human pregnancy. An analysis of a global pharmacovigilance database, which included spontaneous and solicited reports, and both prospective and retrospective reporting, found an overall incidence of congenital anomalies of 4.6% (66/1,450, 95% CI 3.5%, 5.8%) among live births in pregnancies exposed to ustekinumab with known outcomes and an incidence of major congenital anomalies of 2.6% (37/1,450, 95% CI 1.8%, 3.5%). Limitations such as the lack of comparators and the variability of outcome ascertainment limit the ability to draw definitive conclusions about drug-related effects.
The decision to continue OTULFI/OTULFI I.V. during pregnancy should be carefully evaluated taking into consideration clinical practice guidelines to ensure the safety of the pregnant woman and the fetus. OTULFI/OTULFI I.V. should be given to a pregnant woman only if the benefit clearly outweighs the risk.
7.1.2 Breastfeeding
Limited data from published literature suggests that ustekinumab is excreted in human breast milk in small amounts and it is not known if ustekinumab is absorbed systemically after ingestion. Because of the potential for adverse reactions in nursing infants from ustekinumab, a decision should be made whether to discontinue nursing or to discontinue the drug.
7.1.3 Pediatrics
Pediatrics (< 18 years of age): The efficacy of OTULFI (ustekinumab) has been studied in 110 plaque psoriasis patients 12-17 years of age where the majority of patients (77/110) were 15-17 years of age. The efficacy of OTULFI was studied in 44 plaque psoriasis patients 6-11 years of age where half of the patients (22/44) were 6-9 years of age. Studies of OTULFI in pediatric plaque psoriasis patients below 6 years of age have not been conducted (14.4 Clinical Trials-Reference Biologic Drug, Pediatric Plaque Psoriasis (6 to 17 years of age)).
Pediatric studies of OTULFI I.V. have not been conducted. No studies have been conducted in pediatric patients with psoriatic arthritis, Crohn’s disease or ulcerative colitis.
7.1.4 Geriatrics
Geriatrics (> 65 years of age): Of the 6709 patients exposed to ustekinumab in clinical trials, a total of 353 were 65 years or older (183 patients with psoriasis, 69 patients with psoriatic arthritis, 58 patients with Crohn’s disease and 43 patients with ulcerative colitis). No major age-related differences in clearance or volume of distribution were observed in clinical studies. Although no overall differences in safety and efficacy were observed between older and younger patients in clinical studies in approved indications, the number of patients aged 65 and over is not sufficient to determine whether they respond differently from younger patients. Patients over 60 years of age should be closely monitored for skin cancer (see 7 WARNINGS AND PRECAUTIONS, Carcinogenesis and Mutagenesis).
8. Adverse Reactions
The adverse drug reaction profiles reported in clinical studies that compared OTULFI/OTULFI I.V. to the reference biologic drug were comparable. The description of adverse reactions in this section is based on clinical experience with the reference biologic drug.
8.1 Adverse Reaction Overview
The most common adverse reactions (> 5%) in controlled periods of the clinical studies with ustekinumab among all indications were nasopharyngitis, and headache. Most were considered to be mild and did not necessitate drug discontinuation. The overall safety profile of ustekinumab was similar for patients among all indications. Serious infections and malignancies were also reported in clinical studies (see 8.2 Clinical Trial Adverse Reactions; Infections and Malignancies).
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials; therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
Adults
The safety data described below reflect exposure to ustekinumab I.V. in 14 Phase 2 and Phase 3 studies in 6709 patients (4135 with psoriasis and/or psoriatic arthritis, 1749 with Crohn’s disease, and 825 with ulcerative colitis), including 4577 exposed for at least 6 months, 3253 exposed for at least 1 year, 1482 exposed for at least 4 years and 838 for at least 5 years.
Psoriasis and Psoriatic Arthritis
The safety data described below reflect exposure to ustekinumab in 7 phase 2 and phase 3 studies in 4135 adult patients with psoriasis and/or psoriatic arthritis, including 3256 exposed for at least 6 months, 1482 exposed for at least 4 years and 838 for at least 5 years.
Table 5 summarizes the adverse reactions that occurred at a rate of at least 1% in the ustekinumab group during the placebo-controlled period of the Phase 3 studies (PHOENIX 1, PHOENIX 2, PSUMMIT 1 and PSUMMIT 2).
Table 5 Adverse reactions reported by ≥ 1% of patients during the placebo controlled period of PHOENIX 1 and 2 and PSUMMIT 1 and 2*
| System organ class | Placebo | Ustekinumab | |||||||
|---|---|---|---|---|---|---|---|---|---|
| 45 mg | 90 mg | ||||||||
| Patients treated | 974 | 972 | 974 | ||||||
| Infections and infestations | |||||||||
| Nasopharyngitis | 64 (6.6%) | 72 (7.4%) | 70 (7.2%) | ||||||
Upper respiratory tract infection | 44 (4.5%) | 46 (4.7%) | 40 (4.1%) | ||||||
| Dental Infection | 2 (0.2%) | 9 (0.9%) | 10 (1.0%) | ||||||
| Nervous system disorders | |||||||||
| Headache | 29 (3.0%) | 48 (4.9%) | 41 (4.2%) | ||||||
| Dizziness | 9 (0.9%) | 11 (1.1%) | 13 (1.3%) | ||||||
| Respiratory, thoracic and mediastinal disorders | |||||||||
| Oropharyngeal pain | 9 (0.9%) | 16 (1.6%) | 15 (1.5%) | ||||||
| Gastrointestinal disorders | |||||||||
| Diarrhea | 15 (1.5%) | 22 (2.3%) | 18 (1.8%) | ||||||
| Nausea | 10 (1.0%) | 18 (1.9%) | 15 (1.5%) | ||||||
| Skin and subcutaneous tissue disorders | |||||||||
| Pruritus | 9 (0.9%) | 14 (1.4%) | 12 (1.2%) | ||||||
| Musculoskeletal and connective tissue disorders | |||||||||
| Arthralgia | 23 (2.4%) | 30 (3.1%) | 26 (2.7%) | ||||||
| Back pain | 9 (0.9%) | 12 (1.2%) | 19 (2.0%) | ||||||
| Myalgia | 5 (0.5%) | 8 (0.8%) | 11 (1.1%) | ||||||
| General disorders and administration site conditions | |||||||||
| Fatigue | 16 (1.6%) | 24 (2.5%) | 24 (2.5%) | ||||||
| Injection site erythema | 6 (0.6%) | 8 (0.8%) | 16 (1.6%) | ||||||
*Placebo controlled periods are through Week 12 in PHOENIX 1 AND 2 and through Week 16 in PSUMMIT 1 and 2.
Table 6 present the rates at which the ustekinumab ADRs occurred in treatment groups in the ACCEPT trial.
Table 6 Adverse drug reactions reported by ≥ 1% of patients through Week 12 in ACCEPT
ENBREL® (etanercept) | Ustekinumab | ||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| 45 mg | 90 mg | ||||||||||||
| Patients treated | 347 | 209 | 347 | ||||||||||
| Infections and infestations | |||||||||||||
| Nasopharyngitis | 29 (8.4%) | 21 (10.0%) | 34 (9.8%) | ||||||||||
Upper respiratory tract infection | 20 (5.8%) | 13 (6.2%) | 22 (6.3%) | ||||||||||
| Nervous system disorders | |||||||||||||
| Headache | 38 (11.0%) | 31 (14.8%) | 41 (11.8%) | ||||||||||
| Dizziness | 8 (2.3%) | 3 (1.4%) | 6 (1.7%) | ||||||||||
| Respiratory, thoracic and mediastinal disorders | |||||||||||||
| Oropharyngeal pain | 14 (4.0%) | 5 (2.4%) | 14 (4.0%) | ||||||||||
| Gastrointestinal disorders | |||||||||||||
| Diarrhea | 9 (2.6%) | 8 (3.8%) | 9 (2.6%) | ||||||||||
| Nausea | 8 (2.3%) | 8 (3.8%) | 10 (2.9%) | ||||||||||
| Skin and subcutaneous tissue disorders | |||||||||||||
| Pruritus | 14 (4.0%) | 12 (5.7%) | 16 (4.6%) | ||||||||||
| Musculoskeletal and connective tissue disorders | |||||||||||||
| Arthralgia | 9 (2.6%) | 11 (5.3%) | 10 (2.9%) | ||||||||||
| Back pain | 7 (2.0%) | 14 (6.7%) | 15 (4.3%) | ||||||||||
| Myalgia | 7 (2.0%) | 3 (1.4%) | 7 (2.0%) | ||||||||||
| General disorders and administration site conditions | |||||||||||||
| Fatigue | 13 (3.7%) | 8 (3.8%) | 19 (5.5%) | ||||||||||
| Injection site erythema | 51 (14.7%) | 2 (1.0%) | 2 (0.6%) | ||||||||||
Crohn’s Disease
In the three Phase 3 studies and two Phase 2 studies, 1749 subjects with Crohn’s disease were exposed to ustekinumab with 849 exposed for 6 months and 464 exposed for at least 1 year with a total 1106 subject-years of follow-up.
The safety of ustekinumab was assessed in three Phase 3 randomized, double-blind, placebo-controlled studies. Two 8-week IV induction studies (UNITI-1 and UNITI-2) were followed by a 44-week subcutaneous randomized withdrawal maintenance study (IM-UNITI) representing 52 weeks of therapy. The overall safety profile of ustekinumab was consistent with the safety profile seen in the psoriasis and psoriatic arthritis clinical studies with the exception of new adverse drug reactions of acne, asthenia, vomiting and vulvovaginal mycotic infections.
The safety profile remained generally consistent throughout the Week 272 safety analysis.
Table 7 Adverse drug reactions reported by ≥ 1%# of ustekinumab I.V. treated patients UNITI-1 and UNITI-2 Induction Studies through Week 8
| Patients Treated | Placebo (n=466) | Ustekinumab I.V. ~6mg/kg¥ (n=470) |
|---|---|---|
| Patients Treated | Placebo (n=466) | Ustekinumab I.V. ~6mg/kg¥ (n=470) |
| Treatment Emergent Adverse Events (SOC/preferred term) | ||
| Gastrointestinal disorders | ||
| Nausea | 22 (4.7%) | 25 (5.3%) |
| Vomiting | 12 (2.6%) | 20 (4.3%) |
| Infections and infestations | ||
| Nasopharyngitis | 23 (4.9%) | 25 (5.3%) |
| Musculoskeletal and connective tissue disorders | ||
| Arthralgia | 22 (4.7%) | 24 (5.1%) |
| Back Pain | 9 (1.9%) | 10 (2.1%) |
| General disorders and administration site conditions | ||
| Asthenia | 2 (0.4%) | 7 (1.5%) |
| Skin and subcutaneous tissue disorders | ||
| Pruritus | 2 (0.4%) | 7 (1.5%) |
| Acne | 2 (0.4%) | 5 (1.1%) |
#≥ 1% and more frequently with ustekinumab than placebo.
¥ tiered weight-based dose approximating 6 mg/kg (see 4 DOSAGE AND ADMINISTRATION, Table 3)
Table 8 Adverse drug reactions reported by ≥ 1%¥ of patients in any ustekinumab-treated groups IM-UNITI study through Week 0 to Week 44 of maintenance
| Patients Treated | Placebo (n=133) | Ustekinumab 90 mg | |
|---|---|---|---|
| Patients Treated | Placebo (n=133) | Ustekinumab 90 mg | |
Q12w (n=132) | Q8w (n=131) | ||
Q12w (n=132) | Q8w (n=131) | ||
| Treatment Emergent Adverse Events (SOC/preferred term) | |||
| Infections and Infestations | |||
| Nasopharyngitis | 10 (7.5%) | 17 (12.9%) | 14 (10.7%) |
| Vulvovaginal mycotic infection (including candidiasis) | 1 (0.8%) | 1 (0.8%) | 6 (4.6%) |
| Gastrointestinal system disorders | |||
| Diarrhea | 7 (5.3%) | 11 (8.3%) | 5 (3.8%) |
| Nausea | 9 (6.8%) | 10 (7.6%) | 4 (3.1%) |
| Musculoskeletal and connective tissue disorder | |||
| Arthralgia | 19 (14.3%) | 22 (16.7%) | 18 (13.7%) |
| Back pain | 6 (4.5%) | 5 (3.8%) | 6 (4.6%) |
| Myalgia | 1 (0.8%) | 5 (3.8%) | 1 (0.8%) |
| General disorders and administration site conditions | |||
| Fatigue | 6 (4.5%) | 8 (6.1%) | 6 (4.6%) |
| Injection site erythema | 0 | 1 (0.8%) | 7 (5.3%) |
| Injection site pain | 1 (0.8%) | 2 (1.5%) | 0 |
| Skin and subcutaneous tissue disorder | |||
| Pruritus | 3 (2.3%) | 2 (1.5%) | 5 (3.8%) |
| Acne | 1 (0.8%) | 1 (0.8%) | 2 (1.5%) |
| Nervous system disorder | |||
| Headache | 15 (11.3%) | 15 (11.4%) | 16 (12.2%) |
| Psychiatric disorders | |||
| Depression | 2 (1.5%) | 3 (2.3%) | 2 (1.5%) |
¥≥ 1% and more frequently with either ustekinumab 90 mg q12w or ustekinumab 90 mg q8w than placebo.
Ulcerative Colitis
The safety of ustekinumab was evaluated in two randomized, double-blind, placebo-controlled studies (UNIFI-I and UNIFI-M) in 960 adult patients with moderately to severely active ulcerative colitis. The overall safety profile was similar for patients with psoriasis, psoriatic arthritis, Crohn’s disease and ulcerative colitis.
The safety profile remained generally consistent throughout the Week 96 safety analysis.
Table 9 Adverse drug reactions reported by ≥ 1%# of ustekinumab I.V. treated patients in the ulcerative colitis induction study (UNIFI-I) through Week 8
| Patients Treated | Placebo (n=319) | Ustekinumab I.V. ~6mg/kg¥ (n=320) |
|---|---|---|
| Treatment Emergent Adverse Events (SOC/preferred term) | ||
| Gastrointestinal disorders | ||
| Vomiting | 1 (0.3%) | 4 (1.3%) |
| Infections and infestations | ||
| Nasopharyngitis | 9 (2.8%) | 18 (5.6%) |
| Musculoskeletal and connective tissue disorders | ||
| Arthralgia | 3 (0.9%) | 6 (1.9%) |
| General disorders and administration site conditions | ||
| Fatigue | 5 (1.6%) | 8 (2.5%) |
| Nervous system | ||
| Dizziness | 1 (0.3%) | 4 (1.3%) |
| Respiratory, thoracic and mediastinal disorders | ||
| Oropharyngeal pain | 1 (0.3%) | 8 (2.5%) |
# ≥ 1% and more frequently with ustekinumab than placebo.
¥ tiered weight-based dose approximating 6 mg/kg (see 4 DOSAGE AND ADMINISTRATION, Table 3)
Table 10 Adverse drug reactions reported by ≥ 1%¥ of patients in any ustekinumab-treated patients in the ulcerative colitis maintenance study (UNIFI-M) through Week 0 to Week 44 of maintenance
| Patients Treated | Placebo (n=175) | Ustekinumab 90 mg | |
|---|---|---|---|
| Patients Treated | Placebo (n=175) | Ustekinumab 90 mg | |
Q12w (n=172) | Q8w (n=176) | ||
Q12w (n=172) | Q8w (n=176) | ||
| Treatment Emergent Adverse Events (SOC/preferred term) | |||
| Infections and Infestations | |||
| Nasopharyngitis | 28 (16.0%) | 31 (18.0%) | 26 (14.8%) |
| Upper respiratory tract infection | 8 (4.6%) | 5 (2.9%) | 16 (9.1%) |
| Sinusitis | 2 (1.1%) | 2 (1.2%) | 7 (4.0%) |
| Gastrointestinal system disorders | |||
| Diarrhea | 2 (1.1%) | 5 (2.9%) | 7 (4.0%) |
| Nausea | 4 (2.3%) | 4 (2.3%) | 6 (3.4%) |
| Musculoskeletal and connective tissue disorder | |||
| Arthralgia | 15 (8.6%) | 15 (8.7%) | 8 (4.5%) |
| General disorders and administration site conditions | |||
| Fatigue | 4 (2.3%) | 4 (2.3%) | 7 (4.0%) |
| Injection site erythema | 1 (0.6%) | 1 (0.6%) | 3 (1.7%) |
| Skin and subcutaneous tissue disorder | |||
| Acne | 0 (0%) | 2 (1.2%) | 3 (1.7%) |
| Nervous system disorder | |||
| Dizziness | 0 (0%) | 0 (0%) | 3 (1.7%) |
| Headache | 7 (4.0%) | 11 (6.4%) | 18 (10.2%) |
| Respiratory, thoracic and mediastinal disorders | |||
| Nasal congestion | 0 (0%) | 0 (0%) | 3 (1.7%) |
| Oropharyngeal pain | 5 (2.9%) | 4 (2.3%) | 7 (4.0%) |
| Psychiatric disorders | |||
| Depression | 1 (0.6%) | 2 (1.2%) | 1 (0.6%) |
¥ ≥ 1% and more frequently with either ustekinumab 90 mg q12w or ustekinumab 90 mg q8w than placebo.
Infections:
In placebo-controlled studies of patients with psoriasis, psoriatic arthritis, Crohn’s disease and ulcerative colitis, the rates of infection or serious infection were similar between ustekinumab-treated patients and those treated with placebo. In the placebo-controlled period of these clinical studies, the rate of infection was 1.36 per patient-year of follow-up in ustekinumab-treated patients, and 1.34 per patient-year of follow-up in placebo-treated patients. Serious infections occurred at a rate of 0.03 per patient-year of follow-up in ustekinumab-treated patients (30 serious infections in 930 patient-years of follow-up) and 0.03 per patient-year of follow-up in placebo-treated patients (15 serious infections in 434 patient-years of follow-up) (see 7 WARNINGS AND PRECAUTIONS).
In the controlled and non-controlled portions of placebo-controlled psoriasis, psoriatic arthritis, Crohn’s disease and ulcerative colitis clinical studies representing 11,581 patient-years of exposure in 6,709 patients, the median follow-up was 1.0 years; 1.1 years for psoriatic disease studies, 0.6 year for Crohn’s disease studies and 1.0 years for ulcerative colitis studies. The rate of infection was 0.91 per patient-year of follow-up in ustekinumab-treated patients. The rate of serious infections was 0.02 per patient-year of follow-up in ustekinumab-treated patients (199 serious infections in 11581 patient-years of follow-up) and included pneumonia, anal abscess, sepsis, cellulitis, diverticulitis, gastroenteritis and viral infections.
Malignancies:
In the placebo-controlled period of the psoriasis, psoriatic arthritis, Crohn’s disease and ulcerative colitis clinical studies, the incidence of non-melanoma skin cancer was 0.43 per 100 patient-years of follow-up for ustekinumab-treated patients (4 patients in 929 patient-years of follow-up) compared with 0.46 per 100 patient-years of follow-up for placebo-treated patients (2 patient in 433 patient-years of follow-up) during the placebo-controlled periods. In a Phase 3 clinical trial (ACCEPT) comparing ustekinumab and etanercept for the treatment of moderate to severe plaque psoriasis, 209 patients received ustekinumab 45 mg, 347 patients received ustekinumab 90 mg, and 347 patients received etanercept. Through Week 12, three (0.5%) subjects in the ustekinumab groups had a non-melanoma skin cancer detected in areas of psoriasis that had cleared with treatment. No skin cancers were observed in the etanercept group but due to the short treatment period, the possible pre-existing malignancies and the differences in efficacy (see 14 CLINICAL TRIALS), the clinical relevance has not been established.
The incidence of malignancies excluding non-melanoma skin cancer was 0.11 per 100 patient-years of follow-up for ustekinumab-treated patients (1 patient in 929 patient-years of follow-up) compared with 0.23 per 100 patient-years of follow-up for placebo-treated patients (1 patient in 434 patient-years of follow-up) during the placebo-controlled periods. In the ACCEPT trial, through Week 12, one subject (0.2%) with a familial history of breast cancer was diagnosed with breast cancer versus no malignancies in the etanercept group.
In the controlled and non-controlled periods of psoriasis, psoriatic arthritis, Crohn’s disease and ulcerative colitis clinical studies representing 11,561 patient-years of exposure in 6709 patients, the median follow-up was 1.0 years; 1.1 years for psoriatic disease studies, 0.6 year for Crohn’s disease studies and 1.0 years for ulcerative colitis studies. Malignancies excluding non- melanoma skin cancers were reported in 62 patients in 11561 patient-years of follow-up. This represents an incidence of 0.54 per 100 patients-years of follow-up for ustekinumab- treated patients. This rate of malignancies reported in ustekinumab-treated patients was comparable to the rate expected in the general population (standardized incidence ratio = 0.93 [95% confidence interval: 0.71,1.20]). The most frequently observed malignancies, other than non-melanoma skin cancer, were prostate (16), colorectal (7), melanoma (6), and breast (5). The incidence of non-melanoma skin cancer was 0.49 per 100 patient-years of follow-up for ustekinumab-treated patients (56 patients in 11545 patient-years of follow-up). The ratio of patients with basal versus squamous cell skin cancers (3:1) is comparable with the ratio expected in the general population.
Among 1569 patients exposed to ustekinumab for at least 3 years, 0.9% (n= 14) of patients reported NMSC and 1.4% (n=22) of patients reported malignancies excluding NMSC. This represents an incidence of 0.18 and 0.29 per 100 patient-years of follow-up for NMSC and malignancies excluding NMSC, respectively.
Hypersensitivity and Infusion Reactions:
Subcutaneous Administration
During the controlled periods of the psoriasis and psoriatic arthritis clinical studies of ustekinumab, rash and urticaria have each been observed in < 1% of patients.
In the maintenance Crohn’s disease study, 1.7% of patients reported a placebo injection-site reaction and 3.0% reported an ustekinumab injection-site reaction.
Intravenous Administration
In Crohn’s disease and ulcerative colitis induction studies, no events of anaphylaxis or other serious infusion reactions were reported. In these studies, 2.2% of 785 placebo treated patients and 1.9% of 790 patients treated with the recommended dose of ustekinumab I.V. reported adverse events occurring during or within an hour of the infusion.
Immunogenicity:
In psoriasis and psoriatic arthritis clinical studies, up to 12.4% of patients treated with ustekinumab developed antibodies to ustekinumab. In Crohn’s disease and ulcerative colitis clinical studies, 2.9% and 4.6% of patients, respectively, developed antibodies to ustekinumab when treated with ustekinumab for approximately 1 year. No apparent association between the development of antibodies to ustekinumab and the development of injection site reactions was observed. 123 of 168 (73%) of psoriasis and psoriatic arthritis patients who were positive for antibodies to ustekinumab had neutralizing antibodies. Patients positive for antibodies to ustekinumab exhibited mean or median serum levels of ustekinumab that were consistently lower than those in patients negative or undetectable for antibodies to ustekinumab and tended to have lower efficacy; however, antibody positivity did not preclude a clinical response.
Immunogenicity tests are generally product-specific. Comparison of antibody rates to those from other products, or comparison of the incidence of antibodies between different tests without cross-validation is not appropriate.
8.2.1 Clinical Trial Adverse Reactions – Pediatrics
Pediatric Patients with Psoriasis
The safety of ustekinumab has been studied in two phase 3 studies of pediatric patients with moderate to severe plaque psoriasis. The first study was in 110 patients from 12 to 17 years of age treated for up to 60 weeks (CADMUS). The second study was in 44 patients from 6 to 11 years of age treated for up to 56 weeks (CADMUS Jr.). In general, the adverse events reported in these two studies were similar to those seen in previous studies in adults with plaque psoriasis.
Pediatrics (12 to 17 years of age)
Table 11 Adverse reaction reported by >5% of patients during the placebo-controlled period of CADMUS
| Placebo | Ustekinumab | |||||||||
|---|---|---|---|---|---|---|---|---|---|---|
| Half Standard Dosage | Standard Dosage | |||||||||
| Patients treated | 37 | 37 | 36 | |||||||
| Infections and infestations | ||||||||||
| Upper respiratory tract infection | 2 (5.4%) | 1 (2.7%) | 3 (8.3%) | |||||||
| Nervous system disorders | ||||||||||
| Headache | 2 (5.4%) | 4 (10.8%) | 3 (8.3%) | |||||||
| Gastrointestinal disorders | ||||||||||
| Diarrhea | 0 | 0 | 2 (5.6%) | |||||||
Pediatric (6 to 11 years of age)
No new safety issues were identified in pediatric patients 6 to 11 years of age and the observed safety profile in these pediatric patients was similar to the safety profile observed in ustekinumab - treated adolescent patients 12 to 17 years of age.
8.3 Less Common Clinical Trial Adverse Reactions
The following adverse reactions occurred at rates less than 1% during the controlled period of ustekinumab clinical trials:
General disorders and administration site conditions: injection site reactions (including swelling, pruritus, induration, hemorrhage, hematoma), asthenia
Infections and infestations: cellulitis, herpes zoster, viral upper respiratory tract infections, vulvovaginal mycotic infections, dental infections
Psychiatric disorders: depression
Respiratory, thoracic and mediastinal disorders: nasal congestion
Skin and Subcutaneous tissue disorders: acne
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data
During the placebo-controlled period of the Phase 2 and Phase 3 psoriasis studies (through week 12), an increase in non-fasting blood glucose levels was observed, as shown in Table 12. The clinical significance of these changes in glucose is unknown. No such increase in fasting blood glucose levels was observed in the same subjects.
Table 12 Proportion of patients with elevated non-fasting blood glucose levels in clinical trials
| Increase in non-fasting blood glucose levels | Placebo N (%) | Combined ustekinumab group n (%) |
|---|---|---|
| Number of Patients | 730 | 1580 |
| Subjects with any abnormal value | 49 (6.7%) | 83 (5.3%) |
| Subjects with > 1 abnormal value | 9 (1.2%) | 35 (2.2 %) |
8.5 Post-Market Adverse Reactions
Additional adverse events reported from worldwide post-marketing experience with ustekinumab are included in Table 13. Because these events are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to ustekinumab exposure.
Table 13 Post-marketing Reports
| Immune system disorders | Hypersensitivity reactions (including rash, urticaria) Serious allergic reactions (including anaphylaxis and angioedema) |
|---|---|
| Infections and infestations | Lower respiratory tract infection |
| Respiratory, thoracic and mediastinal disorders | Allergic alveolitis, eosinophilic pneumonia |
Skin and subcutaneous tissue disorders | Pustular psoriasis Exfoliative dermatitis, erythrodermic psoriasis, hypersensitivity vasculitis |
9. Drug Interactions
9.2 Drug Interactions Overview
Specific drug interaction studies have not been conducted with ustekinumab.
In population pharmacokinetic analysis, the effect of the most frequently used concomitant medications in patients with psoriasis (including paracetamol/acetaminophen, ibuprofen, acetylsalicylic acid, metformin, atorvastatin, naproxen, levothyroxine, hydrochlorothiazide, and influenza vaccine) on pharmacokinetics of ustekinumab was explored and none of the concomitant medications exerted significant impact. In psoriatic arthritis studies, concomitant MTX use did not appear to influence the pharmacokinetics of ustekinumab. In Crohn’s disease and ulcerative colitis induction studies, immunomodulators (6-MP, AZA, MTX) were used concomitantly in approximately 30% of patients and corticosteroids were used concomitantly in approximately 40% and 50% of Crohn’s disease and ulcerative colitis patients, respectively. Use of these concomitant therapies did not appear to influence the pharmacokinetics of ustekinumab.
9.3 Drug-Behaviour Interactions
The pharmacokinetics of ustekinumab were not impacted by the use of tobacco or alcohol.
9.4 Drug-Drug Interactions
Live Vaccines
Live vaccines should not be given concurrently with ustekinumab (see 7 WARNINGS AND PRECAUTIONS, Immune, Immunization). Information regarding the administration of live vaccines in infants exposed to ustekinumab in utero is provided earlier in this product monograph (see 7 WARNINGS AND PRECAUTIONS, Immune, Infant exposure in utero).
Immunosuppressants
The safety and efficacy of ustekinumab in combination with immunosuppressive agents or phototherapy have not been evaluated (see 7 WARNINGS AND PRECAUTIONS, Immune, Concomitant immunosuppressive therapy).
CYP450 Substrates
The effects of IL-12 or IL-23 on the regulation of CYP450 enzymes were evaluated in an in vitro study using human hepatocytes, which showed that IL-12 and/or IL-23 at levels of 10 ng/mL did not alter human CYP450 enzyme activities (CYP1A2, 2B6, 2C9, 2C19, 2D6, or 3A4). The clinical significance of this is not known, although these results do not suggest the need for dose adjustments in patients who are receiving concomitant CYP450 substrates.
9.5 Drug-Food Interactions
Interactions with food have not been established.
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10. Clinical Pharmacology
10.1 Mechanism of Action
Ustekinumab is a fully human IgG1қ monoclonal antibody, a first-in-class agent that binds with specificity to the shared p40 protein subunit of human cytokines interleukin IL-12 and IL-23.
Ustekinumab inhibits the bioactivity of human IL-12 and IL-23 by preventing p40 from binding to the IL-12Rβ1 receptor protein expressed on the surface of immune cells. Ustekinumab cannot bind to IL-12 or IL-23 that is already bound to IL-12Rβ1 cell surface receptors. Thus, ustekinumab is not likely to contribute to complement or antibody-mediated cytotoxicity of cells expressing IL-12 and/or IL-23 receptors.
IL-12 and IL-23 are heterodimeric cytokines secreted by activated antigen-presenting cells, such as macrophages and dendritic cells. IL-12 stimulates natural killer (NK) cells and drives the differentiation of CD4+ T cells toward the T helper 1(Th1) phenotype and stimulates interferon gamma (IFNγ) production. IL-23 induces the T helper 17 (Th17) pathway and promotes secretion of IL-17A, IL-21, and IL-22. Levels of IL-12 and IL-23 are elevated in the skin and blood of patients with psoriasis, and serum IL12/23p40 distinguishes patients with psoriatic arthritis from healthy individuals, implicating IL-12 and IL-23 in the pathophysiology of psoriatic inflammatory diseases. Genetic polymorphisms in IL23A, IL23R, and IL-12B genes confer susceptibility to these disorders. Additionally, IL-12 and IL-23 are highly expressed in lesional psoriatic skin, and IL-12-mediated induction of IFNγ correlates with psoriasis disease activity. IL-23 responsive T-cells have been found in the entheses in a mouse model of inflammatory arthritis, where IL-23 drives entheseal inflammation. In addition, there is pre-clinical evidence implicating IL-23 and downstream pathways in bone erosion and destruction through up-regulation of receptor activator of nuclear factor-κB ligand (RANKL), which activates osteoclasts.
In patients with Crohn’s disease, IL-12 and IL-23 are elevated in the intestines and lymph nodes.
By binding the shared p40 subunit of IL-12 and IL-23, ustekinumab may exert its clinical effects in psoriasis, psoriatic arthritis, Crohn’s disease and ulcerative colitis through interruption of the Th1 and Th17 cytokine pathways, which have been implicated as contributors in the pathology of these diseases.
10.2 Pharmacodynamics
Treatment with ustekinumab resulted in significant improvement in histological measures of psoriasis including epidermal hyperplasia and cell proliferation. These results are consistent with the clinical efficacy observed. In patients with psoriasis and/or psoriatic arthritis ustekinumab had no apparent effect on the percentages of circulating immune cell populations including memory and naive T-cell subsets or circulating cytokine levels. Systemic markers of inflammation were measurable in the serum at baseline and 4 markers (MDC, VEGF, MCSF-1 and YKL-40) showed modest differences in concentration post-treatment in ustekinumab-treated patients as compared to placebo.
Treatment with ustekinumab resulted in a decrease in the gene expression of its molecular targets IL-12 and IL-23 as shown by analyses of mRNA obtained from lesional skin biopsies of psoriatic patients at baseline and up to two weeks post-treatment. In addition, ustekinumab down-regulated the gene expression of inflammatory cytokines and chemokines such as MCP-1, TNF-alpha, IP-10 and IL-8 in lesional skin biopsies. These results are consistent with the significant clinical benefit observed with ustekinumab treatment.
In psoriasis and psoriatic arthritis studies, clinical response (improvement in PASI or ACR measurements, respectively) appeared to be related to serum ustekinumab levels. Patients with psoriasis with higher PASI response had higher median serum concentrations of ustekinumab than those with lower clinical responses. In psoriasis studies, the proportion of patients with psoriasis who achieved PASI 75 response increased with increasing serum levels of ustekinumab. The proportion of patients who achieved PASI 75 response at Week 28 increased with increasing serum ustekinumab trough levels at Week 28. In psoriatic arthritis studies, patients achieving an ACR 20 response had higher median serum concentrations of ustekinumab than ACR 20 non-responders. The proportion of patients who achieved ACR 20 and ACR 50 response increased with increasing serum levels of ustekinumab.
In patients with Crohn’s disease and ulcerative colitis, treatment with ustekinumab resulted in a significant decrease in inflammatory markers including C-Reactive Protein (CRP) and fecal calprotectin. In patients with Crohn’s disease, decrease in gene expression for IL-12Rβ1 and IL-23 was observed in inflamed colon tissue in responders to ustekinumab I.V. treatment while no significant changes were observed in placebo treated patients at Week 6.
10.3 Pharmacokinetics
The median pharmacokinetic parameters of ustekinumab following a single SC administration in adult patients with psoriasis are shown in Table 14. The pharmacokinetic parameters of ustekinumab (CL/F, Vz/F, and t1/2) were generally comparable between 45 mg and 90 mg subcutaneous doses.
Table 14 Summary of Pharmacokinetic Parameters of Ustekinumab Following a Single 45 or 90 mg Subcutaneous Administration in Adult Patients with Psoriasis
| Dose | 45 mg | 90 mg | ||||
|---|---|---|---|---|---|---|
| PK parameter | N | Median (Range) | Mean (± SD) | N | Median (Range) | Mean (± SD) |
| Cmax (mcg/mL) | 22 | 2.4 (1.0, 5.4) | 2.7 (± 1.2) | 24 | 5.3 (1.2, 12.3) | 6.1 (± 3.6) |
| tmax (day) | 22 | 13.5 (1.9, 58.2) | 15.3 (± 13.5) | 24 | 7.0 (2.9, 27.1) | 9.9 (± 7.4) |
| AUC (mcg·day/mL) | 18 | 84.9 (31.2, 1261.9) | 196.7 (± 298.2) | 21 | 226.9 (57.1, 755.5) | 274.9 (± 206.5) |
| t1/2 (day) | 18 | 19.8 (5.0, 353.6) | 45.6 (± 80.2) | 21 | 21.2 (13.6, 85.8) | 26.7 (± 19.3) |
| CL/F (mL/day/kg) | 18 | 5.3 (0.2, 12.9) | 5.8 (± 3.5) | 21 | 4.5 (1.5, 14.9) | 5.7 (± 3.6) |
| Vz/F (mL/kg) | 18 | 154.2 (32.6, 280.5) | 160.5 (± 64.5) | 21 | 160.5 (37.3, 354.1) | 178.7 (± 85.2) |
Source data: C0379T04 CSR
Dose Linearity: The systemic exposure of ustekinumab (Cmax and AUC) increased in a linear manner following a single subcutaneous administration at doses ranging from approximately 24 mg to 240 mg in patients with psoriasis.
Single Dose vs. Multiple Doses: Serum concentration-time profiles of ustekinumab were generally predictable after single or multiple subcutaneous dose administrations on the basis of a one-compartment model. In patients with psoriasis, steady-state serum concentrations of ustekinumab were achieved by Week 28 after initial subcutaneous doses at Weeks 0 and 4 followed by doses every 12 weeks. The median steady-state trough concentration ranged from 0.21 mcg/mL to 0.26 mcg/mL (45 mg; n = 242 to 390) and from 0.47 mcg/mL to 0.49 mcg/mL (90 mg; n = 236 to 386) in patients with psoriasis. There was no apparent accumulation in serum ustekinumab concentration over time when given subcutaneously every 12 weeks.
Population Pharmacokinetic Analysis
Of the demographic factors (e.g., gender, race, age, body size), baseline patient physical or biochemical characteristics, medical or medication history, or concomitant medications evaluated in a population pharmacokinetic analysis, only body weight, diabetes comorbidity, and positive immune response to ustekinumab were found to be important covariates affecting the systemic exposure to ustekinumab in patients with moderate to severe psoriasis. Body weight and positive immune response to ustekinumab were also found to be important covariates affecting the systemic exposure to ustekinumab in subjects with psoriatic arthritis. Clinical relevance of the effects of these important covariates, however, needs to be evaluated concurrently with clinical efficacy and safety data.
Absorption
The median time to reach the maximum serum concentration (tmax) was 8.5 days after a single 90 mg subcutaneous administration in healthy subjects (n = 30). The median tmax values of ustekinumab following a single subcutaneous administration of either 45 mg or 90 mg in patients with psoriasis were comparable to that observed in healthy subjects.
The absolute bioavailability (F) of ustekinumab following a single subcutaneous administration was estimated to be 57.2% in patients with psoriasis (n = 17).
Following the recommended IV induction dose, median peak serum ustekinumab concentration was 126.1 mcg/mL (IQ range 106.1 – 146.2 mcg/mL) in patients with Crohn’s disease and 127.0 mcg/mL (IQ range 109.2 – 145.9 mcg/mL) in patient with ulcerative colitis. Starting at Week 8, subcutaneous maintenance dosing of 90 mg ustekinumab was administered every 8 or 12 weeks. Steady state ustekinumab concentration was achieved by the start of the second maintenance dose.
Following subcutaneous maintenance dosing of 90 mg ustekinumab every 8 weeks, median steady-state trough concentrations ranged from 1.97 mcg/mL to 2.24 mcg/mL in patients with Crohn’s disease and 2.69 mcg/mL to 3.09 mcg/mL in patients with ulcerative colitis. Following subcutaneous maintenance dosing of 90 mg ustekinumab every 12 weeks, median steady state trough concentrations ranged from 0.61 mcg/mL to 0.76 mcg/mL in patients with Crohn’s disease and 0.92 mcg/mL to 1.19 mcg/mL in patients with ulcerative colitis. The steady-state trough ustekinumab levels resulting from 90 mg ustekinumab every 8 weeks were associated with higher clinical remission rates as compared to the steady-state trough levels following 90 mg every 12 weeks.
Distribution
The median apparent volume of distribution during the terminal phase (Vz/F) following a single subcutaneous administration to patients with psoriasis ranged from 76 to 161 mL/kg (n = 4 to 21).
In a population pharmacokinetic analysis of ustekinumab in patients with Crohn’s disease, the total volume of distribution at steady-state was 4.62 L and 4.44 L in patients with ulcerative colitis.
Metabolism
The exact metabolic pathway for ustekinumab is unknown.
Elimination
The median apparent clearance (CL/F) following a single subcutaneous administration to patients with psoriasis ranged from 2.7 to 5.3 mL/day/kg. The median half-life (t1/2) of ustekinumab was approximately 3 weeks in patients with psoriasis and/or psoriatic arthritis, Crohn’s disease and ulcerative colitis ranging from 15 to 32 days across all psoriasis and psoriatic arthritis studies (n = 4 to 55).
In a population pharmacokinetic analysis, the clearance of ustekinumab was 0.19 L/day (95% CI: 0.185, 0.197) in patients with Crohn’s disease and 0.19 L/day (95% CI: 0.179, 0.192) in patients with ulcerative colitis with an estimated median terminal half-life of approximately 19 days in patients with Crohn’s disease and ulcerative colitis.
Special Populations and Conditions
Pediatrics
Pediatrics (< 18 years of age): Studies of ustekinumab in pediatric patients with plaque psoriasis below 6 years of age have not been conducted. No pharmacokinetic data are available in pediatric patients with Crohn’s disease or ulcerative colitis. Pediatric studies of ustekinumab I.V. have not been conducted.
Serum ustekinumab concentrations in plaque psoriasis patients 6 to 17 years of age, treated with the recommended weight-based dose were generally comparable to those in the adult psoriasis population treated with the adult dose.
Geriatrics
Geriatrics (> 65 years of age): No specific studies have been conducted in elderly patients. A population pharmacokinetic analysis indicated there were no apparent changes in CL/F and V/F estimates in patients ≥ 65 years.
- Sex, Ethnic Origin and Genetic Polymorphism: The apparent clearance of ustekinumab was not impacted by sex, age, or race.
- Hepatic Insufficiency: No pharmacokinetic data are available in patients with impaired hepatic function.
- Renal Insufficiency: No pharmacokinetic data are available in patients with renal insufficiency.
Obesity
Impact of Weight on Pharmacokinetics:
Serum ustekinumab concentrations were affected by weight in patients with psoriasis and/or psoriatic arthritis. When given the same dose, patients of higher weight (> 100 kg) had lower median serum ustekinumab concentrations compared with those in patients of lower weight (≤ 100 kg). However, across doses, the median trough serum concentrations of ustekinumab in patients with higher weight (> 100 kg) in the 90 mg group were comparable to those in patients with lower weight (≤ 100 kg) in the 45 mg group.
10.4 Immunogenicity
All therapeutic proteins have the potential for immunogenicity.
The detection of antibody formation is highly dependent on the sensitivity and specificity of the assay. Additionally, the observed incidence of antibody (including neutralizing antibody) positivity in an assay may be influenced by several factors including assay methodology, sample handling, timing of sample collection, concomitant medications, and underlying disease. For these reasons, comparison of incidence of antibodies in the studies described below with the incidences of antibodies in other studies or to other products may be misleading.
11. Storage, Stability and Disposal
OTULFI/OTULFI I.V must be refrigerated at 2 oC to 8 oC and protected from light. Keep the product in the original carton to protect from light until the time of use. Do not freeze. Do not shake.
If needed, individual OTULFI pre-filled syringes may be stored at room temperature up to 30 °C for a maximum single period of up to 30 days in the original carton with protection from light. Record the date when the pre-filled syringe is first removed from the refrigerator and the new expiry date on the carton in the spaces provided. The new expiry date must not exceed the original expiry date printed on the carton. Once a syringe has been stored at room temperature, it should not be returned to the refrigerator. Discard the syringe if not used within 30 days at room temperature storage.
If necessary, the diluted OTULFI I.V. infusion solution may be stored for up to eight hours at room temperature. Do not freeze. Discard any unused portion of the infusion solution.
12. Special Handling Instructions
Following administration of OTULFI/OTULFI I.V, discard any unused portion. The syringe should be disposed of in a puncture-resistant container for syringes and needles. Patients or caregivers should be instructed in the technique as well as proper syringe and needle disposal, and not to reuse these items.
PART 2: Scientific Information
13. Pharmaceutical Information
Drug Substance
Proper name: ustekinumab
Chemical name: ustekinumab
Molecular formula and molecular mass: Ustekinumab is a fully human IgG1κ mAb, with an approximate molecular weight of 148,600 daltons.
Physicochemical properties: OTULFI (ustekinumab) is clear to slightly opalescent, colourless to light brownish-yellow with a pH of approximately 6.0. OTULFI I.V. is clear to slightly opalescent, colourless to light brownish-yellow with a pH of approximately 6.0.
Product Characteristics:
OTULFI
OTULFI (ustekinumab) is supplied as a single use, sterile solution for subcutaneous injection in a Type 1 glass syringe with a fixed 29G, half-inch needle and rigid needle shield. The syringe is fitted with a needle safety device. OTULFI is also supplied as a sterile solution for subcutaneous injection in a single-use (Type 1) glass vial for SC administration.
OTULFI is supplied as 2 dosage presentations at 45 mg in 0.5 mL volume as a pre-filled syringe or a single-use vial or at 90 mg in a 1 mL volume as a pre-filled syringe. Each 1 mL of OTULFI solution contains 90 mg ustekinumab. No preservatives are present.
OTULFI I.V.
OTULFI I.V., 130 mg vial, is supplied as a sterile solution for intravenous infusion in a single use (Type 1) glass vial. The vial is stoppered with a coated stopper.
Viral Inactivation
Ustekinumab is produced by a recombinant cell line cultured by a fed-batch process and is purified by a series of steps that include measures to inactivate and remove viruses.
14. Clinical Trials
14.1 Clinical Trials by Indication
Plaque Psoriasis - Adults
The safety and efficacy of ustekinumab were assessed in two multicentre, randomized, double-blind, placebo-controlled studies (PHOENIX 1 and PHOENIX 2) in patients 18 years of age and older with chronic (> 6 months) plaque psoriasis who had a minimum body surface area (BSA) involvement of 10%, and Psoriasis Area and Severity Index (PASI) score ≥ 12 and who were candidates for phototherapy or systemic therapy. Patients with guttate, erythrodermic, or pustular psoriasis were excluded from the studies. No concomitant anti-psoriatic therapies were allowed during the study with the exception of low-potency topical corticosteroids on the face and groin after Week 12. A total of 1996 patients were enrolled in the two studies. The safety and efficacy of ustekinumab beyond 5 years have not been established.
In addition, a multicenter, randomized, active-controlled study (ACCEPT) compared the safety and efficacy of ustekinumab and etanercept in patients 18 years of age and older with chronic (> 6 months) plaque psoriasis who had a minimum BSA involvement of 10%, PASI score ≥ 12, Physician Global Assessment (PGA) score ≥ 3, who were candidates for phototherapy or systemic therapy, and who had had an inadequate response to, intolerance to, or contraindication to cyclosporine, methotrexate, or PUVA therapy. A total of 903 patients were enrolled in the study.
Baseline disease characteristics across PHOENIX 1 and 2 were similar (Table 15 and Table 16). In both studies, patients in all treatment groups had a median baseline PASI score ranging from 17 to 18. Approximately two-thirds of all patients had received prior phototherapy, 69% had received either prior conventional systemic or biologic therapy for the treatment of psoriasis, with 56% receiving prior conventional systemic therapy and 43% receiving prior biologic therapy. A total of 28% of study patients had a history of psoriatic arthritis. Similar disease characteristics were also seen in the ACCEPT trial (Table 15 and Table 16).
Table 15 Summary of patient demographics for PHOENIX 1, PHOENIX 2 and ACCEPT
| Study # | Study design | Dosage, route of administration and duration | Study subjects (n) | Mean age (Range) | Sex |
| Study # | Study design | Dosage, route of administration and duration | Study subjects (n) | Mean age (Range) | Sex |
C0743T08 (PHOENIX 1) | Double-Blind Placebo- Controlled | Fixed doses: Placebo (N = 255) Placebo → 45 mg SC regimena (N = 123) Placebo → 90 mg SC regimena (N = 120) 45 mg SC Weeks 0, 4 then q12w (N = 255) 90 mg SC Weeks 0, 4 then q12w (N = 256) | N=766 | 45.3 (19,76) | M=531 F=235 |
C0743T09 (PHOENIX 2) | Double-Blind Placebo- Controlled | Fixed doses: Placebo (N = 410)-Placebo → 45 mg SC regimena (N = 197) Placebo → 90 mg SC regimena (N = 195) 45 mg SC Weeks 0, 4 then q12w (N = 409) 90 mg SC Weeks 0, 4 then q12w (N = 411) | N=1230 | 46.2 (18, 86) | M=840 F=390 |
C0743T12 (ACCEPT) | Assessor- Blind Active- Comparator Controlled | Fixed doses: Etanercept 50 mg (N=347) twice weekly through Week 12 Ustekinumab 45 mg (N=209) at Week 0 and 4 Ustekinumab 90 mg (N=347) at Week 0 and 4 | N=903 | 45.0 (18, 81) | M=613 F=290 |
a The placebo groups crossed over to receive ustekinumab (45 mg or 90 mg) at Weeks 12 and 16 then q12w.
Table 16 Baseline Disease Characteristics in PHOENIX 1, PHOENIX 2 and ACCEPT
| PHOENIX 1 | PHOENIX 2 | ACCEPT | ||||||||||||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| PHOENIX 1 | PHOENIX 2 | ACCEPT | ||||||||||||||||||||||||
| Placebo | Ustekinumab | Placebo | Ustekinumab | Etanercept | Ustekinumab | |||||||||||||||||||||
| Placebo | Ustekinumab | Placebo | Ustekinumab | Etanercept | Ustekinumab | |||||||||||||||||||||
| Patients randomized at Week 0 | N=255 | N=511 | N=410 | N=820 | N=347 | N=556 | ||||||||||||||||||||
| Median BSA | 22.0 | 21.0 | 20.0 | 21.0 | 19.0 | 20.0 | ||||||||||||||||||||
| BSA ≥ 20% | 145 (57%) | 276 (54%) | 217 (53%) | 445 (54%) | 169 (49%) | 289 (52%) | ||||||||||||||||||||
| Median PASI | 17.80 | 17.4 | 16.90 | 17.60 | 16.8 | 17.1 | ||||||||||||||||||||
| PASI ≥ 20 | 91 (36%) | 169 (33%) | 133 (32%) | 300 (37%) | 102 (29%) | 205 (37%) | ||||||||||||||||||||
| PGA of marked or severe | 112 (44%) | 223 (44%) | 160 (39%) | 328 (40%) | 148 (43%) | 242 (44%) | ||||||||||||||||||||
| History of psoriatic arthritis | 90 (35%) | 168 (33%) | 105 (26%) | 200 (24%) | 95 (27%) | 157 (28%) | ||||||||||||||||||||
| Prior phototherapy | 150 (59%) | 342 (67%) | 276 (67%) | 553 (67%) | 224 (65%) | 368 (66%) | ||||||||||||||||||||
| Prior conventional systemic therapy excluding biologicsa | 142 (56%) | 282 (55%) | 241 (59%) | 447 (55%) | 199 (57%) | 311 (56%) | ||||||||||||||||||||
| Prior conventional systemic or biologic therapya | 189 (74%) | 364 (71%) | 287 (70%) | 536 (65%) | 218 (63%) | 337 (61%) | ||||||||||||||||||||
| Failed to respond to, had contraindication for, or intolerant to ≥ 1 conventional therapya | 139 (55%) | 270 (53%) | 254 (62%) | 490 (60%) | 347 (100%) | 555 (100%) | ||||||||||||||||||||
| Failed to respond to, had | 30 (12%) | 54 (11%) | 66 (16%) | 134 (16%) | 52 (15%) | 78 (14%) | ||||||||||||||||||||
| contraindication for, or intolerant to ≥ 3 conventional therapiesa | ||||||||||||||||||||||||||
a In PHOENIX 1 and 2, conventional systemic agents include acitretin, PUVA, methotrexate, and cyclosporine. In ACCEPT, conventional systemic agents included PUVA, methotrexate, and cyclosporine. All patients were required to be etanercept naïve at baseline in ACCEPT, but in PHOENIX 1 and 2 patients may have previously received etanercept.
PHOENIX 1 evaluated the safety and efficacy of ustekinumab versus placebo in 766 patients with plaque psoriasis. Patients were randomized in equal proportion to placebo, 45 mg or 90 mg of ustekinumab. Patients randomized to ustekinumab received 45 mg or 90 mg doses at Weeks 0 and 4 followed by the same dose every 12 weeks. Patients randomized to receive placebo at Weeks 0 and 4 crossed over to receive ustekinumab (either 45 mg or 90 mg) at Weeks 12 and 16 followed by the same dose every 12 weeks. To evaluate the efficacy of every 12-week dosing, patients who were PASI 75 responders at both Weeks 28 and 40 were re-randomized to either continue dosing of ustekinumab every 12 weeks or to placebo (i.e., withdrawal of therapy). Patients withdrawn from ustekinumab at Week 40 reinitiated ustekinumab at their original dosing regimen when they experienced at least a 50% loss of their PASI improvement obtained at Week 40. Patients were followed for at least 76 weeks.
PHOENIX 2 evaluated the safety and efficacy of ustekinumab versus placebo in 1230 patients with plaque psoriasis. This study design was identical to PHOENIX 1 through Week 28.
Dose Adjustment (every 8 weeks)
At Week 28, PHOENIX 1 patients who were nonresponders (< PASI 50 response) discontinued treatment and patients who were partial responders (≥ PASI 50 response and < PASI 75 response) were adjusted to every-8-week dosing. PASI 75 responders at Week 28 who became partial responders or nonresponders at Week 40 were adjusted to every-8-week dosing.
In PHOENIX 2, patients who were partial responders at Week 28 were re-randomized to either continue every 12 weeks dosing of ustekinumab or to switch to every 8 weeks dosing.
All patients were followed for up to 76 weeks in PHOENIX 1 and up to 52 weeks in PHOENIX 2 following first administration of study treatment.
In both studies, the primary endpoint was the proportion of patients who achieved a reduction in score of at least 75% from baseline at Week 12 by the PASI (PASI 75). Patients achieving ≥ 90% improvement in PASI from baseline (PASI 90) were considered PASI 90 responders and patients with ≥ 50% improvement in PASI from baseline (PASI 50) were considered PASI 50 responders. Another key efficacy assessment was the Physician’s Global Assessment (PGA), a 6-category scale ranging from 0 (cleared) to 5 (severe) that indicates the physician’s overall assessment of psoriasis focusing on plaque thickness/induration, erythema, and scaling.
The Dermatology Life Quality Index (DLQI), a dermatology-specific quality of life instrument designed to assess the impact of the disease on a patient’s quality of life, was assessed in both PHOENIX 1 and PHOENIX 2. Other efficacy assessments included the Nail Psoriasis Severity Index (NAPSI), a physician-assessed score that measures the severity of nail involvement (PHOENIX 1); the Itch Visual Analog Scale (VAS), used to assess the severity of itch at the time of the assessment (PHOENIX 1); the Hospital Anxiety and Depression Scale (HADS), a self- rating tool developed to evaluate psychological measures in patients with physical ailments (PHOENIX 2); and the Work Limitations Questionnaire (WLQ), a 25-item, self-administered questionnaire that was used to measure the impact of chronic health conditions on job performance and work productivity among employed populations (PHOENIX 2).
The ACCEPT trial compared the efficacy of ustekinumab to etanercept and evaluated the safety of ustekinumab and etanercept in moderate to severe psoriasis patients. The active-controlled portion of the study was from Week 0 to Week 12, during which the efficacy and safety of etanercept and 2 dose levels of ustekinumab were evaluated. This trial was powered to test the superiority of each dose level to etanercept and the primary endpoint was the proportion of patients who achieved a PASI 75 at week 12.
Study results
The results of PHOENIX 1 and PHOENIX 2 for key psoriasis clinical outcomes are presented in Table 17.
Efficacy at the Primary Endpoint, PHOENIX 1 and PHOENIX 2
The onset of action with ustekinumab was rapid and improvement was seen within 2 weeks of the first dose. In both the PHOENIX 1 and PHOENIX 2 studies, a significantly greater proportion of patients randomized to treatment with ustekinumab were PASI 75 responders compared with placebo at Week 12 (Table 17). In the PHOENIX 1 study, 67% and 66% of patients receiving ustekinumab 45 mg and 90 mg, respectively, achieved a PASI 75 response at Week 12 compared with 3% of patients receiving placebo. In the PHOENIX 2 study, 67% and 76% of patients receiving ustekinumab 45 mg and 90 mg, respectively, achieved a PASI 75 response at Week 12 compared with 4% of patients receiving placebo.
All 3 components of the PASI (plaque thickness/induration, erythema, and scaling) contributed comparably to the improvement in PASI.
The efficacy of ustekinumab was significantly superior (p<0.001) to placebo across all subgroups defined by baseline demographics, clinical disease characteristics (including patients with a history of psoriatic arthritis) and prior medication usage. While pharmacokinetic modelling suggested a trend towards higher CL/F in patients with diabetes, a consistent effect on efficacy was not observed.
Table 17 Clinical Outcomes - PHOENIX 1 and PHOENIX 2
| PHOENIX 1 | PHOENIX 2 | ||||||||||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| PHOENIX 1 | PHOENIX 2 | ||||||||||||||||||||||
| Ustekinumab |
| Ustekinumab | ||||||||||||||||||||
| Ustekinumab |
| Ustekinumab | ||||||||||||||||||||
| 45 mg | 90 mg | 45 mg | 90 mg | ||||||||||||||||||||
| 45 mg | 90 mg | 45 mg | 90 mg | ||||||||||||||||||||
| Week 12 | |||||||||||||||||||||||
| Patients randomized | 255 | 255 | 256 | 410 | 409 | 411 | |||||||||||||||||
| PASI response | |||||||||||||||||||||||
| PASI 50 responsea | 26 (10%) | 213 (84%) | 220 (86%) | 41 (10%) | 342 (84%) | 367 (89%) | |||||||||||||||||
| PASI 75 responsea | 8 (3%) | 171 (67%) | 170 (66%) | 15 (4%) | 273 (67%) | 311 (76%) | |||||||||||||||||
| PASI 90 responsea | 5 (2%) | 106 (42%) | 94 (37%) | 3 (1%) | 173 (42%) | 209 (51%) | |||||||||||||||||
| PASI 100 responsea | 0 (0%) | 33 (13%) | 28 (11%) | 0 (0%) | 74 (18%) | 75 (18%) | |||||||||||||||||
| PGA of Cleared or Minimala | 10 (4%) | 151 (59%) | 156 (61%) | 18 (4%) | 277 (68%) | 300 (73%) | |||||||||||||||||
| Week 28 | |||||||||||||||||||||||
| Patients evaluated | -- | 250 | 243 | -- | 397 | 400 | |||||||||||||||||
| PASI response | |||||||||||||||||||||||
| PASI 50 response | -- | 228 (91%) | 234 (96%) | -- | 369 (93%) | 380 (95%) | |||||||||||||||||
| PASI 75 response | -- | 178 (71%) | 191 (79%) | -- | 276 (70%) | 314 (79%) | |||||||||||||||||
| PASI 90 response | -- | 123 (49%) | 135 (56%) | -- | 178 (45%) | 217 (54%) | |||||||||||||||||
| PASI 100 response | -- | 52 (21%) | 71 (29 %) | -- | 74 (19%) | 118 (30%) | |||||||||||||||||
| PGA of Cleared or Minimal | -- | 146 (58%) | 160 (66%) | -- | 241 (61%) | 279 (70%) | |||||||||||||||||
a p < 0.001 for 45 mg or 90 mg comparison with placebo.
Other efficacy measures at Week 12
In both PHOENIX 1 and PHOENIX 2, compared with placebo, significantly greater proportions of patients randomized to 45 mg or 90 mg ustekinumab achieved a cleared or minimal PGA score, and significantly greater proportions of patients randomized to 45 mg or 90 mg ustekinumab were PASI 50, PASI 90 and PASI 100 responders at Week 12 (Table 17). In the PHOENIX 1 study, 60% and 62% of the patients treated with 45 mg and 90 mg ustekinumab, respectively, achieved PGA scores of cleared or minimal compared with 4% of placebo-treated patients. In PHOENIX 2, 68% and 73% of patients receiving 45 mg or 90 mg ustekinumab, respectively, had cleared or minimal PGA scores compared with 5% of the placebo patients. In PHOENIX 1, PASI 90 was achieved by 42% and 37% of the patients treated with 45 mg and 90 mg ustekinumab, respectively, compared with 2% of placebo-treated patients. In addition, a significantly higher proportion of subjects treated with either 45 mg (13%) or 90 mg (11%) achieved a PASI of 0 (i.e., PASI 100 response) compared with the placebo group (0.0%; p<0.001). In PHOENIX 2, the percentage of patients achieving PASI 100 and PASI 90 was 18% and 42%, respectively, in the 45 mg ustekinumab group, and 18% and 51%, respectively, in the 90 mg ustekinumab group versus 1% in the placebo group. The percentage of patients achieving PASI 50 in PHOENIX 1 was 84% and 86% in the 45 mg and 90 mg ustekinumab groups, respectively, compared with 10% in the placebo group. Similarly, 84% of patients treated with 45 mg ustekinumab, 89% of patients treated with 90 mg ustekinumab and 10% of patients treated with placebo reached PASI 50 in PHOENIX 2 (Table 17).
Response over time
In PHOENIX 1, significantly greater proportions of ustekinumab-treated patients had PASI 50 responses (9% and 10% for the 45 mg and 90 mg groups, respectively) compared with placebo (2%) by Week 2 (p<0.001). Significantly greater proportions of patients treated with ustekinumab achieved PASI 75 responses (9% and 12% for the 45 mg and 90 mg ustekinumab groups, respectively) compared with placebo (0.4%) by Week 4 (p<0.001). Maximum response was generally achieved by Week 24 in the 45 mg and 90 mg ustekinumab treatment groups, and response rates were generally sustained through Week 36 (Figure 1). In PHOENIX 1, PASI 75 rates at Week 24 were 76% for the 45 mg group, and 85% for the 90 mg group. Higher response rates were observed in patients receiving ustekinumab 90 mg than in those receiving ustekinumab 45 mg by Week 16 and these higher response rates were sustained through Week 36 (Figure 1). Similar results were observed in the PHOENIX 2 study through Week 28.
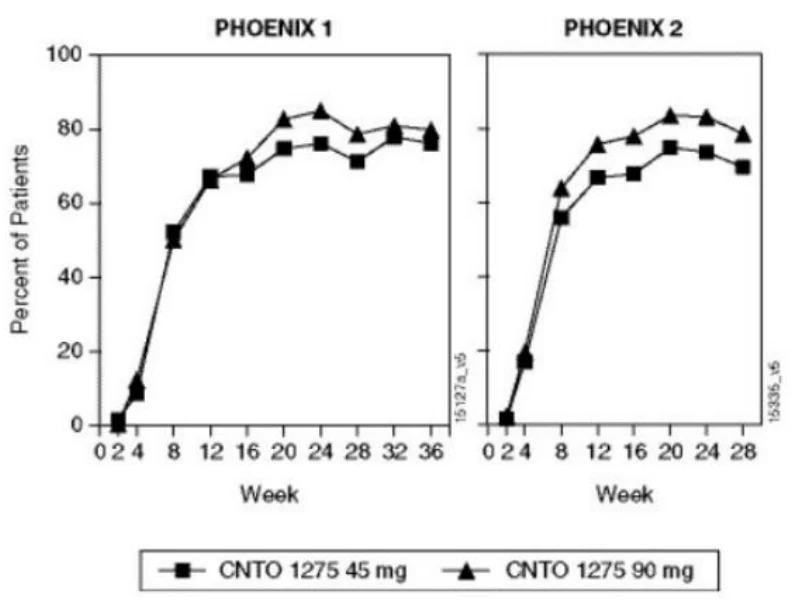
Figure 1 PASI 75 response over time in PHOENIX 1 and 2
In prespecified analyses of efficacy by body weight in PHOENIX 1 and PHOENIX 2, no consistent pattern of dose response was seen in patients ≤ 100 kg. In patients who weighed > 100 kg, higher PASI 75 response rates were seen with 90 mg dosing compared with 45 mg dosing, and a higher proportion of patients receiving 90 mg dosing had PGA scores of cleared or minimal compared with patients receiving 45 mg dosing (Table 18).
Table 18 Clinical Outcomes by Weight – PHOENIX 1 and PHOENIX 2
| Week 12 | |||||||||||||||||||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| PHOENIX 1 | PHOENIX 2 | ||||||||||||||||||||||||||||||
| Placebo | Ustekinumab | Placebo | Ustekinumab | ||||||||||||||||||||||||||||
| 45 mg | 90 mg | 45 mg | 90 mg | ||||||||||||||||||||||||||||
| Patients randomized at Week 0 | 255 | 255 | 256 | 410 | 409 | 411 | |||||||||||||||||||||||||
| PASI 75 response by weight | |||||||||||||||||||||||||||||||
| ≤ 100 kg | |||||||||||||||||||||||||||||||
| N | 166 | 168 | 164 | 290 | 297 | 289 | |||||||||||||||||||||||||
| PASI 75 response | 6 (4%) | 124 (74%) | 107 (65%) | 12 (4%) | 218 (73%) | 225 (78%) | |||||||||||||||||||||||||
| >100 kg | |||||||||||||||||||||||||||||||
| N | 89 | 87 | 92 | 120 | 112 | 121 | |||||||||||||||||||||||||
| PASI 75 response | 2 (2%) | 47 (54%) | 63 (68%) | 3 (3%) | 55 (49%) | 86 (71%) | |||||||||||||||||||||||||
| PGA of Cleared or Minimal by weight | |||||||||||||||||||||||||||||||
| ≤ 100 kg | |||||||||||||||||||||||||||||||
| N | 166 | 168 | 164 | 290 | 297 | 289 | |||||||||||||||||||||||||
| PGA response | 7 (4%) | 110 (65%) | 104 (63%) | 16 (6%) | 219 (74%) | 217 (75%) | |||||||||||||||||||||||||
| > 100 kg | |||||||||||||||||||||||||||||||
| N | 89 | 87 | 92 | 120 | 112 | 121 | |||||||||||||||||||||||||
| PGA response | 3 (3%) | 44 (51%) | 54 (59%) | 4 (3%) | 59 (53%) | 85 (70%) | |||||||||||||||||||||||||
| Week 28 | |||||||||||||||||||||||||||||||
| PHOENIX 1 | PHOENIX 2 | ||||||||||||||||||||||||||||||
| Ustekinumab | Ustekinumab | ||||||||||||||||||||||||||||||
| 45 mg | 90 mg | 45 mg | 90 mg | ||||||||||||||||||||||||||||
| N | 250 | 243 | 397 | 400 | |||||||||||||||||||||||||||
| PASI 75 response by weight | |||||||||||||||||||||||||||||||
| ≤ 100 kg | |||||||||||||||||||||||||||||||
| N | 164 | 153 | 287 | 280 | |||||||||||||||||||||||||||
| PASI 75 response | 130 (79%) | 124 (81%) | 217 (76%) | 226 (81%) | |||||||||||||||||||||||||||
| > 100 kg | |||||||||||||||||||||||||||||||
| N | 86 | 90 | 110 | 119 | |||||||||||||||||||||||||||
| PASI 75 response | 48 (56%) | 67 (74%) | 59 (54%) | 88 (74%) | |||||||||||||||||||||||||||
| PGA of Cleared or Minimal by weight | |||||||||||||||||||||||||||||||
| ≤ 100 kg | |||||||||||||||||||||||||||||||
| N | 164 | 153 | 287 | 280 | |||||||||||||||||||||||||||
| PGA response | 107 (65%) | 107 (70%) | 194 (68%) | 208 (74%) | |||||||||||||||||||||||||||
| > 100 kg | |||||||||||||||||||||||||||||||
| N | 86 | 90 | 110 | 119 | |||||||||||||||||||||||||||
| PGA response | 40 (47%) | 54 (60%) | 49 (45%) | 71 (60%) | |||||||||||||||||||||||||||
Therapeutic benefit of long-term continuous use
At Week 40 in PHOENIX 1, among patients who were PASI 75 responders at both weeks 28 and 40, 162 patients were re-randomized to receive ustekinumab at 45 mg and 90 mg given every 12 weeks (maintenance treatment) and 160 were re-randomized to receive placebo (treatment withdrawal). Maintenance of PASI 75 was significantly superior with continuous maintenance treatment compared with treatment withdrawal (p<0.001) through at least 1.5 years of follow-up. Similar results were seen with each dose of ustekinumab.
At 1 year (Week 52), 89% of patients re-randomized to maintenance treatment were PASI 75 responders compared with 63% of patients re-randomized to placebo (treatment withdrawal) (p<0.001) (Table 19). At Week 76, 84% of patients re-randomized to maintenance treatment were PASI 75 responders compared with 19% of patients re-randomized to placebo (treatment withdrawal) (p<0.001). Through 18 months (Week 76), the proportion of subjects in the combined maintenance treatment group who were PASI 50 responders remained consistently at greater than 95%. By contrast, the proportion of PASI 50 responders in the combined withdrawal group progressively decreased over time such that by Weeks 52 and 76, only 50% and 31% remained as PASI 50 responders respectively. Among patients withdrawn from treatment, the rates of loss of the various PASI responses (PASI 50, 75, 90) were generally comparable in all groups regardless of dose. No rebound of psoriasis occurred in patients who were randomized to treatment withdrawal. Among the patients who reached PASI 75 response at weeks 28 and 40 and were re-randomized to maintenance treatment, 82% were PASI 75 responders at 3 years (Week 148). At 5 years (Week 244), 80% of patients (112/140) re-randomized to maintenance treatment were PASI 75 responders.
Table 19 Summary of PASI response from Week 40 through Week 76 in subjects randomized at Week 40 in PHOENIX 1
| Ustekinumab | Ustekinumab | Ustekinumab | ||||||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| 45 mg | 90 mg | Combined | ||||||||||||||||||
| Placebo | q12 wks | Placebo | q12 wks | Placebo | q12 wks | |||||||||||||||
| Patients randomized at Week 40 | 73 | 77 | 87 | 85 | 160 | 162 | ||||||||||||||
| Week 52 N | 73 | 77 | 86 | 85 | 159 | 162 | ||||||||||||||
| ≥ 90% improvement | 27 (37.0%) | 45 (58.4%) | 33 (38.4%) | 60 (70.6%) | 60 (37.7%) | 105 (64.8%) | ||||||||||||||
| ≥ 75% improvement | 47 (64%) | 67 (87.0%) | 53 (61.6%) | 77 (90.6%) | 100 (62.9%) | 144 (88.9%) | ||||||||||||||
| ≥ 50% improvement | 63 (86%) | 75 (97.4%) | 71 (82.6%) | 83 (97.6%) | 134 (84.3%) | 158 (97.5%) | ||||||||||||||
| Week 76 N | 71 | 77 | 85 | 82 | 156 | 159 | ||||||||||||||
| ≥ 90% improvement | 5 (7.0%) | 38 (49.4%) | 4 (4.7%) | 52 (63.4%) | 9 (5.8%) | 90 (56.6%) | ||||||||||||||
| ≥ 75% improvement | 14 (19.7%) | 63 (81.8%) | 15 (17.6%) | 71 (86.6%) | 29 (18.6%) | 134 (84.3%) | ||||||||||||||
| ≥ 50% improvement | 22 (31.0%) | 74 (96.1%) | 27 (31.8%) | 79 (96.3%) | 49 (31.4%) | 153 (96.2%) | ||||||||||||||
Efficacy of retreatment
In PHOENIX 1, after randomized withdrawal from therapy at week 40, patients reinitiated their original ustekinumab treatment regimen after a loss of ≥ 50% of PASI improvement. Retreatment with ustekinumab resulted in 71% of evaluated patients regaining PASI 75 response within 8 weeks after reinitiating therapy and 85% of evaluated patients regaining PASI 75 response within 12 weeks after reinitiating therapy.
Dosing interval adjustment
In PHOENIX 1, Week 28 and Week 40 partial responders and Week 40 nonresponders were adjusted from every-12-week to every-8-week dosing. Approximately 40%-50% of Week 28 partial responders to every-12-week dosing achieved PASI 75 response after adjustment to every-8-week dosing and this proportion of PASI 75 responders was maintained through Week 52. A similar proportion of patients who were PASI 75 responders at Week 28 and subsequently became partial responders or nonresponders at Week 40 achieved PASI 75 response following a dosing interval adjustment to every 8 weeks.
In PHOENIX 2, among patients initially randomized to 90 mg dosing who were partial responders at Week 28, dosing adjustment to every 8 weeks resulted in consistently superior efficacy as compared with continued every 12 weeks dosing: Partial responders randomized to 90 mg every 8 weeks achieved PASI 75 response at more visits between Weeks 40 and 52 than partial responders randomized to continue 90 mg every 12 weeks (p = 0.014), and a higher proportion of subjects achieved a PASI 75 response at Week 52 (68.8% with every 8 weeks dosing versus 33.3% with every 12 weeks dosing; p = 0.004). Among patients initially randomized to 45 mg dosing who were partial responders at Week 28, response rates were not higher among patients in whom dosing was adjusted to every 8 weeks compared with patients who continued every 12 weeks dosing.
Quality of life
In PHOENIX 1 and 2, the mean baseline DLQI scores ranged from 11 to 12. In PHOENIX 1, the mean baseline SF-36 Physical Component ranged from 47-49 and the mean baseline SF-36 Mental Component was approximately 50. Quality of life improved significantly in patients randomized to 45 mg or 90 mg ustekinumab compared with patients randomized to placebo as evaluated by DLQI in PHOENIX 1 and 2 and SF-36 in PHOENIX 1. Quality of life improvements were significant as early as 2 weeks in patients treated with ustekinumab (p<0.001) and these improvements were maintained over time with continued dosing.
In PHOENIX 1, 65% and 71% of patients treated with 45 mg and 90 mg of ustekinumab, respectively, showed a clinically meaningful reduction (5 or more points) in DLQI from baseline at week 12 compared to 18% in placebo group (p<0.001 for both groups compared with placebo). Furthermore, 33% and 34% of patients treated with 45 mg and 90 mg of ustekinumab, respectively, showed a DLQI score of 0 compared to 1% in the placebo group (p<0.001 for both groups compared with placebo), indicating no impairment in QOL from disease or treatment in these patients. In PHOENIX 2, 72% and 77% of patients treated with 45 mg and 90 mg of ustekinumab, respectively, showed a clinically meaningful reduction (5 or more points) in DLQI from baseline at Week 12 compared to 21% in placebo group (p<0.001 for both groups compared with placebo). In addition, 37% and 39% of patients treated with 45 mg and 90 mg of ustekinumab, respectively, showed a DLQI score of 0 compared to 1% in the placebo group (p<0.001 for both groups compared with placebo).
In PHOENIX 1, the median baseline NAPSI score for nail psoriasis was 4.0 and the median number of fingernails involved with psoriasis was 8.0. Nail psoriasis improved significantly in patients randomized to 45 mg or 90 mg ustekinumab compared with patients randomized to placebo when measured by the NAPSI score (p≤0.001). Improvements in physical and mental component summary scores of the SF-36 and in the Itch Visual Analogue Scale (VAS) were also significant in each ustekinumab treatment group compared with placebo (p<0.001). In PHOENIX 2, the Hospital Anxiety and Depression Scale (HADS) and Work Limitations Questionnaire (WLQ) were also significantly improved in each ustekinumab treatment group compared with placebo (p<0.001).
ACCEPT
Significantly greater proportions of subjects treated with ustekinumab 45 mg (67%; p = 0.012) or 90 mg (74%; p < 0.001) were PASI 75 responders at Week 12 compared with the etanercept group (56.8%). PASI 90 response was observed in 36% and 45 % of patients in the ustekinumab 45 mg and 90 mg groups, respectively, compared with 23% of patients receiving etanercept (p<0.001 for each comparison versus etanercept). PASI 100 response was observed in 12% and 21% of patients in the ustekinumab 45 mg and 90 mg groups, respectively, compared to 6% of patients receiving etanercept (Table 20). In addition, a greater proportion of patients in the ustekinumab 45 mg and 90 mg treatment groups achieved a PGA score of “cleared” or “minimal” (65 % and 71 %, respectively) compared with patients in the etanercept treatment group (49 %) (p<0.001 for each comparison versus etanercept).
Table 20 Clinical outcomes at Week 12: ACCEPT
| ACCEPT | ||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|
| ACCEPT | ||||||||||||
Etanercept (50mg twice a week) | Ustekinumab (at week 0 and week 4) | |||||||||||
Etanercept (50mg twice a week) | Ustekinumab (at week 0 and week 4) | |||||||||||
| 45 mg | 90 mg | |||||||||||
| 45 mg | 90 mg | |||||||||||
| Patients randomized | 347 | 209 | 347 | |||||||||
| PASI response | ||||||||||||
| PASI 50 response | 286 (82%) | 181 (87%) | 320 (92%)a | |||||||||
| PASI 75 response | 197 (57%) | 141 (67%)b | 256 (74%)a | |||||||||
| PASI 90 response | 80 (23%) | 76 (36%)a | 155 (45%)a | |||||||||
| PASI 100 response | 22 (6%) | 25 (12%)c | 74 (21%)a | |||||||||
| PGA of Cleared or Minimala | 170 (49%) | 136 (65%)a | 245 (71%)a | |||||||||
| PASI 75 RESPONSE BY WEIGHT | ||||||||||||
| ≤ 100 kg | ||||||||||||
| N | 251 | 151 | 244 | |||||||||
| PASI 75 response | 154 (61%) | 109 (72%) | 189 (77%) | |||||||||
| > 100 kg | ||||||||||||
| N | 96 | 58 | 103 | |||||||||
| PASI 75 response | 43 (45%) | 32 (55%) | 67 (65%) | |||||||||
| PGA of Cleared or Minimal by weight | ||||||||||||
| ≤ 100 kg | ||||||||||||
| N | 251 | 151 | 244 | |||||||||
| PGA response | 131 (52%) | 110 (73%) | 185 (76%) | |||||||||
| > 100 kg | ||||||||||||
| N | 96 | 58 | 103 | |||||||||
| PGA response | 39 (41%) | 26 (45%) | 60 (58%) | |||||||||
a p <0.001 for ustekinumab 45 mg or 90 mg comparison with etanercept.
b p =0.012 for ustekinumab 45 mg comparison with etanercept.
c p =0.020 for ustekinumab 45 mg comparison with etanercept.
Greater proportions of subjects in the ustekinumab 45 mg and 90 mg groups achieved PASI 75 responses when compared with subjects in the etanercept group regardless of a subject’s previous psoriasis medication history.
Pediatric Plaque Psoriasis (6 to 17 years of age)
The safety and efficacy of ustekinumab in pediatric patients with plaque psoriasis was assessed in two multicenter phase 3 studies, CADMUS and CADMUS Jr.
Plaque Psoriasis – Pediatrics (12 to 17 years of age): CADMUS
The efficacy of ustekinumab was studied in 110 pediatric patients 12 to 17 years of age, in a multicenter, Phase 3, randomized, double blind, placebo-controlled study (CADMUS). Two distinct, subcutaneous weight based dosages of ustekinumab were studied. Randomization was stratified by investigational site and baseline weight (≤ 60 kg or > 60 kg).
Patients were randomized to one of four treatment groups (Groups 1, 2, 3a and 3b) at week 0 as follows:
Group 1: ustekinumab half-standard dosage at Weeks 0 and 4 followed by doses every 12 weeks, with the last dose at Week 40.
Group 2: Ustekinumab standard dosage at Weeks 0 and 4 followed doses every 12 weeks, with the last dose at Week 40.
Group 3: Placebo at Weeks 0 and 4. At Weeks 12 and 16, subjects crossed over to receive either ustekinumab half-standard dosage (Group 3a) or standard dosage (Group 3b) followed by doses every 12 weeks, with the last dose at Week 40. The dosage assignment (Group 3a or 3b) following crossover was randomly assigned at week 0, ensuring that the assignment remained double blinded throughout the duration of the study.
All subjects were followed for efficacy through Week 52 and for safety through Week 60.
Adolescent patients with a diagnosis of plaque-type psoriasis for at least 6 months prior to first study agent administration, who had moderate to severe disease, and with PASI ≥ 12, PGA ≥ 3 and BSA involvement of at least 10%, and who were candidates for systemic or phototherapy, were eligible for the study. 43% and 11% of subjects had prior exposure to conventional systemic or biologic therapies respectively.
The primary endpoint was the proportion of patients who achieve a PGA score of cleared (0) or minimal (1) at Week 12. Secondary endpoints included PASI 75 at Week12. Subjects who discontinued study treatment due to lack of efficacy, an adverse event (AE) of psoriasis, or who started a protocol-prohibited medication/therapy prior to Week 12 were considered as non- responders. Subject with missing PGA or PASI scores at Week 12 were considered non- responders. For the Week 12 analysis, any subject receiving moderate to high potency topical steroid preparations were considered as non-responders.
The study population were predominantly Caucasian (89%) and 51% were female. Median body weight was 61.6 kg, 56% had a body weight of between 50 and 70 kg and the median body mass index was 22.15 kg/m2. Median psoriasis duration was 5.29 years with median age at onset of 10 years. The majority of subjects (70.0%) were 15 to 17 years of age, with a median age of 15.5 years. 57% of subjects had ≥ 20% body surface area affected with psoriasis and median PASI score was 18.8 (range 12-51), and 62% and 38% of subjects had PGA scores of moderate and marked/severe respectively.
Table 21 Summary of patient demographics for CADMUS
| Study # | Study design | Dosage, route of administration and duration | Study subjects (n) | Mean age (Range) | Sex |
|---|---|---|---|---|---|
| CNTO1275 PSO3006 (CADMUS) | Double-Blind Placebo- Controlled | Fixed doses (weight based): Placebo (N=37) Placebo → Half-standard dosage (N=19) Placebo → Standard dosage (N=18) Half-standard dosage Weeks 0, 4 then q12w (N=37) Standard dosage Weeks 0, 4 then q12w (N=36) | N=110 | 15,2 (12,17) | M=54 (49%) F=56 (51%) |
Study Results
At Week 12, subjects treated with ustekinumab showed significantly greater improvement in their psoriasis compared with placebo (Table 22).
Table 22 Summary of Primary and Secondary End points at Week 12
| Placebo | Ustekinumab Half Standard Dose | Ustekinumab Standard Dose | |||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|
| n (%) | n (%) | n (%) | |||||||||
| Patients randomized at Week 0 | 37 | 37 | 36 | ||||||||
Number of patients who achieved a PGA score of cleared (0) or minimal (1) | 2 (5.4%) | 25 (67.6%)a | 25 (69.4%) a | ||||||||
| PASI 75 responders | 4 (10.8%) | 29 (78.4%)a | 29 (80.6%) a | ||||||||
a p<0.001 P-values are based on the Cochran-Mantel-Haenszel chi-square test stratified by baseline weight (≤ 60kg, > 60kg). Multiplicity was controlled by sequential testing of endpoints. | |||||||||||
All patients were followed for efficacy for up to 52 weeks following first administration of study agent. The PGA scores of cleared (0) or minimal (1) and PASI 75 responders at Week 52 are summarized in Table 23.
Table 23 Summary of Secondary Endpoints at Week 52
Ustekinumab Half- Standard Dose | Ustekinumab Standard Dose | |
|---|---|---|
| Number of evaluable subjects at Week 52 | n=34 | n=35 |
Number of patients who achieved a PGA score of cleared (0) or minimal (1) | 20 (58.8%) | 20 (57.1%) |
| PASI 75 responders | 23 (67.6%) | 28 (80%) |
Plaque Psoriasis – Pediatrics (6 to 11 years of age): CADMUS Jr
The efficacy of ustekinumab was studied in 44 pediatric patients 6 to 11 years of age with moderate to severe plaque psoriasis in an open label, single-arm, multicenter, Phase 3 study. Patients were treated with the recommended dose of Ustekinumab (n=44) based on body weight measured at each visit (see 4.2 Recommended Dose and Dosage Adjustment) by subcutaneous injection at Weeks 0 and 4 followed by every 12 week (q12w) dosing.
The primary endpoint was the proportion of patients who achieved a PGA score of cleared (0) or minimal (1) at Week 12. Secondary endpoints included PASI 75 at Week 12.
Patients with moderate to severe plaque-type psoriasis with or without psoriatic arthritis (PsA) for at least 6 months prior to first administration of study drug, with widespread lesions defined by PASI ≥ 12, PGA ≥ 3, and involved BSA ≥ 10% and who were candidates for phototherapy or systemic treatment or had psoriasis poorly controlled with topical therapy after an adequate dose and duration of therapy were eligible for the study. Approximately 18% and 5% of patients had prior exposure to conventional systemic or biologic therapies respectively. The study population was predominantly Caucasian (91%) and 61% were female. The median body weight was 33.3 kg, with 91% of patients having a body weight less than 60 kg. The median body mass index was 18.0 kg/m2. The median psoriasis duration was 2.9 years and the median age of onset of disease was 6.0 years. The median percent of BSA affected with psoriasis was 18.0%. The median PASI score was 16.1. The median age was 9.5 years, with 50.0% of subjects < 10 years of age. All ages across the age range (≥ 6 to < 12 year of age) were represented in the study population. The majority of subjects (65.9%) had PGA scores of moderate and 34.1% had a PGA score of marked or severe. The median PASI score was 16.1 and the median Children’s Dermatology Life Quality Index (CDLQI) score was 7.0 (representing a moderate impact of psoriasis on quality of life).
Table 24 Summary of patient demographics for CADMUS Jr
| Study # | Study design | Dosage, route of administration and duration | Study subjects (n) | Mean age (Range) | Sex |
|---|---|---|---|---|---|
| CNTO1275 PSO3013 (CADMUS Jr) | Open-label single arm, multicentre | Fixed doses (weight based): Standard dosage (0.75 mg/kg for patients < 60 kg, 45 mg for patients ≥ 60 kg to ≤ 100 kg and 90 mg for patients > 100 kg) Weeks 0, 4 then q12w (N=36) | N=44 | 8.9 (6,11) | M=17 (39%) F=27 (61%) |
Study Results
At Week 12, patients treated with ustekinumab showed clinically meaningful improvements in their psoriasis. All patients were followed for efficacy for up to 52 weeks following first administration ustekinumab. The PGA scores and PASI 75 responders at Week 12 and 52 are summarized in Table 25. Efficacy measured by PGA score of 0 or 1 was observed as early as the first post-baseline visit at Week 4 and increased through Week 16 and then remained relatively stable through Week 52. Improvements in PGA and PASI were maintained through Week 52.
Table 25 Summary of Primary and Secondary End-points at Week 12 and 52: CADMUS Jr. (Age 6-11)
Ustekinumab Week 12 | Ustekinumab Week 52 | |
|---|---|---|
| N (%) | N (%) | |
| Patients enrolled at Week 0 | 44 | 41 |
Number of patients who achieved a PGA score of cleared (0) or minimal (1) | 34 (77.3%) | 31 (75.6%) |
| PGA of cleared (0) | 17 (38.6%) | 23 (56.1%) |
| PASI 75 responders | 37 (84.1%) | 36 (87.8%) |
Psoriatic Arthritis
The safety and efficacy of ustekinumab was assessed in two multicenter, randomized, double-blind, placebo-controlled, phase 3 studies, PSUMMIT I and PSUMMIT II, in patients with active psoriatic arthritis. Patients were randomized to receive treatment with either ustekinumab 45 mg, 90 mg, or placebo subcutaneous injections at Weeks 0 and 4 followed by every 12 week (q12w) dosing. The primary endpoint in these studies was the reduction in the signs and symptoms of psoriatic arthritis (PsA) as measured by the percentage of ACR 20 responders at Week 24. Secondary endpoints included change from baseline in Disability Index of the Health Assessment Questionnaire (HAQ-DI), PASI 75, ACR 50, ACR 70 and change from baseline in total radiographic scores of the hands and feet at Week 24. Efficacy data were collected and analyzed through Week 52.
These studies included 927 adult patients (≥18 years) who had active psoriatic arthritis (≥5 swollen joints and ≥5 tender joints, despite disease modifying antirheumatic (DMARD) and/or nonsteroidal anti-inflammatory (NSAID) therapy. Methotrexate (MTX) use was allowed during the studies but was not mandatory. Approximately 50% of patients continued on stable doses of MTX (≤25 mg/week). In PSUMMIT I and PSUMMIT II, 80% and 86% of the patients, respectively, had been previously treated with DMARDs.
In PSUMMIT I patients, who had been previously treated with anti-TNFα therapy, prior to the first study dose, were excluded. In PSUMMIT II, the majority of patients (58%, n=180) had been previously treated with one or more an anti-TNFα agent(s) for at least 8 weeks (14 weeks with infliximab) or had discontinued anti-TNFα for intolerance at any time. Among the patients who had been previously treated with an anti-TNFα agent, over 70% had discontinued their anti-TNFα treatment for lack of efficacy or intolerance.
Patients with each subtype of psoriatic arthritis were enrolled, including polyarticular arthritis with no evidence of rheumatoid nodules (39%, N=362), spondylitis with peripheral arthritis (28%, N=255), asymmetric peripheral arthritis (21%, N=193), distal interphalangeal (DIP) arthritis (12%, N=112) and arthritis mutilans (0.5%, N=5). Over 70% and 40% of the patients in both studies had enthesitis and dactylitis at baseline, respectively.
Table 26 Summary of patient demographics in PSUMMIT I and PSUMMIT II
| Study # | Study design | Dosage, route of administration and duration | Study subjects (n) | Mean age (Range) | Sex |
|---|---|---|---|---|---|
| Study # | Study design | Dosage, route of administration and duration | Study subjects (n) | Mean age (Range) | Sex |
| CNTO1275 PSA3001 (PSUMMIT I) | Double-Blind Placebo- Controlled | Placebo SC (n=206): Placebo SC at Weeks 0, 4,16, and 20 Placebo→45 mg SC at Weeks 24 and 28 followed by q12w dosing through Week 88 45 mg SC (n=205): 45 mg SC at Weeks 0 and 4 followed by q12w dosing through Week 88 90 mg SC (n=204): 90 mg SC at Weeks 0 and 4 followed by q12w dosing through Week 88 | 615 | 47.1 (18, 81) | M=330 F=285 |
| CNTO1275 PSA3002 (PSUMMIT II) | Double-Blind Placebo- Controlled | Placebo SC (n=104): Placebo SC at Weeks 0, 4, 16, and 20 45 mg SC at Weeks 24 and 28 followed by q12w dosing through Week 40 45 mg SC (n=103): 45 mg SC at Weeks 0 and 4 followed by q12w dosing through Week 40 90 mg SC (n=105): 90 mg SC at Weeks 0 and | 312 | 48.0 (19, 75) | M=148 F=164 |
| 4 followed by q12w dosing through Week 40 | |||||
Study Results
Reduction in Signs and Symptoms
In both studies, a significantly greater proportion of patients achieved ACR 20 and ACR 50 responses at Week 24 in the ustekinumab 45 mg and 90 mg groups compared to placebo (Table 27). In PSUMMIT I, a significantly greater proportion of patients and in PSUMMIT II, a numerically greater proportion of patients (p=NS) achieved ACR 70 responses in the ustekinumab 45 mg and 90 mg groups compared to placebo (Table 27).
Table 27 Number of patients who achieved ACR 20, ACR 50 and ACR 70 at Week 24
| PSUMMIT I | PSUMMIT II | ||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
Placebo (N=206) | Ustekinumab | Placebo (N= 104) | Ustekinumab | ||||||||||||
45 mg (N= 205) | 90 mg (N= 204) | 45 mg (N= 103) | 90 mg (N= 105) | ||||||||||||
| ACR 20 | 47 (23%) | 87 (42%)a | 101 (50%)a | 21 (20%) | 45 (44%)a | 46 (44%)a | |||||||||
| ACR 50 | 18 (9%) | 51 (25%)a | 57 (28%)a | 7 (7%) | 18 (17%)b | 24 (23%)a | |||||||||
| ACR 70 | 5 (2%) | 25 (12%)a | 29 (14%)a | 3 (3%) | 7 (7%)c | 9 (9%)c | |||||||||
a p<0.001, b p<0.05, c p= NS
An ACR 20 response (Felson et al, 1995) was defined as:
- 1. ≥ 20% improvement in swollen joint count (66 joints) and tender joint count (68 joints); and
- 2.
≥ 20 % improvement in ≥3 of the following 5 assessments:
- Patient’s assessment of pain [Visual Analog Scale (VAS)]
- Patient’s global assessment of disease activity (VAS)
- Physician’s global assessment of disease activity (VAS)
- Patient’s assessment of physical function as measured by the HAQ-DI
- CRP
ACR 50 or ACR 70 are similarly defined.
The time course for ACR 20 response rates during the first 24 weeks in both studies for patients receiving ustekinumab or placebo are summarized in Figure 2. During the controlled phase of the studies, ACR 20 responses showed improvement at the first assessment (Week 4) and maximum responses were achieved at Week 20 or 24. ACR 20, 50 and 70 responses continued to improve or were maintained through Week 52.
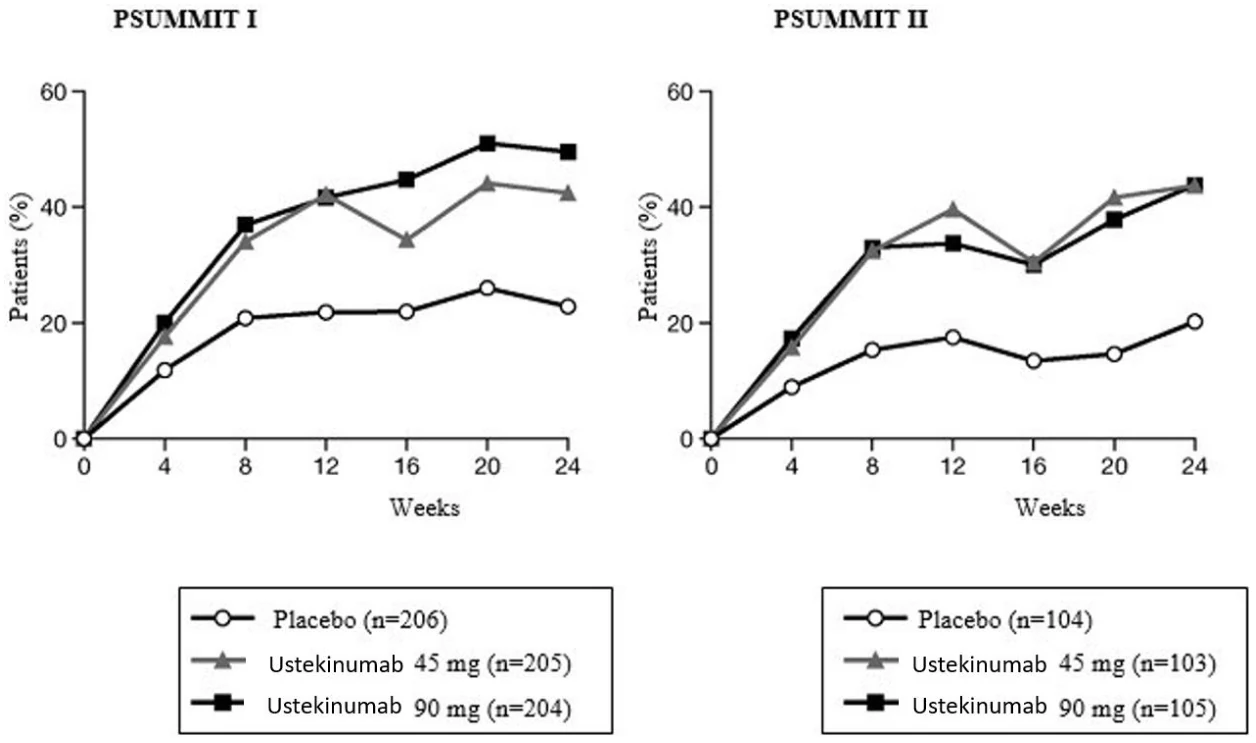
Figure 2 Percent of patients achieving ACR 20 response through Week 24
In PSUMMIT I, of 205 subjects randomized to ustekinumab 45 mg, 153 continued the same dose and were available for evaluation at Week 52. Among those, ACR 20, 50 and 70 responses were achieved by 99 (64.7%), 57 (37.3%) and 34 (22.2%) subjects respectively. Of 204 subjects randomized to ustekinumab 90 mg, 185 were available for evaluation at Week 52. Among those, ACR 20, 50 and 70 responses were achieved by 120 (64.9%), 74 (40%) and 41 (22.2%) subjects respectively.
In PSUMMIT II, of 103 subjects randomized to ustekinumab 45 mg, 68 continued the same dose and were available for evaluation at Week 52. Among those, ACR 20, 50, and 70 responses were achieved by 41 (60.3%), 23 (33.8%) and 11 (16.2%) subjects respectively. Of 105 subjects randomized to ustekinumab 90 mg, 83 were available for evaluation at Week 52. Among those, ACR 20, 50 and 70 responses were achieved by 49 (59%), 26 (31.3%) and 17 (20.5%) subjects respectively.
Additionally, within each weight group (≤100 kg and >100 kg), ACR 20, ACR 50 and ACR 70 responses were consistently higher in the ustekinumab 45 mg and 90 mg groups than in the placebo group (Table 28).
Table 28 Number of patients who achieved ACR 20, ACR 50 and ACR 70 responses by weight at Week 24
| PSUMMIT I | PSUMMIT II | ||||||||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| PSUMMIT I | PSUMMIT II | ||||||||||||||||||||
Placebo (N=206) | Ustekinumab | Placebo (N=104) | Ustekinumab | ||||||||||||||||||
Placebo (N=206) | Ustekinumab | Placebo (N=104) | Ustekinumab | ||||||||||||||||||
45 mg (N=205) | 90 mg (N=204) | 45 mg (N=103) | 90 mg (N=105) | ||||||||||||||||||
45 mg (N=205) | 90 mg (N=204) | 45 mg (N=103) | 90 mg (N=105) | ||||||||||||||||||
| Patients randomized with weight ≤100 kg | |||||||||||||||||||||
| at baseline | 154 | 153 | 154 | 74 | 74 | 73 | |||||||||||||||
| ACR 20 | 39 (25%) | 67 (44%) | 78 (51%) | 17 (23%) | 32 (43%) | 34 (47%) | |||||||||||||||
| ACR 50 | 14 (9%) | 38 (25%) | 48 (31%) | 6 (8%) | 15 (20%) | 21 (29%) | |||||||||||||||
| ACR 70 | 5 (3%) | 20 (13%) | 26 (17%) | 3 (4%) | 6 (8%) | 8 (11%) | |||||||||||||||
| Patients randomized with weight >100 kg at baseline | 52 | 52 | 50 | 30 | 29 | 31 | |||||||||||||||
| ACR 20 | 8 (15%) | 20 (38%) | 23 (46%) | 4 (13%) | 13 (45%) | 12 (39%) | |||||||||||||||
| ACR 50 | 4 (8%) | 13 (25%) | 9 (18%) | 1 (3%) | 3 (10%) | 3 (10%) | |||||||||||||||
| ACR 70 | 0 | 5 (10%) | 3 (6%) | 0 | 1 (3%) | 1 (3%) | |||||||||||||||
Ustekinumab treatment resulted in significantly greater improvement compared with placebo for each ACR component at week 24 (Table 29).
Table 29 Median percent improvement from baseline in ACR components at Week 24
| PSUMMIT I | PSUMMIT II | |||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
Placebo (N=206) | Ustekinumab | Placebo (N=104) | Ustekinumab | |||||||||||
45 mg (N=205) | 90 mg (N=204) | 45 mg (N=103) | 90 mg (N=105) | |||||||||||
| Number of swollen jointsd | 21.54 | 58.82a | 60.00a | 0.00 | 52.94b | 50.00c | ||||||||
| Number of tender jointse | 13.61 | 45.45a | 51.51a | 0.00 | 33.33a | 35.00c | ||||||||
Patient’s assessment of Painf | 0.00 | 31.33a | 42.58a | 0.00 | 24.19a | 24.29a | ||||||||
| Patient global assessmentf | 4.11 | 32.84a | 42.44a | 0.00 | 21.25a | 22.54a | ||||||||
Physician global Assessmentf | 17.64 | 48.39a | 55.91a | 0.83 | 36.67a | 36.11a | ||||||||
| Disability index (HAQ-DI)g | 0.00 | 22.22a | 32.46a | 0.00 | 12.50a | 14.29a | ||||||||
| CRP (mg/dL)h | 0.00 | 38.56a | 48.30a | 0.00 | 25.61c | 33.69a | ||||||||
a p<0.001
b p<0.05
c p<0.01
d Number of swollen joints counted (0-66)
e Number of tender joints counted (0-68)
f Visual analogue scale; 0=best, 10=worst.
g Disability Index of the Health Assessment Questionnaire; 0=best, 3=worst, measures the patient’s ability to perform the following: dress/groom, arise, eat, walk, reach, grip, maintain hygiene, and maintain daily activity.
h CRP: (Normal Range 0.0-1.0 mg/dL)
In PSUMMIT I and PSUMMIT II, the proportion of subjects with good or moderate Disease Activity Index Score 28 using C-reactive protein (DAS28-CRP) responses and the proportion of subjects in DAS28 remission were greater in both ustekinumab-treated groups compared to placebo at Week 24. DAS28-CRP responses were maintained through Week 52.
Methotrexate Use
The proportion of patients achieving ACR responses were consistently greater in patients treated with ustekinumab than those treated with placebo regardless of concomitant MTX use. Responses observed in the ustekinumab groups were similar in patients receiving or not receiving concomitant MTX. ACR responses were maintained through Week 52 (Table 30).
Table 30 Summary of patients achieving ACR 20, ACR 50 and ACR 70 responses through Week 24 by methotrexate usage
| PSUMMIT I | ||||||||||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Receiving MTX at baseline | Not receiving MTX at baseline | |||||||||||||||||||||
Placebo (N=206) | Ustekinumab | Placebo (N=206) | Ustekinumab | |||||||||||||||||||
45 mg (N=205) | 90 mg (N=204) | 45 mg (N=205) | 90 mg (N=204) | |||||||||||||||||||
| Patients randomized | 96 | 99 | 101 | 110 | 106 | 103 | ||||||||||||||||
| ACR 20 | 25 (26%) | 43 (43%) | 46 (46%) | 22 (20%) | 44 (42%) | 55 (53%) | ||||||||||||||||
| ACR 50 | 8 (8%) | 23 (23%) | 27 (27%) | 10 (9%) | 28 (26%) | 30 (29%) | ||||||||||||||||
| ACR 70 | 2 (2%) | 11 (11%) | 13 (13%) | 3 (3%) | 14 (13%) | 16 (16%) | ||||||||||||||||
| PSUMMIT II | ||||||||||||||||||||||
| Receiving MTX at baseline | Not receiving MTX at baseline | |||||||||||||||||||||
Placebo (N=104) | Ustekinumab | Placebo (N=104) | Ustekinumab | |||||||||||||||||||
45 mg (N=103) | 90 mg (N=105) | 45 mg (N=103) | 90 mg (N=105) | |||||||||||||||||||
| Patients randomized | 49 | 54 | 52 | 55 | 49 | 53 | ||||||||||||||||
| ACR 20 | 14 (29%) | 27 (50%) | 21 (40%) | 7 (13%) | 18 (37%) | 25 (47%) | ||||||||||||||||
| ACR 50 | 4 (8%) | 10 (19%) | 12 (23%) | 3 (5%) | 8 (16%) | 12 (23%) | ||||||||||||||||
| ACR 70 | 2 (4%) | 4 (7%) | 3 (6%) | 1 (2%) | 3 (6%) | 6 (11%) | ||||||||||||||||
Prior Anti-TNFα therapy
PSUMMIT II evaluated 180 patients who were previously treated with one or more anti-TNFα agents for at least 8 weeks (14 weeks with infliximab) or had documented intolerance of anti-TNFα therapy at any time in the past.
Among patients previously treated with anti-TNFα agents, a greater proportion of ustekinumab-treated patients in both the 45 mg and 90 mg groups achieved an ACR 20 response at Week 24 compared to placebo (37% and 34% vs 15%). ACR 20 response was generally maintained through Week 52.
Enthesitis and Dactylitis
For patients with enthesitis and/or dactylitis at baseline, in PSUMMIT I, greater improvement in enthesitis and dactylitis score was observed in the ustekinumab 45 mg and 90 mg groups compared to placebo. For enthesitis, the median improvement was 43% and 50% for each dose group respectively, compared to 0% for placebo. For dactylitis, the median improvement was 75% and 71% for each dose group respectively, compared to 0% for placebo. In PSUMMIT II, a greater improvement was observed in enthesitis score in both doses and in dactylitis score in the 90 mg group compared with the placebo group. In both studies, improvement in enthesitis score and dactylitis score were maintained at Week 52.
Psoriasis Skin Response
In PSUMMIT I and PSUMMIT II, the proportion of patients with psoriasis involvement of ≥3% BSA at baseline who achieved a ≥75% improvement in the PASI assessment at Week 24 was significantly greater in the ustekinumab 45 mg and 90 mg groups compared with the placebo group (Table 31). In both studies the proportion of patients achieving the PASI 75 response was maintained through Week 52.
Table 31 Number of patients who achieved PASI 75, PASI 90 and PASI 100 responses at Week 24
| PSUMMIT I | PSUMMIT II | |||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
Placebo (N=206) | Ustekinumaba | Placebo (N= 104) | Ustekinumaba | |||||||||||||
45 mg (N=205) | 90 mg (N=204) | 45 mg (N=103) | 90 mg (N=105) | |||||||||||||
Patients with ≥ 3% BSA psoriasis skin involvement at baseline | 146 | 145 | 149 | 80 | 80 | 81 | ||||||||||
| PASI 75 | 16 (11%) | 83 (57%) | 93 (62%) | 4 (5%) | 41 (51%) | 45 (56%) | ||||||||||
| PASI 90 | 4 (3%) | 60 (41%) | 65 (44%) | 3 (4%) | 24 (30%) | 36 (44%) | ||||||||||
| PASI 100 | 2 (1%) | 29 (20%) | 41 (28%) | 1 (1%) | 13 (16%) | 17 (21%) | ||||||||||
ap<0.001 for 45 mg or 90 mg comparison with placebo.
Additionally, within each weight group (≤ 100 kg and > 100 kg), PASI 75, 90 and 100 responses were consistently higher in the ustekinumab 45 mg and 90 mg groups than in the placebo group. In both studies, the proportion of patients who achieved a PASI 75 response at Week 24 was consistently higher in ustekinumab 45 mg and 90 mg groups compared with placebo regardless of concomitant MTX use. PASI 75 responses were maintained through Week 52.
Radiographic Response
Structural damage in both hands and feet was assessed by readers unaware of treatment group and order of visits, and expressed as change in total van der Heijde-Sharp score (vdH-S score), modified for PsA by addition of hand distal interphalangeal (DIP) joints, compared to baseline. A pre-specified major secondary endpoint based on the integrated analysis combining data from 927 subjects in both PSUMMIT I and PSUMMIT II was performed. At Week 24, based on this integrated analysis, patients treated with either ustekinumab 45 mg (n=308, mean change in total vdH-S score=0.40) or 90 mg (n=309, mean change=0.39) demonstrated significantly less progression of structural damage compared to placebo (n=310, mean change=0.97), p<0.05 and p<0.001 for the 45 mg and 90 mg groups, respectively. This effect was demonstrated irrespective of concomitant MTX use, and was maintained through Week 52.
Similar results were seen in PSUMMIT I for patients treated with either ustekinumab 45 mg (n=205, mean change=0.28) or 90 mg (n=204, mean change=0.17) compared to placebo (n=206, mean change=1.20). In PSUMMIT II, the mean change was 0.66 for 45 mg (n=103), 0.81 for 90 mg (n=105) and 0.51 for placebo (n=104).
Physical Function and Health-Related Quality of Life
In PSUMMIT I and PSUMMIT II, physical function and health-related quality of life were assessed using the Disability Index of the Health Assessment Questionnaire (HAQ-DI) and the SF-36 health survey.
Patients treated with ustekinumab 45 mg and 90 mg showed significant improvement in physical function as assessed by the HAQ-DI at Week 24 as compared to placebo in both PSUMMIT I and PSUMMIT II. The proportion of patients achieving a clinically meaningful ≥ 0.3 improvement in HAQ-DI score from baseline at Week 24 was also significantly greater in the ustekinumab groups when compared with placebo. Improvement was observed at the first assessment (Week 4), reached maximum at Week 12 and was maintained through Week 24. In both studies the improvement in HAQ-DI at Week 24 was consistently greater in the ustekinumab 45 mg and 90 mg groups compared with placebo regardless of concomitant MTX use. Improvement in HAQ-DI score from baseline was maintained at Week 52 (Table 32).
Table 32 Improvement in physical function as measured by HAQ-DI at Week 24
| PSUMMIT I | PSUMMIT II | ||||||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
Placebo (N=206) | Ustekinumab | Placebo (N=104) | Ustekinumab | ||||||||||||||||
45 mg (N=205) | 90 mg (N=204) | 45 mg (N=103) | 90 mg (N=105) | ||||||||||||||||
| HAQ-DI Baseline Score | |||||||||||||||||||
| N | 204 | 205 | 204 | 104 | 103 | 104 | |||||||||||||
| Mean (SD) | 1.24 (0.647) | 1.22 (0.610) | 1.22 (0.634) | 1.25 (0.723) | 1.34 (0.704) | 1.29 (0.666) | |||||||||||||
| Median | 1.25 | 1.25 | 1.25 | 1.25 | 1.38 | 1.25 | |||||||||||||
| Improvement in HAQ-DI | |||||||||||||||||||
| N c | 206 | 205 | 204 | 104 | 103 | 105 | |||||||||||||
| Mean (SD) | 0.10 (0.390) | 0.31 (0.521) | 0.40 (0.514) | 0.03 (0.380) | 0.21 (0.461) | 0.22 (0.436) | |||||||||||||
| MEDIAN | 0.00 | 0.25 a | 0.25 a | 0.00 | 0.13 b | 0.25 a | |||||||||||||
| HAQ-DI RESPONDERS* | 58 (28%) | 98 (48%) a | 97 (48%) a | 17 (16%) | 35 (34%) b | 40 (38%) a | |||||||||||||
a p<0.001
b p<0.01
c Includes all randomized subjects
* achieving a ≥ 0.3 improvement from baseline
In PSUMMIT I, of 205 subjects randomized to ustekinumab 45 mg, 153 continued the same dose and were available for evaluation at Week 52. Among those, the HAQ-DI response was achieved by 83 (54.2%) subjects. Of 204 subjects randomized to ustekinumab 90 mg, 185 were available for evaluation at Week 52. Among those, HAQ-DI response was achieved by 102 (55.1%) subjects.
In PSUMMIT II, of 103 subjects randomized to ustekinumab 45 mg, 68 continued the same dose and were available for evaluation at Week 52. Among those, the HAQ-DI response was achieved by 29 (42.6%) subjects. Of 105 subjects randomized to ustekinumab 90 mg, 83 were available for evaluation at Week 52. Among those, HAQ-DI response was achieved by 44 (53%) subjects.
In both PSUMMIT I and PSUMMIT II, at Week 24, the change from baseline in the SF-36 physical component summary (PCS) scores was significantly greater in the ustekinumab 45 mg and 90 mg groups compared with the placebo group. In both studies, the change from baseline in the SF-36 mental component summary (MCS) scores at Week 24 was greater in both ustekinumab groups compared with the placebo group. In both studies, the change from baseline in the SF- 36 PCS and MCS scores was maintained at Week 52.
The DLQI was assessed by comparing the change in DLQI scores from baseline for those patients with ≥3% BSA at baseline. In both studies at Week 24, there was a greater improvement from baseline in DLQI scores in both the ustekinumab 45 mg and 90 mg groups as compared with placebo and the improvement was maintained at Week 52.
In PSUMMIT II, the improvement from baseline in Functional Assessment of Chronic Illness Therapy-Fatigue (FACIT-F) scores at Week 24 was greater in the ustekinumab 45 mg and 90 mg groups compared with the placebo group. Similarly, the percentage of patients with clinically meaningful improvement in fatigue from baseline (4 points in FACIT-F) was greater in both dose groups compared with the placebo group. The change from baseline in the FACIT-F scores was maintained at Week 52.
Crohn’s Disease
The safety and efficacy of ustekinumab were evaluated in three randomized, double-blind, placebo-controlled clinical trials in adult patients with moderately to severely active Crohn’s disease (Crohn’s Disease Activity Index [CDAI] score of 220 to 450). The clinical development program consisted of two 8-week IV induction studies (UNITI-1 and UNITI-2) followed by a 44-week subcutaneous randomized withdrawal maintenance study (IM-UNITI) representing 52 weeks of therapy (Table 33).
Table 33 Summary of controlled clinical trials supporting safety and efficacy in patients with CD
| Study # | Study Design | Dosage: Route of Administration and Duration | Study Subjects (n) | Median Age (Range) | Sex |
|---|---|---|---|---|---|
UNITI-1 (Induction) | Multicentre, double-blinded, randomized, placebo- controlled | IV administration at Week 0 | 741 | 36 (18, 71) | M: 317, 43 F: 424, 57 |
| Placebo | 247 | ||||
| Ustekinumab I.V. 130 mg | 245 | ||||
| Ustekinumab I.V. ~6 mg/kga | 249 | ||||
UNITI-2 (Induction) | Multicentre, double-blinded, randomized, placebo- controlled | IV administration at Week 0 | 628 | 37.0 (18, 77) | M:293, 47 F:335, 53 |
| Placebo | 210 | ||||
| Ustekinumab I.V. 130 mg | 209 | ||||
| Ustekinumab I.V. ~6 mg/kga | 209 | ||||
IM-UNITI (Maintenance) | Multicentre, double-blinded, placebo- controlled randomized- withdrawal | SC administration at Week 0b, and then q8w or q12w for 44 weeks | 397 | 36.0 (18, 75) | M:173, 44 F: 224, 56 |
| placebo | 133 | ||||
| Ustekinumab 90 mg q8w | 132 | ||||
| Ustekinumab 90 mg q12w | 132 | ||||
a tiered weight-based dose approximating 6 mg/kg (see 4 DOSAGE AND ADMINISTRATION)
b 8 weeks following the intravenous dose of ustekinumab I.V.
Induction Studies: UNITI-1 and UNITI-2
UNITI-1 and UNITI-2 studies included 1409 (UNITI-1, n=769; UNITI-2 n=640) patients. Of these subjects, 1368 (UNITI-1, n=741; UNITI-2, n=627) patients are included in the final efficacy analysis. In both studies, patients were permitted to concomitantly receive oral 5-ASA compounds, immunomodulators, corticosteroids, and/or antibiotics. Patients were randomized to receive a single IV administration of either 130 mg ustekinumab I.V., or approximately 6 mg/kg ustekinumab I.V. designed as a tiered dose based on patient body weight or placebo at Week 0.
The primary endpoint for UNITI-1 and UNITI-2 was clinical response defined as a reduction in CDAI score of ≥ 100 points or CDAI score < 150 (for subjects with a baseline CDAI score of ≥ 220 to ≤ 248) at Week 6. Secondary endpoints included clinical remission (CDAI score of < 150 points) at Week 8, clinical response at Week 8, 70-point response at Week 3, and 70-point response at Week 6. Efficacy data were collected and analyzed through Week 8 for both studies.
In UNITI-1, patients had failed or were intolerant to prior anti-TNFα therapy. At baseline, patients had a median (min, max) baseline CDAI score of 317 (198, 515), and approximately 46% (n=340) patients were receiving corticosteroids (including budesonide) and 31.4% of patients were receiving immunomodulators. Approximately 48% had failed 1 prior anti-TNFα therapy and 52% had failed 2 or 3 prior anti-TNFα therapies (40.8% and 10.4%, respectively). In this study, 29.1% patients had an inadequate initial response (primary non-responders), 69.4% responded but subsequently lost response (secondary non-responders), and 36.4% were intolerant to anti-TNFα therapies.
Patients in UNITI-2 had failed at least one conventional therapy (corticosteroids or immunomodulators) and were either anti-TNFα naïve (68.6%) or had previously received but not failed anti-TNFα therapy (31.4%). At baseline, patients had a median (min, max) baseline CDAI score of 292.5 (198, 608), and approximately 40% patients were receiving corticosteroids (including budesonide) and 35% patients were receiving immunomodulators.
Maintenance: IM-UNITI
The maintenance study (IM-UNITI) evaluated 388 patients who achieved clinical response (≥ 100 point reduction in CDAI score or CDAI score < 150 [patients with a baseline CDAI score of ≥ 220 to ≤ 248]) at Week 8 of induction with ustekinumab I.V. in UNITI-1 or UNITI-2 out of 397 patients who were randomized into the study. Of those, approximately 60% of the patients entered the maintenance study in remission. Patients were randomized to receive a subcutaneous maintenance regimen of either 90 mg ustekinumab every 8 weeks, 90 mg ustekinumab every 12 weeks or placebo for an additional 44 weeks. Patients who completed the maintenance study through Week 44 were eligible to continue treatment through Week 272. An efficacy analysis was performed at Week 92 of the extension study.
Concomitant doses of oral 5-ASA compounds, immunomodulators, corticosteroids and antibiotics were permitted. At baseline, 45.6% of patients were receiving corticosteroids and 35% of patients were receiving immunomodulators. Corticosteroids were tapered at the start of the maintenance trial and during the trial in patients in clinical response. The primary endpoint was clinical remission (CDAI < 150) at Week 44 of maintenance. Secondary endpoints assessed at Week 44 of maintenance included clinical response, clinical remission among ustekinumab treated patients in clinical remission after induction, corticosteroid-free remission, and clinical remission in the subset of patients who were refractory or intolerant to anti-TNFα treatment. Other endpoints and planned analyses included evaluations for inflammatory markers, such as C-reactive protein and fecal calprotectin, fistula response, and patient reported outcomes.
Study Results
Induction of Response and Remission
In these induction studies, efficacy was higher and better sustained in the tiered dose group compared to the 130 mg dose group, and tiered dosing is therefore the recommended IV induction dose. In both UNITI-1 and UNITI-2, a significantly greater proportion of patients were in clinical response at Week 6 and remission at Week 8 in the group treated with ustekinumab I.V. compared to placebo (Table 34, Figure 3). Clinical response and remission were observed as early as Week 3 in ustekinumab I.V. treated patients and continued to improve through Week 8 (Figure 3).
Table 34 Induction of Clinical Response and Remission in UNITI-1* and UNITI 2**
| UNITI-1 | UNITI-2 | |||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
Placebo N=247 | Ustekinumab I.V. N=249 | Treatment difference, 95% CI and p-value | Placebo N=209 | Ustekinumab I.V. N=209 | Treatment difference, 95% CI and p-value | |||||||||
Clinical Response Week 6c | 53 (21.5%) | 84 (33.7%) | 12% | 60 (28.7%) | 116 (55.5%) | 27% | ||||||||
| (4%, 20%) | (18%, 36%) | |||||||||||||
| p = 0.003ab | p < 0.001ab | |||||||||||||
Clinical Remission, Week 8c | 18 (7.3%) | 52 (20.9%) | 14% | 41 (19.6%) | 84 (40.2%) | 21% | ||||||||
| (8%, 20%) | (12%, 29%) | |||||||||||||
| p < 0.001ab | p < 0.001ab | |||||||||||||
Clinical Response Week 8c | 50 (20.2%) | 94 (37.8%) | 18% | 67 (32.1%) | 121 (57.9%) | 26% | ||||||||
| (10%, 25%) | (17%, 35%) | |||||||||||||
| p < 0.001ab | p < 0.001ab | |||||||||||||
70 Point Response, Week 6c | 75 (30.4%) | 109 (43.8%) | 13% | 81 (38.8%) | 135 (64.6%) | 19% | ||||||||
| (5%, 22%) | (10%, 28%) | |||||||||||||
| p = 0.002ab | p < 0.001ab | |||||||||||||
70 Point Response, Week 3c | 67 (27.1%) | 101 (40.6%) | 13% | 66 (31.6%) | 106 (50.7%) | 26% | ||||||||
| (5%, 22%) | (17%, 35%) | |||||||||||||
| p < 0.001ab | p < 0.001ab | |||||||||||||
Clinical remission is defined as CDAI score < 150; Clinical response is defined as reduction in CDAI score by at least 100 points or being in clinical remission (for subjects with a baseline CDAI score of
≥ 220 to ≤ 248).
70 point response is defined as reduction in CDAI score by at least 70 points.
* Patients who failed or were intolerant to anti-TNF α agents.
** Patients who failed or were intolerant to corticosteroids or immunomodulators. Patients may have previously received but not failed an anti-TNFα agent or were never treated with an anti-TNFα agent.
a Based on a Cochran-Mantel-Haenszel chi-square test, stratified by study region (Asia, Eastern Europe, or Rest of World), CDAI score (≤ 300 or > 300), and initial response to TNF antagonist therapy (yes or no; CRD3001 only)
b To control the overall Type I error rate at the 0.05 significance level, the endpoints were tested in the hierarchical order presented in this table
c Subjects who had a prohibited Crohn's disease-related surgery, had prohibited concomitant medication changes, or had insufficient data to determine response and remission status were considered to not be in response or remission.
| Placebo | Ustekinumab I.V., 6 mg/kg |
|---|
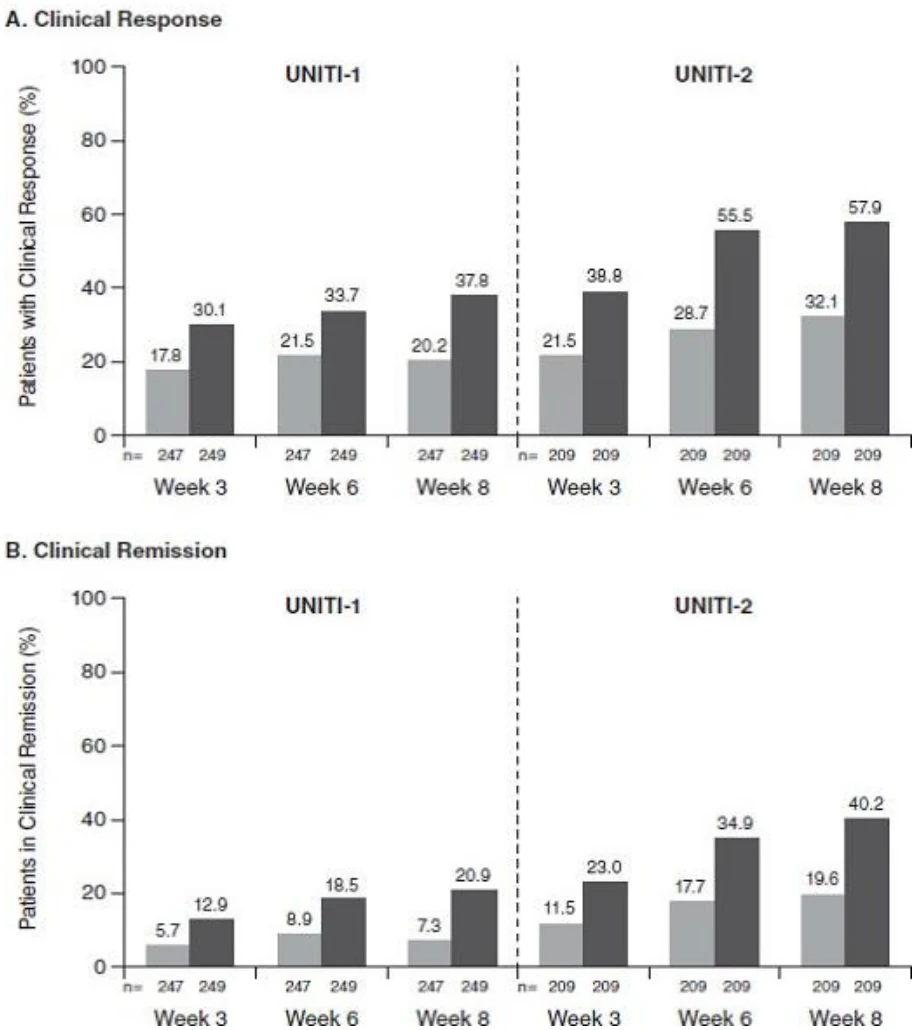
Figure 3 Proportion of Ustekinumab I.V. treated patients in clinical response (A) and remission (B) through Week 8 in UNITI-1 and UNITI-2 studies
Anti-TNFα Naïve group
UNITI-2 evaluated 246 patients (69% of the UNITI-2 population) who have had an inadequate response, loss of response or were intolerant to conventional therapy but have never been exposed to anti-TNF α agents. Among this subgroup of patients, 56.3% of ustekinumab I.V.-treated patients and 32.6% of patients treated with placebo achieved a clinical response at Week 6.
Maintenance of Response and Remission
In IM-UNITI, significantly higher proportions of patients maintained clinical remission and response in the ustekinumab treated groups as compared to placebo at Week 44 of maintenance (Table 35).
Table 35 Maintenance of Clinical Response and Remission in IM-UNITI (Week 44; 52 weeks from initiation of the induction dose)
Placebo* N=131† | 90 mg Ustekinumab every 12 weeks N=129† | Treatment difference, 95% CI and p-value | 90 mg Ustekinumab every 8 weeks N=128† | Treatment difference, 95% CI and p-value | |
|---|---|---|---|---|---|
Clinical Remissionc n (%) | 47 (35.9%) | 63 (48.8%) | 13% (1%, 25%) p = 0.040ab | 68 (53.1%) | 17% (5%, 29%) p = 0.005ab |
Clinical Responsec n (%) | 58 (44.4%) | 75 (58.1%) | 14% (2%, 26%) p = 0.033ab | 76 (59.4%) | 15% (3%, 27%) p = 0.018ab |
Clinical Remission in patients in remission at the start of maintenance therapyc n/N (%) | 36/79 (45.6%) | 44/78 (56.4%) | 10.8% (-5%, 26%) p = 0.189 abd | 52/78 (66.7%) | 21% (6%, 36%) p = 0.007ab |
Clinical remission is defined as CDAI score < 150; Clinical response is defined as reduction in CDAI of at least 100 points or being in clinical remission (for subjects with a baseline CDAI score of ≥ 220 to
≤ 248)
* The placebo group consisted of patients who were in response to ustekinumab and were randomized to receive placebo at the start of maintenance therapy.
† Patients who achieved a clinical response to ustekinumab I.V. at start of maintenance therapy a Based on a Cochran-Mantel-Haenszel chi-square test, stratified by clinical remission status at Week 0 (yes or no), ustekinumab I.V. induction dose (130 mg or tiered doses approximating ustekinumab 6 mg/kg), and induction study (UNITI-1 or UNITI-2)
b To control the overall Type I error rate at the 0.05 significance level, the endpoints were tested in the hierarchical order presented in this table for the q8w dosing regimen and then in the same hierarchical order for the q12w regimen.
c Subjects who had a prohibited Crohn's disease-related surgery, had a loss of response, had prohibited concomitant medication changes, discontinued study agent due to lack of efficacy or due to an adverse event indicated to be of worsening Crohn's disease, or had insufficient data to determine the response and remission status were considered to not be in response or remission.
d p-value is not significant at the 0.05 level of significance.
Patients who were not in clinical response 8 weeks after ustekinumab I.V. induction were not included in the primary efficacy analysis for IM-UNITI; however, these patients were eligible to receive a 90 mg subcutaneous injection of ustekinumab upon entry in IM-UNITI. Of these patients, 236/467 (50.5%) achieved clinical response eight weeks later and were followed for the duration of the study.
In IM-UNITI, patients who did not maintain response to ustekinumab when treated every 12 weeks were allowed to increase the frequency of dosing and receive ustekinumab every 8 weeks. In these patients (n=29), 55% and 41% achieved clinical response and clinical remission respectively 16 weeks after dosing frequency adjustment.
Of the randomized patients in clinical remission at Week 44 who entered the long-term extension, 57/69 (83%) and 52/65 (80%) of patients who received ustekinumab q8w and q12w respectively were in clinical remission at Week 92. Of the randomized patients in clinical response at Week 44 who entered the long-term extension, 64/78 (82%) and 69/82 (84%) of patients who received ustekinumab q8w and q12w respectively were in clinical response at Week 92.
Corticosteroid Use in Maintenance
At Week 44, 47% and 43% of patients who received ustekinumab q8w and q12w respectively were corticosteroid-free and in clinical remission compared to 30% of patients in the placebo group. In the subgroup of patients who were on corticosteroids at baseline, 30% of subjects in the ustekinumab treated groups were corticosteroid free and in clinical remission at Week 44, compared to 15% in the placebo group.
Endoscopic Assessment of Bowel Mucosa
Mucosal disease of the bowel (ileum and colon) was evaluated in 252 patients with baseline endoscopic disease activity in a substudy. At Week 8, after a single IV induction dose, the reduction in Simplified Endoscopic Activity Score for Crohn’s Disease (SES-CD) was -3.0 in patients treated with ustekinumab I.V. (n=83), compared -0.7 in patients treated with placebo (n=97).
Other Health Related Outcomes
Health-related quality of life was assessed by the disease specific instrument, Inflammatory Bowel Disease Questionnaire (IBDQ). In UNITI-1, the median change from baseline in the IBDQ score at Week 8 was 20 in the group treated with ustekinumab I.V. compared with 7 in the placebo group. The corresponding changes in UNITI-2 are 29 in the group treated with ustekinumab I.V. compared with 9 in the placebo group. At Week 44, the median change in IBDQ scores from Week 0 of the maintenance study was -2.5 in the ustekinumab q12w dose group and -2.0 in the ustekinumab q8w dose group, compared with -14.5 in the placebo group.
Ulcerative Colitis
The safety and efficacy of ustekinumab was assessed in two randomized, double-blind, placebo-controlled, clinical trials in adult patients with moderately to severely active ulcerative colitis who had an inadequate response to or failed to tolerate a biologic (i.e., anti-TNFα agent and/or vedolizumab) or conventional therapy. An 8-week IV induction study (UNIFI-I) was followed by a 44-week subcutaneous randomized withdrawal maintenance study (UNIFI-M) representing a total 52 weeks of therapy (Table 36).
Disease assessment was based on the Mayo score, which ranged from 0 to 12 and has four subscores that were each scored from 0 (normal) to 3 (most severe): stool frequency, rectal bleeding, findings of endoscopy, and physician global assessment. Moderately to severely active ulcerative colitis was defined at baseline (Week 0) as Mayo score of 6 to 12, including a Mayo endoscopy subscore ≥ 2. The endoscopy subscore was assessed by the investigator (i.e., local endoscopist) during the endoscopy procedure and by a central reader who reviewed a video of the endoscopy. Patients were permitted to receive concomitant aminosalicylates, immunomodulators, and/or corticosteroids and 90% of patients continued to receive at least one of these medications.
Table 36 Summary of controlled clinical trials supporting safety and efficacy in patients with UC
| Study # | Study Design | Dosage: Route of Administration and Duration | Study Subjects (n) | Median Age (Range) | Sex |
|---|---|---|---|---|---|
UNIFI-I (Induction) | Multicentre, double-blinded, randomized, placebo- controlled | IV administration at Week 0 | 961 | 41 (18-84) | M: 582, 61 F: 379, 39 |
| Placebo | 319 | ||||
| Ustekinumab I.V. 130 mg | 320 | ||||
| Ustekinumab I.V. ~6 mg/kga | 322 | ||||
UNIFI-M (Maintenance) | Multicentre, double-blinded, placebo- controlled randomized- withdrawal | SC administration at Week 0b, and then q8w or q12w for 44 weeks | 523 | 40 (18-84) | M: 297, 57 F: 226, 43 |
| Placebo | 175 | ||||
| Ustekinumab 90 mg q8w | 176 | ||||
| Ustekinumab 90 mg q12w | 172 | ||||
a tiered weight-based dose approximating 6 mg/kg (see 4 DOSAGE AND ADMINISTRATION)
b 8 weeks following the intravenous dose of ustekinumab I.V.
Induction Study: UNIFI-I
In the induction study (UNIFI-I), 961 patients were randomized to receive a single intravenous administration of 130 mg ustekinumab I.V., or approximately 6 mg/kg ustekinumab I.V. designed as a tiered dose based on patient body weight or placebo at Week 0. Randomization was stratified by biologic failure status (yes/no) and region (Eastern Europe, Asia, or rest of world).
The primary endpoint was clinical remission (defined as a Mayo score ≤ 2 points, with no individual sub-score > 1) at Week 8. The secondary endpoints included: clinical response (≥ 3 points and 30% decrease in Mayo score with either a decrease from baseline in the rectal bleeding subscore ≥ 1 or a rectal bleeding subscore of 0 or 1), improvement of endoscopic appearance of the mucosa (Mayo endoscopy subscore of 0 or 1), and histo-endoscopic mucosal healing (defined as combined improvement of endoscopic appearance of the mucosa and histologic healing of the colon tissue [neutrophil infiltration in < 5% of crypts, no crypt destruction, and no erosions, ulcerations, or granulation tissue]).
Patients enrolled in UNIFI-I had to have failed conventional therapy (corticosteroids or immunomodulators) or at least one biologic (an anti-TNFα agent and/or integrin antagonist). Of the total population, 49% of patients had failed conventional therapy but not a biologic (of which 94% were biologic-naïve) and 51% of patients had failed or were intolerant to a biologic. Approximately 50% of patients had failed at least 1 prior anti-TNFα agent (of which 48% were primary non-responders) and 17% had failed both an anti-TNFα agent and an integrin antagonist. At induction baseline and throughout the study, approximately 52% of patients were receiving oral corticosteroid, 28% of patients were receiving immunomodulators (AZA, 6-MP, or MTX) and 69% of patients were receiving aminosalicylates.
In UNIFI-I, a significantly greater proportion of patients were in clinical remission and response and achieved improvement of endoscopic appearance of the mucosa and histo-endoscopic mucosal healing in the ustekinumab I.V. treated group (at the recommended dose of approximately 6 mg/kg) compared to placebo at Week 8 (Table 37).
Table 37 Results for Efficacy Endpoints at Week 8 in UNIFI-I*
Placebo N = 319 | Ustekinumab I.V. ~6 mg/kg N = 322 | Treatment difference, 97.5% CI | |
|---|---|---|---|
| Clinical Remission** | 17 (5.3%) | 50 (15.5%) | 10.2 (5.0, 15.5)a |
| Biologic-naïve⸸ | 15/151 (9.9%) | 27/147 (18.4%) | |
| With prior biologic failure | 2/161 (1.2%) | 21/166 (12.7%) | |
| Improvement of endoscopic appearance of the mucosa‡ | 44 (13.8%) | 87 (27.0%) | 13.3 (6.4, 20.1)a |
| Biologic-naïve⸸ | 32/151 (21.2%) | 49/147 (33.3%) | |
| With prior biologic failure | 11/161 (6.8%) | 35/166 (21.1%) | |
| Clinical Response§ | 100 (31.3%) | 199 (61.8%) | 30.5 (22.2, 38.8)a |
| Biologic-naïve⸸ | 54/151 (35.8%) | 98/147 (66.7%) | |
| With prior biologic failure | 44/161 (27.3%) | 95/166 (57.2%) | |
| Histo-Endoscopic Mucosal Healing† | 28 (8.8%) | 58 (18.0%) | 9.3 (3.4, 15.2)a |
| Biologic-naïve⸸ | 21/151 (13.9%) | 33/147 (22.4%) | |
| With prior biologic failure | 6/161 (3.7%) | 22/166 (13.3%) |
* Subjects who had insufficient data or had a prohibited change in concomitant UC medication or an ostomy or colectomy prior to the Week 8 visit were considered not to have achieved the respective endpoints.
⸸An additional 7 patients on placebo and 9 patients on ustekinumab (~6 mg/kg) had been exposed to, but had not failed, biologics.
** Clinical remission is defined as Mayo score ≤2 points, with no individual subscore > 1.
‡ Improvement of endoscopic appearance of the mucosa is defined as a Mayo endoscopic sub-score of 0 or 1 determined by central review of the endoscopy.
§ Clinical response was defined as a decrease from baseline in the Mayo score by ≥ 30% and ≥ 3 points, with either a decrease from baseline in the rectal bleeding subscore ≥ 1 or a rectal bleeding subscore of 0 or 1.
†Histo-endoscopic mucosal healing is defined as combined improvement of endoscopic appearance of the mucosa (Mayo endoscopy sub-score of 0 or 1) and histologic healing of the colon tissue (neutrophil infiltration in < 5% of crypts, no crypt destruction, and no erosions, ulcerations, or granulation tissue).
a p < 0.001; p-value is based on a Cochran-Mantel-Haenszel (CMH) chi-square test stratified by biologic failure status and region. Type I error rate is controlled at the 0.025 significance level based on a pre- defined hierarchical testing procedure.
Maintenance Study: UNIFI-M
The maintenance study (UNIFI-M), evaluated 523 patients who achieved clinical response at Week 8 following the administration of ustekinumab I.V. in UNIFI-I. These patients were randomized to receive a subcutaneous maintenance regimen of either 90 mg ustekinumab every 8 weeks, 90 mg ustekinumab every 12 weeks or placebo for 44 weeks. Randomization was stratified by clinical remission status at maintenance baseline (yes/no), oral corticosteroid use at maintenance baseline (yes/no), and induction treatment.
The primary endpoint was the proportion of patients in clinical remission at Week 44. Secondary endpoints included the proportion of patients maintaining clinical response through Week 44, the proportion of patients with improvement of endoscopic appearance of the mucosa at Week 44, the proportion of patients with corticosteroid-free clinical remission at Week 44, and the proportion of patients maintaining clinical remission through Week 44 in patients who achieved clinical remission 8 weeks after induction. Patients who completed the maintenance study through Week 44 were eligible to continue treatment through Week 96.
Results of the primary and secondary endpoints at Week 44 in patients treated with ustekinumab at the recommended dosage (90 mg every 8 weeks) compared to the placebo are shown in Table 38.
Table 38 Results for Efficacy Endpoints at Week 44 in UNIFI-M (52 weeks from initiation of the induction dose)*
Placebo¥ N = 175 | Ustekinumab 90 mg every 8 Weeks N = 176 | Treatment difference, 95% CI | |
|---|---|---|---|
| Clinical Remission** | 42 (24.0%) | 77 (43.8%) | 19.7 (10.3, 29.0)ab |
| Biologic-naïve⸸ | 27/84 (32.1%) | 40/79 (50.6%) | |
| With prior biologic failure | 15/88 (17.0%) | 36/91 (39.6%) | |
Maintenance of Clinical Response through Week 44§ | 78 (44.6%) | 125 (71.0%) | 26.4 (16.6, 36.1)ab |
| Biologic-naïve⸸ | 44/84 (52.4%) | 61/79 (77.2%) | |
| With prior biologic failure | 34/88 (38.6%) | 59/91 (64.8%) | |
| Improvement of Endoscopic Appearance of the Mucosa† | 50 (28.6%) | 90 (51.1%) | 22.5 (12.8, 32.2)ab |
| Biologic-naïve⸸ | 30/84 (35.7%) | 46/79 (58.2%) | |
| With prior biologic failure | 20/88 (22.7%) | 41/91 (45.1%) | |
| Corticosteroid free clinical remission | 41 (23.4%) | 74 (42.0%) | 18.5 (9.3, 27.8)ab |
| Biologic-naïve⸸ | 27/84 (32.1%) | 39/79 (49.4%) | |
| With prior biologic failure | 14/88 (15.9%) | 34/91 (37.4%) | |
| Maintenance of clinical remission through week 44 in patients who achieved clinical remission 8 weeks after induction | 17/45 (37.8%) | 22/38 (57.9%) | |
| Biologic-naïve⸸ | 9/25 (36.0%) | 12/16 (75.0%) | |
| With prior biologic failure | 8/20 (40.0%) | 10/20 (50.0%) |
* Subjects who had insufficient data or had a prohibited change in UC medication, an ostomy or colectomy, or used a rescue medication after clinical flare, or discontinued study agent due to lack of therapeutic effect or due to an AE of worsening of UC prior to the Week 44 visit were considered not to have achieved the respective endpoints
¥ The placebo group consisted of patients who were in response to ustekinumab I.V. and were randomized to receive placebo at the start of maintenance therapy
⸸ An additional 3 patients on placebo and 6 patients on q8w ustekinumab had been exposed to, but had not failed, biologics
** Clinical remission is defined as Mayo score ≤2 points, with no individual subscore > 1
§ Clinical response was defined as a decrease from baseline in the Mayo score by ≥ 30% and ≥ 3 points, with either a decrease from baseline in the rectal bleeding subscore ≥ 1 or a rectal bleeding subscore of 0 or 1
† Improvement of endoscopic appearance of the mucosa is defined as a Mayo endoscopic sub-score of ≤ 1 point
a p < 0.001
b p value is based on a Cochran-Mantel-Haenszel (CMH) chi-square test stratified by clinical remission status at maintenance baseline (not applicable to the last endpoint) and induction treatment. Type I error rate is controlled based on a pre-defined hierarchical testing procedure
Week 16 Responders to Ustekinumab I.V Induction
Patients who were not in clinical response 8 weeks after ustekinumab I.V. induction were not included in the primary efficacy analysis for UNIFI-M; however, these patients were eligible to receive a 90 mg subcutaneous injection of ustekinumab at Week 8. Of the 101 patients who received the recommended induction dose of 6 mg/kg who were not in clinical response at Week 8, 59/101 (58.4%) achieved clinical response at Week 16 of UNIFI-I and received ustekinumab every 8 weeks during UNIFI-M. Patients who did not achieve clinical response at Week 16 were discontinued from the study.
Histo-Endoscopic Mucosal Healing
The proportion of patients achieving histo-endoscopic mucosal healing at Week 44 was 79/176 (44.9%) in patients receiving ustekinumab every 8 weeks compared to 41/175 (23.4%) in patients treated with placebo. The relationship of histo-endoscopic mucosal healing at Week 44 to progression of disease or long-term outcomes was not evaluated.
15. Microbiology
No microbiological information is required for this drug product.
16. Non-Clinical Toxicology
The toxicity of ustekinumab was specifically evaluated in a number of nonclinical studies. An overview of these toxicity studies is provided in Table 39.
General Toxicology: In repeated-dose toxicity studies in cynomolgus monkeys, ustekinumab was well tolerated following IV doses up to 45 mg/kg/week for up to 1 month and following twice-weekly SC doses up to 45 mg/kg for 6 months. There were no ustekinumab-related findings in the immunotoxicity and cardiovascular safety pharmacology evaluations. In histopathology evaluations there were no preneoplastic changes observed. No evidence of ustekinumab-related local intolerance was observed in examinations of subcutaneous injection sites in a local tolerance study and in the chronic subcutaneous toxicity study.
The 45 mg/kg dose is approximately 45-fold higher than the highest equivalent dose intended to be administered to patients with psoriasis (based on administration of a 90 mg SC dose to a 90 kg patient) and the average Cmax value observed following the last SC 45 mg/kg dose in the 6-month chronic toxicity study in cynomolgus monkeys was approximately 118-fold higher than the median Cmax value of ustekinumab observed following 4 weekly 90 mg SC doses in psoriasis patients.
Genotoxicity: The genotoxic potential has not been evaluated.
Carcinogenicity: The carcinogenic potential has not been evaluated.
Reproductive and Developmental Toxicology: Three developmental toxicity studies were conducted in cynomolgus monkeys. No ustekinumab-related maternal toxicity, abortions, still-births, embryotoxicity, developmental delays, malformations or birth defects were observed at doses up to 45 mg/kg following weekly or twice weekly administration of ustekinumab via the IV or SC routes, respectively. In neonates born from pregnant monkeys treated with ustekinumab, no adverse effects on growth or functional development were observed and no deficits were observed in immunotoxicity evaluations. In a male fertility study in cynomolgus monkeys, no ustekinumab-related effects on mating behaviour, sperm parameters, or serum concentrations of male hormones were observed following twice weekly subcutaneous administration of ustekinumab at doses up to 45 mg/kg.
A female fertility toxicity study was conducted in mice using an analogous antibody that binds to and inhibits IL-12 and IL-23 activity in mice. Twice weekly subcutaneous administration of the anti-mouse IL-12/23 antibody was well tolerated at doses up to 50 mg/kg and no adverse effects on female fertility parameters were observed.
Table 39 Non-Clinical Toxicology Studies with Ustekinumab
| Study | Species/ Strain | Route | Duration of Dosing | Doses (mg/kg) | Results |
|---|---|---|---|---|---|
| Study | Species/ Strain | Route | Duration of Dosing | Doses (mg/kg) | Results |
| Study | Species/ Strain | Route | Duration of Dosing | Doses (mg/kg) | Results |
| Repeat-Dose Toxicity | |||||
| Subchronic toxicity | Monkey/ Cynomolgus | IV | 1 month | 9, 45 weekly | No treatment-related signs of toxicity. |
| Subchronic toxicity | Monkey/ Cynomolgus | IV | 1 month | 9, 45 weekly | No treatment-related signs of toxicity. |
| Chronic toxicity | Monkey/ Cynomolgus | SC | 6 months | 22.5, 45 twice weekly | No treatment-related signs of toxicity. No preneoplastic changes observed on histopathology. |
| Reproductive and Developmental Toxicity | |||||
| Embryofetal Development | Monkey/ Cynomolgus | IV | Pregnant females: gestation day 20 to | 9, 45 weekly | No maternal or fetal abnormalities were observed. |
gestation day 50 | |||||
| Embryofetal Development | Monkey/ Cynomolgus | SC | Pregnant females: gestation day 20 – gestation day 51 | 22.5, 45 twice weekly | A statistically significant increase in maternal 17ß- estradiol levels relative to the control group was observed on days 80 and 100 of gestation in the 22.5 and 45 mg/kg groups. However, foetal 17ß-estradiol levels were not affected, and there were no other treatment-related maternal or foetal abnormalities observed at either dose level. |
| Male fertility | Monkey/ Cynomolgus | SC | Males: 13 weeks | 22.5, 45 twice weekly | No changes in fertility parameters observed. |
| Female fertility | Mouse/Crl CD-1 | SC | Beginning 15 days before cohabitation and continuing through day 7 of presumed gestation | 25, 50 twice weekly | No maternal or fetal abnormalities were observed. |
| Embryofetal and pre- and postnatal development | Monkey/ Cynomolgus | SC | Pregnant females: gestation day 20 –postpartum day 30 | 22.5, 45 twice weekly | No effects on pregnancy or delivery; or morphological, functional and immunological developmental parameters of offspring. Ustekinumab was detected in the milk of lactating monkeys. |
| Local Tolerance | |||||
| Pharmacokin etics and injection site irritation | Monkey/ Cynomolgus | SC | 18 days | 45 twice weekly | Minimal signs of local irritation at injection sites were observed, with no associated histopathologic findings. |
| Other Toxicity Studies | |||||
| Tissue cross- reactivity | Human Tissues | In vitro | 1.13, 11.3, 113, 225 mg/mL | No binding to nontarget normal human tissues. | |
| Tissue cross- reactivity | Human Tissues | In vitro | 1.13, 11.3, 113, 225 | No binding to nontarget normal human tissues. | |
| mg/mL | |||||
| Asthma model | Monkey/ Cynomolgus | IV | Single dose | 9, 45 | No exacerbation of pulmonary function or cellular responses. |
| Asthma model | Monkey/ Cynomolgus | IV | 1 week | 45 | No exacerbation of pulmonary function or cellular responses. |
IV : Intravenous
SC: Subcutaneous
17. Supporting Product Monographs
- 1. PrStelara® (solution, 45 mg/0.5 mL. 90 mg/1.0 mL)/ PrStelara®I.V. (solution, 130 mg/26 mL (5 mg/mL)), submission control 278990, Product Monograph, Janssen Inc., 2024-08-14.