


Product Monograph - PMS-Dexamethasone
1 INDICATIONS
pms-DEXAMETHASONE (dexamethasone tablets) is used orally in the management of disorders responsive to adrenocortical hormone therapy such as:
- Allergic States: Control of severe or incapacitating allergic conditions not responsive to adequate trials of conventional treatment: seasonal or perennial allergic rhinitis, bronchial asthma (including status asthmaticus), laryngeal edema, contact dermatitis, atopic dermatitis, serum sickness, drug hypersensitivity reactions.
- Rheumatic Disorders: As adjunctive therapy for short term administration during an acute episode or exacerbation of psoriatic arthritis, rheumatoid arthritis including juvenile rheumatoid arthritis (selected cases may require low dose maintenance therapy), ankylosing spondylitis, acute and subacute bursitis, acute nonspecific tenosynovitis, acute gouty arthritis.
- Dermatologic Diseases: Pemphigus, bullous dermatitis herpetiformis, severe erythema multiform (Stevens-Johnson syndrome), exfoliative dermatitis, mycosis fungoides, severe psoriasis, severe seborrheic dermatitis.
- Ophthalmic Diseases: Severe acute and chronic allergic and inflammatory processes involving the eye and its adnexa such as allergic conjunctivitis, keratitis, allergic corneal marginal ulcers, herpes zoster ophthalmicus (but not herpes simplex), iritis and iridocyclitis, chorioretinitis, anterior segment inflammation, diffuse posterior uveitis and choroiditis, optic neuritis, sympathetic ophthalmia.
- Endocrine Disorders: Primary or secondary adrenocortical insufficiency (hydrocortisone or cortisone is the first choice; synthetic analogs may be used in conjunction with mineralocorticoids where applicable; in infancy, mineralocorticoid supplementation is of particular importance); congenital adrenal hyperplasia; nonsuppurative thyroiditis; hypercalcemia associated with cancer.
- Respiratory Diseases: Symptomatic sarcoidosis, Loeffler's syndrome not manageable by other means, berylliosis, fulminating or disseminated pulmonary tuberculosis when concurrently accompanied by appropriate antituberculous chemotherapy, aspiration pneumonitis. Dexamethasone is also used in the antenatal prophylaxis of neonatal respiratory distress.
- Hematologic Disorders: Idiopathic and secondary thrombocytopenia in adults, acquired (autoimmune) hemolytic anemia, erythroblastopenia (RBC anemia), congenital (erythroid) hypoplastic anemia.
- Neoplastic Diseases: For palliative management of leukemias and lymphomas in adults, acute childhood leukemia.
Edematous States: To induce a diuresis or emission of proteinuria in the nephrotic syndrome, without uremia, of the idiopathic type or that due to lupus
- erythematosus.
- Cerebral Edema: Dexamethasone may be administered orally to treat patients with cerebral edema from various causes. Patients with cerebral edema associated with primary or metastatic brain tumors may benefit from oral administration. Dexamethasone may be used also in the preoperative preparation of patients with increased intracranial pressure secondary to brain tumors, and also for palliation of patients with inoperable or recurrent brain neoplasms, and in the management of cerebral edema associated with neurosurgery. Some patients with cerebral edema due to head injury or pseudotumor cerebri also may benefit from oral dexamethasone therapy. Use of dexamethasone in cerebral edema is not a substitute for careful neurosurgical evaluation and definitive management such as neurosurgery or other specific therapy.
- Gastrointestinal Diseases: During a critical period of the disease in ulcerative colitis, regional enteritis.
- Miscellaneous: Tuberculous meningitis with subarachnoid block or impending block when concurrently accompanied by appropriate antituberculous chemotherapy, trichinosis with neurologic or myocardial involvement. During an exacerbation or as maintenance therapy in selected cases of systemic lupus erythematosus, acute rheumatic carditis.
- Diagnostic testing: Dexamethasone is used in the diagnostic testing of adrenocortical hyperfunction.
- Antiemetic effect: High-dose dexamethasone regimens have been used effectively for the prevention of nausea and vomiting associated with emetogenic cancer chemotherapy, including that associated with cisplatin; however, the safety and role of high-dose dexamethasone regimens for antiemetic therapy remain to be clearly determined.
2 CONTRAINDICATIONS
pms-DEXAMETHASONE is contraindicated in:
- Patients who are hypersensitive to this drug or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see section 5: DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING.
- Systemic fungal infections
- Stomach ulcer or duodenal ulcer
- Infection with tropical worms
- Active or suspected ocular or periocular infections
- Advanced glaucoma in patients with cup to disk ratios greater than 0.8
- Systemic infection unless specific anti-infective therapy is employed
3 DOSAGE AND ADMINISTRATION
Individualize dosage according to the severity of the disease and the patient's response. The severity, prognosis, expected duration of the disease and the patient's reaction to medication are primary factors in determining dosage. (For infants and children, the recommended doses usually will have to be reduced, but dosage should be dictated by the severity of the condition rather than by age or body weight).
Hormone therapy is an adjunct to, not a replacement of, conventional therapy, which should be instituted as indicated.
Decrease dosage or discontinue therapy gradually when administration has been continued for more than a few days.
Continued supervision of the patient after cessation of corticosteroids is essential, since there may be a sudden reappearance of severe manifestations of the disease for which the patient was treated, and it may take up to a year for adrenal function to return to normal.
In acute conditions where prompt relief is urgent, large doses are permissible and may be mandatory for a short period.
In chronic conditions requiring long-term therapy, use the lowest dosage that provides adequate, but not necessarily complete, relief. If a high dosage for prolonged periods is considered essential, observe patients closely for signs that might necessitate a dosage reduction or discontinuance of the hormone.
Chronic conditions are subject to periods of spontaneous remission. When such periods occur, discontinue corticosteroids gradually. Carry out routine laboratory studies such as urinalysis, two-hour post-prandial blood sugar, determinations of blood pressure and body weight, and a chest x-ray at regular intervals during prolonged therapy. Periodic determinations of serum potassium are advisable if large doses are being used. Take upper gastrointestinal x-rays when treatment is prolonged, in patients with a history of ulcer or when there is gastric distress.
The following mg equivalents facilitate changing to dexamethasone from other glucocorticoids: dexamethasone 0.75 mg = methylprednisolone and triamcinolone 4 mg = prednisolone and prednisone 5 mg = hydrocortisone 20 mg = cortisone 25 mg.
In chronic, usually nonfatal disease including endocrine and chronic rheumatic disorders, edematous states, respiratory and gastrointestinal diseases, some dermatologic diseases and hematologic disorders, start with a low dose (0.5 to 1 mg a day) and gradually increase dosage to the smallest amount that gives the desired degree of symptomatic relief. Dosage may be administered 2, 3 to 4 times a day, at equally spaced intervals. Dexamethasone should be taken with food or milk to minimize gastrointestinal irritation. When symptoms have been suppressed adequately, maintain dosage at the minimum amount capable of providing sufficient relief without excessive hormonal effects.
In congenital adrenal hyperplasia, the usual dose is 0.5 to 1.5 mg.
In acute, nonfatal diseases, including allergic states, ophthalmic diseases, acute and subacute rheumatic disorders, dosage ranges between 2 and 3 mg a day; however, higher doses are necessary in some patients. Since the course of these conditions is self-limited, prolonged maintenance therapy is not usually necessary.
In acute, self-limited, allergic disorders or acute exacerbations of chronic allergic disorders (e.g. acute allergic rhinitis, acute attacks of seasonal allergic bronchial asthma, urticaria medicamentosa and contact dermatoses), the following dosage schedule is suggested: first day: 4 or 8 mg intramuscularly; second and third days: 1.5 mg orally twice a day; fourth day: 0.75 mg orally twice a day; fifth and sixth days: 0.75 mg orally; seventh day: no treatment; eighth day: follow-up visit.
In chronic, potentially fatal diseases such as systemic lupus erythematosus, pemphigus, symptomatic carcoidosis: initial dosage is 2 to 4.5 mg a day; higher doses are necessary in some patients. As soon as adequate relief is obtained, reduce the dosage gradually to the minimum amount that will produce the desired therapeutic effect.
When the disease is acute and life-threatening (e.g., acute rheumatic carditis, crisis of systemic lupus erythematosus, severe allergic reactions, pemphigus, neoplastic diseases), the initial dosage is between 4 and 10 mg a day, administered in at least 4 divided doses; this dosage may have to be increased in some patients to establish control. As soon as control is attained, reduce the dosage gradually to the minimum amount that will maintain relief.
Croup:
The usual dose of dexamethasone is 2 to 5 mg depending on the child's age and weight. Conventional croup therapy must be given concomitantly, including adequate doses of a suitable antibiotic. In particularly severe cases, steroid therapy may be continued in small doses for 2 to 3 days as a precaution against recurrence.
In the adrenogenital syndrome, daily dosages of 0.5 to 1.5 mg may keep children in remission and prevent the recurrence of abnormal excretion of 17-ketosteroids.
As massive therapy in certain conditions, such as acute leukemia, the nephrotic syndrome, and pemphigus, the dosage is from 10 to 15 mg a day. Observe patients receiving such a high dosage very closely for the appearance of severe reactions.
In cerebral edema, dexamethasone sodium phosphate is generally administered initially in acute conditions. When maintenance therapy is required, this should be changed to oral dexamethasone as soon as possible. For palliative management of patients with recurrent or inoperable brain tumors, individualize maintenance therapy with either dexamethasone sodium phosphate injection or oral dexamethasone. A dosage of 2 mg 2 or 3 times a day may be effective. Utilize the smallest dosage necessary to control cerebral edema.
In dental postoperative inflammatory reactions, administer from 0.5 to 0.75 mg 3 times a day, for no more than 2 or 3 days.
Dexamethasone suppression test: as a screening test for Cushing's Syndrome, give 0.5 mg of dexamethasone orally every 6 hours for 48 hours. Determine 17-hydroxycorticosteroids in 24-hour urine collection. For greater accuracy, give 1 mg orally at 11.00 p.m. Draw blood for plasma corticol determination at 8:00 a.m. the following morning. To distinguish adrenal tumor from adrenal hyperplasia, give 2 mg of dexamethasone orally every 6 hours for 48 hours. Make 24-hour urine collection for determination of 17-hydroxycorticosteroid excretion.
Missed Dose
If the patient misses a dose, instruct the patient to take the dose as soon as they remember. If it is almost time for the next dose, inform the patient to skip the missed dose and continue the regular dosing schedule.
4 OVERDOSAGE
Symptoms:
Hypertension, edema.
Treatment:
In the event of overdosage, no specific antidote is available; treatment is supportive and symptomatic.
Anaphylactic and hypersensitivity reactions may be treated with epinephrine, positive pressure artificial respiration, and aminophylline. Keep the patient warm and quiet. Treatment probably is not indicated for reactions due to chronic overdosage unless the patient has a condition that would render him/her unusually susceptible to ill effects from corticosteroids.
For management of a suspected drug overdose, contact your regional poison control centre.
5 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 1 – Dosage Forms, Strengths, Composition and Packaging
Description
0.5 mg: Each yellow colored, pentagonal, flat, beveled edge tablet, debossed with a «P» logo over a score line and «084» under it on one side of the tablet and plain on the other. Available in bottles of 100 tablets.
0.75 mg: Each blue, pentagonal, flat, beveled edge tablet debossed with a «P» logo over a score line and «085» under it on one side of the tablet and plain on the other. Available in bottles of 100 tablets.
2 mg: Each white, pentagonal, flat, beveled edge tablet, debossed with a «P» logo over a score line and «086» under it on one side of the tablet and plain on the other. Available in bottles of 100 tablets.
4 mg: Each white, pentagonal, flat, beveled edge tablet, debossed with a «P» logo over a score line and «087» under it on one side of the tablet and plain on the other. Available in bottles of 100 tablets.
| Route of Administration | Dosage Form Strength | Non-medicinal Ingredients |
| Oral | Tablets 0.5 mg 0.75 mg 2 mg 4 mg | Croscarmellose sodium, lactose, magnesium stearate, microcrystalline cellulose, stearic acid, D&C Yellow. Croscarmellose sodium, lactose, magnesium stearate, microcrystalline cellulose, stearic acid, D&C Yellow and FD&C Blue. Croscarmellose sodium, lactose, magnesium stearate, microcrystalline cellulose, stearic acid. Croscarmellose sodium, lactose, magnesium stearate, microcrystalline cellulose, stearic acid. |
6 WARNINGS AND PRECAUTIONS
General
While on corticosteroid therapy, patients should not be vaccinated against smallpox because of potential complications. Conversely, patients with vaccinia should not receive corticosteroid therapy. Other immunization procedures should not be undertaken in patients who are on corticosteroids, especially on high doses, because of possible hazards of neurological complications and a lack of antibody response. However, immunization procedures may be undertaken in patients who are receiving corticosteroids as replacement therapy, e.g., for Addison's disease.
Use the lowest possible dose of corticosteroid to control the condition under treatment, and when dosage reduction is possible, the reduction should be gradual.
During treatment with dexamethasone for specific physical stress conditions (trauma, surgery, childbirth, etc.), a temporary increase in dose may be required.
Since complications of treatment with corticosteroids are dependent on the size of the dose and the duration of treatment, a risk/benefit decision must be made in each individual case as to dose and duration of treatment and as to whether daily or intermittent therapy should be used.
Use corticosteroid with caution in renal insufficiency; hypertension; osteoporosis; and myasthenia gravis.
Regular checkups with doctors (including vision checkups in three-month intervals) are advised during long-term treatment.
Even in cases of prolonged adrenocortical insufficiency after discontinuation of treatment, the administration of glucocorticoids can be necessary in physically stressful situations. An acute therapy-induced adrenocortical insufficiency can be minimized by slow dose reduction until a planned discontinuation time.
The following risks should be considered upon interruption or discontinuation of long-term glucocorticoid treatment:
- Exacerbation or recurrence of the underlying disease, acute adrenal insufficiency, corticosteroid withdrawal syndrome.
- Certain viral diseases (chickenpox, measles) in patients treated with glucocorticoids, may be very severe.
- Children and immunocompromised persons without previous chickenpox or measles infection are particularly at risk. If these people have contact with people infected with measles or chickenpox while undergoing treatment with dexamethasone, a preventative treatment should be introduced if necessary.
Carcinogenesis and Mutagenesis
Kaposi's sarcoma has been reported to occur in patients receiving corticosteroid therapy, most often for chronic conditions. Discontinuation of corticosteroids may result in clinical improvement.
In post marketing experience tumour lysis syndrome (TLS) has been reported in patients with haematological malignancies following the use of dexamethasone alone or in combination with other chemotherapeutic agents. Patient at high risk of TLS, such as patients with high proliferative rate, high tumour burden, and high sensitivity to cytotoxic agents, should be monitored closely and appropriate precaution taken.
Cardiovascular / Cardio-Renal
Average and large doses of corticosteroids can cause elevation of blood pressure, sodium and water retention, and increased excretion of potassium. These effects are less likely to occur with the synthetic derivatives except when used in large doses. Dietary salt restriction and potassium supplementation may be necessary. All corticosteroids increase calcium excretion.
At high doses, sufficient calcium intake and sodium restriction, as well as serum potassium levels should be monitored. Depending on the length and dosage of the treatment, a negative influence on calcium metabolism can be expected.
Because of the risk of deterioration, patients with severe cardiac insufficiency should be carefully monitored.
Literature reports suggest an apparent association between use of corticosteroids and left ventricular free wall rupture after a recent myocardial infarction; therefore, therapy with corticosteroids should be used with great caution in these patients.
As sodium retention with resultant edema and potassium loss may occur in patients receiving corticosteroids, these agents should be used with caution in patients with congestive heart failure, hypertension, or renal insufficiency.
Dependence/Tolerance
Psychological and/or physiological dependency may develop with long term use of corticosteroids. Dis-continuance of therapy may lead to the development of withdrawal symptoms, including anorexia, vague pains, weakness, and lethargy. Patients should be warned not to discontinue the use of corticosteroids abruptly or without medical supervision. As prolonged use may cause adrenal insufficiency and make patients dependent on corticosteroids, they should advise their healthcare professional that they are taking corticosteroids and they should seek medical advice at once should they develop an acute illness including fever or other signs of infection.
Driving and Operating Machinery
Patients should be advised not to drive, use any tools or machines, or carry out any hazardous tasks if they experience side effects, such as confusion, hallucinations, dizziness, tiredness, sleepiness, fainting or blurred vision.
Endocrine and Metabolism
Corticosteroids can produce reversible hypothalamic-pituitary adrenal (HPA) axis suppression with the potential for corticosteroid insufficiency after withdrawal of treatment. Adrenocortical insufficiency may result from too rapid withdrawal of corticosteroids and may be minimized by gradual reduction of dosage. This type of relative insufficiency may persist for months after discontinuation of therapy; therefore, in any situation of stress occurring during that period, hormone therapy should be reinstituted. If the patient is receiving steroids already, dosage may have to be increased.
Drug-induced secondary adrenocortical insufficiency may be minimized by gradual reduction of dosage. Since mineralocorticoid secretion may be impaired, salt and/or a mineralocorticoid should be administered concurrently.
Metabolic clearance of corticosteroids is decreased in hypothyroid patients and increased in hyperthyroid patients. Changes in thyroid status of the patient may necessitate adjustment in dosage.
There is an enhanced effect due to decreased metabolism of corticosteroids in patients with cirrhosis.
A higher need for insulin or oral antidiabetics must be taken into consideration when administering dexamethasone to diabetics.
Cushing syndrome may occur with prolonged exposure; use lowest corticosteroid dose for shortest duration possible.
Pheochromocytoma crisis, potentially fatal, may occur after administration of systemic corticosteroids; consider risk prior to use in patients with suspected or identified pheochromocytoma.
Gastrointestinal
Steroids should be used with caution in active or latent peptic ulcers, diverticulitis, fresh intestinal anastomoses, and nonspecific ulcerative colitis since they may increase the risk of a perforation.
Because of the risk of an intestinal perforation, dexamethasone must only be used under urgent indication and under appropriate monitoring for severe ulcerative colitis with threatened perforation; diverticulitis; entero-anastomosis (immediately postoperative).
Signs of peritoneal irritation following gastrointestinal perforation in patients receiving corticosteroids may be minimal or absent.
When large doses are given, antacids may be administered between meals to help prevent peptic ulcer.
Hematologic
Idiopathic thrombocytopenic purpura in adults should be treated by intravenous injection.
Immune
Patients who are on corticosteroids are more susceptible to infections than are healthy individuals. There may be decreased resistance and inability to localize infection when corticosteroids are used. Infection with any pathogen (viral, bacterial, fungal, protozoan or helminthic) in any location of the body may be associated with the use of corticosteroids alone or in combination with other immunosuppressive agents. These infections may be mild to severe. With increasing doses of corticosteroids, the rate of occurrence of infectious complications increases. Corticosteroids may also mask some signs of current infection.
Treatment with dexamethasone can conceal the symptoms of an existing or developing infection thereby making a diagnosis more difficult.
Fungal Infections: Corticosteroids may exacerbate systemic fungal infections and therefore should not be used in the presence of such infections unless they are needed to control life-threatening drug reactions. There have been cases reported in which concomitant use of amphotericin B and hydrocortisone was followed by cardiac enlargement and congestive heart failure.
Special Pathogens: Latent disease may be activated or there may be an exacerbation of intercurrent infections due to pathogens, including those caused by Amoeba, Candida, Cryptococcus, Mycobacterium, Nocardia, Pneumocystis, Toxoplasma.
It is recommended that latent amebiasis or active amebiasis be ruled out before initiating corticosteroid therapy in any patient who has spent time in the tropics or any patient with unexplained diarrhea.
Similarly, corticosteroids should be used with great care in patients with known or suspected Strongyloides (threadworm) infestation. In such patients, corticosteroid-induced immunosuppression may lead to Strongyloides hyperinfection and dissemination with widespread larval migration, often accompanied by severe enterocolitis and potentially fatal gram-negative septicemia.
Corticosteroids should not be used in cerebral malaria.
Tuberculosis: The use of corticosteroids in active tuberculosis should be restricted to those cases of fulminating or disseminated tuberculosis in which the corticosteroid is used for the management of the disease in conjunction with an appropriate antituberculous regimen.
If corticosteroids are indicated in patients with latent tuberculosis or tuberculin reactivity, close observation is necessary as reactivation of the disease may occur. During prolonged corticosteroid therapy, these patients should receive chemoprophylaxis.
Vaccination: Administration of live or live, attenuated vaccines is contraindicated in patients receiving immunosuppressive doses of corticosteroids. Killed or inactivated vaccines may be administered. However, the response to such vaccines cannot be predicted. Immunization procedures may be undertaken in patients who are receiving corticosteroids as replacement therapy, e.g., for Addison's disease.
Viral Infections: Chickenpox and measles can have a more serious or even fatal course in pediatric and adult patients on corticosteroids. In pediatric and adult patients who have not had these diseases, particular care should be taken to avoid exposure. The contribution of the underlying disease and/or prior corticosteroid treatment to the risk is also not known. If exposed to chickenpox, prophylaxis with varicella zoster immune globulin (VZIG) may be indicated. If exposed to measles, prophylaxis with immune globulin (IG) may be indicated. If chickenpox develops, treatment with antiviral agents should be considered.
Reactivation of hepatitis B may occur.
Monitoring and Laboratory Tests
Glucocorticoids can suppress skin reaction to allergy testing. They can also affect the nitroblue tetrazolium test for bacterial infections and cause false-negative results.
False-negative results in the dexamethasone suppression test (DST) in patients being treated with indomethacin have been reported. Thus, results of the DST should be interpreted with caution in these patients.
Musculoskeletal
Corticosteroids decrease bone formation and increase bone resorption both through their effect on calcium regulation (i.e., decreasing absorption and increasing excretion) and inhibition of osteoblast function. This, together with a decrease in the protein matrix of the bone secondary to an increase in protein catabolism, and reduced sex hormone production, may lead to inhibition of bone growth in pediatric patients and the development of osteoporosis at any age. Special consideration should be given to patients at increased risk of osteoporosis (e.g., postmenopausal women) before initiating corticosteroid therapy.
Neurologic
Available evidence suggests long-term neurodevelopmental adverse events after early treatment (<96 hours) of premature infants with chronic lung disease at starting doses of 0.25 mg/kg twice daily.
An acute myopathy has been observed with the use of high doses of corticosteroids, most often occurring in patients with disorders of neuromuscular transmission (e.g., myasthenia gravis), or in patients receiving concomitant therapy with neuromuscular blocking drugs. This acute myopathy is generalized, may involve ocular and respiratory muscles, and may result in quadriparesis. Elevation of creatinine kinase may occur. Clinical improvement or recovery after stopping corticosteroids may require weeks to years.
Ophthalmologic
Use of corticosteroids may produce posterior subcapsular cataracts, glaucoma with possible damage to the optic nerves, and may enhance the establishment of secondary ocular infections due to bacteria, fungi, or viruses. The use of oral corticosteroids is not recommended in the treatment of optic neuritis and may lead to an increase in the risk of new episodes. Corticosteroids should not be used in active ocular herpes simplex.
Intraocular pressure may become elevated in some individuals. If steroid therapy is continued for more than 6 weeks, intraocular pressure should be monitored.
Use not recommended in the presence of most active viral diseases of the cornea and conjunctiva including epithelial herpes simplex keratitis (dendritic keratitis), vaccinia, and varicella, and also in mycobacterial infection of the eye and fungal disease of ocular structures.
Central serous chorioretinopathy (CSCR) which have been reported after use of systemic and topical corticosteroids. Visual disturbance may be reported with systemic and topical corticosteroid use. If a patient presents with symptoms such as blurred vision or other visual disturbances, the patient should be considered for referral to an ophthalmologist for evaluation.
Psychiatric
Potentially severe psychiatric adverse reactions may occur with systemic steroids. Symptoms typically emerge within a few days or weeks of starting the treatment. Risks may be higher with high doses/systemic exposure, although dose levels do not allow prediction of the onset, type, severity or duration of reactions. Most reactions recover after either dose reduction or withdrawal, although specific treatment may be necessary.
Patients/carers should be encouraged to seek medical advice if worrying psychological symptoms develop, especially if depressed mood or suicidal ideation is suspected. Patients/carers should also be alert to possible psychiatric disturbances that may occur either during or immediately after dose tapering/withdrawal of systemic steroids, although such reactions have been reported infrequently.
Care is required when considering the use of systemic corticosteroids in patients with existing or previous history of severe affective disorders in themselves or in their first-degree relatives. These would include depressive or manic-depressive illness and previous steroid psychosis.
Reproductive Health: Female and Male Potential
Fertility: Corticosteroids may increase or decrease motility and number of spermatozoa in some patients. Advise patients to inform subsequent physicians of the prior use of corticosteroids.
Teratogenic Risk: Corticosteroids have been shown to be teratogenic in many species when given in doses equivalent to the human dose. There are no adequate and well-controlled studies in pregnant women (see Section 6.1.1 Pregnant Women).
Sensitivity/Resistance
Because rare instances of anaphylactoid reactions have occur-red in patients receiving parenteral corticosteroid therapy, appropriate precautionary measures should be taken prior to administration, especially when the patient has a history of allergy to any drug.
6.1 Special Populations
6.1.1 Pregnant Women
Corticosteroids have been shown to be teratogenic in many species when given in doses equivalent to the human dose. Animal studies in which corticosteroids have been given to pregnant mice, rats, and rabbits have yielded an increased incidence of cleft palate in the offspring. There are no adequate and well-controlled studies in pregnant women.
Long-term or repeated corticosteroid therapy in pregnancy increases the risk of intrauterine growth retardation.
Infants born to mothers who have received substantial doses of corticosteroids during pregnancy should be carefully observed for signs of hypoadrenalism.
Studies have shown an increased risk of neonatal hypoglycaemia following antenatal administration of a short course of corticosteroid to women at risk for late preterm delivery.
Corticosteroids should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus.
6.1.2 Breast-feeding
Systemically administered corticosteroids appear in human milk and could suppress growth, interfere with endogenous corticosteroid production, or cause other untoward effects. Because of the potential for serious adverse reactions in nursing infants from corticosteroids, a decision should be made whether to discontinue nursing or to discontinue the drug, taking into account the importance of the drug to the mother.
6.1.3 Pediatrics
No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use.
Like adults, pediatric patients should be carefully observed with frequent measurements of blood pressure, weight, height, intraocular pressure, and clinical evaluation for the presence of infection, psychosocial disturbances, thromboembolism, peptic ulcers, cataracts, and osteoporosis. Pediatric patients who are treated with corticosteroids by any route, including systemically administered corticosteroids, may experience a decrease in their growth velocity. This negative impact of corticosteroids on growth has been observed at low systemic doses and in the absence of laboratory evidence of hypothalamic-pituitary-adrenal (HPA) axis suppression (i.e., cosyntropin stimulation and basal cortisol plasma levels). Growth velocity may therefore be a more sensitive indicator of systemic corticosteroid exposure in pediatric patients than some commonly used tests of HPA axis function. The linear growth of pediatric patients treated with corticosteroids should be monitored, and the potential growth effects of prolonged treatment should be weighed against clinical benefits obtained and the availability of treatment alternatives. In order to minimize the potential growth effects of corticosteroids, pediatric patients should be titrated to the lowest effective dose.
6.1.4 Geriatrics
Clinical studies did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. Other reported clinical experience has not identified differences in responses between the elderly and younger patients. In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy. In particular, the increased risk of diabetes mellitus, fluid retention and hypertension in elderly patients treated with corticosteroids should be considered.
Close clinical monitoring is required to prevent life-threatening reaction.
7 ADVERSE REACTIONS
Blood and lymphatic system disorders: Leukocytosis, lymphopenia, eosinopenia, polycythemia.
Cardiovascular disorders: Bradycardia, cardiac arrest, cardiac arrhythmias, cardiac enlargement, circulatory collapse, congestive heart failure, fat embolism, hypertension*, hypertrophic cardiomyopathy in premature infants, myocardial rupture following recent myocardial infarction, edema, pulmonary edema, syncope, tachycardia, thromboembolism, thrombophlebitis, vasculitis.
Endocrine disorders: Suppression of the hypothalamic-pituitary-adrenal axis*, decreased carbohydrate and glucose tolerance, development of cushingoid state*, hyperglycemia*, glycosuria, hirsutism, hypertrichosis, increased requirements for insulin or oral hypoglycemic agents in diabetes, manifestations of latent diabetes mellitus, menstrual irregularities, secondary adrenocortical and pituitary unresponsiveness (particularly in times of stress, as in trauma, surgery, or illness), suppression of growth in pediatric patients*, moon face.
Eye disorders: Chorioretinopathy, corneal and scleral atrophy, exophthalmos, glaucoma*, increased intraocular pressure, papilledema, posterior subcapsular cataracts*, worsening of symptoms associated with corneal ulcers. Increased ophthalmic viral, fungal and bacterial infections, worsening of symptoms associated with corneal ulcers.
Fluid and electrolyte disturbances: Sodium retention; fluid retention; congestive heart failure in susceptible patients; potassium loss; hypokalemic alkalosis; hypertension; hypotension or shock like reaction.
Gastrointestinal disorders: Abdominal distention, elevation in serum liver enzyme levels (usually reversible upon discontinuation), hepatomegaly, increased appetite, nausea, pancreatitis, peptic ulcer with possible perforation and hemorrhage*, perforation of the small and large intestine (particularly in patients with inflammatory bowel disease), ulcerative esophagitis.
General disorders and administration site conditions: Delayed wound healing, discomfort, steroid withdrawal syndrome, malaise. Steroid withdrawal syndrome: a too rapid reduction in corticosteroid dose after prolonged treatment can lead to acute adrenal insufficiency.
Immune system disorders: Anaphylactoid reaction, anaphylaxis, angioedema.
Infections and infestations: Decreased resistance to infection. Increased susceptibility to, or exacerbation of, (latent) infections with masking of clinical symptoms, opportunistic infections, reactivation of latent tuberculosis, exacerbation of eye infections, candidiasis.
Injury, poisoning and procedural complications: Reduced response to vaccination and skin tests, tendency to bruise.
Metabolism and nutrition disorders: Congestive heart failure in susceptible patients, fluid retention, hypokalemic alkalosis, potassium loss, sodium retention, weight gain, abnormal fat deposits; negative nitrogen balance due to protein catabolism; manifestation of latent diabetes mellitus, impaired carbohydrate tolerance with increased dose requirements of antidiabetic therapy, hypercholesterolemia, hypertriglyceridemia.
Musculoskeletal and connective tissue disorders: Aseptic necrosis of femoral and humeral heads, loss of muscle mass, muscle weakness, osteoporosis*, pathologic fracture of long bones, steroid myopathy, tendon rupture, vertebral compression fractures; growth inhibition in infants, children and adolescents; premature epiphyseal closure.
Nervous system disorders: Convulsions, headache, increased intracranial pressure with papilledema (pseudotumor cerebri) usually following discontinuation of treatment, neuritis, neuropathy, paresthesia, vertigo; manifestation of latent epilepsy, increased seizures in overt epilepsy.
Psychiatric disorders: Depression*, emotional instability, euphoria, insomnia, mood swings, personality changes, psychic disorders.
Reproductive system and breast disorders: Irregular menses, amenorrhea, impotence, increased or decreased motility and number of spermatozoa.
Respiratory, thoracic and mediastinal disorders: Hiccups.
Skin and subcutaneous disorders: Acne*, allergic dermatitis, dry scaly skin, ecchymoses and petechiae, erythema, impaired wound healing, increased sweating, rash, striae, suppression of reactions to skin tests, thin fragile skin, thinning scalp hair, urticaria, impaired wound healing.
Vascular disorders: Hypertension, vasculitis, increased atherosclerosis, risk of thrombosis / thromboembolism.
Adverse reactions related to parenteral corticosteroid therapy: Rare instances of blindness associated with intralesional therapy around the face and head; hyperpigmentation or hypopigmentation; subcutaneous and cutaneous atrophy; sterile abscess; post injection flare (following intra-articular use); Charcot-like arthropathy.
*Terms marked with an asterisk are rated as more common (≥ 1%).
8 DRUG INTERACTIONS
The drugs listed in this table are based on either drug interaction case reports or studies, or potential interactions due to the expected magnitude and seriousness of the interaction (i.e., those identified as contraindicated).
| Proper/Common name | Clinical comment |
| Aminoglutethimide | Aminoglutethimide may diminish adrenal suppression by corticosteroids. |
| Amphotericin B Injection and Potassium-depleting Agents | When corticosteroids are administered concomitantly with potassium-depleting agents (e.g., amphotericin B, diuretics), patients should be observed closely for development of hypokalemia. In addition, there have been cases reported in which concomitant use of amphotericin B and hydrocortisone was followed by cardiac enlargement and congestive heart failure. |
| Antibiotics | Macrolide antibiotics have been reported to cause a significant decrease in corticosteroid clearance. |
| Anticholinesterases | Concomitant use of anticholinesterase agents and corticosteroids may produce severe weakness in patients with myasthenia gravis. If possible, anticholinesterase agents should be withdrawn at least 24 hours before initiating corticosteroid therapy. |
| Anticoagulants, Oral | Co-administration of corticosteroids and warfarin usually results in inhibition of response to warfarin, although there have been some conflicting reports. Therefore, coagulation indices should be monitored frequently to maintain the desired anticoagulant effect. |
| Antidiabetics | Because corticosteroids may increase blood glucose concentrations, dosage adjustments of antidiabetic agents may be required. |
| Antitubercular Drugs | Serum concentrations of isoniazid may be decreased. Patients taking isoniazid should be closely monitored. |
| Cholestyramine | Cholestyramine may decrease the absorption of dexamethasone. |
| Cyclosporine | Corticosteroid clearance may be decreased, and plasma concentrations of cyclosporine may be increased through mutual inhibition of metabolism. Seizures have been reported in patients receiving high-dose corticosteroid and cyclosporine concurrently. Monitor cyclosporine levels closely; adjust dose of both medication if required. |
| Digitalis Glycosides | Patients on digitalis glycosides may be at increased risk of arrhythmias due to hypokalemia. |
| Ephedrine | Ephedrine may enhance the metabolic clearance of corticosteroids, resulting in decreased blood levels and lessened physiologic activity, thus requiring an increase in corticosteroid dosage. |
| Estrogens, Including Oral Contraceptives | Estrogens may decrease the hepatic metabolism of certain corticosteroids, thereby increasing their effect. |
| Gastrointestinal topicals, antacids, charcoal | A decrease in digestive absorption of glucocorticoids have been reported with prednisolone and dexamethasone. Therefore, glucocorticoids should be taken separately from gastrointestinal topicals, antacids or charcoal, with an interval between treatment of at least two hours. |
| Hepatic Enzyme Inducers, Inhibitors and Substrates | Drugs which induce cytochrome P450 3A4 (CYP 3A4) enzyme activity (e.g., barbiturates, phenytoin, carbamazepine, rifampin) may enhance the metabolism of corticosteroids and require that the dosage of the corticosteroid be increased. Drugs which inhibit CYP 3A4 (e.g., ketoconazole, macrolide antibiotics such as erythromycin) have the potential to result in increased plasma concentrations of corticosteroids. Dexamethasone is a moderate inducer of CYP 3A4. Co-administration with other drugs that are metabolized by CYP 3A4 (e.g., indinavir, erythromycin) may increase their clearance, resulting in decreased plasma concentration. |
| Insulin, sulfonylureas, metformin | Increase in blood glucose, with sometimes diabetic ketosis, since corticosteroids impair carbohydrate tolerance. Therefore, blood and urine self-monitoring should be reinforced by the patient, in particular at the start of treatment. |
| Ketoconazole | Ketoconazole has been reported to decrease the metabolism of certain corticosteroids by up to 60%, leading to increased risk of corticosteroid side effects. In addition, ketoconazole alone can inhibit adrenal corticosteroid synthesis and may cause adrenal insufficiency during corticosteroid withdrawal. |
| Nonsteroidal Anti-Inflammatory Agents (NSAIDs) | Concomitant use of NSAIDs and corticosteroids increases the risk of gastrointestinal side effects. Aspirin should be used cautiously in conjunction with corticosteroids in hypoprothrombinemia. The clearance of salicylates may be increased with concurrent use of corticosteroids. |
| Phenytoin | In post-marketing experience, there have been reports of both increases and decreases in phenytoin levels with dexamethasone co-administration, leading to alterations in seizure control. |
| Praziquantel | Decrease in praziquantel plasma concentrations, with a risk of treatment failure, due to its hepatic metabolism increased by dexamethasone. |
| Sultopride | Sultopride has been linked to ventricular arrhythmias, especially torsade de pointes. This combination is not recommended. |
| Thalidomide | Co-administration with thalidomide should be employed cautiously, as toxic epidermal necrolysis has been reported with concomitant use. |
| Vaccines | Patients on corticosteroid therapy may exhibit a diminished response to toxoids and live or inactivated vaccines due to inhibition of antibody response. Corticosteroids may also potentiate the replication of some organisms contained in live attenuated vaccines. Routine administration of vaccines or toxoids should be deferred until corticosteroid therapy is discontinued if possible. |
9 CLINICAL PHARMACOLOGY
Dexamethasone is a synthetic glucocorticoid. In physiologic doses, dexamethasone is administered to replace deficient endogenous hormones. In larger (pharmacological) doses, dexamethasone decreases inflammation and suppresses the immune response by multiple mechanisms. It also stimulates the erythroid cells of the bone marrow and lengthens the survival time of erythrocytes and platelets and possesses an antiemetic effect. In pharmacologic doses, systemically administered dexamethasone suppresses release of corticotropin (adrenocorticotropic hormone, ACTH) from the pituitary; thus, the adrenal cortex ceases secretion of endogenous corticosteroids (secondary adrenocortical insufficiency).
Pharmacokinetics
Most glucocorticoids in the form of free alcohols, ketones, cypionates or acetates are readily absorbed when administered orally. A water-soluble corticosteroid salt should be administered I.V. to achieve a rapid onset of action.
In animal studies, most glucocorticoids have been shown to be removed rapidly from blood and distributed to muscles, liver, skin, intestine and kidneys. Because only unbound drug is pharmacologically active, patients with low serum albumin concentrations may be more susceptible to the effects of glucocorticoids than patients with normal serum albumin concentrations. Glucocorticoids cross the placenta and may be distributed into breast milk.
Pharmacologically active compounds are metabolized primarily in the liver to biologically inactive compounds. Inactive metabolites, primarily glucuronides and sulfates, are excreted by the kidneys. Small amounts of the unmetabolized drug are excreted in urine and bile.
The peak effect after oral administration of dexamethasone is seen in 1 to 2 hours, and the duration of action is approximately 2.75 days. The plasma half-life of dexamethasone is 3 to 4.5 hours, while its biological half-life is 36 to 54 hours.
10 STORAGE, STABILITY AND DISPOSAL
Store at room temperature (15-30°C). Protect from light.
Keep out of reach and sight of children. Bring unused and expired prescription drugs to your local pharmacist for proper disposal.
11 PHARMACEUTICAL INFORMATION
Drug Substance
Proper Name: dexamethasone
Chemical Name: Pregna-1,4-diene-3,20-dione, 9-fluoro-11,17,21-trihydroxy-16-methyl-, (11β,16α)-9-Fluoro-11β,17,21-trihydroxy-16α-methylpregna-1,4-diene-3,20-dione
Molecular formula and molecular mass: C22H29FO5 and 392.47 g/mol
Structural formula:
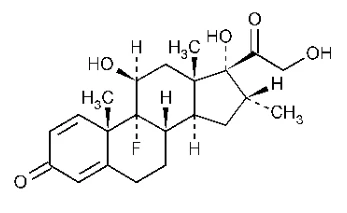
Physicochemical properties: Dexamethasone is a white to practically white, odorless, crystalline powder. Stable in air. Dexamethasone is insoluble in water, sparingly soluble in acetone and alcohol and methanol. It demonstrates a melting point at ~ 250°C with some decomposition.