


Product Monograph - Sugammadex Injection (Juno Pharma Canada)
RECENT MAJOR LABEL CHANGES
| 1 Indications, 1.1 Pediatrics | 05/2026 |
|---|---|
| 4 Dosage and Administration, 4.2 Recommended Dose and Dosage Adjustment, Pediatrics | 05/2026 |
| 7 Warnings and Precautions, 7.1.3 Pediatric | 05/2026 |
TABLE OF CONTENTS
Certain Sections or subsections that are not applicable at the time of the preparation of the most recent authorized product monograph are not listed.
RECENT MAJOR LABEL CHANGES .................................................................................................................... 2
TABLE OF CONTENTS ...................................................................................................................................... 2
PART I: HEALTH PROFESSIONAL INFORMATION .............................................................................................. 4
1 INDICATIONS ...................................................................................................................................... 4
1.1 Pediatrics ............................................................................................................................................4
1.2 Geriatrics .............................................................................................................................................4
2 CONTRAINDICATIONS ......................................................................................................................... 4
3 SERIOUS WARNINGS AND PRECAUTIONS BOX .................................................................................... 4
- 4.
DOSAGE AND ADMINISTRATION ......................................................................................................... 4
4.1 Dosing Considerations ....................................................................................................................4
4.2 Recommended Dose and Dosage Adjustment ...............................................................................5
4.3 Reconstitution ..............................................................................................................................7
4.4 Administration ..............................................................................................................................7
4.5 Missed Dose ........................................................................................................................................7
5 OVERDOSAGE ................................................................................................................................... 8
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ....................................................... 8
7 WARNINGS AND PRECAUTIONS .......................................................................................................... 8
7.1 Special Populations .......................................................................................................................... 11
7.1.1 Pregnant Women ........................................................................................................................ 11
7.1.2 Breast-feeding ............................................................................................................................. 11
7.1.3 Pediatrics ..................................................................................................................................... 11
7.1.4 Geriatrics ..................................................................................................................................... 12
8 ADVERSE REACTIONS ........................................................................................................................ 12
8.1 Adverse Reaction Overview........................................................................................................ 12
8.2 Clinical Trial Adverse Reactions ................................................................................................. 13
8.2.1 Clinical Trial Adverse Reactions – Pediatrics ........................................................................... 14
8.3 Less Common Clinical Trial Adverse Reactions ........................................................................... 15
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data 15
8.5 Post-Market Adverse Reactions ................................................................................................ 15
9 DRUG INTERACTIONS ....................................................................................................................... 15
9.1 Serious Drug Interactions ............................................................................................................ 15
9.2 Drug Interactions Overview ........................................................................................................ 15
9.3 Drug-Behavioural Interactions .................................................................................................... 15
9.4 Drug-Drug Interactions ................................................................................................................ 16
9.5 Drug-Food Interactions ............................................................................................................... 17
9.6 Drug-Herb Interactions ................................................................................................................ 17
9.7 Drug-Laboratory Test Interactions .............................................................................................. 17
10 CLINICAL PHARMACOLOGY ............................................................................................................... 17
10.1 Mechanism of Action .................................................................................................................. 17
10.2 Pharmacodynamics .................................................................................................................... 17
10.3 Pharmacokinetics ....................................................................................................................... 17
11 STORAGE, STABILITY AND DISPOSAL ................................................................................................. 20
12 SPECIAL HANDLING INSTRUCTIONS .................................................................................................. 20
PART II: SCIENTIFIC INFORMATION ............................................................................................................... 21
13 PHARMACEUTICAL INFORMATION ................................................................................................... 21
14 CLINICAL TRIALS ............................................................................................................................... 22
14.1 Trial Design and Study Demographics ......................................................................................... 22
14.2 Study Results - Adults .................................................................................................................. 28
14.3 Comparative Bioavailability Studies ............................................................................................ 34
14.4 Immunogenicity ........................................................................................................................... 34
14.5 Clinical Trials - Reference Biologic Drug ...................................................................................... 34
15 MICROBIOLOGY ............................................................................................................................... 34
16 NON-CLINICAL TOXICOLOGY ............................................................................................................ 34
16.1 Comparative Non-Clinical Pharmacology and Toxicology ........................................................... 35
17 SUPPORTING PRODUCT MONOGRAPHS ........................................................................................... 35
PATIENT MEDICATION INFORMATION .......................................................................................................... 36
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
Sugammadex Injection (sugammadex sodium) is indicated for:
reversal of moderate to deep neuromuscular blockade induced by rocuronium or vecuronium in adult and pediatric patients undergoing surgery.
1.1 Pediatrics
Based on the data submitted and reviewed by Health Canada, the safety and efficacy of sugammadex sodium in pediatric patients, aged birth to 17 years, have been established. (see 7.1.3 Pediatrics)
1.2 Geriatrics
Evidence from clinical studies and experience suggests that use in the geriatric population is not associated with clinically meaningful differences in safety or effectiveness. (see 7.1.4 Geriatrics)
2 CONTRAINDICATIONS
Sugammadex Injection is contraindicated in patients who are hypersensitive to this drug or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING.
Hypersensitivity reactions, ranging from isolated skin reactions to serious systemic reactions (i.e. anaphylaxis, or anaphylactic reactions), have occurred in individuals with or without prior exposure to sugammadex (see 3 SERIOUS WARNINGS AND PRECAUTIONS; 8.2 ADVERSE REACTIONS, Clinical Trial Adverse Reactions).
3 SERIOUS WARNINGS AND PRECAUTIONS BOX
Serious Warnings and Precautions
- Sugammadex Injection should be administered by trained healthcare providers familiar with the use, actions, characteristics, and complications of neuromuscular blocking agents (NMBA) and neuromuscular block reversal agents.
- Sugammadex Injection may cause hypersensitivity reactions, including anaphylaxis or anaphylactoid reactions, on first or subsequent exposure. Clinicians should take the necessary precautions for the possibility of such reactions (see 7 WARNINGS AND PRECAUTIONS, Hypersensitivity Reactions; 8.2 ADVERSE REACTIONS, Clinical Trial Adverse Reactions).
4. DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
- Sugammadex Injection should be administered by trained healthcare providers familiar with the use, actions, characteristics, and complications of neuromuscular blocking agents (NMBA) and neuromuscular block reversal agents.
Doses and timing of Sugammadex Injection administration should be based on monitoring for twitch
- responses and the extent of spontaneous recovery that has occurred.
- The recommended dose of Sugammadex Injection does not depend on the anesthetic regimen, but rather on the level of neuromuscular blockade to be reversed. The anesthetic regimen may affect the recovery of the respiratory function and the reversal of the neuromuscular blockade independent of the reversal with Sugammadex Injection.
The use of Sugammadex Injection to reverse neuromuscular blockade induced by other steroidal neuromuscular blockers is not recommended. It does not reverse the blockade induced by nonsteroidal neuromuscular blocking agents such as succinylcholine or benzylisoquinolinium compounds (e.g. atracurium and cisatracurium).
4.2 Recommended Dose and Dosage Adjustment
Pediatrics (birth-17 years of age): As for adults, the dose calculation is based on actual body weight.
A dose of 2 mg/kg Sugammadex Injection is recommended when spontaneous recovery has reached the reappearance of T2 (moderate blockade) following rocuronium or vecuronium induced neuromuscular blockade.
A dose of 4 mg/kg Sugammadex Injection is recommended for reversal of rocuronium or vecuronium induced blockade if spontaneous recovery has reached at least 1-2 post-tetanic counts (PTC), and there is no twitch response to train-of-four (TOF) stimulation (deep blockade).
Immediate reversal has not been studied in the pediatric population. Doses higher than 4 mg/kg are not recommended for routine reversal of neuromuscular blockade as they may be associated with higher incidence of hypersensitivity and other adverse reactions.
Adults: Sugammadex Injection can be used to reverse different levels of rocuronium or vecuronium induced neuromuscular blockade to recovery defined as a train-of-four (TOF) (T4/T1) ratio of 0.9. The dose calculation is based on actual body weight. (see 10.2 CLINICAL PHARMACOLOGY, Pharmacodynamics).
A dose of 2.0 mg/kg Sugammadex Injection is recommended when spontaneous recovery has reached the reappearance of T2 (moderate blockade) following rocuronium or vecuronium induced neuromuscular blockade.
A dose of 4.0 mg/kg Sugammadex Injection is recommended for reversal of rocuronium or vecuronium induced blockade if spontaneous recovery has reached at least 1-2 post-tetanic counts (PTC), and there is no twitch response to train-of-four (TOF) stimulation (deep blockade) following administration of rocuronium or vecuronium induced neuromuscular blockade.
A dose higher than 4 mg/kg Sugammadex Injection is not recommended for routine reversal of neuromuscular blockade induced by rocuronium or vecuronium, as it has not been studied and is possibly associated with higher incidence of hypersensitivity reactions.
Table 1: Sugammadex Injection Dosing Guide
Moderate blockade (Reappearance of second twitch [T2] on TOF) | 2 mg/kg |
|---|---|
Deep blockade (1-2 post-tetanic counts [PTCs]), TOF-count 0 | 4 mg/kg |
Following Rocuronium Only
For immediate reversal, a dose of 16 mg/kg Sugammadex Injection is recommended only if there is an urgent or emergent need to reverse neuromuscular blockade following administration of a single dose of 1.2 mg/kg rocuronium for intubation. The efficacy of 16 mg/kg sugammadex sodium for such use was studied in surgical patients without airway emergency. The efficacy of the 16 mg/kg dose of sugammadex sodium following administration of vecuronium has not been studied (see 10 CLINICAL PHARMACOLOGY)
This dose is associated with a 1-2% risk of an anaphylaxis in addition to higher frequencies of other less serious hypersensitivity reactions in studies of healthy volunteers (see 10 CLINICAL PHARMACOLOGY).
Waiting Times for Re-Administration of Neuromuscular Blocking Agents for Intubation Following Reversal with Sugammadex Injection: A minimum waiting time is necessary before administration of a steroidal neuromuscular blocking agent after administration of Sugammadex Injection. Recommendations are based upon a clinical study in healthy volunteers and simulations from a PK-PD model; the actual clinical patient response may vary significantly (see 10 CLINICAL PHARMACOLOGY).
If neuromuscular blockade is required before the recommended waiting time has elapsed, use a nonsteroidal neuromuscular blocking agent. The onset of a depolarizing neuromuscular blocking agent might be slower than expected, because a substantial fraction of postjunctional nicotinic receptors can still be occupied by the neuromuscular blocking agent.
For re-administration of rocuronium and vecuronium, the suggested minimum waiting time is outlined in the table below.
Table 2. Re-administration of rocuronium or vecuronium after routine reversal (up to 4 mg/kg Sugammadex Injection)
| Minimum Waiting time | NMBA and dose to be administered |
|---|---|
| 5 minutes | 1.2 mg/kg rocuronium |
| 4 hours | 0.6 mg/kg rocuronium or 0.1 mg/kg vecuronium |
When rocuronium 1.2 mg/kg is administered within 30 minutes after reversal with Sugammadex Injection, the onset of neuromuscular blockade may be delayed up to approximately 4 minutes and the duration of neuromuscular blockade may be shortened up to approximately 15 minutes.
For re-administration of rocuronium or administration of vecuronium after reversal of rocuronium with 16 mg/kg Sugammadex Injection, a waiting time of 24 hours is suggested.
Renal Impairment: Sugammadex Injection is not recommended for use in patients with severe (CrCl <30 mL/min) renal impairment including those requiring dialysis (see 7 WARNINGS AND PRECAUTIONS). No dose adjustment is necessary for patients with mild and moderate renal impairment (creatinine clearance between ≥30 and <80 mL/min; see 10.3 CLINICAL PHARMACOLOGY, Pharmacokinetics).
The recommended waiting time in patients with mild or moderate renal impairment for re - use of 0.6 mg/kg rocuronium or 0.1 mg/kg vecuronium after reversal with up to 4 mg/kg Sugammadex Injection should be 24 hours. If a shorter waiting time is required, the rocuronium dose for a new neuromuscular blockade should be 1.2 mg/kg.
Hepatic impairment: No dose adjustment is necessary in patients with any degree of hepatic impairment. Sugammadex Injection is mainly excreted renally. Recovery times may be prolonged (see 7 WARNINGS AND PRECAUTIONS). In patients with hepatic impairment accompanied by coagulopathy, hemostasis may be
- affected (see 7 WARNINGS AND PRECAUTIONS – Effect on hemostasis).
- Cardiac Patients: In patients with a history of cardiac disease (e.g., patients with ischemic heart disease, chronic heart failure, or arrhythmia), no dosage adjustment is necessary. General caution is advised, as these patients are more vulnerable (see 7 WARNINGS AND PRECAUTIONS).
- Pulmonary Patients: In patients with a history of pulmonary complications, no dosage adjustment is necessary. General caution is advised as these patients are more vulnerable (see 7 WARNINGS AND PRECAUTIONS).
Obese Patients: In obese patients, including morbidly obese patients, the dose of Sugammadex Injection should be calculated based on actual body weight. No dose adjustment is necessary.
4.3 Reconstitution
Not applicable.
4.4 Administration
Sugammadex Injection solution should be inspected visually for clarity, particulate matter, precipitation, discolouration, and leakage prior to administration.
Sugammadex Injection should be administered intravenously as a single bolus injection. The bolus injection should be given rapidly, within 10 seconds into an existing intravenous line. The infusion line should be adequately flushed (e.g. with 0.9 % sodium chloride) between administration of Sugammadex Injection and other drugs. Examine the site of intravenous line for any signs of leakage.
For pediatric patients, Sugammadex Injection 100 mg/mL may be diluted to a concentration of 10 mg/mL, using sodium chloride 9 mg/mL (0.9%), to increase the accuracy of dosing in the pediatric population. To prepare the required dose, aseptically transfer all the contents of the 2 mL single-dose vial of Sugammadex Injection (100 mg/mL) to a bottle (or intravenous bag) containing 18 mL of 0.9% sodium chloride injection in order to achieve a final concentration of 10 mg/mL sugammadex. The diluted solution can be stored up to 48 hours refrigerated (5°C) or at room temperature (25°C) (see 11 STORAGE, STABILITY AND DISPOSAL).
Sugammadex Injection can be injected into the intravenous line of a running infusion with the following intravenous solutions:
0.9% sodium chloride,
5% dextrose, Gelofusine,
0.45% sodium chloride and 2.5% dextrose,
Ringers lactate solution,
Ringers solution, Lactec,
Lactec D and G, Hespander,
Veen-F,
Physio 140,
5% dextrose and 0.9% sodium chloride and isolyte P with 5% dextrose.
Sugammadex Injection must not be mixed with other medicinal products except those listed above. Physical incompatibility was observed with verapamil, ondansetron and ranitidine.
4.5 Missed Dose
Not applicable.
5 OVERDOSAGE
In clinical studies, 1 case of an accidental overdose with 40 mg/kg was reported without any significant side effects. In a human tolerance study, sugammadex was tolerated well in doses up to 96 mg/kg. Sugammadex Injection can be removed using hemodialysis with a high flux filter, but not with a low flux filter. Based upon clinical studies, sugammadex concentrations in plasma are reduced by about 70% after a 3 to 6-hour dialysis session.
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 3 – Dosage Forms, Strengths, Composition and Packaging
| Route of Administration | Dosage Form / Strength | All Non-medicinal Ingredients |
|---|---|---|
| Intravenous | Solution for injection, 100 mg/mL (as sugammadex sodium) | hydrochloric acid (for pH adjustment), sodium hydroxide (for pH adjustment), water for injection |
Sugammadex Injection is supplied as a solution for injection containing 100 mg/mL of sugammadex as sugammadex sodium (108.8 mg/mL). Vials contain a clear and colorless to slightly yellow- brown solution. The pH is between 7 and 8 and osmolality is between 300 and 500 mOsm/kg.
100 mg/mL sugammadex is equivalent to 108.8 mg/mL of sugammadex sodium with up to 7 mg/mL mono-OH derivative.
Each vial of Sugammadex Injection contains the following inactive ingredients: hydrochloric acid (for pH adjustment) or sodium hydroxide (for pH adjustment), water for injection
Single use injection glass vials closed with bromobutyl stoppers. The stoppers are held in position on the glass vials by aluminium crimp-caps with a “flip-off” seal. The rubber stopper of the vial does not contain latex. Pack sizes contain presentations of 2 mL (10 vials) or 5 mL (10 vials per carton).
Description
Not applicable.
7 WARNINGS AND PRECAUTIONS
Please see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX.
General
Hypersensitivity Reactions:
A designated clinical trial in 375 healthy volunteers given up to 3 doses of placebo or sugammadex shows that sugammadex may cause hypersensitivity reactions, including on first exposure. The observed rates were 1.3% (1/76) on placebo, 6.6% (10/151) on 4 mg/kg, and 9.5% (14/148) on 16 mg/kg. One case of anaphylaxis was seen in the group on 16 mg/kg (0.7%, 1/148). Anaphylaxis and anaphylactoid reactions have also been reported in the post- marketing setting, including at doses in the range of 2 – 4 mg/kg. The most commonly described clinical features in reports of anaphylaxis were dermatologic symptoms (including urticaria, rash, erythema, flushing and skin eruption); and clinically important hypotension often requiring the use of vasopressors for circulatory support. In addition, prolonged hospitalization and/or the use of additional respiratory support until full recovery (re- intubation, prolonged intubation, manual or mechanical ventilation) have been noted in a number of the anaphylaxis reports.
The mechanism of the hypersensitivity reactions is not well understood. Laboratory indicators of a specific immune-mediated reaction may or may not be present.
Cardiovascular
- Marked Bradycardia:
Across all pediatric ages and adults,marked bradycardia has been observed within minutes after the administration of sugammadex for reversal of neuromuscular blockade. Some cases required medical intervention. Isolated cases of bradycardia with cardiac arrest have also been reported (see 8 ADVERSE REACTIONS). Patients should be closely monitored for hemodynamic changes during and after reversal of neuromuscular blockade. Treatment with anti-cholinergic agents such as atropine should be administered if clinically significant bradycardia is observed.
- Cardiac Electrophysiology:
Sugammadex administered at doses of up to twice the maximum recommended dose, does not have clinically relevant effects on the QTc interval (see 10.2 CLINICAL PHARMACOLOGY, Pharmacodynamics).
Hematologic
- Effect on Hemostasis:
Sugammadex doses up to 16 mg/kg were associated with limited (≤25%) and transient (≤1 hour) increases in the coagulation parameters activated partial thromboplastin time (aPTT) and prothrombin time international normalized ratio [PT(INR)] in healthy volunteers. In surgical patients concomitantly treated with an anticoagulant, small and transient increases were observed in aPTT and PT(INR) associated with sugammadex 4 mg/kg, which did not translate into an increased bleeding risk with sugammadex compared with usual treatment.
In in vitro experiments additional aPTT and PT (INR) prolongations were noted for sugammadex in combination with vitamin K antagonists, unfractionated heparin, low molecular weight heparinoids, rivaroxaban and dabigatran up to ~25% and ~50% at Cmax levels of sugammadex corresponding to 4 mg/kg and 16 mg/kg doses, respectively.
Since bleeding risk has not been studied systematically at higher doses than sugammadex 4 mg/kg, coagulation parameters should be carefully monitored according to routine clinical practice in patients with known coagulopathies and in patients using anticoagulants who receive a dose of sugammadex higher than 4 mg/kg.
Hepatic
In patients with hepatic impairment, recovery times may be prolonged. In patients with hepatic impairment accompanied by coagulopathy, hemostasis may be affected (see 7 WARNINGS AND PRECAUTIONS, Hematologic).
Neurologic
- Driving and Operating Machinery:
Sugammadex Injection is not expected to have an effect on alertness and concentration, or on the recovery from anesthetics. The patient’s ability to drive and use machines must be assessed based on adequate recovery of motor strength and coordination, as well as mental alertness and concentration. Exercise caution when driving or operating a vehicle or potentially dangerous machinery.
- Use in Intensive Care Unit (ICU):
Sugammadex has not been investigated in the ICU setting
Peri-Operative Considerations
- Anesthetic Complication:
The depth of anesthesia should be carefully monitored and maintained whenever a neuromuscular relaxant is used, as well as when its effects are reversed. If neuromuscular blockade is reversed while anesthesia is continued, anesthetic management may need to be adjusted as clinically indicated (see 8 ADVERSE REACTIONS).
When neuromuscular blockade was reversed in the middle of anesthesia in clinical trials, i.e. when investigating urgent reversal, signs of light anesthesia were noted occasionally (movement, coughing, grimacing and suckling of the tracheal tube).
Awareness under surgical anesthesia is a serious complication associated with excessive neuromuscular blockade without adequate analgesia and sedation. Excessive use of rocuronium or vecuronium may potentially obscure the signs of inadequate anesthesia. Its use without adequate management of the depth of anesthesia is associated with an increase frequency of this complication. Such practice should be avoided even when Sugammadex Injection can be used to accelerate the reversal of deep neuromuscular blockade induced by rocuronium or vecuronium.
After reversal of neuromuscular blockade with Sugammadex Injection, care must be taken to assess the recovery from the effects of the anesthetics, while observing any signs of hypersensitivity reactions. Clinical trial data indicate that the speed of emergence from anesthesia may vary considerably from patient to patient, depending on the residual effects of the anesthetics given during surgery.
- Delayed Recovery:
Prolonged recovery times after administration of Sugammadex Injection are possible. Patients should be monitored for adequate recovery. Conditions associated with prolonged circulation time such as cardiovascular disease, old age, severe renal impairment, or edematous state (e.g., severe hepatic impairment) may be associated with longer recovery times.
- Respiratory Function Monitoring During Recovery:
Ventilatory support is mandatory for patients until adequate spontaneous respiration on is restored following reversal of neuromuscular blockade. Even if recovery from neuromuscular blockade is complete, other medicinal products used in the peri - and postoperative period could depress respiratory function and therefore ventilatory support might still be required.
- Risk of Prolonged Neuromuscular Blockade:
In clinical trials, a small number of patients experienced a delayed or minimal response to the administration of sugammadex. Adequate anesthetic management, including ventilation support is mandatory until the patient has adequately emerged from anesthesia.
- Risk of Recurrence of Neuromuscular Blockade:
Patients should be monitored for recurrence of neuromuscular blockade after reversal. Should neuromuscular blockade reoccur following extubation, adequate ventilation should be provided. The use of lower than recommended doses may lead to an increased risk of recurrence of neuromuscular blockade after initial reversal and is not recommended (see 8 ADVERSE REACTIONS).
Renal Impairment
Sugammadex is known to be substantially excreted by the kidney and is not recommended for use in patients with severe renal impairment (creatinine clearance <30 mL/min) due to insufficient safety information combined with the prolonged and increased overall exposure in these patients [see 10.3 CLINICAL PHARMACOLOGY, Pharmacokinetics].
Effect of mild or moderate renal impairment (creatinine clearance ≥30 and ≤80 mL/min) on sugammadex PK and PD was obtained from a study in elderly patients. Although clearance of drug decreased in elderly subjects with mild and moderate renal impairment, there was no significant difference in the ability of sugammadex to reverse the pharmacodynamic effect of rocuronium. Hence, no dosage adjustment is necessary for mild and moderate renal impairment.
7.1 Special Populations
7.1.1 Pregnant Women
Surgery: No clinical data are available for the use of Sugammadex in pregnant women undergoing surgery.
Labour and Delivery: No clinical data are available for the use of Sugammadex in women during labour and delivery.
A series of repeat-dose reproductive safety studies were conducted in rats and rabbits. No teratogenicity was found at any doses studied during embryo-fetal development studies. In a prenatal and postnatal study, increased postnatal loss was found in drug treatment groups. No drug-related effects on parturition were observed. (see 16 NON-CLINICAL TOXICOLOGY, Reproductive Toxicology).
7.1.2 Breast-feeding
Excretion of sugammadex in human milk has not been studied. Sugammadex is excreted into milk in rats with a maximum level of 0.22% of the dose per gram milk, which decreases when plasma levels decrease. Oral exposure via milk does not induce any effects on survival, body weight and physical or behavioral developmental parameters monitored in newborn rats in peri- and postnatal development studies.
7.1.3 Pediatrics
Pediatrics (birth – 17 years of age):
Safety and efficacy data support the use of sugammadex for routine reversal in this patient population.
Immediate reversal has not been investigated in the pediatric population. Doses higher than 4 mg/kg are not recommended for routine reversal of neuromuscular blockade as they may be associated with higher incidence of hypersensitivity and other adverse reactions (see 4.2 Recommended Dose and Dosage Adjustment).
.
7.1.4 Geriatrics
In a clinical study in the elderly, after administration of sugammadex at reappearance of T2 following a rocuronium induced blockade, the median time to recovery of the T4/T1 ratio to 0.9 in adults (18-64 years) was 2.2 minutes, 2.6 minutes in elderly adults (65-74 years), and 3.6 minutes in very elderly adults (75 years or more). Even though the recovery times in elderly tend to be slower, the same dose recommendation as for adults should be followed (see 4.2 DOSAGE AND ADMINISTRATION, Recommended Dose and Dosage Adjustment).
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
Sugammadex was studied in healthy volunteers and surgical patients undergoing general anesthesia to reverse the neuromuscular blockade induced with rocuronium or vecuronium, in comparison with placebo or other reversal agents. The causality of adverse events is sometimes difficult to assess in these patients. The identified Serious Adverse Drug Reactions caused by sugammadex include anaphylaxis and hypersensitivity (see 2 CONTRAINDICATIONS; 7 WARNINGS AND PRECAUTIONS, Hypersensitivity) and marked bradycardia (see 7 WARNINGS AND PRECAUTIONS, Cardiovascular).
In the placebo-controlled dataset, the overall frequencies of all Adverse Events (AEs) were 70.7% on rocuronium plus sugammadex vs. 82.5% on rocuronium plus placebo; 88.7% on vecuronium plus sugammadex vs. 95.2% on vecuronium plus placebo. The individual AEs that occurred in at least 2.0% of sugammadex subjects and at least twice as frequently as in placebo subjects included cough (4.7% sugammadex, 2.0% placebo), airway complication of anesthesia (3.9% sugammadex, 0% placebo), anesthetic complication (3.4% sugammadex, 0.2% placebo), procedural hypotension (3.3% sugammadex, 1.7% placebo) and procedural complication (2.0% sugammadex, 0.6% placebo). In the active-controlled dataset, the overall AEs were 79.8% on rocuronium plus sugammadex vs. 84.2% on rocuronium plus neostigmine; 93.8% on vecuronium plus sugammadex vs. 94.0% on vecuronium plus neostigmine. The one AEs that occurred in at least 2.0% of sugammadex patients and at least twice as frequently as in neostigmine patients was hypertension (3.8% sugammadex, 1.5% neostigmine).
Pediatric Patients:
2 to 17 years of age:
The safety of sugammadex has been assessed in a randomized, active-controlled study of pediatric patients 2 to 17 years of age, with 242 receiving treatment with either 2 mg/kg or 4 mg/kg sugammadex. Adverse events occurring in ≥5% of pediatric patients were bradycardia/sinus bradycardia (10% in the 2 mg/kg group; 7% in the 4 mg/kg group), nausea (6% in the 4 mg/kg group), vomiting (8% in the 2 mg/kg group; 10% in the 4 mg/kg group), incision site pain (6% in the 2 mg/kg group), procedural nausea (8% in the 2 mg/kg group; 5% in the 4 mg/kg group), procedural pain (59% in the 2 mg/kg group; 58% in the 4 mg/kg group), and procedural vomiting (6% in the 2 mg/kg group). The safety profile was generally consistent with that observed in adults.
Birth to <2 years of age:
The safety of sugammadex has been assessed in a randomized, double-blinded, active comparator-controlled study of pediatric patients from birth to <2 years of age, with 138 receiving study treatment. Adverse events occurring in ≥5% of pediatric patients were vomiting (9% in the 2 mg/kg group), pyrexia (7% in the 2 mg/kg group), procedural pain (41% in the 2 mg/kg group; 54% in the 4 mg/kg group), and procedural vomiting (7% in the 2 mg/kg group). The safety profile was generally consistent with that observed in pediatric patients from 2 to <17 years of age and adults.
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials; therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
The data described below reflect 1078 subjects exposed to sugammadex and 544 to placebo in placebo-controlled trials, where subjects received anesthesia and/or neuromuscular blocking agent. The population was 18 to 91 years old, approximately equally divided between males and females, mostly ASA (American Society of Anesthesiologists) Class 1-3, and predominantly Caucasian. Most subjects on sugammadex received a single dose of 2 or 4 mg/kg.
The incidence of treatment-emergent adverse events was 74% with sugammadex and 82% for placebo. Treatment-emergent adverse events occurring in ≥2% of subjects treated with sugammadex and at least twice as often compared to placebo for adult subjects who received anesthesia and/or neuromuscular blocking agent in pooled Phase I -III studies are presented in Table 4.
Table 4: Treatment-Emergent Adverse Events Occurring in at Least 2% of Adult Sugammadex Patients in Pooled Phase I-III Studies and Twice as Often in Comparison with Placebo
| System Organ class | Treatment-Emergent Adverse Events (Preferred Term) | Sugammadex | Placebo | ||||
|---|---|---|---|---|---|---|---|
| (N=1078) | (N=544) | ||||||
| n (%) | n (%) | ||||||
| Injury, poisoning and procedural complications | Airway complication of anesthesia | 42 (4) | 0 (0) | ||||
| Anesthetic complication | 37 (3) | 1 (<1) | |||||
| Procedural hypotension | 36 (3) | 9 (2) | |||||
| Procedural complication | 22 (2) | 3 (1) | |||||
| Respiratory, thoracic and mediastinal, disorders | Cough | 51 (5) | 11 (2) | ||||
In clinical studies, the investigator reported terms for complications resulting from anesthesia or surgery were grouped in the adverse event categories below, and included the following:
- Airway Complication of Anesthesia:
Airway complications of anesthesia included bucking against the endotracheal tube, coughing, mild bucking, arousal reaction during surgery, coughing during the anesthetic procedure or during surgery, or contra breath (spontaneous breath of patient, anesthetic procedure related).
- Anesthetic Complication:
Anesthetic complications, indicative of the restoration of neuromuscular function, include movement of a limb or the body or coughing during the anesthetic procedure or during surgery, grimacing, or suckling on the endotracheal tube. (see 7 WARNINGS AND PRECAUTIONS, Anesthetic Complication)
- Procedural Complication:
Procedural complications included coughing, tachycardia, bradycardia, movement, and increase in heart rate.
The data described below reflect 871 subjects exposed to sugammadex and 881 to neostigmine in active-controlled trials, where subjects received anesthesia and a neuromuscular blocking agent. The population was 18 to 93 years old, approximately equally divided between males and females, all ASA (American Society of Anesthesiologists) Class 1-3, and predominantly Caucasian. Most subjects on sugammadex received a single dose of 2 or 4 mg/kg.
The overall incidence of treatment-emergent adverse events was 84% with sugammadex and 87% for neostigmine. The one adverse event that occurred in at least 2.0% of sugammadex patients and at least twice as frequently as in neostigmine patients was hypertension (3.8% sugammadex, 1.5% neostigmine).
Hypersensitivity Reactions:
Hypersensitivity reactions, including anaphylaxis, have occurred in clinical trials in patients and healthy volunteers (see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX; 7 WARNINGS AND PRECAUTIONS). In clinical trials of surgical patients these reactions were reported as infrequent (at least 1/1000, but less than 1/100) and for post-marketing reports the frequency is unknown. Anaphylaxis and anaphylactoid reactions have been reported in the post- marketing setting, including at doses in the range of 2 – 4 mg/kg. These reactions varied from isolated skin reactions to serious systemic reactions (i.e. anaphylaxis, anaphylactic shock) and have occurred in patients with no prior exposure to sugammadex. Symptoms associated with these reactions can include: flushing, urticaria, erythematous rash, (severe) hypotension, tachycardia, swelling of tongue, swelling of pharynx, bronchospasm and pulmonary obstructive events (see 7 WARNINGS AND PRECAUTIONS, Hypersensitivity).
Recurrence of Neuromuscular Blockade:
In clinical studies including subjects treated with rocuronium or vecuronium, in which sugammadex was administered as directed (N=2022), recurrence of neuromuscular blockade as measured by neuromuscular monitoring or clinical signs, was reported in 0.20% patients.
Bronchospasm:
In one dedicated clinical trial and in post-marketing data, in patients with a history of pulmonary complications, bronchospasm was reported as a possibly related adverse event.
Morbidly obese patients (BMI ≥ 40 kg/m2):
In one dedicated clinical trial in adult patients with a body mass index (BMI) ≥ 40 kg/m2 (morbidly obese), the adverse reaction profile was generally similar to the profile in adult patients in pooled Phase 1 to 3 studies (see Table 4).
8.2.1 Clinical Trial Adverse Reactions – Pediatrics
In a clinical study of pediatric patients aged 2 to <17 years, the incidence of bradycardia/sinus bradycardia reported in patients treated with sugammadex 2 mg/kg or 4 mg/kg was 10% and 7%, respectively (see 7 WARNINGS & PRECAUTIONS).
In a clinical study of pediatric patients aged birth to <2 years of age, the incidence of bradycardia reported in patients treated with sugammadex 2 mg/kg or 4 mg/kg was 2.3% (1/44 patients) and 3.2% (2/63 patients), respectively (7 WARNINGS AND PRECAUTIONS).
The safety profile of sugammadex (2 and 4 mg/kg) was otherwise generally consistent with that observed in adults. Adverse reactions reported for adults are also relevant for pediatric patients.
8.3 Less Common Clinical Trial Adverse Reactions
Not applicable.
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data
Not applicable.
8.5 Post-Market Adverse Reactions
The following adverse reactions have been identified during post-approval use of sugammadex. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure.
- Cardiac Disorders: Cases of marked bradycardia and bradycardia with cardiac arrest have been observed within minutes after administration of sugammadex (see 7 WARNINGS AND PRECAUTIONS). Other cardiac rhythm abnormalities have included atrial fibrillation, atrioventricular block, cardiac/cardiorespiratory arrest, ST segment changes, supraventricular tachycardia/ extrasystoles, tachycardia, ventricular fibrillation, and ventricular tachycardia.
- General Disorders and Administration Site Conditions: Cases of sugammadex not having the intended effect.
- Immune System Disorders: Hypersensitivity events including anaphylactic shock, anaphylactic reaction, anaphylactoid reaction, and Type 1 hypersensitivity have been reported.
- Respiratory, Thoracic, and Mediastinal Disorders: Events of laryngospasm, dyspnea, wheezing, pulmonary edema, and respiratory arrest have been reported.
9 DRUG INTERACTIONS
9.1 Serious Drug Interactions
Not applicable.
9.2 Drug Interactions Overview
The information reported is based on binding affinity between sugammadex and other drugs, preclinical experiments, simulations of a Pharmacokinetic-Pharmacodynamic (PK-PD) model and clinical studies. Based on these data, no clinically significant pharmacodynamic interaction with other drugs are expected, with the exception of toremifene, fusidic acid and hormonal contraceptives. For these drugs, a clinical relevant interaction could not be excluded.
Toremifene is not available in Canada.
No clinically relevant interactions were reported during clinical development including with anticholinesterases, such as neostigmine, pyridostigmine, and edrophonium, or muscarinic blockers, such as glycopyrrolate and atropine.
No formal interaction studies have been performed in the pediatric population. The interactions for adults and the warnings in 7 WARNINGS AND PRECAUTIONS should also be taken into account for the pediatric population.
9.3 Drug-Behavioural Interactions
Not applicable.
9.4 Drug-Drug Interactions
Potential Interactions that Potentiate the Effect of Rocuronium or Vecuronium
When drugs which potentiate neuromuscular blockade are used in the post-operative period special attention should be paid to the possibility of recurrence of neuromuscular blockade. Refer to the product monograph of rocuronium or vecuronium for a list of the specific drugs which potentiate neuromuscular blockade. In case recurrence of neuromuscular blockade is observed, the patient may require mechanical ventilation.
Interactions Potentially Affecting the Efficacy of Sugammadex Injection (see 10 CLINICAL PHARMACOLOGY)
Displacement interactions:
Pharmacokinetic-pharmacodynamic modelling indicated that administration of certain drugs after sugammadex, could displace rocuronium or vecuronium from sugammadex. As a result, recurrence of neuromuscular blockade might be observed. In this situation, the patient may require mechanical ventilation. Administration of the drug which caused displacement should be stopped in case of an infusion. The risk of displacement reactions will be at its highest during the period representing 3 times the half-life of sugammadex.
For the following drugs, displacement interactions could not be excluded:
Toremifene
For toremifene, which has a relatively high affinity for sugammadex and for which relatively high plasma concentrations might be present, some displacement of vecuronium or rocuronium from the complex with sugammadex could occur. The recovery of the T4/T1 ratio to 0.9 could therefore be delayed in patients who have received toremifene on the same day of the operation.
Intravenous Administration of Fusidic Acid
The use of fusidic acid in the pre-operative phase may give some delay in the recovery of the T4/T1 ratio to 0.9. However, no recurrence of neuromuscular blockade is expected in the post-operative phase, since the infusion rate of fusidic acid is over a period of several hours and the blood levels are cumulative over 2-3 days. Interactions with topical products containing fusidic acid are not expected.
Interactions Potentially Affecting the Efficacy of Other Drugs (see also 10 CLINICAL PHARMACOLOGY)
Capturing interactions:
Pharmacokinetic-pharmacodynamic modelling indicated that administration of sugammadex may result in binding (capturing) to certain drugs. As a result, these drugs could become less effective due to a lowering of the (free) plasma concentrations.
In this situation, the clinician is advised to consider the re-administration of the drug, the administration of a therapeutically equivalent drug (preferably from a different chemical class) and/or non-pharmacological interventions as appropriate.
Hormonal contraceptives
In a simulation performed with a PK/PD model, it was found that the interaction between 4 mg/kg sugammadex and a progestogen could lead to a decrease in progestogen exposure (34% of AUC) similar to the decrease seen when a daily dose of an oral contraceptive is taken 12 hours too late, which might lead to a reduction in effectiveness.
Therefore, the administration of a bolus dose of sugammadex is considered to be equivalent to one missed daily dose of oral contraceptives containing a progestogen. Capturing interactions with an estrogen, namely ethinyl estradiol, are not expected to be clinically relevant. Refer to the missed dose advice in the package insert of the oral contraceptive for any actions required if an oral contraceptive is taken on the same day that sugammadex is administered.
In the case of non-oral hormonal contraceptives, the patient must use an additional non hormonal contraceptive method for the next 7 days.
9.5 Drug-Food Interactions
Interactions with food have not been established.
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
- Interference with Laboratory Tests
Sugammadex Injection may interfere with the serum progesterone assay. Interference with the test was observed at sugammadex plasma concentrations of 100 µg/mL which is only observed up to a maximum of 30 minutes after a 16 mg/kg dose. sugammadex is not expected to interfere with an ethinyl estradiol assay.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
Sugammadex is a modified gamma cyclodextrin which is a Selective Relaxant Binding Agent. sugammadex encapsulates the neuromuscular blocking agents (NMBA) rocuronium and vecuronium and forms a complex with these agents in plasma. Following administration of sugammadex, a shift in the concentration gradient of the NMBA between the neuromuscular junction and plasma causes a redistribution of the NMBA away from the nicotinic receptor. It thereby reduces the amount of neuromuscular blocking agent available to bind to nicotinic receptors in the neuromuscular junction. This results in the reversal of neuromuscular blockade induced by rocuronium or vecuronium.
10.2 Pharmacodynamics
Sugammadex has been administered in doses ranging from 0.5 mg/kg to 16 mg/kg in dose response studies of rocuronium induced blockade (0.6, 0.9, 1.0 and 1.2 mg/kg rocuronium bromide with and without maintenance doses) and vecuronium induced blockade (0.1 mg/kg vecuronium bromide with or without maintenance doses) at different time points/depths of blockade. In these studies, a clear dose-response relationship was observed.
Cardiac Electrophysiology:
Based on a randomized, double-blind, placebo- and positive-controlled five-period crossover study, sugammadex administered at single intravenous doses of 4 mg/kg and 32 mg/kg does not have clinically relevant effects on the QTc interval, the QRS duration, the PR interval, or ventricular heart rate.
10.3 Pharmacokinetics
The sugammadex pharmacokinetic parameters were calculated from the total sum of non- complex-bound and complex-bound concentrations of sugammadex. Pharmacokinetic parameters as clearance and volume of distribution are assumed to be the same for non- complex-bound and complex-bound sugammadex in anesthetised subjects
Distribution:
The observed steady-state volume of distribution of sugammadex is 11 to 14 liters in adult patients with normal renal function (based on conventional, non-compartmental pharmacokinetic analysis). Neither sugammadex nor the complex of sugammadex and rocuronium bind to plasma proteins or erythrocytes, as was shown in vitro using male human plasma and whole blood. Sugammadex exhibits linear kinetics in the dosage range of 1 to 16 mg/kg when administered as an IV bolus dose.
Metabolism:
In preclinical and clinical studies, no metabolites of sugammadex have been observed and only renal excretion of the unchanged product was observed as the route of elimination.
Elimination:
In adult anaesthetized patients with normal renal function the elimination half-life (t ½) of sugammadex is about 2 hours and the estimated plasma clearance is about 88 mL/min. A mass balance study demonstrated that >90% of the dose was excreted within 24 hours. Ninety-six percent (96%) of the dose was excreted in urine, of which at least 95% could be attributed to unchanged sugammadex. Excretion via feces or expired air was less than 0.02% of the dose. Administration of sugammadex to healthy volunteers resulted in increased renal elimination of rocuronium complex.
Special Populations and Conditions
Pediatrics: The pharmacokinetics of sugammadex in pediatric patients have been evaluated in 2 clinical studies following administration of intravenous doses of 2 or 4 mg/kg sugammadex administered for reversal of moderate or deep neuromuscular blockade, respectively. In one study, sugammadex pharmacokinetic parameters were estimated in pediatric patients 2 to <17 years of age with patients enrolled into 3 age groups (2 to <6, 6 to <12 and 12 to <17 years of age). In a second study, sugammadex pharmacokinetic parameters were estimated in pediatric patients, aged birth to <2 years with patients enrolled into 4 age groups (birth to 27 days, 28 days to <3 months, 3 months to <6 months and 6 months to < 2 years).In pediatric patients, both clearance and volume of distribution increase with increasing age. Predicted pharmacokinetic parameters of sugammadex by age group and renal function based on compartmental modelling are presented in Table 5.
Geriatrics: Population pharmacokinetic analysis indicated that, beyond the effects of a decreased creatinine clearance, increased age has limited impact on sugammadex PK parameters (see 7 WARNINGS AND PRECAUTIONS).
Predicted pharmacokinetic parameters of sugammadex by age group and renal function based on compartmental modeling are presented in Table 5.
Renal Impairment: In a pharmacokinetic study comparing patients with severe renal impairment to patients with normal renal function, sugammadex levels in plasma were similar during the first hour after dosing and thereafter the levels decreased faster in the control group. Total exposure to sugammadex was prolonged, leading to 17-fold higher exposure in patients with severe renal impairment. Low concentrations of sugammadex are detectable for at least 48 hours post-dose in patients with severe renal impairment.
In a second study comparing subjects with moderate or severe renal impairment to subjects with normal renal function, sugammadex clearance progressively decreased and t 1/2 was progressively prolonged with declining renal function. Exposure was 2-fold and 5-fold higher in subjects with moderate and severe renal impairment, respectively. Sugammadex concentrations were no longer detectable beyond 7 days post-dose in subjects with severe renal impairment.
Predicted pharmacokinetic parameters of sugammadex by age group and renal function based on compartmental modelling are presented in Table 5.
- Hepatic Impairment: Sugammadex is not metabolized nor excreted by the liver; therefore, dedicated trials in patients with hepatic impairment have not been conducted.
- Sex: No pharmacokinetic differences between male and female subjects were observed.
- Ethnic Origin: In a study in healthy Japanese and Caucasian subjects no clinically relevant differences in pharmacokinetic parameters were observed. Limited data do not indicate differences in pharmacokinetic parameters in Black or African Americans.
Obesity: Population pharmacokinetic analysis of adult and elderly patients showed no clinically relevant relationship of clearance and volume of distribution with body weight.
In one clinical study in adult patients with a BMI ≥ 40 kg/m2 (morbidly obese), sugammadex 2 mg/kg and 4 mg/kg was dosed according to actual body weight (n=76) or ideal body weight (n=74). Sugammadex exposure increased in a dose-dependent, linear manner following administration according to actual body weight or ideal body weight. No clinically relevant differences in pharmacokinetic parameters were observed between these morbidly obese patients (BMI ≥ 40 kg/m2) and the general population.
Table 5: Summary of Sugammadex Pharmacokinetic Parameters Stratified by Age and Renal Function
| Selected patient characteristics | Mean Predicted PK parameters (CV*%) | |||
|---|---|---|---|---|
Demographics Age Body Weight | Renal function Creatinine clearance (mL/min) | Clearance (mL/min) | Volume of distribution at steady state (L) | Elimination half- life (h) |
| Adult | ||||
| Normal | ||||
| 100 | 84 (26) | 13 | 2.2 (23) | |
40 yrs 75 kg | ||||
| Impaired | ||||
| Mild | 50 | 48 (28) | 15 | 4.1 (25) |
| Moderate | 30 | 29 (28) | 15 | 7.0 (26) |
| Severe | 10 | 8.9 (27) | 16 | 23 (27) |
| Elderly | ||||
| Normal | ||||
| 80 | 73 (27) | 13 | 2.6 (25) | |
75 yrs 75 kg | ||||
| Impaired | ||||
| Mild | 50 | 48 (27) | 15 | 4.1 (25) |
| Moderate | 30 | 29 (26) | 15 | 6.9 (25) |
| Severe | 10 | 8.9 (28) | 16 | 23 (27) |
| Adolescent | ||||
| Normal | ||||
| 95 | 71 (27) | 10 | 2.0 (23) | |
15 yrs 56 kg | ||||
| Impaired | ||||
| Mild | 48 | 41 (28) | 11 | 3.8 (25) |
| Moderate | 29 | 25 (28) | 12 | 6.3 (25) |
| Severe | 9.5 | 7.4 (28) | 12 | 22 (28) |
| Middle Childhood | ||||
| Normal | ||||
| 60 | 39 (29) | 5.8 | 2.1 (24) | |
9 yrs 28 kg | ||||
| Impaired | ||||
| Mild | 30 | 21 (27) | 6.3 | 4.0 (25) |
| Moderate | 18 | 12 (28) | 6.5 | 6.8 (26) |
| Severe | 6.0 | 3.3 (28) | 6.7 | 25 (27) |
| Early Childhood | ||||
| Normal | ||||
| 37 | 22 (26) | 3.4 | 2.1 (24) | |
3.5 yrs 15 kg | ||||
| Impaired | ||||
| Mild | 18 | 11 (28) | 3.5 | 4.2 (25) |
| Moderate | 11 | 6.1 (27) | 3.6 | 7.6 (27) |
| Severe | 3.7 | 1.6 (27) | 3.7 | 28 (27) |
| Toddler | ||||
| Normal | ||||
| 28 | 16 (28) | 2.5 | 2.1 (24) | |
1.5 years 11 kg | ||||
| Impaired | ||||
| Mild | 14 | 7.6 (28) | 2.5 | 4.4 (26) |
| Moderate | 8.4 | 4.2 (28) | 2.6 | 7.9 (28) |
| Severe | 2.8 | 1.1 (27) | 2.6 | 29 (27) |
| Infant | ||||
| Normal | ||||
| 21 | 12 (28) | 1.8 | 2.2 (24) | |
6 months 7.9 kg | ||||
| Impaired | ||||
| Mild | 11 | 5.4 (27) | 1.9 | 4.6 (26) |
| Moderate | 6.4 | 2.9 (26) | 1.9 | 8.3 (26) |
| Severe | 2.1 | 0.76 (28) | 1.9 | 32 (27) |
| Neonate | ||||
| Normal | ||||
| 13 | 13 (28) | 1.1 | 1.3 (22) | |
15 days 3.8 kg | ||||
| Impaired | ||||
| Mild | 6.4 | 5.7 (26) | 1.1 | 2.7 (23) |
| Moderate | 3.9 | 3.1 (27) | 1.1 | 4.8 (26) |
| Severe | 1.3 | 0.77 (27) | 1.1 | 18 (26) |
*CV = coefficient of variation
11 STORAGE, STABILITY AND DISPOSAL
Store between 15˚C to 30˚C. Protect from light. When not protected from light, the vial should be used within 5 days.
12 SPECIAL HANDLING INSTRUCTIONS
Any unused product or waste material should be disposed of in accordance with local requirements.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Common name: sugammadex sodium
Chemical name: 6A,6B,6C,6D,6E,6F,6G,6H-octakis-S-(2-carboxyethyl)-
6A,6B,6C,6D,6E,6F,6G,6H-octathio-γ-cyclodextrin octasodium salt.
Molecular formula: C72H104O48S8Na8
Molecular mass: 2178.01
Structural formula:
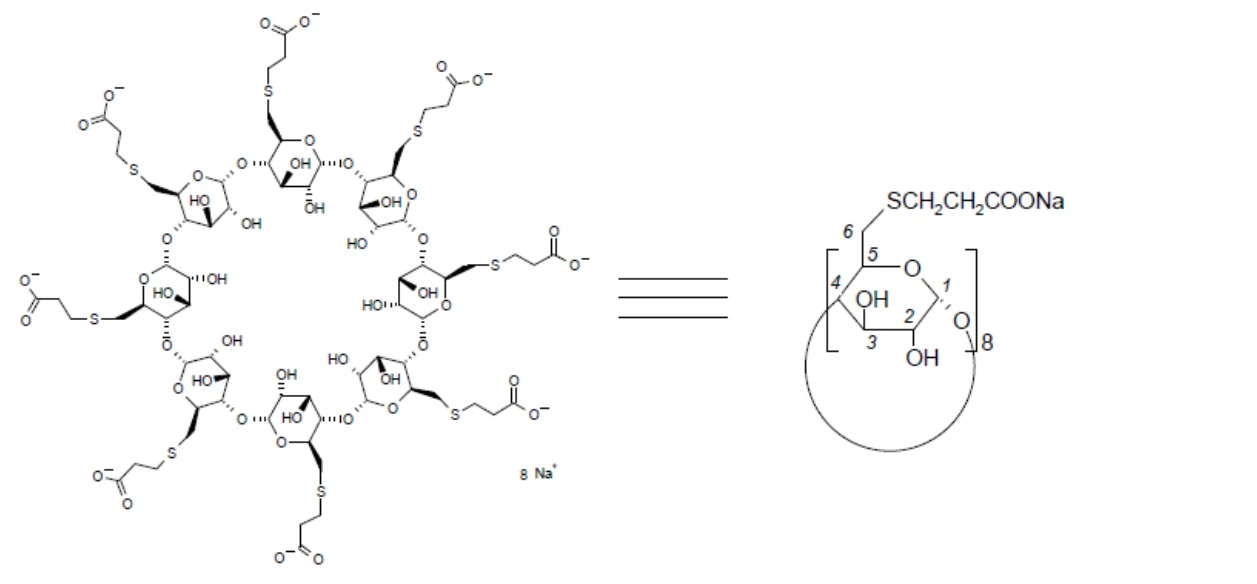
Sugammadex Injection may contain up to 7 mg/mL of the mono OH-derivative of sugammadex. This derivative is chemically designated as 6A,6B,6C,6D,6E,6F,6G-Heptakis-S-(2-carboxyethyl)- 6A,6B,6C,6D,6E,6F,6G-heptathio- γ -cyclodextrin sodium salt (1:7) with a molecular weight of 2067.90.
Physicochemical properties:
Appearance: Sugammadex sodium is a white to off-white powder to grainy powder.
Melting point: Sugammadex sodium is a compound without a melting point or melting range. It decomposes at approximately 220°C.
Solubility: Sugammadex sodium is highly soluble in water
pH: Approximately 7.5
14 CLINICAL TRIALS
14.1 Trial Design and Study Demographics
Table 6: Overview of Clinical Efficacy Trials
Protocol no. No. of centers (country) Trial status (start-end dates) | Trial objectives | Trial design | Dosage form, Dose, route, regimen, & duration | Diagnosis (inclusion criteria) | Enrolled/ treated/ completed, by trial arm | Gendera M/F | Age (yr)a Mean/median/ range | Primary endpoint |
|---|---|---|---|---|---|---|---|---|
Protocol no. No. of centers (country) Trial status (start-end dates) | Trial objectives | Trial design | Dosage form, Dose, route, regimen, & duration | Diagnosis (inclusion criteria) | Enrolled/ treated/ completed, by trial arm | Gendera M/F | Age (yr)a Mean/median/ range | Primary endpoint |
Protocol no. No. of centers (country) Trial status (start-end dates) | Trial objectives | Trial design | Dosage form, Dose, route, regimen, & duration | Diagnosis (inclusion criteria) | Enrolled/ treated/ completed, by trial arm | Gendera M/F | Age (yr)a Mean/median/ range | Primary endpoint |
19.4.301 13 centers (AT, BE, DE, ES, GB, IT, SE) Complete (November 2005 -March 2006) | To demonstrate faster recovery from rocuronium or vecuronium after reversal at reappearance of T2 by 2.0 mg/kg sugammadex compared to 50 µg/kg neostigmine, and to evaluate the safety of 2.0 mg/kg sugammadex and 50 µg/kg neostigmine | Multi-center, randomized, parallel group, comparative, active controlled safety- assessor blinded, pivotal trial | Sugammadex: 100 mg/mL Dose: 2.0 mg/kg iv, single dose Rocuronium bromide: 10 mg/mL Dose: 0.6 mg/kg + maintenance doses, iv Vecuronium bromide: 2 mg/mL Dose: 0.1 mg/kg + maintenance doses, iv Water for Injection: 10 mL ampoules Neostigmine/ glycopyrrolate (premix): 2.5 mg/mL neostigmine and 0.5 mg/mL glycopyrrolate Dose: 50 µg/kg iv, single dose | ASA class 1 to 4, aged ≥18, scheduled for surgical procedure in supine position with a general anesthesia with the use of rocuronium or vecuronium | Rocuronium+ sugammadex : 49/48/47 Rocuronium+ neostigmine: 49/48/47 Vecuronium + sugammadex : 51/48/47 Vecuronium + neostigmine 49/45/44 | Rocuronium + sugammadex : 31/17 Rocuronium + neostigmine: 24/24 Vecuronium + Sugammadex: 26/22 Vecuronium + neostigmine 21/24 | Rocuronium + sugammadex: 51/50/20-83 Rocuronium + neostigmine: 48/51/18-73 Vecuronium + sugammadex: 49/47/20-81 Vecuronium + neostigmine 50/51/21-81 | Time from start administration of IP to recovery of the T4/T1 ratio to 0.9 |
19.4.302 8 centers (USA) Complete (November 2005 - November 2006) | To demonstrate faster recovery from rocuronium or vecuronium after reversal at a block of 1- 2 PTCs by 4.0 mg/kg sugammadex compared with 70 µg/kg neostigmine and to evaluate the safety of a single dose of 4.0 mg/kg sugammadex and 70 µg/kg neostigmine | Multicenter, randomized, parallel group, comparative, active controlled, safety- assessor blinded trial | sugammadex: 100 mg/mL Dose: 4.0 mg/kg iv, single dose Rocuronium bromide: 10 mg/mL Dose: 0.6 mg/kg + maintenance doses, iv Vecuronium bromide: 1 mg/mL Dose: 0.1 mg/kg + maintenance doses, iv Sterile Water for Injection: 20 mL vials Neostigmine: 1 mg/mL Dose: 70 µg/kg iv, single dose Glycopyrrolate: 0.2 mg/mL Dose: 14 µg/kg iv, single dose | Aged 18 years old or older, ASA Class 1 to 4, scheduled to undergo an elective surgical procedure under general anesthesia in the supine position requiring the use of rocuronium or vecuronium for endotracheal intubation and maintenance of neuromuscular blockade | Rocuronium + sugammadex : 48/37/37 Rocuronium + neostigmine: 40/38/37 Vecuronium + sugammadex : 52/46/46 Vecuronium + neostigmine 42/36/35 | Rocuronium + sugammadex : 16/21 Rocuronium + neostigmine: 17/21 Vecuronium + sugammadex : 17/29 Vecuronium + neostigmine 21/15 | Rocuronium + sugammadex: 52/51/19-85 Rocuronium + neostigmine: 54/54/30-73 Vecuronium + sugammadex: 50/51/25-78 Vecuronium + neostigmine 57/60/29-77 | Time from start administration of IP to recovery of the T4/T1 ratio to 0.9 |
19.4.310 8 centers (ES, FR, GB, IT) Complete (Nov 2005- May 2006) | To show a faster recovery with sugammadex after rocuronium as compared to neostigmine after cisatracurium when administered at reappearance of T2, to evaluate the safety of a single dose of 2.0 mg/kg sugammadex and 50 µg /kg neostigmine administered in adult subjects and to show a faster onset of neuromuscular blockade after 0.6 mg/kg rocuronium as compared to 0.15mg/kg cisatracurium. | Multi-center, randomized, safety- assessor blinded, parallel group, active controlled comparative trial. | Sugammadex: 100 mg/mL. Dose 2.0 mg/kg iv single dose Rocuronium bromide: 10 mg/mL. Dose 0.6 mg/kg + maintenance doses, iv Cisatracurium besilate: 2 mg/mL Dose 0.15 mg/kg + maintenance doses, iv Neostigmine/gly -copyrrolate (premix): 2.5 mg/mL neostigmine and 0.5 mg/mL glycopyrrolate Dose 50 µg /kg, iv, single dose | Subjects of ASA class 1 to 4, above or equal to the age of 18 years; scheduled for surgical procedure under general anesthesia requiring neuromuscular relaxation with the use of rocuronium or cisatracurium; scheduled for surgical procedures in supine position | Rocuronium + sugammadex : 40/34/33 Cisatracuriu m + neostigmine: 44/39/39 | Rocuronium + sugammadex : 14/20 Cisatracurium + neostigmine: 23/16 | Rocuronium + sugammadex: 49/48/23-76 Cisatracurium + neostigmine: 42/40/22-69 | Time from start administration of IP to recovery of the T4/T1 ratio to 0.9 |
a Treated
Table 6b: Overview of Clinical Efficacy Trials (adult and pediatric)
Protocol no. No. of centers (country) Trial status (start-end dates) | Trial objective | Trial design | Dosage form Route | Diagnosis (inclusion criteria) | Number of patient (n) randomized/ treated/ completed by Age Group | Gendera M/F | Mean age (SD)a Median (range) | Primary endpoint |
|---|---|---|---|---|---|---|---|---|
Protocol no. No. of centers (country) Trial status (start-end dates) | Trial objective | Trial design | Dosage form Route | Diagnosis (inclusion criteria) | Number of patient (n) randomized/ treated/ completed by Age Group | Gendera M/F | Mean age (SD)a Median (range) | Primary endpoint |
19.4.306 6 (Germany, UK, Finland, France) Complete (May 2005 - May 2006) | dose-response relation of sugammadex given as a reversal agent at reappearance of T2 after 0.6 mg.kg-1 rocuronium in pediatric and adult subjects | multi-center, randomized, parallel dose-finding, safety- assessor blinded trial | Sugammadex: 100 mg/mL. iv single dose | Subjects of ASA class 1 – 2 (Scheduled for general anesthesia with an anticipated duration of anesthesia of at least 60 minutes, without further need for muscle relaxation other than one single dose of 0.6 mg.kg-1 rocuronium; Scheduled for surgical procedures in the supine position) | Infants 28 d to 23 m n = 2/2/2 n = 2/2/2 n = 1/1/1 n = 1/1/1 n= 2/2/2 Total n = 8/8/8 | time from start administratio n of IP to recovery of the T4/T1 ratio to 0.9 | ||
Dose 0.5 mg/kg 1.0 mg/kg 2.0 mg/kg 4.0 mg/kg Placebo | ||||||||
Dose 0.5 mg/kg 1.0 mg/kg 2.0 mg/kg iv 4.0 mg/kg Placebo | Children 2 – 11 yrs n = 6/6/6 n = 5/5/5 n = 5/5/5 n = 5/4/4 n = 5/4/4 Total n = 26/24/24 | 5/1 3/2 3/2 2/2 1/3 14/10 | 9 (3) 9 (3-11) 8 (2) 8 (6 – 10) 9 (2) 9 (6 – 11) 6 (3) 7 (2 – 9) 9 (1) 9 (7 – 10) 8 (2) 9 (2 - 11) | |||||
Dose 0.5 mg/kg 1.0 mg/kg 2.0 mg/kg iv Placebo | Adolescents 12 – 17 yrs n = 6/5/5 n = 6/6/6 n = 6/6/6 | 0/5 3/3 3/3 | 14 (1) 14 (13-15) 15 (2) 15 (12 – 17) 14 (0) 14 (14 – 15) | |||||
n = 6/8 b/8b n = 6/6/6 Total n = 30/31/31 | 4/4 3/3 13/18 | 14 (2) 15 (12 – 16) 15 (2) 15 (12 – 17) 14 (1) 15 (12 – 17) | ||||||
Dose 0.5 mg/kg 1.0 mg/kg 2.0 mg/kg iv 4.0 mg/kg Placebo | Adults 18 - 61yrs n = 6/6/6 n = 6/5/4 n = 6/5/5 n = 6/6/6 n = 6/5/5 Total n = 30/28/27 | 4/2 3/2 4/1 4/2 6/0 21/7 | 41 (17) 46 (20-59) 37 (8) 35 (28-48) 38 (10) 39 (23-51) 38 (14) 40 (18-59) 49 (12) 51 (27-61) 41 (13) 42 (18-61) | |||||
Table 6c: Overview of Pediatric Clinical Efficacy Trials
| Protocol no. | Trial objective | Trial Design | Dose | Diagnosis | Number of patients (n) treated by age group | Gender M/F | Mean age (SD) Median range | Primary endpoint | |
|---|---|---|---|---|---|---|---|---|---|
| P089 | safety and efficacy in reversing both moderate and deep block after rocuronium
-induced NMB | Multi-center, randomized, double- blinded, parallel group, active controlled comparative trial. | 2.0 mg/kg 4.0 mg/kg Neostigmine + (glycopyrrolat e or Atropine) | categorized as ASA Physical Status Class 1, 2, or 3 | 2 to <6 yrs n = 22 n = 80 n = 12 Total n = 114 | 153/123 | 7.7 (4.6) 7.0 (2 to 16) | Time to Recovery of the TOF Ratio ≥ 0.9 | |
2.0 mg/kg 4.0 mg/kg Neostigmine + (glycopyrrolat e or Atropine) | 6 to <12 yrs n = 15 n = 64 n = 13 Total n = 92 | 7.8 (4.4) 7.0 (2 to 16) | |||||||
2.0 mg/kg 4.0 mg/kg Neostigmine + (glycopyrrolat e or Atropine) | 12 to <17 yrs n = 14 n = 47 n = 19 Total n = 70 | 8.5 (4.3) 8.0 (2 to 16) | |||||||
| P169 | safety and efficacy in reversing moderate or deep block after rocuronium
vecuronium -induced NMB | Multi-center, randomized, double-blinded, parallel group, active controlled comparative trial. | 2.0 mg/kg 4.0 mg/kg Neostigmine + (glycopyrrolat e or Atropine) | categorized as ASA Physical Status Class 1, 2, or 3 | Birth to 27 days n = 11 n = 12 n = 5 Total n = 28 | 92/46 | 164.3 (168.0) 100.5 (1 to 720) | Time to neuromuscular recovery | |
2.0 mg/kg 4.0 mg/kg Neostigmine + (glycopyrrolat e or Atropine) | 28 days to <3 mos n = 9 n = 17 n = 9 Total n = 35 | ||||||||
2.0 mg/kg 4.0 mg/kg Neostigmine + (glycopyrrolat e or Atropine) | 3 mos to <6 mos n = 10 n = 19 n = 8 Total n = 37 | ||||||||
2.0 mg/kg 4.0 mg/kg Neostigmine + (glycopyrrolat e or Atropine) | 6 mos to <2 yrs n = 14 n = 15 n = 9 Total n = 38 | ||||||||
a Treated
b subject was randomized into the wrong age category
14.2 Study Results - Adults
Sugammadex Injection can be administered to reverse moderate to deep neuromuscular blockade induced with rocuronium or vecuronium bromide:
Reversal of Moderate Neuromuscular Blockade (Reappearance of T2)
Study 19.4.301 was conducted in patients that underwent elective laparoscopic or open surgical procedures that required general anesthesia. The surgical procedures were mainly endocrine, ocular, ENT, abdominal (gynecological, colorectal, urological) orthopedic, vascular, or dermatological in nature. Patients were randomly assigned to the rocuronium or vecuronium group. After the last dose of rocuronium or vecuronium, at the reappearance of T2, 2.0 mg/kg sugammadex or 50 mcg/kg neostigmine was administered randomly as a single bolus injection. The time from start of administration of sugammadex or neostigmine to recovery of the T4/T1 ratio to 0.9 was assessed (Table 7).
Table 7: Time (minutes) from administration of Sugammadex or neostigmine at reappearance of T2 after rocuronium or vecuronium to recovery of the T4/T1 ratio to 0.9
| Neuromuscular blocking agent | Treatment regimen | p-value* | ||||||
|---|---|---|---|---|---|---|---|---|
| Sugammadex (2.0 mg/kg) | Neostigmine (50 mcg/kg) | |||||||
| Rocuronium | ||||||||
| N | 48 | 48 | ||||||
| Geometric mean (95% CI) | 1.5 (1.3 – 1.7) | 18.5 (14.3 – 23.9) | <0.0001 | |||||
| Median (range) | 1.4 (0.9-5.4) | 17.6 (3.7-106.9) | ||||||
| Vecuronium | ||||||||
| N | 48 | 45 | ||||||
| Geometric mean (95% CI) | 2.8 (2.3 – 3.4) | 16.8 (12.9 – 21.9) | <0.0001 | |||||
| Median (range) | 2.1 (1.2-64.2) | 18.96 (2.9-76.2) | ||||||
*p-value obtained from a 2-way ANOVA on log transformed times to recovery of the T4/T1 ratio to 0.9
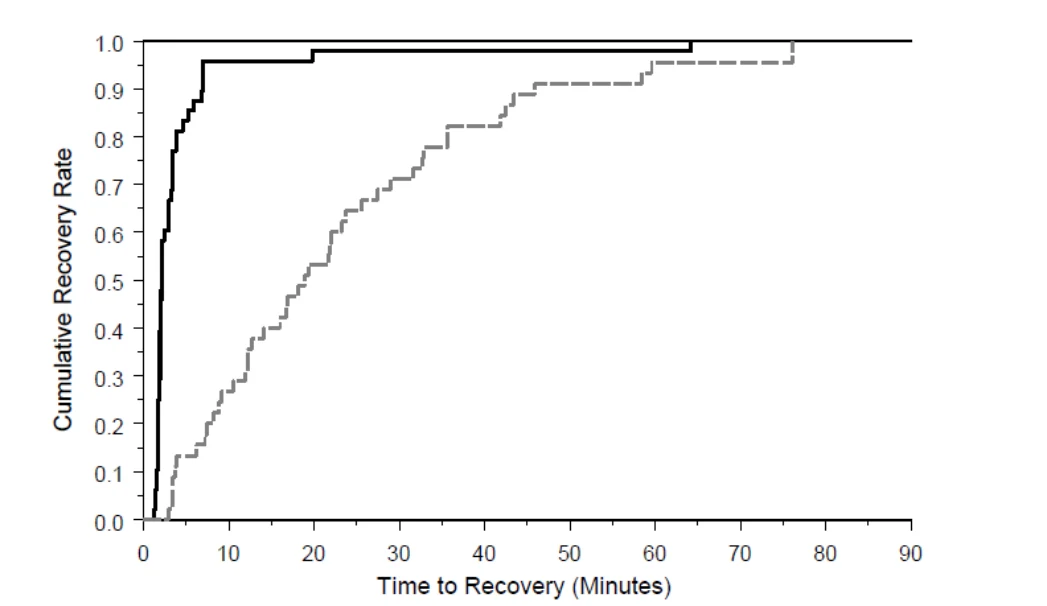
Return of the T4/T1 ratio to 0.9 after the reappearance of T2 was overall faster with sugammadex 2 mg/kg as compared to neostigmine 50 mcg/kg in the setting of rocuronium or vecuronium- induced neuromuscular blockade (Figures 1 and 2). The data were out of normal distribution. They were log transformed for ANOVA analysis. Correlation between T4/T1 ratio ≥ 0.9 with clinically sufficient recovery from neuromuscular blockade endpoints is uncertain.
Figure 1: Time (Minutes) from Administration of Sugammadex or Neostigmine at the Reappearance of T2 after Rocuronium to Recovery of the T4/T1 Ratio to 0.9
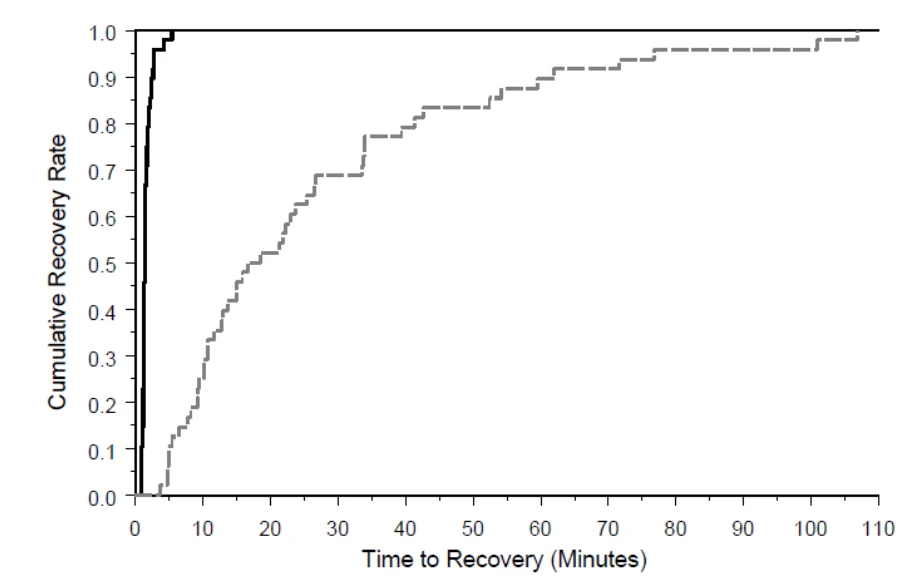
Figure 2: Time (Minutes) from Administration of Sugammadex or Neostigmine at the Reappearance of T2 after Vecuronium to Recovery of the T4/T1 Ratio to 0.9
Rocuronium plus: sugammadex 2 mg/kg (N=48) neostigmine 0.05 mg/kg (N=48)
In study 19.4.310, reversal by sugammadex of the neuromuscular blockade induced by rocuronium was compared to the reversal by neostigmine of the neuromuscular blockade induced by cis - atracurium. Patients underwent elective laparoscopic or open surgical procedures that required general anesthesia. The surgical procedures were mainly abdominal, ENT, orthopedic, or reconstructive in nature. At the reappearance of T2 a dose of 2.0 mg/kg sugammadex or 50 mcg/kg neostigmine was administered as a single bolus injection. The time from start of administration of sugammadex or neostigmine to recovery of the T4/T1 ratio to 0.9 was assessed (Table 7). Correlation between T4/T1 ratio ≥ 0.9 with clinically sufficient recovery from neuromuscular blockade endpoints is uncertain. Table 8 shows that sugammadex provided faster reversal of neuromuscular blockade induced by rocuronium compared to neostigmine reversal of neuromuscular blockade induced by cis-atracurium.
Table 8: Time (minutes) from Administration of Sugammadex or Neostigmine at Reappearance of T2 after Rocuronium or Cis-atracurium to recovery of the T4/T1 Ratio to 0.9
| Neuromuscular blocking agent | Treatment regimen | p-value* | ||||
|---|---|---|---|---|---|---|
| Rocuronium (0.6 mg/kg) and sugammadex (2.0 mg/kg) | Cis-atracurium (0.15 mg/kg) and neostigmine (50 mcg/kg) | |||||
N Geometric mean (95% CI) Median (range) | 34 2.0 (1.7-2.4) 1.9 (0.7-6.4) | 39 8.8 (7.4-10.4) 7.2 (4.2-28.2) | <0.0001 | |||
*p-value obtained from a 2-way ANOVA on log transformed times to recovery of the T4/T1 ratio to 0.9
Reversal of Deep Neuromuscular Blockade
In study 19.4.302, patients underwent elective laparoscopic or open surgical procedures that required
Vecuronium plus: sugammadex 2 mg/kg (N=48) neostigmine 0.05 mg/kg (N=45)
general anesthesia. The surgical procedures were mainly abdominal (gynecological, colorectal, urological), orthopedic, reconstructive, or neurological in nature. Patients were randomly assigned to the rocuronium or vecuronium group. After the last dose of rocuronium or vecuronium, at 1-2 PTCs, 4.0 mg/kg sugammadex or 70 mcg/kg neostigmine was administered in a randomized order as a single bolus injection. The time from start of administration of sugammadex or neostigmine to recovery of the TOF (T4/T1) ratio to 0.9 was assessed (Table 9).
Table 9:Time (minutes) from Administration of Sugammadex or Neostigmine at deep neuromuscular blockade (1-2 PTCs) after Rocuronium or Vecuronium to Recovery of the T4/T1 Ratio to 0.9
Neuromuscular blocking agent | Treatment regimen | p-value* | |||||
|---|---|---|---|---|---|---|---|
Sugammadex (4.0 mg/kg) | Neostigmine (70 mcg/kg) | ||||||
| Rocuronium | |||||||
| N | 37 | 37 | |||||
| Geometric mean (95% CI) | 2.9 (2.5-3.4) | 50.4 (43.5-58.4) | <0.0001 | ||||
| Median (range) | 2.7 (1.2-16.1) | 49.0 (13.3-145.7) | |||||
| Vecuronium | |||||||
| N | 47 | 36 | |||||
| Geometric mean (95% CI) | 4.5 (3.3-6.0) | 66.2 (55.6-78.9) | <0.0001 | ||||
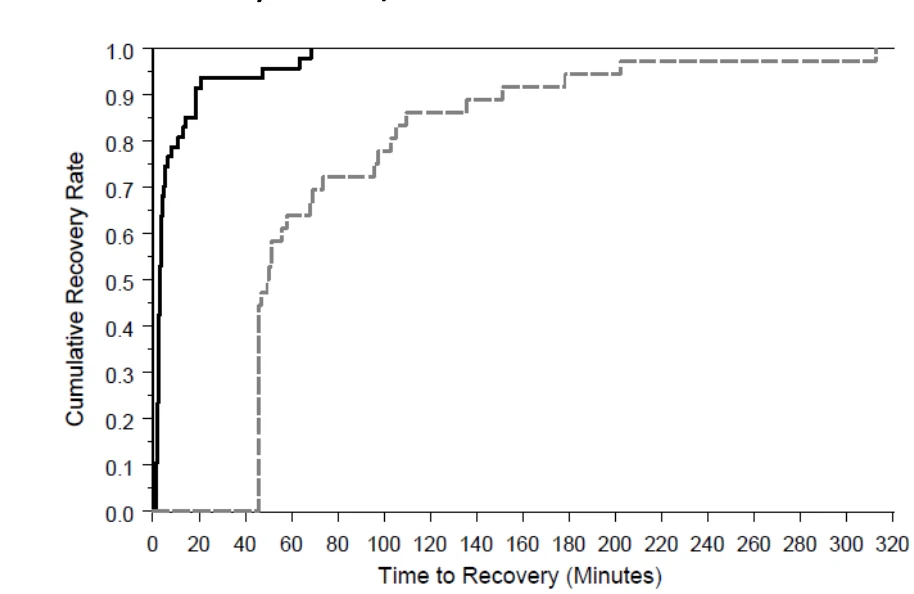
| Median (range ) | 3.3 (1.4-68.4) | 49.9 (46.0-312.7) | |||||
*p-value obtained from a 2-way ANOVA on log transformed times to recovery of the T4/T1 ratio to 0.9
Sugammadex 4 mg/kg provided faster reversal of deep neuromuscular blockade induced by rocuronium or vecuronium compared to neostigmine 70 mcg/kg (Figures 3 and 4). The data were out of normal distribution. They were log transformed for ANOVA analysis. Correlation between T4/T1 ratio ≥ 0.9 with clinically sufficient recovery from neuromuscular blockade endpoints is uncertain.
Figure 3: Time (Minutes) from Administration of Sugammadex or Neostigmine at 1 to 2 PTCs after Rocuronium to Recovery of the T4/T1 Ratio to 0.9
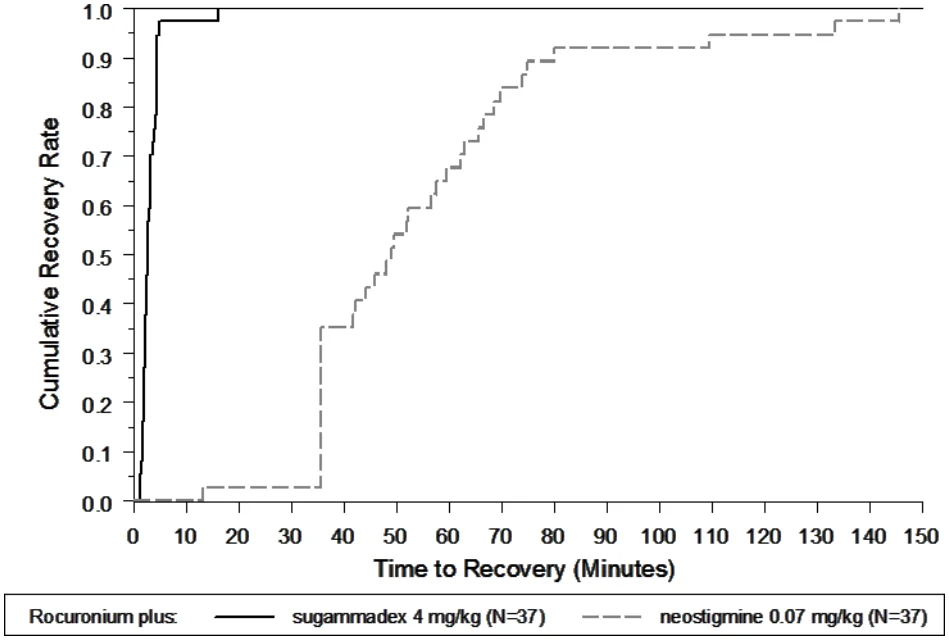
Figure 4: Time (Minutes) from Administration of Sugammadex or Neostigmine at 1 to 2 PTCs after Vecuronium to Recovery of the T4/T1 Ratio to 0.9
Morbidly obese patients (BMI ≥ 40 kg/m2):
A trial of 188 adult patients who were diagnosed as morbidly obese (body mass index ≥ 40 kg/m2) investigated the time to recovery from moderate or deep neuromuscular blockade induced by rocuronium or vecuronium. Patients received 2 mg/kg or 4 mg/kg sugammadex, as appropriate for level of block, dosed according to either actual body weight or ideal body weight in random, double-blinded fashion. Pooled across depth of block and neuromuscular blocking agent, the median time to recover to a train-of-four
Vecuronium plus: sugammadex 4 mg/kg (N=47) neostigmine 0.07 mg/kg (N=36)
(TOF) ratio ≥ 0.9 in patients dosed by actual body weight (1.8 minutes) was statistically significantly faster (p < 0.0001) compared to patients dosed by ideal body weight (3.3 minutes).
Study results - Pediatrics
For routine reversal of rocuronium or vecuronium induced blockade at reappearance of T2 in pediatric patients (birth to 17 years) 2 mg/kg sugammadex is recommended.
A dose of 4 mg/kg sugammadex is recommended for routine reversal of rocuronium or vecuronium induced blockade if recovery has reached at least 1-2 post-tetanic counts (PTC).
Immediate reversal has not been investigated in the pediatric population.
2 to <17 years of age:
A trial of 288 patients aged 2 to < 17 years investigated the safety and efficacy of sugammadex versus neostigmine as a reversal agent for neuromuscular blockade induced by rocuronium or vecuronium. Recovery from moderate block to a TOF ratio of ≥ 0.9 was significantly faster in the sugammadex 2 mg/kg group compared with the neostigmine group (geometric mean of 1.6 minutes for sugammadex 2 mg/kg and 7.5 minutes for neostigmine, ratio of geometric means 0.22, 95 % CI (0.16, 0.32), (p<0.0001)). Sugammadex 4 mg/kg achieved reversal from deep block with a geometric mean of 2.0 minutes, similar to results observed in adults. These effects were consistent for all age cohorts studied (2 to < 6; 6 to < 12; 12 to < 17 years of age) and for both rocuronium and vecuronium.
Birth to <2 years of age:
A total of 138 patients aged birth to < 2 years of age were treated in a randomized, double-blind, parallel-group, active-controlled trial to investigate the safety and efficacy of sugammadex versus neostigmine as a reversal agent for neuromuscular blockade induced by rocuronium or vecuronium. The primary efficacy endpoint, time to neuromuscular recovery, was significantly faster (p=0.0002) in participants dosed with sugammadex 2 mg/kg (median of 1.4 minutes) compared with neostigmine (median of 4.4 minutes). Following deep neuromuscular blockage, administration of sugammadex 4 mg/kg led to neuromuscular recovery with a median of 1.1 minutes. These effects were similar for all age cohorts studied (birth to 27 days; 28 days to <3 months; 3 months to <6 months and 6 months to <2 years).
Table 10: Time (minutes) to Neuromuscular Recovery (Sugammadex [2.0 mg/kg] vs Neostigmine + [Glycopyrrolate or Atropine]) for the reversal of moderate blockade. Sugammadex [4.0 mg/kg] was used for the reversal of deep blockade.
| Treatment regimen | p-value* sugammadex 2 mg/kg vs Neostigmine | |||
sugammadex (2.0 mg/kg) | sugammadex (4.0 mg/kg) | Neostigmine + (Glycopyrrolate or Atropine) | ||
| All patients | 0.0002 | |||
| N | 29 | 31 | 31 | |
| Geometric mean (95% CI) | 1.9 (1.1-2.0) | 1.1 (0.6-1.3) | 5.0 (2.7-7.9) | |
| Median (range) | 1.4 (0.6-121.0) | 1.1 (0.4-36.9) | 4.4 (0.8-269.7) | |
| Vecuronium | -- | |||
| N | 8 | 12 | 12 | |
| Geometric mean (95% CI) | 4.0 (1.0-15.6) | 1.8 (0.9-3.7) | 4.0 (2.2-7.4) | |
| Median (range) | 2.2 (1.0-121.0) | 1.9 (0.4-36.9) | 5.3 (0.8-17.3) | |
| Rocuronium | ||||
| -- | N | 21 | 19 | 19 |
| Geometric mean (95% CI) | 1.5 (1.0-2.1) | 0.8 (0.6-1.0) | 5.8 (3.3-10.3) | |
| Median (range) | 1.2 (0.6-8.4) | 0.7 (0.4-2.5) | 4.4 (1.2-269.7) | |
* Two-sided p-value based on log-rank test stratified by neuromuscular blocking agent and age group.
14.3 Comparative Bioavailability Studies
Not applicable.
14.4 Immunogenicity
Not applicable.
14.5 Clinical Trials - Reference Biologic Drug
Not applicable.
15 MICROBIOLOGY
Not applicable.
16 NON-CLINICAL TOXICOLOGY
General Toxicology: Sugammadex is rapidly cleared in preclinical species, although some sugammadex is observed in bone and teeth of juvenile rats. Preclinical studies in young adult and mature rats demonstrate that sugammadex has no adverse effect on tooth color or bone quality, bone structure or bone metabolism. Sugammadex has no effect on fracture repair and fracture remodelling in rats.
Sugammadex is well tolerated in repeat dose, intravenous toxicology studies of 4-weeks duration in rats at 500 mg/kg/day and in dogs at 250 mg/kg/day. Vacuolation of renal tubular epithelium and/or transitional epithelium of the urinary bladder is consistent with high-dose, parenteral administration of a cyclodextrin in nonclinical species. However, daily administration of sugammadex has no effect on renal function and does not alter tissue morphology.
Carcinogenicity: Carcinogenicity has not been evaluated, given the intended use of sugammadex and absence of genotoxic potential.
Genotoxicity: Sugammadex did not induce gene mutations or chromosome aberrations in vivo or in vitro.
Reproductive and Developmental Toxicology: Sugammadex did not impair male or female fertility in rats at 500 mg/kg/day representing approximately 6- to 50-fold greater exposures as compared to human exposures at recommended dose levels. Further, no morphological alterations of male and female reproductive organs were noted in 4-week toxicity studies in rats and dogs. Sugammadex was not teratogenic in rat and rabbit.
A fertility and early embryonic development study in Sprague-Dawley rats in which male rats were treated daily for 29 days prior to mating and through the mating period and female rats were treated daily for 14 days prior to mating to Day 5 post-coitum via intravenous administration of sugammadex at 20, 100, and 500 mg/kg (0.2, 1, and 6 times the MRHD of 16 mg/kg, respectively, based on AUC comparison) did not show adverse effects on fertility.
In an embryofetal development study in rats, pregnant animals received daily intravenous administration of sugammadex at 0, 20, 100, and 500 mg/kg (0.2, 1, and 6-times the MRHD of 16 mg/kg/day, respectively, based on AUC comparison) during organogenesis (Gestational Days 6 - 17). No treatment related maternal and embryofetal changes were observed.
In another embryofetal development study, pregnant New Zealand white rabbits received daily intravenous administration of sugammadex at 0, 20, 65, 200 mg/kg (0.6, 2, and 8 times the MRHD, respectively, based on AUC comparison) during organogenesis (Gestational Days 6- 18). Fetal body weight decreases (10 and 14%, respectively) were observed in the offspring at maternal doses of 65 mg/kg and 200 mg/kg. In addition, incomplete ossification of sternebra, and unossified 1st metacarpal were noted at a maternal dose of 200 mg/kg/day. Maternal toxicity was also observed at 200 mg/kg. Considering the observed effects of sugammadex on bone, it is possible that these findings may be attributable to drug. There was no evidence of teratogenicity at any dose.
Special Toxicology: Bone and teeth retention of sugammadex occurred in rats after intravenous injection, with mean half-lives of 172 and 8 days, respectively. Sugammadex bound to hydroxyapatite in an in vitro study and distributed in the bone formation area where hydroxyapatite is present for mineralization in vivo.
In adult rat bone toxicity studies, a single dose of sugammadex at 2000 mg/kg (approximately 24 times the maximum recommended human dose (MRHD) of 16 mg/kg by AUC comparison) administered to adult rats caused a slight increase in bone resorption, but had no effect on teeth color. No adverse bone effects were seen following a single dose of sugammadex at 500 mg/kg (4 times the MRHD dose of 16 mg/kg based on plasma AUC comparison).
In a bone repair study, adult rats were treated with intravenous sugammadex weekly for 6 weeks at 0, 30, 120, and 500 mg/kg (approximately 0.4, 1, and 6 times the MRHD, respectively, by AUC comparison). Based on histological data, high dose animals with post-fracture treatment, showed a statistically significant increase in callus formation and decrease in bone formation, suggesting a potential for a slight delay in the bone healing process. However, there were no statistically significant effects on bone volume or bone mineral density.
Juvenile Toxicity: In a bone deposition study, sugammadex concentrations were significantly higher in juvenile rats compared to adult rats (13% vs. 3% of the administered dose, respectively) following a single intravenous (IV) dose at 30 mg/kg (0.3 times the MRHD based on adult AUC comparison).
In a juvenile animal bone toxicity study, 7-day old rats were dosed intravenously once daily for 28 days with 0, 30, 120, and 500 mg/kg sugammadex (approximately 0.1, 0.6, and 3 times the MRHD, respectively, by adult AUC comparison). Sugammadex at 120 and 500 mg/kg decreased ulna and femur bone lengths by approximately 3%, which did not recover after an 8-week treatment-free period. Reversible whitish discoloration and disturbance of enamel formation were also observed in the incisors at these dose levels. In molars, this effect was only observed at 500 mg/kg. The no-observed-effect-level (NOEL) was 30 mg/kg.
In a second juvenile animal bone toxicity study, 7-day old rats were dosed once weekly for 8 weeks with 0, 7.5, 30, and 120 mg/kg (up to 1.2 times the MRHD of 16 mg/kg based on adult AUC comparison). No adverse effects on bone or teeth were noted.
16.1 Comparative Non-Clinical Pharmacology and Toxicology
Not applicable.
17 SUPPORTING PRODUCT MONOGRAPHS
- 1. BRIDION, Solution for Intravenous Injection, 100 mg/mL, Submission Control 289615, Product Monograph, Merck Canada Inc., [Jul 31, 2025]