


Product Monograph - Dojolvi
RECENT MAJOR LABEL CHANGES
Not Applicable.
TABLE OF CONTENTS
RECENT MAJOR LABEL CHANGES ......................................................................................2
TABLE OF CONTENTS ..............................................................................................................2
PART I: HEALTH PROFESSIONAL INFORMATION ............................................................4
1 INDICATIONS....................................................................................................................4
1.1 Pediatrics (<18 years) ................................................................................................4
1.2 Geriatrics (≥65 years of age) ......................................................................................4
2 CONTRAINDICATIONS ..................................................................................................4
3 DOSAGE AND ADMINISTRATION ...............................................................................4
3.1 Dosing Considerations ...............................................................................................4
3.2 Recommended Dose and Dosage Adjustment ...........................................................4
3.3 Administration ...........................................................................................................5
3.4 Missed Dose ...............................................................................................................6
4 OVERDOSAGE .................................................................................................................6
5 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ................7
6 WARNINGS AND PRECAUTIONS ...............................................................................7
General .................................................................................................................................7
Hepatic/Biliary/Pancreatic ...................................................................................................7
6.1 Special Populations ....................................................................................................7
6.1.1 Pregnant Women ................................................................................................... 7
6.1.2 Breast-feeding ....................................................................................................... 7
6.1.3 Pediatrics ............................................................................................................... 8
6.1.4 Geriatrics ............................................................................................................... 8
6.1.5 Hepatic Insufficiency ............................................................................................ 8
6.1.6 Renal Insufficiency ............................................................................................... 8
7 ADVERSE REACTIONS..................................................................................................8
7.1 Adverse Reaction Overview ......................................................................................8
7.2 Clinical Trial Adverse Reactions ...............................................................................9
7.3 Less Common Clinical Trial Adverse Reactions .......................................................9
7.4 Clinical Trial Adverse Reactions (Pediatrics)..........................................................10
7.5 Post-Market Adverse Reactions ...............................................................................10
8 DRUG INTERACTIONS .................................................................................................10
8.1 Overview ..................................................................................................................10
8.2 Drug-Drug Interactions ............................................................................................10
8.3 Drug-Food Interactions ............................................................................................10
8.4 Drug-Herb Interactions ............................................................................................10
8.5 Drug-Laboratory Test Interactions ..........................................................................10
9 ACTION AND CLINICAL PHARMACOLOGY ...........................................................10
9.1 Mechanism of Action ...............................................................................................10
9.2 Pharmacodynamics ..................................................................................................10
9.3 Pharmacokinetics .....................................................................................................10
10 STORAGE, STABILITY AND DISPOSAL..................................................................12
PART II: SCIENTIFIC INFORMATION ...................................................................................13
11 PHARMACEUTICAL INFORMATION ........................................................................13
12 CLINICAL TRIALS .........................................................................................................14
12.1 Trial Design and Study Demographics ................................................................14
12.2 Study Results ........................................................................................................14
13 NON-CLINICAL TOXICOLOGY ...................................................................................14
PATIENT MEDICATION INFORMATION ...............................................................................17
PrDOJOLVITM
(triheptanoin)
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
DOJOLVITM (triheptanoin) is indicated as a source of calories and fatty acids for the treatment of adult and pediatric patients with long-chain fatty acid oxidation disorders (LC-FAOD).
1.1 Pediatrics (<18 years)
Based on the data submitted and reviewed by Health Canada, the safety and efficacy of DOJOLVI in pediatric patients have been established; therefore, Health Canada has authorized an indication for pediatric use. (see ADVERSE REACTIONS and CLINICAL TRIALS)
1.2 Geriatrics (≥65 years of age)
Clinical studies of DOJOLVI did not include sufficient numbers of patients aged 65 and over to determine whether they respond differently from younger patients.
2 CONTRAINDICATIONS
Triheptanoin is contraindicated in patients who are hypersensitive to this drug or to any ingredient in the formulation, including any non-medicinal ingredient or component of the container. For a complete listing, see Dosage Forms, Strengths, Composition and Packaging.
3 DOSAGE AND ADMINISTRATION
3.1 Dosing Considerations
- Assess the metabolic requirements of the patient by determining their daily caloric intake (DCI) prior to calculating the dose of DOJOLVI.
- The neonatal and infant population may require higher fat intake and therefore an increased amount of DOJOLVI. Current nutritional recommendations should be considered when dosing the neonatal or infant population.
3.2 Recommended Dose and Dosage Adjustment
The recommended target daily dosage of DOJOLVI is up to 35% of the patient’s total prescribed DCI divided into at least four doses, administered at mealtimes or with snacks, at 3 to 4 hour intervals or as directed by the healthcare provider.
In order to reach a target daily dosage, patients may require an increase in their total fat intake.
The total daily dosage is converted to a volume of DOJOLVI to be administered in mL using the following calculation:
- Caloric value of DOJOLVI = 8.3 kcal/mL
- Round the total daily dosage to the nearest whole number.
- Divide the total daily dosage into at least four approximately equal individual doses.
Total Daily Dose (____mL) = Patients DCI (____kcal) x Target ____ % dose of DCI 8.3 kcal mL of DOJOLVI
Dosage Initiation and Titration
For patients not currently taking a medium-chain triglyceride (MCT) product
Initiate DOJOLVI at a total daily dosage of approximately 10% DCI divided into at least four times per day and increase to the recommended total daily dosage of up to 35% DCI over a period of 2 to 3 weeks.
For patients switching from another MCT product
Discontinue use of MCT products before starting DOJOLVI.
Initiate DOJOLVI at the last tolerated daily dosage of MCT divided into at least four times per day. Increase the total daily dosage by approximately 5% DCI every 2 to 3 days until the target dosage of up to 35% DCI is achieved.
Tolerability
If a patient has difficulty tolerating 1/4 of the total daily dosage at one time, more frequent smaller doses may be considered.
Monitor patients’ DCI during dosage titration, especially in patients with gastrointestinal adverse reactions, and adjust all components of the diet as needed.
If a patient experiences gastrointestinal adverse reaction(s), consider dosage reduction until the gastrointestinal symptoms resolve. Maintain the patient at the maximum tolerated dosage up to 35% DCI.
3.3 Administration
Administer DOJOLVI mixed with semi-solid food or liquids orally or enterally. Do not administer DOJOLVI alone to avoid gastrointestinal upset.
DOJOLVI is not compatible with certain plastics. Prepare or administer DOJOLVI using containers, dosing syringes or measuring cups made of compatible materials such as stainless steel, glass, high density polyethylene (HDPE), polypropylene, low density polyethylene, polyurethane and silicone.
Do not prepare or administer DOJOLVI using containers, dosing syringes or measuring cups made of polystyrene or polyvinyl chloride (PVC) plastics.
Regularly monitor the containers, dosing syringes or measuring cups that are in contact with DOJOLVI to ensure proper functioning and integrity.
Oral Preparation and Administration
- Use an oral syringe or measuring cup made of compatible materials as listed above to withdraw the prescribed volume of DOJOLVI from the bottle.
- DOJOLVI can be mixed into semi-solid foods and liquids.
- Add the prescribed amount of DOJOLVI to a clean bowl, cup or container, made of the compatible materials as listed above, which contains an appropriate amount of semi-solid food or liquid that takes into consideration the age, size and average consumption of the patient in order to ensure administration of the full dose.
- Mix DOJOLVI thoroughly into the food or liquid.
- The mixture may be stored for up to 24 hours in refrigerated conditions.
Feeding Tube Preparation and Administration
DOJOLVI can be administered via oral or enteral feeding tubes manufactured of silicone or polyurethane. Do not use feeding tubes manufactured of PVC. Feeding tube performance and functionality can degrade over time depending on usage and environmental conditions.
Regularly monitor the feeding tube to ensure proper functioning and integrity.
- Use an oral syringe or measuring cup made of compatible materials as listed above to withdraw the prescribed volume of DOJOLVI from the bottle.
- Add the prescribed amount of DOJOLVI to a clean bowl, cup or container, made of compatible materials as listed above, which contains an amount of formula that takes into consideration the age, size and average consumption of the patient in order to ensure administration of the full dose.
- Mix DOJOLVI thoroughly into the formula.
- Draw up the entire amount of the DOJOLVI-formula mixture into a slip tip syringe.
- Remove the residual air from the syringe and connect the syringe directly into the feeding tube feeding port.
- Push the syringe contents into the feeding tube feeding port using steady pressure until empty.
- Flush the feeding tubes with between 5 mL to 30 mL of water. Flush volume should be modified based on specific patient needs and in cases of fluid restriction.
- Discard any unused portion of the DOJOLVI-formula mixture. Do not save for later use.
3.4 Missed Dose
If a dose (one of the portions taken throughout the day) is missed, take the next dose as soon as possible. Skip the missed dose if it will not be possible to take all doses in a day.
4 OVERDOSAGE
The overdose potential of DOJOLVI has not been evaluated in human studies. In case of overdose, appropriate treatment should be initiated according to the patient’s clinical signs and symptoms.
| For management of a suspected drug overdose, contact your regional poison control centre. |
5 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 1: Dosage Forms, Strengths, Composition and Packaging
DOJOLVI (triheptanoin) is a colorless to light yellow clear liquid supplied in 500 mL bottles containing 100% w/w of triheptanoin active ingredient.
6 WARNINGS AND PRECAUTIONS
General
Feeding Tube Dysfunction
Feeding tube performance and functionality can degrade over time depending on usage and environmental conditions. In clinical trials, feeding tube dysfunction was reported in patients receiving DOJOLVI. The contribution of DOJOLVI to these events cannot be ruled out. Do not administer DOJOLVI in feeding tubes manufactured of PVC. Regularly monitor the feeding tube to ensure proper functioning and integrity.
Hepatic/Biliary/Pancreatic
Intestinal Malabsorption in Patients with Pancreatic Insufficiency
Pancreatic enzymes hydrolyze triheptanoin and release heptanoate as medium-chain fatty acids in the small intestine. Low or absent pancreatic enzymes may reduce absorption of heptanoate leading to insufficient supplementation of medium-chain fatty acids. Avoid administration of DOJOLVI in patients with pancreatic insufficiency.
6.1 Special Populations
6.1.1 Pregnant Women
There are no available data on triheptanoin use in pregnant women to evaluate for a drug-associated risk of major birth defects, miscarriage, or adverse maternal or fetal outcomes. In animal reproduction studies conducted in pregnant rats and rabbits administered triheptanoin during the period of organogenesis, the primary toxicological effect (reduced body weight gain) was considered to be specific to decreased food consumption related to taste aversion in animals. (see TOXICOLOGY – Reproduction and Development)
6.1.2 Breast-feeding
There are no data on the presence of triheptanoin or its metabolites in human or animal milk, the effects on the breastfed infant, or the effects on milk production. Medium-chain triglycerides
| Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
| oral | Liquid, 100% w/w | N/A |
and other fatty acids are normal components of breastmilk and the composition of breastmilk varies within feedings, over stages of lactation, and between mothers and populations due to maternal factors including genetics, environment, and diet. The developmental and health benefits of breastfeeding should be considered along with the clinical need for DOJOLVI and any potential adverse effect on the breastfed infant from DOJOLVI or from the underlying condition.
6.1.3 Pediatrics
The safety and efficacy of DOJOLVI in pediatric patients have been established.
6.1.4 Geriatrics
Clinical studies of DOJOLVI did not include sufficient numbers of patients aged 65 and over to determine whether they respond differently from younger patients.
6.1.5 Hepatic Insufficiency
No studies have been conducted to evaluate the PK of triheptanoin and its metabolites in patients with hepatic impairment.
6.1.6 Renal Insufficiency
No studies have been conducted to evaluate the PK of triheptanoin and its metabolites in patients with renal impairment.
7 ADVERSE REACTIONS
7.1 Adverse Reaction Overview
The most common adverse reactions to DOJOLVI reported in the pooled safety population of Study 1 and Study 2 were gastrointestinal (GI)-related, and included abdominal pain (abdominal discomfort, abdominal distension, abdominal pain, abdominal pain upper, GI pain) [60%], diarrhea [44%], vomiting [44%], and nausea [14%].
In the pooled safety population (Study 1 and Study 2) 5 (6%) subjects had TEAEs leading to dose discontinuation including myalgia, gastroesophageal reflux disease, pain, diarrhea, vomiting and rhabdomyolysis, the latter 3 considered related to triheptanoin.
Dose reductions occurred in 20 subjects (25.3%) including 12 subjects (41%) in Study 1 and 9 subjects (12%) in Study 2. Of these, GI adverse reactions led to dose reductions in 35% and 12% of patients in Study 1 and Study 2, respectively and included abdominal pain (28%), diarrhea (24%), and nausea (3%) in Study 1 and diarrhea (7%), and abdominal pain (5%) in Study 2.
Dose interruptions were made to triheptanoin in 16 subjects (20%) including 10 subjects (34%) in Study 1 and 8 subjects (11%) in Study 2. Of these, GI adverse reactions led to dose interruptions in 3 subjects (10%) in Study 1 for diarrhea (7%), abdominal pain (7%), nausea (3%) and vomiting (3%) and 5 subjects (7%) in Study 2 for vomiting (5%) and diarrhea (1%).
7.2 Clinical Trial Adverse Reactions
Because clinical trials are conducted under very specific conditions, the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
The assessment of adverse reactions was based on a safety population that included 79 patients with LC-FAOD exposed to DOJOLVI in two studies: one open-label single arm 78-week study of DOJOLVI in 29 patients (Study 1 [UX007-CL201]) followed by an open-label extension study (Study 2 [UX007-CL202]). Twenty-four patients from Study 1 continued into Study 2 and the remaining patients were treatment naïve (n=19) or rolled over from investigator sponsored trials (IST)/another trial (n=31). Patients ranged from 4 months to 63 years of age and the population was 52% male. Of the 79 patients, 87% were white, 5% were black or African-American, 4% were Asian and 4% other. The mean average daily dosage of DOJOLVI per patient was 25% DCI (ranged between 5% and 40% DCI) which corresponds to 0.3 g/kg/day to 5.2 g/kg/day for pediatric patients and 0.1 g/kg/day to 1.2 g/kg/day for adult patients for a mean duration of 30 months.
The most common adverse reactions from the pooled safety population of Study 1 and Study 2 were gastrointestinal (GI) in nature (Table 2).
Table 2: Adverse Reactions Reported in Patients with LC-FAOD from Study 1 and Study 2
| Adverse Reaction | DOJOLVI N=79 (%) |
| Abdominal Paina | 60 |
| Diarrhea | 44 |
| Vomiting | 44 |
| Nausea | 14 |
a Abdominal Pain includes the following grouped terms: Abdominal Discomfort, Abdominal distension, Abdominal pain, Abdominal pain upper, and Gastrointestinal pain
Gastrointestinal (GI) Adverse Reactions
GI adverse reactions were severe (1%), moderate (22%) and mild (77%) in severity.
In Study 3, a 4-month double-blind randomized controlled study in 32 adult and pediatric patients with a confirmed diagnosis of LC-FAOD, commonly reported adverse reactions with triheptanoin were similar to those reported in Study 1 and Study 2.
7.3 Less Common Clinical Trial Adverse Reactions
Not applicable.
7.4 Clinical Trial Adverse Reactions (Pediatrics)
The safety profile of triheptanoin in the pediatric population appears to be similar to that observed in the adult population.
7.5 Post-Market Adverse Reactions
No post-market data are available.
8 DRUG INTERACTIONS
8.1 Overview
In vitro studies show that heptanoate is not an inhibitor of CYP1A2, CYP2B6, CYP2C8, CYP2C9, CYP2C19, CYP2D6, or CYP3A4. Heptanoate and BHP are not CYP substrates nor UGT substrates. Heptanoate increases the unbound fraction of valproic acid by approximately 2-fold.
8.2 Drug-Drug Interactions
Pancreatic Lipase Inhibitors
Concomitant use of triheptanoin with pancreatic lipase inhibitor (e.g., orlistat) may reduce the systemic exposure of heptanoate (metabolite of triheptanoin) and may reduce the efficacy of triheptanoin. Avoid co-administration of DOJOLVI with pancreatic lipase inhibitors.
8.3 Drug-Food Interactions
Interactions with food have not been established.
8.4 Drug-Herb Interactions
Interactions with herbal products have not been established.
8.5 Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
9 ACTION AND CLINICAL PHARMACOLOGY
9.1 Mechanism of Action
Triheptanoin is a medium chain triglyceride consisting of three odd-chain 7-carbon length fatty acids (heptanoates) that provide a source of odd-chain fatty acids to bypass the long-chain FAOD enzyme deficiencies for energy production and replacement.
9.2 Pharmacodynamics
No formal pharmacodynamic studies have been conducted with DOJOLVI.
9.3 Pharmacokinetics
Following oral administration, triheptanoin is extensively hydrolyzed to heptanoate and glycerol by pancreatic lipases in the intestines. The exposure of triheptanoin in the human plasma is minimal. Pharmacokinetics of heptanoate exhibits high inter-patient variability. Heptanoate exposure increases greater than dose-proportional in the dose range between triheptanoin 0.3 and 0.4 g/kg.
Absorption: The pharmacokinetics of heptanoate in healthy adult patients following an oral administration of DOJOLVI mixed with food are summarized in Table 4.
Table 4: Summary of Pharmacokinetic Parameters of Heptanoate after Single and Multiple Oral Administration of DOJOLVI to Healthy Adults (N=13)
| DOJOLVI Dose | Cmax (uM) Mean (SD) | Tmax (h) Median (range) | Time toa First peak concentration (h) Median (range) | AUC0-8h (uM*h) Mean (SD) | CL/F (L/h/kg) Mean (SD) | ||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Single dose | 0.3 g/kg | 178.9 (145) | 0.67 (0.42-6.47) | 0.50 (0.42 – 0.97) | 336.5 (223) | 6.05 (2.80) | |||||||
| 0.4 g/kg | 259.1 (134) | 1.17 (0.42 – 8.33) | 0.82 (0.42 – 6.40) | 569.1 (189) | 4.31 (1.02) | ||||||||
| Multiple Doses | 0.3 g/kg administered 4 times a day for 2 days (total daily dosage of 1.3 g/kg/day) | 319.9 (164) | 1.42 (0 – 8.42) | 1.17 (0 – 2.42) | 789.8 (346) | NA | |||||||
a After oral administration of DOJOLVI, multiple peak concentrations of heptanoate are observed.
Distribution: The plasma protein binding of heptanoate is approximately 80% and is independent of total concentration.
Metabolism: Heptanoate, formed by hydrolysis of triheptanoin, can be metabolized to beta-hydroxypentanoate (BHP) and beta-hydroxybutyrate (BHB) in the liver.
Elimination: After single or multiple repeat doses of triheptanoin to healthy subjects, triheptanoin and its metabolites were minimally excreted in urine. After a single dose of either 0.3 g/kg or 0.4 g/kg triheptanoin to healthy patients, the mean apparent clearance (CL/F) of heptanoate was 6.05 and 4.31 L/hr/kg, respectively. Half-life (t1/2) of heptanoate could not be determined due to multiple peak concentrations of heptanoate observed.
10 STORAGE, STABILITY AND DISPOSAL
Store bottle upright at 15° to 30°C.
Once the bottle of DOJOLVI has been opened, use within 9 months or by the expiration date on the bottle, whichever is earlier.
Do not freeze.
Pharmacists should dispense only in glass or HDPE bottles.
Do not dose or store using materials made of polystyrene or polyvinyl chloride (PVC) containers.
PART II: SCIENTIFIC INFORMATION
11 PHARMACEUTICAL INFORMATION
Drug Substance
Proper/Common name: Triheptanoin
Chemical name: heptanoic acid, 1,1',1''-(1,2,3-propanetriyl) ester
Molecular formula and molecular mass: C24H44O6
Molecular Weight: 428.6 g/mol
Structural formula:
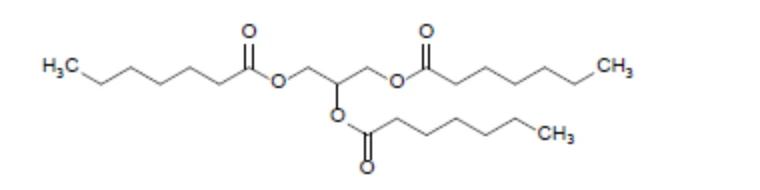
Physicochemical properties:
Physical form: Clear, colorless to light yellow liquid
Solubility: Water solubility: < 0.05 mg/L at 20 C
pH and pKa values: N/A
Partition coefficient (n-octanol/water): Log Pow: 8.86 at 20 °C and pH 6
Melting point/freezing point: ~ -25 °C at ~1013 hPa1
Boiling point: 232.4 °C at ~101 kPa2
Optical rotation: N/A
Refractive index: 1.4440 - 1.4465
Hygroscopicity: N/A
UV absorption maxima and molar absorptivity: N/A
1 hPa = hectopascal
2 kPa = kilopascal
12 CLINICAL TRIALS
12.1 Trial Design and Study Demographics
Table 5: Summary of Patient Demographics for Clinical Trials
| Study # | Trial design | Dosage, route of administration and duration | Study subjects (n) | Age Mean (Range)a | Sex |
| Study 3 | Phase 2 Double-blind randomized controlled study | Target Dose: 20% DCI, oral liquid, 16 weeks | 32 | 24.8 years (7.0 – 64.0) | 12 Male 20 Female |
12.2 Study Results
Study 3
The efficacy of triheptanoin as a source of odd-chain fatty acids was evaluated in Study 3, a 4-month double-blind randomized controlled study comparing triheptanoin (7 carbon chain fatty acid) with trioctanoin (8 carbon chain fatty acid). Study 3 enrolled 32 adult and pediatric patients with a confirmed diagnosis of LC-FAOD and evidence of at least one significant episode of rhabdomyolysis and at least two of the following diagnostic criteria: disease specific elevation of acylcarnitines on a newborn blood spot or in plasma, low enzyme activity in cultured fibroblasts, or one or more known pathogenic mutations in CPT2, ACADVL, HADHA, or HADHB.
The dosage of study drug was titrated to a target of 20% DCI (actual mean daily dose achieved was 16% for triheptanoin and 14% for trioctanoin). Patients ranged in age from 7 years to 64 years (median 22.5 years) and 12 were male.
Cardiac Function
After 4 months, patients in both groups had similar mean changes from baseline in left ventricular ejection fraction and wall mass on resting echocardiogram and similar maximal heart rates on treadmill ergometry. Because cardiovascular function of the patients was within normal range at baseline, interpretation of these changes is limited.
Rhabdomyolysis
Five patients experienced 7 events of rhabdomyolysis in the triheptanoin treatment group and 4 patients experienced 7 events of rhabdomyolysis in the trioctanoin treatment group.
Blood Metabolic Markers
No differences were observed between triheptanoin and trioctanoin groups in blood markers of metabolism including glucose, insulin, lactate, total serum, ketones, acylcarnitines, and serum free fatty acid concentrations.
13 NON-CLINICAL TOXICOLOGY
General Toxicology
Acute toxicity: single-dose toxicity was assessed in rats administered food-grade triheptanoin by oral gavage at doses up to 5 mL/kg (or 4.75 g/kg) with no deaths or signs of toxicity observed in this study.
Chronic toxicity: in repeat-dose studies, triheptanoin was well tolerated at the highest dose level tested in chronic 9-month GLP dietary toxicity studies conducted in rats (up to 1.14 g/kg) and juvenile minipigs (50% DCI equivalent to 10 g/kg).
Carcinogenesis
The 2-year rat carcinogenicity study has not been conducted with triheptanoin. In a published chronic 9-month dietary study conducted in rats, daily administration of triheptanoin at dose levels up to 1.14 g/kg was associated with atrophy or hyperplasia of the intestinal villa. In a chronic 9-month dietary study conducted in juvenile minipigs, treatment with triheptanoin at dose levels up to 10 g/kg was well tolerated with no changes in histopathology suggestive of any carcinogenic potential.
Published studies with structurally similar triglycerides (i.e. MCTs) were also evaluated. In a 2-year dietary study of rats fed tricaprylin (C8 MCT) at dose levels up to 9.5 g/kg (approximately 1.2 times the anticipated maximum clinical dose), there were increased incidences of pancreatic and forestomach hyperplasia and adenomas but not carcinomas. Chronic administration of a diet containing approximately 17% MCT was not shown to promote effects on colon tumor incidence in an azomethane-induced colon tumorigenicity rat model.
Genotoxicity
Triheptanoin was not genotoxic in a battery of genotoxicity tests including the in vitro bacterial reverse mutation in S. typhimurium and E. coli, in vitro mammalian chromosomal aberration test in human peripheral blood lymphocytes and the in vivo mammalian erythrocyte micronucleus test in rat bone marrow.
Reproductive and Developmental Toxicology
Embryo-fetal development studies were performed in rats and rabbits during organogenesis. In pregnant animals, the maternal toxicity (attributed to taste aversion which resulted in reduced maternal body weight and lower corrected total gain) was observed following oral administration of triheptanoin at dose levels equivalent to DCI of ≥30% (in rats) and ≥20% (in rabbits). The no-observed-adverse-effect level (NOAEL) of triheptanoin for maternal toxicity was 10% DCI for both rats and rabbits.
Based on increased incidence of skeletal malformations along with reduced litter weights following oral administration of triheptanoin at higher dose levels (50% DCI in rats and 30% DCI in rabbits), the NOAEL for developmental toxicity was 30% DCI in rats and 20% DCI in rabbits. The developmental toxicity was likely secondary to the maternal toxicity.
In a pre- and postnatal development study in rats, triheptanoin-related effects during F1 generation postweaning phase at 50% DCI were reductions in mean body weights and body weight gains along with delay in sexual maturation. These were likely secondary effects related to maternal toxicity in rats.
Triheptanoin had no effect on fertility or any other parameters of mating performance in rats exposed to repeat dietary administration of triheptanoin at dose levels equivalent to up to 50% daily caloric intake (16 g/kg) that resulted in systemic drug exposure (AUC) of heptanoate approximately equal to the maximum recommended human dose.