


Product Monograph - Waymade-Trientine
RECENT MAJOR LABEL CHANGES
Not applicable.
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
RECENT MAJOR LABEL CHANGES ............................................................................................ 2
TABLE OF CONTENTS .............................................................................................................. 2
PART I: HEALTH PROFESSIONAL INFORMATION ...................................................................... 4
1 INDICATIONS ............................................................................................................... 4
1.1 Pediatrics ................................................................................................................ 4
1.2 Geriatrics ................................................................................................................ 4
2 CONTRAINDICATIONS ................................................................................................. 4
3 SERIOUS WARNINGS AND PRECAUTIONS BOX ............................................................ 4
4 DOSAGE AND ADMINISTRATION ................................................................................. 5
4.1 Dosing Considerations ............................................................................................ 5
4.2 Recommended Dose and Dosage Adjustment ....................................................... 5
4.4 Administration ........................................................................................................ 5
4.5 Missed Dose ........................................................................................................... 6
5 OVERDOSAGE .............................................................................................................. 6
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ................................. 6
7 WARNINGS AND PRECAUTIONS .................................................................................. 6
7.1 Special Populations................................................................................................. 8
7.1.1 Pregnant women .............................................................................................. 8
7.1.2 Breast-feeding .................................................................................................. 8
7.1.3 Pediatrics .......................................................................................................... 8
7.1.4 Geriatrics .......................................................................................................... 8
8 ADVERSE REACTIONS .................................................................................................. 8
8.1 Adverse Reaction Overview .................................................................................... 8
8.2 Clinical Trial Adverse Reactions .............................................................................. 9
8.3 Post-Market Adverse Reactions ............................................................................. 9
9 DRUG INTERACTIONS .................................................................................................. 9
9.4 Drug-Drug Interactions ........................................................................................... 9
9.5 Drug-Food Interactions ........................................................................................... 9
9.6 Drug-Herb Interactions ........................................................................................... 9
9.7 Drug-Laboratory Test Interactions .......................................................................... 9
10 CLINICAL PHARMACOLOGY ......................................................................................... 9
10.1 Mechanism of Action ........................................................................................ 9
10.2 Pharmacodynamics ........................................................................................ 10
10.3 Pharmacokinetics ........................................................................................... 10
11 STORAGE, STABILITY AND DISPOSAL ......................................................................... 11
12 SPECIAL HANDLING INSTRUCTIONS ........................................................................... 12
PART II: SCIENTIFIC INFORMATION ....................................................................................... 13
13 PHARMACEUTICAL INFORMATION ............................................................................ 13
14 CLINICAL TRIALS ........................................................................................................ 13
14.1 Clinical Trials by Indication ............................................................................. 13
The Treatment Of Patients With Wilson's Disease Who Are Intolerant To Penicillamine. ....................................................................................................................................... 13
14.2 Comparative Bioavailability Studies ................................................................ 15
15 MICROBIOLOGY ........................................................................................................ 15
16 NON-CLINICAL TOXICOLOGY ..................................................................................... 16
PATIENT MEDICATION INFORMATION .................................................................................. 17
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
WAYMADE-TRIENTINE (trientine hydrochloride capsules) is indicated for:
- The treatment of patients with Wilson's Disease who are intolerant to penicillamine.
WAYMADE-TRIENTINE should only be initiated by physicians experienced in the management of Wilson’s Disease.
1.1 Pediatrics
Pediatrics (5-17 years of age): Controlled studies of the safety and effectiveness of trientine hydrochloride in pediatric patients have not been conducted. Data are lacking to establish the safety and effectiveness of trientine hydrochloride in children less than 5 years of age.
Pediatrics (<5 years of age): Based on the data submitted and reviewed by Health Canada, the safety and efficacy of WAYMADE-TRIENTINE in these pediatric patients have not been established; therefore, Health Canada has not authorized an indication for children less than 5 years of age.
1.2 Geriatrics
Geriatrics (> 65 years of age): Clinical studies of trientine hydrochloride did not include sufficient numbers of patients aged 65 and over to determine whether they respond differently than patients less than 65 years of age. WAYMADE-TRIENTINE should be used with caution in geriatric patients (see 4.2 Recommended Dose and Dosage Adjustment and 7.1.4 Geriatrics).
2 CONTRAINDICATIONS
Trientine hydrochloride is contraindicated in:
- Patients who are hypersensitive to this drug or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING.
3 SERIOUS WARNINGS AND PRECAUTIONS BOX
Serious Warnings and Precautions
|
|---|
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
- The starting dose of WAYMADE-TRIENTINE would usually be the lowest recommended dose. The dose should subsequently be adjusted according to the patient’s clinical response.
- Patients receiving WAYMADE-TRIENTINE require regular and ongoing monitoring of their clinical condition and response to treatment throughout the period of drug administration (see General).
- Overtreatment carries the risk of copper deficiency. Ongoing regular monitoring for manifestations of overtreatment should be undertaken (see General and Monitoring and Laboratory Tests).
- Studies in animals have shown that trientine hydrochloride is teratogenic (see 16 NON-CLINICAL TOXICOLOGY, Reproductive and Developmental Toxicology). Some data have also shown that trientine hydrochloride has a genotoxic potential (see 16 NON-CLINICAL TOXICOLOGY, Genotoxicity). If used during pregnancy, serum free copper concentrations should be closely monitored and a dosage adjustment to the lowest dose of WAYMADE-TRIENTINE that maintains free copper concentrations within acceptable limits should be considered (see 7.1.1 Pregnant women).
- If iron deficiency develops and iron administration is required, doses of WAYMADE-TRIENTINE and iron should be separated by at least two hours (see Hematologic and 9.4 Drug-Drug Interactions).
- WAYMADE-TRIENTINE should be taken at least one hour apart from any other drug, food, or milk (see 9.5 Drug-Food Interactions).
4.2 Recommended Dose and Dosage Adjustment
Adults: The recommended starting dose of WAYMADE-TRIENTINE is 750 mg/day, given in divided doses 2 to 4 times a day. Subsequently, if required, the daily dose may be increased gradually to a maximum of 2,000 mg/day. Most adult patients can be maintained at a daily dose of 1,250 mg/day or less.
Pediatrics (5-17 years old): The recommended starting dose is 500 mg/day, given in divided doses 2 to 4 times a day. Subsequently, if required, the daily dose may be increased gradually to a maximum of 1,500 mg/day for patients aged 12 years or under.
The daily dose of WAYMADE-TRIENTINE should be increased only when the clinical response is not adequate or the concentration of serum free copper is persistently above 3.1 mcmol/L (20 mcg/dL). The optimal long-term maintenance dosage should generally be determined at 6 to 12 month intervals.
Geriatrics (> 65 years of age): Dose selection should be cautious in patients over the age of 65 years, usually starting at the low end of the dosing range (see 7.1.4 Geriatrics).
Hepatic impairment: Clinical studies evaluating patients with hepatic impairment have not been conducted. No dosage adjustment is required, however it is advised that patients be monitored every two to three weeks after initiation of treatment with WAYMADE-TRIENTINE.
Renal impairment: Clinical studies evaluating patients with renal impairment have not been conducted. There is limited information in patients with renal impairment. No dosage adjustment is required in these patients.
4.4 Administration
WAYMADE-TRIENTINE should be given on an empty stomach, at least one hour before meals or two hours after meals and at least one hour apart from any other drug, food, or milk. The capsules should be swallowed whole with water and should not be opened or chewed (see 9.4 Drug-Drug Interactions and 9.5 Drug-Food Interactions).
4.5 Missed Dose
A missed dose should be administered as soon as possible. However, two doses of WAYMADE-TRIENTINE should not be taken at the same time or very close to each other.
If you missed a dose of this medication, take it as soon as you remember. But if it is almost time for your next dose, skip the missed dose and continue with your next scheduled dose. Go back to the regular dosing schedule. Do not take two doses at the same time.
5 OVERDOSAGE
There is a single report of an adult woman who ingested 30 grams of trientine hydrochloride without apparent ill effects. No other data on overdosage are available.
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 1: Dosage Forms, Strengths, Composition and Packaging
Description
Cylindrical size “1” hard gelatin capsule with opaque orange colour cap printed with “NAV” in black ink and opaque white colour body printed with “101” in black ink. Capsule filled with white to off white colour powder.
Primary packaging system for trientine hydrochloride capsules 250 mg, is 150 cc white HDPE round bottle, 38 mm screw cap, and 1 g silica gel as desiccant. Pack size is 100’s count.
7 WARNINGS AND PRECAUTIONS
Please see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX.
General
Patient experience with trientine hydrochloride is limited (see 14 CLINICAL TRIALS). Patients receiving WAYMADE-TRIENTINE require regular and ongoing monitoring of their clinical condition and response to treatment throughout the period of drug administration.
Overtreatment carries the risk of copper deficiency, which is especially harmful for children and pregnant women, since copper is required for proper growth and mental development. Therefore, ongoing regular monitoring for manifestations of overtreatment should be undertaken.
| For management of a suspected drug overdose, contact your regional poison control centre. |
|---|
| Route of Administration | Dosage Form/ Strength/Composition | Non-medicinal Ingredients |
| Oral | Capsules, 250 mg | Black ink, gelatin, purified water, stearic acid, sunset yellow FCF, titanium dioxide |
Carcinogenesis and Mutagenesis
Data on carcinogenesis, and impairment of fertility are not available. For genotoxicity potential of trientine, see 16 NON-CLINICAL TOXICOLOGY, Genotoxicity.
Hematologic
Trientine hydrochloride is a chelating agent that has been found to reduce serum iron levels, which may lead to iron deficiency anemia. Oral iron supplementation may be necessary, and if required, it should be administered at a different time of day than WAYMADE-TRIENTINE (see 9.4 Drug-Drug Interactions).
Immune
There are no reports of hypersensitivity in patients who have been administered WAYMADE-TRIENTINE for Wilson's Disease. However, there have been reports of asthma, bronchitis and dermatitis occurring after prolonged environmental exposure in workers who use trientine hydrochloride as a hardener of epoxy resins. Patients should be observed closely for signs of possible hypersensitivity.
Monitoring and Laboratory Tests
The most reliable index for monitoring treatment is the determination of free copper in the serum, which equals the difference between quantitatively determined serum total copper and ceruloplasmin-bound copper. Adequately treated patients will usually have less than 3.1 mcmol/L (20 mcg/dL) of serum free copper.
Chelation therapy may be monitored with a 24-hour urinary copper analysis periodically, e.g., every 6 to 12 months. Urine must be collected in copper-free glassware. Since a low copper diet should maintain copper absorption to less than one milligram per day, the patient will probably be in the desired state of negative copper balance if 0.5 to 1.0 mg of copper is present in a 24-hour collection of urine.
Neurologic
Worsening of neurologic or neurocognitive functioning, which can be irreversible, may occur in patients with pre-existing neurologic and/or neuropsychiatric impairment at the time of initiation of chelator therapy with trientine hydrochloride. Initiation of WAYMADE-TRIENTINE should be carried out with caution in these patients, and only after careful consideration of all available treatment options and the determination of an acceptable benefit-risk for the patient. Close monitoring of clinical response in these patients is required in the first few months following initiation of WAYMADE-TRIENTINE.
Reproductive Health: Female and Male Potential
See 7.1.1 Pregnant women.
Fertility
No human fertility studies have been conducted. Based on animal studies, there are no available data regarding effects on fertility (see 16 NON-CLINICAL TOXICOLOGY).
Teratogenic Risk
Trientine hydrochloride may cause fetal harm when administered to a pregnant woman based on results from animal reproduction studies (see 16 NON-CLINICAL TOXICOLOGY, Reproductive and Developmental Toxicology). Some available data have showed that trientine hydrochloride has a genotoxic potential (see 16 NON-CLINICAL TOXICOLOGY, Genotoxicity).
WAYMADE-TRIENTINE should only be used during pregnancy after carefully considering the potential benefits of treatment compared to its risks and when the benefits to women of childbearing potential are judged to outweigh the risks (see 7.1.1 Pregnant women).
Skin
Because of the potential for contact dermatitis, any exposure to the capsule contents should be washed promptly with water.
7.1 Special Populations
7.1.1 Pregnant women
No well-controlled studies of the use of trientine hydrochloride in pregnant women have been conducted. There is only a limited amount of experience with data from the use of trientine hydrochloride in pregnant women. WAYMADE-TRIENTINE should be used during pregnancy only after careful consideration of the potential benefits for the patient, compared with its risks. Factors to consider when using trientine hydrochloride in pregnancy include the risks associated with uncontrolled disease, maintenance of serum iron concentrations, the risks of alternative treatments, and the possible teratogenic effects of trientine hydrochloride.
Studies in animals have shown that trientine hydrochloride is teratogenic in rats at systemic exposures similar to those seen in humans, which may have been the result of trientine-induced copper deficiency. The frequencies of both resorptions and fetal abnormalities of the brain increased, while fetal copper concentrations decreased, when maternal rats were fed trientine hydrochloride in the diet. Some data are available with respect to the genotoxic potential of trientine hydrochloride (see 16 NON-CLINICAL TOXICOLOGY, Genotoxicity). Closely monitor serum free copper concentrations and consider a dosage adjustment to the lowest dose of WAYMADE-TRIENTINE that maintains free copper concentrations within acceptable limits.
7.1.2 Breast-feeding
It is not known whether trientine hydrochloride is excreted in human milk. Limited clinical data suggest that trientine hydrochloride is not excreted in breast milk, however, a risk to newborns and infants cannot be excluded. Because many drugs are excreted in human milk, caution should be exercised when WAYMADE-TRIENTINE is administered to breastfeeding women.
7.1.3 Pediatrics
- Pediatrics (< 18 years of age): Controlled studies of the safety and effectiveness of trientine hydrochloride in pediatric patients have not been conducted.
7.1.4 Geriatrics
Geriatrics (> 65 years of age): Reported clinical experience with trientine hydrochloride has not included sufficient numbers of patients over the age of 65 years to determine whether these patients respond differently than patients less than 65 years of age. In general, dose selection should be cautious in these patients, usually starting at the low end of the dosing range, reflecting the greater frequency of concomitant disease or other drug therapy.
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
Clinical experience with trientine hydrochloride has been limited.
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials; therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
Nausea occurs commonly following treatment initiation with trientine hydrochloride. The occurrence of skin rash has also been reported. Severe duodenitis and/or colitis have been observed on occasion. Sideroblastic anemia and aplastic anemia have been reported rarely.
Iron deficiency has been observed with trientine hydrochloride treatment (see 7 WARNINGS AND PRECAUTIONS, Hematologic).
8.3 Post-Market Adverse Reactions
In addition to the adverse reactions reported during pre-marketing use, the following adverse reactions have been reported in post-marketed use: Neurological deterioration, with signs including dystonia, rigidity, tremor, and dysarthria.
9 DRUG INTERACTIONS
9.4 Drug-Drug Interactions
No interaction studies have been performed with WAYMADE-TRIENTINE. Mineral supplements should be avoided as they may block the absorption of WAYMADE-TRIENTINE. If iron deficiency develops, particularly in children and menstruating or pregnant women, or as a result of the low copper diet recommended for Wilson's Disease, iron may be administered in short courses. As iron and WAYMADE-TRIENTINE inhibit the absorption of each other, doses of WAYMADE-TRIENTINE and iron should be separated by at least two hours.
9.5 Drug-Food Interactions
Trientine hydrochloride is poorly absorbed following oral intake and food further inhibits its absorption. It is important that WAYMADE-TRIENTINE be taken on an empty stomach, at least one hour before meals or two hours after meals and at least one hour apart from any other drug, food, or milk. This permits maximum absorption and reduces the likelihood of inactivation of the drug by metal binding in the gastrointestinal tract.
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
Trientine hydrochloride is a copper chelating agent that aids in the elimination of copper from the body by forming a stable complex that is readily excreted by the kidneys. Trientine hydrochloride may also chelate copper in the intestinal tract, and thus, inhibit copper absorption.
10.2 Pharmacodynamics
Trientine is a chelator with a polyamine-like structure and copper is chelated by forming a stable complex with the four constituent nitrogens in a planar ring. Thus, the pharmacodynamic action of trientine is dependent on its chemical property of chelating copper and not on its interaction with receptors, enzyme systems, or any other biological system that might differ between species.
Preclinical Studies
Studies in animals have shown that trientine hydrochloride has cupriuretic activities in both normal and copper-loaded rats without significant changes in serum copper. Urinary copper excretion was greater and accelerated in copper-loaded rats compared with normal rats. In general, the effects of trientine hydrochloride on urinary copper excretion are similar to those of penicillamine.
Human Studies
Renal clearance studies were carried out with penicillamine and trientine hydrochloride in selected patients with confirmed Wilson’s Disease, treated with penicillamine for at least one year. Six-hour excretion rates of copper were determined pre-treatment (basal) and after a single dose of 500 mg of penicillamine or 1.2 g of trientine. The mean urinary excretion rates of copper were as follows:
| No. of Patients | Single Dose Treatment | Basal Excretion Rate (mcg Cu + + /6 h) | Post-Test Dose Excretion Rate (mcg Cu + + /6 h) |
| 6 | Trientine, 1.2 g | 19 | 234 |
| 4 | Penicillamine, 500 mg | 17 | 320 |
In patients not previously treated with chelating agents, a similar comparison was made:
| No. of Patients | Single Dose Treatment | Basal Excretion Rate (mcg Cu + + /6 h) | Post-Test Dose Excretion Rate (mcg Cu + + /6 hr) |
| 8 | Trientine, 1.2 g | 71 | 1326 |
| 7 | Penicillamine, 500 mg | 68 | 1074 |
Trientine hydrochloride is effective as a cupriuretic agent in patients with Wilson's Disease, although on a molar basis, the effect may be smaller than with penicillamine. The difference in cupriuretic effect between these two drugs could be due to a difference in selectivity of the drugs for different copper pools within the body.
10.3 Pharmacokinetics
Data on the pharmacokinetics of trientine hydrochloride are limited. Dosage adjustment recommendations are based upon clinical use of the drug (see 4 DOSAGE AND ADMINISTRATION).
Table 2: Summary of Trientine Hydrochloride Pharmacokinetic Parameters in Healthy Adult Subject
Cmax (mg/L) | Tmax (h) | t½ (h) | AUC0-∞ (mg.h/L) | |
Multiple dose mean (Day 14, 1.2 g/d) | 1.55 | 0.83 | 10.37 | 11.14 |
Cmax = maximum observed concentration, tmax = time to maximum observed concentration; t1/2 = elimination half-life; AUC = area under the curve.
Absorption
The absorption of trientine hydrochloride following oral administration is low and variable in patients with Wilson’s Disease. Trientine is absorbed with tmax occurring between 0.5 and 4 hours after dosing and shows biexponential decline in serum concentrations. Gender and body weight do not seem to influence pharmacokinetic parameters.
Distribution
No data are available for the tissue distribution of trientine in humans. However, trientine is distributed in most rat tissues, particularly in the liver and kidney. In healthy volunteers, the central and peripheral volumes were shown to be large, indicating that trientine is probably widely distributed in human body tissues.
Metabolism
Trientine is acetylated into two major metabolites, 1-N-acetyltriethylene tetramine (MAT) and N1,N10-diacetyltriethylenetetramine (DAT). MAT may participate in the overall activity of trientine, however the extent to which MAT effects copper concentrations has not been determined.
Elimination
Trientine and its metabolites are rapidly excreted in the urine, although traces could still be detected after 24 hours. Unabsorbed trientine is eliminated through fecal excretion.
Special Populations and Conditions
Pediatrics: A non-compartmental pharmacokinetic analysis of four pediatric patients with confirmed Wilson’s Disease, who were aged 12 years or older and who were receiving a stable regimen of daily trientine (0.3˗0.9 g/day), demonstrated similarity with pharmacokinetic parameters in adult patients with Wilson’s Disease. There are no pharmacokinetic data available for pediatric patients less than 12 years of age.
Health Canada has not authorized an indication for pediatric use in children less than 5 years of age (see 1.1 Pediatrics).
Geriatrics: There are no data available for the pharmacokinetic parameters of trientine in the elderly.
11 STORAGE, STABILITY AND DISPOSAL
Keep container tightly closed.
Store refrigerated between 2° to 8°C. Do not freeze. After opening, the bottle can be stored at room temperature for 2 months, then discarded.
Store in the original container and retain the silica gel sachet in the bottle in order to protect from moisture.
12 SPECIAL HANDLING INSTRUCTIONS
Because of the potential for contact dermatitis, any site of exposure to the capsule contents should be washed with water promptly.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: Trientine Hydrochloride
Chemical name: 1,2-Ethanediamine,N,N’-bis (2-aminoethyl)- dihydrochloride or Triethylenetetramine dihydrochloride
Molecular formula and molecular mass: C6H18N4•2HCL, 219.16 g/mole
Structural formula:
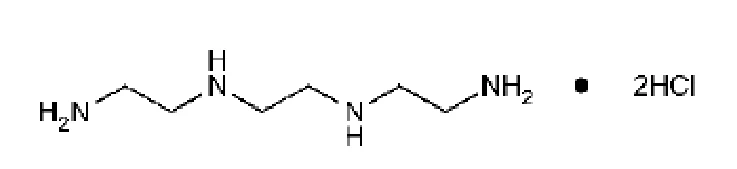
Physicochemical properties: White to pale yellow crystalline powder. Freely soluble in water. Soluble in methanol. Slightly soluble in alcohol. Insoluble in chloroform and in ether.
14 CLINICAL TRIALS
14.1 Clinical Trials by Indication
The Treatment Of Patients With Wilson's Disease Who Are Intolerant To Penicillamine.
Summary of patient demographics for clinical trials in patients with Wilson’s Disease
A total of 405 patients with Wilson’s Disease were evaluated in a retrospective cohort study, which included 380 patients followed at tertiary health care centres in Central Europe by specialist physicians responsible for their care. There were 25 additional patients from the EUROWILSON patient registry who were included in this retrospective analysis, with all of these registry patients receiving trientine hydrochloride monotherapy as treatment for Wilson’s Disease.
Data were collected in this study over a mean of 13.3 years after treatment initiation for Wilson’s Disease. Patients in this study were categorised based on disease status at the time of disease diagnosis, as either asymptomatic, with hepatic disease, with neurologic disease, or with combined hepatic or neurologic presentations. The presence of Kayser–Fleischer rings at slit- lamp examination and hepatic cirrhosis was recorded at study entry.
Patients whose disease course was considered stable were followed yearly. However, upon treatment initiation or following a change in drug treatment, patients were followed more intensively, i.e., at 3, 6 and 12 months, until clinically stable.
Patients received initial treatment with chelation therapy, if symptomatic. The choice of initial chelating agent for each patient, whether penicillamine or trientine hydrochloride, was left to the discretion of attending medical staff. Patients who were treated with zinc salts were excluded from study analysis.
For purposes of study analysis, two treatment regimens in patients were identified for this retrospective analysis, either penicillamine monotherapy, or trientine hydrochloride monotherapy. Stable drug treatment periods of at least six (6) consecutive months were included in the study analyses. Efficacy analyses were conducted on initial and/or subsequent treatment regimens of penicillamine and trientine hydrochloride. In addition, analyses of the cause of treatment discontinuations were conducted.
From patient records, hepatic and neurologic outcomes were assessed at 6, 12, 24, 36 and to a maximum of 48 months, following initiation of each treatment regimen, with outcome measures stratified by first-line and second-line treatment use. Hepatic outcome measures were assessed using clinical symptoms, as well as liver function tests. The presence and/or progress of neurologic disease were evaluated by physician assessment. Both hepatic and neurologic outcomes were categorised as unchanged, improved to normal, improved but not normal, deteriorated, or asymptomatic, over the period of time assessed.
Results of study in patients with Wilson’s Disease
Treatment regimens from a total of 405 patients were reviewed for the analysis. Of these patients, 207 patients (51.1%) presented with hepatic symptoms only, 92 patients (22.7%) presented with neurologic symptoms only, 52 (12.8%) presented with both hepatic and neurologic symptoms, and 54 (13.3%) were asymptomatic. At the time of diagnosis, 21 patients (5.2%) presented in hepatic failure with a fulminant disease course.
Changes in study treatments were common in the study dataset. In total, 467 chelator-based treatment regimens of a duration of at least six months were identified and analysed. Of these, 326 were penicillamine treatment regimens, while 141 were trientine regimens. Of the 326 penicillamine treatment regimens identified for analysis, 294 were first-line therapies, whereas the majority of trientine monotherapies, i.e., 105 of 141, were second-line therapies. None of these patients received penicillamine and trientine concomitantly at any time.
Efficacy was determined for both first-line and second-line study treatments for the last available follow-up evaluation of a 6-month to 48-month follow-up period.
In symptomatic hepatic patients treated with chelator therapy as second-line treatment when first-line treatment failed or was not tolerated, 75.0% of penicillamine treatment regimens and 68.9% of trientine hydrochloride regimens were associated with improvement in hepatic signs and symptoms. For symptomatic hepatic patients, the observed incidence of patients who maintained stable hepatic disease was comparable for penicillamine and trientine hydrochloride treatment in second-line settings. A non-significant trend to increased rates of hepatic deterioration was seen when trientine hydrochloride was used as second-line treatment, compared to second-line penicillamine treatment, however, the majority of second-line trientine hydrochloride-treated patients, at 91.1%, were not observed to have such deterioration. On the other hand, in patients who initially presented free of hepatic symptoms, no worsening in hepatic status was observed for any of these patients who received either of the chelation monotherapy treatment regimens evaluated.
With respect to neurologic outcomes in patients with Wilson’s Disease having symptomatic neurologic disease at baseline, rates of improvement following second-line penicillamine treatment were noted at 23.1%, compared to 51.0% with second-line trientine hydrochloride. Stable neurologic disease was reported in 69.2% of second-line penicillamine treatment regimens, compared to 33.3% of second-line trientine hydrochloride treatments. In this study, neurologic worsening was reported in neurologically symptomatic patients at study entry treated with second-line trientine hydrochloride at 15.7%, compared with second-line penicillamine treatment at 7.3%.
Overall, these efficacy analyses demonstrate the utility of trientine hydrochloride in the treatment of patients with Wilson’s Disease as second-line therapy. In patients with symptomatic hepatic disease,
69% given trientine hydrochloride as second-line therapy, due to intolerance or inadequate response to penicillamine, were observed to have shown hepatic improvement with trientine hydrochloride, while 51% of patients with symptomatic neurological disease at study entry were observed to have shown improvement in these symptoms with trientine hydrochloride when used as second-line treatment.
Over a median follow-up period of over 13 years, study treatment regimens that were discontinued for any reason were 43.6% of penicillamine treatment regimens, compared with 25.5% of trientine hydrochloride treatment regimens.
14.2 Comparative Bioavailability Studies
An open label, randomized, single-dose, two-way, crossover comparative bioavailability study of WAYMADE-TRIENTINE 250 mg capsules (Waymade PLC) and SYPRINE® 250 mg capsules (Valeant Pharmaceuticals North America LLC, USA) was conducted in healthy, adult, male subjects under fasting conditions. Comparative bioavailability data from 38 subjects that were included in the statistical analysis are presented in the following table:
Table 3: Summary Table of the Comparative Bio-Availability Data
Trientine (1 x 250 mg) From measured data Geometric Mean Arithmetic Mean (CV %) | ||||
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 90 % Confidence Interval |
AUCT (ng.h/mL) | 3632.17 4298.19 (56.25) | 3787.00 4444.25 (60.64) | 95.9 | 87.1 – 105.6 |
AUCI (ng.h/mL) | 3804.38 4475.81 (55.74) | 3968.54 4616.42 (58.67) | 95.9 | 87.2 – 105.4 |
Cmax (ng/mL) | 817.15 936.71 (47.52) | 826.50 933.561 (50.93) | 98.9 | 90.3 – 108.2 |
Tmax3 (h) | 1.50 (0.33 – 4.50) | 1.50 (0.50 – 3.50) | ||
| T½4 (h) | 13.52 (59.65) | 13.44 (40.48) | ||
1 WAYMADE-TRIENTINE (trientine dihydrochloride) capsules, 250 mg (Waymade PLC)
2 Syprine® (trientine hydrochloride) capsules, 250 mg (Valeant Pharmaceuticals North America LLC, USA)
3 Expressed as the median (range) only
4 Expressed as the arithmetic mean (CV %) only
15 MICROBIOLOGY
No microbiological information is required for this drug product.
16 NON-CLINICAL TOXICOLOGY
General Toxicology
Mice administered trientine in drinking water exhibited more inflammation of the lung interstitium, including alveolar histiocytic infiltration, liver periportal fatty infiltration, and hematopoietic cell proliferation in the spleen. Body and kidney weights as well as renal cytoplasmic vacuolization were reduced in males. The NOAEL was considered to be 92 and 99 mg/kg/day in males and females, respectively.
Rats administered oral doses of trientine up to 600 mg/kg/day for 26 weeks displayed dose- related incidence and severity of focal chronic interstitial pneumonitis with fibrosis of the alveolar walls, indicative of persistent inflammation or a toxic effect on alveolar cells. As trientine has irritating properties, it was suggested that the accumulation of trientine in bronchial epithelial cells and alveolar pneumocytes had a cytotoxic effect resulting in chronic interstitial pneumonitis. The NOAEL was considered to be 50 mg/kg/day for females and less than 50 mg/kg/day for males as no NOAEL was established.
Dogs administered oral doses of trientine up to 200 mg/kg/day in repeat-dose toxicity studies demonstrated reversible underactivity, tremors, abnormal gait, limited use of limb, and prone posture. The NOAEL was established at 50 mg/kg/day.
Carcinogenicity
No carcinogenicity studies have been conducted with trientine.
Genotoxicity
In vitro, trientine was mutagenic in the Ames test, the Salmonella typhimurium mutation assay, and the sister-chromatid exchange assay in Chinese hamster ovary cells. In hepatocytes, it also produced unscheduled DNA synthesis activity, indicating the induction of primary damage in this assay.
In vivo, trientine was negative in the mouse micronucleus test.
Reproductive and Developmental Toxicology
A study of oral prenatal trientine exposure (doses of 0, 3000, 6000, and 12000 ppm in drinking water) in mice demonstrated that trientine had stronger fetal than maternal adverse effects. Fetal tissues demonstrated low dose-dependent copper concentrations at doses higher than 3000 ppm, which was calculated as approximately 500 mg/kg/day in pregnant mice, and morphological abnormalities in the brain. Fetal resorption increased and fetal viability was reduced in a dose-dependent manner and serum copper concentrations were lower in dams that experienced total resorption at 6000 or 12000 ppm. The effects observed may be due, at least in part, to induction of copper deficiency.