


Product Monograph - Gadopentetate Dimeglumine Injection, USP
INDICATIONS AND CLINICAL USE
Gadopentetate Dimeglumine Injection, USP, by intravenous injection, is indicated for contrast enhancement during cranial and spinal MRI investigations in adults and children, to detect lesions associated with abnormal vascularity or those thought to alter the blood-brain barrier.
Gadopentetate Dimeglumine Injection, USP is also indicated for use with MRI in adults to provide contrast enhancement and facilitate visualization of lesions with abnormal vascularity within the head (extracranial) and neck.
CONTRAINDICATIONS
Gadolinium-based contrast agents (GBCAs) increase risk for Nephrogenic Systemic Fibrosis (NSF) in patients with renal insufficiency. Gadopentetate Dimeglumine Injection, USP is contraindicated:
- In patients with chronic severe kidney insufficiency (glomerular filtration rate <30 mL/min/1.73m2)
- In patients with acute kidney injury
- In neonates up to 4 weeks of age due to their immature renal function
Gadopentetate Dimeglumine should not be administered to patients who are known or suspected of being hypersensitive to it.
WARNINGS
Serious Warnings and Precautions
NEPHROGENIC SYSTEMIC FIBROSIS Gadolinium-based contrast agents (GBCAs) increase the risk for Nephrogenic Systemic Fibrosis (NSF) in patients with renal insufficiency. Gadopentetate Dimeglumine Injection, USP is contraindicated in:
The use of Gadopentetate Dimeglumine in patients with mild to moderate renal impairment (GFR ≥30 to <89 mL/min/1.73m2) needs to be weighed against the risk of performing alternative medical imaging by health care professionals. Gadopentetate Dimeglumine Injection, USP should be used with caution in infants less than 1 year of age. NSF may result in fatal or debilitating systemic fibrosis affecting the skin, muscle, and internal organs. Before administering Gadopentetate Dimeglumine Injection, USP, screen patients for acute kidney injury and any other conditions that may reduce renal function. For patients at risk for chronically reduced renal function (e.g., age >60 years, diabetes mellitus or chronic hypertension), estimate the GFR through laboratory testing. In these patients described above, avoid use of Gadopentetate Dimeglumine Injection, USP unless the diagnostic information is essential and not available with non-contrast enhanced magnetic resonance imaging (MRI). When administering Gadopentetate Dimeglumine Injection, USP, do not exceed the recommended dose (see DOSAGE AND ADMINISTRATION section) and allow a sufficient period of time for elimination of the agent from the body prior to any readministration. (See WARNINGS – General; WARNINGS – Renal Impairment; PRECAUTIONS – Skin; and ADVERSE REACTIONS – Postmarket Adverse Drug Reactions). |
General
MRI procedures which involve the use of Gadopentetate Dimeglumine by injection should be carried out by physicians who have the prerequisite training and a thorough knowledge of the particular procedure to be performed.
Nephrogenic Systemic Fibrosis (NSF)
Gadolinium-based contrast agents (GBCAs) may increase the risk for Nephrogenic Systemic Fibrosis (NSF) in patients with acute or chronic renal insufficiency of any severity. In these patients, avoid use of GBCAs unless the diagnostic information is essential and not available with non-contrast enhanced magnetic resonance imaging (MRI). For patients receiving hemodialysis, healthcare professionals may consider prompt hemodialysis following GBCA administration in order to enhance the contrast agent's elimination. However, it is unknown if hemodialysis prevents NSF.
Among the factors that may increase the risk for NSF are repeated or higher than recommended doses of a GBCA and the degree of renal function impairment at the time of exposure.
NSF development is considered a potential class-related effect of all GBCAs.
Postmarketing reports have identified the development of NSF following single and multiple administrations of GBCAs. These reports have not always identified a specific agent. Where a specific agent was identified, the most commonly reported agent was gadodiamide (Omniscan®), followed by Gadopentetate Dimeglumine and gadoversetamide (OptiMARK®). NSF has also developed following the sequential administration of gadodiamide with gadobenate dimeglumine (MultiHance®) or gadoteridol
(ProHance®). The number of postmarketing reports is subject to change over time and may not reflect the true proportion of cases associated with any specific GBCA.
The extent of risk for NSF following exposure to any specific GBCA is unknown and may vary among the agents. Published reports are limited and predominantly estimate NSF risks with gadodiamide. In 1 retrospective study of 370 patients with severe renal insufficiency who received gadodiamide, the estimated risk for development of NSF was 4%. (1) The risk, if any, for the development of NSF among patients with mild to moderate renal insufficiency or normal renal function is unknown, and the cautious utilization of the lowest possible dose of GBCA is preferable.
Screen all patients for acute kidney injury, renal dysfunction and other conditions that may reduce renal function. Features of acute kidney injury consist of rapid (over hours to days) and usually reversible decrease in kidney function, commonly in the setting of surgery, severe infection, injury or drug-induced kidney toxicity. Serum creatinine levels and estimated GFR may not reliably assess renal function in the setting of acute kidney injury.
For patients at risk for chronically reduced renal function (e.g., age >60 years, diabetes mellitus or chronic hypertension), estimate the GFR through laboratory testing.
When administering a GBCA, do not exceed the recommended dose and allow a sufficient period of time for elimination of the agent from the body prior to any readministration. (See ACTION AND CLINICAL PHARMACOLOGY, WARNINGS - Renal Impairment and
DOSAGE AND ADMINISTRATION.)
A skin biopsy is necessary in order to exclude the diagnosis of similarly presenting skin disorders (eg, scleromyxedema). (See WARNINGS – Serious Warnings and Precautions; WARNINGS - Renal Impairment; PRECAUTIONS – Skin; and ADVERSE REACTIONS – Postmarket Adverse Drug Reactions.)
Hypersensitivity Reactions
The decision to use Gadopentetate Dimeglumine must be made after careful evaluation of the risk-benefit in patients with a history of allergic disposition or bronchial asthma or with any previous reaction to contrast media (2-4), since experience shows that these patients suffer more frequently than others from hypersensitivity reactions.
Patients who experience hypersensitivity reactions while taking beta blockers may be resistant to treatment effects of beta agonists.
Patients with cardiovascular disease are more susceptible to serious, even fatal outcomes of severe hypersensitivity reactions.
As with other intravenous contrast agents, Gadopentetate Dimeglumine can be associated with anaphylactic reactions, anaphylactoid/hypersensitivity or other idiosynchratic reactions characterized by cardiovascular, respiratory, or cutaneous manifestations, and ranging from mild to severe reactions including anaphylactic shock. (3) If such a reaction occurs, stop Gadopentetate Dimeglumine administration and immediately begin appropriate therapy, including resuscitation. These reactions often occur at least within half an hour of administration. Therefore, post-procedure observation of the patient is recommended. In rare cases delayed reactions (hours later or up to several days) may occur (see ADVERSE REACTIONS).
It is important for prompt action in the event of such incidents and to be familiar with the practice of emergency measures. To permit immediate counter-measures to be taken in emergencies, appropriate drugs and instruments (eg, endotracheal tube and ventilator) should be readily available.
As with other contrast-enhanced diagnostic procedures, it is important to closely observe patients with a history of drug reactions, allergy or hypersensitivity disorders, during and up to several hours after Gadopentetate Dimeglumine injection. (5, 6)
Injection Site Reactions
Skin and soft tissue necrosis, thrombosis, fasciitis, and compartment syndrome requiring surgical intervention (eg, compartment release or amputation) have occurred very rarely at
the site of contrast injection or the dosed limb. Total volume and rate of Gadopentetate Dimeglumine injection, extravasation of contrast agent, and patient susceptibility might contribute to these reactions. Phlebetis and thrombophlebitis may be observed generally within
24 hours after Gadopentetate Dimeglumine injection and resolve with supportive treatment. Determine the patency and integrity of the intravenous line before administration of Gadopentetate Dimeglumine injection. Assessment of the dosed limb for the development of injection site reactions is recommended.
Sickle Erythrocytes
Deoxygenated sickle cell erythrocytes have been shown in in vitro studies to align perpendicular to a magnetic field which may result in vaso-occlusive complications in vivo.
The enhancement of magnetic moment by gadopentetate dimeglumine may possibly potentiate sickle erythrocyte alignment. Gadopentetate Dimeglumine in patients with sickle cell anemia and other hemoglobinopathies has not been studied.
Renal Impairment
In patients with renal insufficiency, acute renal failure requiring dialysis or worsening renal function have occurred, mostly within 48 hours of Gadopentetate Dimeglumine injection. The risk of these events is higher with increasing dose of Gadopentetate Dimeglumine. Gadopentetate Dimeglumine should only be used after careful risk/benefit assessment in these patients, including consideration of possible alternative imaging methods, since contrast medium elimination is delayed in such cases. Use the lowest possible dose and evaluate renal function in patients with renal insufficiency (see DOSAGE AND ADMINISTRATION).
- Exposure to GBCAs increases the risk for NSF in patients with acute or chronic severe renal insufficiency (glomerular filtration rate <30 mL/min/1.73m2).
- Screen all patients for renal dysfunction by obtaining a history and/or laboratory tests.
- The risk, if any, for the development of NSF among patients with mild to moderate renal insufficiency or normal renal function is unknown, and the cautious utilization of the lowest possible dose of GBCA is preferable.
(See WARNINGS – Serious Warnings and Precautions; PRECAUTIONS – Skin; and ADVERSE REACTIONS – Postmarket Adverse Drug Reactions.)
Gadopentetate Dimeglumine is contraindicated for use in patients with acute or chronic severe kidney insufficiency (glomerular filtration rate <30 mL/min/1.73m2) (See CONTRAINDICATIONS).
Evaluate all patients for renal dysfunction prior to administration of Gadopentetate Dimeglumine. For patients at risk for chronically reduced renal function (e.g., age >60 years, diabetes mellitus or chronic hypertension) estimate the GFR through laboratory testing. The risk, if any for the development of NSF among patients with mild to moderate renal insufficiency or normal renal function is unknown, and the cautious utilization of the lowest possible dose of GBCA is preferable. Gadopentetate Dimeglumine should only be used after careful risk-benefit evaluation in patients with mild to moderate renal impairment (GFR ≥30 to <89 mL/min/1.73m2) (See WARNINGS).
Because gadopentetate is renally excreted, a sufficient period of time for elimination of the contrast agent from the body should be ensured prior to any re-administration in patients with renal impairment. Elimination half-life in patients with mild or moderate renal impairment is 3 to
4 hours. Elimination half-life in patients with severe renal impairment is about 11 hours, and about 75% of the administered dose was recovered in the urine within two days.
Gadopentetate Dimeglumine can be removed from the body by hemodialysis. (See SYMPTOMS AND TREATMENT OF OVERDOSAGE.)
After 3 consecutive daily dialysis sessions of 3 hours each, about 97% of the administered dose is eliminated from the body, by about 70% with each dialysis session.
For patients already receiving hemodialysis at the time of Gadopentetate Dimeglumine administration, prompt initiation of hemodialysis following the administration of Gadopentetate Dimeglumine should be considered, in order to enhance the contrast agent's elimination.
No studies have been conducted in children with severe renal or hepatic dysfunction, clinically unstable or uncontrolled hypertension, or in premature infants.
Special Populations
Pediatrics
Gadopentetate Dimeglumine is contraindicated in neonates up to 4 weeks of age.
Gadopentetate Dimeglumine should be used with caution in infants less than 1 year of age (See WARNINGS - Serious Warnings and Precautions)
PRECAUTIONS
General
Gadopentetate Dimeglumine is to be administered strictly by intravenous injection. Gadopentetate Dimeglumine will cause tissue irritation and pain if administered extravascularly or if it leaks interstitially.
A sweet taste may be experienced briefly by patients receiving a bolus injection of Gadopentetate Dimeglumine intravenously.
As with any paramagnetic contrast agent, Gadopentetate Dimeglumine might impair the visualization of lesions seen on noncontrast MRI. Therefore, caution should be exercised when Gadopentetate Dimeglumine MRI scans are interpreted without a companion noncontrast MRI scan.
Transient increases or decreases in blood pressure may occur after the administration of
Gadopentetate Dimeglumine. Caution should be exercised by the patient when driving or operating machinery.
Hemolytic States
Gadopentetate dimeglumine alters red blood cell morphology resulting in transient, slight, extravascular (splenic) hemolysis with increased serum iron and total bilirubin levels. Although this effect was of no clinical significance during clinical trials, caution is advised in patients with hepatic disease and/or hemolytic states.
Convulsive States
While there is no evidence suggesting that Gadopentetate Dimeglumine directly precipitates convulsion, the possibility that it may decrease the convulsive threshold in susceptible patients cannot be ruled out. Patients with seizure disorders or intracranial lesions may be at increased risk of seizure activity, as has been reported rarely in association with Gadopentetate Dimeglumine administration (see ADVERSE REACTIONS - Adverse Drug Reaction Overview). Precautionary measures should be taken with patients predisposed to seizure, eg, close monitoring and availability of injectable anticonvulsants (see DOSAGE AND ADMINISTRATION).
Skin
NSF was first identified in 1997 and has, so far, been observed only in patients with renal disease. This is a systemic disorder with the most prominent and visible effects on the skin. Cutaneous lesions associated with this disorder are caused by excessive fibrosis and are usually symmetrically distributed on the limbs and trunk. Involved skin becomes thickened, which may inhibit flexion and extension of joints and result in severe contractures. The fibrosis associated with NSF can extend beyond dermis and involve subcutaneous tissues, striated muscles, diaphragm, pleura, pericardium, and myocardium. NSF may be fatal. (See WARNINGS – Serious Warnings and Precautions; WARNINGS – General; WARNINGS – Renal Impairment; and ADVERSE REACTIONS – Postmarket Adverse Drug Reactions.)
Paediatric
The cautious utilization of the lowest effective dose (0.1 mmol/kg BW) in children is recommended, particularly for neonates and infants, as the pharmacokinetics of Gadopentetate Dimeglumine in neonates and infants with immature renal function have not been studied (see WARNINGS – Renal Impairment).
Pregnancy
Gadopentetate dimeglumine retarded fetal development slightly when given intravenously for 10 consecutive days to pregnant rats at daily doses of 0.25, 0.75, and 1.25 mmol/kg (2.5, 7.5 and 12.5 times the human dose based on body weight) and when given intravenously for 13 consecutive days to pregnant rabbits at daily doses of 0.75 and 1.25 mmol/kg (7.5 and 12.5 times the human dose respectively, based on body weight) but not at daily doses of 0.25 mmol/kg. No congenital anomalies were noted in rats or rabbits.
Adequate and well controlled studies were not conducted in pregnant women. Gadopentetate Dimeglumine should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus.
Nursing Mothers
Gadopentetate Dimeglumine is excreted in human milk. Gadopentetate Dimeglumine was administered intravenously to lactating women with normal renal function at a dose of 0.1 mmol/kg body weight. In these women, less than 0.04% of the administered gadolinium was excreted into the breast milk during the 24-hour period following dosing. Breast milk obtained during the 24 hours following dosing revealed the average cumulative amount of gadolinium excreted in breast milk was 0.57 +/- 0.71 μmols.
The overall duration of excretion of gadolinium into breast milk is unknown. The extent of the absorption of Gadopentetate Dimeglumine in infants and its effect on the breast-fed child remains unknown. Caution should be exercised when Gadopentetate Dimeglumine Injection, USP is administered to a nursing woman.
Use in the Elderly
No special precautions are required for elderly patients (see WARNINGS – Serious Warnings and Precautions).
Drug Interactions
No interactions studies with other medicinal products have been conducted.
Interference with Diagnostic Tests
Serum iron determination using methods measuring complexes (e.g. Bathophenanthroline) may result in low values for up to 24 hours after the administration of Gadopentetate Dimeglumine. This value may be a falsely low value due to the free DTPA contained in Gadopentetate Dimeglumine.
ADVERSE REACTIONS
Adverse Drug Reaction Overview
Side effects in association with the use of Gadopentetate Dimeglumine are usually mild to moderate and transient in nature. However, serious or severe and life-threatening reactions as well as death have been reported.
Nausea, vomiting, headache, dizziness, a sensation of pain, a general feeling of warmth and injection site warmth or coldness are the most frequently recorded reactions.
Gadopentetate Dimeglumine will cause tissue irritation and pain if administered extravascularly.
Clinical Trial Adverse Drug Reactions
Most adverse reactions to Gadopentetate Dimeglumine develop soon after injection; however, the possibility of delayed reactions cannot be ruled out. The most frequently reported adverse reactions following administration of Gadopentetate Dimeglumine were:
| Headache | 8.7%1a |
| in some cases severe | 1.3% |
| Injection Site Discomfort | 6.7% |
| Nausea | 3.2% |
| Localized Pain in Other Parts | |
| of the Body (back, ear, eye, teeth) | 2.8% |
| Hypersensitivity-Type Skin |
1a 42.3% of all cases of headache were considered unrelated to MAGNEVIST administration
| and Mucosal Reactions | 2.1% |
| Dizziness | 1.5% |
| Vomiting | 1.2% |
| Paresthesia | 1.2% |
Adverse reactions occurred in 11 of 319 (3.4%) paediatric patients receiving Gadopentetate Dimeglumine in clinical trials (headache, vasodilatation, dizziness, diarrhea, ear pain, tachycardia, fever, edema, seizure, vomiting, nausea, and urticaria). This adverse reaction profile is consistent with the adverse reaction profile observed in adults.
Transient increases or decreases in blood pressure have been observed to occur after the administration of Gadopentetate Dimeglumine in clinical trials. Three cases of clinically significant hypotension have occurred 2 to 6 hours after Gadopentetate Dimeglumine injection. A relationship to the contrast medium could not be determined. (See PRECAUTIONS - General.)
Convulsions were reported in 4 patients with a history of seizures.
Laboratory Changes
Reversible mild elevations over baseline in serum iron, transaminase, and total bilirubin were observed in clinical trials. Other disturbances in laboratory values (transient increases in liver function tests) have not been associated with the use of Gadopentetate Dimeglumine in clinical trials. Gadopentetate Dimeglumine does not interfere with serum and plasma calcium measurements determined by colorimetric assays.
Postmarket Adverse Drug Reactions
Nephrogenic Systemic Fibrosis
Postmarketing reports have identified the development of NSF following single and multiple administrations of GBCAs. These reports have not always identified a specific agent. Where a specific agent was identified, the most commonly reported agent was gadodiamide (Omniscan®), followed by gadopentetate dimeglumine and gadoversetamide (OptiMARK®). NSF has also developed following the sequential administration of gadodiamide with gadobenate dimeglumine (MultiHance®) or gadoteridol (ProHance®). Cases of nephrogenic systemic fibrosis (NSF) have been reported with Gadopentetate Dimeglumine. The number of postmarketing reports is subject to change over time and may not reflect the true proportion of cases associated with any specific GBCA. The extent of risk for NSF following exposure to any specific GBCA is unknown and may vary among the agents. Published reports are limited and predominantly estimate NSF risks with gadodiamide. In 1 retrospective study of 370 patients with severe renal insufficiency who received gadodiamide, the estimated risk for development of NSF was 4%. (1) The risk, if any, for the development of NSF among patients with mild to moderate renal insufficiency or normal renal function is unknown, and the cautious utilization of the lowest possible dose of GBCA is preferable. (See also WARNINGS – Serious Warnings and Precautions; WARNINGS – Renal Impairment; PRECAUTIONS – General, PRECAUTIONS – Skin.)
Additional Postmarket Adverse Drug Reactions
Overall, the most serious adverse drug reactions in patients receiving Gadopentetate Dimeglumine are:
- Nephrogenic systemic fibrosis
- Anaphylactoid reactions / anaphylactoid shock
Delayed hypersensitivity / anaphylactoid reactions (hours later up to several days) have been rarely observed. (See WARNINGS - Hypersensitivity Reactions.)
The following adverse reactions, listed according to body system, have been reported after administration of Gadopentetate Dimeglumine:
Cardiovascular: heart rate decreased / bradycardiab2 vasodilatation, pallor, thrombophlebitis, non-specific ECG changes, substernal pain, angina, blood pressure increased, tachycardiab, syncopeb, arrhythmia, disturbance of cardiac function, cardiac arrestb
Central nervous system: headache, dizziness, agitation, paresthesia, tinnitus, visual field defect, convulsionsb, hyperesthesia, disorientation, somnolenceb burning sensation, visual disturbance, parosmia, speech disorder, hearing impaired, comab, tremor
Gastrointestinal: nausea, vomiting, abdominal pain, stomach discomfort, thirst, increased salivation, dysgeusia, oral soft tissue pain and paresthesia, diarrhea
Respiratory system: dry mouth, throat irritation, pharyngolaryngeal pain / pharynx discomfort, rhinorrhea, cough, apnea, respiratory rate increased or respiratory rate decreased, respiratory distress, pulmonary edemab
Cutaneous / mucous membranes: sweating, nephrogenic systemic fibrosis (NSF)b, flushing
Miscellaneous: injection site reactions (e.g. injection site coldness, paresthesia, swelling, warmth, burning, pain, edema, irritation, hemorrhage, erythema, discomfort, necrosis, thrombophlebitis, phlebitis, inflammation, extravasation), toothache, pain in extremity, asthenia, pyrexia, edema peripheral, fatigue, chills, malaise, back pain, ear pain, eye pain, lacrimation, arthralgia, vasovagal reactions, body temperature increased or body temperature decreased, feeling hot, feeling cold, chest pain
Laboratory tests: serum iron increasedb and blood bilirubin increased
Immune system: hypersensitivity / anaphylactoid reaction (e.g. anaphylactoid shockb, anaphylactoid reactionb, hypersensitivity reactionsb, shockb, hypotensionb, loss of
consciousnessb, throat tightnessb, sneezing, urticaria, pruritus, rash, erythema, dyspneab, respiratory arrestb, bronchospasmb, wheezing, laryngospasmb, laryngeal edemab, pharyngeal edemab, cyanosisb, rhinitis, angioedemab, edema faceb, reflex tachycardia, conjunctivitis)
2 bLife-threatening and/or fatal cases have been reported
Renal and Urinary: urinary incontinence, urinary urgency, increased serum creatinineb, acute renal failureb,3c
Hepato-biliary: hepatic enzyme increased
The following other adverse events were reported. A causal relationship has neither been established nor refuted:
Cardiovascular: death related to myocardial infarction or other undetermined causes, clinically relevant transient disturbance in heart rate
Central nervous system: anxiety, nystagmus, confusion
Gastrointestinal: constipation, anorexia
Postmarket ADRs in Patients with Dialysis-dependent Renal Failure
In patients with dialysis-dependent renal failure who received Gadopentetate Dimeglumine, delayed and transient inflammatory-like reactions such as fever, chills, and C-reactive protein increase have been commonly observed. These patients had the MRI examination with Gadopentetate Dimeglumine on the day before hemodialysis. (7-9)
SYMPTOMS AND TREATMENT OF OVERDOSAGE
| For management of suspected drug overdosage, consult your regional poison control centre. |
In the event of inadvertent overdosage or in the case of severely impaired renal function, Gadopentetate Dimeglumine can be removed from the body by extracorporeal hemodialysis. Renal function should be monitored in patients with renal impairment.
It is unknown if hemodialysis reduces the risk of NSF.
DOSAGE AND ADMINISTRATION
Dosing Considerations
Special preparation of the patient for examination with Gadopentetate Dimeglumine is not required; however, precautionary measures should be taken with patients predisposed to seizure, eg, close monitoring and availability of injectable anticonvulsants (see PRECAUTIONS). The usual safety rules for MRI (eg, exclusion of ferromagnetic vascular clips) must be observed.
Young children, infants, and neonates may require sedation prior to undergoing an MRI examination, in order to eliminate movement artifacts.
Use the lowest possible dose and evaluate renal function in patients with renal insufficiency. Gadopentetate Dimeglumine should only be used after careful risk/benefit assessment, including consideration of possible alternative imaging methods, in these patients (see WARNINGS).
Recommended Dose and Dose Adjustment
The following dosage guidelines apply to adults and children (including neonates and
3 c In patients with preexisting renal impairment.
infants):
| Recommended Dose: | 0.2 mL/kg (0.1 mmol/kg) |
| Route of Administration: | intravenous (into a large vein, if possible) |
| Rate of Administration: | 10 mL/min or as a bolus injection at 10 mL/15 sec |
| Maximum Single Dose per Injection: | 0.2 mL/kg body weight, to a maximum of 20 mL |
Elderly population (aged 65 years and above)
No dosage adjustment is considered necessary in elderly (aged 65 years and above). In clinical studies, no overall differences in safety or efficacy were observed between elderly (aged 65 years and above) and younger patients. Other reported clinical experience has not identified differences in responses between the elderly and younger patients. (see PHARMACOLOGY - Human Studies).
Hepatic impairment
Since gadopentetate is exclusively eliminated in an unchanged form via the kidneys, no dosage adjustment is considered necessary in patients with moderate hepatic impairment.
Data on patients with severe hepatic impairment are not available (see PHARMACOLOGY - Human Studies).
Administration
In children below two years of age the required dose should be administered manually and not in combination with an autoinjector to avoid injury.
To ensure complete injection of the contrast medium, the injection should be followed by a 5 mL normal saline flush.
If strong clinical suspicion of an intracranial or intraspinal lesion persists, despite a normal MRI scan, the diagnostic yield of the examination may be increased by giving another injection of Gadopentetate Dimeglumine equivalent to the original total dose within 30 minutes and performing MRI again.
No light protection during handling is required. For further information see PHARMACEUTICAL INFORMATION - Stability and Storage Recommendations.
Gadopentetate Dimeglumine Injection, USP should be visually inspected before use. Gadopentetate Dimeglumine Injection, USP should not be used in case of severe discoloration, the occurrence of particulate matter or a defective container.
Gadopentetate Dimeglumine Injection, USP should not be drawn into the syringe until immediately before use. The rubber stopper should never be pierced more than once. Any unused portion must be discarded upon completion of the procedure.
In the absence of compatibility studies, this medicinal product must not be mixed with other medicinal products.
T1-weighted scanning sequences are particularly suitable for contrast-enhanced examinations.
Important Note
The imaging procedure should be completed within one hour. Optimal contrast is generally observed in cranial investigations within 27 minutes following injection of Gadopentetate Dimeglumine and in spinal investigations during the early postadministration phase (10-30 minutes).
In neonates and infants, optimal CNS contrast has been observed to persist for several hours after Gadopentetate Dimeglumine administration. (See PRECAUTIONS – Paediatric.)
PARTT II: SCIENTIFIC INFORMATION
PHARMACEUTICAL INFORMATION
Drug Substance
| Trade Name: | Gadopentetate Dimeglumine Injection, USP |
| Proper Name: | Gadopentetate dimeglumine (USAN) |
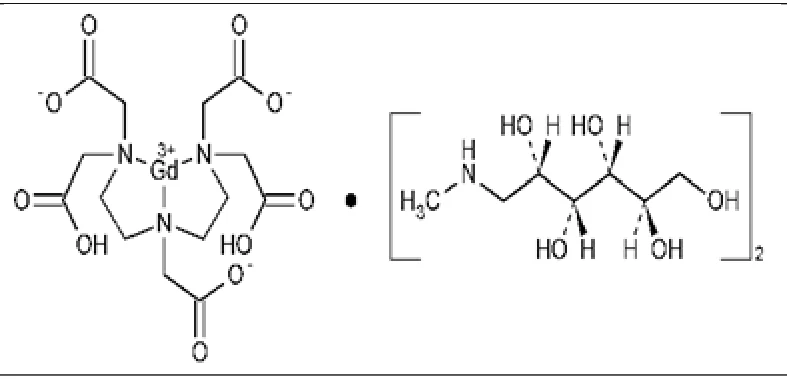
| Chemical Name: | Gadolinate(2-),[N,N-bis[2-[bis(carboxymethyl) amino]ethyl]glycinato(5-)]-, dihydrogen, compound with 1-deoxy-1-(methylamino)- D-glucitol(1:2) |
| Structural Formula: | |
| Molecular Formula: | C14 H20Gd N3O10 . (C7H17NO5)2 |
| Molecular Weight: | 938.02 |
| Solubility: | Freely soluble in water |
| Osmolality: | 1960 mOsm/kg H2O at 37ºC |
Composition
Gadopentetate Dimeglumine Injection, USP for intravenous injection is provided as a sterile, clear, colourless to slightly yellow aqueous solution. Each mL contains 469.01 mg gadopentetate dimeglumine (equivalent to 0.5 mmol/mL), 0.99 mg meglumine, and 0.40 mg diethylenetriamine pentaacetic acid.
Stability and Storage Recommendations
Gadopentetate Dimeglumine Injection, USP should be stored at 15ºC to 30ºC. Gadopentetate Dimeglumine Injection, USP is sensitive to light. Keep the container in the outer carton in order to protect from light. After the vial has been opened, Gadopentetate Dimeglumine Injection, USP remains chemically, physically and microbiologically stable for 24 hours at temperatures not exceeding 30°C and must be discarded thereafter.
AVAILABILITY OF DOSAGE FORMS
Gadopentetate Dimeglumine Injection, USP is provided as a sterile, clear, colourless to slightly yellow aqueous solution. Each mL contains 469.01 mg gadopentetate dimeglumine (equivalent to 0.5 mmol/mL), 0.99 mg meglumine, and 0.40 mg diethylenetriamine pentaacetic acid.
Gadopentetate Dimeglumine Injection, USP is supplied in 20 mL, 15 mL, 10 mL and 5 mL single-dose vials packaged in individual cartons.
PHARMACOLOGY
Animal Studies
Neuropharmacology
The neuropharmacology of gadopentetate dimeglumine was evaluated in rats, following single pericerebral or intracisternal injection. The ED50, based on postural anomalies, seizures, or death, and the LD50 determinations indicated that gadopentetate dimeglumine is considerably less toxic than gadolinium chloride or meglumine diatrizoate. In a similar study, the addition of up to 1.0 mg of free DTPA/mL did not affect the neural tolerance of the gadopentetate dimeglumine (Table 1).
Table 1: A Comparison of the ED50 and LD50 of Gadopentetate Dimeglumine, Gadolinium Chloride, and Meglumine Diatrizoate Following Pericerebral or Intracisternal Administration in Rats
| Compounds | Dose Level (μmol/kg) | ED50 (μmol/kg) | Dose Level (μmol/kg) | LD50 (μmol/kg) |
| Pericerebral Administration | ||||
| Gadopentetate Dimeglumine | 25-296.3 | 96.6 | 463-1852 | 1141.4 |
| 97.1 | 1227.3 | |||
| Gadopentetate Dimeglumine with 1.0 mg DTPA/m | 25-296.3 | 80.2 | 463-1852 | 1063.4 |
| Gadolinium Chloride | 5-25 | 10.8 | 6-100 | 14.9 |
| Meglumine Diatrizoate | 32-53 | 35.0 | 32-53 | 42.8 |
| Intracisternal Administration | ||||
| Gadopentetate Dimeglumine | 16.7-197.9 | 74.0 | 309-1233 | 654.9 |
| 86.2 | a | a | ||
| Gadopentetate Dimeglumine with 0.15 mg DTPA/mL | 16.7-197.9 | 80.0 | a | a |
| Gadopentetate Dimeglumine with 1.0 mg DTPA/mL | 16.7-197.9 | 85.0 | a | a |
| Gadolinium Chloride | 3.3-16.7 | 5.6 | 4-17 | 8.1 |
| Meglumine Diatrizoate | 4-21 | 11.2 | 32-126 | 54.9 |
a - Not evaluated in the study.
Cardiovascular and Hemodynamic Effects
The cardiovascular and hemodynamic effects of gadopentetate dimeglumine were assessed in healthy anesthetized dogs following intravenous administration of 0.25 or 1.25 mmol/kg of body weight. A slight increase in peripheral resistance was noted at the low-dose level. Those dogs receiving 1.25 mmol/kg initially displayed reduced peripheral resistance, lower blood pressure and heart rate, and an increase in the left ventricular end-diastolic pressure, stroke volume, and cardiac output. Thereafter, the peripheral resistance increased, and there was a significant increase in blood pressure which persisted at the same level for the remainder of the experiment.
The hemodynamic effects of gadopentetate dimeglumine were also assessed in dogs with acute ischemia-induced heart failure using doses of 0.25 mmol/kg and 0.75 mmol/kg intravenously. The 0.25 mmol/kg dose elicited a slight decrease in diastolic blood pressure and peripheral resistance and a slight increase in left ventricular dp/dt, cardiac output and stroke index. All parameters returned to the normal range 5 to 10 minutes after administration. The 0.75 mmol/kg dose also elicited a similar transient response in hemodynamic parameters.
Renal Tolerance
The renal tolerance of gadopentetate dimeglumine was examined in rabbits following an intravenous dose of 2 mmol/kg. A slight effect on urinary protein excretion was seen in comparison to a sorbitol control solution; however, gadopentetate dimeglumine exhibited better renal tolerance than other X-ray contrast agents. No effect was seen on serum creatinine or urea-nitrogen levels which served as indicators of renal function. Furthermore, no histological effects could be detected in the kidneys after the 1-week observation period.
Physicochemical and Biochemical Properties
The pharmacological properties of gadopentetate dimeglumine were determined by a battery of in vitro and in vivo tests following intravenous administration in dogs, rabbits and baboons. Gadopentetate dimeglumine was shown to be highly hydrophilic and, consequently, had no protein binding ability and did not interfere with enzyme activity. In short, the compound was physiologically inert at concentrations anticipated for human use.
Effect on Coagulation
Gadopentetate dimeglumine was evaluated using thromboelastography and citrated dog blood for its in vitro effect on the coagulation process. Concentrations up to 29 mmol/L did not affect the coagulation process of citrated dog blood when compared with a control thromboelastogram obtained with normal saline.
Efficacy
The efficacy of gadopentetate dimeglumine was established in rats, rabbits and baboons following intravenous administration for diagnostic MRI. Intravenous doses of 0.01 to 1.0 mmol/kg of body weight enhanced the contrast between healthy and pathological tissue (infarcts, tumors, and inflammations). Since gadopentetate dimeglumine was excreted in the urine, it also enhanced renal contrast in the rat at doses as low as 0.01 mmol/kg of body weight.
Pharmacokinetics
Gadopentetate dimeglumine was administered orally and/or intravenously in the rat (males, pregnant females or lactating females), rabbit (pregnant females), dog (females), and baboon (males) to investigate absorption, distribution, metabolism, and excretion.
After oral administration, radiolabelled gadopentetate dimeglumine was very poorly absorbed from the gastrointestinal tract of rats and dogs and was excreted almost completely in the faeces (ca. 96% in the rat and 94% in the dog).
After intravenous injection, the compound was excreted primarily in the urine (90% in the rat and >96% in the dog). In renally-impaired rats, biliary excretion of radiolabelled gadopentetate accounted for 2% of the dose in 4 hours when both kidneys were occluded.
Intravenous doses of gadopentetate dimeglumine did not result in any significant accumulation in tissues studied in the rat, rabbit, dog, or baboon. However, in rats with total renal impairment, 3.5% of the radiolabelled gadopentetate dimeglumine dose was secreted into the stomach and bowel 4 hours after intravenous administration. These results suggest that this compound can be secreted into the gastrointestinal tract, particularly when severe renal impairment exists.
Following single intravenous administrations of radiolabelled gadopentetate dimeglumine (0.5 mmol/kg) to pregnant rabbits, peak concentrations of radiolabelled gadolinium in the fetuses appeared after 30 minutes. In the dam plasma, liver, heart, and uterus concentrations remained stable after 15 and 30 minutes. Fetal tissue concentrations were ca. 4% after 15 minutes and 8% after 30 minutes of that in the dams' plasma (corresponding to 0.11% and 0.26% of the total dose, respectively). By 120 minutes, fetal concentrations decreased to 1/4 of peak value. The fetal elimination half-life was 30 to 50 minutes, similar to that of maternal plasma and tissue.
Following intravenous administrations of radiolabellled gadopentetate dimeglumine to pregnant rats, the compound was shown to be rapidly distributed, did not pass the blood-brain or placental barriers and cleared within 24 hours postadministration.
In lactating rats that were given intravenous administrations of the radiolabelled gadopentetate dimeglumine less than 0.2% of the administered dose was transferred to the offspring via the maternal milk. In rats, absorption from the gastrointestinal tract after oral administration was found to be small with about 4% absorbed.
Intravenous doses of radiolabelled gadopentetate dimeglumine administered to dogs exhibited no evidence of any metabolism occurring during passage through the body. High performance liquid chromatography did not detect any unchelated gadolinium ion in the animals.
Human Studies
Pharmacokinetics
The pharmacokinetic profile of Gadopentetate Dimeglumine was investigated in male volunteers undergoing Magnetic Resonance Imaging (MRI) of the kidneys and urinary bladder during an open label safety and efficacy study conducted in Europe. A single dose of Gadopentetate Dimeglumine was administered intravenously into a cubital vein of each of 20 healthy male volunteers. Four dose levels, ranging from 0.005 mmol/kg to 0.25 mmol/kg, were evaluated in groups of 5 subjects each.
Pharmacokinetic analysis of the plasma concentration versus time data for the 2 highest doses (0.1 and 0.25 mmol/kg) showed that the disposition of gadopentetate dimeglumine in the body follows a 2-compartment model with a mean distribution half-life of 0.2 hour and a mean elimination half-life of 1.6 hours. Dose-dependent kinetics were not observed for the 0.1 and 0.25 mmol/kg doses. Gadopentetate is exclusively eliminated in the urine with an average for all four doses of 83% excreted within 6 hours, and 91% of the dose excreted by 24 hours postinjection. No metabolites of gadopentetate were found in urine, indicating that gadopentetate, which forms the active ingredient of the MRI contrast agent, remains intact. In lactating women (aged 23-38 years), less than 0.04% of administered gadopentetate is excreted into human breast milk.
The urinary and plasma elimination rates (111±19 mL/min and 122±14 mL/min, respectively) for gadopentetate are essentially identical. The volume of distribution (266±43 mL/kg) is equal to the calculated volume of extracellular water, and the clearance is similar to that of substances which are subject to glomerular filtration, eg, inulin and 51Cr-EDTA. In man, the plasma half-life (1.6 hours) is similar to that reported for dogs and also similar to the elimination characteristics of commonly used x-ray contrast agents for angio-urography.
Clinical Laboratory Evaluations
Clinical laboratory evaluations revealed elevations in serum iron and, in some cases, serum bilirubin levels, which were considered to be definitely drug-related. In about 15% of female and 30% of male patients, increases in serum iron levels above baseline were noted. The increases appeared within 2 to 4 hours postinjection and declined within 24 hours postinjection. By 48 hours postinjection, the levels had returned to baseline. Hemoglobin, hematocrit, red blood cell count, and liver function enzymes were unaffected. This effect is considered to be due to a slight degree of hemolysis, probably extravascular and too small to result in a change in hemoglobin, hematocrit, or red blood cell count.
Although Gadopentetate Dimeglumine is not a risk for patients with normal hematological status, it is possible that those patients with hematolytic anemia may be at an increased risk, since gadopentetate dimeglumine appears to exert an effect on red blood cell morphology. About 8% of the patients who show a rise in serum iron levels also show a rise in serum bilirubin levels, apparently because these patients are somewhat less efficient in conjugating
bilirubin resulting from hemolysis.
Clinical Studies in Adults with Cranial and Spinal Lesions
The efficacy of Gadopentetate Dimeglumine as an MRI contrast enhancement agent in the diagnosis and evaluation of brain lesions and lesions of the spine and associated tissues was demonstrated in 6 pivotal clinical trials and in 3 special studies in which films were read by independent evaluators.
In the 6 clinical trials, a total of 597 patients (571 Gadopentetate Dimeglumine, 26 placebo) were evaluated for efficacy. 196 of these patients (55 brain, 141 spine) were evaluated for inclusion in the radiologist-reader evaluations of Gadopentetate Dimeglumine.
Assessment of efficacy included global efficacy evaluations, intensity scores and film evaluations (including contrast, morphology, and diagnosis).
Contrast enhancement: following the injection of Gadopentetate Dimeglumine, an increase in intensity scores was seen for all tissue types evaluated (healthy tissue, lesion, edema, and necrosis). Comparative intensity scores, which showed the relative contrast between tissue types, were calculated for the pre- and post-Gadopentetate Dimeglumine scan. Gadopentetate
Dimeglumine greatly increased the difference in intensity scores between lesion, edema, and healthy tissue compared to the pretreatment difference. Similar increases in contrast were seen for lesion-edema and lesion-necrosis comparisons.
In 5 of the 6 studies (cranial and spinal), contrast enhancement was assessed as an increase in intensity of a lesion compared to its surrounding environment. 292 (86%) of 339 patients showed enhancement after Gadopentetate Dimeglumine. None of the scans from 26 placebo patients showed enhancement.
In 4 of the 6 studies, additional lesions were detected in 113 (24%) of 466 patients following the administration of Gadopentetate Dimeglumine.
Diagnostic ability: the diagnostic ability of the investigators was improved or facilitated with Gadopentetate Dimeglumine in 107 (66%) of 162 patients in the cranial studies. In the spinal studies, diagnosis was facilitated in 131 (78%) of 169 patients.
Change in diagnosis: in the cranial and spinal studies a change in diagnosis was made by the investigators in 129 (41%) of 317 patients who showed enhancement with Gadopentetate dimeglumine. Cranial lesions which were enhanced by Gadopentetate Dimeglumine were compatible with presenting symptoms in 95% of cases. The most common diagnostic changes in the cranial studies were: nonspecific neoplasms, meningiomas, metastases, and glial cell tumors. In the spinal studies, the most common change was increased differentiation of scar tissue from abnormal disc material (recurrent postoperative back pain studies) and a better delineation of spinal lesions (changes in lesion size, location, and configuration) in patients with suspected spinal tumors.
Film evaluations: film evaluation revealed better contrast in 2/3 of patients with T1-weighted scans and more than 1/3 of patients with T2-weighted scans. From a group of 167 patients in the cranial studies for whom neither T1-weighted nor T2-weighted pre- Gadopentetate Dimeglumine scans were diagnostic, diagnosis became possible after the injection of Gadopentetate Dimeglumine in 122 patients (73%).
In the independent radiologist-reader evaluations of the cranial and spinal scans, a significant improvement in the number of lesions detected was observed after Gadopentetate Dimeglumine. This would have a significant impact on prognosis or treatment, especially in patients where enhanced visualization results in a change of diagnosis, such as a change from negative to positive findings or from a solitary lesion to metastatic disease. The evaluation also showed that Gadopentetate Dimeglumine significantly increased diagnostic accuracy when compared with MRI alone or with computed tomography (CT).
Diagnostic mode (pulse sequence): T1-weighted scans provided better enhancement in 138 (93%) of 148 patients in the cranial studies. T2-weighted was the better diagnostic mode for 10 (7%) patients. In the spinal studies (postoperative back pain), the T1-weighted mode provided better enhancement in 55 (95%) of 58 patients and the T2-weighted mode provided better enhancement for 3 (5%) patients.
Time of the best scan: the time of the best scan in the cranial studies was determined both by global efficacy evaluation and by analysis of contrast score results after film evaluations. Both evaluations demonstrated that early post-injection images are best for diagnosis. Of 148 patients with contrast enhancement, 108 (73%) had the best image within 27 minutes of the injection of Gadopentetate Dimeglumine. Of these, more than half had the best scan within 14 minutes of the injection of contrast agent. In spinal investigations, the early postinjection scans (10-30 minutes) also tended to provide the best images.
Clinical Studies in Children with Cranial and Spinal Lesions
The efficacy of Gadopentetate Dimeglumine was demonstrated in 2 pivotal clinical studies, involving 142 children with a preliminary diagnosis of CNS abnormality, based upon diagnostic methods other than MRI. Their ages ranged from newborn to 18 years. MRI was performed on all patients before and after the administration of 0.2 mL/kg (0.1 mmol/kg) Gadopentetate Dimeglumine. Some patients were given an additional 0.1 mmol/kg dose within 30 minutes of the first dose, if this was necessary to make a diagnosis.
Contrast evaluations: after Gadopentetate Dimeglumine injection, the contrast-to-noise ratio of the magnetic resonance images increased notably, with a further increase in those patients receiving a second Gadopentetate Dimeglumine injection. The signal intensity ratio of lesion to normal tissue was significantly increased for head and spinal T1 scans after Gadopentetate Dimeglumine injection.
Investigator ratings of lesion contrast compared to normal tissue and of lesion demarcation compared to surrounding tissue improved after Gadopentetate Dimeglumine injection. Most ratings progressed from "none" or "poor" to "excellent".
Diagnostic usefulness: Gadopentetate Dimeglumine significantly improved the possibility of making a definitive diagnosis. For patients with demonstrated lesions (n=57) with the T1 or T2 scan, this possibility increased from 44% prior to Gadopentetate Dimeglumine injection, to 74% after Gadopentetate Dimeglumine injection. The diagnostic quality of both T1 and T2 scans significantly improved after Gadopentetate Dimeglumine injection, for patients with both normal and abnormal scans.
Lesion morphology was better characterized after Gadopentetate Dimeglumine administration in 11/70 (16%) patients, allowing a better assessment of cystic, necrotic, tumor, or blood components of the lesion. A gain of diagnostic information was documented for 22/40 (55%) patients, and was statistically significant.
Gadopentetate Dimeglumine was demonstrated to be useful in 40/70 (57%) patients. These include 14 patients who were found to have no abnormality after the final MRI, 14 patients in whom a lesion was observed post- Gadopentetate Dimeglumine only, 6 patients in whom a definitive diagnosis was only made possible post-Gadopentetate Dimeglumine , 3 patients in whom complete tumor resection was confirmed by absence of enhancement, 2 patients in whom the solid, cystic, or necrotic component of the lesion was further characterized, and 1 patient in whom the lesion size was better defined.
Clinical Studies in Adults with Head and Neck Lesions
The efficacy of Gadopentetate Dimeglumine as an MRI contrast enhancement agent was evaluated in 87 patients with head (extracranial) and neck lesions. Film sets from 78 of these patients were additionally assessed by radiologists (“blinded readers”) who had not participated in the clinical trials and were not apprised of patient history. Efficacy analyses consisted of comparisons between post-Gadopentetate Dimeglumine scans and corresponding pre- Gadopentetate Dimeglumine scans with respect to contrast enhancement, facilitation of visualization, and contrast scores.
Post- Gadopentetate Dimeglumine contrast enhancement of lesions was demonstrated for 78 of 87 (90%) patients in the clinical trials. When evaluated by blinded readers, contrast enhancement was demonstrated for 56 of the 66 (85%) film sets included in the final data set.
Facilitation of visualization was demonstrated primarily by showing that the post-Gadopentetate Dimeglumine scans provided additional radiologic information concerning parameters such as lesion location, size, configuration, and differentiation from edema or necrosis. Post-Gadopentetate Dimeglumine MR scans provided additional radiologic information for 63 of 87 (72%) patients in the clinical trials. Additionally, there was a significant improvement (P<0.001) in lesion visualization of post-Gadopentetate Dimeglumine MR scans versus pre-Gadopentetate Dimeglumine MR scans by the blinded readers. Post-Gadopentetate Dimeglumine scans provided a better visualization of lesion configuration versus pre-Gadopentetate Dimeglumine scans for 40 of the 60 (67%) scans where lesion configuration could be determined. Additional radiologic information was observed in 48 of 66 (73%) post- adopentetate Dimeglumine scans viewed by the blinded readers.
Each patient’s pre- and post- Gadopentetate Dimeglumine MR images were scored on a 4-point scale, measuring the relative intensity of a lesion in relation to its adjacent tissue (0=no contrast; 1=equivocal; 2=good; 3=excellent). For 63 of 86 (73%) patients in the clinical trials, post-Gadopentetate Dimeglumine contrast scores were higher than pre-Gadopentetate Dimeglumine scores (P<0.001). In the blinded reader evaluation, post-Gadopentetate Dimeglumine contrast scores were higher than pre- Gadopentetate Dimeglumine scores in 36 of 66 (55%) patients (P<0.001).
TOXICOLOGY
Data from non-clinical studies did not reveal specialized hazard in experimental animals based on conventional studies of safety pharmacology, systemic toxicity, genotoxicity, carcinogenic potential, and toxicity to reproduction.
Acute Toxicity
Acute intravenous studies have been carried out with gadopentetate dimeglumine in mice, rats, and dogs. Acute oral toxicity studies have been carried out in mice and rats.
Table 2:
Species Predominant Sex (number of animals / group) | Route of Administration, Dose (mmol/kg) | LD50 – Range (mmol/kg) | Relevant Prominent Findings |
| Mice, M (3) | oral, 0.25, 1.0, 5.0 | > 5.0 | None |
| Mice, M (3) | IV, 2.5, 5.0, 6.25, 7.5, 10.0 | 5.0 - 7.5 | Apathy, changes in respiration, disturbed gait |
| Mice, F (3) | IV, 6.25, 10.0, 12.5, 15.0 | 6.25 - 12.5 | |
| Rats, M (3) | oral, 0.2, 0.8, 4.0 | > 4.0 | None |
| Rats, M (3) | IV, 10.0, 11.5, 13.5, 15.0 | 11.5 - 15.0 | Prostration, apathy, accelerated respiration, disturbed gait |
| Rats, F (3) | IV, 7.5, 10.0, 12.5, 15.0 | 10.0 - 15.0 | |
| Dogs, M+F (3) | IV, 6.0 | >6.0 | Reddening of mucosa and skin, licking, tremor, haematuria, disturbances of gait, retching, vomiting and bleeding at the injection site. |
Subacute Toxicity
Table 3:
Species Predominant Sex (number of animals / group) | Route of Administration, Dose (mmol/kg) | LD50 – Range (mmol/kg) | Relevant Prominent Findings |
Rats 10/sex/dose | IV 1.0, 2.5, 5.0 | 5 doses/week for 4 weeks | 1.0 mmol\kg - without findings. From 2.5 mmol\kg onwards - Dose related apathy, increase in drinking water, consumption, recumbency, respiratory distress, vacuoles in epithelial cells of convoluted tubules and in liver parenchymal cells, slight decrease in hematological parameters, increased absolute and relative liver and kidney weights. Additionally after 5 mmol\kg - Convulsion, decrease in body weight gain, half of the animals died. |
Rats 5/males/dose | IV 2.5, 5.0 | once or 5 doses/ week for 4 weeks, with 8 and 16 day recovery period | Time-related and dose-related reversibility of renal and hepatic vacuolization. After 5 mmol/kg - atrophy of the spermatogenic cells, not reversible within 15 days. |
Dogs, Beagle 2/sex/dose | IV 0.25, 1.0, 2.5 | 5 doses/week for 4 weeks | 0.25 mmol/kg - without findings. From 1.0 mmol/kg onwards - dose related reddening of skin, vacuolization of proximal tubules. 2.5 mmol/kg - elevated kidney weights, decrease in body weight, increase in drinking water consumption. |
Rats, pregnant 25/females/dose | IV 0.25, 0.75, 1.25 | 10 days, day 6-15 of gestation | 0.25 - 0.75 mmol/kg - without findings. 1.25 mmol/kg - slight increase in wave-like curved ribs, slight retardation of ossification in the fetuses. |
Rabbits, pregnant 21-22 / females/dose | IV 0.25, 0.75, 1.25 | 13 days | 0.25 mmol/kg - without findings. 0.75 - 1.25 mmol/kg - dose-related retardation of fetal development. |
Mutagenicity Studies
Gadopentetate dimeglumine was evaluated for its mutagenic potential in vitro using both bacterial assays (S. typhimurium, E. coli) and mammalian tests (HGPRT test in V 79 cells, UDS test in hepatocytes, cellular transformation assay in C3H 10T1/2 cells); in vivo, the product was assessed using two different systems, namely the micronucleus test and dominant lethal assay.
There was no indication that gadopentetate dimeglumine possesses any mutagenic potential in vitro or in vivo.
Local Tolerance
Gadopentetate dimeglumine was evaluated for its ability to induce local irritation in rabbits following intravenous, paravenous, intramuscular, and subcutaneous administration. Intravenous administration of gadopentetate dimeglumine elicited only very slight evidence of irritation. However, paravenous, intramuscular or subcutaneous injections resulted in moderate local irritation.
REFERENCES
- 1. Marckmann P, Skov L, Rossen K, Dupont A, Damholt MB, Heaf JG, et al. Nephrogenic systemic fibrosis: suspected causative role of gadodiamide used for contrast-enhanced magnetic resonance imaging. J Am Soc Nephrol. 2006 Sep;17(9):2359-62.
- 2. Niendorf HP, Alhassan A, Balzer T, Claub W, Greens v. Safety and risk of Gadolinium-DPTA: extended clinical experience after more than 20 million applications. In: R Felix, A Heshiki, N Hosten and H Hricak, Editors, MAGNEVIST, Blackwell Wissenschafts-Verlag, Berlin, Germany 1998 (3rd rev. Ed.,):17-27.
- 3. Weiss KL. Severe anaphylactoid reaction after i.v. Gd-DTPA. Magn Reson Imaging. 1990;8(6):817-8.
- 4. Nelson KL, Gifford LM, Lauber-Huber C, Gross CA, Lasser TA. Clinical safety of gadopentetate dimeglumine. Radiology. 1995 Aug;196(2):439-43.
- 5. Morcos SK, Thomsen HS. Adverse reactions to iodinated contrast media. Eur Radiol. 2001;11(7):1267-75.
- 6. Shellock FG, Kanal E. Safety of magnetic resonance imaging contrast agents. J Magn Reson Imaging. 1999 Sep;10(3):477-84.
- 7. Krahe T, Gotz R, Lackner K, Haustein J, Klemenz U, Landwehr P, et al. [Pharmacokinetics of gadolinium-DTPA in chronic renal insufficiency requiring dialysis]. Rofo. 1992 Jun;156(6):523-6.
- 8. Lackner K, Krahe T, Gotz R, Haustein J. The dialysability of Gd-DTPA. In Bydder G et al. (Eds.) Contrast media in MRI Int. Workshop in Berlin, February 1-3, . 1990:321-6.
- 9. Tokmak F, al. e. Gadolinium-DTPA-induced acute phase reaction in hemodialysis patients. Congress for Nephrology. 2006.
- 10. Allen ED, Byrd SE, Darling CF, Tomita T, Wilczynski MA. The clinical and radiological evaluation of primary brain neoplasms in children, Part II: Radiological evaluation. J Natl Med Assoc. 1993 Jul;85(7):546-53.
- 11. Brasch RC, Weinmann HJ, Wesbey GE. Contrast-enhanced NMR imaging: animal studies using gadolinium-DTPA complex. AJR Am J Roentgenol. 1984 Mar;142(3):625-30.
- 12. Bydder GM, Brown J, Niendorf HP, Young IR. Enhancement of cervical intraspinal tumors in MR imaging with intravenous gadolinium-DTPA. J Comput Assist Tomogr. 1985 Sep-Oct;9(5):847-51.
- 13. Carr DH. The use of proton relaxation enhancers in magnetic resonance imaging. Magn Reson Imaging. 1985;3(1):17-25.
- 14. Carr DH, Brown J, Bydder GM, Weinmann HJ, Speck U, Thomas DJ, et al. Intravenous chelated gadolinium as a contrast agent in NMR imaging of cerebral tumours. Lancet. 1984 Mar 3;1(8375):484-6.
- 15. Claussen C, Laniado M, Schorner W. Computer Tomographic and Nuclear Magnetic Resonance Diagnoses of Cerebral Tumors Using Conventional and Paramagnetic Contrast Medium. Rontgen-B1. 1985;38:143-9.
- 16. Dietrich R. MR and Gadolinium Define Pediatric Brain Pathology. Diagnostic Imaging. 1989 February:69-103.
- 17. Eldevik OP, Brunberg JA. Gadopentetate dimeglumine-enhanced MR of the brain: clinical utility and safety in patients younger than two years of age. AJNR Am J Neuroradiol. 1994 Jun;15(6):1001-8.
- 18. Felix R, Schorner W, Laniado M, Niendorf HP, Claussen C, Fiegler W, et al. Brain tumors: MR imaging with gadolinium-DTPA. Radiology. 1985 Sep;156(3):681-8.
- 19. Goldstein EJ, Burnett KR, Hansell JR, Casaia J, Dizon J, Farrar B, et al. Gadolinium DTPA (an NMR proton imaging contrast agent): chemical structure, paramagnetic properties and pharmacokinetics. Physiol Chem Phys Med NMR. 1984;16(2):97-104.
- 20. Peterman SB, Steiner RE, Bydder GM, Thomas DJ, Tobias JS, Young IR. Nuclear magnetic resonance imaging (NMR), (MRI), of brain stem tumours. Neuroradiology. 1985;27(3):202-7.
- 21. Runge VM, Clanton JA, Herzer WA, Gibbs SJ, Price AC, Partain CL, et al. Intravascular contrast agents suitable for magnetic resonance imaging. Radiology. 1984 Oct;153(1):171-6.
- 22. Runge VM, Clanton JA, Price AC, Wehr CJ, Herzer WA, Partain CL, et al. The use of Gd DTPA as a perfusion agent and marker of blood-brain barrier disruption. Magn Reson Imaging. 1985;3(1):43-55.
- 23. Wesbey GE, Engelstad BL, Brasch RC. Paramagnetic pharmaceuticals for magnetic resonance imaging. Physiol Chem Phys Med NMR. 1984;16(2):145-55.
- 24.
Product Monograph for MAGNEVIST® (Gadopentetate Dimeglumine Injection). Bayer Inc.. Submission Control No.: 170935; Date of Revision: February 7, 2014.
Serious Warnings and Precautions
Gadolinium-based contrast agents (such as Gadopentetate Dimeglumine Injection, USP) increase the risk of a rare disease called Nephrogenic Systemic Fibrosis (NSF) in patients with kidney disease. Gadopentetate Dimeglumine Injection, USP should not be used in:
- Patients with chronic, severe kidney disease
- Patients with acute kidney injury
- New-borns up to 4 weeks of age due to their developing kidneys
Patients with mild to moderate kidney disease should only be given Gadopentetate Dimeglumine Injection, USP after a careful assessment by your physician.
Gadopentetate Dimeglumine Injection, USP should be used with caution in infants less than 1 year of age.
Your doctor will monitor your health before and after administration of Gadopentetate Dimeglumine Injection, USP if you are considered to be at risk for developing NSF (for details, see Nephrogenic Systemic Fibrosis).
PART III: CONSUMER INFORMATION
IMPORTANT: PLEASE READ
CONSUMER INFORMATION
Gadopentetate Dimeglumine Injection, USP
This leaflet is designed specifically for Consumers. This leaflet is a summary and will not tell you everything about Gadopentetate Dimeglumine. Contact your doctor or pharmacist if you have any questions about the drug.
ABOUT THIS MEDICATION
Gadopentetate Dimeglumine Injection, USP is a contrast medium for magnetic resonance imaging (MRI) of the head, neck and spine.
MRI is a form of medical imaging that uses a complex system of magnets and radiowaves to obtain pictures of normal and abnormal tissues.
What is does:
Gadopentetate Dimeglumine helps tissues viewed by MRI appear brighter to make it easier for the healthcare professional to see any potential abnormalities.
When it should not be used:
Gadolinium-based contrast agents (such as Gadopentetate Dimeglumine Injection, USP) increase the risk of a rare disease called Nephrogenic Systemic Fibrosis (NSF) in patients with kidney disease. Gadopentetate Dimeglumine Injection, USP should not be used in:
- Patients with chronic, severe kidney disease
- Patients with acute kidney injury
- New-borns up to 4 weeks of age due to their developing kidneys
If you are hypersensitive (experience allergy-like reactions) to gadopentetate dimeglumine or to any of the other ingredients of Gadopentetate Dimeglumine Injection, USP (see below).
What the medicinal ingredient is:
gadopentetate dimeglumine
What the important nonmedicinal ingredients are:
meglumine, and diethylenetriamine pentaacetic acid
What dosage forms it comes in:
Gadopentetate Dimeglumine is a ready-to-use solution (corresponding to 0.5 mmol/mL) for rapid injection into a vein.
WARNINGS AND PRECAUTIONS
BEFORE you are given Gadopentetate Dimeglumine Injection, USP, talk to your doctor if any of the following situations apply to you. The doctor will decide whether the intended examination is possible or not:
- You have or have had a previous reaction to contrast media.
- You suffer or have suffered from an allergy (eg, hay fever, hives) or asthma.
- You have very poor kidney function.
- You have recently had, or soon expect to have, a liver transplant.
- You have epilepsy or suffer from brain conditions with seizures.
- You are pregnant or could be pregnant (even if you are not sure), since Gadopentetate Dimeglumine Injection, USP should not be used under such circumstances unless it is considered absolutely necessary.
- You suffer from heart or blood circulation problems. This is because in the rare event that you do have an allergic reaction, it is more likely to be serious or fatal.
- You have sickle cell anemia, hemolytic conditions (destruction of red blood cells), or related blood disorders of hemoglobin in the blood (hemoglobinopathies).
- Heart problems, breathing difficulties, or skin reactions may occur with the use of Gadopentetate Dimeglumine Injection, USP. Severe reactions may occur. Most of these reactions occur within half an hour of administration. Therefore, your attending healthcare professional may observe you in this period. Delayed reactions may occur hours or even days later.
Gadopentetate Dimeglumine Injection, USP may increase or decrease blood pressure, so caution must be used when driving or operating machinery.
Kidney Impairment
Before you receive Gadopentetate Dimeglumine Injection, USP, your healthcare professional will check how well your kidneys are working. Patients with severe kidney disease should not be given Gadopentetate Dimeglumine Injection, USP (See WARNINGS AND PRECAUTIONS – Serious Warnings and Precautions). Patients with mild to moderate kidney disease should only be given Gadopentetate Dimeglumine Injection, USP after a careful assessment by your physician. Your doctor may decide to take a blood test to check this before making the decision to use Gadopentetate Dimeglumine Injection, USP.
If you have poor kidney function, your healthcare professional will make sure that Gadopentetate Dimeglumine Injection, USP has been eliminated from your body before you receive a second injection of Gadopentetate Dimeglumine Injection, USP.
Gadopentetate Dimeglumine can be removed from the body by dialysis. If you are already undergoing regular dialysis, your healthcare professional will decide if you should receive dialysis after you have been given Gadopentetate Dimeglumine Injection, USP.
Breastfeeding
Gadopentetate Dimeglumine is excreted in human breast milk. Discuss with your doctor.
Nephrogenic Systemic Fibrosis
There have been postmarket reports of a rare disease called Nephrogenic Systemic Fibrosis (NSF) following gadolinium-based contrast agent (GBCA) use.
NSF is a rare condition which has only been observed so far in patients with severe kidney disease. At present, there is no evidence that other patient groups are at risk of developing the condition. Due to NSF, the skin becomes thickened, coarse, and hard, which sometimes makes bending of the joints difficult. NSF may spread to other organs and even cause death.
Patients with severe kidney disease should avoid the use of Gadopentetate Dimeglumine Injection, USP unless the health care professional believes the possible benefits outweigh the potential risks. Those who have already had an MR imaging procedure and who have any of the following symptoms should seek medical attention as soon as possible:
- Swelling, hardening, and tightening of the skin
- Reddened or darkened patches on the skin
- Burning or itching of the skin
- Yellow spots on the whites of the eyes
- Stiffness in the joints, problems moving or straightening arms, hands, legs, or feet
- Pain deep in the hip bone or ribs
- Weakness of the muscles
Your healthcare professional will monitor your health after administering Gadopentetate Dimeglumine Injection, USP, if you are considered to be at risk of NSF.
INTERACTIONS WITH THIS MEDICATION
Drug interaction studies have not been done for Gadopentetate Dimeglumine.
Interference with Diagnostic Tests:
Before you have any blood tests, tell your healthcare professional you have been given Gadopentetate Dimeglumine Injection, USP. This is because some tests for iron levels in the blood may be affected for up to 24 hours after Gadopentetate Dimeglumine Injection, USP has been given.
Tell your healthcare professional if you are taking or have recently taken any other medicines, including medicines obtained without a prescription.
PROPER USE OF THIS MEDICATION
Usual dose:
Gadopentetate Dimeglumine Injection, USP is injected by a healthcare professional via a needle or catheter into a vein. The recommended dose of Gadopentetate Dimeglumine is 0.2 milliliters per kg body weight. The actual dosage (volume) of Gadopentetate Dimeglumine Injection, USP that is right for you will depend on your body weight.
If you receive a bolus injection of Gadopentetate Dimeglumine Injection, USP (a large dose quickly) you may notice a temporary sweet taste in your mouth.
Overdose:
In case of drug overdose, contact a health care practitioner, hospital emergency department or regional Poison Control Centre immediately, even if there are no symptoms.
You can help improve the safe use of health products for Canadians by reporting serious and unexpected side effects to Health Canada. Your report may help to identify new side effects and change the product safety information. 3 ways to report:
- Online at MedEffect (http://hc-sc.gc.ca/dhp-mps/medeff/index-eng.php);
- By calling 1-866-234-2345 (toll-free);
By completing a Consumer Side Effect Reporting Form and sending it by:
- Fax to 1-866-678-6789 (toll-free), or
Mail to: Canada Vigilance Program
Health Canada, Postal Locator 0701E
Ottawa, ON
K1A 0K9
Postage paid labels and the Consumer Side Effect Reporting Form are available at MedEffect (http://hc-sc.gc.ca/dhp-mps/medeff/index-eng.php).
NOTE: Contact your health professional if you need information about how to manage your side effects.
SIDE EFFECTS AND WHAT TO DO ABOUT THEM
Like all medicines, Gadopentetate Dimeglumine Injection, USP can cause side effects, although not everybody gets them.
Common side effects observed in clinical trials (between 1 and 10 in every 100 patients are likely to get these):
- Headache (in some cases severe)
- Injection site discomfort
- Nausea (feeling sick)
- Pain (back, ear, eye, teeth)
- Hypersensitivity (allergic-like reactions) such as rash, hives, and swelling of the skin and mucous membranes (eg, mouth, throat, lips)
- Dizziness
- Vomiting
- Paresthesia (“pins and needles”)
The most serious side effects in patients receiving Gadopentetate Dimeglumine are Nephrogenic Systemic Fibrosis (NSF) and anaphylactoid reactions (allergy-like reactions) including severe reactions such as shock.
In rare cases (1 to 10 in 10 000 patients), serious allergy-like reactions may occur including severe reactions such as shock that may need immediate medical intervention. If you notice mild swelling of the face, lips, tongue or throat, coughing or sneezing, difficulty in breathing, stopped breathing, itching, runny nose, hives, throat tightness, voice box spasm, blue lips, or lose consciousness, tell your healthcare professional immediately. These may be the first signs that a severe reaction is happening. Your investigation may need to be stopped, and you may need further treatment.
Delayed reactions hours to several days after the administration of Gadopentetate Dimeglumine, have been observed in rare cases. If this should happen to you tell your healthcare professional.
The following side effects have been life-threatening or fatal in some cases:
- Fainting
- Heart rhythm disturbances: slow heartbeat, fast heartbeat, irregular heartbeat, or chest pain
- Heart stopping (cardiac arrest)
- Fits or seizures
- Unresponsiveness
Coma
- Fluid in the lungs
- Nephrogenic systemic fibrosis (NSF)
- Acute kidney failure
| SERIOUS SIDE EFFECTS, HOW OFTEN THEY HAPPEN AND WHAT TO DO ABOUT THEM | ||||
| Symptom / Effect | Talk with your doctor or pharmacist | Stop taking drug and call your doctor or pharmacist | ||
Only if severe | In all cases | |||
| Rare | Serious allergy-like reactions, sometimes fatal, with symptoms such as swelling of the mouth and throat, difficulty in breathing, rash. | ✓ | ||
This is not a complete list of side effects. For any unexpected effects while taking Gadopentetate Dimeglumine Injection, USP, contact your doctor or pharmacist.
HOW TO STORE IT
Gadopentetate Dimeglumine Injection, USP should be stored at temperatures between 15°C to 30°C. Gadopentetate Dimeglumine Injection, USP is sensitive to light. Keep the container in the outer carton in order to protect from light.
REPORTING SUSPECTED SIDE EFFECTS
Jubilant DraxImage Inc.
You can report any suspected adverse reactions associated with the use of health products to Jubilant DraxImage Inc. by:
- Toll-free telephone: 1-888-633-5343
- E-mail: pharmacovigilance@jdi.jubl.com
Regular Mail : Jubilant DraxImage Inc.
16751 Trans Canada Hwy
Kirkland, Quebec
H9H 4J4
Canada
NOTE: Should you require information related to the management of side effects, please contact your health professional. Jubilant DraxImage Inc. does not provide medical advice.
MORE INFORMATION
For more information, please contact your health professional or pharmacist first, or
Jubilant DraxImage Inc. at 1-888-633-5343.
This document plus the full Product Monograph, prepared for health professionals can be found contacting the sponsor at: 1-888-633-5343.
Jubilant DraxImage Inc.
16751 Trans Canada Hwy
Kirkland, Quebec
H9H 4J4
Canada
Last revised: September 12, 2014