


Product Monograph - Radicava (Shionogi)
RECENT MAJOR LABEL CHANGES
| N/A |
|---|
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
RECENT MAJOR LABEL CHANGES ............................................................................................ 2
TABLE OF CONTENTS .............................................................................................................. 2
PART I: HEALTHCARE PROFESSIONAL INFORMATION ............................................................. 4
1 INDICATIONS ............................................................................................................... 4
1.1 Pediatrics .................................................................................................................... 4
1.2 Geriatrics .................................................................................................................... 4
2 CONTRAINDICATIONS ................................................................................................. 4
4 DOSAGE AND ADMINISTRATION ................................................................................. 4
4.1 Dosing Considerations ................................................................................................ 4
4.2 Recommended Dose and Dosage Adjustment ........................................................... 4
4.4 Administration ............................................................................................................ 5
4.5 Missed Dose ............................................................................................................... 5
5 OVERDOSE .................................................................................................................. 5
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ................................. 6
Description ....................................................................................................................... 6
7 WARNINGS AND PRECAUTIONS .................................................................................. 6
7.1 Special Populations .................................................................................................... 7
7.1.1 Pregnancy ................................................................................................................ 7
7.1.2 Breastfeeding .......................................................................................................... 7
7.1.3 Pediatrics ................................................................................................................. 7
7.1.4 Geriatrics ................................................................................................................. 8
8 ADVERSE REACTIONS .................................................................................................. 8
8.1 Adverse Reaction Overview ........................................................................................ 8
8.2 Clinical Trial Adverse Reactions .................................................................................. 8
8.3 Less Common Clinical Trial Adverse Reactions ......................................................... 11
8.5 Post-Market Adverse Reactions – RADICAVA ........................................................... 11
9 DRUG INTERACTIONS ................................................................................................ 11
9.2 Drug Interactions Overview ...................................................................................... 11
9.3 Drug-Behaviour Interactions .................................................................................... 11
9.4 Drug-Drug Interactions ............................................................................................. 11
9.5 Drug-Food Interactions ............................................................................................ 12
9.6 Drug-Herb Interactions ............................................................................................. 12
9.7 Drug-Laboratory Test Interactions ........................................................................... 13
10 CLINICAL PHARMACOLOGY ....................................................................................... 13
10.1 Mechanism of Action .............................................................................................. 13
10.2 Pharmacodynamics ................................................................................................ 13
10.3 Pharmacokinetics ................................................................................................... 13
11 STORAGE, STABILITY AND DISPOSAL ......................................................................... 17
12 SPECIAL HANDLING INSTRUCTIONS ........................................................................... 17
PART II: SCIENTIFIC INFORMATION ....................................................................................... 18
13 PHARMACEUTICAL INFORMATION ............................................................................ 18
14 CLINICAL TRIALS ........................................................................................................ 18
14.1 Clinical Trials by Indication ..................................................................................... 18
14.2 Comparative Bioavailability Studies ....................................................................... 20
15 MICROBIOLOGY ........................................................................................................ 20
16 NON-CLINICAL TOXICOLOGY ..................................................................................... 20
PATIENT MEDICATION INFORMATION .................................................................................. 23
INSTRUCTIONS FOR USE ....................................................................................................... 27
PART I: HEALTHCARE PROFESSIONAL INFORMATION
1 INDICATIONS
PrRADICAVA® is indicated for the treatment of patients with amyotrophic lateral sclerosis (ALS).
1.1 Pediatrics
No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use.
1.2 Geriatrics
Evidence from clinical studies and experience suggests that use in the geriatric population is not associated with differences in safety or effectiveness (see 7 WARNINGS AND PRECAUTIONS, Special populations, 7.1.4 Geriatrics).
2 CONTRAINDICATIONS
Edaravone is contraindicated in patients who are hypersensitive to this drug or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container (see 7 WARNINGS AND PRECAUTIONS, Hypersensitivity Reactions). For a complete listing, see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING.
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
Not applicable.
4.2 Recommended Dose and Dosage Adjustment
The recommended dose of RADICAVA (oral suspension) is 105 mg (5 mL) taken orally or via a feeding tube [Nasogastric (NG) tube or Percutaneous Endoscopic Gastrostomy (PEG) tube] according to the following schedule:
- An initial treatment cycle with daily dosing for 14 days, followed by a 14-day drug-free period
- Subsequent treatment cycles with daily dosing for 10 days out of 14-day periods, followed by 14-day drug-free periods.
RADICAVA (oral suspension) should be taken in the morning after fasting overnight for at least 8 hours and waiting at least 1 hour before eating or drinking anything except water.
For patients who are unable to fast overnight, the required fasting interval can be shortened depending on the type of meal (see Table 1 for specific fasting conditions, and see 10 CLINICAL PHARMACOLOGY and PATIENT MEDICATION INFORMATION, How to take RADICAVA (oral suspension).
Table 1: RADICAVA (oral suspension) Administration Relative to Type of Food Consumption
| Type of food/caloric supplement consumed | Fasting time before and after RADICAVA (oral suspension) dose administration with regard to meal type |
|---|---|
| High-fat meal (800-1000 calories, 50% fat) | 8 hours before administration and one hour after administration |
| Low-fat meal (400-500 calories, 25% fat) | 4 hours before administration and one hour after administration |
| Caloric supplement (250 calories, e.g., protein drink) | 2 hours before administration and one hour after administration |
No dosage adjustment is required in patients with hepatic impairment or mild and moderate renal impairment (see 10 CLINICAL PHARMACOLOGY, Special Populations and Conditions, Hepatic Insufficiency; Renal Insufficiency).
4.4 Administration
Take RADICAVA (oral suspension) using a 5 mL oral syringe that is provided to the patient with the product. Shake the RADICAVA (oral suspension) bottle vigorously up and down for at least 30 seconds before use.
RADICAVA (oral suspension) can be administered by mouth or via feeding tube. Silicone and polyvinyl chloride (PVC) feeding tubes can be used.
| Administration via | Tube Type (Tube diameter) | Flush volume |
|---|---|---|
| Nasogastric tube | Silicone, PVC (12-16 Fr) | 30 mL |
| Gastrostomy tube | Silicone, PVC (12-24 Fr) | 30 mL |
Before and after administration with a feeding tube, flush the tube with 30 mL (1 ounce) of water.
For complete details, refer to the PATIENT MEDICATION INFORMATION, How to take RADICAVA (oral suspension) and Instructions for Use.
4.5 Missed Dose
In case of a missed dose of RADICAVA (oral suspension), take the next dose as soon as possible after the time of the missed dose. Do not double the daily dose.
5 OVERDOSE
For the most recent information in the management of a suspected drug overdose, contact your regional poison control centre or Health Canada’s toll-free number, 1-844 POISON-X (1-844-764-
7669).
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 2: Dosage Forms, Strengths, Composition and Packaging
Description
RADICAVA (oral suspension) is a white to off-white suspension in a multi-dose child resistant 60 mL amber glass bottle which is supplied as two configurations:
| Unit of sale | Package configuration |
|---|---|
| RADICAVA (oral suspension) Starter Kit | Carton of two (2) inner cartons, each containing of one (1) bottle of 35 mL (105 mg/5 mL dose), two (2) oral dosing syringes and one bottle adapter. |
| RADICAVA (oral suspension) Kit | One carton of one (1) bottle of 50 mL (105 mg/5 ml dose), two (2) oral dosing syringes and one (1) bottle adapter |
7 WARNINGS AND PRECAUTIONS
Note
RADICAVA (injection) was discontinued from sale on April 1, 2025.
Neurologic
An imbalance of neurologic adverse events, such as gait disturbance, have been reported in placebo-controlled clinical trials (see 8.2 Clinical Trial Adverse Reactions). Neurological findings were also observed in dogs and monkeys administered edaravone (see 16 NON-CLINICAL TOXICOLOGY, Neurotoxicity).
Sensitivity/Resistance
Hypersensitivity Reactions:
Hypersensitivity reactions (redness, wheals and erythema multiforme) and cases of anaphylaxis (urticaria, decreased blood pressure and dyspnea) have been reported in spontaneous post marketing reports with RADICAVA (injection). Based on the spontaneous post marketing reports, it appears RADICAVA (injection) can cause anaphylactic reactions.
| Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
| Oral | Suspension / 105 mg / 5 mL | L-cysteine hydrochloride hydrate, phosphoric acid, polyvinyl alcohol, simethicone emulsion, sodium bisulfite, sodium hydroxide, sorbitol, xanthan gum, purified water |
Patients should be monitored carefully for hypersensitivity reactions. If hypersensitivity reactions occur, discontinue RADICAVA (injection)/ RADICAVA (oral suspension), treat per standard of care and monitor until the condition resolves. (see 2 CONTRAINDICATIONS).
Sulfite Allergic Reactions:
RADICAVA (injection) / RADICAVA (oral suspension) contain sodium bisulfite, a sulfite that may cause allergic type reactions, including anaphylactic symptoms and life-threatening or less severe asthmatic episodes in susceptible people. The overall prevalence of sulfite sensitivity in the general population is unknown. Sulfite sensitivity occurs more frequently in people with asthma.
Skin
A higher incidence of skin-related adverse events was identified in RADICAVA (injection) patients compared to placebo patients in pooled placebo-controlled clinical trials (26% RADICAVA; 19% placebo), including eczema (7% RADICAVA; 2% placebo), dermatitis contact (6% RADICAVA; 3% placebo), rash (4% RADICAVA; 2% placebo), and erythema (3% RADICAVA; 2% placebo). There was also one case of toxic skin eruption on RADICAVA (injection). Based on the clinical trial reports, it appears RADICAVA (injection) can cause skin reactions.
7.1 Special Populations
7.1.1 Pregnancy
There are no adequate data on the developmental risk associated with the use of RADICAVA (injection) / RADICAVA (oral suspension) in pregnant women. In animal studies, administration of edaravone to pregnant rats and rabbits resulted in adverse developmental effects (increased mortality, decreased growth, delayed sexual development, and altered behaviour) at clinically relevant doses. Most of these effects occurred at doses that were also associated with maternal toxicity (see 16 NON-CLINICAL TOXICOLOGY, Reproduction).
7.1.2 Breastfeeding
There are no data on the presence of edaravone in human milk, the effects on the breastfed infant, or the effects of the drug on milk production. Edaravone and its metabolites are excreted in the milk of lactating rats. Precaution should be exercised because many drugs can be excreted in human milk. The developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for RADICAVA (injection) / RADICAVA (oral suspension) and any potential adverse effects on the breastfed infant from RADICAVA (injection) / RADICAVA (oral suspension).
7.1.3 Pediatrics
No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use.
7.1.4 Geriatrics
Of the 184 patients with ALS who received RADICAVA (injection) in 3 placebo-controlled clinical trials, a total of 53 patients were 65 years of age and older, including 2 patients 75 years of age and older.
Of the 185 patients with ALS who received RADICAVA (oral suspension) in an open label clinical trial, a total of 65 patients were 65 years of age and older, including 6 patients 75 years of age and older.
No overall differences in safety or effectiveness were observed between these patients and younger patients.
8 ADVERSE REACTIONS
Note
RADICAVA (injection) was discontinued from sale on April 1, 2025.
8.1 Adverse Reaction Overview
The most common adverse reactions with RADICAVA in pooled placebo-controlled trials were contusion, gait disturbance, and headache.
Discontinuation due to an adverse event occurred in 2% (4/184) of RADICAVA (injection) patients vs 5% (10/184) of patients on placebo in pooled placebo-controlled trials. Discontinuation due to an adverse event occurred in 6% (11/185) of RADICAVA (oral suspension) patients in an open-label safety trial.
Overall, 4 patients (2%) on RADICAVA (injection) and 2 (1%) patients on placebo died during pooled placebo-controlled trials. All deaths in the trials were from respiratory disorder/failure. Six patients (3%) on RADICAVA (oral suspension) died during an open-label safety trial. The majority of deaths in the trial were from respiratory failure including 3 patients on RADICAVA (oral suspension).
8.2 Clinical Trial Adverse Reactions
RADICAVA (injection)
Because clinical trials are conducted under very specific conditions, the adverse reaction rates observed in the clinical trials, therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real world use.
The safety profile of RADICAVA (injection) was compared to placebo in 3 clinical trials:
- Two double-blind, randomized, placebo-controlled studies in patients with grade 1-2 ALS (Japanese severity classification). From these 2 studies, 171 patients received RADICAVA and 160 of the 171 patients completed the placebo-controlled period (6 months).
- One double-blind, randomized, placebo-controlled study in 25 patients with grade 3 ALS. Thirteen patients received RADICAVA and 9 of the 13 patients completed the 6-month trial.
In these double-blind randomized, placebo-controlled trials, patients were administered RADICAVA (injection) 60 mg (n=184) or placebo (n=184) in treatment cycles for 6 months of which 169 RADICAVA (injection) and 162 patients on placebo completed 6 months of treatment. The population consisted of Japanese patients who had a median age of 60 years (range 29-75) and were 59% male. Most (93%) of these patients were living independently at the time of screening.
RADICAVA (oral suspension)
The safety profile of RADICAVA (oral suspension) was evaluated in an open-label safety study in ALS patients (n=185). Of the 185 patients that received RADICAVA (oral suspension), 160 patients completed 6 months (interim analysis). The population consisted of White (58%), Japanese (35%), Asian – not Japanese (2%), and Black (2%) patients. The median age was 61 years (range 22-75) and 64% of patients were male.
Most Common Adverse Reactions Observed During Clinical Trials
Table 3: Adverse Reactions from Pooled Placebo-Controlled Trialsa that Occurred in ≥2% of patients treated with RADICAVA (injection) and ≥2% More Frequently than in Placebo Patients
| Adverse Reaction | RADICAVA (injection) (N=184) n (%) | Placebo (N=184) n (%) |
|---|---|---|
| Contusion | 27 (15%) | 16 (9%) |
| Gait disturbance | 23 (13%) | 17 (9%) |
| Headache | 18 (10%) | 11 (6%) |
| Dermatitis | 14 (8%) | 10 (5%) |
| Eczema | 12 (7%) | 7 (4%) |
| Respiratory failure, respiratory disorder, hypoxia | 11 (6%) | 7 (4%) |
| Glycosuria | 7 (4%) | 3 (2%) |
| Tinea infection | 7 (4%) | 4 (2%) |
a Pooled placebo-controlled studies include two additional studies [MCI186-16 (102 RADICAVA patients and 104 placebo patients) and MCI186-18 (13 RADICAVA patients and 12 placebo patients)], all using the same treatment regimen (see 14 CLINICAL TRIALS).
Table 4: Adverse Reactions from an Open-Label Safety Study that Occurred in ≥2% of patients treated with RADICAVA (oral suspension)
| Adverse Reaction | RADICAVA (oral suspension) (N=185) n (%) |
|---|---|
| Fall, Contusion, Ligament sprain, Skin abrasion, Skin laceration | 40 (22%) |
| Muscular weakness | 30 (16%) |
| Musculoskeletal pain | 24 (13%) |
| Fatigue, Asthenia | 18 (10%) |
| Constipation | 13 (7%) |
| Headache | 11 (6%) |
| Dyspnoea | 10 (5%) |
| Insomnia | 9 (5%) |
| Salivary hypersecretion | 9 (5%) |
| Upper respiratory tract infection | 9 (5%) |
| Abdominal pain | 8 (4%) |
| Dysphagia | 8 (4%) |
| Depression | 7 (4%) |
| Dizziness | 7 (4%) |
| Muscle spasms | 7 (4%) |
| Cough | 6 (3%) |
| Nausea | 6 (3%) |
| Peripheral swelling | 6 (3%) |
| Weight decreased | 6 (3%) |
| Amyotrophic lateral sclerosis | 5 (3%) |
| Anxiety | 5 (3%) |
| Arthralgia | 5 (3%) |
| Balance disorder | 5 (3%) |
| COVID-19 | 5 (3%) |
| Decreased appetite | 5 (3%) |
| Hypertension | 5 (3%) |
| Musculoskeletal stiffness | 5 (3%) |
| Rash | 5 (3%) |
| Diarrhoea | 4 (2%) |
| Dry skin | 4 (2%) |
| Respiratory failure | 4 (2%) |
8.3 Less Common Clinical Trial Adverse Reactions
List of less common adverse reactions reported in ≤ 2% of RADICAVA patients and that occurred at least 1% more frequently than in placebo patients, in pooled placebo-controlled trials.
- Gastrointestinal disorders: Abdominal pain, Abdominal pain upper, Gastritis
- General disorders and administration site conditions: Gait inability, Chest pain
- Hepatobiliary disorders: Hepatic steatosis, Liver disorder
- Infections and infestations: Tinea infection
- Injury, poisoning and procedural complications: Procedural pain
- Musculoskeletal and connective tissue disorders: Neck pain
Abnormal Laboratory Findings
In an open-label safety trial, CK elevation >3x ULN was noted in 16 (10%) RADICAVA oral suspension patients.
8.5 Post-Market Adverse Reactions – RADICAVA
The following adverse reactions have been identified during post-approval use of RADICAVA. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure.
- Hypersensitivity reactions and anaphylaxis
- Skin and subcutaneous tissue disorders
9 DRUG INTERACTIONS
9.2 Drug Interactions Overview
The pharmacokinetics of edaravone are not expected to be significantly affected by inhibitors of cytochrome P450 (CYP) enzymes, UGT conjugating enzymes, or major transporters. There is little potential for clinically significant interactions with drugs cleared by either CYP3A4 or the drug transporters BCRP or OAT3 at the recommended clinical dose of edaravone (see Table 5).
9.3 Drug-Behaviour Interactions
The interaction of RADICAVA with individual behavioural risks (e.g. cigarette smoking, cannabis use, and/or alcohol consumption) has not been studied.
9.4 Drug-Drug Interactions
The drugs listed in this table are based on drug interaction studies.
Table 5: Established Drug-Drug Interactions
| Edaravone | Source of Evidence | Effect | Clinical Comment |
|---|---|---|---|
| Sildenafil (CYP3A4 substrate) | CT | Simultaneous oral administration of edaravone did not result in clinically significant changes in the Cmax and AUC of sildenafil. | None |
| Rosuvastatin (BCRP substrate) | CT | Simultaneous oral administration of edaravone did not result in clinically significant changes in the Cmax and AUC of rosuvastatin. | None |
| Furosemide (OAT3 substrate) | CT | Simultaneous oral administration of edaravone did not result in clinically significant changes in the Cmax and AUC of furosemide. | None |
| Legend: CT = Clinical Trial | |||
In vitro studies demonstrated that, at the approved clinical dose, edaravone and its metabolites are not expected to significantly inhibit CYP enzymes (CYP1A2, CYP2B6, CYP2C8, CYP2C9, CYP2C19, CYP2D6 and CYP3A), conjugating enzymes UGT1A1 and UGT2B7, or transporters (p-gp, OATP1B1, OATP1B3, OAT1, OCT2, MATE1 and MATE2-K) in humans. Edaravone and its metabolites are not expected to induce CYP1A2 or CYP2B6, at the recommended clinical dose of edaravone.
9.5 Drug-Food Interactions
In order to maximize exposure, RADICAVA (oral suspension) should be taken in the morning after fasting overnight for at least 8 hours and waiting at least 1 hour after administration before eating or drinking anything except water. For patients who are unable to fast overnight, the required fasting interval can be shortened depending on the type of meal.
Please refer to 4 DOSAGE AND ADMINISTRATION, 10 CLINICAL PHARMACOLOGY, Pharmacokinetics, and the PATIENT MEDICATION INFORMATION for dosing details for oral administration.
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10 CLINICAL PHARMACOLOGY
Note
RADICAVA (injection) was discontinued from sale on April 1, 2025.
10.1 Mechanism of Action
The mechanism by which edaravone exerts its therapeutic effect in patients with ALS is unknown.
10.2 Pharmacodynamics
Cardiac Electrophysiology
At exposures approximately 5 times higher than that of the recommended dose of RADICAVA, edaravone did not prolong the QT interval to any clinically relevant extent in healthy Japanese male subjects.
10.3 Pharmacokinetics
A pharmacokinetic single-dose study of RADICAVA (injection) and RADICAVA (oral suspension) was performed in healthy adult subjects under fasting conditions.
Table 6 provides a description of this study, along with the comparative pharmacokinetic parameters for both oral and intravenous administration. RADICAVA (oral suspension) administered at the dose of 105 mg demonstrated an equivalent AUC compared to RADICAVA (injection) at a dose of 60 mg i.v. for 60 minutes, and a Cmax not less than that of RADICAVA (injection). RADICAVA (oral suspension) demonstrated similar pharmacokinetics following administration via feeding tubes and oral administration.
Table 6: Study Description and Summary of Pharmacokinetic Parameters of Unchanged Edaravone for Single Doses of 105 mg/mL Oral Suspension and 60 mg/60 min IV Formulation in Healthy Adult Subjects
| Study # | Trial design | Dosage, route of administration and duration | Study subjects (n) | Mean age (yrs) (Range) | Sex (%) |
|---|---|---|---|---|---|
| MCI186-J03 | Single-dose, randomized, open-label, crossover study | Oral suspension: 105 mg IV: 60 mg/60 min. | 42 | 33.1 (20 – 45) | Male (66.7%) Female (33.3%) |
| Single dose Treatment | Plasma PK Parameters | Cmax ng/mL | Tmax[a] (h) | AUC 0-t ng*h/mL | AUC0-∞ ng*h/mL | T1/2 (h) | CL (L/h) | F (%) |
Oral (N=42) | Mean CV% | 1656 44.3 | 0.50 0.25, 0.75 | 1743 30.7 | 1762 30.6 | 9.75 86.9 | 67.9[b] 44.4 | 57.3 21.9 |
IV (N=42) | Mean CV% | 1253 18.3 | 1.00 0.98, 1.02 | 1720 18.9 | 1736 19.1 | 8.82 94.4 | 35.9 20.9 | - - |
[a] Median and range [b] CL/F CV: Coefficient of variation
Absorption:
RADICAVA (oral suspension):
RADICAVA (oral suspension) is administered orally or via feeding tube. Edaravone is absorbed rapidly, with median peak concentrations occurring at approximately 0.5 hour (range: 0.25 to 0.75 hours) after fasted oral administration. The absolute bioavailability is about 57% because of a first pass effect when comparing 105 mg edaravone oral suspension and 60 mg edaravone intravenous formulation.
The maximum plasma concentration (Cmax) and area under the concentration-time curve (AUC) of edaravone increases more than dose-proportional over the dose range of 30 to 300 mg. Edaravone does not accumulate in plasma with once-daily administration.
Effect of Food on Absorption:
Following oral administration of a developmental edaravone oral suspension to healthy subjects, the Cmax decreased by 83% and the AUCT decreased by 61% with a high-fat meal (800 – 1000 calories, 50% fat) compared to fasted conditions. Following oral administration of edaravone 4 hours after a high-fat meal, the Cmax and AUCT decreased by 48% and 26%, respectively. Following oral administration of edaravone 2 hours after low-fat meal (400 – 500 calories, 25% fat), the Cmax and AUCT decreased by 46% and 20%, respectively.
Oral administration of an edaravone oral suspension to healthy subjects 8 hours after a high-fat meal, 4 hours after a low-fat meal or 2 hours after caloric supplement (250 calories, e.g., a protein drink), did not significantly impact the rate (Cmax) and extent (AUCT) of edaravone exposure. Administration of an oral suspension of edaravone 1 hour before a high-fat, high-calorie meal resulted in 34% and 16% decreases in the Cmax and AUCT, respectively; however, the decrease in exposure is not considered to be clinically significant.
In order to maximize exposure, RADICAVA (oral suspension) should be taken in the morning after fasting overnight for at least 8 hours and waiting at least 1 hour after administration before eating or drinking anything except water. For patients who are unable to fast overnight, the required fasting interval can be shortened depending on the type of meal (see 4 DOSAGE AND ADMINISTRATION and the PATIENT MEDICATION INFORMATION for dosing details).
RADICAVA (injection)
Following i.v. administration, the maximum plasma concentration (Cmax) of edaravone was reached by the end of infusion. There was a trend of a more than dose-proportional increase in area under the concentration-time curve (AUC) and Cmax of edaravone. With multiple-dose administration, edaravone does not accumulate in plasma.
Distribution:
Edaravone is bound to human serum proteins (92%), mainly to albumin, with no concentration dependence in the range of 0.1 to 50 micromol/L. Edaravone has a mean volume of distribution of 63.1 L following intravenous administration, suggesting substantial tissue distribution. Edaravone has an apparent volume of distribution of 164 L following oral administration.
Metabolism:
Edaravone is metabolized to a sulfate conjugate and a glucuronide conjugate, which are not pharmacologically active. Multiple uridine diphosphate glucuronosyltransferase (UGT) isoforms (UGT1A1, UGT1A6, UGT1A7, UGT1A8, UGT1A9, UGT1A10, UGT2B7, and UGT2B17) are involved in the glucuronidation of edaravone. In human plasma, edaravone is mainly detected as the sulfate conjugate, which is presumed to be formed by sulfotransferases. RADICAVA (oral suspension) results in 1.3- and 1.7-fold higher exposures for both sulfate and glucuronide metabolites, respectively, when compared to RADICAVA (injection) because of first pass metabolism.
Elimination:
Edaravone was excreted mainly in the urine as its glucuronide conjugate form (60-80% of the dose up to 48 hours). Approximately 6-8% of the dose was recovered in the urine as the sulfate conjugate, and <1% of the dose was recovered in the urine as the unchanged drug. In vitro studies suggest that the sulfate conjugate of edaravone is hydrolyzed back to edaravone, which is then converted to the glucuronide conjugate in the human kidney before excretion into the urine. The mean terminal elimination half-life of edaravone is approximately 9 hours. The half-lives of its metabolites are 3 to 6 hours. The total clearance of edaravone is estimated to be 35.9 L/h following intravenous administration, and the apparent total clearance of edaravone is estimated to be 67.9L/h following oral administration.
Special Populations and Conditions
- Pediatrics: No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use.
- Geriatrics: No age effect on edaravone pharmacokinetics has been found.
- Sex: No gender effect on edaravone pharmacokinetics has been found.
- Pregnancy and Breast-feeding: There are no adequate data on the developmental risk associated with the use of RADICAVA (oral suspension) and RADICAVA (injection) in pregnant women. There are no data on the presence of edaravone in human milk, the effects on the breastfed infant, or the effects of the drug on milk production.
- Ethnic Origin: There were no significant racial differences in Cmax and AUC of edaravone between Japanese and Caucasian subjects.
- Hepatic Insufficiency: Following a single IV infusion of 30 mg edaravone (half the recommended dose of RADICAVA (injection)) over 60 minutes, the mean Cmax and AUC0-∞ of unchanged edaravone were 1.20 and 1.17-fold greater in the subjects with mild hepatic impairment (Child-Pugh score of 5 or 6), 1.24 and 1.25-fold greater in the subjects with moderate hepatic impairment (Child-Pugh score of 7 to 9), and 1.20 and 1.19-fold greater in the subjects severe hepatic impairment (Child-Pugh score of 10 to 14) when compared to subjects with normal hepatic function, respectively. These changes in exposures are not considered to be clinically significant. No dosage adjustments are necessary in patients with hepatic impairment.
- Renal Insufficiency: Following a single IV infusion of 30 mg edaravone (half the recommended dosage of RADICAVA (injection)) over 60 minutes, the mean Cmax and AUC0-∞ of unchanged edaravone were 1.15 and 1.20-fold greater in the subjects with mild renal impairment (eGFR 60-89 mL/min/1.73m2), and 1.25 and 1.29-fold greater in the subjects with moderate renal impairment (eGFR 30-59 mL/min/1.73m2), when compared to subjects with normal renal function, respectively. These changes in exposures are not considered to be clinically significant. No dosage adjustments are necessary in patients with mild to moderate renal impairment. The effects of severe renal impairment on the pharmacokinetics of edaravone have not been studied.
11 STORAGE, STABILITY AND DISPOSAL
Pharmacy
Store RADICAVA (oral suspension) refrigerated between 2oC – 8oC and protect from light. Do not freeze. Store upright.
Patient
Store RADICAVA (oral suspension) upright at room temperature between 20°C–25°C. Protect from light.
Dispose of any RADICAVA (oral suspension) that is not used within 15 days after opening the bottle or within the 30 days (if unopened) from the date of shipment indicated on the carton label, whichever happens first.
RADICAVA (oral suspension) is supplied in cartons as listed below.
- RADICAVA (oral suspension) Starter Kit (14-day treatment cycle), including two (2) inner cartons, each containing one (1) bottle of 735 mg/35mL (105 mg/5 mL dose), two oral dosing syringes and one bottle adapter.
- RADICAVA (oral suspension) Kit (10-day treatment cycle), including one (1) bottle of 1050 mg/50 mL (105 mg/5 ml dose) with two oral dosing syringes and one bottle adapter.
12 SPECIAL HANDLING INSTRUCTIONS
Keep out of the sight and reach of children.
Discard 15 days after opening bottle or if unopened 30 days from date of shipment indicated on the carton pharmacy label.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Non-proprietary name of the drug substance(s): edaravone
Chemical name: 3-methyl-1-phenyl-2-pyrazolin-5-one
Molecular formula and molecular mass: The molecular formula is C10H10N2O and the molecular mass is 174.20.
Structural formula:
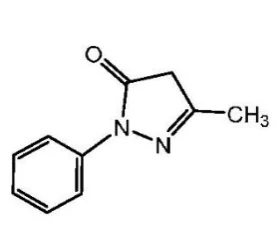
Physicochemical properties: Edaravone is a white crystalline powder with a melting point of 129.7°C. It is freely soluble in acetic acid, methanol, or ethanol and slightly soluble in water or diethyl ether.
14 CLINICAL TRIALS
Note
RADICAVA (injection) was discontinued from sale on April 1, 2025.
14.1 Clinical Trials by Indication
The efficacy of RADICAVA (injection) was established in a 6-month, randomized, placebo-controlled, double-blind study of intravenous RADICAVA (injection) (see Table 7).
Table 7: Summary of patient demographics for clinical trial of RADICAVA (injection) in Amyotrophic Lateral Sclerosis (ALS)
| Study # | Study design | Dosage, route of administration and duration | Study subjects (n) | Mean age (Range) | Sex |
| MCI186-19 | Randomized, placebo-controlled, double-blind study | Intravenous infusion of 60 mg over 60 minutes 6 months (6 cycles) treatment | RADICAVA (69) Placebo (68) | 60.5 (30-75) | Male (55%) Female (45%) |
- Study MCI186-19
Study MCI186-19 was conducted in Japanese patients with ALS who were living independently and met the following criteria at screening:
- 1. Functionality retained most activities of daily living (defined as scores of 2 points or better on each individual item of the ALS Functional Rating Scale – Revised [ALSFRS-R; described below])
- 2. Normal respiratory function (defined as percent-predicted forced vital capacity values of [%FVC] ≥ 80%)
- 3. Definite or Probable ALS based on El Escorial revised criteria
- 4. Disease duration of 2 years or less
The study enrolled 69 patients in the RADICAVA (injection) arm and 68 in the placebo arm. Baseline characteristics were similar between these groups, with over 90% of patients in each group being treated with riluzole.
RADICAVA (injection) was administered as an intravenous infusion of 60 mg given over a 60-minute period according to the following schedule:
- An initial treatment cycle with daily dosing for 14 days, followed by a 14-day drug-free period (Cycle 1)
- Subsequent treatment cycles with daily dosing for 10 days out of 14-day periods, followed by 14-day drug-free periods (Cycles 2-6).
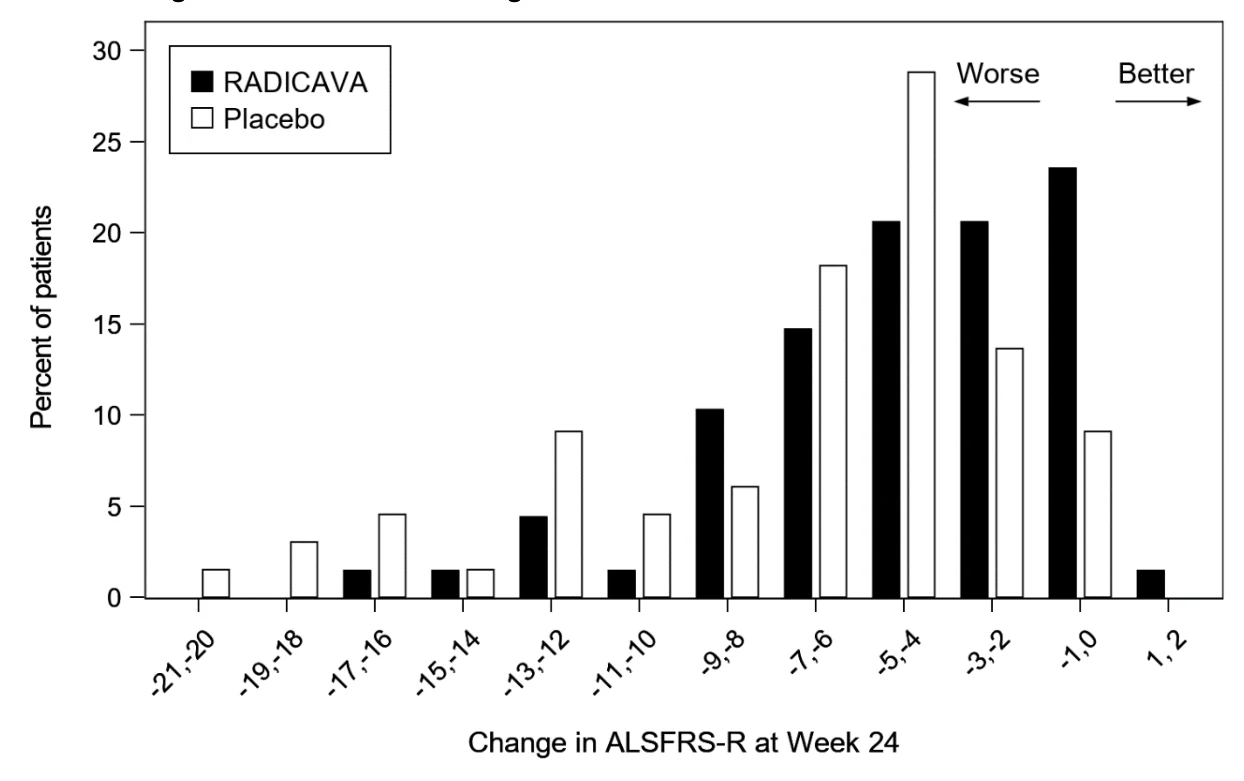
The primary efficacy endpoint was a comparison of the change between treatment arms in the ALSFRS-R total scores from baseline to Week 24. The ALSFRS-R scale consists of 12 questions that evaluate the fine motor, gross motor, bulbar, and respiratory function of patients with ALS (speech, salivation, swallowing, handwriting, cutting food, dressing/hygiene, turning in bed, walking, climbing stairs, dyspnea, orthopnea, and respiratory insufficiency). Each item is scored from 0-4, with higher scores representing greater functional ability. The decline in ALSFRS-R scores from baseline was significantly less in the RADICAVA-treated patients as compared to placebo (see Table 8). The distribution of change in ALSFRS-R scores from baseline to Week 24 by percent of patients is shown in Figure 1.
Table 8: Analysis of Change from Baseline to Week 24 in ALSFRS-R Scores
| Treatment | Change from Baseline LS Mean ± SE (95% CI) | Treatment Difference (RADICAVA – placebo [95% CI]) | p-value |
|---|---|---|---|
| RADICAVA (injection) 60mg | −5.01±0.64 | 2.49 (0.99, 3.98) | 0.0013 |
| Placebo | −7.50±0.66 | ||
Figure 1: Distribution of Change from Baseline to Week 24 in ALSFRS-R Scores
14.2 Comparative Bioavailability Studies
The efficacy of RADICAVA (oral suspension) is based on the comparative bioavailability study of RADICAVA (injection) and RADICAVA (oral suspension) in healthy subjects, demonstrating comparable exposure with both formulations (see 10 CLINICAL PHARMACOLOGY, 10.3 Pharmacokinetics).
15 MICROBIOLOGY
No microbiological information is required for this drug product.
16 NON-CLINICAL TOXICOLOGY
Note
RADICAVA (injection) was discontinued from sale on April 1, 2025.
Neurotoxicity:
Neurotoxic changes following 24-hour continuous IV infusion (60-1000 mg/kg/day) in monkeys and dogs for 14-28 days and following oral administration of edaravone (100-300 mg/kg/day) in dogs for 39 weeks were characterized by white matter vacuolation in the spinal cord and vacuolation and nerve fiber atrophy in the sciatic nerve. The microscopic findings were accompanied by gait abnormalities, loss of patellar reflex, and inability to rise. Plasma edaravone exposure (AUC) at the no observed adverse effect level (NOAEL) for neurotoxicity (oral 30 mg/kg/day) was approximately 2 times greater than the exposure in humans at the recommended human dose (RHD) of RADICAVA (oral suspension) (105 mg/day).
Genotoxicity:
Edaravone was negative in in vitro assays (bacterial reverse mutation and Chinese hamster lung chromosomal aberration) and in vivo assays (mouse micronucleus).
Carcinogenicity:
In a 26-week carcinogenicity study, in male and female CB6F1-Tg rasH2 mice, edaravone showed no indication of carcinogenic potential following repeated daily oral dosing of up to 350 mg/kg/day. In SD rats, edaravone showed no indication of carcinogenic potential following repeated daily oral dosing up to 200 mg/kg/day in males for 104 weeks and up to 250 mg/kg/day in females for 92 weeks.
Reproductive and Developmental Toxicology:
Impairment of Fertility
Intravenous administration of edaravone (0, 3, 20, or 200 mg/kg) prior to and throughout mating in male and female rats and continuing in females to gestation day 7 had no effect on fertility; however, disruption of the estrus cycle and mating behavior was observed at the highest dose tested. No effects on reproductive function were observed at the lower doses, which were approximately 2 to 3 times the RHD for RADICAVA (injection) 60 mg or RADICAVA (oral suspension) 105 mg, on a body surface area (mg/m2) basis.
Reproduction
In rats, intravenous administration of edaravone (0, 3, 30, or 300 mg/kg/day) throughout the period of organogenesis resulted in reduced fetal weight at all doses. In dams allowed to deliver naturally, offspring weight was reduced at the highest dose tested. Maternal toxicity was also observed at the highest dose tested. There were no adverse effects on reproductive function in the offspring. A no-effect dose for embryofetal developmental toxicity was not identified; the low dose was less than the RHD for RADICAVA (injection) 60 mg and RADICAVA (oral suspension) 105 mg, on a body surface area (mg/m2) basis.
In rabbits, intravenous administration of edaravone (0, 3, 20, or 100 mg/kg/day) throughout the period of organogenesis resulted in embryofetal death at the highest dose tested, which was associated with maternal toxicity. The higher no-effect dose for embryofetal developmental toxicity was approximately 4 to 6 times the RHD for RADICAVA (injection) 60 mg or RADICAVA (oral suspension) 105 mg on a body surface area (mg/m2) basis.
The effects on offspring of edaravone (0, 3, 20, or 200 mg/kg/day), administered by intravenous injection to rats from GD 17 throughout lactation, were assessed in two studies. In the first study, offspring mortality was observed at the highest dose and increased activity was observed at the mid and high doses. In the second study, there was an increase in stillbirths, offspring mortality, and delayed physical development (vaginal opening) at the highest dose tested. Reproduction function in offspring was not affected in either study. Maternal toxicity was evident in both studies at all but the lowest dose tested. The no-effect dose for developmental toxicity (3 mg/kg/day) was less than the RHD for RADICAVA (injection) 60 mg and RADICAVA (oral suspension) 105 mg on a mg/m2 basis.