


Product Monograph - Lupron Depot (Abbvie, 7.5 mg, ..., 45 mg)
RECENT MAJOR LABEL CHANGES
| 1 INDICATIONS | 2025-11 |
|---|---|
| 1 INDICATIONS, Central Precocious Puberty (CPP) | 2025-11 |
| 1 INDICATIONS, Prostate Cancer | 2025-11 |
| 1 INDICATIONS, 1.2 Geriatrics | 2025-11 |
| 3 SERIOUS WARNINGS AND PRECAUTIONS BOX | 2025-11 |
| 4 DOSAGE AND ADMINISTRATION, 4.1.2 Prostate Cancer | 2025-11 |
| 4 DOSAGE AND ADMINISTRATION, 4.2 Recommended Dose and Dosage Adjustment, Prostate Cancer | 2025-11 |
| 7 WARNINGS AND PRECAUTIONS, Hypersensitivity Reactions, Delayed Hypersensitivity Reactions | 2025-11 |
| 7 Warnings and Precautions, Skin | 2025-06 |
| 7 Warnings and Precautions, All Populations | 2024-03 |
| 7 Warnings and Precautions, Prostate Cancer population (Only) | 2024-01 |
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
RECENT MAJOR LABEL CHANGES .......................................................................................... 2
TABLE OF CONTENTS ............................................................................................................ 2
PART I: HEALTH PROFESSIONAL INFORMATION .................................................................... 5
1 INDICATIONS ............................................................................................................. 5
1.1 Pediatrics .................................................................................................................. 6
1.2 Geriatrics .................................................................................................................. 6
2 CONTRAINDICATIONS ................................................................................................ 6
3 SERIOUS WARNINGS AND PRECAUTIONS BOX ........................................................... 7
4 DOSAGE AND ADMINISTRATION ................................................................................ 7
4.1 Dosing Considerations ............................................................................................. 7
4.1.1 Central Precocious Puberty ............................................................................... 7
4.1.2 Prostate Cancer .................................................................................................. 8
4.1.3 Endometriosis .................................................................................................... 8
4.1.4 Uterine Fibroids ................................................................................................. 8
4.2 Recommended Dose and Dosage Adjustment ........................................................ 8
4.3 Reconstitution ........................................................................................................ 11
4.4 Administration ....................................................................................................... 12
4.5 Missed Dose ........................................................................................................... 12
5 OVERDOSAGE .......................................................................................................... 12
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING .............................. 13
7 WARNINGS AND PRECAUTIONS ............................................................................... 13
7.1 Special Populations ................................................................................................ 25
7.1.1 Pregnant Women ............................................................................................. 25
7.1.2 Breast-feeding .................................................................................................. 25
7.1.3 Pediatrics .......................................................................................................... 25
7.1.4 Geriatrics .......................................................................................................... 25
8 ADVERSE REACTIONS............................................................................................... 26
8.1 Adverse Reaction Overview ................................................................................... 26
8.1.1 Central Precocious Puberty ............................................................................. 26
8.1.2 Prostate Cancer ................................................................................................ 26
8.1.3 Endometriosis/Uterine Fibroids ....................................................................... 26
8.2 Clinical Trial Adverse Reactions ............................................................................. 27
8.2.1 Clinical Trial Adverse Reactions – Pediatrics.................................................... 35
8.3 Less Common Clinical Trial Adverse Reactions ...................................................... 36
8.3.1 Less Common Clinical Trial Adverse Reactions – Pediatrics ............................ 39
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data ............................................................................................................. 39
8.5 Post-Market Adverse Reactions ............................................................................. 41
9 DRUG INTERACTIONS .............................................................................................. 44
9.1 Serious Drug Interactions ...................................................................................... 44
9.2 Drug Interactions Overview ................................................................................... 44
9.3 Drug-Behavioural Interactions ............................................................................... 44
9.4 Drug-Drug Interactions .......................................................................................... 44
9.5 Drug-Food Interactions .......................................................................................... 44
9.6 Drug-Herb Interactions .......................................................................................... 45
9.7 Drug-Laboratory Test Interactions......................................................................... 45
10 CLINICAL PHARMACOLOGY ...................................................................................... 45
10.1 Mechanism of Action ....................................................................................... 45
10.2 Pharmacodynamics .......................................................................................... 45
10.2.1 Central Precocious Puberty ............................................................................. 46
10.2.2 Endometriosis .................................................................................................. 47
10.3 Pharmacokinetics ............................................................................................. 48
11 STORAGE, STABILITY AND DISPOSAL ........................................................................ 50
12 SPECIAL HANDLING INSTRUCTIONS .......................................................................... 50
PART II: SCIENTIFIC INFORMATION ..................................................................................... 51
13 PHARMACEUTICAL INFORMATION .......................................................................... 51
14 CLINICAL TRIALS ...................................................................................................... 51
14.1 Clinical Trials by Indication .............................................................................. 51
Central Precocious Puberty ............................................................................................. 51
Prostate Cancer ................................................................................................................ 52
Endometriosis .................................................................................................................. 56
Uterine Fibroids ............................................................................................................... 68
15 MICROBIOLOGY ...................................................................................................... 72
16 NON-CLINICAL TOXICOLOGY .................................................................................... 72
Patient Medication Information for Central Precocious Puberty .......................................... 76
Patient Medication Information for Prostate Cancer ........................................................... 82
Patient Medication Information for Gynecology ................................................................. 89
Instructions for Use ............................................................................................................ 95
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
LUPRON DEPOT (leuprolide acetate for extended-release injectable suspension) must be administered by a healthcare professional.
Central Precocious Puberty (CPP)
LUPRON DEPOT 3.75 mg (1-Month) and 7.5 mg (1-Month) are indicated for:
- the treatment of children with central precocious puberty (CPP).
Children should be selected using the following criteria:
- 1. Clinical diagnosis of CPP (idiopathic or neurogenic) with onset of secondary sexual characteristics earlier than 8 years in females and 9 years in males.
- 2.
Clinical diagnosis should be confirmed prior to initiation of therapy as follows:
- a) Confirmation of diagnosis by a pubertal response to a gonadotropin-releasing hormone (GnRH) stimulation test. The sensitivity and methodology of this assay must be understood.
- b) Bone age advanced one year beyond the chronological age.
- 3.
Baseline evaluation should also include:
- a) Height and weight measurements
- b) Sex steroid levels
- c) Adrenal steroid level to exclude congenital adrenal hyperplasia
- d) Beta human chorionic gonadotropin level to rule out a chorionic gonadotropin secreting tumor
- e) Pelvic/adrenal/testicular ultrasound to rule out a steroid secreting tumor
- f) Computerized tomography of the head to rule out intracranial tumor
Prostate Cancer
LUPRON DEPOT 7.5 mg (1-Month), 22.5 mg (3-Month), 30 mg (4-Month), and 45 mg (6-Month) are indicated for:
- the treatment of advanced prostate cancer.
Endometriosis
LUPRON DEPOT 3.75 mg (1-Month) and 11.25 mg (3-Month) are indicated for:
- the treatment of endometriosis, including pain relief and reduction of endometriosis lesions, for a period of six months.
LUPRON DEPOT with norethindrone acetate 5 mg daily is indicated for the initial management of endometriosis and for management of recurrence of symptoms.
LUPRON DEPOT can be used as sole therapy where it may provide symptomatic relief for women close to menopause who do not desire surgery, or as an adjunct to surgery.
Uterine Fibroids
LUPRON DEPOT 3.75 mg (1-Month) concomitantly with iron therapy is indicated for the preoperative hematologic improvement in women of reproductive age with anemia caused by uterine leiomyomata (uterine fibroids). Recommended duration of therapy with LUPRON DEPOT 3.75 mg (1-Month) is up to three months.
1.1 Pediatrics
Based on the data submitted and reviewed by Health Canada, the safety and efficacy of LUPRON DEPOT 3.75 mg (1-Month), 7.5 mg (1-Month), 11.25 mg (1-Month, as one injection each of 3.75 mg and 7.5 mg) and 15 mg (1-Month, as two injections of 7.5 mg) in pediatric patients have been established; therefore, Health Canada has authorized an indication for pediatric use (see 4.2 Recommended Dose and Dosage Adjustment).
1.2 Geriatrics
The majority of the patients studied in the clinical trials for the advanced treatment of prostate cancer with LUPRON DEPOT were 65 years and older. See 14 CLINICAL TRIALS.
LUPRON DEPOT 3.75 mg (1-Month) and 11.25 mg (3-Month) are not indicated for women over 65 years of age.
2 CONTRAINDICATIONS
- LUPRON DEPOT (leuprolide acetate for extended-release injectable suspension) is contraindicated in patients with hypersensitivity to the drug or its components or similar nonapeptides or components of the container. Isolated cases of anaphylaxis have been reported. For a complete listing, see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING.
LUPRON DEPOT is contraindicated in women who are or may become pregnant. When LUPRON DEPOT was administered on Day 6 of pregnancy at test dosages of 0.00024, 0.0024, and 0.024 mg/kg (1/1200 to 1/12 the human pediatric dose) or 1/300 to 1/3 the 3.75 mg LUPRON DEPOT human dose) to rabbits, LUPRON DEPOT produced a dose-related increase in major fetal abnormalities. Similar studies in rats failed to demonstrate an increase in fetal malformations. There was increased fetal mortality and decreased fetal weights with the two higher doses of LUPRON DEPOT in rabbits and with the highest dose (0.024 mg/kg) in rats. The effects on fetal mortality are logical consequences of the alterations in hormonal levels brought about by this drug. Therefore, the possibility exists that spontaneous abortion may occur if the drug is administered during pregnancy.
Patients treated with LUPRON DEPOT should use non-hormonal methods of contraception.
- It is not known whether leuprolide acetate is excreted in human milk; therefore, LUPRON DEPOT is contraindicated in patients who are breast-feeding.
- For patients with uterine fibroids or endometriosis LUPRON DEPOT is also contraindicated in patients with undiagnosed abnormal vaginal bleeding.
- For patients with endometriosis, refer to the norethindrone acetate 5 mg tablet Product Monograph for contraindications specific to norethindrone acetate.
3 SERIOUS WARNINGS AND PRECAUTIONS BOX
Serious Warnings and Precautions
Prostate Cancer LUPRON DEPOT (leuprolide acetate for extended-release injectable suspension) should be prescribed by a qualified physician experienced in the use of hormonal therapy in prostate cancer. LUPRON DEPOT should be administered by a healthcare professional. The following are clinically significant adverse events: |
|---|
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
LUPRON DEPOT (leuprolide acetate for extended-release injectable suspension) must be administered by a healthcare professional.
4.1.1 Central Precocious Puberty
LUPRON DEPOT 3.75 mg (1-Month) and 7.5 mg (1-Month) administered intramuscularly is designed to provide continuous sustained release of leuprolide for 1 month.
The dose of leuprolide acetate must be individualized for each child. The dose is based on a mg/kg ratio of drug to body weight. Younger children require higher doses on a mg/kg ratio.
For each dosage form, after 1 to 2 months of initiating therapy or changing doses, the child must be monitored with a GnRH stimulation test, sex steroids, and Tanner staging to confirm downregulation. Measurements of bone age for advancement should be monitored every 6 to 12 months. The dose should be titrated upward until no progression of the condition is noted either clinically and/or by laboratory parameters.
The first dose found to result in adequate downregulation can probably be maintained for the duration of therapy in most children. However, there are insufficient data to guide dosage adjustments as patients move into higher weight categories after beginning therapy at very young ages and low dosages. It is recommended that adequate downregulation be verified in such patients whose weight has increased significantly while on therapy.
Discontinuation of leuprolide acetate should be considered before age 11 for females and age 12 for males (see 4.2 Recommended Dose and Dosage Adjustment).
4.1.2 Prostate Cancer
- LUPRON DEPOT 7.5 mg (1-Month), 22.5 mg (3-Month), 30 mg (4-Month), and 45 mg (6-Month) administered intramuscularly is designed to provide continuous sustained release of leuprolide for one, three four, and six months, respectively.
- In patients treated with GnRH analogues for prostate cancer, treatment is usually continued upon development of castration-resistant prostate cancer. Reference should be made to relevant guidelines.
4.1.3 Endometriosis
LUPRON DEPOT 3.75 (1-Month) and 11.25 mg (3-Month) administered intramuscularly is designed to provide continuous sustained release of leuprolide for one and three months, respectively.
4.1.4 Uterine Fibroids
LUPRON DEPOT 3.75 mg (1-Month) administered intramuscularly is designed to provide continuous sustained release of leuprolide for one month.
4.2 Recommended Dose and Dosage Adjustment
Central Precocious Puberty
The recommended starting dose is 0.3 mg/kg/4 weeks (minimum 7.5 mg) administered as a single intramuscular injection, after reconstitution with the special diluent. See 4.4 Administration. The starting dose will be dictated by the child’s weight as indicated in Table 1.
Table 1. LUPRON DEPOT Starting Dose per Child’s Weight for Central Precocious Puberty
| Child’s Weight | Total Monthly Dose |
|---|---|
| ≤ 25 kg | 7.5 mg |
| > 25 to ≤ 37.5 kg | 11.25 mg (as one injection each of 3.75 mg and 7.5 mg) |
| > 37.5 kg | 15 mg (as two injections of 7.5 mg) |
When multiple injections are required to achieve the desired total dosage, they should be administered at the same time.
If total downregulation is not achieved, the dose should be titrated upward in increments of 3.75 mg every 4 weeks to a maximum of 15 mg per month. This dose will be considered the maintenance dose.
Due to different release characteristics, a fractional dose of the 3-month depot formulation is not equivalent to the same dose of the monthly formulation and should not be given.
Prostate Cancer
The recommended dose of LUPRON DEPOT (1-Month) is 7.5 mg administered monthly as a single intramuscular injection, after reconstitution with the special diluent. See 4.4 Administration and Patient Medication Information for Prostate Cancer.
The recommended dose of LUPRON DEPOT (3-Month) is 22.5 mg administered as a single intramuscular injection once every three months (12 weeks), after reconstitution with the special diluent. See 4.4 Administration and Patient Medication Information for Prostate Cancer. Due to different release characteristics, a fractional dose of this 3-Month depot formulation is not equivalent to the same dose of the monthly formulation and should therefore not be given.
The recommended dose of LUPRON DEPOT (4-Month) is 30 mg administered as a single intramuscular injection once every four months (16 weeks), after reconstitution with the special diluent. See 4.4 Administration and Patient Medication Information for Prostate Cancer. Due to different release characteristics, a fractional dose of this 4-Month depot formulation is not equivalent to the same dose of the monthly formulation and should therefore not be given.
The recommended dose of LUPRON DEPOT (6-Month) is 45 mg administered as a single intramuscular injection once every six months (24 weeks), after reconstitution with the special diluent. See 4.4 Administration, and Patient Medication Information for Prostate Cancer. Due to different release characteristics, a fractional dose of this 6-Month depot formulation is not equivalent to the same dose of the monthly formulation and should therefore not be given.
Endometriosis
Table 2. LUPRON DEPOT Dose for Endometriosis
LUPRON DEPOT 3.75 mg (1-Month) | LUPRON DEPOT 11.25 mg (3-Month) |
3.75 mg for 6 months (6 monthly injections) | 11.25 mg for 6 months (1 injection every 3 months) |
Due to different release characteristics, a fractional dose of the three-month depot formulation is not equivalent to the same dose of the monthly formulation and should therefore not be given.
LUPRON DEPOT 3.75 mg (1-Month)
The recommended dose of LUPRON DEPOT (1-Month) is 3.75 mg administered monthly as a single intramuscular injection, after reconstitution with the special diluent. See 4.4 Administration and Patient Medication Information for Gynecology. The recommended duration of the initial treatment with LUPRON DEPOT 3.75 mg alone or in combination with norethindrone acetate 5 mg daily is six months.
LUPRON DEPOT 11.25 mg (3-Month)
The recommended dose of LUPRON DEPOT (3-Month) is 11.25 mg administered as a single intramuscular injection once every three months, after reconstitution with the special diluent. See 4.4 Administration and Patient Medication Information for Gynecology. The recommended duration of the initial treatment with LUPRON DEPOT 11.25 mg alone or in combination with norethindrone acetate 5 mg daily is six months.
Retreatment with LUPRON DEPOT alone cannot be recommended since safety data for retreatment are not available. If the symptoms of endometriosis recur after the course of initial therapy, and further treatment with either LUPRON DEPOT 3.75 mg (1-Month) or LUPRON DEPOT 11.25 mg (3-Month) is contemplated, combination with norethindrone acetate 5 mg daily may be considered for an additional six-month course of treatment. Retreatment beyond this additional six-month course cannot be recommended. It is recommended that bone density be assessed before retreatment begins to ensure that values are within normal limits. If norethindrone acetate is contraindicated for the individual patient, then retreatment is not recommended.
An assessment of cardiovascular risk and management of risk factors such as cigarette smoking is recommended before beginning treatment with LUPRON DEPOT and LUPRON DEPOT with norethindrone acetate.
Uterine Fibroids
LUPRON DEPOT 3.75 mg (1-Month)
The recommended dose of LUPRON DEPOT (1-Month) is 3.75 mg administered monthly as a single intramuscular injection with concomitant daily oral iron therapy for the preoperative hematologic improvement of patients with leiomyomas and iron-deficiency anemia caused by excessive uterine bleeding. The recommended duration of the treatment with LUPRON DEPOT 3.75 mg is up to three months.
Daily oral iron supplementation should be taken. Instruct the patient on the daily dose.
The iron supplement can be chosen in accordance with what is locally available. Refer to the Iron Natural and Non-prescription Health Products Directorate (NNHPD) monograph and/or product packaging labels for information on iron dosage and administration.
4.3 Reconstitution
The lyophilized microspheres contained in the front chamber of the pre-filled dual-chamber syringe are to be reconstituted prior to intramuscular administration, in accord with the following directions:
- 1. The LUPRON DEPOT powder should be visually inspected and the syringe should NOT BE USED if clumping or caking is evident. A thin layer of powder on the wall of the syringe is considered normal. The diluent should appear clear.
- 2. To prepare for injection, screw the white plunger into the end stopper until the stopper begins to turn.
- 3. Remember to tighten the needle by twisting the needle cap clockwise. Do not overtighten.
- 4. Holding the syringe upright, release the diluent by SLOWLY PUSHING (6 to 8 seconds) the plunger until the first stopper is at the blue line in the middle of the barrel.
- 5. Keep the syringe upright. Gently shake the syringe to thoroughly mix the microspheres (powder) to form a uniform suspension. The suspension will appear milky.
- 6. If the microspheres adhere to the stopper or caking/clumping is present, tap the syringe against your finger to disperse. DO NOT USE if any of the powder has not gone into suspension.
- 7. Keep the syringe upright. With the opposite hand, remove the needle cap without twisting and advance the plunger to expel the air from the syringe.
- 8. At the time of reconstitution, inject the entire contents of the syringe intramuscularly by inserting the needle at a 90 degree angle into the gluteal area, anterior thigh, or deltoid; injection sites should be alternated.
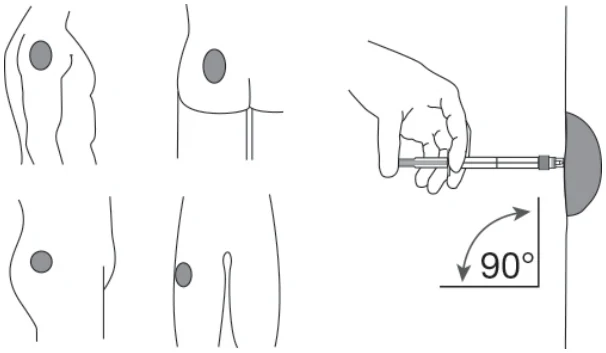
The suspension settles very quickly following reconstitution; therefore, LUPRON DEPOT should be mixed and used immediately.
Note: Aspirated blood would be visible just below the luer lock connection if a blood vessel is accidentally penetrated. If present, blood can be seen through the transparent LuproLoc® safety device. If blood is present remove the needle immediately. Do not inject the medication.
- 9. After injection, withdraw the needle. Immediately activate the LuproLoc safety device by pushing the arrow forward with the thumb or finger until the device is fully extended and a CLICK is heard or felt.
Please also see booklet of Instructions for Use.
Although the suspension has been shown to be stable for 24 hours following reconstitution, since the product does not contain a preservative, the suspension should be discarded if not used immediately.
4.4 Administration
As with all parenteral products, inspect container's solution for discoloration and particulate matter before each use.
LUPRON DEPOT needs to be reconstituted prior to administration (see 4.3 Reconstitution).
As with other drugs administered by injection, the injection site should be varied periodically.
4.5 Missed Dose
Central Precocious Puberty
Regular injections are important. Adherence to four-week drug administration schedules must be accepted if therapy is to be successful. If a shot is missed or is administered a week late, the child’s pubertal development could begin again. See 7 WARNINGS AND PRECAUTIONS.
Prostate Cancer
Maintaining testosterone suppression is important in treating the symptoms of hormone-dependent prostate cancer. Missing an appointment by a few days should not disrupt the benefits of treatment, but keeping a consistent schedule of LUPRON DEPOT injection is an important part of treatment.
Endometriosis/Uterine Fibroids
Missing an appointment by a few days should not disrupt the benefits of treatment, but keeping a consistent schedule of LUPRON DEPOT injections is an important part of treatment.
5 OVERDOSAGE
| For the most recent information in the management of a suspected drug overdose, contact your regional poison control centre or Health Canada’s toll-free number, 1-844 POISON-X (1-844-764-7669). |
|---|
There is no clinical experience with the effects of an acute overdose. Because the acute animal toxicity of the drug is low, adverse effects are not expected. No difference in adverse reactions was observed in patients who received either 1 or 10 mg/day leuprolide acetate for up to three years or 20 mg/day for up to two years.
In cases of overdosage, the patients should be monitored closely and management should be symptomatic and supportive.
In rats, subcutaneous administration of leuprolide acetate as a single dose 333 times the recommended human pediatric dose, expressed on a per body weight basis, resulted in dyspnea, decreased activity, and excessive scratching.
In rats, subcutaneous administration of approximately 133 times the recommended human dose, expressed on a per body weight basis, resulted in dyspnea, decreased activity, and local irritation at the injection site. There is no evidence at present that there is a clinical counterpart of this phenomenon.
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
LUPRON DEPOT is available in six strengths: 3.75 mg (1-Month), 7.5 mg (1-Month), 11.25 mg (3-Month), 22.5 mg (3-Month), 30 mg (4-Month), and 45 mg (6-Month).
LUPRON DEPOT is supplied in single-dose kits containing one pre-filled dual-chamber USP Type I glass syringe with 23-gauge needle. The white sterile powder for suspension is found in the front chamber and the colorless sterile diluent is found in the rear chamber.
Table 3. Dosage Forms, Strengths, Composition and Packaging for Lupron Depot Formulations
| Route of Administration | Dosage Form/ Strength/Composition | Non-Medicinal Ingredients |
|---|---|---|
| Intramuscular | Powder 3.75 mg (1-Month), 7.5 mg (1-Month), 11.25 mg (3-Month), 22.5 mg (3-Month), 30 mg (4-Month), and 45 mg (6-Month) leuprolide acetate per syringe | carboxymethylcellulose sodium, DL-lactic and glycolic acids copolymer (only 3.75 mg and 7.5 mg strengths), D-mannitol, gelatin (only 3.75 mg and 7.5 mg strengths), glacial acetic acid, polylactic acid (only 11.25 mg, 22.5 mg, 30 mg and 45 mg strengths), polysorbate 80, stearic acid (only 45 mg strength), water for injection |
During the manufacturing process of LUPRON DEPOT, acetic acid is lost, leaving the leuprolide peptide.
7 WARNINGS AND PRECAUTIONS
ALL POPULATIONS
The following Warnings and Precautions are applicable to all indicated, approved treatment populations in Canada.
General
During the early phase of therapy, sex steroids temporarily rise above baseline because of the physiologic effect of the drug. Therefore, an increase in clinical signs and symptoms may be observed during the initial days of therapy, but these will dissipate with continued therapy at adequate doses.
Carcinogenesis and Mutagenesis
Two-year carcinogenicity studies were conducted in rats and mice. In rats, a dose-related increase of benign pituitary hyperplasia and benign adenomas was noted at 24 months when the drug was administered subcutaneously at high daily doses (0.6 to 4 mg/kg/day). Also in rats, there was a significant but not a dose-related increase of pancreatic islet-cell adenomas in females and of testicular interstitial cell adenomas in males (highest incidence in the low-dose group). In mice, no pituitary abnormalities were observed at a dose as high as 60 mg/kg/day for two years.
Patients have been treated with leuprolide acetate for up to three years with doses as high as 10 mg/day and for two years with doses as high as 20 mg/day without demonstrable pituitary abnormalities.
Mutagenicity studies have been performed with leuprolide acetate using bacterial and mammalian systems. These studies provided no evidence of a mutagenic potential. See 16 NON-CLINICAL TOXICOLOGY.
Dependence/Tolerance
No drug-dependence has been reported with the use of leuprolide acetate.
Hepatic/Biliary/Pancreatic
The pharmacokinetics of the drug in patients with hepatic, biliary or pancreatic impairment have not been determined.
Hypersensitivity Reactions
Acute Hypersensitivity Reactions
Acute hypersensitivity reactions, including anaphylaxis, have been reported with LUPRON DEPOT use. LUPRON DEPOT is contraindicated in patients with a history of hypersensitivity to gonadotropin-releasing hormone (GnRH) or GnRH agonist analogs.
In clinical trials of LUPRON DEPOT 3.75 mg and 11.25 mg, adverse events of asthma were reported in patients with pre-existing histories of asthma, sinusitis, and environmental or drug allergies. Symptoms consistent with an anaphylactoid or asthmatic process have been reported postmarketing.
Delayed Hypersensitivity Reactions
Delayed hypersensitivity reactions including the severe cutaneous adverse reactions (SCAR) of Stevens-Johnson Syndrome (SJS) and Toxic Epidermal Necrolysis (TEN) have been very rarely reported postmarketing in association with leuprolide acetate therapy (see 8.5 Post-Market Adverse Reactions). Discontinue future leuprolide acetate therapy at first signs or symptoms of a delayed hypersensitivity reaction and treat patients according to current clinical practice.
Neurologic
Convulsions
Postmarketing reports of convulsions have been observed in patients receiving GnRH agonists, including leuprolide acetate. These included patients in the female and pediatric populations, patients with a history of seizures, epilepsy, cerebrovascular disorders, central nervous system anomalies or tumors, and in patients on concomitant medications that have been associated with convulsions such as bupropion and selective serotonin reuptake inhibitors (SSRIs). Convulsions have also been reported in patients in the absence of any of the conditions mentioned above.
Renal
The pharmacokinetics of the drug in patients with renal impairment have not been determined.
Skin
Cases of skin necrosis at the injection site have been reported. Discontinue further injections at the affected site.
CENTRAL PRECOCIOUS PUBERTY POPULATION (Only)
Noncompliance with the drug regimen or inadequate dosing may result in inadequate control of the pubertal process. The consequences of poor control include the return of pubertal signs such as menses, breast development, and testicular growth. The long-term consequences of inadequate control of gonadal steroid secretion are unknown but may include a further compromise of adult stature.
Endocrine and Metabolism
Changes in Bone Mineral Density
Bone mineral density (BMD) changes can occur during the hypoandrogenic state caused by long-term use of LUPRON DEPOT. In patients with significant risk factors for decreased bone mineral content and/or bone mass such as family history of osteoporosis, chronic use of corticosteroids or anticonvulsants or chronic abuse of alcohol or tobacco, leuprolide acetate may pose additional risk. In these patients, risk versus benefit must be weighed carefully before initiation of leuprolide acetate therapy.
BMD may decrease with GnRH agonist, including LUPRON DEPOT, in children with central precocious puberty. However, after cessation of treatment subsequent bone mass accrual is preserved and peak bone mass in late adolescence does not seem to be affected by treatment.
Hypogonadism
Long-term administration of leuprolide acetate will cause suppression of pituitary gonadotropins and gonadal hormone production with clinical symptoms of hypogonadism. These changes have been observed to reverse on discontinuation of therapy. However, whether the clinical symptoms of induced hypogonadism will reverse in all patients has not yet been established.
Monitoring and Laboratory Tests
Response to LUPRON DEPOT should be monitored 1 to 2 months after the start of therapy with a GnRH stimulation test and sex steroid levels. Measurement of bone age for advancement should be done every 6 to 12 months.
Sex steroids may increase or rise above prepubertal levels if the dose is inadequate. See 7 WARNINGS AND PRECAUTIONS. Once a therapeutic dose has been established, gonadotropin and sex steroid levels will decline to prepubertal levels.
Neurologic
Postmarketing reports of convulsions have been observed in patients receiving GnRH agonists, including LUPRON DEPOT. These included patients in the female and pediatric populations, patients with a history of seizures, epilepsy, cerebrovascular disorders, central nervous system anomalies or tumors, and in patients on concomitant medications that have been associated with convulsions such as bupropion and SSRIs. Convulsions have also been reported in patients in the absence of any of the conditions mentioned above.
Pseudotumor cerebri/idiopathic intracranial hypertension
Pseudotumor cerebri (PTC)/idiopathic intracranial hypertension has been reported in pediatric patients receiving leuprolide acetate. Monitor patients for signs and symptoms of PTC, including headache, papilledema, blurred vision, diplopia, loss of vision, pain behind the eye or pain with eye movement, tinnitus, dizziness, and nausea. Refer the patient to an ophthalmologist to confirm the presence of papilledema. If PTC is confirmed, treat the patient in accordance to the established treatment guidelines and permanently discontinue use of leuprolide acetate.
Psychiatric
Psychiatric events have been reported in patients taking GnRH agonists including LUPRON DEPOT. Postmarketing reports with this class of drugs include symptoms of emotional lability, such as crying, irritability, impatience, anger and aggression. Monitor for development or worsening of psychiatric symptoms during treatment with LUPRON DEPOT (see 8.5 Post-Market Adverse Reactions).
PROSTATE CANCER POPULATION (Only)
Please see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX.
LUPRON DEPOT, like other gonadotropin-releasing hormone (LHRH) agonists, causes a transient increase in serum concentration of testosterone during the first weeks of treatment. Patients may experience worsening of symptoms or onset of new symptoms, including bone pain, neuropathy, hematuria, or ureteral or bladder outlet obstruction. Cases of spinal cord compression, which may contribute to paralysis with or without fatal complications, have been reported with LHRH agonists. If spinal cord compression or renal impairment due to ureteral obstruction develops, standard treatment of these complications should be instituted.
Patients with metastatic vertebral lesions and/or with urinary tract obstruction should begin leuprolide acetate therapy under close supervision.
Cardiovascular
Increased risk of developing myocardial infarction, sudden cardiac death and stroke has been reported in association with use of gonadotropin-releasing hormone (GnRH) agonists in men. The risk should be evaluated carefully along with cardiovascular risk factors when determining a treatment for patients with prostate cancer. Patients receiving GnRH agonists should be monitored for symptoms and signs suggestive of development of cardiovascular disease and be managed according to current clinical practice. See 7 WARNINGS AND PRECAUTIONS.
Effect on QT/QTc Interval
Androgen deprivation therapy has the potential to prolong QT/QTc interval on an ECG. Physicians should consider whether the benefits of androgen deprivation therapy outweigh the potential risk in patients with congenital long QT syndrome, electrolyte abnormalities, or congestive heart failure and in patients taking Class IA (e.g., quinidine, procainamide), Class III (e.g., amiodarone, sotalol, dofetilide, ibutilide), or Class IC (e.g., flecainide, propafenone) antiarrhythmic medications.
In a randomized, active-controlled trial to compare leuprolide acetate 7.5 mg with an LHRH antagonist in patients with prostate cancer, periodic electrocardiograms were collected and evaluated. In the leuprolide cohort, a mean QTcF increase of 17 msec from baseline was reported. The percentage of subjects who experienced maximum QTcF changes of > 30 to < 60 msec and ≥ 60 msec was 41 and 4%, respectively.
Endocrine and Metabolism
Metabolic changes
In men treated with androgen deprivation therapy (ADT), including GnRH agonists, an increased risk of developing metabolic changes such as hyperglycemia, hyperlipidemia, non-alcoholic fatty liver disease (NAFLD), and diabetes has been reported. See 8 ADVERSE REACTIONS. Hyperglycemia may represent development of diabetes mellitus or worsening of glycemic control in patients with diabetes. Patients at increased risk should be monitored for the signs and symptoms of metabolic syndrome including lipids, blood glucose and/or glycosylated hemoglobin (HbA1c) and liver function.
Changes in Bone Density
Decreased bone mineral density can be anticipated with long-term use of an LHRH agonist. Androgen deprivation therapy is associated with increased risks of osteoporosis and skeletal bone fractures. The risk of skeletal fracture increases with the duration of androgen deprivation therapy. Assessment of osteoporosis risk and management according to clinical practice and guidelines should be considered.
In patients with significant risk factors for decreased bone mineral content and/or bone mass such as chronic alcohol and/or tobacco use, presumed or strong family history of osteoporosis or chronic use of drugs that can reduce bone mass such as anticonvulsants or corticosteroids, leuprolide acetate may pose an additional risk. In these patients, risk versus benefit must be weighed carefully before therapy with LUPRON DEPOT is instituted.
Hypogonadism
Long-term administration of leuprolide acetate will cause suppression of pituitary gonadotropins and gonadal hormone production with clinical symptoms of hypogonadism. These changes have been observed to reverse on discontinuation of therapy. However, whether the clinical symptoms of induced hypogonadism will reverse in all patients has not yet been established.
Reduction in Glucose Tolerance
A reduction in glucose tolerance and an increased risk in developing diabetes have been reported in men treated with androgen deprivation therapy. Patients treated with LUPRON DEPOT should undergo periodic monitoring of blood glucose. Diabetic patients may require more frequent monitoring when receiving LUPRON DEPOT.
Hematologic
Anemia is a known physiologic consequence of testosterone suppression. Assessment of anemia risk and management according to local clinical practice and guidelines should be considered.
Hepatic/Biliary/Pancreatic
In the postmarketing setting, cases of serious liver injury (including reports of fatal cases) have been described in which a causal association with leuprolide acetate therapy is suspected. Elevations in alanine aminotransferase (ALT) in patients receiving LUPRON DEPOT in clinical trials have been reported. Monitoring of liver function in patients treated with LUPRON DEPOT should be considered.
Monitoring and Laboratory Tests
Response to LUPRON DEPOT should be monitored by measuring serum levels of testosterone, as well as prostate-specific antigen and prostatic acid phosphatase. In the majority of patients, testosterone levels increased above baseline during the first week, declining thereafter to baseline levels or below by the end of the second week. In the LUPRON DEPOT 30 mg (4-Month) study, castrate levels were reached within two to four weeks, and once achieved, were maintained in most patients (45/49) for as long as the patients received their injections. See 14 CLINICAL TRIALS.
The effects of leuprolide acetate on bone lesions may be monitored by bone scans, while its effects on prostatic lesions may be monitored by ultrasonography and/or computed tomography (CT) scan in addition to digital rectal examination.
Intravenous pyelogram, ultrasonography, or CT scan may also be utilized to diagnose or assess the status of obstructive uropathy.
Periodic monitoring of serum testosterone and Prostatic Specific Antigen (PSA) levels is recommended, especially if the anticipated clinical or biochemical response to treatment has not been achieved. It should be noted that results of testosterone determinations are dependent on assay methodology. It is advisable to be aware of the type and precision of the assay methodology to make appropriate clinical and therapeutic decisions.
Baseline risk factors of cardiovascular diseases should be assessed. Patients receiving LUPRON DEPOT should be monitored periodically for risk factors, signs and symptoms of cardiovascular diseases. In addition, baseline ECG recording and serum potassium, calcium, and magnesium levels are recommended. Monitoring of ECG and serum electrolyte levels during treatment should also be considered for those at risk for electrolyte abnormality and QTc prolongation.
Blood glucose levels and/or glycosylated hemoglobin (HbA1c) should be checked periodically in patients treated with LUPRON DEPOT and more frequently in diabetic patients. See 7 WARNINGS AND PRECAUTIONS.
Monitoring of liver function in patients treated with LUPRON DEPOT should be considered.
Psychiatric
Like other drugs in this class, mood swings, including depression, have been reported with LUPRON DEPOT (see 8.2 Clinical Trial Adverse Reactions). There have been reports of suicidal ideations and attempt (see 8.5 Post-Market Adverse Drug Reactions). Patients should be counseled on the possibility of development or worsening of depression during treatment with LUPRON DEPOT.
ENDOMETRIOSIS/UTERINE FIBROIDS POPULATION (Only)
Isolated cases of short-term worsening of signs and symptoms have been reported during initiation of leuprolide therapy. They are sometimes, but not necessarily, associated with a stimulation of the pituitary gland and an initial increase in the levels of circulating gonadal hormones.
Worsening of the clinical condition may occasionally require discontinuation of therapy and/or surgical intervention.
Before initiating treatment with LUPRON DEPOT, pregnancy must be ruled out. See 7.1.1 Pregnant Women.
Patients on leuprolide therapy should be assessed on a regular basis by their attending physician.
For patients with endometriosis, refer to the norethindrone acetate 5 mg tablet Product Monograph for information on the WARNINGS and PRECAUTIONS related to norethindrone acetate.
Endocrine and Metabolism
Changes in Bone Density
Endometriosis
Since bone loss can be anticipated as part of natural menopause, it may also be expected to occur during the medically induced hypoestrogenic state caused by the long-term use of LUPRON DEPOT. For a period of up to six months, this bone loss should not be important.
Clinical studies indicate that concurrent hormonal replacement therapy (add-back therapy) with norethindrone acetate 5 mg daily and calcium supplementation is effective in reducing the loss of bone mineral density which occurs with LUPRON DEPOT. See 14.1 Clinical Trials by Indication, Endometriosis, LUPRON DEPOT 3.75 mg (1-Month), Clinical Evaluation in Studies M92-878 and M97-777, Bone Mineral Density.
If the symptoms of endometriosis recur after a course of therapy, and further treatment with LUPRON DEPOT is contemplated, it is recommended that bone density be assessed before retreatment begins to ensure that values are within normal limits. Retreatment with a six-month course of LUPRON DEPOT and norethindrone acetate 5 mg daily may be considered. Retreatment with LUPRON DEPOT alone is not recommended.
In patients with significant risk factors for decreased bone mineral content and/or bone mass such as family history of osteoporosis, chronic use of corticosteroids or anticonvulsants or chronic abuse of alcohol or tobacco, leuprolide may pose additional risk. In these patients, risk versus benefit must be weighed carefully before initiation of leuprolide therapy, and concomitant treatment with norethindrone acetate 5 mg daily should be considered. Retreatment with gonadotropin-releasing hormone analogs, including LUPRON DEPOT, is not advisable in patients with major risk factors for loss in bone mineral content.
A controlled study in endometriosis patients showed that vertebral bone density, as measured by dual energy X-ray absorptiometry (DEXA), decreased by an average of 4.1% at six months compared with the pretreatment value.
For those patients who were tested at 6 or 12 months after discontinuation of therapy, the mean bone density returned to -2.6% of pretreatment.
Earlier studies in endometriosis patients, utilizing quantitative computed tomography (QCT), demonstrated that in the few patients who were retested at 6 and 12 months, partial to complete recovery of bone density was recorded in the posttreatment period. Use of LUPRON DEPOT for longer than six months or in the presence of other known risk factors for decreased bone mineral content may cause additional bone loss.
Two clinical studies demonstrated that concurrent hormonal therapy with norethindrone acetate 5 mg daily and calcium supplementation significantly reduced the loss of bone mineral density that occurs with LUPRON DEPOT treatment, without compromising the efficacy of LUPRON DEPOT in relieving symptoms of endometriosis. The bone mineral density data from these two studies, evaluated after six months and one year of treatment at the lumbar spine, are presented in
Table 4.
Table 4. Mean Percent Change from Baseline in Bone Mineral Density of Lumbar Spine in the Add-Back Studies
| LUPRON DEPOT 3.75 mg | LUPRON DEPOT 3.75 mg + norethindrone acetate 5 mg daily | ||||||||||||
Controlled Study (Study M92-878) | Controlled Study (Study M92-878) | Open Label Study (Study M97-777) | |||||||||||
| N | Change | N | Change | N | Change | ||||||||
| Week 241 | 41 | -3.2% | 42 | -0.3% | 115 | -0.2% | |||||||
| Week 522 | 29 | -6.3% | 32 | -1.0% | 84 | -1.1% | |||||||
| |||||||||||||
The safety of retreatment as well as treatment beyond six months with LUPRON DEPOT has not been established.
Adverse events occurring in clinical studies with LUPRON DEPOT that are associated with hypoestrogenism include hot flashes, headaches, emotional lability, decreased libido, acne, myalgia, reduction in breast size, and vaginal dryness. Estrogen levels returned to normal after treatment was discontinued.
Uterine Fibroids
It can be anticipated that the administration of LUPRON DEPOT 3.75 mg (1-Month) in women causes some reduction of BMD. However, the short treatment duration (up to three months) in women with uterine fibroids who plan to undergo uterine fibroid surgery and the fact that BMD will rise again post therapy when sex steroids return to normal levels will make an impact on clinical outcome, such as fractures, unlikely.
Monitoring and Laboratory Tests
Changes in Laboratory Values During Treatment
Plasma Enzymes
Endometriosis
During clinical trials with LUPRON DEPOT alone, regular laboratory monitoring revealed that serum glutamic oxaloacetic transaminase (SGOT) levels were more than twice the upper limit of normal in only one patient. There was no other clinical or laboratory evidence of abnormal liver function.
In two other clinical trials, 6 of 191 patients receiving LUPRON DEPOT 3.75 mg (1-Month) plus norethindrone acetate 5 mg daily for up to 12 months developed an elevated (at least twice the upper limit of normal) serum glutamic pyruvic transaminase (SGPT) or gamma-glutamyltransferase (GGT). Five of the six increases were observed beyond six months of treatment. None were associated with elevated bilirubin concentration.
Uterine Fibroids
In clinical trials with LUPRON DEPOT 3.75 mg (1-Month), five (3%) patients had a post-treatment transaminase value that was at least twice the baseline value and above the upper limit of the normal range. None of the laboratory increases were associated with clinical symptoms.
Hematology
Endometriosis
Slight decreases in hemoglobin and hematocrit values to below normal were noted with receipt of LUPRON DEPOT 11.25 mg (3-Month), but none were considered clinically significant.
Uterine Fibroids
In LUPRON DEPOT 3.75 mg (1-Month) treated patients, although there were statistically significant mean decreases in platelet counts from baseline to final visit, the last mean platelet counts were within the normal range. Decreases in total WBC count and neutrophils were observed, but were not clinically significant.
Lipids
Endometriosis
At enrolment, 4% of LUPRON DEPOT 3.75 mg (1-Month) patients and 1% of the danazol patients had total cholesterol values above the normal range. These patients also had cholesterol values above the normal range at the end of treatment. Of those patients whose pretreatment cholesterol values were in the normal range, 7% of the LUPRON DEPOT patients and 9% of the danazol patients had posttreatment values above the normal range.
The mean (± SEM) pretreatment values for total cholesterol from all patients were 4.63 (0.08) mmol/L in the LUPRON DEPOT 3.75 mg (1-Month) group and 4.54 (0.08) mmol/L in the danazol group. At the end of treatment, the mean values for total cholesterol from all patients were 5.01 mmol/L in the LUPRON DEPOT group and 5.03 mmol/L in the danazol group. These increases from the pretreatment values were statistically significant (p < 0.03) in both groups.
Triglycerides were increased above the upper limit of normal in 12% of the patients who received LUPRON DEPOT 3.75 mg (1-Month) and in 6% of the patients who received danazol.
At the end of treatment, high-density lipoprotein (HDL) cholesterol fractions decreased below the lower limit of the normal range in 2% of the LUPRON DEPOT 3.75 mg (1-Month) patients compared with 54% of those receiving danazol. Low-density lipoprotein (LDL) cholesterol fractions increased above the upper limit of the normal range in 6% of the patients receiving LUPRON DEPOT 3.75 mg (1-Month) compared with 23% of those receiving danazol. There was no increase in the LDL/HDL ratio in patients receiving LUPRON DEPOT 3.75 mg (1-Month), but there was approximately a two-fold increase in the LDL/HDL ratio in patients receiving danazol. The clinical implication of these changes in this patient population for a restricted therapeutic period is unclear.
Isolated elevations of SGOT were observed in leuprolide acetate- and danazol-treated patients.
In subjects receiving LUPRON DEPOT 11.25 mg (3-Month), triglycerides were slightly elevated (range 142 to 210 mg/dL) in 32% of the subjects who had demonstrated normal baseline values.
In two other clinical trials, LUPRON DEPOT 3.75 mg (1-Month) plus norethindrone acetate 5 mg daily were evaluated for 12 months of treatment. LUPRON DEPOT 3.75 mg (1-Month) was used as a control group in one study. Percent changes from baseline for serum lipids and percentages of patients with serum lipid values outside of the normal range in the two studies are summarized in Table 5 and Table 6, below.
Table 5. Serum Lipids: Mean Percent Changes from Baseline Values at Treatment Week 24 in the Add-Back Studies
Controlled Study (Study M92-878) | Open Label Study (Study M97-777) | |||||||||||||||||||
LUPRON DEPOT 3.75 mg N=39 | LUPRON DEPOT 3.75 mg + norethindrone acetate 5 mg N=41 | LUPRON DEPOT 3.75 mg + norethindrone acetate 5 mg N=117 | ||||||||||||||||||
| Baseline Value (mg/dL) | Week 24 % Change | Baseline Value (mg/dL) | Week 24 % Change | Baseline Value (mg/dL) | Week 24 % Change | |||||||||||||||
| Total Cholesterol | 170.5 | 9.2% | 179.3 | 0.2% | 181.2 | 2.8% | ||||||||||||||
| HDL Cholesterol | 52.4 | 7.4% | 51.8 | -18.8% | 51.0 | -14.6% | ||||||||||||||
| LDL Cholesterol | 96.6 | 10.9% | 101.5 | 14.1% | 109.1 | 13.1% | ||||||||||||||
| LDL/HDL Ratio1 | 2.0 | 5.0% | 2.1 | 43.4% | 2.3 | 39.4% | ||||||||||||||
| Triglycerides | 107.8 | 17.5% | 130.2 | 9.5% | 105.4 | 13.8% | ||||||||||||||
| ||||||||||||||||||||
Changes from baseline tended to be greater at Week 52. After treatment, mean serum lipid levels from patients with follow up data returned to pretreatment values.
Table 6. Percentage of Patients with Serum Lipid Values Outside of the Normal Range in the Add-Back Studies
Controlled Study (Study M92-878) | Open Label Study (Study M97-777) | ||||||||||||||
LUPRON DEPOT 3.75 mg N=39 | LUPRON DEPOT 3.75 mg + norethindrone acetate 5 mg N=41 | LUPRON DEPOT 3.75 mg + norethindrone acetate 5 mg N=117 | |||||||||||||
| Week 0 | Week 241 | Week 0 | Week 241 | Week 0 | Week 241 | ||||||||||
| Total Cholesterol (>240 mg/dL) | 15% | 23% | 15% | 20% | 6% | 7% | |||||||||
| HDL Cholesterol (<40 mg/dL) | 15% | 10% | 15% | 44% | 15% | 41% | |||||||||
LDL Cholesterol (>160 mg/dL) | 0% | 8% | 5% | 7% | 9% | 11% | |||||||||
| LDL/HDL Ratio (>4.0) | 0% | 3% | 2% | 15% | 7% | 21% | |||||||||
| Triglycerides (>200 mg/dL) | 13% | 13% | 12% | 10% | 5% | 9% | |||||||||
| |||||||||||||||
Low HDL-cholesterol (<40 mg/dL) and elevated LDL-cholesterol (>160 mg/dL) are recognized risk factors for cardiovascular disease. The long-term significance of the observed treatment-related changes in serum lipids in women with endometriosis is unknown. Therefore, assessment of cardiovascular risk factors should be considered prior to initiation of concurrent treatment with LUPRON DEPOT and norethindrone acetate.
Uterine Fibroids
In patients receiving LUPRON DEPOT 3.75 mg (1-Month), mean changes in cholesterol (+11 mg/dL to +29 mg/dL), LDL cholesterol (+8 mg/dL to +22 mg/dL), HDL cholesterol (0 to +6 mg/dL), and the LDL/HDL ratio (-0.1 to +0.5) were observed across studies. In the one study in which triglycerides were determined, the mean increase from baseline was 32 mg/dL.
Other Changes
Endometriosis
In comparative studies, the following changes were seen in approximately 5 to 8% of patients. LUPRON DEPOT was associated with elevations of lactate dehydrogenase (LDH) and phosphorus, and decreases in white blood cell (WBC) counts, and danazol therapy was associated with increases in hematocrit, platelet count, and LDH.
Uterine Fibroids
Slight to moderate mean increases were noted for glucose, uric acid, BUN, creatinine, total protein, albumin, bilirubin, alkaline phosphatase, LDH, calcium, and phosphorus. None of these increases were clinically significant.
7.1 Special Populations
7.1.1 Pregnant Women
Safe use of the drug in pregnancy has not been established; therefore, a nonhormonal method of contraception should be used during treatment. Patients should be advised that if they miss or postpone a dose of LUPRON DEPOT, ovulation may occur with the potential for conception. If a patient becomes pregnant during treatment, she should discontinue treatment and consult her physician.
Since menstruation should stop with effective doses of LUPRON DEPOT, the patient should notify her physician if regular menstruation persists. Patients missing successive doses of LUPRON DEPOT may experience breakthrough bleeding.
Before initiating treatment with LUPRON DEPOT, pregnancy must be ruled out.
7.1.2 Breast-feeding
It is not known whether leuprolide is excreted in human milk; therefore, LUPRON DEPOT is contraindicated in patients who are breast-feeding.
7.1.3 Pediatrics
Pediatrics (< 18 years of age): Safety and effectiveness of LUPRON DEPOT 22.5 mg (3-Month), 11.25 mg (3-Month) and 30 mg (4 Month) have not been established in pediatric patients. See 7 WARNINGS AND PRECAUTIONS for the safety and effectiveness of LUPRON DEPOT in children with central precocious puberty.
Experience with LUPRON DEPOT 3.75 mg (1-Month) for treatment of endometriosis or uterine fibroids has been limited to women 18 years of age and older.
7.1.4 Geriatrics
Geriatrics (> 65 years of age): In prostatic cancer clinical trials for LUPRON DEPOT, the majority of subjects studied were at least 65 years of age. The labelling therefore reflects the pharmacokinetics, efficacy and safety of LUPRON DEPOT in this population.
LUPRON DEPOT 3.75 mg (1-Month) and 11.25 mg (3-Month) have not been studied in women over 65 years of age and are not indicated in this population.
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
8.1.1 Central Precocious Puberty
Potential exacerbation of signs and symptoms during the first few weeks of treatment is a concern in patients with rapidly advancing central precocious puberty. See 7 WARNINGS AND PRECAUTIONS.
8.1.2 Prostate Cancer
In clinical studies, an initial rise in serum testosterone levels usually occurred in non-orchiectomized patients during the first week of treatment.
This occasionally was associated with a worsening of signs and symptoms, usually an increase in bone pain. See 7 WARNINGS AND PRECAUTIONS. In some cases, temporary renal impairment was accompanied by mental confusion, joint pain, nausea and vomiting. In each case, leuprolide acetate administration was continued, and the symptom(s) subsided in one to two weeks.
The potential for exacerbation of signs and symptoms during the first few weeks of treatment is a concern in patients with vertebral metastases and/or in patients with severe obstructive uropathy which, if aggravated, may lead to neurological problems such as temporary weakness and/or paresthesia of the lower limbs or worsening of urinary symptoms, such as hematuria and urinary tract obstruction.
Interstitial lung disease has been reported with a variable time to onset in the postmarketing reports of patients treated with leuprolide acetate. Although a direct causal relationship between leuprolide acetate therapy and interstitial lung disease has not been established on the basis of the prostate cancer treatment, discontinuation of leuprolide acetate to allow for a potential resolution of the interstitial lung disease should be considered.
8.1.3 Endometriosis/Uterine Fibroids
Estradiol levels may increase during the first weeks following the initial injection, but then decline to basal levels. This transient increase in estradiol can be associated with a temporary worsening of signs and symptoms. See 7 WARNINGS AND PRECAUTIONS.
For patients with endometriosis, refer to the norethindrone acetate 5 mg tablet Product Monograph for information on the adverse reactions related to norethindrone acetate.
Interstitial lung disease has been reported with a variable time to onset in the postmarketing reports of patients treated with leuprolide acetate. Although a direct causal relationship between leuprolide acetate therapy and interstitial lung disease has not been established on the basis of the underlying disease (i.e., endometriosis), discontinuation of leuprolide acetate to allow for a potential resolution of the interstitial lung disease should be considered.
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials; therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
Prostate Cancer
LUPRON DEPOT 7.5 mg (1-Month), 22.5 mg (3-Month), 30 mg (4-Month)
The following possibly or probably related systemic adverse reactions were reported by ≥ 5% of the patients using LUPRON DEPOT 7.5, 22.5, and 30 mg in clinical studies (Table 7 ). Reactions not considered drug related are excluded.
Table 7. Incidence (%) of Possibly or Probably Related Systemic Adverse Reactions Reported by ≥ 5% of Patients Treated with LUPRON DEPOT 7.5 mg (1 injection every month), LUPRON DEPOT 22.5 mg (1 injection every 3 months), and LUPRON DEPOT 30 mg (1 injection every 4 months)
LUPRON DEPOT 7.5 mg (1-Month) N=56 (%) Study M85-097 | LUPRON DEPOT 22.5 mg (3-Month)2 Non-Orchiectomized N=94 (%) Studies M91-583 and M91-653 | LUPRON DEPOT 30 mg (4-Month) Non-Orchiectomized N=49 (%) Study M93-013 | LUPRON DEPOT 30 mg (4-Month) Orchiectomized N=24 (%) Study M93-0123 | ||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Body as a Whole | |||||||||||||||
| Asthenia | 3 (5) | 7 (7) | 6 (12) | - | |||||||||||
| Flu syndrome | - | - | 6 (12) | - | |||||||||||
| General pain | 4 (7) | 25 (27) | 16 (33) | - | |||||||||||
| Headache | - | 6 (6) | 5 (10) | - | |||||||||||
| Injection site reaction | - | 13 (14) | 4 (8) | 9 (38) | |||||||||||
| Cardiovascular System | |||||||||||||||
| Hot flashes/sweats1 | 33 (59) | 55 (59) | 23 (47) | 2 (8) | |||||||||||
| Gastrointestinal System | |||||||||||||||
| Nausea/vomiting | 3 (5) | - | - | - | |||||||||||
| GI disorder | - | 15 (16) | 5 (10) | 3 (13) | |||||||||||
| Metabolic and Nutritional Disorders | |||||||||||||||
| Dehydration | - | - | 4 (8) | - | |||||||||||
| Edema | 7 (13) | - | 4 (8) | 5 (21) | |||||||||||
LUPRON DEPOT 7.5 mg (1-Month) N=56 (%) Study M85-097 | LUPRON DEPOT 22.5 mg (3-Month)2 Non-Orchiectomized N=94 (%) Studies M91-583 and M91-653 | LUPRON DEPOT 30 mg (4-Month) Non-Orchiectomized N=49 (%) Study M93-013 | LUPRON DEPOT 30 mg (4-Month) Orchiectomized N=24 (%) Study M93-0123 | ||||||||||||
| Musculoskeletal System | |||||||||||||||
| Joint disorder | - | 11 (12) | 8 (16) | - | |||||||||||
| Myalgia | - | 4 (8) | - | ||||||||||||
| Central/Peripheral Nervous System | |||||||||||||||
| Dizziness/Vertigo | - | 6 (6) | 3 (6) | 2 (8) | |||||||||||
| Insomnia/Sleep disorders | - | 8 (9) | - | - | |||||||||||
| Neuromuscular disorders | - | 9 (10) | 3 (6) | - | |||||||||||
| Paresthesia | - | - | 4 (8) | - | |||||||||||
| Respiratory System | |||||||||||||||
| Dyspnea | 3 (5) | - | - | - | |||||||||||
| Respiratory disorders | - | 6 (6) | 4 (8) | - | |||||||||||
| Skin and Appendages | |||||||||||||||
| Skin reaction | - | 8 (9) | 6 (12) | - | |||||||||||
| Urogenital System | |||||||||||||||
| Testicular atrophy1 | 3 (5) | 19 (20) | - | - | |||||||||||
| Impotence1 | 3 (5) | - | - | - | |||||||||||
| Urinary disorders | 14 (15) | 5 (10) | 4 (17) | ||||||||||||
| |||||||||||||||
LUPRON DEPOT 45 mg (6-Month)
Table 8. Incidence (%) of Adverse Reactions Reported by ≥ 5% of Patients Treated with LUPRON DEPOT 45 mg (1 injection every 6 months) in Study L-PC07-169
LUPRON DEPOT 45 mg (6-Month) N =151 (%) | |||||||
|---|---|---|---|---|---|---|---|
| Any Relationship | Possibly or Probably Related | ||||||
| Vascular Disorders | |||||||
| Hot flush1 | 88 (58) | 87 (58) | |||||
| Hypertension | 9 (6) | - | |||||
| |||||||
LUPRON DEPOT 45 mg (6-Month) N =151 (%) | |||||||
| Any Relationship | Possibly or Probably Related | ||||||
| Blood and Lymphatic System Disorders | |||||||
| Anemia | 8 (5) | - | |||||
| Gastrointestinal Disorders | |||||||
| Constipation | 15 (10) | - | |||||
| General Disorders and Administration Site Conditions | |||||||
| Injection site pain | 27 (18) | 15 (10) | |||||
| Fatigue1 | 18 (12) | 15 (10) | |||||
| Infections and Infestations | |||||||
| Nasopharyngitis | 10 (7) | - | |||||
| Upper respiratory tract infection | 8 (5) | - | |||||
| Urinary tract infection | 8 (5) | - | |||||
| Musculoskeletal and Connective Tissue Disorders | |||||||
| Arthralgia | 14 (9) | - | |||||
| Back pain | 8 (5) | - | |||||
| Musculoskeletal pain | 8 (5) | - | |||||
| Nervous System Disorders | |||||||
| Headache | 11 (7) | - | |||||
| Dizziness | 8 (5) | - | |||||
| Psychiatric Disorders | |||||||
| Insomnia | 13 (9) | - | |||||
| Renal and Urinary Disorders | |||||||
| Haematuria | 10 (7) | - | |||||
| Dysuria | 9 (6) | - | |||||
| Nocturia | 8 (5) | - | |||||
| Respiratory, Thoracic and Mediastinal Disorders | |||||||
| Chronic obstructive pulmonary disease | 8 (5) | - | |||||
| Cough | 10 (7) | - | |||||
| Skin and Subcutaneous Tissue Disorders | |||||||
| Rash | 9 (6) | - | |||||
In Study L-PC07-169, 8 patients who had escapes from suppression (any testosterone value greater than 50 ng/dL after castrate levels achieved) did not experience any associated increases in PSA levels or adverse reactions.
Endometriosis
LUPRON DEPOT 3.75 mg (1-Month)
In two controlled clinical trials treating endometriosis, one comparing LUPRON DEPOT 3.75 mg (1-Month) with danazol (800 mg/day) and the other with placebo, the following adverse reactions were reported to have a possible or probable relationship to study drugs as ascribed by the treating physician in 5% or more of the patients receiving the drug (Table 9).
Table 9. Adverse Reactions Reported Having a Possible or Probable Relationship to Study Drugs in 5% or More of Patients Receiving LUPRON DEPOT 3.75 mg (1-Month) versus Danazol (800 mg/day) and LUPRON DEPOT 3.75 mg (1-Month) versus Placebo
LUPRON DEPOT 3.75 mg (1-Month) N=166 (%) | Danazol 800 mg/day N=136 (%) | Placebo N=31 (%) | |||||||
|---|---|---|---|---|---|---|---|---|---|
| Number of Reports (%) | |||||||||
| Cardiovascular System | |||||||||
| Edema | 12 (7) | 17 (13) | 1 (3) | ||||||
| Gastrointestinal System | |||||||||
| Nausea/vomiting | 21 (13) | 17 (13) | 1 (3) | ||||||
| GI disturbances1 | 11 (7) | 8 (6) | 1 (3) | ||||||
| Endocrine System | |||||||||
| Hot flashes/sweats1 | 139 (84) | 77 (57) | 9 (29) | ||||||
| Breast changes, tenderness/pain1 | 10 (6) | 12 (9) | 0 (0) | ||||||
| Decreased libido1 | 19 (11) | 6 (4) | 0 (0) | ||||||
| Androgen-like effects | 22 (13) | 44 (32)2 | 1 (3) | ||||||
| Virilism | 0 (0) | 1 (1) | 0 (0) | ||||||
| Acne | 17 (10) | 27 (20) | 0 (0) | ||||||
LUPRON DEPOT 3.75 mg (1-Month) N=166 (%) | Danazol 800 mg/day N=136 (%) | Placebo N=31 (%) | |||||||
| Number of Reports (%) | |||||||||
| Seborrhea | 2 (1) | 5 (4) | 0 (0) | ||||||
| Hirsutism | 2 (1) | 9 (7) | 1 (3) | ||||||
| Voice alteration | 1 (1) | 2 (1) | 0 (0) | ||||||
| Musculoskeletal System | |||||||||
| Myalgia1 | 1 (1) | 7 (5) | 0 (0) | ||||||
| Joint disorder1 | 14 (8) | 11 (8) | 0 (0) | ||||||
| Central/Peripheral Nervous System | |||||||||
| Depression/emotional lability1 | 36 (22) | 27 (20) | 1 (3) | ||||||
| Headaches1 | 53 (32) | 30 (22) | 2 (6) | ||||||
| Dizziness | 19 (11) | 4 (3) | 0 (0) | ||||||
| Insomnia/sleep disorders1 | 2 (1) | 4 (3) | 0 (0) | ||||||
| General pain | 31 (19) | 22 (16) | 1 (3) | ||||||
| Neuromuscular disorders1 | 11 (7) | 17 (13) | 0 (0) | ||||||
| Nervousness1 | 8 (5) | 11 (8) | 0 (0) | ||||||
| Paresthesias | 12 (7) | 11 (8) | 0 (0) | ||||||
| Integumentary System | |||||||||
| Skin reactions | 17 (10) | 20 (15) | 1 (3) | ||||||
| Urogenital System | |||||||||
| Vaginitis1 | 46 (28) | 23 (17) | 0 (0) | ||||||
| Miscellaneous | |||||||||
| Asthenia | 5 (3) | 9 (7) | 0 (0) | ||||||
| Weight gain/loss | 22 (13) | 36 (26) | 0 (0) | ||||||
Reactions considered not drug-related are excluded. | |||||||||
LUPRON DEPOT 11.25 mg (3-Month)
In a pharmacokinetic trial involving 20 healthy female subjects receiving LUPRON DEPOT 11.25 mg (3-Month), a few adverse events were reported with this formulation that were not reported previously. These included face edema, agitation, laryngitis and ear pain, and are noted in Table 10.
Table 10. Adverse Events Reported by 20 Healthy Female Subjects Receiving LUPRON DEPOT 11.25 mg (3-Month) in a Pharmacokinetic Trial
LUPRON DEPOT 11.25 mg (3-Month) N=20 (%) | |||
|---|---|---|---|
| Body as a Whole | |||
| Asthenia | 1 (5.0) | ||
| Face edema | 1 (5.0) | ||
| General pain | 4 (20.0) | ||
| Headache/migraine1 | 16 (80.0) | ||
| Cardiovascular System | |||
| Hot flashes/sweats | 13 (65.0) | ||
| Digestive System | |||
| GI disturbance1 | 2 (10.0) | ||
| Liver function test abnormal | 1 (5.0) | ||
| Nausea/vomiting | 2 (10.0) | ||
| Metabolic and Nutritional Disorders | |||
| Edema | 1 (5.0) | ||
| Musculoskeletal System | |||
| Myalgia1 | 2 (10.0) | ||
| Nervous System | |||
| Agitation | 1 (5.0) | ||
| Depression/emotional lability1 | 1 (5.0) | ||
| Dizziness/vertigo | 1 (5.0) | ||
| Insomnia/sleep disorders1 | 2 (10.0) | ||
| Neuromuscular disorders1 | 1 (5.0) | ||
| Respiratory System | |||
| Laryngitis | 1 (5.0) | ||
| Special Senses | |||
| Ear pain | 1 (5.0) | ||
| Urogenital System | |||
| Dysmenorrhea | 1 (5.0) | ||
| |||
Table 11 lists the potentially drug-related adverse events observed in at least 5% of patients in any treatment group, during the first six months of treatment in the add-back clinical studies, in which patients were treated with monthly LUPRON DEPOT 3.75 mg (1-Month) with or without norethindrone acetate co-treatment.
Table 11. Treatment-Related Adverse Events Occurring in ≥ 5% of Patients
Controlled Study (Study M92-878) | Open Label (Study M97-777) | |||||||||
|---|---|---|---|---|---|---|---|---|---|---|
LUPRON DEPOT 3.75 mg N=51 (%) | LUPRON DEPOT 3.75 mg + norethindrone acetate 5 mg N=55 (%) | LUPRON DEPOT 3.75 mg + norethindrone acetate 5 mg N=136 (%) | ||||||||
| Any Adverse Event | 50 (98) | 53 (96) | 126 (93) | |||||||
| Body as a Whole | ||||||||||
| Asthenia | 9 (18) | 10 (18) | 15 (11) | |||||||
| Headache/migraine | 33 (65) | 28 (51) | 63 (46) | |||||||
| Injection site reaction | 1 (2) | 5 (9) | 4 (3) | |||||||
| Pain | 12 (24) | 16 (29) | 29 (21) | |||||||
| Cardiovascular System | ||||||||||
| Hot flashes/sweats | 50 (98) | 48 (87) | 78 (57) | |||||||
| Digestive System | ||||||||||
| Altered bowel function | 7 (14) | 8 (15) | 14 (10) | |||||||
| Changes in appetite | 2 (4) | 0 (0) | 8 (6) | |||||||
| GI disturbance | 2 (4) | 4 (7) | 6 (4) | |||||||
| Nausea/vomiting | 13 (25) | 16 (29) | 17 (13) | |||||||
| Metabolic and Nutritional Disorders | ||||||||||
| Edema | 0 (0) | 5 (9) | 9 (7) | |||||||
| Weight changes | 6 (12) | 7 (13) | 6 (4) | |||||||
| Nervous System | ||||||||||
| Anxiety | 3 (6) | 0 (0) | 11 (8) | |||||||
| Depression/emotional lability | 16 (31) | 15 (27) | 46 (34) | |||||||
| Dizziness/vertigo | 8 (16) | 6 (11) | 10 (7) | |||||||
| Insomnia/sleep disorder | 16 (31) | 7 (13) | 20 (15) | |||||||
| Libido changes | 5 (10) | 2 (4) | 10 (7) | |||||||
| Memory disorder | 3 (6) | 1 (2) | 6 (4) | |||||||
| Nervousness | 4 (8) | 2 (4) | 15 (11) | |||||||
| Neuromuscular disorder | 1 (2) | 5 (9) | 4 (3) | |||||||
| Skin and Appendages | ||||||||||
| Alopecia | 0 (0) | 5 (9) | 4 (3) | |||||||
| Androgen-like effects | 2 (4) | 3 (5) | 24 (18) | |||||||
| Skin/mucous membrane reaction | 2 (4) | 5 (9) | 15 (11) | |||||||
Controlled Study (Study M92-878) | Open Label (Study M97-777) | |||||||||
LUPRON DEPOT 3.75 mg N=51 (%) | LUPRON DEPOT 3.75 mg + norethindrone acetate 5 mg N=55 (%) | LUPRON DEPOT 3.75 mg + norethindrone acetate 5 mg N=136 (%) | ||||||||
| Urogenital System | ||||||||||
| Breast changes/pain/tenderness | 3 (6) | 7 (13) | 11 (8) | |||||||
| Menstrual disorders | 1 (2) | 0 (0) | 7 (5) | |||||||
| Vaginitis | 10 (20) | 8 (15) | 11 (8) | |||||||
In the controlled clinical trial, 50 of 51 (98%) patients in the LUPRON DEPOT 3.75 mg group and 48 of 55 (87%) patients in the LUPRON DEPOT 3.75 mg + norethindrone acetate 5 mg group reported experiencing hot flashes on one or more occasions during treatment. The median number of days on which hot flashes were reported during treatment was 25 and 5 (P<0.05) in the LUPRON DEPOT 3.75 mg and LUPRON DEPOT 3.75 mg + norethindrone acetate 5 mg treatment groups, respectively. The median maximum number of hot flashes in a day during treatment was 5 and 1 (P<0.05) in the LUPRON DEPOT 3.75 mg and LUPRON DEPOT 3.75 mg + norethindrone acetate 5 mg treatment groups, respectively.
Uterine Fibroids
Table 12 lists the adverse drug reactions observed in at least 5% of the LUPRON DEPOT treated patients in uterine fibroids clinical trials.
Table 12. Treatment-Related Adverse Events Occurring in ≥ 5% of Patients treated with LUPRON DEPOT for Uterine Fibroids Studies M86-034, M86-049, M86-062, and M90-411
| System Organ Class (SOC) | N (%) | |
|---|---|---|
LUPRON DEPOT N = 167 | Placebo N = 163 | |
| Infections and Infestations | ||
| Vaginal infection | 18 (10.8) | 2 (1.2) |
| Psychiatric Disorders | ||
| Depression | 13 (7.8) | 4 (2.5) |
| Affect lability | 10 (6.0) | 4 (2.5) |
| Nervousness | 8 (4.8) | 1 (0.6) |
| Insomnia | 8 (4.8) | 1 (0.6) |
| Nervous System Disorders | ||
| Headache | 44 (26.3) | 31 (19.0) |
| Vascular Disorders | ||
| Vasodilatation | 122 (73.1) | 28 (17.2) |
| System Organ Class (SOC) | N (%) | |
LUPRON DEPOT N = 167 | Placebo N = 163 | |
| Musculoskeletal and Connective Tissue Disorders | ||
| Arthralgia | 11 (6.6) | 6 (3.7) |
| General Disorders and Administration site Conditions | ||
| Asthenia | 13 (7.8) | 9 (5.5) |
| Oedema peripheral | 8 (4.8) | 2 (1.2) |
8.2.1 Clinical Trial Adverse Reactions – Pediatrics
In two studies of children with central precocious puberty, in 2% or more of the patients receiving the drug, the following adverse reactions were reported to have a possible or probable relationship to drug as prescribed by the treating physician (see Table 13). Reactions considered not drug related are excluded.
Table 13. Adverse Reactions Reported Having a Possible or Probable Relationship to Drug in 2% or more of Patients Receiving the Drug
Number of Patients N = 421(%) | |||
|---|---|---|---|
| Body as a Whole | |||
| General pain | 12 (3) | ||
| Headache | 11 (3) | ||
| Injection site reaction including abscess1 | 37 (9) | ||
| Cardiovascular System | |||
| Vasodilatation | 9 (2) | ||
| Integumentary System | |||
| Acne/seborrhea | 8(2) | ||
| Rash including erythema multiforme | 12 (3) | ||
| Nervous System | |||
| Emotional lability | 19 (5) | ||
| Urogenital System | |||
| Vaginitis/vaginal bleeding/vaginal discharge | 13 (3) | ||
| |||
8.3 Less Common Clinical Trial Adverse Reactions
Prostate Cancer
The following possibly or probably related systemic adverse reactions were reported by less than 5% of the patients using LUPRON DEPOT 7.5 mg (1-Month), 22.5 mg (3-Month), 30 mg (4-Month), and 45 mg (6-Month) in clinical studies. Reactions not considered drug-related are excluded.
LUPRON DEPOT 7.5 mg (1-Month)
| Cardiovascular System: | angina, cardiac arrhythmia |
|---|---|
| Central/Peripheral Nervous System: | insomnia, paresthesia |
| Endocrine System: | gynecomastia, libido decrease |
| Gastrointestinal System: | anorexia, diarrhea |
| Integumentary System: | dermatitis, local skin reactions, hair growth |
| Musculoskeletal System: | bone pain, myalgia |
| Respiratory System: | dyspnea, hemoptysis |
| Urogenital System: | dysuria, frequency/urgency, hematuria, testicular pain |
| Miscellaneous: | asthenia, diabetes, fever/chills, hard nodule in throat, increased calcium, increased uric acid, serum glutamic oxaloacetic transaminase (SGOT) (> 2 times normal values), weight gain |
LUPRON DEPOT 22.5 mg (3-Month)
| Body as a Whole: | enlarged abdomen, fever |
|---|---|
| Cardiovascular System: | arrhythmia, bradycardia, heart failure, hypertension, hypotension, varicose vein |
| Central/ Peripheral Nervous System: | anxiety, delusions, depression, hypesthesia, libido decrease1, nervousness, paresthesia |
| Digestive System: | anorexia, duodenal ulcer, increased appetite, thirst/dry mouth |
| Hemic and Lymphatic System: | anemia, lymphedema |
| Metabolic and Nutritional Disorders: | dehydration, edema |
| Respiratory System: | epistaxis, pharyngitis, pleural effusion, pneumonia |
| Special Senses: | abnormal vision, amblyopia, dry eyes, tinnitus |
| Urogenital System: | gynecomastia, impotence1, penis disorders, testis disorders |
| |
LUPRON DEPOT 30 mg (4-Month)
| Body as a Whole: | abscess, accidental injury, allergic reaction, cyst, fever, generalized edema, hernia, neck pain, neoplasm |
|---|---|
| Cardiovascular System: | atrial fibrillation, deep thrombophlebitis, hypertension |
| Digestive System: | anorexia, eructation, gastrointestinal hemorrhage, gingivitis, gum hemorrhage, hepatomegaly, increased appetite, intestinal obstruction, periodontal abscess |
| Hemic and Lymphatic System: | lymphadenopathy |
| Metabolic and Nutritional Disorders: | healing abnormal, hypoxia, weight loss |
| Musculoskeletal System: | leg cramps, pathological fracture, ptosis |
| Nervous System: | abnormal thinking, amnesia, confusion, convulsion, dementia, depression, insomnia/sleep disorders, libido decreased1, neuropathy, paralysis |
| Respiratory System: | asthma, bronchitis, hiccup, lung disorder, sinusitis, voice alteration |
| Skin and Appendages: | herpes zoster, melanosis |
| Urogenital System: | bladder carcinoma, epididymitis, impotence1, prostate disorder, testicular atrophy1, urinary incontinence, urinary tract infection |
| |
LUPRON DEPOT 45 mg (6-Month)
| Blood and Lymphatic System Disorders: | anemia |
|---|---|
| Cardiac Disorders: | angina pectoris, mitral valve incompetence, tachycardia, tricuspid valve incompetence |
| Gastrointestinal Disorders: | abdominal pain upper, colonic pseudo-obstruction, constipation, diarrhea, dry mouth, flatulence, haematochezia, nausea, retching |
| General Disorders and Administration Site Conditions: | asthenia, chills, feeling hot, injection site discomfort, injection site erythema, injection site induration, injection site nodule, injection site swelling, injection site warmth, oedema peripheral, pain, pitting oedema, pyrexia |
| Infections and Infestations | injection site cellulitis, sinusitis |
| Injury, Poisoning and Procedural Complications | rib fracture |
| Investigations | alanine aminotransferase increased (ALT), aspartate aminotransferase increased (AST), blood alkaline phosphatase increased, blood glucose increased, gamma-glutamyl transferase (GGT) increased, heart rate irregular, hepatic enzyme increased, liver function test abnormal, weight increased |
| Metabolism and Nutrition Disorders: | anorexia, central obesity, gout, hypercholesterolaemia, hyperkalaemia |
| Musculoskeletal and Connective Tissue Disorders: | arthralgia, bone pain, bursitis, joint stiffness, muscle fatigue, muscle spasms, myalgia, neck pain, osteoarthritis, pain in extremity |
| Neoplasms benign, malignant and unspecified (incl cysts and polyps) | metastases to bone |
| Nervous System Disorders: | dizziness, headache, lethargy, memory impairment |
| Psychiatric Disorders: | depressed mood, libido decreased1, loss of libido, sleep disorders |
| Reproductive System and Breast Disorders: | erectile dysfunction, gynaecomastia, pelvic pain, testicular atrophy |
| Respiratory, Thoracic and Mediastinal Disorders: | cough, dyspnoea, dyspnoea exertional |
| Skin and Subcutaneous Tissue Disorders: | actinic keratosis, cold sweat, erythema, hyperhidrosis, night sweats, pruritus, rash, rash pruritic |
| Vascular Disorders | flushing, hypertension |
| |
Endometriosis and Uterine Fibroids
LUPRON DEPOT 3.75 mg (1-Month)
The following were reported in less than 5% of patients treated with LUPRON DEPOT in endometriosis and uterine fibroids studies:
Body as a Whole: body odor, flu syndrome and injection site reactions
Cardiovascular System: palpitations, syncope and tachycardia
Gastrointestinal System: appetite changes, dry mouth and thirst
Central/Peripheral Nervous System: anxiety1, delusions, memory disorder, insomnia/sleep disorders1, and personality disorder
Endocrine System: androgen-like effects
Hemic and Lymphatic Systems: ecchymosis and lymphadenopathy
Respiratory System: rhinitis
Skin and Appendages: alopecia, hair disorder and nail disorder
Special Senses: conjunctivitis, ophthalmologic disorders1 and taste perversion
Urogenital System: dysuria1, lactation and menstrual disorders
- 1. Physiologic effects of decreased estrogen.
8.3.1 Less Common Clinical Trial Adverse Reactions – Pediatrics
In two studies of children with central precocious puberty, the following adverse reactions were reported by less than 2% of the patients.
Body as a Whole: aggravation of pre-existing tumor and decreased vision, allergic reaction, body odor, fever, flu syndrome, infection, hypertrophy
Cardiovascular System: bradycardia, hypertension, peripheral vascular disorder, syncope
Digestive System: constipation, dyspepsia, dysphagia, gingivitis, increased appetite, nausea/vomiting
Endocrine System: accelerated sexual maturity, feminization, goiter
Hemic and Lymphatic System: purpura
Metabolic and Nutritional Disorders: growth retarded, peripheral edema, weight gain
Musculoskeletal System: arthralgia, joint disorder, myalgia, myopathy
Nervous System: depression, hyperkinesia, nervousness, somnolence
Respiratory System: asthma, epistaxis, pharyngitis, rhinitis, sinusitis
Integumentary System: alopecia, hair disorder, hirsutism, leukoedema, nail disorder, skin hypertrophy, urticaria
Urogenital System: cervix disorder/neoplasm, dysmenorrhea, gynecomastia/breast disorders, menstrual disorder, urinary incontinence
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data
Central Precocious Puberty
The following laboratory events were recorded as adverse reactions: antinuclear antibody present and increased sedimentation rate.
See 9.7 Drug-Laboratory Test Interactions section.
Prostate Cancer
Abnormalities of certain parameters observed in hematologic and clinical chemistry determinations were recorded, but relationship to drug is difficult to assess in this population.
The following were recorded in ≥ 5% of patients in clinical studies with LUPRON DEPOT 7.5 mg (1-Month), 22.5 mg (3-Month), 30 mg (4-Month), and 45 mg (6-Month):
LUPRON DEPOT 7.5 mg (1-Month)
Lactate dehydrogenase (LDH) (> 2 times normal values), alkaline phosphatase (> 1.5 times normal values).
In the Phase 3, open-label, multicenter 24-week study of previously untreated patients with stage D2 prostate cancer (Study M85-097), treated with LUPRON DEPOT 7.5 mg (1-Month) injected monthly, 1/56 (2%) patients had an asymptomatic elevation of aspartate aminotransferase (AST) > 3X ULN. This patient did not have a concomitant elevation in bilirubin. Alanine aminotransferase (ALT) was not measured in this study.
LUPRON DEPOT 22.5 mg (3-Month)
Increased BUN, hyperglycemia, hyperlipidemia [total cholesterol, low-density lipoprotein (LDL)-cholesterol, triglycerides], hyperphosphatemia, abnormal liver function tests, increased PT, increased PTT. Additional laboratory abnormalities reported were: decreased platelets, decreased potassium and increased WBC.
LUPRON DEPOT (3-Month) has not clinically affected the mean systolic or diastolic blood pressure. Nor the effect on the mean pulse rate is indicative of a clinically significant trend. However, mean body weight significantly increased (p < 0.001) during the treatment. These results were not unexpected, since patients generally showed clinical improvement with treatment during the study. The effect on clinical laboratory determinations [hemogram, white blood cell (WBC), % basophils, total-, high-density lipoprotein (HDL)-, low-density lipoprotein (LDL)-cholesterol, triglycerides, serum glutamate pyruvate transaminase (SGPT), phosphorus, sodium and glucose) were often attributed, by the investigator, to the underlying disease state, to non-fasting blood collection, or as being consistent with the age and status of the patient population studied. As expected, pretreatment levels of alkaline phosphatase reflected the presence of bony metastatic disease. Changes during treatment reflected the continuing presence of, and presumably the treatment-related reduction, in bony metastatic disease.
LUPRON DEPOT 30 mg (4-Month)
Abnormalities of certain parameters were observed, but their relationship to drug treatment are difficult to assess in this population. The following were recorded in ≥ 5% of patients: decreased bicarbonate, decreased hemoglobin/hematocrit/red blood cell (RBC), hyperlipidemia (total cholesterol, LDL-cholesterol, triglycerides), decreased high-density lipoprotein (HDL)-cholesterol, eosinophilia, increased glucose, increased liver function tests [alanine aminotransferase (ALT), aspartate aminotransferase (AST), gamma-glutamyl transpeptidase (GGTP), lactate dehydrogenase (LDH)], and increased phosphorus. Additional laboratory abnormalities were reported: increased BUN and PT, leukopenia, thrombocytopenia, uricaciduria, urine abnormality.
See 9.7 Drug-Laboratory Test Interactions section for more details.
LUPRON DEPOT 45 mg (6-Month)
Abnormalities of certain parameters were observed, but their relationship to drug treatment is difficult to assess in this population. The following abnormalities were recorded in ≥ 5% of patients: decreased hemoglobin, decreased hematocrit, decreased red blood cells, increased eosinophils, increased AST, increased GGT, increased BUN, increased phosphorus, increased creatinine, increased glucose, increased LDL-cholesterol, increased total cholesterol, increased triglycerides, decreased HDL-cholesterol, and decreased eGFR. Additional laboratory abnormalities reported were increased ALT and increased LDH.
Endometriosis/Uterine Fibroids
See 7 WARNINGS AND PRECAUTIONS.
8.5 Post-Market Adverse Reactions
Central Precocious Puberty
Isolated cases of anaphylaxis have been reported. Symptoms consistent with an anaphylactoid or asthmatic process have been rarely reported.
Pituitary Apoplexy
During postmarketing surveillance, rare cases of pituitary apoplexy (a clinical syndrome secondary to infarction of the pituitary gland) have been reported after the administration of gonadotropin-releasing hormone agonists. In a majority of these cases, a pituitary adenoma was diagnosed, with a majority of pituitary apoplexy cases occurring within two weeks of the first dose, and some within the first hour. In these cases, pituitary apoplexy has presented as sudden headache, vomiting, visual changes, ophthalmoplegia, altered mental status, and sometimes cardiovascular collapse. Immediate medical attention has been required.
Psychiatric Events
Psychiatric events have been reported in patients taking GnRH agonists. Postmarketing reports with this class of drugs include symptoms of emotional lability, such as crying, irritability, impatience, anger and aggression. A definitive cause and effect relationship between the treatment with GnRH agonists and the occurrence of these events has not been established. Monitor for development or worsening of psychiatric symptoms during treatment with leuprolide acetate.
During postmarketing surveillance, which includes other dosage forms and other patient populations, the following adverse events were reported:
Cardiovascular System: hot flush, hypertension, hypotension, flushing
Digestive System: abdominal pain, nausea, vomiting
Hemic and Lymphatic System: decreased WBC
Central/Peripheral Nervous System: convulsion, peripheral neuropathy, pseudotumor cerebri/idiopathic intracranial hypertension, spinal fracture/paralysis
Immune System Disorders: acute hypersensitivity reactions (such as anaphylaxis, rash, urticaria), Stevens-Johnson Syndrome, Toxic Epidermal Necrolysis, dermatitis bullous, dermatitis exfoliative, erythema multiforme, hyperhidrosis, photosensitivity reactions
Metabolic and Nutritional Disorders: diabetes mellitus, weight increased
Musculoskeletal System: tenosynovitis-like symptoms
Respiratory System: chest pain
Urogenital System: prostate pain
Miscellaneous: injection site reactions including pain, inflammation, sterile abscess, induration, hematoma and necrosis
Prostate Cancer
Isolated cases of anaphylaxis have been reported. Symptoms consistent with an anaphylactoid or asthmatic process have been rarely reported.
There have been reports of suicidal ideation and attempt. Many, but not all, of these patients had a history of depression or other psychiatric illness.
Pituitary Apoplexy
During postmarketing surveillance, rare cases of pituitary apoplexy (a clinical syndrome secondary to infarction of the pituitary gland) have been reported after the administration of gonadotropin-releasing hormone agonists. In a majority of these cases, a pituitary adenoma was diagnosed, with a majority of pituitary apoplexy cases occurring within two weeks of the first dose, and some within the first hour. In these cases, pituitary apoplexy has presented as sudden headache, vomiting, visual changes, ophthalmoplegia, altered mental status, and sometimes cardiovascular collapse. Immediate medical attention has been required.
Changes in Bone Density
Decreased bone density has been reported in the medical literature in men who have had orchiectomy or who have been treated with an LHRH agonist analog. In a clinical trial, 25 men with prostate cancer, 12 of whom had been treated previously with leuprolide acetate for at least six months, underwent bone density studies as a result of pain. The leuprolide acetate-treated group had lower bone density scores than the non-treated control group. From another case report, two additional men, one 64 and the other 70 years, respectively, receiving goserelin acetate, were observed to have collapsed vertebrae thought to be due to decreased bone mineral density. It can be anticipated that long periods of medical castration in men will have effects on bone density.
During postmarketing surveillance, which includes other dosage forms and other patient populations, the following adverse events were reported:
Cardiovascular System: cardiac arrest, hypotension, myocardial infarction, and sudden cardiac death
Central/Peripheral Nervous System: convulsion, peripheral neuropathy, spinal fracture/paralysis
Hemic and Lymphatic System: decreased WBC
Hepatobiliary Disorders: non-alcoholic fatty liver disease, serious liver injury (including fatal cases)
Immune System Disorders: acute hypersensitivity reactions (such as anaphylaxis, rash, urticaria), Stevens-Johnson Syndrome, Toxic Epidermal Necrolysis, dermatitis bullous, dermatitis exfoliative, erythema multiforme, photosensitivity reactions
Musculoskeletal System: tenosynovitis-like symptoms
Urogenital System: prostate pain
Miscellaneous: injection site reactions including pain, inflammation, sterile abscess, induration, hematoma and necrosis
Respiratory System: interstitial lung disease, pulmonary fibrosis
Endometriosis/Uterine Fibroids
Isolated cases of anaphylaxis have been reported. Symptoms consistent with an anaphylactoid or asthmatic process have been rarely reported.
Cases of serious venous and arterial thromboembolism have been reported, including deep vein thrombosis, pulmonary embolism, myocardial infarction, stroke, and transient ischemic attack. Although a temporal relationship was reported in some cases, most cases were confounded by risk factors or concomitant medication use. It is unknown if there is a causal association between the use of GnRH agonists and these events.
Like other drugs in this class, mood swings, including depression, have been reported as a physiologic effect of decreased sex steroids. There have been very rare reports of suicidal ideation and attempt. Many, but not all, of these patients had a history of depression or other psychiatric illness. Patients should be counselled on the possibility of worsening of depression.
Pituitary Apoplexy
During postmarketing surveillance, rare cases of pituitary apoplexy (a clinical syndrome secondary to infarction of the pituitary gland) have been reported after the administration of gonadotropin-releasing hormone agonists. In a majority of these cases, a pituitary adenoma was diagnosed, with a majority of pituitary apoplexy cases occurring within two weeks of the first dose, and some within the first hour. In these cases, pituitary apoplexy has presented as sudden headache, vomiting, visual changes, ophthalmoplegia, altered mental status, and sometimes cardiovascular collapse. Immediate medical attention has been required.
Symptoms consistent with fibromyalgia (e.g., joint and muscle pain, headaches, sleep disorders, gastrointestinal distress, and shortness of breath) have been reported individually and collectively. The relationship of any of these symptoms to leuprolide acetate has not been established.
The following events have been reported during postmarketing surveillance:
Cardiovascular System: hypotension
Central/Peripheral Nervous System: convulsion, peripheral neuropathy, spinal fracture/paralysis
Hemic and Lymphatic Systems: decreased WBC
Hepatobiliary Disorders: hepatic dysfunction, serious liver injury
Immune System Disorders: acute hypersensitivity reactions (such as anaphylaxis, rash, urticaria), Stevens-Johnson Syndrome, Toxic Epidermal Necrolysis, dermatitis bullous, dermatitis exfoliative, erythema multiforme, photosensitivity reactions
Miscellaneous: injection site reactions including pain, inflammation, sterile abscess, induration, hematoma and necrosis
Musculoskeletal System: tenosynovitis-like symptoms
Respiratory System: dyspnea, interstitial lung disease, pulmonary fibrosis
Urogenital System: menstrual disorders
9 DRUG INTERACTIONS
9.1 Serious Drug Interactions
Not applicable
9.2 Drug Interactions Overview
Leuprolide being approximately 46% bound to plasma proteins, and a peptide that is primarily degraded by peptidase and not by cytochrome P-450 enzymes as noted in specific studies, drug interactions would not be expected to occur.
For patients with endometriosis, refer to the norethindrone acetate 5 mg tablet Product Monograph for information on the drug interactions specific to norethindrone acetate.
9.3 Drug-Behavioural Interactions
Not applicable.
9.4 Drug-Drug Interactions
No pharmacokinetic-based drug-drug interaction studies have been conducted.
Since androgen deprivation treatment may prolong the QTc interval, the concomitant use of leuprolide acetate with medicinal products known to prolong the QTc interval or medicinal products able to induce torsades de pointes should be carefully evaluated. Such medicinal products include but are not limited to the examples that follow: Class IA (e.g., quinidine, disopyramide), Class III (e.g., amiodarone, dronedarone, sotalol, dofetilide, ibutilide), or Class IC (e.g., flecainide, propafenone) antiarrhythmic medicinal products, antipsychotics (e.g. chlorpromazine), antidepressants (e.g., amitriptyline, nortriptyline), opioids (e.g. methadone), macrolide antibiotics and analogues (e.g., erythromycin, clarithromycin, azithromycin), quinolone antibiotics (e.g., moxifloxacin), antimalarials (e.g., quinine), azole antifungals, 5 hydroxytryptamine (5-HT3) receptor antagonists (e.g., ondansetron), and beta-2 adrenoceptor agonists (e.g. salbutamol).
9.5 Drug-Food Interactions
Interactions with food have not been established.
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
Administration of leuprolide acetate in therapeutic doses results in suppression of the pituitary-gonadal system. Normal function is usually restored within 4 to 12 weeks after treatment is discontinued. Diagnostic tests of pituitary-gonadal function conducted during treatment and within 4 to 8 weeks after discontinuation of LUPRON DEPOT therapy may therefore be misleading.
As expected, leuprolide acetate administration will initially affect selected serum and urine parameters in the first week of treatment: elevation of BUN, creatinine, acid phosphatase, testosterone and dihydrotestosterone can be expected. With chronic administration, these high values will usually return to normal, or drop below baseline in the case of testosterone, dihydrotestosterone and acid phosphatase.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
Leuprolide acetate is a synthetic nonapeptide analog of naturally-occurring gonadotropin-releasing hormone (GnRH or LHRH). The analog possesses greater potency than the natural hormone. When administered as indicated, leuprolide acetate acts as a potent inhibitor of gonadotropin production. It is chemically unrelated to steroids.
Unlike steroid hormones, leuprolide acetate exerts specific action on the pituitary gonadotrophs and the human reproductive tract.
This specificity reduces the likelihood of secondary adverse effects such as gynecomastia, thromboembolism, edema, liver and gallbladder involvement.
10.2 Pharmacodynamics
Animal and human studies indicate that, following an initial stimulation, chronic administration of leuprolide acetate results in the inhibition of gonadotropin production. Consequently, ovarian or testicular steroidogenesis is suppressed. These effects are reversible on discontinuation of drug therapy. The therapeutic effect of leuprolide acetate in the treatment of hormone-dependent tumors, such as in prostatic cancer, results from the reduction in serum gonadotropins and gonadal steroids.
Chronic administration of leuprolide acetate has resulted in inhibition of tumor growth (prostatic tumors in Noble and Dunning male rats, 7-12-dimethylbenz[α]-anthracene (DMBA)-induced mammary tumors in female rats) as well as atrophy of the reproductive organs. An additional mechanism of action, a direct effect on the gonads by downregulation of the gonadotropin receptors, is suggested in some animal studies.
In humans, subcutaneous administration of single daily doses of leuprolide acetate results in an initial increase in circulating levels of luteinizing hormone (LH) and follicle stimulating hormone (FSH), leading to a transient increase in the levels of the gonadal steroids (testosterone and dihydrotestosterone in males and estrone and estradiol in premenopausal females). However, continuous administration results in decreased levels of LH and FSH in all patients. In males, testosterone is reduced to castrate levels. In premenopausal females, estrogens are reduced to postmenopausal levels. These decreases occur within two to four weeks after initiation of treatment, and are maintained as long as treatment continues. Castrate levels of testosterone in prostatic cancer patients have been demonstrated for periods of up to five years.
10.2.1 Central Precocious Puberty
Two chronic studies involving the treatment of children with central precocious puberty (CPP), demonstrated that following the administration of leuprolide acetate, stimulated and basal gonadotropins are reduced to prepubertal levels. Testosterone and estradiol are reduced to prepubertal levels in males and females, respectively, and a reduction of gonadotropins will allow for normal physical and psychological growth and development. Natural maturation occurs when gonadotropins return to pubertal levels following discontinuation of leuprolide acetate.
The following physiological effects have been noted with the chronic administration of leuprolide acetate in CPP patients.
- Skeletal Growth: A measurable increase in body length can be noted since the epiphyseal plates will not close prematurely.
- Organ Growth: Reproductive organs will return to a prepubertal state.
- Menses: Menses, if present, will cease.
Intramuscular injection of LUPRON DEPOT provides plasma concentrations of leuprolide acetate over a period of one month.
In a study of 22 children with central precocious puberty, doses of LUPRON DEPOT were given every four weeks and plasma levels were determined according to weight categories as summarized in Table 14.
Table 14. Determination of Leuprolide Plasma Levels According to Weight Categories in Children with Central Precocious Puberty
Patient Weight Range (kg) | Group Weight Average (kg) | Dose (mg) | Trough Plasma Leuprolide Level Mean ± SD (ng/mL)1 |
|---|---|---|---|
| 20.2 - 27.0 | 22.7 | 7.5 | 0.77 ± 0.033 |
| 28.4 - 36.8 | 32.5 | 11.25 | 1.25 ± 1.06 |
| 39.3 - 57.5 | 44.2 | 15.0 | 1.59 ± 0.65 |
| |||
10.2.2 Endometriosis
Endometriosis is a gynecologic disorder wherein endometrial tissue is found to be established in sites outside the endometrial cavity. As definitive diagnosis can only be made during surgery, the true incidence of the disease is unknown.
The etiology of the disease is unclear. An accepted theory of the etiology of endometriosis is the retrograde flow of menstrual fluid with subsequent implantation of viable fragments of endometrium within the pelvic cavity (Sampson's theory). However, this theory does not explain the extra-pelvic sites of endometriosis such as the limbs, thoracic cavity and elsewhere. It has also been suggested that chronic irritation of the peritoneum by menstrual blood may be causative. Another theory is that endometrial tissues are displaced into an implant in new sites during surgery. Genetic and immunologic factors may account for spontaneous endometriosis in a small segment of the population. It is also believed that endometriosis may be caused by lymphatic and hematogenous spread of normal endometrium to distant sites.
Endometriosis may be treated both surgically and medically. Since endometriosis resolves after oophorectomy and menopause, surgical castration may be used to treat the disease. A menopausal state may also be achieved medically. The resultant hypoestrogenic environment results in atrophic changes in both the uterine and ectopic endometrial tissue.
LUPRON DEPOT achieves a menopausal state by suppression of the pituitary-ovarian axis by inhibiting the output of gonadotropins (FSH and LH) from the pituitary gland.
In female volunteers receiving a single dose of LUPRON DEPOT 3.75 mg (1-Month) intramuscularly, an initial burst of leuprolide in plasma was observed. Mean plasma leuprolide levels of approximately 0.23 to 0.34 ng/mL were maintained over a period of four to five weeks, and then slowly tapered off, becoming undetectable eight weeks after injection.
In a pharmacokinetic/pharmacodynamic study of healthy female subjects (N=20), the onset of estradiol suppression was observed for individual subjects between Day 4 and Week 4 after dosing. By the third week following the injection, the mean estradiol concentration (8 pg/mL) reached the menopausal range. Throughout the remainder of the dosing period, mean serum estradiol levels ranged from the menopausal to the early follicular range.
LUPRON DEPOT 11.25 mg (3-Month) induced amenorrhea in 85% (N=17) of subjects during the initial month and 100% during the second month following the injection. All subjects remained amenorrhoeic through the remainder of the 12-week dosing interval. Episodes of light bleeding and spotting were reported by a majority of subjects during the first month after the injection and in a few subjects at later time-points. Menses resumed on average 12 weeks (range 2.9 to 20.4 weeks) following the end of the 12-week dosing interval.
LUPRON DEPOT 11.25 mg (3-Month) produced similar pharmacodynamic effects in terms of hormonal and menstrual suppression to those achieved with monthly injections of LUPRON DEPOT 3.75 mg (1-Month) during the controlled clinical trials for the management of endometriosis. Similar clinical outcome to that with LUPRON DEPOT 3.75 mg (1-Month) administered monthly is predicted with LUPRON DEPOT 11.25 mg (3-Month) administered every three months.
10.3 Pharmacokinetics
Intramuscular injections of LUPRON DEPOT 3.75 mg (1-Month), 7.5 mg (1-Month), 11.25 mg (3-Month), 22.5 mg (3-Month), 30 mg (4-Month), and 45 mg (6-Month) provide plasma concentrations of leuprolide acetate over a period of one, three, four, and six months.
Leuprolide is not active when given orally.
Absorption
A single dose of LUPRON DEPOT 3.75 mg (1-Month) was administered by intramuscular injection to healthy adult female volunteers. The absorption of leuprolide was characterized by an initial increase in plasma concentration, with peak concentration ranging from 4.6 to 10.2 ng/mL at four hours post-dosing. However, intact leuprolide and an inactive metabolite could not be distinguished by the assay used in the study. Following the initial rise, leuprolide concentrations started to plateau within two days after dosing and remained relatively stable for about four to five weeks with plasma concentrations of about 0.30 ng/mL.
Following a single LUPRON DEPOT 7.5 mg (1-Month) intramuscular injection to adult patients, the mean peak leuprolide plasma concentration was almost 20 ng/mL at four hours and then declined to 0.36 ng/mL at four weeks. However, intact leuprolide and an inactive major metabolite could not be distinguished by the assay used in the study. Undetectable leuprolide plasma concentrations have been observed during chronic LUPRON DEPOT 7.5 mg (1-Month) administration, but testosterone levels appear to be maintained at castrated levels.
The pharmacokinetic profile of LUPRON DEPOT 22.5 mg (3-Month) was characterized in 23 orchiectomized prostate cancer patients. Following a single injection of the three-month formulation of LUPRON DEPOT 22.5 mg (3-Month), a mean peak plasma leuprolide concentration of 48.9 ng/mL was observed at four hours and then declined to 0.67 ng/mL at 12 weeks. Leuprolide appeared to be released at a constant rate following the onset of steady state level during the third week after dosing, providing steady plasma concentrations through the 12-week dosing interval. Detectable levels of leuprolide were present at all measurement points in all patients during this 12-week period. The initial burst, followed by the rapid decline to a steady-state level, was similar to the release pattern seen with the monthly formulation.
Following a single injection of the three-month formulation of LUPRON DEPOT 11.25 mg (3-Month) in healthy females, a mean peak plasma leuprolide concentration of 36.3 ng/mL was observed at four hours. Leuprolide appeared to be released at a constant rate following the onset of steady-state levels during the third week after dosing and mean levels then declined gradually to near the lower limit of detection by 12 weeks. The mean (± standard deviation) leuprolide acetate concentration from 3 to 12 weeks was 0.23 ± 0.09 ng/mL. However, intact leuprolide and an inactive major metabolite could not be distinguished by the assay which was employed in the study. The initial burst, followed by the rapid decline to a steady-state level, was similar to the release pattern seen with the monthly formulation.
Following a single injection of LUPRON DEPOT 30 mg (4-Month) in 16 orchiectomized prostate cancer patients, a mean plasma leuprolide concentration of 59.3 ng/mL was observed at four hours and the mean concentration then declined to 0.30 ng/mL at 16 weeks. The mean plasma concentration of leuprolide from Weeks 3.5 to 16 was 0.44 ± 0.20 ng/mL (range: 0.20 to 1.06). Leuprolide appeared to be released at a constant rate following the onset of steady-state levels during the fourth week after dosing, providing steady plasma concentrations throughout the 16-week dosing interval. However, intact leuprolide and an inactive major metabolite could not be distinguished by the assay which was employed in the study. The initial burst, followed by the rapid decline to a steady-state level, was similar to the release pattern seen with the other depot formulations.
In adults, bioavailability by subcutaneous administration is comparable to that by intravenous administration. Leuprolide acetate has a plasma half-life of 2.9 hours.
Following a single injection of LUPRON DEPOT 45 mg (6-Month) in 26 prostate cancer patients, a mean peak plasma leuprolide concentration of 6.7 ng/mL was observed at 2 hours and the mean concentration then declined to 0.07 ng/mL at 24 weeks. Leuprolide appeared to be released continuously following the onset of steady-state levels during the third week after dosing providing steady plasma concentrations through the 24-week dosing interval. The initial burst, followed by the rapid decline to a steady-state level, was similar to the release pattern seen with the other depot formulations. In this study, mean leuprolide plasma concentration-time profiles were similar after the first and second dose.
Distribution
The mean steady-state volume of distribution of leuprolide following intravenous bolus administration to healthy male volunteers was 27 L. In vitro binding to human plasma proteins ranged from 43 to 49%.
Metabolism
In healthy male volunteers, a 1 mg bolus of leuprolide acetate administered intravenously revealed that the mean systemic clearance was 7.6 L/h, with a terminal elimination half-life of approximately three hours based on a two-compartment model.
In rats and dogs, administration of 14C-labelled leuprolide was shown to be metabolized to smaller inactive peptides, pentapeptide (Metabolite I), tripeptides (Metabolites II and III) and dipeptide (Metabolite IV). These fragments may be further catabolized.
The major metabolite (M-I) plasma concentrations measured in five prostate cancer patients reached mean maximum concentration two to six after dosing and were approximately 6% of the peak parent drug concentration. One week after dosing, mean plasma M-I concentrations were approximately 20% of leuprolide concentrations.
Elimination
Following administration of LUPRON DEPOT 3.75 mg (1-Month) to three patients, less than 5% of the dose was recovered as parent and M-I metabolite in the urine.
Special Populations and Conditions
Pediatrics
A pharmacokinetic study of leuprolide acetate in children has not been performed.
Geriatrics
See 7.1.4 Geriatrics section.
Sex
No gender related pharmacokinetic differences have been observed in adult patients studied.
Genetic Polymorphism
No data available on genetic polymorphism.
Ethnic Origin
Pharmacokinetic differences due to race have not been identified.
Hepatic Insufficiency
The pharmacokinetics of the drug in patients with hepatic impairment have not been determined.
Renal Insufficiency
The pharmacokinetics of the drug in patients with renal impairment have not been determined.
11 STORAGE, STABILITY AND DISPOSAL
Store at room temperature between 15 and 25°C. Protect from freezing.
Although the suspension has been shown to be stable for 24 hours following reconstitution, since the product does not contain a preservative, the suspension should be discarded if not used immediately.
Keep out of reach and sight of children.
12 SPECIAL HANDLING INSTRUCTIONS
It is very important to activate the LuproLoc safety device immediately after injection. This is done by pushing the arrow forward with the thumb or finger until the device is fully extended and a CLICK is heard or felt. See 4.3.2 Reconstitution.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: leuprolide acetate
Chemical name: 5-oxo-L-prolyl-L-histidyl-L-tryptophyl-L-seryl-L-tyrosyl-D Leucyl-L-leucyl-L-arginyl-N-ethyl-L-prolinamide acetate.
or: des-Glycine10, [D-Leucine6) LH-RH ethylamide acetate
or:[D-Leu6, des-Gly-NH210, Proethylamide9] GnRH
Molecular formula and molecular mass: C59H84N16O12 ∙C2H4O2 1209.41 as free base
Structural formula:
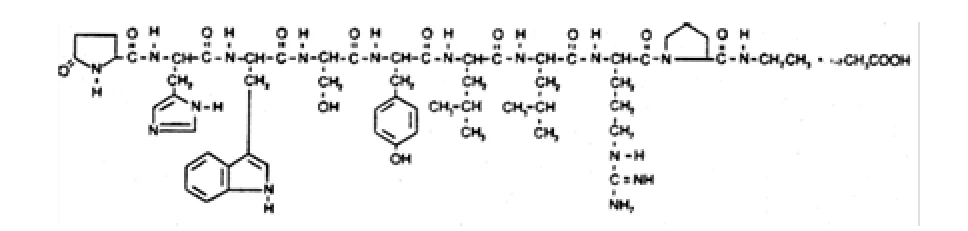
Physicochemical properties: Leuprolide acetate is a fine or fluffy, white to off-white powder, very soluble in water, ethanol and propylene glycol; pKa = 9.6.
14 CLINICAL TRIALS
14.1 Clinical Trials by Indication
Central Precocious Puberty
Table 15. Summary of Patient Demographics for Clinical Trials in Patients with Central Precocious Puberty
| Study # | Trial design | Dosage, route of administration and duration | Study subjects (n) | Mean age (Range) | Gender |
|---|---|---|---|---|---|
| M90-516 | Phase 3, open, multicenter study | LUPRON DEPOT 7.5, 11.25 or 15 mg based on body weight Intramuscular Drug is discontinued when an age appropriate for puberty is attained | 22 | 6.9 years (1.1 - 8.9 years) | 2 M, 20 F |
| Definitions: M = male; F = female | |||||
In an open, multicenter study, LUPRON DEPOT was shown to be safe and effective in the therapeutic management of children with central precocious puberty (CPP). Successful suppression of gonadotropins and sex steroids to prepubertal levels was achieved in 95% of the children by Week 4. In addition, the majority of these children demonstrated decreases or stabilization in Tanner staging of breast, pubic hair, and genitalia compared with baseline. Menses ceased in all females by the end of the second therapeutic month, and growth rates were reduced.
Table 16. Results of Study M90-516 in Patients with Central Precocious Puberty
| Primary Endpoints | Associated value and statistical significance for LUPRON DEPOT |
|---|---|
The criteria for effectiveness include:
| Successful suppression of gonadotropins and sex steroids to prepubertal levels was achieved in 95% of the children by week 4. |
In an open, non-comparative, multi-centre study involving leuprolide acetate injection and LUPRON DEPOT, once adequate suppression of the pituitary-gonadal axis was achieved, the children demonstrated both physical and psychological regression of sexual maturation, slowing of linear growth velocity, and a decrease in the ratio of bone age to chronological age.
Although no clinical studies have been completed in children to assess the full reversibility of fertility suppression, animal studies (prepubertal and adult rats and monkeys) with leuprolide acetate and other gonadotropin-releasing hormone (GnRH) analogs have shown functional recovery. However, following a study with leuprolide acetate, immature male rats demonstrated tubular degeneration in the testes even after a recovery period. In spite of the failure to recover histologically, the treated males proved to be as fertile as the controls. Also, no histologic changes were observed in the female rats following the same protocol. In both sexes, the offspring of the treated animals appeared normal. The effect of the treatment of the parents on the reproductive performance of the F1 generation was not tested. The clinical significance of these findings is unknown.
Prostate Cancer
LUPRON DEPOT
Table 17. Summary of Patient Demographics for Clinical Trials with LUPRON DEPOT in Prostate Cancer
| Study # | Trial Design | Dosage, Route of Administration and Duration | Study Subjects (n) | Mean Age (Range) |
|---|---|---|---|---|
| M91-653 | Phase III, open-label, multicenter study | 22.5 mg LUPRON DEPOT injected every 12 weeks Intramuscular Minimum 24 weeks | 331 | 69 years (55 to 82 years) |
| M93-013 | Phase III, open-label, multicenter study | 30 mg LUPRON DEPOT injected every 16 weeks Intramuscular Minimum 32 weeks | 49 | 70 years (54 to 84 years) |
| L-PC07-169 | Phase III, open-label, multicenter study | 45 mg LUPRON DEPOT injected every 24 weeks Intramuscular 48 weeks | 151 | 75 (48 to 92 years) |
| ||||
| Study # | Trial Design | Dosage, Route of Administration and Duration | Study Subjects (n) | Mean Age (Range) |
| M85-097 | Phase III, open-label, multicenter study | 7.5 mg LUPRON DEPOT injected every 4 weeks Intramuscular 24 weeks | 53 | -- |
| M91-583 | Phase III, open-label, multicenter study | 22.5 mg LUPRON DEPOT injected every 12 weeks Intramuscular Minimum 24 weeks | 611 | 71 years (53 to 86 years) |
Study M85-097 LUPRON DEPOT 7.5 mg for 1-Month Administration
A Phase 3, open, multicenter study was carried out to determine whether the LUPRON DEPOT 7.5 mg (1-Month) injected intramuscularly once every four weeks would reduce testosterone to, and maintain it at, castrate levels (≤ 50 ng/dL) in 56 previously untreated prostate cancer patients, and to evaluate objective clinical response.
The results are as follows:
Objective response
Best objective response was determined over a period of 24 weeks for 53 evaluable patients. Eighty one percent (81%) of the patients responded favourable (no progression) to treatment at some time. This result was not significantly different from the response rate of 86% observed for patients receiving the daily subcutaneous injection of leuprolide acetate solution reported in the previous study.
Testosterone levels
The median time to onset of castrate levels of testosterone for 53 evaluable patients was 21 days, and mean testosterone levels fell within the castrate range by Week 3 of treatment. After the onset of castrate levels, there were no escapes of testosterone values, provided that patients received their monthly injections on time. The pattern of testosterone release over the first 24 weeks of treatment did not differ from that observed in patients receiving the daily subcutaneous injection of leuprolide acetate solutions when an injection was delayed by 7 to 12 days; testosterone levels remained within the castrate range for the majority of patients.
Studies M91-583 and M91-653 LUPRON DEPOT 22.5 mg for 3-Month Administration
LUPRON DEPOT 22.5 mg (3-Month) was found to be effective in suppressing serum testosterone and maintaining it at the castrate level.
Serum testosterone
Following the initial depot injection, the characteristic increase in mean testosterone over the pretreatment level occurred on Day 4, followed by a steady decline to the castrate range by Week 3. The median time to onset of castrate levels was 22 days. Testosterone suppression was sustained throughout each 12-week dosing interval. After falling into the castrate range, mean testosterone remained well within the castrate range throughout the 12-week interval.
As expected elevated pretreatment levels of alkaline phosphatase (AP) and prostatic specific antigen (PSA) reflected the presence of bony metastatic disease and the general prostatic cancer status respectively. Decreases and/or normalization (in AP and PSA) during treatment reflected the continuing presence of, and presumably the treatment related reduction in bony metastatic disease and/or improvement in the general prostatic cancer status.
Objective response
According to the tumour response rating of the patients, an 85% "no progression" rate (based on best objective response) was achieved during the 24-week treatment period. Complete response was achieved in 1% of the patients, 37% patients had a partial response and 47% patients showed a stable condition.
Eighty (85%) patients responded favourably to the treatment.
Of the 83% of the patients who completed the first 24 weeks of treatment, and continued with the long-term phase of the study, only 17% of the patients discontinued from the study prior to receiving the third injection. Four (4%) patients received only the first injection, 12 (13%) patients received only two injections and 78 (83%) patients received the third injection. Only six patients prematurely terminated the treatment at least in part due to an adverse event. Among those, adverse event was not the primary reason to stop the treatment in four patients. Only one patient discontinued the treatment due to intolerable hot flashes which was, according to the investigator, treatment related.
In summary, the leuprolide acetate depot injection releases leuprolide acetate at an apparently steady state; its efficacy in the treatment of advanced prostatic cancer does not differ from the efficacy of the daily subcutaneous injection.
Study M93-013 LUPRON DEPOT 30 mg for 4-Month Administration
In an open-label, non-comparative, multicenter clinical study using LUPRON DEPOT 30 mg (4-Month), 49 patients with stage D2 prostatic adenocarcinoma (with no prior treatment) were enrolled. The study design and patient demographics is shown in Table 17. The objectives were to determine whether a 30 mg depot formulation of leuprolide acetate injected once every 16 weeks would reduce and maintain serum testosterone levels at castrate levels (≤ 50 ng/dL), and to assess the safety of the formulation. The study was divided into an initial 32-week treatment phase and a long-term treatment phase. Serum testosterone levels were determined biweekly or weekly during the first 32 weeks of treatment. Once the patient completed the initial 32-week treatment period, treatment continued at the investigator’s discretion with serum testosterone levels being done every four months prior to the injection.
In the majority of patients, testosterone levels increased 50% or more above the baseline during the first week of treatment. Mean serum testosterone subsequently suppressed to castrate levels within 30 days of the first injection in 94% of patients and within 43 days in all 49 patients during the initial 32-week treatment period. The median dosing interval between injections was 112 days. One escape from suppression (two consecutive testosterone values > 50 ng/dL after castrate levels achieved) was noted at Week 16. In this patient, serum testosterone transiently increased to above the castrate range following the second depot injection (Week 16) but returned to the castrate level by Week 18. No adverse events were associated with this rise in serum testosterone. A second patient had a rise in testosterone at Week 17, then returned to the castrate level by Week 18 and remained there through Week 32. In the long-term treatment phase, two patients experienced testosterone elevations, both at Week 48. Testosterone for one patient returned to the castrate range at Week 52, and one patient discontinued the study at Week 48 due to disease progression.
Secondary efficacy endpoints evaluated in the study were the objective tumor response as assessed by clinical evaluations of tumor burden (complete response, partial response, objectively stable and progression) and elevations of changes in prostatic involvement and PSA. These evaluations were performed at Weeks 16 and 32 of the treatment phase. The long-term treatment phase monitored PSA at each visit (every 16 weeks). The objective tumor response analysis showed “no progression” (i.e. complete or partial response, or stable disease) in 86% (37/43) of patients at Week 16, and in 77% (37/48) of patients at Week 32. Local disease improved or remained stable in all patients evaluated at Week 16 and/or 32. For patients with elevated baseline PSA, 50% (23/46) had a normal PSA (< 4.0 ng/mL) at Week 16, and 51% (19/37) had a normal PSA at Week 32.
Using historical comparisons, the safety and efficacy of LUPRON DEPOT 30 mg (4-Month), appear similar to the other depot formulations.
Study L-PC07-169 LUPRON DEPOT 45 mg for 6-Month Administration
In an open-label, noncomparative, multicenter clinical study of leuprolide acetate 6-month 45 mg, 151 patients with prostate cancer (NCI Stage II, III, or IV) including patients who had recently failed definitive treatment, and patients with advanced prostate cancer were enrolled. The objectives were to determine whether a 45 mg depot formulation of leuprolide acetate injected once every 24 weeks would reduce and maintain serum testosterone levels at castrate levels (≤ 50 ng/dL), and to assess the safety of the formulation. The study drug was administered as two intramuscular injections of leuprolide acetate 45 mg at 24 week intervals, and patients were followed for a total of 48 weeks.
For the primary endpoint, 93.7% of patients had serum testosterone suppressed to values ≤ 50 ng/dL from Week 4 through Week 48 (two-sided 95% CI: 89.7%, 97.7%). One patient failed to achieve testosterone suppression by Week 4, and eight patients had escapes from suppression (any testosterone value greater than 50 ng/dL after castrate levels achieved). The majority of the testosterone escapes were transient and none of the eight patients with testosterone escapes had associated increases in PSA. The percentage of patients with testosterone ≤ 20 ng/dL was 78.7%
(118/150) at Week 4 and 94.1% (128/136) at Week 48 in the ITT population. Mean testosterone levels increased to 613 ng/dL from a baseline of 433 ng/dL during the first week of treatment. By Week 4, the mean testosterone concentration had decreased to 16.0 ng/dL (Figure 1).
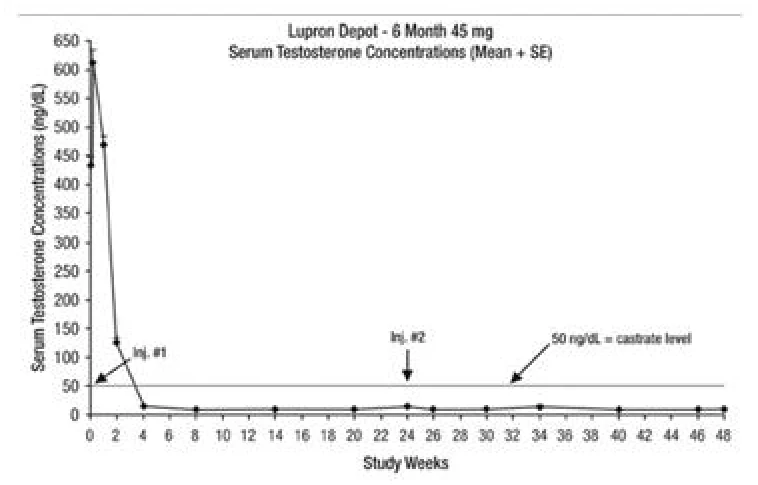
Figure 1. LUPRON DEPOT 45 mg for 6-Month Administration Serum Testosterone Concentrations (Mean + SE)
Endometriosis
LUPRON DEPOT 3.75 mg (1-Month)
The first two studies conducted were Phase III, randomized, double-blind, multi-centre studies of the effects of LUPRON DEPOT (leuprolide acetate for extended-release injectable suspension) 3.75 mg (1-Month) in endometriosis. Study M86-031 was placebo-controlled, while Study M86-039 used danazol as an active control. The studies were conducted at a total of 23 investigative sites, with 11 investigators participating in both studies. Study M86-031 had a planned sample size of 60 (30 LUPRON DEPOT, 30 placebo), and Study M86-039 had a planned sample size of 250 (125 LUPRON DEPOT, 125 danazol).
A total of 333 patients for the two studies were enrolled at 23 investigative centres.
Sixty-three patients entered the Study M86-031 and 270 patients entered Study M86-039.
The number of patients enrolled into each study and the number of evaluable (for efficacy) is summarized in Table 18.
Table 18. Number of Patients Enrolled in Two Phase III, Randomized, Double-Blind, Multicentre Studies Evaluating the Effects of LUPRON DEPOT 3.75 mg (1-Month) in Endometriosis (Studies M86-031 and M86-039)
| Study | Number of Investigators | Number of Patients Entered | Number of Evaluable Patients | ||||
|---|---|---|---|---|---|---|---|
| LUPRON DEPOT | Placebo | Danazol | LUPRON DEPOT | Placebo | Danazol | ||
M86-031 M86-039 | 12 22 | 32 134 | 31 -- | -- 136 | 28 128 | 24 -- | -- 125 |
| Total | 231 | 166 | 31 | 136 | 156 | 24 | 125 |
| |||||||
A total of 166 patients were exposed to LUPRON DEPOT in Studies M86-031 and M86-039. Of the 166 patients, 153 were treated for the full six-month study period and 13 prematurely terminated from the study and were treated for periods ranging from one to six months. The patients were treated with LUPRON DEPOT for a total of 79 accumulated patient-years experience in these two studies (assuming each injection is equivalent to four weeks treatment).
A summary of the trial design and patient demographics is shown in Table 19.
Table 19. Summary of Patient Demographics for Clinical Trials in Endometriosis
| Study # | Trial design | Dosage, route of administration and duration | Study subjects (n) | Mean age (Range) | Gender |
|---|---|---|---|---|---|
| M86-031 | Phase III, parallel randomized, double-blind, multicenter study | 3.75 mg LUPRON DEPOT vs. placebo Intramuscular 24 weeks | 63 | 30 (19 to 44) | Females only |
| M86-039 | Phase III, parallel randomized, double-blind, multicenter study | 3.75 mg LUPRON DEPOT plus danazol placebo vs. LUPRON DEPOT placebo plus 200 mg danazol b.i.d. Intramuscular 24 weeks | 270 | Not available | Females only |
| M92-878 | Phase III, 4-arm, parallel, randomized, double-blind, multicenter study | 3.75 mg LUPRON DEPOT alone vs. LUPRON DEPOT plus norethindrone acetate 5 mg 52 weeks | 106 | 28.6 (18 to 43) | Females only |
| Study # | Trial design | Dosage, route of administration and duration | Study subjects (n) | Mean age (Range) | Gender |
| M97-777 | Phase IV, open-label, single-arm, multicenter extension of Study III | LUPRON DEPOT plus norethindrone acetate 5 mg 52 weeks | 136 | 28.8 (17 to 41) | Females only |
| Definitions: b.i.d. = twice daily; n = number. | |||||
Two other clinical studies were conducted with LUPRON DEPOT 3.75 mg (1-Month) in patients with endometriosis. Study M92-878 was a double-blind, randomized, parallel-group, multi-center study, conducted at 26 investigative sites, with planned sample sizes of 200 (four groups of 50 patients; LUPRON DEPOT alone or in combination with estrogen and/or the progestin norethindrone acetate as add-back regimens). Study M97-777 was an open-label, single-arm, multi-center extension of Study M92-878, conducted at 24 investigative sites, with a planned sample size of 135. Both studies had a 52-week Treatment Period with either 24 months (Study M92-878) or 12 months (Study M97-777) of follow-up after the completion of treatment.
The primary efficacy objective of studies M92-878 and M97-777 was to compare the efficacy of continuous, combined administration of oral norethindrone acetate 5 mg and LUPRON DEPOT to the efficacy of administration of LUPRON DEPOT alone, in the management of endometriosis.
A total of 242 patients were enrolled in studies M92-878 and M97-777 to receive either LUPRON DEPOT alone (51 patients) or in combination with norethindrone acetate 5 mg (191 patients). The number of patients enrolled into each study and the number of evaluable (for efficacy) is summarized in Table 20.
Table 20. Number of Patients Enrolled in Studies M92-878 and M97-777
| Study | Number of Investigators | Number of Patients Randomized | Number of Patients Completing Treatment | ||
|---|---|---|---|---|---|
| LUPRON DEPOT 3.75 mg | LUPRON DEPOT 3.75 mg + norethindrone acetate 5 mg | LUPRON DEPOT 3.75 mg | LUPRON DEPOT 3.75 mg + norethindrone acetate 5 mg | ||
| M92-878 | 26 | 51 | 55 | 32 | 31 |
| M97-777 | 24 | -- | 136 | -- | 82 |
| Total | 441 | 51 | 191 | 32 | 113 |
| |||||
Of the 51 patients randomized to receive LUPRON DEPOT only, 32 completed the 52-week study period while 19 terminated prematurely. Of the 191 patients who received LUPRON DEPOT with norethindrone acetate, 113 completed the 52-week study period and 78 terminated prematurely.
LUPRON DEPOT 3.75 mg (1-Month)
The results of the studies were as follows:
Clinical Evaluation in Studies M86-031 and M86-039
At each study visit, an assessment was made of dysmenorrhea, non-menstrual pelvic pain, and dyspareunia (by patient interview). Symptoms were graded as absent, mild, moderate, or severe. Degree of analgesic use was utilized by the investigators to help assess pelvic pain. Pelvic tenderness, induration, and ovarian enlargement (by pelvic examination) were evaluated at every monthly visit for patients in the placebo-controlled pain study and every 12 weeks for patients in the active-controlled study. Pelvic tenderness and induration were also graded as absent, mild, moderate, or severe; ovarian size was assessed to be normal, two times normal, or greater than or equal to three times normal.
At each visit, a patient was considered improved if her evaluation at that visit had a less severe classification than did her baseline evaluation. A change to a more severe classification was counted as worse. Patients with a baseline classification of absent could not improve and patients with a baseline classification of severe could not get worse. Therefore, the percentages of patients with treatment changes of "worse", "no change", and "improved" do not add to 100%.
Forty-nine patients (28 LUPRON DEPOT, 21 placebo) in the placebo-controlled study and 251 patients (127 LUPRON DEPOT, 124 danazol) in the active-controlled study were evaluable for one or more of the clinical valuation variables.
Dysmenorrhea
LUPRON DEPOT patients showed reductions in dysmenorrhea compared to baseline at every visit in both studies. Table 21 summarizes changes in clinical evaluation of dysmenorrhea at the Final Visit against baseline for patients included in the efficacy analysis.
Table 21. Summary of Changes in Clinical Evaluation of Dysmenorrhea at the Final Visit Against Baseline for Patients Included in the Efficacy Analysis
| LUPRON DEPOT | Danazol | Placebo | |
|---|---|---|---|
| Worse | 1/121 = 1% | 3/11 = 3% | 7/12 = 58% |
| No change | 20/155 = 13% | 14/124 = 11% | 6/21 = 29% |
| Improved | 134/136 = 99% | 107/112 = 96% | 8/21 = 30% |
Pelvic pain
LUPRON DEPOT patients showed decreases in pelvic pain severity levels at each visit. Table 22 summarizes the changes in clinical evaluation of pelvic pain at the Final Visit compared to baseline for patients included in the efficacy analysis.
Table 22. Summary Changes in Clinical Evaluation of Pelvic Pain at the Final Visit Compared to Baseline for Patients Included in the Efficacy Analysis
| LUPRON DEPOT | Danazol | Placebo | |
|---|---|---|---|
| Worse | 13/145 = 9% | 5/116 = 4% | 2/13 = 15% |
| No change | 56/155 = 36% | 56/124 = 45% | 10/21 = 48% |
| Improved | 86/118 = 73% | 63/86 = 73% | 9/21 = 43% |
Dyspareunia
LUPRON DEPOT patients in both studies showed slight decreases or no change when compared to baseline at all visits. Table 23 summarizes the changes in clinical evaluation of dyspareunia at the Final Visit compared to baseline for patients included in the efficacy evaluation.
Table 23. Summary of the Changes in Clinical Evaluation of Dyspareunia at the Final Visit Compared to Baseline for Patients Included in the Efficacy Analysis
| LUPRON DEPOT | Danazol | Placebo | |
|---|---|---|---|
| Worse | 22/126 = 17% | 7/105 = 7% | 4/13 = 31% |
| No change | 65/139 = 47% | 62/110 = 56% | 6/13 = 46% |
| Improved | 42/72 = 58% | 41/58 = 71% | 3/10 = 30% |
Pelvic Tenderness
Decreases in severity levels of pelvic tenderness occurred at every visit for the combined LUPRON DEPOT group. Pelvic tenderness changes from baseline to the Final Visit for both studies are summarized in Table 24.
Table 24. Pelvic Tenderness Changes from Baseline to the Final Visit for the Placebo- and Active-Controlled Studies
| LUPRON DEPOT | Danazol | Placebo | |
|---|---|---|---|
| Worse | 8/150 = 5% | 6/120 = 5% | 3/20 = 15% |
| No change | 55/152 = 36% | 61/122 = 50% | 11/21 = 52% |
| Improved | 89/117 = 76% | 55/70 = 79% | 7/21 = 33% |
Induration
At baseline in each study, treatment groups were similar. In the placebo-controlled study, LUPRON DEPOT patients showed similar or better results (less induration) than the placebo group at all visits. At the Final Visit, induration was significantly less for the LUPRON DEPOT group (p=0.023). In active-controlled study, LUPRON DEPOT patients showed similar results compared to the danazol group at all visits. No significant differences were seen between groups.
Ovarian Enlargement
For both studies, ovarian enlargement had a relatively low prevalence rate at baseline. Ovarian enlargement for most LUPRON DEPOT patients and danazol patients either improved over time or did not change. Only two placebo patients had ovarian enlargement at baseline.
Menses
Menses were considered suppressed if no menstrual-like bleeding occurred for more than 60 days (day of first injection or first day of one episode of menstrual-like bleeding to the first day of the subsequent episode of menstrual-like bleeding or end-of-study).
In the placebo-controlled study menses were suppressed in all of the LUPRON DEPOT patients (100%) and one of the placebo patients (4%). Once suppressed, menses remained suppressed through the study for all except three LUPRON DEPOT patients.
In the active-controlled study menses were suppressed in 99% of the LUPRON DEPOT patients and 96% of the danazol patients. However, suppression did not occur in one LUPRON DEPOT and five danazol patients. Menses were completely suppressed from the initiation of treatment for 77% of the LUPRON DEPOT and 63% of the danazol patients. The number of episodes of menstrual-like bleeding before suppression is presented in Table 25.
Table 25. Number of Episodes of Menstrual-Like Bleeding Before Suppression in the Active-Controlled Study
| Number of Episodes | Number of Patients LUPRON DEPOT | Number of Patients Danazol |
|---|---|---|
| 0 | 98 | 79 |
| 1 | 29 | 26 |
| 2 | 0 | 10 |
| 3 | 0 | 4 |
Once suppressed, menses remained suppressed through the study for all except eight LUPRON DEPOT and 23 danazol patients.
Hormone Determinations
In each study, mean estradiol decreases were significantly greater for LUPRON DEPOT patients compared to each of the control groups (p < 0.05). Most estradiol values for LUPRON DEPOT patients were at or near the postmenopausal range (< 1.5 ng/dL). Progesterone decreased significantly within each treatment group in each study at every visit where hormonal determinations were made (p < 0.05); however, between group significance was seen only in the placebo-controlled study.
Analgesic Usage
Analgesic usage for each patient was surveyed at each visit to assist the investigator in the evaluation of pain. In the placebo-controlled pain study, 98% of the patients took analgesics for pain; in the active-controlled study, 78% of the patients took analgesics for pain. The most common pain medications used were mild analgesics or non-narcotic analgesics.
Adverse Events
All 333 patients enrolled in the two studies were included in the adverse event analysis.
Adverse events reported by 95% (n=158) of the 166 LUPRON DEPOT patients, by 93% (n=127) of the 136 danazol patients, and by 45% (n=14) of the 31 placebo patients. The most frequently reported adverse event in all treatment groups was vasodilatation (hot flashes) with 83% (n=138) of the LUPRON DEPOT patients, 54% (n=74) of the danazol patients, and 29% (n=9) of the placebo patients reporting it.
Eighty-seven percent of those reporting vasodilatation rated it mild or moderate with 32 LUPRON DEPOT, 9 danazol, and 1 placebo patient reporting it as severe. The mean onset of vasodilatation was 29 days after the initiation of treatment for the LUPRON DEPOT group and 35 days for the danazol group. Generally, vasodilatation continued intermittently throughout the study. The difference between treatment groups in the proportion of patients reporting it was statistically significant (p < 0.05) in each study.
Other than vasodilatation, the adverse events having the highest prevalence (>10%) among LUPRON DEPOT patients were headache (35%), vaginitis (27%), insomnia (17%), emotional lability (15%), nausea (13%), nervousness (12%), weight gain (11%), dizziness (11%), decreased libido (11%), and depression (11%). The severity of these events was predominantly mild or moderate.
The most prevalent events in the danazol group were vasodilatation (54%), weight gain (27%), headache (26%), acne (20%), vaginitis (19%), edema (18%), nervousness (16%), nausea (13%), depression (12%), and emotional lability (11%). In the placebo group, the most prevalent event was vasodilatation (29%). The only other adverse events to occur in more than 5% of the placebo patients were headache (10%) and insomnia (7%).
In the placebo-controlled study, the difference in prevalence between the treatment groups was significant for vasodilatation and headache. In the active-controlled study, the LUPRON DEPOT group had significantly higher prevalence of vasodilatation, pelvic pain, insomnia, and decreased libido than did the danazol patients. Danazol patients had significantly more edema and weight gain than did the LUPRON DEPOT patients.
Many of the adverse events occurring in more than 5% of the LUPRON DEPOT group had onset within the first two months of treatment. Forty-nine percent (n=262) of the 530 total initial occurrences of these events had onset within the first month of treatment and 72% within the first two months.
Most of the events occurring in at least 5% of the LUPRON DEPOT group are symptoms that occur frequently in the postmenopausal population and are generally considered to be related to the hypoestrogenic state. Other symptoms such as weight gain, acne, and hypertonia occurred with much greater frequency in the active-controlled study where LUPRON DEPOT was compared with danazol which is known to have androgenic effects.
Other symptoms, such as pain, have no apparent explanation. Most of the adverse events reported in the studies were considered by the investigator to be probably or possibly related to treatment.
Eight patients in the LUPRON DEPOT group terminated prematurely from the studies due to adverse events. Overall, 19 patients (8 LUPRON DEPOT, 10 danazol, and 1 placebo) prematurely terminated the studies due to adverse events.
The length of treatment received by these patients who terminated prematurely is summarized in Table 26.
Table 26. Treatment Length for Patients Who Prematurely Terminated in the Placebo- and Active-Controlled Studies
| Treatment (months) | LUPRON DEPOT | Danazol | Placebo |
|---|---|---|---|
| 1 | 1 | 5 | 0 |
| 2 | 3 | 1 | 1 |
| 3 | 0 | 2 | 0 |
| 4 | 3 | 0 | 0 |
| 5 | 0 | 1 | 0 |
| 6 | 1 | 1 | 0 |
| Total | 8 | 10 | 1 |
Bone Mineral Density
Bone density measurements were performed pre-study and at the end of the treatment period.
An analysis of percent changes in bone mineral density from baseline to the end of treatment for the combined LUPRON DEPOT patients from both studies shows that one hundred fifteen patients had a mean decrease of 4.2% in bone mineral density. This decrease was significant within the LUPRON DEPOT treatment group (p < 0.001) and is consistent with data published on the effect of other GnRH agonists on bone mineral density.
When LUPRON DEPOT was compared to danazol, moderate mean decreases were observed in the LUPRON DEPOT group, and slight to moderate mean increases were observed in the danazol group. Treatment with LUPRON DEPOT produces a hypoestrogenic environment which can result in increased bone turnover, and treatment with danazol can result in androgenic effects such as increased bone mass.
Clinical Evaluation in Studies M92-878 and M97-777
Clinical assessment of pain parameters (dysmenorrhea, pelvic pain, deep dyspareunia, pelvic tenderness, and pelvic induration) was evaluated on the four-point Biberoglu and Berhman scale completed by the study staff. Return to baseline pain levels during follow-up was also assessed using this scale. Improvement in pain was also evaluated via patient evaluations of dysmenorrhea, pelvic pain and deep dyspareunia using analog scales (0 = none; 10 = intolerable). Pain evaluations were collected at each visit during treatment and the first year of follow-up. Improvement in ovarian enlargement was assessed by comparing ovarian size determined at each visit during treatment and the first year of the Follow-Up period to baseline measurements. Estradiol level was assessed at each Treatment period visit beginning with Day 0 (baseline) and once at the first Follow-Up period visit after resumption of menses. Menses frequency and duration were collected on patient diaries. Suppression of estradiol (E2) and menses are used as efficacy markers.
Pain Parameters
Statistically significant mean decreases from baseline in all pain scores were seen in patients taking either LUPRON DEPOT alone or in combination with norethindrone acetate 5 mg (p < 0.001). The improvements were generally statistically significant by Week 4 and were maintained throughout the 52-week Treatment Period. Table 27 summarizes the prevalence in clinical pain variables at the Final Visits against baseline for patients included in the efficacy analysis.
Table 27. Prevalence of Clinical Pain Variables at Baseline and the Final Treatment Visit (Integrated Results from Study M92-878 and Study M97-777)
| Variable | Treatment Group | Baseline | Final Treatment Visit |
|---|---|---|---|
| n/N (%) | n/N (%) | ||
| Dysmenorrhea | LUPRON DEPOT | 51/51 (100) | 2/50 (4) |
| LUPRON DEPOT + norethindrone acetate | 190/191 (99) | 14/188 (7) | |
| Pelvic Pain | LUPRON DEPOT | 51/51 (100) | 33/50 (66) |
| LUPRON DEPOT + norethindrone acetate | 188/191 (98) | 115/188 (61) | |
| Deep Dyspareunia | LUPRON DEPOT | 35/42 (83) | 17/46 (37) |
| LUPRON DEPOT + norethindrone acetate | 129/145 (89) | 78/153 (51) | |
| Pelvic Tenderness | LUPRON DEPOT | 48/51 (94) | 17/50 (34) |
| LUPRON DEPOT + norethindrone acetate | 184/190 (97) | 70/187 (37) | |
| Pelvic Induration | LUPRON DEPOT | 26/51 (51) | 6/50 (12) |
| LUPRON DEPOT + norethindrone acetate | 127/190 (67) | 37/187 (20) |
Serum Estradiol Levels
Statistically significant within-group mean decreases from baseline were noted for both groups at all visits starting at Week 4 (p < 0.001) and were generally constant throughout the Treatment Period. For the majority of visits, the mean decrease for the LUPRON DEPOT plus norethindrone acetate group was statistically significantly greater than that of the LUPRON DEPOT-Only group (p < 0.01). The mean of serum estradiol levels averaged over the Treatment Period was within or near the menopausal range
(< 15 pg/mL) for both treatment groups: 8.40 pg/mL for Integrated LUPRON DEPOT plus norethindrone acetate and 15.59 pg/mL for LUPRON DEPOT-Only.
Menstrual Suppression
Menses were considered suppressed if no menstrual-like bleeding occurred for more than 60 days (day of first injection or first day of one episode of menstrual-like bleeding to the first day of the subsequent episode of menstrual-like bleeding or end-of-study). A summary of menstrual data for patients who were in the Treatment Period for at least 60 days is presented in Table 28.
Table 28. Menses Suppression During the Treatment Period
| Parameter | LUPRON DEPOT | LUPRON DEPOT + norethindrone acetate 5 mg |
|---|---|---|
| Suppression n/N (%) | 47/47 (100) | 174/177 (98)1 |
| Suppression Maintained to End of Treatment n/N (%) | 41/47 (87) | 132/174 (76)1 |
| ||
Efficacy
The placebo- and active-controlled studies have proven that LUPRON DEPOT is safe and effective in reducing not only the symptoms of endometriosis but also the extent of disease. It is at least as effective in this regard as is danazol and shows less of the androgenic adverse events which commonly accompany danazol treatments.
Based on results from studies M92-878 and M97-777, norethindrone acetate 5 mg daily is an effective add-back regimen combined with LUPRON DEPOT and does not have any relevant negative impact on endometriosis symptoms when compared with LUPRON DEPOT alone. Duration of initial treatment or retreatment should be limited to a period of six months.
Conclusion
LUPRON DEPOT, alone or in combination with norethindrone acetate 5 mg add-back, was effective in producing a transient, therapeutic menopausal state in patients with endometriosis facilitating statistically and medically significant improvement in disease signs and symptoms, and reduction in the extent of disease.
Adverse Events
Almost 100% of patients (190 of 191) in the Integrated LUPRON DEPOT plus norethindrone acetate group reported one or more adverse events during the Treatment Period. The most prevalent adverse events were vasodilatation (hot flashes) and headache, which were reported by 68% and 60% of patients, respectively.
When the Integrated LUPRON DEPOT plus norethindrone acetate group was compared with the LUPRON DEPOT-Only group from Study M92-878, statistically significant differences (p < 0.05) were noted between the groups in the prevalence of hot flashes and sweating. The prevalence of hot flashes was greater for the LUPRON DEPOT-Only group, while the prevalence of sweating was greater for the LUPRON DEPOT plus norethindrone acetate group. Potentially study drug-related adverse events for which there was a difference between the Integrated LUPRON DEPOT plus norethindrone acetate and LUPRON DEPOT-Only groups of 10% or more are summarized in Table 29.
Table 29. Adverse Events Attributed to Study Drug with ≥ 10% Difference Between Groups in Prevalence During the Treatment Period
| COSTART Term | Study M92-878 | Integrated Studies M92-878 and M97-777 | ||
|---|---|---|---|---|
LUPRON DEPOT N=51 | LUPRON DEPOT + norethindrone acetate 5 mg N=191 | |||
| N | % | N | % | |
| Hot Flashes/ Sweats | 50 | 98 | 136 | 711 |
| Headache/Migraine | 34 | 67 | 98 | 51 |
| Nausea/Vomiting | 15 | 29 | 37 | 19 |
| Edema | 0 | 0 | 21 | 112 |
| Insomnia/Sleep Disorders | 16 | 31 | 38 | 20 |
| Androgen-Like Effects | 2 | 4 | 29 | 152 |
| Vaginitis | 12 | 24 | 24 | 13 |
| ||||
There is minimal overall risk to treatment with the combination of LUPRON DEPOT and norethindrone acetate. The adverse event pattern characteristically seen in patients treated with LUPRON DEPOT or other GnRH agonists and norethindrone acetate largely reflects the menopausal symptom profile seen with GnRH agonist treatment. Although much reduced in incidence compared to the administration of LUPRON DEPOT alone, hot flashes remain the most prevalent of these events.
Bone Mineral Density
The mean changes from baseline in BMD during the Treatment Period experienced by the Integrated LUPRON DEPOT plus norethindrone acetate group were compared to those of the Study M92-878 LUPRON DEPOT-Only group. There was no statistically significant difference in mean BMD between the two groups at baseline. Statistically significant (p < 0.001) mean decreases in BMD from baseline were noted for the Integrated LUPRON DEPOT plus norethindrone acetate group at Week 52, and at all evaluations for the LUPRON DEPOT-Only group.
Comparisons of the mean percent changes from baseline between the two groups showed that the LUPRON DEPOT plus norethindrone acetate group experienced a statistically significantly (p < 0.001) smaller decrease in BMD than the LUPRON DEPOT-Only group at all evaluations. The results of the analyses of percent change in BMD from baseline to the Week 24 and Week 52 visits for the comparison of the Integrated LUPRON DEPOT plus norethindrone acetate (with calcium supplementation) and Study M92-878 LUPRON DEPOT-Only treatment groups are presented in Table 30.
Table 30. Mean Percent Change from Baseline in Lumbar Spine Bone Mineral Density
| Treatment Group | N | Week 24 | N | Week 52 |
|---|---|---|---|---|
| LUPRON DEPOT | 41 | -3.2%1 | 29 | -6.3%1 |
| LUPRON DEPOT + norethindrone acetate 5 mg daily | 157 | -0.2%2 | 116 | -1.0%1,2 |
| ||||
Overall, changes in safety parameters as a result of LUPRON DEPOT administration did not exceed expected limits. Adverse events experienced by patients in the four studies were primarily those symptoms characteristically experienced in the postmenopausal population and reflect the hormonal suppression which forms the basis of the therapeutic effect. In Studies M92-878 and M97-777, bone mineral density was minimally decreased from baseline after 12 months of treatment with LUPRON DEPOT when used in conjunction with norethindrone acetate and calcium supplementation. This decrease was considerably less than that seen with LUPRON DEPOT alone. The concurrent use of LUPRON DEPOT with norethindrone acetate 5 mg daily is effective in reducing loss of bone mineral density that occurs with LUPRON DEPOT alone.
Hot Flashes
The incidence of the menopausal symptoms of vasodilatation (hot flashes) and sweating was significantly less than that seen in patients who received treatment with leuprolide acetate alone.
Conclusion
The primary consequence of treatment with LUPRON DEPOT is the predictable, yet substantially reversible, bone turnover consequent to hypoestrogenism. After six months of treatment, the risks attending this decrease in bone mineral density are minimal in women who began treatment with normal bone density. Concomitant administration of norethindrone acetate 5 mg in combination with LUPRON DEPOT resulted in a decreased prevalence and severity of adverse events attributable to the chronic hypoestrogenic state induced by LUPRON DEPOT and greatly attenuated the loss of bone mineral density and the incidence of hot flashes.
LUPRON DEPOT 11.25 mg (3-Month)
In a pharmacokinetic/pharmacodynamic study of healthy female subjects (N=20), the onset of estradiol suppression was observed for individual subjects between Day 4 and Week 4 after dosing. By the third week following the injection, the mean estradiol concentration (8 pg/mL) reached the menopausal range. Throughout the remainder of the dosing period, mean serum estradiol levels ranged from the menopausal to the early follicular range.
Serum estradiol was suppressed to ≤ 20 pg/mL in all subjects within four weeks and remained suppressed (≤ 40 pg/mL) in 80% of subjects until the end of the 12-week dosing interval, at which time two of these subjects had a value between 40 and 50 pg/mL. Four additional subjects had at least two consecutive elevations of estradiol (range 43 to 240 pg/mL) levels during the 12-week dosing interval, but there was no indication of luteal function for any of the subjects during this period.
LUPRON DEPOT 11.25 mg (3-Month) induced amenorrhea in 85% (N=17) of subjects during the initial month and 100% during the second month following the injection. All subjects remained amenorrheic through the remainder of the 12-week dosing interval. Episodes of light bleeding and spotting were reported by a majority of subjects during the first month after the injection and in a few subjects at a later time-points. Menses resumed on average 12 weeks (range 2.9 to 20.4 weeks) following the end of the 12-week dosing interval.
LUPRON DEPOT 11.25 mg (3-Month) produced similar pharmacodynamic effects in terms of hormonal and menstrual suppression to those achieved with monthly injections of LUPRON DEPOT 3.75 mg (1-Month) during the controlled clinical trials for the management of endometriosis. Similar clinical outcome to that with LUPRON DEPOT 3.75 mg (1-Month) administered monthly is predicted with LUPRON DEPOT 11.25 mg (3-Month) administered every three months.
Uterine Fibroids
The safety and efficacy of leuprolide acetate were assessed in 309 adult women with uterine fibroids in one pivotal trial (Study M90-411) and additional 128 patients enrolled in three supportive trials (Studies M86-034, M86-049, and M86-062).
Study M90-411 was a Phase 3, stratified, randomized, double-blind, parallel-group, multicenter study, with a 12-week treatment period and a 6-month follow-up (Table 31). The study evaluated 2 doses of leuprolide acetate [7.5 mg (not approved for uterine fibroids indication), 3.75 mg] plus iron versus placebo plus iron for the preoperative treatment of anemia caused by uterine fibroids. Subjects were enrolled by stratifying hematologic status at baseline (hematocrit ≤ 28% and > 28%).
The supportive controlled trials had similar study designs, sample sizes, and treatment duration (24 weeks), and assessed the safety and efficacy of leuprolide acetate 3.75 mg versus placebo in women with uterine fibroids who were surgical candidates.
Table 31. Summary of Controlled Clinical Trials Supporting Safety and Efficacy in Patients with Uterine Fibroids
| Study # | Trial Design | Dosage, Route of Administration and Duration | Study Subjects by Arm Entered/Completed (n) | Mean Age (Range)1 |
|---|---|---|---|---|
| M90-411 | Phase 3, stratified, randomized, double-blind, parallel-group multicenter study | LA 7.5 mg3 + iron LA 3.75 mg + iron Placebo + iron | LA 7.5 mg3 + iron: 107/104 LA 3.75 mg + iron: 104/93 Placebo + iron: 98/84 | LA 7.5 mg3 + iron: 39.1 (26–52) yrs LA 3.75 mg + iron: 39.4 (23–50) yrs Placebo: 39.2 (23–51) yrs |
| LA and placebo given intramuscular at 4-week intervals, oral iron tablet given 2 or 3 times daily2 | ||||
| 12-week treatment period and a 6-month follow-up | ||||
| M86-034 | Phase 3, randomized, double-blind, parallel-group single-center study | LA 3.75 mg Placebo Intramuscular monthly 24 weeks | LA: 20/17 Placebo: 20/17 | LA: 41.1 (29–53) yrs Placebo: 39.3 (29–49) yrs |
| M86-049 | Phase 3, randomized, double-blind, parallel-group multicenter study | LA 3.75 mg Placebo Intramuscular monthly 24 weeks | LA: 22/20 Placebo: 22/10 | LA: 36.5 (25–47) yrs Placebo: 35.0 (28-45) yrs |
| M86-062 | Phase 3, randomized, double-blind, parallel-group multicenter study | LA 3.75 mg Placebo Intramuscular monthly 24 weeks | LA: 21/20 Placebo: 23/10 | LA: 34.5 (28–47) yrs Placebo: 33.0 (20–44) yrs |
Definition: LA = leuprolide acetate
| ||||
Description of Clinical Studies
In the controlled Phase 3 studies, 255 of 274 subjects (93.1%) randomized to leuprolide acetate completed the treatment period compared to 122 of 163 subjects (74.8%) randomized to placebo. A total of 248 leuprolide acetate subjects and 141 placebo subjects were included in efficacy evaluations.
The primary efficacy endpoint in Study M90-411 was the change in hematologic status from baseline to each monthly visit (Weeks 4, 8, and 12) and to the final visit. A response was defined as an increase of ≥ 2 g/dL in hemoglobin and/or ≥ 6% in hematocrit. Because subjects could meet these criteria and still be anemic, absolute cutoffs were also specified for a response. These were hemoglobin ≥ 12 g/dL and hematocrit ≥ 36%. Efficacy was additionally evaluated based on changes uterine and fibroid volume by pelvic ultrasound or MRI, uterine size (in gestational weeks) by pelvic examination, clinical signs and symptoms, estradiol levels, uterine bleeding, and quality of life.
The primary efficacy endpoints in the supportive studies were changes in uterine and fibroid volume. Uterine volume was measured by pelvic ultrasound in Study M86-034; uterine and fibroid volumes were measured by non-magnetic resonance (NMR) imaging in Study M86-049 or by ultrasound or NMR imaging in Study M86-062. Efficacy was additionally evaluated based on changes in gestational weeks, clinical signs and symptoms, hormone levels, hematocrit determinations, and the menstrual record.
Results from the pivotal Study M90-411 for both the efficacy subset of subjects as well as for all subjects demonstrated a statistically significantly higher percentage of subjects in each of the leuprolide acetate dose groups and therefore, a hematologic response in both hemoglobin and hematocrit at Final Visit relative to placebo (Table 32).
Table 32. Study M90-411: Percentage of Subjects with Hematologic Response at Final Visit
| n/N (%) of Subjects with an Increase of ≥ 2 g/dL in Hemoglobin and an Increase of ≥ 6% in Hematocrit | ||||||||
|---|---|---|---|---|---|---|---|---|
| Stratum B (hematocrit > 28%) | 24/48 (50) | 48/62 (77) P = 0.004 | 43/56 (77) P = 0.007 | |||||
| Combined Strata | 33/72 (46) | 72/97 (74) P < 0.001 | 62/84 (74) P < 0.001 | |||||
| All Subjects, N = 296 | ||||||||
| Stratum A (hematocrit ≤ 28%) | 12/35 (34) | 28/40 (70) P = 0.003 | 24/35 (69) P = 0.008 | |||||
| Stratum B (hematocrit > 28%) | 32/60 (53) | 51/66 (77) P = 0.005 | 45/60 (75) P = 0.022 | |||||
| Combined Strata | 44/95 (46) | 79/106 (75) P < 0.001 | 69/95 (73) P < 0.001 | |||||
Note: For the comparisons within each stratum, the P value is from a pairwise Fisher's exact test. For the comparisons for the combined strata, the P value is from a CMH statistic with strata as the blocking factor.
| ||||||||
| n/N (%) of Subjects with an Increase of ≥ 2 g/dL in Hemoglobin and an Increase of ≥ 6% in Hematocrit | ||||||||
| Evaluation | Placebo | LUPRON DEPOT 7.5 mg1 | LUPRON DEPOT 3.75 mg | |||||
| Evaluable Subjects, N = 253 | ||||||||
| Stratum A (hematocrit ≤ 28%) | 18/24 (75) | 33/35 (94) P = 0.053 | 26/28 (93) P = 0.123 | |||||
| Stratum B (hematocrit > 28%) | 20/48 (42) | 43/62 (69) P = 0.006 | 42/56 (75) P < 0.001 | |||||
| Combined Strata | 38/72 (53) | 76/97 (78) P < 0.001 | 68/84 (81) P < 0.001 | |||||
| All Subjects, N = 296 | ||||||||
| Stratum A (hematocrit ≤ 28%) | 27/35 (77) | 38/40 (95) P = 0.038 | 34/35 (97) P = 0.028 | |||||
| Stratum B (hematocrit > 28%) | 29/60 (48) | 46/66 (70) P = 0.018 | 44/60 (73) P = 0.009 | |||||
| Combined Strata | 56/95 (59) | 84/106 (79) P = 0.001 | 78/95 (82) P < 0.001 | |||||
| n/N (%) of Subjects with Hemoglobin ≥ 12 g/dL and Hematocrit ≥ 36% | ||||||||
| Evaluable Subjects, N = 253 | ||||||||
| Stratum A (hematocrit ≤ 28%) | 9/24 (38) | 24/35 (69) P = 0.032 | 19/28 (68) P = 0.050 | |||||
In Study M90-411, at least 25% reduction from baseline to Final Visit in uterine and fibroid volume was reported in 36/60 (60%) and 22/41 (54%) of the efficacy evaluable patients treated with leuprolide acetate 3.75 mg (combined strata). For the efficacy evaluable subjects treated with leuprolide acetate 3.75 mg (combined strata), median reduction in uterine volume was 39%, and median reductions in fibroid volume was 27%. For the placebo-treated subjects there was a slight increase in median uterine volume (10%) and fibroid volume (8%). The differences were statistically significant between the leuprolide acetate 3.75 mg and placebo groups for all analyses for the reduction in uterine volume except for Stratum A (subjects with hematocrit ≤ 28%) for evaluable subjects.
Reductions in uterine volume were reflected in improvements in clinical symptoms. A smaller percentage of subjects who received leuprolide acetate 3.75 mg compared with those who received placebo experienced bloating [38/76 (50.0%) and 37/56 (66.1%), respectively], pelvic pain [32/76 (42.1%) and 35/56 (62.5%)], pressure [28/76 (36.8%) and 25/56 (44.6%)], and menorrhagia [3/76 (3.9%) and 31/56 (55.4%)] at Final Visit (no statistical test was performed for these analyses). There was no consistent treatment effect with leuprolide acetate against symptoms of constipation, dyspareunia, menometrorrhagia, and urinary disorder.
In the supportive controlled studies (M86-034, M86-049, and M86-062), leuprolide acetate 3.75 mg was shown to be statistically significantly superior to placebo in reducing uterine and fibroid volume (Table 33).
In an analysis combining the 3 supportive controlled studies, there was a statistically significantly (P = 0.004) greater increase in hematocrit at Final Visit with leuprolide acetate 3.75 mg (1.6%) compared to placebo (-1.1%) in subjects who had menorrhagia prior to treatment. Ninety-five percent of these patients became amenorrheic.
Table 33. Studies M86-034, M86-049, and M86-062: Percent of Evaluable Subjects with ≥ 25% Reduction in Uterine or Fibroid Volume at Final Visit
| n/N (%) of Subjects with ≥ 25% Reduction in Uterine or Fibroid Volume | ||||||||
|---|---|---|---|---|---|---|---|---|
| Endpoint | Placebo | Leuprolide Acetate 3.75 mg | P value versus Placebo | |||||
| Uterine Volume | ||||||||
| M86-034 | 0/20 (0) | 13/17 (76) | < 0.001 | |||||
| M86-049 | 3/19 (16) | 16/21 (76) | < 0.001 | |||||
| M86-062 | 2/19 (11) | 14/18 (78) | < 0.001 | |||||
| Fibroid Volume | ||||||||
| M86-049 | 1/18 (6) | 15/19 (79) | < 0.001 | |||||
| M86-062 | 3/17 (18) | 9/15 (60) | 0.027 | |||||
Notes: P value is from Fisher's exact test. Fibroid volume was not measured in Study M86-034. | ||||||||
15 MICROBIOLOGY
No microbiological information is required for this drug product.
16 NON-CLINICAL TOXICOLOGY
Acute Toxicity
Mice and rats were given leuprolide acetate with different routes of administration: oral, intraperitoneal and subcutaneous (doses of 5 g/kg) and intramuscular (doses of 2 g/kg). No death occurred. The LD50 was concluded to be greater than 5 g/kg for intraperitoneal and subcutaneous routes and 2 g/kg for the intramuscular route.
Long-Term Toxicity
Rat
Leuprolide acetate was administered intramuscularly to three groups of male rats at doses from 10, 30 and 100 mg/kg/week (corresponding to 0.8, 2.4 and 8.0 mg/kg/week of leuprolide acetate injection) once a week for 13 weeks. Rats dosed at 100 mg/kg/week showed atrophy of testes; in addition white spots were noted at the injection sites. The atrophy of the testes was reported to be due to the hormonal action of leuprolide acetate injection; the "no-toxic-effect" dose was considered to be 100 mg/kg/week.
In another toxicity study, male rats were given leuprolide acetate subcutaneously once a week for three weeks, at doses of 30 mg/kg/week (corresponding to 2.4 mg/kg/week of leuprolide acetate injection). Atrophy of the testes, and a slight induration were noted. The "no-toxic effect" dose was considered to be 30 mg/kg/week.
In a third study, leuprolide acetate was given subcutaneously to groups of male and female rats, at doses of 0, 10, 30 and 100 mg/kg/week once a week for 13 weeks (corresponding to 0, 0.8, 2.4 and
8 mg/kg/week of leuprolide acetate injection). Atrophy of the testes was noted, with induration at injection site; in female rats, the vagina failed to open throughout the dosing period. Leuprolide acetate produced changes related to the expected pharmacologic effects. The "no-toxic-effect" dose was considered to be 100 mg/kg/week.
Dog
In two different studies, female and male beagle dogs were given leuprolide acetate subcutaneously for 13 weeks, once a week at doses of 10, 30, 100 mg/kg/week, corresponding to 0.8, 2.4 and 8 mg/kg/week leuprolide acetate injection. No death was reported. Signs and symptoms include inflammatory lesions at the injection sites, and atrophic changes of the primary and accessory sex glands. The injection site change, seen in both control and test groups, was induced by the microcapsule, not leuprolide, and was reversible.
Mutagenicity
In the Ames Test, using S. typhimurium, strains TA 98, TA 100, TA 1535 and TA 1537, and E. coli strain WP2hcr, leuprolide acetate was found not mutagenic at dosing ranging from 0.03 to 10 mg/plate, irrespective of treatment with mammalian metabolic activation system (S-9 mix).
Carcinogenicity
Two rodent carcinogenicity studies were conducted for two years with daily doses of 0.6, 1.5, and 4 mg/kg/day in the rat, and with 0.6, 6, and 60 mg/kg/day in the mouse.
In rats, a dose-related incidence of pituitary hyperplasia, hypertrophy and benign pituitary adenomas were noted at 12 month necropsy, while a statistically significant dose-related incidence of benign pituitary adenomas was observed in both male and female rats after 24 months when the drug was administered subcutaneously at high daily doses (0.6 to 4 mg/kg).
In mice, no drug-induced neoplastic changes or pituitary abnormalities were observed at doses as high as 60 mg/kg for two years.
Patients have been treated with leuprolide for up to three years with doses as high as 10 mg/day, and for two years with doses as high as 20 mg/day. Clinical signs of pituitary abnormalities have not been observed in any of these patients.
Reproductive and Developmental Toxicology
Fertility and reproductive performance studies cannot be conducted with leuprolide, because the compound affects the pituitary-gonadal axis and influences endocrine reproductive organs. As a result, there would be a decrease in fertility and reproduction.
Clinical and pharmacologic studies in adult females with leuprolide acetate and similar analogs have shown full reversibility of fertility suppression when the drug is discontinued after continuous administration for periods of up to 24 weeks. There are no data in humans relating to male fertility following treatment with leuprolide acetate.
Although no clinical studies have been completed in children to assess the full reversibility of fertility suppression, animal studies (prepubertal and adult rats and monkeys) with leuprolide acetate and other GnRH analogs have shown functional recovery. However, following a study with leuprolide acetate, immature male rats demonstrated tubular degeneration in the testes even after a recovery period. In spite of the failure to recover histologically, the treated males proved to be as fertile as the controls. Also, no histologic changes were observed in the female rats following the same protocol. In both sexes, the offspring of the treated animals appeared normal. The effect of the treatment of the parents on the reproductive performance of the F1 generation was not tested. The clinical significance of these findings is unknown.
Teratology
Leuprolide administered to pregnant rats at dosages of 0, 1, 3 and 10 mcg/kg/day from gestational Day 6 to gestational Day 15 (major period of organogenesis) was not teratogenic. At 10 mcg/kg/day, leuprolide increased the incidence of resorptions; surviving fetuses showed no abnormalities. The "no-toxic-effect" dosage was 3 mcg/kg/day.
Leuprolide increased the incidence of embryonic resorptions in pregnant rabbits when dosed with 0, 0.1, 0.3 or 1.0 mcg/kg/day during the period of major organogenesis, i.e., Gestational Day 6 through Gestational Day 18. Surviving fetuses showed no abnormalities (see 2 CONTRAINDICATIONS).
Special Toxicology Studies
Rabbit
In a preliminary local irritation study, male rabbits were given single subcutaneous injections (1 mL/animal) of a 15% suspension of leuprolide acetate into the abdominal tissue.
Deposition of the test drug at site of injection was noted at 2 and 14 days with slight hemorrhage and capillary dilatation at 50 days after the injection. Leuprolide acetate was reported not to produce significant subcutaneous irritation in rabbits in this study.
In the second irritation study, male rabbits were injected once or four successive times with leuprolide acetate (15% suspension) by intramuscular administration. Results were compared with placebo-microcapsule or 0.75% acetic acid solution as the positive control. Deposition at injection sites, and slight irritation changes (hemorrhage, edema, inflammation) were noted. Leuprolide acetate produced the same effects with the same degree as the placebo-microcapsule, but these were less than those of the positive control (0.75% acetic acid), and their severity were not potentiated by four repeated injections.
In the third irritation study, rabbits were administered with intramuscular and subcutaneous injections of leuprolide acetate (3-Month) at doses of 11.25 mg/mL for intramuscular injection into the left vastus lateralis muscle and 5.64 mg/mL for subcutaneous injection into the abdominal region. Mild irritative changes such as mild hemorrhage and muscle fiber degeneration were noted two days after the injection. Granulation tissue composed of macrophages and multinucleated giant cells was observed, with a decrease in the size noted 13 weeks after the injection. Therefore, these changes were characterized mainly by foreign body reactions caused by the persistence of the microcapsule formulation.
In the fourth irritation study, male rabbits were administered with intramuscular injections of leuprolide acetate (6-Month) at a dose of 25 mg/mL into the dorsal sacrospinalis muscle. Slight to moderate irritative changes such as hemorrhage, muscle fiber necrosis, inflammatory cell infiltration, and foreign body response were noted two days after the injection. Mononuclear and multinucleated giant cell infiltration was observed at the injection sites, with an increase in severity by Week 13 and a decrease to slight by Week 34. Moderate fibrosis was noted at Week 13 and a decrease to slight by Week 34. These changes were characterized by foreign body reactions.
Guinea Pig
Two studies were performed to evaluate the potential of leuprolide acetate to produce either systemic anaphylaxis or delayed hypersensitivity reactions in guinea pigs.
Preliminary antigenicity study. Leuprolide acetate was given to guinea pigs at a dose of 123 mg/kg every two weeks by intramuscular route four times, and once by subcutaneous route two weeks after the last intramuscular dose. Results were compared to controls treated with placebo-microcapsule 122 mg/kg intraperitoneally, or with ovalbumin 5 mg/animal intravenously. No systemic anaphylactic reactions were observed with animals treated with leuprolide acetate and placebo-microcapsule, but some induced equivocal weak antibody production was noted.
In a second study, the sensitization potential of leuprolide acetate at doses of 50 mg/animal/dosing by intramuscular (systemic anaphylaxis) or at doses of approximately 7.2 mg/animal/dosing (0.05 mL of a 144.23 mg/mL of suspension) intradermal (delayed hypersensitivity), were compared to those seen with gelatin, egg albumin or captan. No signs of anaphylactic reactions nor delayed hypersensitivity were observed for leuprolide acetate, while signs of anaphylactic reactions (such as nose scratching, sneezing, dyspnea or local irritation) were noted with other compounds.