


Product Monograph - Pegetron (Merck Canada, 200 mg / 50 mcg, ..., 200 mg / 120 mcg)
SUMMARY PRODUCT INFORMATION
| Route of Administration | Dosage Form / Strength | Clinically Relevant Non-medicinal Ingredients |
ribavirin: oral | Capsules / 200 mg | Lactose monohydrate For a complete listing see Dosage Forms, Composition and Packaging section. |
peginterferon alfa-2b: subcutaneous |
| None For a complete listing see Dosage Forms, Composition and Packaging section. |
DESCRIPTION
PEGETRON® product is a combination of ribavirin and peginterferon alfa-2b, specifically PEGETRON® (ribavirin) Capsules and PEGETRON® (peginterferon alfa-2b) Powder for Solution.
PEGETRON® (ribavirin) Capsules: Ribavirin is a synthetic nucleoside analog, which has shown in vitro activity against some, but not all, RNA and DNA viruses.
PEGETRON® (peginterferon alfa-2b) Powder for Solution: Peginterferon alfa-2b is a covalent conjugate of recombinant interferon alfa-2b with monomethoxy polyethylene glycol (PEG, with an average molecular weight of 12,000 daltons). The average molecular weight of the conjugated molecule is approximately 31,000 daltons.
INDICATIONS AND CLINICAL USE
PEGETRON® (ribavirin plus peginterferon alfa-2b) is indicated for:
- Treatment of adult patients (≥ 18 years of age) with chronic hepatitis C who have compensated liver disease and are positive for HCV-RNA, including patients who have not received previous treatment or who failed prior treatment with interferon alpha (pegylated or non-pegylated) and ribavirin combination therapy.
Retreatment should be considered in the context of each patient’s characteristics and assessment of individual benefit/risk (see CLINICAL TRIALS section for details).
Patients with the following characteristics are more likely to benefit from retreatment after failing a course of combination therapy: previous relapse, previously treated with
- interferon therapy (non-pegylated), lower fibrosis score, lower baseline viral load, or infection with HCV genotype 2 or 3.
- Patients with the following characteristics are less likely to benefit from retreatment after failing a course of combination therapy: previous non-response, previously treated with pegylated interferon therapy, significant bridging fibrosis or cirrhosis, or infection with HCV genotype 1.
CONTRAINDICATIONS
- PEGETRON® is contraindicated in patients with a hypersensitivity to any interferons and/or ribavirin or any component of the injection and/or capsule. For a complete listing, see the Dosage Forms, Composition and Packaging section of the product monograph.
- PEGETRON® must not be used by pregnant women or by men whose female partners are pregnant. Extreme care must be taken to avoid pregnancy in female patients and in female partners of male patients taking PEGETRON® therapy. PEGETRON® therapy must not be initiated until a report of a negative pregnancy test has been obtained immediately prior to initiation of therapy. Women of childbearing potential and their male partners must not receive PEGETRON® therapy unless they are using effective contraception (two reliable forms, one for each partner) during treatment with PEGETRON® and for the 6-month post-therapy period (i.e., 15 half-lives for ribavirin clearance from the body). Significant teratogenic and/or embryocidal effects have been demonstrated for ribavirin in all animal species in which adequate studies have been conducted. These effects occurred at doses as low as one twentieth of the recommended human dose of PEGETRON® (ribavirin) Capsules (see WARNINGS AND PRECAUTIONS section).
- Patients with autoimmune hepatitis or a history of autoimmune disease must not be treated with PEGETRON® therapy.
- PEGETRON® is contraindicated in patients who have pre-existing severe psychiatric condition or a history of severe psychiatric disorder.
- PEGETRON® is contraindicated in patients who have pre-existing thyroid abnormalities for which thyroid function cannot be maintained in the normal range by medication.
- Patients with severe renal dysfunction (creatinine clearance < 50 mL/min) must not be treated with PEGETRON®.
- Patients with decompensated liver disease should not be treated with PEGETRON®.
- PEGETRON® is contraindicated in patients who have epilepsy.
WARNINGS AND PRECAUTIONS
Serious Warnings and Precautions
Alpha interferons, including PEGETRON®, cause or aggravate fatal or life-threatening neuropsychiatric, autoimmune, ischemic and infectious disorders. Patients should be monitored closely with periodic clinical and laboratory evaluations. Patients with persistently severe or worsening signs or symptoms of these conditions should be withdrawn from therapy. In many cases, but not all cases, these disorders resolve after stopping interferon therapy.
Life-threatening or fatal psychiatric effects, particularly severe depression, suicidal behavior (suicidal or homicidal ideation, attempted suicide and suicide), psychosis including hallucinations, and aggressive behavior, sometimes directed towards others, have occurred in patients with and without previous psychiatric disorders during ribavirin plus peginterferon alfa-2b or ribavirin plus interferon alfa-2b treatment and follow-up (see ADVERSE REACTIONS section). Other Central Nervous System (CNS) effects including confusion and alterations of mental status have been observed with alpha interferons, including peginterferon alfa-2b.
PEGETRON® therapy should be used with extreme caution in patients with a history of pre-existing psychiatric disorders who report a history of severe depression. If patients develop psychiatric or CNS problems, including clinical depression, it is recommended that the patients be carefully monitored during treatment and in the 6 month follow-up period, due to the potential seriousness of these undesirable effects. If such symptoms appear, the potential seriousness of these undesirable effects must be borne in mind by the prescribing physician. If symptoms persist or worsen, discontinue PEGETRON® therapy.
General
PEGETRON® therapy should not be used in patients with severe, debilitating medical conditions.
Based on results of clinical trials, the use of PEGETRON® (ribavirin) Capsules as monotherapy is not effective and PEGETRON® (ribavirin) Capsules must not be used alone. The safety and efficacy of ribavirin has only been established in combination with peginterferon alfa-2b (PEGETRON®).
PEGETRON® may cause moderate to severe adverse experiences requiring dose reduction or temporary interruption of PEGETRON® (peginterferon alfa-2b) Powder for Solution or PEGETRON® (ribavirin) Capsules therapy, or temporary cessation of both drugs. Generally, medical management of these adverse experiences is accomplished with these modifications. Occasionally, discontinuation from further therapy is required. More stringent dose-modification guidelines are recommended for cardiac patients (see DOSAGE AND ADMINISTRATION section).
Carcinogenesis and Mutagenesis
Conventional carcinogenicity studies in rodents with low exposures compared to human exposure under therapeutic conditions (factor 0.1 in rats and 1 in mice) did not reveal tumorigenicity of ribavirin. In addition, in a 26 week carcinogenicity study using the heterozygous p53 (+/-) mouse model, ribavirin did not produce tumors at the maximally tolerated dose of 300 mg/kg (plasma exposure factor approximately 2.5 compared to human exposure). Ribavirin was non-carcinogenic when administered for 2 years to rats at doses up to 40 mg/kg (estimated human equivalent of 5.71 mg/kg based on body surface area adjustment for a 60 kg adult). While these studies do not suggest a carcinogenic potential of PEGETRON® (ribavirin) Capsules in humans, this dose was less than the maximum tolerated dose, and therefore the 2-year study was not adequate to fully characterize the carcinogenic potential of ribavirin. Ribavirin should be considered a potential carcinogen.
Ribavirin is genotoxic and mutagenic in some in vivo and in vitro genotoxicity assays. Studies indicated that ribavirin was not oncogenic in mice at oral gavage doses up to 75 mg/kg/day, or in rats at oral gavage doses up to 40 mg/kg/day (see TOXICOLOGY section).
See also TOXICOLOGY section for animal data.
Cardiovascular
Chest pain, hypertension, cardiac arrhythmia, cardiac ischemia, and myocardial infarction have been reported in patients with and without a history of cardiac disorder or abnormality in association with the use of alpha interferon therapies including peginterferon alfa-2b (see ADVERSE REACTIONS section). PEGETRON® should not be administered to patients with a history of severe pre-existing cardiac disease including unstable or uncontrolled cardiac disease in the previous 6 months. As with other alpha interferons, patients with a history of congestive heart failure, myocardial infarction and/or previous or current arrhythmic disorders receiving PEGETRON® therapy require close monitoring. It is recommended that patients who have pre-existing cardiac abnormalities have electrocardiograms taken prior to and during the course of treatment. Cardiac arrhythmias (primarily supraventricular) usually respond to conventional therapy but may require discontinuation of PEGETRON® therapy. Cardiomyopathy, that may be reversible upon discontinuation of alpha interferon therapy, has been reported rarely in patients without prior evidence of cardiac disease.
A case of deep vein thrombosis has been reported from a clinical trial of retreatment of patients who failed previous treatment with interferon and ribavirin combination therapy.
Hydration: Adequate hydration must be maintained in patients undergoing therapy with PEGETRON® since hypotension related to fluid depletion has been seen in some patients treated with alpha interferons, including peginterferon alfa-2b. Fluid replacement may be necessary.
Cerebrovascular Disorders
Ischemic and hemorrhagic cerebrovascular events have been observed in patients treated with interferon alpha-based therapies, including peginterferon alfa-2b. Events occurred in patients with few or no reported risk factors for stroke, including patients less than 45 years of age. Because these are spontaneous reports, estimates of frequency cannot be made and a causal relationship between interferon alpha-based therapies and these events is difficult to establish.
Dental and Periodontal Disorders
Dental and periodontal disorders have been reported in patients receiving ribavirin and peginterferon combination therapy. In addition, dry mouth could have a damaging effect on teeth and mucous membranes of the mouth during long-term treatment with the combination of ribavirin and peginterferon alfa-2b. Patients should brush their teeth thoroughly twice daily and have regular dental examinations. In addition some patients may experience vomiting. If this reaction occurs, they should be advised to rinse out their mouth thoroughly afterwards.
Ear/Nose/Throat
Hearing disorder and hearing loss have been reported with the use of alpha interferons, including peginterferon alfa-2b therapy.
Endocrine and Metabolism
Diabetes Mellitus and Hyperglycemia: As with other alpha interferons, diabetes mellitus and hyperglycemia have been observed in patients treated with peginterferon alfa-2b therapy. Symptomatic patients should have their blood glucose measured and followed up accordingly. Patients with diabetes mellitus may require adjustment of their anti-diabetic regimen.
Thyroid Changes: Infrequently, patients treated for chronic hepatitis C with alpha interferons, including peginterferon alfa-2b, have developed thyroid abnormalities, either hypothyroidism or hyperthyroidism. After discontinuation of therapy, thyroid dysfunction may or may not be reversed. Determine thyroid-stimulating hormone (TSH) levels if, during the course of therapy, a patient develops symptoms consistent with possible thyroid dysfunction. In the presence of thyroid dysfunction, PEGETRON® treatment may be initiated or continued only if TSH levels can be maintained in the normal range by medication.
Hypertriglyceridemia: Hypertriglyceridemia and aggravation of hypertriglyceridemia, sometimes severe, have been observed with peginterferon alfa-2b therapy. Monitoring of lipid levels is, therefore, recommended.
Gastrointestinal
Colitis: As seen with other alpha interferons, ulcerative and ischemic colitis, sometimes serious, have been observed within 12 weeks of starting peginterferon alfa-2b therapy. PEGETRON® should be discontinued immediately if symptoms of colitis develop (typical manifestations include abdominal pain, bloody diarrhea and fever). The colitis usually resolves within 1 to 3 weeks of discontinuation of alpha interferon.
Hematologic
Anemia: Hemolytic anemia (hemoglobin levels to < 10 g/dL) was observed in up to 28 % of patients treated with ribavirin in combination with peginterferon alfa-2b in clinical trials. Anemia occurred within 1 - 4 weeks of initiation of PEGETRON® (ribavirin) Capsules therapy. Because of this initial acute drop in hemoglobin, it is advised that complete blood counts (CBC) should be obtained pretreatment and at Week 2 and Week 4 of therapy or more frequently if clinically indicated. Patients should then be followed as clinically appropriate.
Although ribavirin has no direct cardiovascular effects, anemia associated with ribavirin may result in deterioration of cardiac function and/or exacerbation of the symptoms of coronary disease. Patients should be assessed before initiation of therapy and should be appropriately monitored during therapy. If there is any deterioration of cardiovascular status, therapy should be suspended or discontinued (see DOSAGE AND ADMINISTRATION section). Because cardiac disease may be worsened by drug-induced anemia, patients with a history of significant or unstable cardiac disease should not be treated with PEGETRON®.
PEGETRON® therapy should not be used in patients with hemoglobinopathies (e.g., thalassemia, sickle-cell anemia).
Hepatic/Biliary/Pancreas
Hepatic Failure: Peginterferon alfa-2b increases the risk of hepatic decompensation and death in patients with cirrhosis. Monitor hepatic function with serum bilirubin, ALT (alanine transaminase), AST (aspartate aminotransferase), alkaline phosphatase and LDH (lactate dehydrogenase) at 2, 8, and 12 weeks following initiation of peginterferon alfa-2b, then every 6 months while receiving peginterferon alfa-2b. Permanently discontinue peginterferon alfa-2b for evidence of severe (Grade 3) hepatic injury or hepatic decompensation (Child-Pugh score >6 [class B and C]).
Hepatic Function: Any patient developing liver function abnormalities or hepatopathy during treatment should be monitored closely. As with treatment with any interferon, discontinue treatment with PEGETRON® in patients who develop prolongation of coagulation markers or other markers of hepatic function, which might indicate liver decompensation (see DOSAGE AND ADMINISTRATION section). The safety and efficacy of peginterferon alfa-2b have not been evaluated in patients with severe hepatic dysfunction. Therefore, PEGETRON® must not be used for these patients. PEGETRON® therapy should be discontinued for any patient developing signs and symptoms of liver failure. Patients should be tested for the presence of hepatitis C virus (HCV) antibodies. Other causes of chronic hepatitis including autoimmune hepatitis should be excluded.
There is limited data available for the use of PEGETRON® in patients with mild and moderate hepatic dysfunction. In a single dose, parallel group, Phase I study in a limited number of patients (n = 5 to 7 subjects per group) with various degrees of hepatic dysfunction (mild, moderate and severe) Cmax increased with increasing severity of liver dysfunction (P < 0.05). While there were no statistically significant differences detected with AUCt, the limited size of the study population does not permit any generalizations to be made.
Pancreatitis: Pancreatitis, sometimes life-threatening, has occurred in patients treated with alpha interferons, including peginterferon alfa-2b. PEGETRON® therapy should be suspended if symptoms or signs of pancreatitis are observed. PEGETRON® should be discontinued in patients diagnosed with pancreatitis.
Immune
Acute Hypersensitivity: Acute hypersensitivity reactions, (e.g., angioedema, bronchoconstriction and anaphylaxis), have been observed rarely during alpha interferon therapy. If such a reaction develops during treatment with PEGETRON®, discontinue treatment and institute appropriate medical therapy immediately. As with other alpha interferons, urticaria has been observed rarely during peginterferon alfa-2b therapy. Transient rashes do not necessitate interruption of treatment.
Bone Marrow Toxicity: Alpha interferons, including peginterferon alfa-2b, may suppress bone marrow function which may result in severe cytopenias. As with other alpha interferons, peginterferon alfa-2b may be very rarely associated with aplastic anemia. PEGETRON® dosing should be reduced or discontinued in patients developing decreases in neutrophil or platelet counts (see DOSAGE AND ADMINISTRATION - Dose modification section).
Immunological Effects: A number of immune-mediated dermatological reactions associated with the use of alpha interferons have been reported ranging from erythema multiforme to more severe but very rare occurrences of Stevens Johnson Syndrome and toxic epidermal necrolysis.
Autoimmune Disease: As with other alpha interferons, the development of autoantibodies has been reported during treatment with peginterferon alfa-2b. Clinical manifestations of autoimmune disease during interferon therapy may occur more frequently in patients predisposed to the development of autoimmune disorders.
Fever: While fever may be associated with the “flu-like” syndrome reported commonly during interferon therapy, other causes of persistent fever must be ruled out.
Neurologic
More significant obtundation and coma, including cases of encephalopathy, have been observed in some patients, usually elderly, treated at higher doses. While these effects are generally reversible upon discontinuation of therapy, in a few patients full resolution took up to three weeks. Very rarely, seizures have occurred with high doses of peginterferon alfa-2b.
Effects on Ability to Drive and Use Machines: Patients who develop fatigue, somnolence or confusion during treatment with PEGETRON® therapy are cautioned to avoid driving or operating machinery.
Ophthalmologic
Ocular Changes: As with other alpha interferons, ophthalmologic disorders, including retinopathies (including macular edema), retinal hemorrhages, retinal artery or vein obstruction, serous retinal detachment, cotton wool spots, loss of visual acuity or visual field, optic neuritis, and papilledema have been reported in rare instances after treatment with peginterferon alfa-2b (see ADVERSE REACTIONS section). These events have been reported after treatment for several months, but also have been reported after shorter treatment periods. All patients should have a baseline eye examination. Any patient complaining of ocular symptoms, including loss of visual acuity or visual field must have a prompt and complete eye examination. Because these ocular events may occur in conjunction with other disease states, periodic ocular examinations during PEGETRON® therapy are recommended in patients with disorders that may be associated with retinopathy, such as diabetes mellitus or hypertension. Discontinuation of PEGETRON® therapy should be considered in patients who develop new or worsening ophthalmological disorders.
Psychiatric
Patients with Substance Use/Abuse: HCV infected patients having a co-occurring substance use disorder (alcohol, cannabis, etc.) are at an increased risk of developing psychiatric disorders or exacerbation of already existing psychiatric disorders when treated with alpha interferon. If treatment with alpha interferon is judged necessary in these patients, the presence of psychiatric co-morbidities and the potential for other substance use should be carefully assessed and adequately managed before initiating therapy. If necessary, an inter-disciplinary approach including a mental health care provider or addiction specialist should be considered to evaluate, treat and follow the patient. Patients should be closely monitored during therapy and even after treatment discontinuation. Early intervention for re-emergence or development of psychiatric disorders and substance use is recommended.
Renal
Renal Function: It is recommended that renal function be evaluated in all patients prior to initiation of PEGETRON® therapy and that patients be monitored closely during treatment (see DOSAGE AND ADMINISTRATION section). Increases in serum creatinine levels have been observed in patients with renal insufficiency treated with interferons, including PEGETRON®. Patients with impairment of renal function should be closely monitored for signs and symptoms of toxicity, including increases in serum creatinine, and, should have their weekly dose of peginterferon alfa-2b reduced if medically appropriate (see DOSAGE AND ADMINISTRATION section). Patients with impaired renal function and/or those over the age of 50 should be more carefully monitored with respect to the development of anemia. Patients with severe renal dysfunction (creatinine clearance < 50 mL/min) must not be treated with PEGETRON®, as the clearance of peginterferon alfa-2b is reduced in patients with significant renal impairment (see ACTIONS AND CLINICAL PHARMACOLOGY section and CONTRAINDICATIONS section). If serum creatinine rises to > 2 mg/dL, PEGETRON® must be discontinued.
The pharmacokinetics of ribavirin were assessed, in a limited number of subjects (n = 6 per group), after administration of a single oral dose (400 mg) of ribavirin to subjects with varying degrees of renal function. Both Cmax and AUCt of ribavirin appeared to increase with increasing severity of renal dysfunction. Due to the limited size of the study groups, no dosing recommendations can be made and, therefore, the use of PEGETRON® in the presence of moderate to severe renal dysfunction cannot be recommended.
Respiratory
Pulmonary Changes: As with other alpha interferons, pulmonary infiltrates, pneumonitis, pulmonary hypertension, and pneumonia, occasionally resulting in fatality, have been observed rarely in peginterferon alfa-2b treated patients. Any patient developing fever, cough, dyspnea or other respiratory symptoms must have a chest X-ray taken. If the chest X-ray shows pulmonary infiltrates or there is evidence of pulmonary function impairment, the patient is to be monitored closely. If appropriate, discontinue PEGETRON® therapy. Prompt discontinuation of therapy and treatment with corticosteroids appear to be associated with resolution of pulmonary adverse events (AEs). These symptoms have been reported more frequently when Shosaikoto (also known as Xiao-Chai-Hu-Tang), a Chinese herbal medication, has been administered concomitantly with alpha interferons. PEGETRON® should not be administered to patients with chronic obstructive pulmonary disease (COPD).
Sexual Function/Reproduction
Effects on Fertility: No reproductive toxicology studies have been performed using peginterferon alfa-2b in combination with ribavirin. However, evidence provided below for interferon and ribavirin when administered alone indicates that both agents have adverse effects on reproduction. It should be assumed that the effects produced by either agent alone will also be caused by the combination of the two agents.
Interferons, including peginterferon alfa-2b, may impair fertility. In studies of interferon administration in non-human primates, menstrual cycle abnormalities have been observed. Decreases in serum estradiol and progesterone concentrations have been reported in women treated with human leukocyte interferon. The effects of interferon on male fertility have not been studied. Therefore, a possible effect on male fertility should be considered. The genotoxicity of peginterferon alfa-2b was evaluated in bacterial (Ames) and mammalian cell clastogenicity (HPBL) assays, and was negative in both assays.
PEGETRON® therapy should be used with caution in fertile men. In studies in mice to evaluate the time course and reversibility of ribavirin-induced testicular degeneration at doses of 15 to 150 mg/kg/day (estimated human equivalent of 1.25 - 12.5 mg/kg/day, based on body surface area adjustment for a 60 kg adult; 0.2 - 0.8 times the maximum human 24-hour dose of ribavirin) administered for 3 or 6 months, abnormalities in sperm occurred. Upon cessation of treatment, essentially total recovery from ribavirin-induced testicular toxicity was apparent within one or two spermatogenesis cycles.
Skin
Psoriatic Disease and Sarcoidosis: Use of alpha interferons, including peginterferon alfa-2b, has been associated with exacerbating pre-existing psoriatic disease and sarcoidosis. Use of PEGETRON® in patients with psoriasis or sarcoidosis is recommended only if the potential benefit justifies the potential risk.
Special Populations
Pregnant Women: (see CONTRAINDICATIONS section): PEGETRON® must not be used during pregnancy. Interferon alfa-2b has been shown to have abortifacient effects in Macaca mulatta (rhesus monkeys) at 15 and 30 million IU/kg (estimated human equivalent of 5 and 10 million IU/kg, based on body surface area adjustment for a 60 kg adult). This same effect is expected with peginterferon alfa-2b. High doses of other forms of interferon alpha and beta are known to produce dose-related anovulatory and abortifacient effects in rhesus monkeys.
Significant teratogenic and/or embryocidal potential have been demonstrated for ribavirin in all animal species in which adequate studies have been conducted, occurring at doses as low as one twentieth of the recommended human dose. Malformations of the skull, palate, eye, jaw, limbs, skeleton and gastrointestinal tract were noted. The incidence and severity of teratogenic effects increased with escalation of the ribavirin dose. Survival of fetuses and offspring was reduced. In conventional embryotoxicity/teratogenicity studies in rats and rabbits, observed no effect dose levels were well below those for proposed clinical use (0.3 mg/kg/day for both the rat and rabbit; approximately 0.06 times the recommended human 24-hour dose of ribavirin). No maternal toxicity or effects on offspring were observed in a peri/postnatal toxicity study in rats dosed orally at up to 1 mg/kg/day (estimated human equivalent dose of 0.17 mg/kg based on body surface area adjustment for a 60 kg adult; approximately 0.01 times the maximum recommended human 24-hour dose of ribavirin).
Treatment and Post-treatment: Potential Risk to the Fetus: Because of the potential human teratogenic effects of PEGETRON® (ribavirin) Capsules, male patients must be advised to take every precaution to avoid risk of pregnancy for their female partners during treatment with PEGETRON® and for six months after treatment has been concluded (i.e., 15 half-lives for ribavirin clearance from the body). Ribavirin accumulates intracellularly and is cleared from the body very slowly. In animal studies, ribavirin produced changes in sperm at doses below the clinical dose. It is unknown whether the ribavirin that is contained in sperm will exert its known teratogenic effects upon fertilization of the ova. In a study in rats, it was concluded that dominant lethality was not induced by ribavirin at doses up to 200 mg/kg for 5 days (estimated human equivalent doses of 7.14 - 28.6 mg/kg, based on body surface area adjustment for a 60 kg adult; up to 1.7 times the maximum recommended human dose of ribavirin).
Women of childbearing potential and their male partners must not receive PEGETRON® therapy unless the patient and his/her partner are using effective contraceptive (two reliable forms, one for each partner) during the therapy period. In addition, effective contraception should be utilized for six months post-therapy based on a multiple dose half-life (t1/2) of ribavirin of 12 days.
Male patients and their female partners must practice effective contraception (two reliable forms, one for each partner) during treatment with PEGETRON® and for the 6-month post-therapy period (e.g., 15 half-lives for ribavirin clearance from the body).
If pregnancy occurs in a patient or partner of a patient during treatment or during the six months after treatment cessation, the patient must be advised of the significant teratogenic risk of PEGETRON® (ribavirin) Capsules to the fetus and physicians should report such cases by calling Merck Canada Inc., Medical Information Centre Department at 1-800-567-2594.
Nursing Women: It is not known whether interferon alfa-2b, peginterferon alfa-2b and/or ribavirin are excreted in human milk. Because of the potential for serious adverse reactions from PEGETRON® in nursing infants, nursing must be discontinued prior to the start of PEGETRON® therapy.
Pediatrics (< 18 years of age): Safety and effectiveness of PEGETRON® in these patients have not been evaluated (see INDICATIONS AND CLINICAL USE section). PEGETRON is not recommended for use in children and adolescents under the age of 18 years.
HCV/HIV/HBV Co-infection: The safety and efficacy of PEGETRON® treatment have not been established for hepatitis C patients co-infected with human immunodeficiency virus (HIV) or hepatitis B virus (HBV).
Transplantation: The safety and efficacy of PEGETRON® treatment have not been established for patients with liver or other organ transplants. Preliminary data indicates that interferon alpha therapy may be associated with an increased rate of kidney graft rejection. Liver graft rejection has also been reported but a causal association with interferon alpha therapy has not been established.
Monitoring and Laboratory Tests
Standard hematologic tests, blood chemistry and a test of thyroid function must be conducted in all patients prior to initiating therapy. Acceptable baseline values that may be considered as a guideline prior to initiation of PEGETRON® therapy are:
- Hemoglobin: ≥ 12 g/dL (females), ≥ 13 g/dL (males)
- Platelets: ≥ 100 x 109/L
- Neutrophil Count: ≥ 1.5 x 10⁹/L
- TSH Levels: must be within normal limits
Laboratory evaluations are to be conducted at weeks 2 and 4 of therapy, and periodically thereafter as clinically appropriate.
Uric acid may increase due to hemolysis with PEGETRON® (ribavirin) Capsules use; therefore, the potential for development of gout must be carefully monitored in predisposed patients.
ADVERSE REACTIONS
Adverse Drug Reaction Overview
Potentially serious adverse reactions have been reported with PEGETRON® in controlled clinical trials (see ADVERSE REACTIONS, General Safety Information section).
The most frequently reported adverse reactions (≥ 25 %) with PEGETRON® were fatigue, fever, headache, rigors, myalgia, insomnia, injection site inflammation, injection site reaction, “flu-like” symptoms, weight decreased, anorexia, nausea, arthralgia, myalgia, depression, irritability, dyspnea, alopecia, pruritus, anemia, and neutropenia. The most frequently reported adverse reactions were mostly mild to moderate in severity and were manageable without the need for modification of doses or discontinuation of therapy.
Clinical Trial Adverse Drug Reactions
Because clinical trials are conducted under very specific conditions the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse drug reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
The safety of PEGETRON® was evaluated in two controlled clinical trials of over 3,500 HCV-infected naïve adult patients treated with ribavirin plus peginterferon alfa-2b for up to 48 weeks. Additionally, the safety of PEGETRON® was evaluated in one controlled clinical trial of over 2,200 HCV-infected adults who had failed previous treatment combination alpha interferon/ribavirin and who were subsequently treated with peginterferon alfa-2b for up to 48 weeks.
Study 1: ribavirin plus peginterferon alfa-2b vs. ribavirin plus interferon alfa-2b in naïve patients
A PEGETRON® randomized study compared treatment with two peginterferon alfa-2b/ribavirin regimens [peginterferon alfa-2b 1.5 mcg/kg subcutaneously once weekly/ribavirin Capsules 800 mg p.o. daily (in divided doses); peginterferon alfa-2b 1.5 mcg/kg subcutaneously once weekly for 4 weeks then 0.5 mcg/kg subcutaneously once weekly for 44 weeks/ribavirin 1,000/1,200 mg p.o. daily (in divided doses)] with INTRON A® (interferon alfa-2b) [3 MIU subcutaneously thrice weekly/ribavirin 1,000/1,200 mg p.o. daily (in divided doses)] in 1,530 adults. Interferon-naïve patients were treated for 48 weeks and followed for 24 weeks post-treatment.
The most common AEs that occurred with ≥ 10 % incidence are provided in the following table by treatment group:
Table 1 - Adverse Events Reported in Study 1 (10 % of patients in any treatment group)
| % of patients | |||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|
| PEGETRON® | interferon alfa-2b + ribavirin | ||||||||||
| PEG2b 1.5/R | PEG2b 0.5/R n = 514 | I/R n = 505 | |||||||||
800 mg n = 511 | > 10.6 mg/kg n = 188 | ||||||||||
Application Site Disorder Injection site inflammation Injection site reaction Autonomic Nervous System Mouth dry Sweating increased Body as a Whole Asthenia Fatigue Fever Headache “Flu-like” symptoms Rigors RUQ1 pain Weight decrease Central Nervous System Dizziness Gastrointestinal System Abdominal Pain Anorexia Diarrhea Nausea Vomiting Musculoskeletal Arthralgia Musculoskeletal pain Myalgia Psychiatric Anxiety Concentration impaired Depression Emotional lability Insomnia Irritability Resistance Mechanism Infection viral Respiratory System Coughing Dyspnea Pharyngitis Rhinitis Skin and Appendages Alopecia Pruritus Rash Skin dry | 25 58 12 11 18 64 46 62 24 48 12 29 21 13 32 22 43 14 34 21 56 15 17 31 11 40 35 12 17 26 12 8 36 29 24 24 | 20 54 11 7 28 56 41 59 21 43 10 30 18 15 35 22 43 16 32 19 51 16 19 34 11 38 32 15 19 27 16 10 45 28 23 26 | 27 59 8 9 16 62 44 58 27 45 7 17 19 12 29 16 36 14 34 17 48 15 16 29 11 40 34 10 15 23 11 8 29 26 22 18 | 18 36 8 7 18 60 33 58 23 41 6 20 17 13 27 17 33 12 28 19 50 15 21 34 10 41 34 12 13 24 13 6 32 28 23 23 | |||||||
PEG2b = peginterferon alfa-2b
R = ribavirin
I = interferon alfa-2b
1: Right Upper Quadrant
Adverse events reported between 5 and 10 % in the treatment group receiving the recommended dose of PEGETRON® were chest pain, right upper quadrant (RUQ) pain, paresthesia, hypothyroidism, constipation, dyspepsia, tachycardia, agitation, nervousness, menorrhagia, menstrual disorder, non-productive cough, rhinitis, taste perversion, and blurred vision.
Adverse events reported between 2 and 5 % in the treatment group receiving the recommended dose of PEGETRON® were injection site pain, flushing, hypotension, lacrimal gland disorder, erythema, malaise, hypertension, syncope, confusion, hyperesthesia, hypoesthesia, hypertonia, decreased libido, tremor, vertigo, hyperthyroidism, flatulence, gingival bleeding, glossitis, loose stools, stomatitis, ulcerative stomatitis, hearing impairment/loss, tinnitus, palpitation, thirst, thrombocytopenia, aggressive behavior, somnolence, herpes simplex, fungal infection, amenorrhea, prostatitis, otitis media, bronchitis, nasal congestion, respiratory disorder, rhinorrhea, sinusitis, eczema, abnormal hair texture, photosensitivity reaction, erythematous rash, maculopapular rash, migraine, conjunctivitis, neutropenia, thyroid disorders, eye pain, apathy, and lymphadenopathy.
Study 2 (IDEAL): ribavirin plus peginterferon alfa-2b vs. ribavirin plus peginterferon in naïve patients
This PEGETRON® study with 3,070 adults compared two peginterferon alfa-2b (1.5 mcg/kg/week and 1.0 mcg/kg/week) doses in combination with ribavirin (800-1,400 mg/day) and included a third treatment group in which patients received peginterferon alfa-2a (180 mcg/week)/ribavirin (1,000-1,200 mg/day).
Table 2 - Adverse Reactions Reported in Study 2 Occurring in ≥ 1 % of Patients in either PEG 2b Arm
| SOC/Adverse Reactions | Number (%) of Patients | ||
|---|---|---|---|
PEG2b 1.5/R n = 1,019 | PEG2b 1.0/R n = 1,016 | PEG2a/R n = 1,035 | |
Blood and Lymphatic System Disorders Anemia Neutropenia Leukopenia Thrombocytopenia Hemolytic anemia | 499 (49) 343 (34) 263 (26) 95 (9) 28 (3) 16 (2) | 413 (41) 293(29) 188 (19) 69 (7) 23 (2) 8 (< 1) | 540 (52) 348 (34) 325 (31) 106 (10) 66 (6) 3 (< 1) |
Cardiac Disorders Palpitations | 23 (2) 9 (< 1) | 34 (3) 23 (2) | 29 (3) 16 (2) |
Ear and Labyrinth Disorders Tinnitus | 46 (5) 19 (2) | 46 (5) 13 (1) | 43 (4) 9 (< 1) |
Endocrine Disorders Hypothyroidism Hyperthyroidism | 61 (6) 54 (5) 13 (1) | 55 (5) 38 (4) 22 (2) | 61 (6) 46 (4) 21 (2) |
Eye Disorders Vision blurred Dry eye Eye pain Photophobia Retinal exudates Visual disturbance | 133 (13) 38 (4) 30 (3) 11 (1) 14 (1) 12 (1) 11 (1) | 113 (11) 54 (5) 17 (2) 5 (< 1) 7 (< 1) 4 (< 1) 9 (< 1) | 146 (14) 64 (6) 35 (3) 13 (1) 5 (< 1) 8 (< 1) 12 (1) |
Gastrointestinal Disorders Nausea Diarrhea Vomiting Constipation Dry mouth Abdominal pain Dyspepsia Abdominal pain upper | 630 (62) 412 (40) 154 (15) 121 (12) 51 (5) 53 (5) 38 (4) 45 (4) 32 (3) | 583 (57) 357 (35) 162 (16) 100 (10) 59 (6) 50 (5) 31 (3) 42 (4) 32 (3) | 577 (56) 351 (34) 147 (14) 87 (8) 51 (5) 45 (4) 37 (4) 55 (5) 36 (3) |
| SOC/Adverse Reactions | Number (%) of Patients |
|---|
PEG2b 1.5/R n = 1,019 | PEG2b 1.0/R n = 1,016 | PEG2a/R n = 1,035 | |
|---|---|---|---|
Stomatitis Gastroesophageal reflux disease Mouth ulceration Abdominal distension Aphthous stomatitis Abdominal discomfort Cheilitis Glossodynia Stomach discomfort Flatulence Gingival bleeding | 28 (3) 23 (2) 17 (2) 13 (1) 12 (1) 6 (< 1) 14 (1) 14 (1) 15 (1) 8 (< 1) 10 (1) | 33 (3) 25 (2) 21 (2) 11 (1) 10 (1) 10 (1) 6 (< 1) 14 (1) 14 (1) 10 (1) 6 (< 1) | 25 (2) 33 (3) 21 (2) 15 (1) 12 (1) 3 (< 1) 5 (< 1) 11 (1) 12 (1) 5 (< 1) 3 (< 1) |
General Disorders and Administration Site Conditions Fatigue Chills Pyrexia Irritability Influenza like illness Injection site erythema Pain Injection site reaction Asthenia Chest pain Injection site rash Injection site pruritus Chest discomfort Feeling abnormal Malaise Injection site irritation Injection site pain Edema peripheral Temperature intolerance | 917 (90) 663 (65) 397 (39) 352 (35) 251 (25) 164 (16) 166 (16) 120 (12) 101 (10) 50 (5) 39 (4) 41 (4) 29 (3) 16 (2) 19 (2) 21 (2) 12 (1) 12 (1) 5 (< 1) 6 (< 1) | 933 (92) 665 (65) 362 (36) 323 (32) 259 (25) 152 (15) 178 (18) 133 (13) 112 (11) 43 (4) 31 (3) 38 (4) 19 (2) 22 (2) 10 (1) 18 (2) 10 (1) 13 (1) 11 (1) 10 (1) | 892 (86) 649 (63) 241 (23) 219 (21) 262 (25) 157 (15) 123 (12) 90 (9) 57 (6) 41 (4) 27 (3) 20 (2) 13 (1) 12 (1) 12 (1) 20 (2) 7 (< 1) 8 (< 1) 11 (1) 3 (< 1) |
Infections and Infestations Sinusitis Influenza Bronchitis Cellulitis Oral herpes Upper respiratory tract infection | 162 (16) 30 (3) 20 (2) 14 (1) 7 (< 1) 14 (1) 7 (< 1) | 152 (15) 11 (1) 19 (2) 11 (1) 10 (1) 20 (2) 19 (2) | 197 (19) 27 (3) 14 (1) 21 (2) 9 (< 1) 19 (2) 19 (2) |
Investigations Weight decreased Hemoglobin decreased Blood amylase increased Blood thyroid stimulating hormone increased Neutrophil count decreased Platelet count decreased | 225 (22) 135(13) 21(2) 7(< 1) 12(1) 13(1) 12(1) | 183 (18) 100(10) 19(2) 12(1) 13(1) 7(< 1) 9(< 1) | 189 (18) 100 (10) 21 (2) 5 (< 1) 11 (1) 13 (1) 15 (1) |
Metabolism and Nutrition Disorders Decreased appetite Anorexia Hyperuricemia Dehydration | 340 (33) 182 (18) 121 (12) 14 (1) 11 (1) | 284 (28) 156 (15) 95 (9) 17 (2) 6 (< 1) | 252 (24) 141 (14) 75 (7) 17 (2) 7 (< 1) |
Musculoskeletal Pain Myalgia Arthralgia Back pain Muscle spasms Pain in extremity Neck pain Musculoskeletal pain | 473 (46) 271 (27) 218 (21) 59 (6) 46 (5) 35 (3) 9 (< 1) 8 (< 1) | 505 (50) 264 (26) 219 (22) 65 (6) 39 (4) 40 (4) 10 (1) 10 (1) | 467 (45) 226 (22) 228 (22) 72 (7) 54 (5) 39 (4) 10 (1) 15 (1) |
| SOC/Adverse Reactions | Number (%) of Patients |
|---|
PEG2b 1.5/R n = 1,019 | PEG2b 1.0/R n = 1,016 | PEG2a/R n = 1,035 | |
|---|---|---|---|
Nervous System Disorders Headache Dizziness Dysgeusia Disturbance in attention Hypoesthesia Memory impairment Amnesia Hyperesthesia Migraine Paresthesia Sinus headache Tremor Poor quality of sleep Syncope Somnolence Lethargy | 664 (65) 501 (49) 155 (15) 79 (8) 71 (7) 28 (3) 27 (3) 16 (2) 17 (2) 17 (2) 25 (2) 17 (2) 20 (2) 9 (< 1) 14 (1) 8 (< 1) 5 (< 1) | 626 (62) 474 (47) 139 (14) 69 (7) 51 (5) 25 (2) 37 (4) 29 (3) 10 (1) 15 (1) 24 (2) 6 (< 1) 21 (2) 14 (1) 12 (1) 11 (1) 10 (1) | 601 (58) 426 (41) 136 (13) 66 (6) 71 (7) 26 (3) 33 (3) 18 (2) 3 (< 1) 13 (1) 17 (2) 5 (< 1) 10 (1) 12 (1) 12 (1) 7 (< 1) 5 (< 1) |
Psychiatric Disorders Insomnia Depression Anxiety Affect lability Agitation Anger Crying Libido decreased Mood swings Restlessness Confusional state Mood altered Nervousness | 588 (58) 384 (38) 254 (25) 107 (11) 31 (3) 17 (2) 25 (2) 16 (2) 24 (2) 18 (2) 14 (1) 10 (1) 9 (< 1) 6 (< 1) | 561 (55) 377 (37) 192 (19) 111 (11) 23 (2) 15 (1) 20 (2) 12 (1) 11 (1) 19 (2) 16 (2) 8 (< 1) 12 (1) 10 (1) | 587 (57) 417 (40) 209 (20) 105 (10) 21 (2) 16 (2) 10 (1) 4 (< 1) 13 (1) 16 (2) 6 (< 1) 5 (< 1) 11 (1) 8 (< 1) |
Renal and Urinary Disorders Pollakiuria | 34 (3) 14 (1) | 32 (3) 15 (1) | 24 (2) 10 (1) |
Reproductive System and Breast Disorders Erectile Dysfunction | 38 (4) 13 (1) | 38 (4) 15 (1) | 50 (5) 18 (2) |
Respiratory, Thoracic and Mediastinal Disorders Dyspnea Cough Dyspnea exertional Pharyngolaryngeal pain Respiratory tract congestion Epistaxis Nasal congestion Productive cough Sinus congestion Increased upper airway secretion Nasal dryness Postnasal drip Rhinorrhea | 383 (38) 170 (17) 139 (14) 55 (5) 32 (3) 26 (3) 21 (2) 18 (2) 23 (2) 23 (2) 13 (1) 10 (1) 11 (1) 7 (< 1) | 391 (38) 160 (16) 155 (15) 54 (5) 39 (4) 18 (2) 24 (2) 20 (2) 7 (< 1) 24 (2) 6 (< 1) 8 (< 1) 12 (1) 10 (1) | 411 (40) 165 (16) 172 (17) 72 (7) 37 (4) 17 (2) 29 (3) 28 (3) 8 (< 1) 30 (3) 5 (< 1) 8 (< 1) 5 (< 1) 9 (< 1) |
Skin and Subcutaneous Tissue Disorders Alopecia Rash Pruritus Dry skin Rash generalized Rash pruritic Hyperhidrosis Dermatitis | 592 (58) 232 (23) 212 (21) 156 (15) 117 (11) 42 (4) 38 (4) 30 (3) 23 (2) | 547 (54) 205 (20) 205 (20) 133 (13) 110 (11) 25 (2) 27 (3) 31 (3) 16 (2) | 617 (60) 176 (17) 274 (26) 173 (17) 128 (12) 36 (3) 38 (4) 33 (3) 20 (2) |
| SOC/Adverse Reactions | Number (%) of Patients |
|---|
PEG2b 1.5/R n = 1,019 | PEG2b 1.0/R n = 1,016 | PEG2a/R n = 1,035 | |
|---|---|---|---|
Erythema Pruritus generalized Eczema Night sweats Psoriasis Rash erythematous Rash papular Skin exfoliation | 16 (2) 25 (2) 14 (1) 13 (1) 9 (< 1) 12 (1) 12 (1) 3 (< 1) | 17 (2) 20 (2) 10 (1) 21 (2) 11 (1) 5 (< 1) 6 (< 1) 10 (1) | 9 (< 1) 24 (2) 4 (< 1) 16 (2) 13 (1) 13 (1) 16 (2) 7 (< 1) |
Vascular Disorders Hot flush Hypertension | 45 (4) 19 (2) 12 (1) | 47 (5) 12 (1) 18 (2) | 47 (5) 17 (2) 18 (2) |
SOC = System Organ Class
PEG2b = peginterferon alfa-2b
R = ribavirin
PEG2a = peginterferon alfa-2a
Study 3 (EPIC): retreatment of prior treatment failures (relapser and non-responder patients)
In a single-arm trial, adult patients with moderate to severe fibrosis who failed previous treatment with combination of alpha interferon (pegylated or non-pegylated) and ribavirin, including non-responders and relapsers, were subsequently retreated with peginterferon alfa-2b, 1.5 mcg/kg subcutaneously, once weekly, in combination with body weight-adjusted ribavirin (800-1,400 mg/day, p.o.). Prior non-responders (n = 1,401) were defined as patients who were HCV-RNA positive at the end of a minimum 12 weeks of treatment and prior relapsers (n = 647) were defined as patients who were HCV-RNA negative at the end of a minimum 12 weeks of treatment and subsequently relapsed after post-treatment follow-up.
A total of 2,312 patients were eligible for safety analysis, while 2,293 patients were included in efficacy analysis. 943 patients (41 %) completed dosing of combination therapy and were treated for 48 weeks. 1,061 patients (46 %) were identified as virologic treatment failures after 12 weeks of treatment, were discontinued from the study by Treatment Week 18 and were eligible for other studies; 308 patients (13 %) were discontinued from the study due to other reasons.
Table 3 - Adverse Reactions Reported in Study 3 Occurring in ≥ 1 % of Patients
| SOC/Adverse Reactions | Number (%) of Patients* |
|---|---|
PEG2b 1.5/R n = 2,312 | |
Blood and Lymphatic System Disorders Neutropenia Anemia Leukopenia Thrombocytopenia Lymphopenia | 738 (32) 459 (20) 368 (16) 239 (10) 127 (7) 25 (1) |
Ear and Labyrinth Disorders Vertigo | 90 (4) 46 (2) |
Endocrine Disorders Hypothyroidism | 54 (2) 46 (2) |
Eye Disorders Dry eye Vision blurred | 172 (7) 44 (2) 40 (2) |
| Gastrointestinal Disorders | 1,097 (47) |
| SOC/Adverse Reactions | Number (%) of Patients* |
|---|
PEG2b 1.5/R n = 2,312 | |
|---|---|
Nausea Diarrhea Vomiting Dry mouth Abdominal pain upper Dyspepsia Constipation Stomatitis Aphthous stomatitis Gastroesophageal reflux disease Gastritis Mouth ulceration | 560 (24) 281 (12) 178 (8) 132 (6) 114 (5) 95 (4) 58 (3) 33 (1) 28 (1) 27 (1) 24 (1) 24 (1) |
General Disorders and Administration Site Conditions Pyrexia Fatigue Chills Asthenia Influenza like illness Irritability Injection site erythema Injection site reaction Malaise Pain Chest pain Injection site pruritus Injection site irritation Injection site rash | 1,972 (85) 887 (38) 747 (32) 505 (22) 492 (21) 491 (21) 394 (17) 236 (10) 120 (5) 92 (4) 85 (4) 44 (2) 29 (1) 28 (1) 25 (1) |
Hepatobiliary Disorders Hyperbilirubinemia | 63 (3) 42 (2) |
Infections and Infestations Oral herpes Influenza Nasopharyngitis | 311 (13) 50 (2) 39 (2) 25 (1) |
Investigations Weight decreased Hemoglobin decreased Neutrophil count decreased Platelet count decreased White blood cell count decreased Blood bilirubin increased Blood uric acid increased | 366 (16) 151 (7) 82 (4) 59 (3) 45 (2) 42 (2) 27 (1) 23 (1) |
Metabolism and Nutrition Disorders Anorexia Decreased appetite Hyperuricemia | 561 (24) 284 (12) 195 (8) 37 (2) |
Musculoskeletal and Connective Tissue Disorders Myalgia Arthralgia Back pain Pain in extremity Muscle spasms Musculoskeletal pain Bone pain | 1,071 (46) 705 (30) 371 (16) 109 (5) 62 (3) 53 (2) 36 (2) 28 (1) |
Nervous System Disorders Headache Dizziness Disturbance in attention Lethargy | 1,167 (50) 907 (39) 223 (10) 109 (5) 73 (3) |
| SOC/Adverse Reactions | Number (%) of Patients* |
|---|
PEG2b 1.5/R n = 2,312 | |
|---|---|
Dysgeusia Memory impairment Paresthesia Tremor Hypoesthesia | 68 (3) 38 (2) 35 (2) 31 (1) 24 (1) |
Psychiatric Disorders Insomnia Depression Anxiety Sleep disorder Depressed mood Affect lability Libido decreased Mood altered Mood swings Aggression Nervousness | 924 (40) 487 (21) 272 (12) 182 (8) 56 (2) 34 (1) 33 (1) 33 (1) 33 (1) 33 (1) 29 (1) 23 (1) |
Respiratory, Thoracic and Mediastinal Disorders Cough Dyspnea Dyspnea exertional Epistaxis Pharyngolaryngeal pain Nasal congestion | 699 (30) 325 (14) 238 (10) 81 (4) 57 (2) 57 (2) 31 (1) |
Skin and Subcutaneous Tissue Disorders Alopecia Pruritus Rash Dry skin Erythema Hyperhidrosis Eczema | 1,012 (44) 388 (17) 338 (15) 213 (9) 192 (8) 73 (3) 56 (2) 36 (2) |
Vascular Disorders Hypertension | 73 (3) 29 (1) |
SOC = System Organ Class
*: Includes all METAVIR scores (F1-F4) and missing METAVIR scores
PEG2b = peginterferon alfa-2b
R = ribavirin
There was a trend of increasing incidence with increasing dose of ribavirin for diarrhea, dry mouth, injection site erythema, anxiety, and exertional dyspnea. The following AEs were more common (≥ 5 % difference) with the 1,400 mg ribavirin dose than with the lower doses: thrombocytopenia, decrease hemoglobin, decreased neutrophil count, nausea, vomiting, chills, fatigue, irritability, pain, headache, and dyspnea. There is a tendency of increased Serious Adverse Events and discontinuation of treatment due to AEs with increasing ribavirin dose. Dose modification due to AEs occurred more often in 1,400 mg/day group.
Less Common Clinical Trial Adverse Drug Reactions (< 1 %) (IDEAL and EPIC)
Some Adverse Drug Reactions (ADRs) were only reported in a single trial. Some ADRs with an incidence of ≥ 1 % for the EPIC trial but were < 1 % in the IDEAL trial are also reported in the above Table 3.
Blood and Lymphatic System Disorders: lymphadenopathy, pancytopenia
Cardiac Disorders: tachycardia, cardiomyopathy, myocardial infarction, pericarditis
Ear and Labyrinth Disorders: ear pain, vertigo
Eye Disorders: abnormal sensation in eye, eye irritation, retinopathy, visual acuity reduced
Gastrointestinal Disorders: gingival pain, hemorrhoids, oral pain, rectal hemorrhage, toothache, abdominal pain lower, glossitis, oral disorder, retching, tongue ulceration, colitis ischemic, gingivitis, pancreatitis
General Disorders and Administration Site Conditions: feeling hot, injection site bruising, injection site dryness, thirst, feeling jittery, injection site hemorrhage, face edema, injection site inflammation, injection site necrosis, non-cardiac chest pain, edema
Hepatobiliary Disorders: hepatic pain, hyperbilirubinemia
Immune System Disorders: drug hypersensitivity, sarcoidosis
Infections and Infestations: candidiasis, nasopharyngitis, oral candidiasis, urinary tract infection, onychomycosis, ear infection, sinusitis, infection bacterial including sepsis, fungal infection, furuncle, herpes simplex, injection site infection, lower respiratory tract infection, otitis media, respiratory tract infection, rhinitis, upper respiratory tract infection
Injury, Poisoning and Procedural Complications: contusion, overdose
Investigations: blood pressure increased, blood thyroid stimulating hormone decreased, blood triglycerides increased, blood uric acid increased, heart rate increased, blood glucose increased, hematocrit decreased, blood alkaline phosphatase increased, white blood cell count decreased
Metabolism and Nutrition Disorders: hyperglycemia, hypertriglyceridemia, diabetes mellitus, increased appetite, diabetic ketoacidosis, hypercalcemia
Musculoskeletal and Connective Tissue Disorders: flank pain, joint stiffness, muscle tightness, muscle weakness, bone pain, arthritis, rheumatoid arthritis
Nervous System Disorders: parosmia, restless leg syndrome, hypogeusia, neuralgia, neuropathy, neuropathy peripheral
Psychiatric Disorders: apathy, depressed mood, suicidal ideation, tearfulness, stress, abnormal behavior, abnormal dreams, psychosis, aggression, bipolar disorder, hallucination, homicidal ideation, panic attack, sleep disorder, suicide attempt
Renal and Urinary Disorders: dysuria, micturition frequency decreased, micturition urgency, polyuria renal failure, urine abnormality
Reproductive System and Breast Disorders: menorrhagia, amenorrhea, menstrual disorder, menstruation irregular, breast pain, prostatitis, sexual dysfunction
Respiratory, Thoracic and Mediastinal Disorders: dysphonia, paranasal sinus hypersecretion, wheezing, dry throat, nasal ulcer
Skin and Subcutaneous Tissue Disorders: increased tendency to bruise, skin discoloration, skin lesions, rash macular, rash maculopapular, hair texture abnormal, photosensitivity reaction, skin ulcer, urticaria, pain of skin, cutaneous sarcoidosis, erythema multiforme, nail disorder
Vascular Disorders: pallor, flushing, hypotension, vasculitis, deep vein thrombosis
General Safety Information
In clinical trials, approximately 1.2 % of patients treated with PEGETRON® reported life-threatening psychiatric events during treatment. These events included suicide, attempted suicide, suicidal ideation, psychosis including hallucinations, bipolar disorders and aggressive behavior, sometimes directed towards others (see WARNINGS AND PRECAUTIONS section).
As with other alpha interferons, ophthalmological disorders including retinopathies (including macular edema), retinal hemorrhages, retinal artery or vein obstruction, cotton wool spots, loss of visual acuity or visual field, optic neuritis, and papilledema have been rarely reported during therapy with peginterferon alfa-2b (see WARNINGS AND PRECAUTIONS section).
Adverse reactions of the cardiovascular system (CVS), particularly arrhythmia, appeared to be correlated mostly with pre-existing CVS disease and prior cardiotoxic therapy. Cardiomyopathy was also observed in patients treated with peginterferon alpha and has been reported more frequently in patients with known risk factors for cardiovascular diseases. There are limited data to assess the reversibility of cardiomyopathy reported with the use of peginterferon alpha; however cases of reversible cardiomyopathy have been reported with the use of interferon alpha.
As with other alpha interferons, seizures, pancreatitis, hypertriglyceridemia, arrhythmia, diabetes, peripheral neuropathy, colitis (including ischemic and ulcerative), aplastic anemia, hypertension, cardiac ischemia, myocardial infarction, cerebrovascular ischemia, cerebrovascular hemorrhage, encephalopathy (see WARNINGS AND PRECAUTIONS section), sarcoidosis or exacerbation of sarcoidosis, erythema multiforme, Stevens Johnson syndrome, toxic epidermal necrolysis, injection site necrosis, rhabdomyolysis, myositis, renal failure and renal insufficiency have been rarely or very rarely reported during therapy with peginterferon alfa-2b.
Very rarely, alpha interferons, including peginterferon alfa-2b used alone or in combination with ribavirin, may be associated with pure red cell aplasia (PRCA).
Alpha interferons have been associated with altered lipid metabolism (including hypercholesterolemia and hyperlipemia) and pulmonary hypertension.
Adequate hydration must be maintained in patients undergoing peginterferon alfa-2b therapy since hypotension related to fluid depletion has been seen in some patients treated with alpha interferons. Fluid replacement may be necessary.
Abnormal Hematologic and Clinical Chemistry Findings from Studies 1 and 2
Hemoglobin levels in study 1 dropped below 10 g/dL in up to 14 % of patients treated with PEGETRON®. Most cases of anemia, neutropenia and thrombocytopenia were mild (WHO grades 1 or 2). Some cases of more severe neutropenia in patients treated with the recommended doses of PEGETRON® were reported (WHO grade 3 [21 %] and grade 4 [7 %]).
In addition, patients receiving peginterferon alfa-2b (1.5 mcg/kg)/ribavirin, in the IDEAL study (study 2), had decreases in hemoglobin levels to between 8.5 to < 10 g/dL (28 %) and to < 8.5 g/dL (3 %). WHO grades 3 and 4 leukopenia was also reported in 7 % and 0.3 % of this treatment group.
An increase in uric acid and indirect bilirubin values associated with hemolysis was observed in some patients treated with PEGETRON®, but values returned to baseline levels by four weeks after the end of therapy. Among those patients with elevated uric acid levels, very few patients treated with PEGETRON® developed clinical gout, none of which required treatment modification or discontinuation from the clinical trials.
Post-Market Adverse Drug Reactions
Very rarely, post-marketing reports of pancreatitis, seizures, ulcerative and ischemic colitis, rhabdomyolysis, myositis, stomatitis, vertigo, renal insufficiency, renal failure, injection site necrosis, erythema multiforme, Stevens Johnson syndrome, toxic epidermal necrolysis, cerebrovascular ischemia, cerebrovascular hemorrhage, hearing impairment, hearing loss, cardiac ischemia, pulmonary fibrosis, myocardial infarction and and hepatitis B reactivation in HCV/HBV co-infected patients have been received. A wide variety of autoimmune and immune-mediated disorders have been reported with alpha interferons including idiopathic thrombocytopenic purpura, thrombotic thrombocytopenic purpura, rheumatoid arthritis, systemic lupus erythematosus, vasculitis and Vogt-Koyanagi-Harada syndrome.
Very rare cases of PRCA were reported in patients receiving both anti-hepatitis C therapy and erythropoietin (EPO) stimulating agents. The potential for an increased risk of PRCA and development of anti-EPO antibodies should therefore be kept in mind when considering EPO stimulating agents use for hepatitis C treatment induced – anemia.
Cases of acute hypersensitivity reactions, including anaphylaxis, urticaria and angioedema have been reported.
Other AEs reported with peginterferon alfa-2b alone or in combination with ribavirin include: abdominal pain, anxiety, asthenic conditions (including asthenia, malaise and fatigue), bacterial infection (including sepsis), chest pain, cough, dehydration, dyspnea, dry skin, emotional lability, facial palsy, fungal infection, hypertension, hyperthyroidism, hypotension, hypothyroidism, irritability, migraine headache, palpitations, paresthesia, peripheral neuropathy, pruritus, rash, and serous retinal detachment.
DRUG INTERACTIONS
Overview
The potential interaction of peginterferon alfa-2b on substrates of metabolic enzymes were evaluated in 4 clinical pharmacology studies. In one study, a single, subcutaneous dose (1 mcg/kg) of peginterferon alfa-2b did not affect the activities of CYP1A2 (caffeine), CYP2C9 (tolbutamide), CYP2D6 (dextromethorphan), CYP3A4 (midazolam) and N-acetyltransferase (dapsone) as assessed in healthy subjects (N=12). In the remaining 3 studies, the effects of multiple-dose regimens of peginterferon alfa-2b were investigated in Hepatitis C subjects (1.5 mcg/week) or healthy subjects (1 mcg/week or 3 mcg/week) (Table 4). A clinically significant pharmacokinetic interaction was not observed between peginterferon alfa-2b and tolbutamide, midazolam or dapsone; therefore, no dosing adjustment is necessary when peginterferon alfa-2b is administered with drugs metabolized by CYP2C9, CYP3A4 and N-acetyltransferase. Concomitant administration of peginterferon alfa-2b with caffeine or desipramine modestly increased the exposure of caffeine and desipramine. When patients are administered peginterferon alfa-2b with medications metabolized by CYP1A2 or CYP2D6, the extent of the decrease in cytochrome P 450 activity is unlikely to have a clinical impact, except with drugs which have a narrow therapeutic margin (see Table 5).
Drug-Drug Interactions
Table 4 - Effect of peginterferon alfa-2b on Coadministered Drugs
| Coadministered Drug | peginterferon alfa-2b | Study Population | Geometric Mean Ratio (ratio with/without peginterferon alfa-2b) | |||||||
AUC (90% CI) | Cmax (90% CI) | |||||||||
caffeine (CYP1A2 substrate) | 1.5 mcg/kg/week (4 weeks) | Chronic Hepatitis C subjects (N=22) | 1.39 (1.27, 1.51) | 1.02 (0.95, 1.09) | ||||||
1 mcg/kg/week (4 weeks) | Healthy subjects (N=24) | 1.18 (1.07, 1.31) | 1.12 (1.05, 1.19) | |||||||
3 mcg/kg/week (2 weeks) | Healthy subjects (N=13) | 1.36 (1.25-1.49) | 1.16 (1.10-1.24) | |||||||
tolbutamide (CYP2C9 substrate) | 1.5 mcg/kg/week (4 weeks) | Chronic Hepatitis C subjects (N=22) | 1.1a (0.94, 1.28) | NA | ||||||
1 mcg/kg/week (4 weeks) | Healthy subjects (N=24) | 0.90 a (0.81, 1.00) | NA | |||||||
3 mcg/kg/week (2 weeks) | Healthy subjects (N=13) | 0.95 (0.89-1.01) | 0.99 (0.92-1.07) | |||||||
dextromethorphan hydrobromide (CYP2D6 and CYP3A substrate) | 1.5 mcg/kg/week (4 weeks) | Chronic Hepatitis C subjects (N=22) | 0.96b (0.73, 1.26) | NA | ||||||
1 mcg/kg/week (4 weeks) | Healthy subjects (N=24) | 2.03 a (1.55, 2.67) | NA | |||||||
desipramine (CYP2D6 substrate) | 3 mcg/kg/week (2 weeks) | Healthy subjects (N=13) | 1.30 (1.18-1.43) | 1.08 (1.00-1.16) | ||||||
midazolam (CYP3A4 substrate) | 1.5 mcg/kg/week (4 weeks) | Chronic Hepatitis C subjects (N=24) | 1.07 (0.91, 1.25) | 1.12 (0.94,1.33) | ||||||
1 mcg/kg/week (4 weeks) | Healthy subjects (N=24) | 1.07 (0.99, 1.16) | 1.33 (1.15, 1.53) | |||||||
3 mcg/kg/week (2 weeks) | Healthy subjects (N=13) | 1.18 (1.06-1.32) | 1.24 (1.07-1.43) | |||||||
dapsone (N- | 1.5 mcg/kg/week (4 weeks) | Chronic Hepatitis C subjects | 1.05 (1.02, 1.08) | 1.03 (1.00, 1.06) | ||||||
| acetyltransferase substrate) | (N=24) |
a: Calculated from urine data collected over an interval of 48-hours.
b: Calculated from urine data collected over an interval of 24-hours.
Table 5 - Precautions for Coadministration (peginterferon alfa-2b should be administered with care when coadministered with the following drugs.)
| Drugs | Signs, Symptoms, and Treatment | Mechanism and Risk Factors |
| theophylline | Coadministration of theophylline with the product (peginterferon alfa-2b) may increase the blood concentrations of theophylline. Careful coadministration of theophylline with the product (peginterferon alfa-2b) is recommended. Package inserts of theophylline should be referred to when coadministering with the product (peginterferon alfa-2b). | Metabolism of theophylline is suppressed by inhibitory action of the product (peginterferon alfa-2b) on CYP1A2. |
| thioridazine | Coadministration of thioridazine with the product (peginterferon alfa-2b) may increase the blood concentrations of thioridazine. Careful coadministration of thioridazine with the product (peginterferon alfa-2b) is recommended. Package inserts of thioridazine should be referred to when coadministering with the product (peginterferon alfa-2b). | Metabolism of thioridazine is suppressed by inhibitory action of the product (peginterferon alfa-2b) on CYP2D6. |
theophylline, antipyrine, warfarin | Elevation of blood concentrations of these drugs has been reported when administered in combination with other interferon preparations and therefore care should be taken. | Metabolism of other drugs in the liver may be suppressed. |
| zidovudine | When administered in combination with other interferon preparations, suppressive effect on bone marrow function may be strengthened and aggravation of blood cell reduction such as white blood cells decreased may occur. | Mechanism of action is unknown, but it is considered that both drugs have bone marrow depressive effects. |
| immuno-suppressive therapy | When administered in combination with other interferon preparations, effect of immunosuppressive therapy may be weakened in transplant (kidney, bone marrow, etc.) patients. | It is considered that graft rejection reactions may be induced. |
Ribavirin was shown in vitro to inhibit phosphorylation of the nucleoside analog reverse transcriptase inhibitors (NRTIs) zidovudine and stavudine. The clinical significance of these findings is unknown. However, these in vitro findings raise the possibility that concurrent use of PEGETRON® (ribavirin) Capsules with either zidovudine or stavudine might lead to increased HIV plasma viremia. Therefore, it is recommended that plasma HIV-RNA levels be closely monitored in patients treated with PEGETRON® (ribavirin) Capsules concurrently with either of these two agents. If HIV-RNA levels increase, the use of PEGETRON® (ribavirin) Capsules concomitantly with NRTIs must be reviewed.
Use of nucleoside analogs, alone or in combination with other nucleosides, has resulted in lactic acidosis. Pharmacologically, ribavirin increases phosphorylated metabolites of purine nucleosides in vitro. This activity could potentiate the risk of lactic acidosis induced by purine nucleoside analogues (e.g., didanosine or abacavir). Co-administration of ribavirin and didanosine is not recommended. Reports of mitochondrial toxicity in particular lactic acidosis and pancreatitis, of which some fatal, have been reported.
An increased risk of developing peripheral neuropathy cannot be ruled out for treatments combining telbivudine with any alpha (standard or pegylated types) and beta interferon products. This risk might occur when the drug is used with interferon products other than pegylated interferon alfa-2a. Development of peripheral neuropathy was reported in a small clinical trial in
Hepatitis B investigating the use of both 600 mg daily of telbivudine and 180 mcg once weekly by subcutaneous administration of pegylated interferon alfa-2a. The safety and efficacy of telbivudine in combination with interferon alfa-2b has not been established in patients with Hepatitis B; therefore, telbivudine in combination with alpha interferons is not recommended.
There are limited data regarding the efficacy and safety of combining PEGETRON® with Highly Active Anti-Retroviral Therapy (HAART) for HIV-HCV co-infected patients. Patients co-infected with HIV and who are receiving HAART may be at increased risk of developing lactic acidosis. Caution should be used when treating HIV-HCV co-infected subjects with PEGETRON® in combination with HAART.
Any potential for interactions may persist for up to two months (5 half-lives for PEGETRON® (ribavirin) Capsules) after cessation of PEGETRON® therapy due to the long half-life of PEGETRON® (ribavirin) Capsules.
There is no evidence that ribavirin interacts with non-nucleoside reverse transcriptase inhibitors (NNRTIs) or protease inhibitors.
Antacid: The bioavailability of ribavirin (600 mg) was decreased by co-administration with an antacid containing magnesium aluminum and simethicone; AUCtf decreased 14 %. This interaction is not considered to be clinically relevant.
Drug-Food Interactions
Interactions with food have not been established.
Drug-Herb Interactions
As with other alpha interferons, pulmonary infiltrates, pneumonitis, and pneumonia, occasionally resulting in fatality, have been observed rarely in peginterferon alfa-2b treated patients. These symptoms have been reported more frequently when Shosaikoto (also known as Xiao-Chai-Hu-Tang), a Chinese herbal medication, has been administered concomitantly with alpha interferons.
Drug-Laboratory Interactions
Interactions with laboratory tests have not been established.
DOSAGE AND ADMINISTRATION
PEGETRON® (peginterferon alfa-2b) Powder for Solution is administered subcutaneously using either the plastic disposable syringes or the CLEARCLICK™ Single Dose Delivery System with the disposable push-on needles supplied. PEGETRON® (ribavirin) Capsules are for oral administration only.
PEGETRON® treatment should be initiated only by a physician experienced in the treatment of patients with hepatitis C.
Adults- HCV/HBV co-infection:
The safety and efficacy of peginterferon alfa-2b alone or in combination with boceprevir or ribavirin for the treatment of chronic hepatitis C genotype 1 infection in patients co-infected with hepatitis B Virus (HBV) and HCV have not been studied (see also WARNINGS AND PRECAUTIONS/ HCV/HIV/HBV Co-infection).
Recommended Dose
Based on the results of the clinical trials, the recommended dose of PEGETRON® (peginterferon alfa-2b) Powder for Solution is 1.5 mcg/kg/week subcutaneously in combination with PEGETRON® (ribavirin) Capsules. PEGETRON® (peginterferon alfa-2b) Powder for Solution should be administered once a week. The dose of PEGETRON® (ribavirin) Capsules to be used in combination with PEGETRON® (peginterferon alfa-2b) Powder for Solution is based on patient body weight. PEGETRON® (ribavirin) Capsules are to be administered orally each day in two divided doses with food (morning and evening).
Recommended Dose for Treatment Naïve Patients Infected with HCV Genotype 1
PEGETRON® (peginterferon alfa-2b) Powder for Solution: 1.5 mcg/kg/week
PEGETRON® (ribavirin) Capsules: 800 - 1,400 mg daily based upon patient weight
Table 6 - PEGETRON® Dosing Recommendations for Treatment Naïve Patients Infected with HCV Genotype 1‡
Patient Weight (kg) | PEG2b Powder for Solution | ribavirin Capsules | ||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|
Weekly Dose (mcg/kg) | Vial or CLEARCLICK™ Size (mcg/0.5 mL)1¥ | Daily Dose (mg) | Number of Capsules (200 mg) | |||||||||
| < 40 | 1.5 | 50 | 800 | 2 x 200 mg capsules A.M. 2 x 200 mg capsules P.M. | ||||||||
| 40 to 50 | 1.5 | 80 | 800 | 2 x 200 mg capsules A.M. 2 x 200 mg capsules P.M. | ||||||||
| 51 to 65 | 1.5 | 100 | 800 | 2 x 200 mg capsules A.M. 2 x 200 mg capsules P.M. | ||||||||
| 66 to 80 | 1.5 | 120 | 1,000 | 2 x 200 mg capsules A.M. 3 x 200 mg capsules P.M. | ||||||||
| 81 to 105 | 1.5 | 150 | 1,200 | 3 x 200 mg capsules A.M. 3 x 200 mg capsules P.M. | ||||||||
| > 105 | 1.5 | * | 1,400 | 3 x 200 mg capsules A.M. 4 x 200 mg capsules P.M. | ||||||||
PEG2b = peginterferon alfa-2b
‡: The daily dose for PEGETRON® (ribavirin) Capsules approximately falls within 13 ± 2 mg/kg/day.
1: When reconstituted as instructed
*: Should be calculated based on the body weight of an individual patient
¥: PEGETRON® (peginterferon alfa-2b) Powder for Solution in vials is available in the following strengths: 50 mcg/0.5 mL & 150 mcg/0.5 mL.
PEGETRON® (peginterferon alfa-2b) Powder for Solution in CLEARCLICK™ delivery system is not available in the 50 mcg/0.5 mL strength.
Recommended Dose for Treatment Naïve Patients Infected with HCV non-Genotype 1
PEGETRON® (peginterferon alfa-2b) Powder for Solution: 1.5 mcg/kg/week
PEGETRON® (ribavirin) Capsules: 800 - 1,200 mg daily based upon patient weight
Table 7 - PEGETRON® Dosing Recommendations for Treatment Naïve Patients Infected with HCV non-Genotype 1‡
Patient Weight (kg) | PEG2b Powder for Solution | ribavirin Capsules | |||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|
Weekly Dose (mcg/kg) | Vial or CLEARCLICK™ Size (mcg/0.5 mL)1¥ | Daily Dose (mg) | Number of Capsules (200 mg) | ||||||||
| < 40 | 1.5 | 50 | 800 | 2 x 200 mg capsules A.M. 2 x 200 mg capsules P.M. | |||||||
| 40 to 50 | 1.5 | 80 | 800 | 2 x 200 mg capsules A.M. 2 x 200 mg capsules P.M. | |||||||
| 51 to 65 | 1.5 | 100 | 800 | 2 x 200 mg capsules A.M. 2 x 200 mg capsules P.M. | |||||||
Patient Weight (kg) | PEG2b Powder for Solution | ribavirin Capsules |
|---|
Weekly Dose (mcg/kg) | Vial or CLEARCLICK™ Size (mcg/0.5 mL)1¥ | Daily Dose (mg) | Number of Capsules (200 mg) | |
|---|---|---|---|---|
| 66 to 85 | 1.5 | 120 | 1,000 | 2 x 200 mg capsules A.M. 3 x 200 mg capsules P.M. |
| > 85 | 1.5 | 150 | 1,200 | 3 x 200 mg capsules A.M. 3 x 200 mg capsules P.M. |
PEG2b = peginterferon alfa-2b
‡: The daily dose for PEGETRON® (ribavirin) Capsules approximately falls within 13 ± 2 mg/kg/day.
1: When reconstituted as instructed
¥: PEGETRON® (peginterferon alfa-2b) Powder for Solution in vials is available in the following strengths: 50 mcg/0.5 mL & 150 mcg/0.5 mL.
PEGETRON® (peginterferon alfa-2b) Powder for Solution in CLEARCLICK™ delivery system is not available in the 50 mcg/0.5 mL strength.
Recommended Dose for Retreatment of Prior Treatment Failures (Relapser and Non-responder Patients) Infected with Any HCV Genotypes
PEGETRON® (peginterferon alfa-2b) Powder for Solution: 1.5 mcg/kg/week
PEGETRON® (ribavirin) Capsules: 800 - 1,400 mg daily based upon patient weight
Table 8 - PEGETRON® Dosing Recommendations for Retreatment of Prior Treatment Failures (Relapser and Non-responder Patients) Infected with Any HCV Genotypes‡
Patient Weight (kg) | PEG2b Powder for Solution | ribavirin Capsules | ||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|
Weekly Dose (mcg/kg) | Vial or CLEARCLICK™ Size (mcg/0.5 mL)1 | Daily Dose (mg) | Number of Capsules (200 mg) | |||||||||
| < 40 | 1.5 | 50 | 800 | 2 x 200 mg capsules A.M. 2 x 200 mg capsules P.M. | ||||||||
| 40 to 50 | 1.5 | 80 | 800 | 2 x 200 mg capsules A.M. 2 x 200 mg capsules P.M. | ||||||||
| 51 to 65 | 1.5 | 100 | 800 | 2 x 200 mg capsules A.M. 2 x 200 mg capsules P.M. | ||||||||
| 66 to 85 | 1.5 | 120 | 1,000 | 2 x 200 mg capsules A.M. 3 x 200 mg capsules P.M. | ||||||||
| 86 to 105 | 1.5 | 150 | 1,200 | 3 x 200 mg capsules A.M. 3 x 200 mg capsules P.M. | ||||||||
| > 105 | 1.5 | * | 1,400 | 3 x 200 mg capsules A.M. 4 x 200 mg capsules P.M. | ||||||||
PEG2b = peginterferon alfa-2b
‡: The daily dose for PEGETRON® (ribavirin) Capsules approximately falls within 13 ± 2 mg/kg/day.
1: When reconstituted as instructed
*: Should be calculated based on the body weight of an individual patient
¥: PEGETRON® (peginterferon alfa-2b) Powder for Solution in vials is available in the following strengths: 50 mcg/0.5 mL & 150 mcg/0.5 mL.
PEGETRON® (peginterferon alfa-2b) Powder for Solution in CLEARCLICK™ delivery system is not available in the 50 mcg/0.5 mL strength.
Duration of Treatment
Naïve Patients
The recommended duration of treatment is 48 weeks. Duration should be individualized in accordance with the baseline characteristics of the disease, response to therapy, and tolerance of the regimen. Virological response by week 12 has been shown to be predictive for sustained response. After 12 weeks of treatment with no virologic response (HCV-RNA positive and < 2 log10 decrease from baseline) for an adult genotype 1 patient, discontinuation of treatment should be considered. After 24 weeks of treatment, virologic response (HCV-RNA below lower limit of detection) should be assessed. If a virologic response has not occurred by 24 weeks of treatment, PEGETRON® should be discontinued, as a virologic response is unlikely to occur after this time.
Therapeutic Milestones
Futility Rule at Week 12
If chronic hepatitis C genotype 1 adult patient fails to demonstrate an early virologic response (EVR), defined as either detectable HCV-RNA with at least a 2 log10 reduction from baseline in viral titer or undetectable HCV-RNA, at the end of 12 weeks of therapy, with peginterferon alfa-2b in combination with ribavirin, consideration should be given to treatment withdrawal.
Futility Rule at Week 24
Those chronic hepatitis C genotype 1 adult patients who had detectable HCV-RNA with at least a 2 log10 reduction in viral titer from baseline after 12 weeks of treatment, who fail to achieve undetectable HCV-RNA after 24 weeks of therapy, warrant withdrawal of treatment.
Retreatment of Prior Treatment Failures (Relapser and Non-responder Patients)
All patients, irrespective of genotype, who have demonstrated serum HCV-RNA below the limits of detection at Week 12, should receive 48 weeks of therapy. Retreated patients who fail to achieve undetectable HCV-RNA at Week 12 of therapy are highly unlikely to become sustained virological responders after 48 weeks of therapy and discontinuation of therapy should be considered (see CLINICAL TRIALS section).
Dose Modification
In general, the dosage may be adjusted according to the patient’s tolerance to the medication. If severe adverse reactions or laboratory abnormalities develop during the course of treatment, the dosage should be modified or therapy should be temporarily discontinued until the adverse reactions abate. If persistent or recurrent intolerance develops despite adequate dosage adjustment, or if the disease progresses rapidly, treatment with PEGETRON® should be discontinued.
Dose Modification for Naïve Patients Infected with HCV Genotype 1
It is recommended that a patient whose hemoglobin level falls below 10g/dL have his/her PEGETRON® (ribavirin) Capsules dose reduced (see Table 9). A patient whose hemoglobin level falls below 8.5g/dL should be permanently discontinued from PEGETRON® therapy.
Table 9 - PEGETRON® (ribavirin) Capsules Dose Reduction for Naïve Patients Infected with HCV Genotype 1
Starting dose (mg) | Dose after 1st dose reduction (mg) | Dose after 2nd dose reduction, if required (mg) |
| 800 | 600 | 400 |
| 1,000 | 800 | 600 |
| 1,200 | 1,000 | 800 |
| 1,400 | 1,000 | 800 |
For patients with a history of stable cardiovascular disease, a PEGETRON® (ribavirin) Capsule dose reduction is required if the hemoglobin decreases by ≥ 2 g/dL during any 4 week period. In addition, for these cardiac history patients, if the hemoglobin remains < 12 g/dL after 4 weeks on a reduced dose, the patient should discontinue PEGETRON® therapy.
It is recommended that a patient whose neutrophil count falls below 0.75 x 10⁹/L, have his/her PEGETRON® (peginterferon alfa-2b) Powder for Solution dose reduced (see Table 10). A patient whose neutrophil count falls below 0.5 x 10⁹/L should be permanently discontinued from PEGETRON® therapy.
Table 10 -PEGETRON® (peginterferon alfa-2b) Powder for Solution Dose Reduction for Naïve Patients Infected with HCV Genotype 1
Starting dose (mcg/kg/week) | Dose after 1st dose reduction (mcg/kg/week) | Dose after 2nd dose reduction, if required (mcg/kg/week) |
| 1.5 | 1 | 0.5 |
The following guidelines for dose modification were developed in clinical trials based on laboratory values:
Table 11 - Dose Modification for Naïve Patients Infected with HCV Genotype 1
| Reduce ribavirin dose, if*: | Reduce PEG2b if§: | Discontinue combination therapy if: | |||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|
| Hemoglobin in patients without history of cardiac disease | 8.5 to < 10 g/dL | - | < 8.5 g/dL | ||||||||
| Hemoglobin in patients with history of cardiac disease ± | ≥ 2 g/dL decrease in hemoglobin during any 4-week period during treatment (permanent dose reduction) | < 8.5 g/dl or < 12 g/dL after 4 weeks of dose reduction | |||||||||
| White blood cell count | - | 1.0 to < 1.5 x 10⁹/L | < 1.0 x 10⁹/L | ||||||||
| Neutrophil count | - | 0.5 to < 0.75 x 10⁹/L | < 0.5 x 10⁹/L | ||||||||
| Platelet count | - | 25 to < 50 x 109/L | < 25 x 109/L | ||||||||
| Bilirubin - Direct | - | - | 2.5 x upper limit of normal | ||||||||
| Bilirubin - Indirect | > 5 mg/dL | - | > 4 mg/dL (for > 4 weeks) | ||||||||
| Creatinine | - | - | > 2.0 mg/dL | ||||||||
| ALT/AST | - | - | 2 x baseline AND > 10 x upper limit of normal | ||||||||
PEG2b = peginterferon alfa-2b
*: Ribavirin dose reduction: 1st dose reduction of ribavirin for adult patients is by 200 mg/day except in patients receiving the 1,400 mg; it is by 400 mg/day. If needed, 2nd dose reduction of ribavirin is by an additional 200 mg/day. Patients whose dose of ribavirin is reduced to 600 mg daily receive one 200 mg capsule in the morning and two 200 mg capsules in the evening.
§: Peginterferon alfa-2b dose reduction: dose reduction of peginterferon alfa-2b should be implemented in increments of 0.5 mcg/kg/week.
± These guidelines are for patients with stable cardiac disease. Patients with a history of significant or unstable cardiac disease should not be treated with PEGETRON® See WARNINGS AND PRECAUTIONS.
Dose Modification for Naïve Patients Infected with HCV non-Genotype 1
For patients with a history of stable cardiovascular disease, a PEGETRON® (ribavirin) Capsules dose reduction to 600 mg/day (1 x 200 mg capsule in AM and 2 x 200 mg capsules in PM) is required if the hemoglobin decreases by ≥ 2g/dL during any 4 week period. In addition, for these cardiac history patients, if the hemoglobin remains < 12g/dL after 4 weeks on a reduced dose, the patient should discontinue PEGETRON® therapy.
It is recommended that a patient whose hemoglobin level falls below 10g/dL have his/her PEGETRON® (ribavirin) Capsules dose reduced to 600 mg daily. A patient whose hemoglobin level falls below 8.5g/dL should be permanently discontinued from PEGETRON® therapy.
It is recommended that a patient whose neutrophil count falls below 0.75 x 10⁹/L, have his/her PEGETRON® (peginterferon alfa-2b) Powder for Solution dose reduced to 0.75 mcg/kg/week. A patient whose neutrophil count falls below 0.5 x 10⁹/L should be permanently discontinued from PEGETRON® therapy.
The following guidelines for dose modification were used in clinical trials:
Table 12 - Dose Modification for Naïve Patients Infected with HCV non-Genotype 1
| Reduce PEGETRON® (ribavirin) Capsules dose to 600 mg/day*, if: | Reduce PEG2b Powder for Solution to one-half dose if: | Permanent Discontinuation of PEGETRON® therapy if: | ||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Hemoglobin in patients without history of cardiac disease | 8.5 to < 10 g/dL | - | < 8.5 g/dL | |||||||||||
| Hemoglobin in patients with history of cardiac disease± | ≥ 2 g/dL decrease in hemoglobin during any 4-week period during treatment (permanent dose reduction) | < 8.5 g/dl or < 12 g/dL after 4 weeks of dose reduction | ||||||||||||
| White blood cell count | - | 1.0 to < 1.5 x 10⁹/L | < 1.0 x 10⁹/L | |||||||||||
| Neutrophil count | - | 0.5 to < 0.75 x 10⁹/L | < 0.5 x 10⁹/L | |||||||||||
| Platelet count | - | 50 to < 80 x 109/L | < 50 x 109/L | |||||||||||
| Bilirubin - Direct | - | - | 2.5 x upper limit of normal | |||||||||||
| Bilirubin - Indirect | > 5 mg/dL | - | > 4 mg/dL (for > 4 weeks) | |||||||||||
| Creatinine | - | - | > 2.0 mg/dL | |||||||||||
| ALT/AST | - | - | 2 x baseline AND > 10 x upper limit of normal | |||||||||||
PEG2b = peginterferon alfa-2b
*: Patients whose dose of PEGETRON® (ribavirin) Capsules is reduced to 600 mg daily receive one 200 mg capsule in the morning and two 200 mg capsules in the evening.
± These guidelines are for patients with stable cardiac disease. Patients with a history of significant or unstable cardiac disease should not be treated with PEGETRON® See WARNINGS AND PRECAUTIONS.
Dose Modification for Retreatment of Prior Treatment Failures (Relapser and Non-responder Patients) Infected with Any HCV Genotypes
It is recommended that a patient whose hemoglobin level falls below 10g/dL have his/her PEGETRON® (ribavirin) Capsules dose reduced (see Table 13). A patient whose hemoglobin level falls below 8.5g/dL should be permanently discontinued from PEGETRON® therapy.
Table 13 - Dose Modification for Retreatment of Prior Treatment Failures (Relapser and Non-responder Patients) Infected with Any HCV Genotypes
Starting dose (mg) | Dose after 1st dose reduction (mg) | Dose after 2nd dose reduction, if required (mg) |
| 800 | 600 | 400 |
| 1,000 | 800 | 600 |
| 1,200 | 800 | 600 |
| 1,400 | 1,000 | 800 |
For patients with a history of stable cardiovascular disease, a PEGETRON® (ribavirin) Capsule dose reduction is required if the hemoglobin decreases by ≥ 2 g/dL during any 4 week period. In addition, for these cardiac history patients, if the hemoglobin remains < 12 g/dL after 4 weeks on a reduced dose, the patient should discontinue PEGETRON® therapy.
It is recommended that a patient whose neutrophil count falls below 0.75 x 10⁹/L, have his/her PEGETRON® (peginterferon alfa-2b) Powder for Solution dose reduced (see Table 14). A patient whose neutrophil count falls below 0.5 x 10⁹/L should be permanently discontinued from PEGETRON® therapy.
Table 14 - PEGETRON® (peginterferon alfa-2b) Powder for Solution Dose Reduction for Retreatment of Prior Treatment Failures (Relapser and Non-responder Patients) Infected with Any HCV Genotypes
Starting dose (mcg/kg/week) | Dose after 1st dose reduction (mcg/kg/week) | Dose after 2nd dose reduction, if required (mcg/kg/week) |
| 1.5 | 1 | 0.5 |
The following guidelines for dose modification were used in clinical trials:
Table 15 - Dose Modification for Retreatment of Prior Treatment Failures (Relapser and Non-responder Patients) Infected with Any HCV Genotypes
| Reduce ribavirin dose, if*: | Reduce PEG2b if§: | Discontinue combination therapy if: | |||||||||
| Hemoglobin in patients without history of cardiac disease | 8.5 to < 10 g/dL | - | < 8.5 g/dL | ||||||||
| Hemoglobin in patients with history of cardiac disease± | ≥ 2 g/dL decrease in hemoglobin during any 4-week period during treatment (permanent dose reduction) | < 8.5 g/dl or < 12 g/dL after 4 weeks of dose reduction | |||||||||
| White blood cell count | - | 1.0 to < 1.5 x 10⁹/L | < 1.0 x 10⁹/L | ||||||||
| Neutrophil count | - | 0.5 to < 0.75 x 10⁹/L | < 0.5 x 10⁹/L | ||||||||
| Platelet count | - | 25 to < 50 x 109/L | < 25 x 109/L | ||||||||
| Bilirubin - Direct | - | - | 2.5 x upper limit of normal | ||||||||
| Bilirubin - Indirect | > 5 mg/dL | - | > 4 mg/dL (for > 4 weeks) | ||||||||
| Creatinine | - | - | > 2.0 mg/dL | ||||||||
| ALT/AST | - | - | 2 x baseline AND > 10 x upper limit of normal | ||||||||
PEG2b = peginterferon alfa-2b
*: Ribavirin dose reduction: 1st dose reduction of ribavirin for adult patients is by 200 or 400 mg/day depending on starting dose (see Table 13). Patients whose dose of ribavirin is reduced to 600 mg daily receive one 200 mg capsule in the morning and two 200 mg capsules in the evening.
§: Peginterferon alfa-2b dose reduction: dose reduction of peginterferon alfa-2b should be implemented in increments of 0.5 mcg/kg/week.
± These guidelines are for patients with stable cardiac disease. Patients with a history of significant or unstable cardiac disease should not be treated with PEGETRON® See WARNINGS AND PRECAUTIONS.
Concomitant Therapy
Acetaminophen has been used successfully to alleviate the symptoms of fever and headache, which can occur with peginterferon alfa-2b therapy. The recommended acetaminophen dosage is 500 mg to 1 g given 30 minutes before administration of PEGETRON® (peginterferon alfa-2b) Powder for Solution. The maximum dosage of acetaminophen to be given is 1 g four times daily. In order to properly assess the source of fever, adjunctive acetaminophen should be limited to a maximum of 5 consecutive days unless otherwise specified by the prescribing physician.
Reconstitution
To Reconstitute the PEGETRON® (peginterferon alfa-2b) Powder for Solution in Vials
Each vial of PEGETRON® (peginterferon alfa-2b) Powder for Solution must be reconstituted with 0.7 mL of the accompanying Sterile Water for Injection to give a final volume of 0.74 mL for administration of up to 0.5 mL of solution. The reconstituted solutions will have concentrations of 100, 160, 200, 240 and 300 mcg/mL respectively.
To reconstitute use a sterilized syringe and injection needle, inject 0.7 mL of diluent slowly, into the vial of PEGETRON® (peginterferon alfa-2b) Powder for Solution aiming the stream of liquid at the glass wall of the vial. It is best not to aim the stream directly at the white solid or powder, or to inject the liquid quickly, as this causes a greater amount of bubbles. The solution may appear cloudy or bubbly for a few minutes. Swirl the vial gently to complete dissolution of the powder. Do not shake, but gently turn the vial upside down. The contents should now be completely dissolved. Once the solution has settled and all bubbles have risen to the top of the solution, you should have a clear solution with a small ring of tiny bubbles around the top. The appropriate dose can now be withdrawn with a sterilized injection syringe and injected. A small volume is lost during preparation of PEGETRON® (peginterferon alfa-2b) solution when the dose is measured and injected. Thus, each unit contains an excess amount of diluent and PEGETRON® (peginterferon alfa-2b) Powder for Solution to ensure delivery of the labeled dose in 0.5 mL of PEGETRON® (peginterferon alfa-2b) Injection. The labeled strength will be contained in 0.5 mL of the reconstituted solution. The reconstituted solution for each of the available strengths will have a concentration of 50 mcg/0.5 mL, 80 mcg/0.5 mL, 100 mcg/0.5 mL, 120 mcg/0.5 mL or 150 mcg/0.5 mL.
As for all parenteral medicinal products, inspect visually the reconstituted solution prior to administration. Do not use if discoloration is present. Discard any unused solution. PEGETRON® (peginterferon alfa-2b) Powder for Solution must not be mixed with other injectable products.
Incompatibilities: PEGETRON® (peginterferon alfa-2b) Powder for Solution should only be reconstituted with Sterile Water for Injection and must not be mixed with other medicinal products.
PEGETRON® (peginterferon alfa-2b) Powder for Solution vials are single dose vials. Once reconstituted, use immediately (see Storage of PEGETRON® (peginterferon alfa-2b) Powder for Solution section).
To Reconstitute the PEGETRON® (peginterferon alfa-2b) Powder for Solution in CLEARCLICK™ Delivery System
Before you inject PEGETRON® (peginterferon alfa-2b) Powder for Solution using the CLEARCLICK™ Single Dose Delivery System, the two-chamber cartridge must be activated, to mix (reconstitute) the powder with the sterile diluent to form a solution. The powder must be completely dissolved. The appropriate PEGETRON® dose should be properly dialed and injected subcutaneously. Detailed steps for reconstitution and administration are provided in the Consumer Information (Part III).
As for all parenteral medicinal products, inspect visually the reconstituted solution prior to administration. Do not use if discoloration is present.
PEGETRON® should be administered at room temperature.
OVERDOSAGE
Distinction between the therapeutic dose of peginterferon alfa-2b and overdose has not been clearly defined. Symptoms of overdose may include amplification of the adverse effects, notably “flu-like” symptoms, leukopenia or thrombocytopenia and increased serum liver enzyme levels. The severity of the adverse reactions can be ameliorated by adjusting the dose level and schedule, or in some cases termination of peginterferon alfa-2b therapy. Cardiovascular side effects such as hypotension and arrhythmia may require supportive therapy.
There is limited experience with overdosage. The primary effects of overdose were an increased incidence and severity of AEs reported at the therapeutic doses of PEGETRON®. Serious adverse events reported in cases of PEGETRON® overdose include affect lability, anemia, anxiety, ataxia, bursitis, dehydration, depression, fatigue, hallucination, hallucination auditory, hyperesthesia, hypothyroidism, mental disorder, myalgia, nausea, non-accidental overdose, neutropenia, paranoia, pneumonia, pyrexia, suicidal ideation, suicide attempt, thyroid disorder, urinary tract infection, and vomiting. In cases of overdoses, symptomatic treatment and close observation of the patient are recommended (see DOSAGE AND ADMINISTRATION; Dose modification section).
In ribavirin plus interferon alfa-2b clinical trials, the maximum overdose reported was 10g of ribavirin capsules (50 x 200 mg capsules) taken with a dose of 39 million units of interferon alfa-2b (13 subcutaneous injections of 3 million IU each). The patient was observed for two days in the emergency room during which time no AE from the overdose was noted.
Absorption of ribavirin is generally complete after one hour. Treatment of overdose with ribavirin consists of general supportive measures including monitoring of vital signs and observation of clinical status of the patient. There is no specific antidote for overdose with ribavirin. Although no data currently exists, administration of activated charcoal may be used to aid in the removal of unabsorbed drug. Ribavirin concentration is essentially unchanged by hemodialysis.
| For management of a suspected drug overdose, contact your regional Poison Control Centre. |
ACTION AND CLINICAL PHARMACOLOGY
Mechanism of Action
PEGETRON® (ribavirin) Capsules: The mechanism by which ribavirin exerts its effects against HCV is unknown. At physiologic concentrations, neither ribavirin nor its intracellular nucleotide metabolites have been shown to inhibit HCV-specific enzymes or HCV replication. Oral formulations of ribavirin monotherapy have been investigated as therapy for chronic hepatitis C in several clinical studies showing that ribavirin monotherapy had no effect on eliminating serum HCV or improving hepatic histology after 6 to 12 months of therapy and 6 months of follow up. However, when used in combination with peginterferon alfa-2b in the treatment of chronic hepatitis C, ribavirin has been shown to increase the efficacy of peginterferon alfa-2b used alone, as measured by reduction of viral load.
PEGETRON® (peginterferon alfa-2b) Powder for Solution: In vitro and in vivo studies suggest that the biological activity of peginterferon alfa-2b is derived from its interferon alfa-2b moiety. Interferons exert their cellular activities by binding to specific membrane receptors on the cell surface. Studies with other interferons have demonstrated species specificity. However, certain monkey species, e.g., Rhesus monkeys, are susceptible to pharmacodynamic stimulation upon exposure to human type I interferons. The results of several studies suggest that, once bound to the cell membrane, interferon initiates a complex sequence of intracellular events that include the induction of certain enzymes. It is thought that this process, at least in part, is responsible for the various cellular responses to interferon, including inhibition of virus replication in virus-infected cells, suppression of cell proliferation and such immunomodulation activities as enhancement of the phagocytic activity of macrophages and augmentation of the specific cytotoxicity of lymphocytes for target cells. Any or all of these activities may contribute to interferon’s therapeutic effects.
PEGETRON® (ribavirin plus peginterferon alfa-2b): The mechanism of inhibition of HCV-RNA by PEGETRON® therapy has not been established.
Pharmacokinetics
PEGETRON® (ribavirin) Capsules
Ribavirin is rapidly and extensively absorbed following oral administration. However, due to first-pass metabolism, absolute bioavailability is approximately 33 % - 64 %. There is a linear relationship between dose and AUCtf following single doses of 200-1,200 mg ribavirin. Volume of distribution is approximately 5,000 L. Based upon Cmax from single dose to 6 weeks, accumulation of ribavirin in plasma is approximately 4.7 fold, although steady state may not have been achieved at 6 weeks. Following oral dosing with 600 mg ribavirin BID, mean plasma concentrations of 2,200 (37 %) ng/mL were achieved. Upon discontinuation of dosing, the mean half-life was 298 (30 %) hours, which probably reflects slow elimination from non-plasma compartments.
Ribavirin has been shown to produce high inter- and intra-subject pharmacokinetic variability following single oral doses (intrasubject variability of approximately 30 % for both AUC and Cmax). This may be due to extensive first pass metabolism and transfer within and beyond the blood compartment.
Ribavirin transport into non-plasma compartments has been most extensively studied in red cells, and has been identified to be primarily via an es-type equilibrative nucleoside transporter. This type of transporter is present on virtually all cell types and may account for the high volume of distribution of ribavirin. The ratio of whole blood:plasma ribavirin concentrations is approximately 60:1; the excess of ribavirin in whole blood exists as ribavirin nucleotides sequestered in erythrocytes.
Ribavirin has two pathways of metabolism: (i) a reversible phosphorylation pathway in nucleated cells; and (ii) a degradative pathway involving deribosylation and amide hydrolysis to yield a triazole carboxamide metabolite. Ribavirin and its triazole carboxylic acid metabolites are excreted renally. Following oral administration of 600 mg of 14C-ribavirin, approximately 61 % and 12 % of the radioactivity was eliminated in the urine and feces, respectively, in 336 hours. Unchanged ribavirin accounted for 17 % of the administered dose.
Effect of Food on Absorption of Ribavirin: Both AUCt (AUC from time zero to last measurable concentration) and Cmax increased by 70 % when ribavirin was administered with a high fat meal (841 kcal, 53.8 g fat, 31.6 g protein, and 57.4 g carbohydrate) in a single-dose pharmacokinetic study. It is possible that the increased bioavailability in this study was due to delayed transit of ribavirin or modified pH. The clinical relevance of results from this single dose study is unknown. In the pivotal clinical efficacy trial, patients were instructed to take ribavirin with food to achieve the maximal plasma concentration of ribavirin.
PEGETRON® (peginterferon alfa-2b) Powder for Solution
Peginterferon alfa-2b is a well-characterized polyethylene glycol-modified (“pegylated”) derivative of interferon alfa-2b and is predominantly composed of monopegylated species with small amounts of dipegylated and free interferon alfa-2b. The plasma half-life of peginterferon alfa-2b is prolonged compared with non-pegylated interferon alfa-2b. Peginterferon alfa-2b has a potential to depegylate to free interferon alfa-2b. The biologic activity of the pegylated isomers is qualitatively similar to, but lower than that of free interferon alfa-2b.
Following subcutaneous administration, maximal serum concentrations occur between 15 - 44 hours post-dose, and are sustained for up to 48 - 72 hours post-dose. Peginterferon alfa-2b Cmax and AUC measurements increase in a dose-related manner. Mean apparent volume of distribution is 0.99 L/kg.
Upon multiple dosing, there is an accumulation of immunoreactive interferons. There is, however, only a modest increase in biologic activity as measured by a bioassay.
Mean peginterferon alfa-2b elimination half-life is approximately 40 hours, with apparent clearance of 22.0 mL/hr×kg. The mechanisms involved in clearance of interferons in man have not yet been fully elucidated. Based on a retrospective regression analysis of peginterferon alfa-2b CI/F and creatinine clearance, from an expanded database, it is estimated that renal clearance of peginterferon alfa-2b may account for approximately 30 % of the apparent clearance.
Pharmacokinetic Analysis of Combined Ribavirin and Peginterferon alfa-2b Administration: A ribavirin population pharmacokinetic analysis was conducted upon serum samples obtained at weeks 12, 24 and 48 during treatment with PEGETRON®. Based upon pharmacokinetic modeling, the recommended dose of 800/1,000/1,200 mg/day based on body weights of < 65/65 - 85/> 85 kg (in combination with peginterferon alfa-2b 1.5 mcg/kg), showed an overall 6.3 % improved sustained response1 rate relative to a fixed dose of 800 mg/day. The improved sustained response rate was larger (+7.4 %) in the patients with HCV Genotype 1 compared to patients with HCV Genotype non-1 (3.8 %).
The toxicity rate, defined as the percentage of patients with hemoglobin below 10.5 mg/dL at week four of treatment was only minimally increased by 2.5 % relative to a fixed dose of 800 mg/day. This increase in toxicity was considered mild and clinically manageable.
Peginterferon alfa-2b trough concentrations were obtained at weeks 12, 24 and 48 during treatment with PEGETRON®. The observed concentrations and the trend toward accumulation were similar to that observed previously with peginterferon alfa-2b monotherapy for chronic hepatitis C, supporting the lack of pharmacokinetic interaction between peginterferon alfa-2b and ribavirin.
Special Populations and Conditions
Pediatric: Specific pharmacokinetic evaluations in patients under 18 years of age were not performed. Safety and effectiveness of PEGETRON® in these patients have not been evaluated. PEGETRON® is indicated for the treatment of chronic hepatitis C only in patients 18 years of age or older.
Geriatrics: (≥ 65 years of age): In a single dose study using a subcutaneous dose of 1.0 mcg/kg, the pharmacokinetics of peginterferon alfa-2b were not affected by age. The study was not powered to detect specified differences between the age groups (20 - 45 years and 65 - 80 years). There does not appear to be a significant age-related effect on the pharmacokinetics of ribavirin. However, as in younger patients, renal function must be determined prior to the administration of PEGETRON® therapy.
Hepatic Function:
- PEGETRON® (ribavirin) Capsules: Single-dose pharmacokinetics of ribavirin in patients with mild, moderate or severe hepatic dysfunction (Child-Pugh classification A, B or C) showed a similar extent of absorption to that of normal controls.
- PEGETRON® (peginterferon alfa-2b) Powder for Solution: The pharmacokinetics of peginterferon alfa-2b have not been evaluated in patients with severe hepatic dysfunction. Therefore, PEGETRON® must not be used in these patients.
Renal Function:
- PEGETRON® (ribavirin) Capsules: Single-dose ribavirin pharmacokinetics were altered (increased AUCtf and Cmax) in patients with renal dysfunction compared with control subjects (creatinine clearance > 90 mL/minute). This appears to be due to reduction of apparent clearance in these patients.
- PEGETRON® (peginterferon alfa-2b) Powder for Solution: Renal clearance appears to account for 30 % of total clearance of peginterferon alfa-2b. In a single dose study (1.0 mcg/kg) in patients with impaired renal function, Cmax, AUC, and half-life increased in relation to the degree of renal impairment (see CONTRAINDICATIONS and WARNINGS AND
1 Sustained response was assessed by the response rate 24 weeks after the cessation of treatment
- PRECAUTIONS sections). Because of marked intra-subject variability in interferon pharmacokinetics, it is recommended that patients be monitored closely during treatment with PEGETRON® (see WARNINGS AND PRECAUTIONS section).
Patients with severe renal dysfunction (creatinine clearance < 50 mL/min) must not be treated with PEGETRON® (see CONTRAINDICATIONS section).
STORAGE AND STABILITY
Storage of PEGETRON® Packages:
Store the PEGETRON® (ribavirin) Capsules plus PEGETRON® (peginterferon alfa-2b) Powder for Solution package refrigerated between 2°C and 8°C (36°F to 46°F).
Storage of PEGETRON® (ribavirin) Capsules:
When separated, PEGETRON® (ribavirin) Capsules should be stored in the refrigerator between 2°C and 8°C (36°F to 46°F) or at room temperature between 15°C and 30°C (59°F to 86°F).
Storage of PEGETRON® (peginterferon alfa-2b) Powder for Solution:
When separated and before reconstitution, the individual carton of PEGETRON® (peginterferon alfa-2b) Powder for Solution should be stored in the refrigerator at 2°C to 8°C (36°F to 46°F). After reconstitution with Sterile Water for Injection, the reconstituted product is to be used immediately. Since no preservative is present, it is recommended that administration of the solution occur as soon as possible and within 3 hours of reconstitution. For reconstitution under controlled and validated aseptic conditions such as a hospital pharmacy, the chemical and physical in-use stability for the reconstituted solution has been demonstrated for 24 hours at 2°C - 8°C (36°F to 46°F). Discard any unused portion. Do not use past expiry date on the label.
Storage for PEGETRON® CLEARCLICK™ Delivery System:
When separated and before reconstitution, store the individual carton of PEGETRON® CLEARCLICK™ at 2°C to 8°C (36°F to 46°F). Once reconstituted PEGETRON® CLEARCLICK™ should be used immediately but may be stored at 2°C - 8°C for up to 24 hours. Do not freeze.
Do not use past expiry date on the label.
DOSAGE FORMS, COMPOSITION AND PACKAGING
Availability of Dosage Forms
Please refer to DOSAGE AND ADMINISTRATION for recommended dosing.
PEGETRON® (ribavirin) Capsules are available as opaque, white, hard gelatin capsules containing a white powder and printed with an S-P logo and “200 mg” in blue ink.
PEGETRON® (peginterferon alfa-2b) Powder for Solution in Vials: PEGETRON® (peginterferon alfa-2b) Powder for Solution is supplied as a white powder packaged in single-dose vials, which deliver either 50, or 150 mcg in each 0.5 mL. Each vial of diluent supplied with PEGETRON® (peginterferon alfa-2b) Powder for Solution contains 1 mL of Sterile Water for Injection.
PEGETRON® (peginterferon alfa-2b) Powder for Solution in CLEARCLICK™ Delivery System: PEGETRON® (peginterferon alfa-2b) CLEARCLICK™ Single Dose Delivery System consists of a dual-chamber glass cartridge with a chamber containing PEGETRON® as a white to off-white lyophilized powder and another chamber containing Sterile Water for Injection.
PEGETRON® is available in the following package presentations, which provide sufficient ribavirin and peginterferon alfa-2b for two weeks of PEGETRON® therapy:
Deliverable Dose 50 mcg/0.5 mL
A box containing 2 vials of PEGETRON® (peginterferon alfa-2b) Powder for Solution, 50 mcg/vial, with 2 vials of diluent containing 1 mL of Sterile Water for Injection, 4 syringes and 4 alcohol swabs; plus 1 box of 56 PEGETRON® (ribavirin) Capsules.
Deliverable Dose 80 mcg/0.5 mL
A box containing 2 PEGETRON® (peginterferon alfa-2b) CLEARCLICK™ Single Dose Delivery Systems, 80 mcg/CLEARCLICK™, with two 30-gauge push-on needles (0.3 x 8 mm), 4 alcohol swabs and two pen holders; plus 1 box of 56 PEGETRON® (ribavirin) Capsules.
Deliverable Dose 100 mcg/0.5 mL
A box containing 2 PEGETRON® (peginterferon alfa-2b) CLEARCLICK™ Single Dose Delivery Systems, 100 mcg/CLEARCLICK™, with two 30-gauge push-on needles (0.3 x 8 mm), 4 alcohol swabs and two pen holders; plus 1 box of 56 PEGETRON® (ribavirin) Capsules.
Deliverable Dose 120 mcg/0.5 mL
A box containing 2 PEGETRON® (peginterferon alfa-2b) CLEARCLICK™ Single Dose Delivery Systems, 120 mcg/CLEARCLICK™, with two 30-gauge push-on needles (0.3 x 8 mm), 4 alcohol swabs and two pen holders; plus 1 box of 70 PEGETRON® (ribavirin) Capsules.
Deliverable Dose 150 mcg/0.5 mL
- 1. A box containing 2 vials of PEGETRON® (peginterferon alfa-2b) Powder for Solution, 150 mcg/vial, with 2 vials of diluent containing 1 mL of Sterile Water for Injection, 4 syringes and 4 alcohol swabs; plus 1 box of 84 PEGETRON® (ribavirin) Capsules.
- 2. A box containing 2 PEGETRON® (peginterferon alfa-2b) CLEARCLICK™ Single Dose Delivery Systems, 150 mcg/CLEARCLICK™ with two 30-gauge push-on needles (0.3 x 8 mm), 4 alcohol swabs and two pen holders; plus 1 box of 84 PEGETRON® (ribavirin) Capsules.
- 3. A box containing 2 vials of PEGETRON® (peginterferon alfa-2b) Powder for Solution, 150 mcg/vial, with 2 vials of diluent containing 1 mL of Sterile Water for Injection, 4 syringes and 4 alcohol swabs; plus 1 box of 98 PEGETRON® (ribavirin) Capsules.
- 4. A box containing 2 PEGETRON® (peginterferon alfa-2b) CLEARCLICK™ Single Dose Delivery Systems, 150 mcg/CLEARCLICK™, with two 30-gauge push-on needles (0.3 x 8 mm), 4 alcohol swabs and two pen holders; plus 1 box of 98 PEGETRON® (ribavirin) Capsules.
Composition
(A) PEGETRON® (peginterferon alfa-2b) Powder for Solution in Vials: PEGETRON® (peginterferon alfa-2b) Powder for Solution is supplied as a lyophilized powder of peginterferon alfa-2b to deliver doses of 50 or 150 mcg in 0.5 mL of reconstituted solution. Each vial for single use contains 74 or 222 mcg peginterferon alfa-2b.
Each vial contains peginterferon alfa-2b as the active ingredient. When reconstituted as directed, each 0.5 mL contains 0.75 mg sodium phosphate dibasic anhydrous, 0.75 mg sodium phosphate monobasic dihydrate, 40 mg sucrose, and 0.05 mg polysorbate 80. The diluent provided for parenteral use is Sterile Water for Injection.
PEGETRON (peginterferon alfa-2b) Powder for Solution in CLEARCLICK™ Delivery System: PEGETRON® (peginterferon alfa-2b) Powder for Solution in CLEARCLICK™ Single Dose Delivery System consists of a dual-chamber glass cartridge with a sterile active chamber containing peginterferon alfa-2b as a white to off-white lyophilized powder and a diluent chamber containing Sterile Water for Injection. The cartridge is provided in a pen device for reconstitution, dose preparation and subcutaneous administration, to deliver doses of 80, 100, 120 or 150 mcg in 0.5 mL of reconstituted solution. Each CLEARCLICK™ contains 108, 135, 162 or 202.5 mcg peginterferon alfa-2b. Following reconstitution of the powder with the diluent contained within the cartridge, each CLEARCLICK™ gives a final volume of 0.675 mL for administration of up to 0.5 mL. The reconstituted solution contains 160, 200, 240, 300 mcg/mL respectively.
Each CLEARCLICK™ contains peginterferon alfa-2b as the active ingredient. When reconstituted, each 0.5 mL solution contains 0.75 mg sodium phosphate dibasic anhydrous, 0.75 mg sodium phosphate monobasic dihydrate, 40 mg sucrose, and 0.05 mg polysorbate 80.
(B) PEGETRON® (ribavirin) Capsules: Each PEGETRON® (ribavirin) Capsule contains 200 mg ribavirin. Non-medicinal ingredients are croscarmellose sodium, lactose monohydrate, magnesium stearate and microcrystalline cellulose. The capsule shell contains gelatin, sodium lauryl sulfate, silicon dioxide, and titanium dioxide.
PART II: SCIENTIFIC INFORMATION
PHARMACEUTICAL INFORMATION
Drug Substance
Proper Name:
(A) peginterferon alfa-2b
(B) ribavirin; 1-b-D-ribofuranosyl-H-1,2,4-triazole-3-carboxamide
Molecular Formula and Molecular Mass:
(A) peginterferon alfa-2b: see Structural Formula
31,994 daltons (with a distribution from 30,000 - 34,000 daltons due to PEG heterogeneity)
(B) ribavirin: C8H12N4O5
244.2 daltons
Structural Formula:
(A) peginterferon alfa-2b
Peginterferon alfa-2b is the covalent conjugate of recombinant interferon alfa-2b (IFN) with monomethoxypolyethylene glycol (PEG, average molecular weight of 12,000 daltons).
Peginterferon alfa-2b is predominantly composed of monopegylated species (one PEG molecule is attached to one interferon molecule), with only a small amount of dipegylated species. Fourteen different PEG attachment sites on the interferon molecule have been identified.
(B) ribavirin
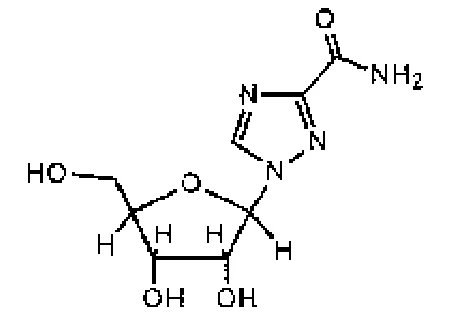
Physicochemical Properties:
- (A) The drug substance, peginterferon alfa-2b, is soluble in water and is a solution in 0.02 M sodium phosphate, pH 6.8, buffer. Before reconstitution, PEGETRON® Powder for Solution may appear either as a white, tablet shaped solid that is whole or in pieces, or as a white powder.
- (B) Ribavirin is a synthetic nucleoside. It is a white crystalline powder, freely soluble in water and slightly soluble in dehydrated alcohol, in a white opaque gelatin capsule.
CLINICAL TRIALS
Study 1: ribavirin plus peginterferon alfa-2b vs. ribavirin plus interferon alfa-2b
Study Demographics and Trial Design
Patients with confirmed chronic hepatitis C (HCV-RNA > 100 copies/mL by PCR), a liver biopsy consistent with a histological diagnosis of chronic hepatitis with no other cause for the chronic hepatitis, abnormal serum ALT and not previously treated with an alpha interferon, peginterferon or alpha interferon plus ribavirin were enrolled in a randomized, open-label, blinded observation study comparing peginterferon alfa-2b plus ribavirin to unpegylated interferon alfa-2b plus ribavirin. A total of 1,530 naïve patients were treated for 48 weeks with one of the following combination regimens:
- 511 with peginterferon alfa-2b (1.5 mcg/kg/week) plus ribavirin (800 mg/day) for 48 weeks;
- 514 with peginterferon alfa-2b (1.5 mcg/kg/week for 4 weeks followed by 0.5 mcg/kg/week for 44 weeks) plus ribavirin (1,000 or 1,200 mg/day based on body weight);
- 505 with interferon alfa-2b (3 MIU TIW) plus ribavirin (1,000 or 1,200 mg/day based on body weight) for 48 weeks.
Study Results
Efficacy
The pivotal efficacy and safety study demonstrated that peginterferon alfa-2b plus ribavirin is superior to the combination of interferon alfa-2b and ribavirin (Table 16), and was significantly more effective particularly in patients infected with genotype 1. Sustained response was assessed by the response rate 24 weeks after the cessation of treatment.
HCV genotype and baseline virus load are prognostic factors, which are known to affect response rates. However, response rates in this trial were shown to be dependent also on the dose of ribavirin administered in the combination. Response rates in those patients who received > 10.6 mg/kg ribavirin (800 mg dose in a typical 75 kg patient), regardless of genotype or viral load, were significantly higher than in those patients who received ≤ 10.6 mg/kg ribavirin (Table 16). Response rates in patients who received > 13.2 mg/kg ribavirin were even higher.
The benefit of PEGETRON® was evident for both patients with developing cirrhosis or cirrhosis (55 %) and for those with minimal fibrosis (61 %). In patients with developing cirrhosis or cirrhosis, the sustained virological response (SVR) rate was higher for patients treated with PEGETRON® than for those given the combination of interferon alfa-2b with ribavirin (55 % vs. 41 %).
Response rates in this trial were increased if patients were able to maintain compliance. Regardless of genotype, patients who received the recommended combination regimen and received ≥ 80 % of their treatment with peginterferon alfa-2b and ribavirin had a higher sustained response 24 weeks after the completion of 48 weeks of treatment than those who took < 80 % of their treatment (72 % vs. 46 %).
Table 16 - Sustained Response Rates with Combination Treatment (by ribavirin Dose [mg/kg])
| HCV Genotype | ribavirin dose (mg/kg) | P 1.5/R (%) | P 0.5/R (%) | I/R (%) |
|---|---|---|---|---|
| All Genotypes | All ≤ 10.6 > 10.6 | 54 50 61 | 47 41 48 | 47 27 47 |
| Genotype 1 | All ≤ 10.6 > 10.6 | 42 38 48 | 34 25 34 | 33 20 34 |
Genotype 1 ≤ 2 million copies/mL | All ≤ 10.6 > 10.6 | 73 74 71 | 51 25 52 | 45 33 45 |
Genotype 1 > 2 million copies/mL | All ≤ 10.6 > 10.6 | 30 27 37 | 27 25 27 | 29 17 29 |
| Genotype 2/3 | All ≤ 10.6 > 10.6 | 82 79 88 | 80 73 80 | 79 50 80 |
P 1.5/R = peginterferon alfa-2b 1.5 mcg/kg + ribavirin 800 mg
P 0.5/R = peginterferon alfa-2b 1.5 to 0.5 mcg/kg + ribavirin 1,000/1,200 mg
I/R = interferon alfa-2b 3 MIU + ribavirin 1,000/1,200 mg
Safety
There are no unique AEs with ribavirin plus peginterferon alfa-2b that have not already been reported with the combination of interferon alfa-2b and ribavirin. With the exception of injection site reactions and some “flu-like” symptoms, the frequency of the common AEs is essentially the same with the two combinations. The increase in the incidence of some “flu-like” effects with the peginterferon alfa-2b 1.5 mcg/kg dose is not unexpected, given the higher dose of interferon alfa-2b being administered. Furthermore, optimization of the ribavirin does not appear to adversely affect the safety profile.
Anemia is ribavirin dose-related and, as would be expected, the higher optimized dose of ribavirin results in a greater fall in hemoglobin levels, but this is managed by dose-modification of ribavirin. Neutropenia is interferon dose-related, and is slightly increased by co-administration of the optimized dose of ribavirin. But, as with anemia, it is easily managed by dose modification and does not appear to have clinical sequelae.
Study 2 (IDEAL): ribavirin plus peginterferon alfa-2b vs. ribavirin plus peginterferon alfa-2a
Study Demographics and Trial Design
A large randomized trial in 3,070 treatment-naïve adults with chronic hepatitis C genotype 1 treated for 48 weeks with two peginterferon alfa-2b/ribavirin regimens [peginterferon alfa-2b 1.5 mcg/kg and 1.0 mcg/kg subcutaneously once weekly both in combination with ribavirin 800 to 1,400 mg p.o. daily (in two divided doses)] and peginterferon alfa-2a 180 mcg subcutaneously once weekly with ribavirin 1,000 to 1,200 mg p.o. daily (in two divided doses). Response to the treatment was defined as undetectable HCV-RNA (Roche COBAS TaqMan assay, a lower limit of quantitation of 27 IU/mL) at 24 weeks post-treatment (see Table 18). The IDEAL study was double-blinded for the peginterferon alfa-2b dose arms and open-label for the peginterferon alfa-2a dose arm.
Table 17 - Summary of Patient Demographics and Trial Design for IDEAL Study
| Study # | Study design | Dosage, route of administration and duration | Study subjects | Mean age | Gender |
| P03471 | randomized; blinded for PEG2b dose arms and open-label for PEG2a and R | Dosage:
Duration: up to 48 weeks | Total: n = 3,070 PEG2b 1.5/R: n = 1,019 PEG2b 1.0/R: n = 1,016 PEG2a/R: n = 1,035 | PEG2b 1.5/R: 47.5 years PEG2b 1.0/R: 47.5 years PEG2a/R: 47.6 years | PEG2b 1.5/R: Men: 613 Women: 406 PEG2b 1.0/R: Men: 607 Women: 409 PEG2a/R: Men: 613 Women: 422 |
PEG2b 1.5/R = peginterferon alfa- 2b 1.5 mcg/kg/week plus ribavirin
PEG2b 1.0/R = peginterferon alfa-2b 1.0 mcg/kg/week plus ribavirin
PEG2a/R = peginterferon alfa-2a 180 mcg/week plus ribavirin
R = ribavirin
Study Results
Table 18 - Virologic Response at End of Treatment, Sustained Virological Response and Relapse Rate
| Treatment Group | % (number) of Subjects | ||||||||||||||||
PEG 2b 1.5/R (Arm 1) | PEG 2b 1.0/R (Arm 2) | PEG 2a 180 mcg/R (Arm 3) | Arm 1 vs. Arm 3 | Arm 1 vs. Arm 2 | Arm 2 vs. Arm 3 | ||||||||||||
P value | Adj Diffb % (95 % CI) | P value | Adj Diffb % (95 % CI) | P value | Adj Diffb % (95 % CI) | ||||||||||||
| EOTa | 53.2 (542/1,019) | 49.2 (500/1,016) | 64.4 (667/1,035) | < 0.001 | -11.5 (-15.6, -7.4) | 0.035 | 3.9 (-0.3, 8.1) | < 0.001 | -15.5 (-19.6, -11.4) | ||||||||
| SVRa | 39.8 (406/1,019) | 38.0 (386/1,016) | 40.9 (423/1,035) | 0.567 | -1.1 (-5.3, 3.0) | 0.195 | 1.8 (-2.3, 6.0) | 0.151 | -3.0 (-7.2, 1.1) | ||||||||
| Relapsec | 23.5 (123/523) | 20.0 (95/475) | 31.5 (193/612) | 0.012 | -8.0 (-13.2, -2.8) | 0.236 | 3.5 (-1.6, 8.6) | < 0.001 | -11.5 (-16.7, -6.4) | ||||||||
PEG2b 1.5/R = peginterferon alfa- 2b 1.5 mcg/kg/week plus ribavirin
PEG2b 1.0/R = peginterferon alfa-2b 1.0 mcg/kg/week plus ribavirin
PEG2a 180mcg/R = peginterferon alfa-2a 180 mcg/week plus ribavirin
Adj Diff = adjusted difference in
CI = confidence interval
EOT = end of treatment
SVR = sustained virological response
a: The p values and odds ratios are based on a logistic regression model that includes treatment and baseline stratification factors: viral load (≤ 600,000 IU/mL vs. > 600,000 IU/mL, measured by the SP laboratory) and race (Black vs. non-Black). Odds ratios (95 % confidence interval) for SVR are: Arm 1 vs. Arm 3: 0.95 (0.79, 1.14); Arm 1 vs. Arm 2: 1.08 (0.90, 1.30); Arm 2 vs. Arm 3: 0.88 (0.73, 1.05).
b: The adjusted differences between treatment arms and associated 95 % CIs are based on Cochran-Mantel-Haenszel proportions adjusting for baseline viral load (≤ 600,000 IU/mL vs. > 600,000 IU/mL, measured by the SP laboratory) and race (Black vs. non-Black).
c: The p values for relapse are based on a final multiple logistic regression model developed using a stepwise procedure to select variables (significance level of 0.05 for variables to both enter and stay in the final model) from a set of potential factors that included treatment and various baseline demographic and disease characteristics.
Note: Sensitivity analysis was conducted to include subjects with undetectable HCV-RNA at EOT with missing Follow-up Week (FW) 12 and FW 24 HCV-RNA levels, but who had FW 4 HCV-RNA results. Those with detectable HCV-RNA levels at FW 4 and the expected number of relapsers in those with undetectable HCV-RNA levels at FW 4 was estimated using proportional imputation for each treatment arm. These data were incorporated in the relapse rate calculation resulting in ‘adjusted’ relapse rates of 23.3 % in the PEG2b 1.5/R arm, 20.2 % in the PEG2b 1.0/R arm and 32.0 % in the PEG2a/R arm.
In patients with undetectable HCV-RNA at Treatment Week 12 (TW12) who received peginterferon alfa-2b (1.5 mcg/kg)/ribavirin, the SVR rate was 80.6 % (328/407).
In all three treatment groups, SVR rates were similar. This was also seen when evaluating the subgroups with high viral load. In the majority of patients with poor prognostic factors, treatment with peginterferon alfa-2b (1.5 mcg/kg)/ribavirin combination therapy resulted in a higher SVR rate compared to peginterferon alfa-2b 1.0 mcg/kg dose.
For the peginterferon alfa-2b 1.5 mcg/kg plus ribavirin regimen, SVR rates were lower in patients with cirrhosis, in patients with normal ALT levels, in patients with a baseline viral load 600,000 IU/mL, and in patients > 40 years old. Caucasian patients had a higher SVR rate compared to African-Americans.
Among patients with undetectable HCV-RNA at the end of treatment, the relapse rate was 23.5 %.
In this trial, lack of EVR by TW 12 (undetectable HCV-RNA or ≥ 2 log10 reduction from baseline) was the criteria for discontinuation of treatment.
Predictive value of in-treatment virologic response in Genotype 1 naïve patients was analyzed at treatment weeks 4 and 12 (see Table 19).
Table 19 - Predictive Value of In-Treatment Virologic Response in Genotype 1 Patients while on peginterferon alfa-2b 1.5 mcg/kg/ribavirin 800-1,400 mg Combination Therapy
| Negative | Positive | |||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|
| No response at Treatment Week | No Sustained Response | Predictive Value | Response at Treatment Week | Sustained Response | Predictive Value | |||||||
| Genotype 1* | ||||||||||||
| By Week 4** (n = 950) | ||||||||||||
| HCV-RNA negative | 834 | 539 | 65 % (539/834) | 116 | 107 | 92 % (107/116) | ||||||
| HCV-RNA negative or ≥ 1 log decrease in viral load | 220 | 210 | 95 % (210/220) | 730 | 392 | 54 % (392/730) | ||||||
| By Week 12** (n = 915) | ||||||||||||
| HCV-RNA negative | 508 | 433 | 85 % (433/508) | 407 | 328 | 81 % (328/407) | ||||||
| HCV-RNA negative or ≥ 2 log decrease in viral load | 206 | 205 | N/A† | 709 | 402 | 57 % (402/709) | ||||||
*: Genotype 1 received 48 weeks treatment
**: The presented results are from a single point of time. A patient may be missing or have had a different result for Week 4 or Week 12.
†: These criteria were used in the protocol: If Week 12 HCV-RNA is detectable and < 2 log10 decrease from baseline, patients to stop therapy. If Week 12 HCV-RNA is detectable and decreased ≥ 2 log10 from baseline, then retest HCV-RNA at Week 24 and if detectable, patients to stop therapy.
Relapse Rate
Response rates at the end of treatment as well as relapse rates were higher with peginterferon alfa-2a/ribavirin therapy than with either peginterferon alfa-2b regimen; however, the SVR rates reported at 24 weeks post-treatment were comparable between three treatment groups.
Using a multivariate regression model that employed a stepwise selection method, the predictors of relapse were similar to those identified in the SVR model, with assigned treatment regimen being the one notable addition (Figure 1).
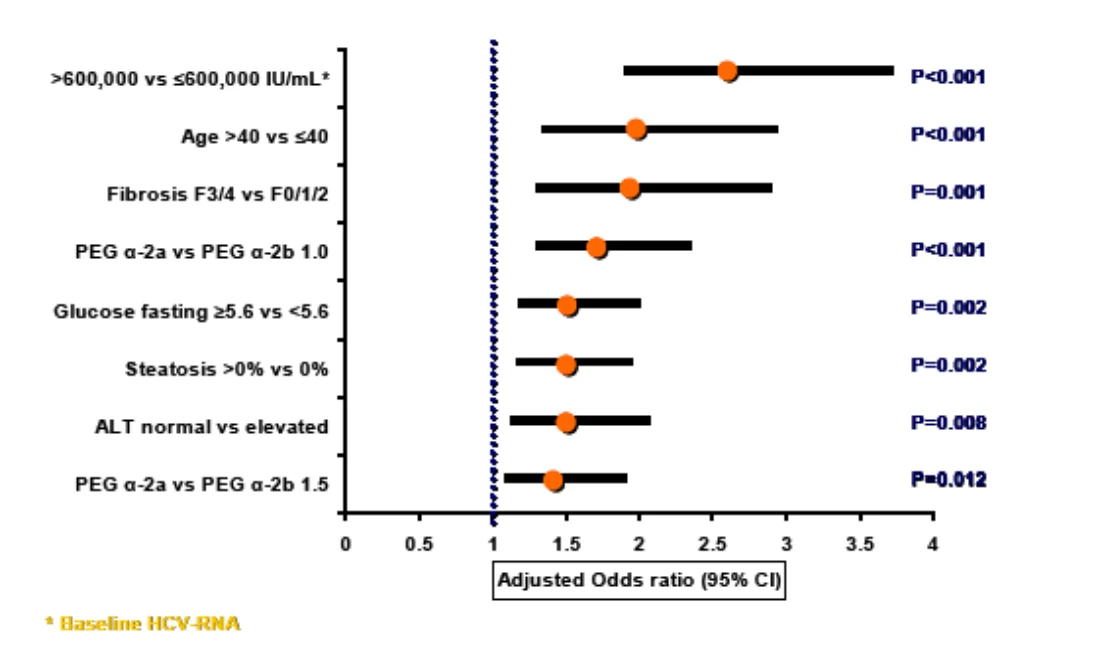
Figure 1 - Factors Significantly Affecting Relapse: Multivariate Logistic Regression Model Using the Stepwise Model Selection Method
Effect of Adherence to Treatment
In the IDEAL study, adherent subjects (defined as the 80/80/80 adherence evaluation: 80 % of both peginterferon and ribavirin (according to the assigned dosing regimen) for at least 80 % of treatment duration) who received the peginterferon alfa-2b 1.5/ribavirin regimen, had higher relative SVR rates (70.0 % [95 % CI: 65.7, 74.2]) compared to non-adherent subjects (28.9 % [95 % CI: 23.8, 34.0]).
Subjects in the lower dose peginterferon alfa-2b 1.0/ribavirin and the peginterferon alfa-2a/ribavirin groups who were adherent also had higher SVR rates than those who were non-adherent (74.0 % [95 % CI: 69.6, 78.1] vs. 27.2 % [95 % CI: 21.3, 33.1] and 61.4 % [95 % CI: 57.2, 65.5] vs. 32.8 % [95 % CI: 27.4, 38.1], respectively).
Predictability of Response
As shown in Table 20, subjects with an undetectable HCV-RNA level at Treatment Week 4 (TW4) who were treated with peginterferon alfa-2b 1.5 mg/kg/week had a SVR rate of 92.2 %. At week 12 and week 24, the responses were 80.6 % and 73.0 %, respectively. The positive predictive value (PPV) was higher in peginterferon alfa-2b 1.5/ribavirin arm than in the peginterferon alfa-2b 1.0/ribavirin arm and peginterferon alfa-2a/ribavirin arm; however SVR rates reported at 24 weeks post-treatment were similar for all three treatment groups (Table 20).
Table 20 - Positive Predictive Values at TW 4; TW 12 and TW 24
| Visit | % (Number) of Subjects | |
| PEG2b 1.5/R | ||
| PPV | 95 % CI | |
| Rapid Virologic Response: Undetectable at TW 4 | 92.2 (107/116) | 87.4, 97.1 |
| Complete EVR: Undetectable at TW 12a | 80.6 (328/407) | 76.7, 84.4 |
| Partial EVR ≥ 2 log reduction and Detectable at TW 12 and Undetectable at TW 24 | 44.6 (70/157) | 36.8, 52.4 |
| Undetectable at TW 24 | 73.0 (379/519) | 69.2, 76.8 |
PEG2b 1.5/R = peginterferon alfa-2b 1.5 mcg/kg/week plus ribavirin
PPV = positive predictive value
CI = confidence interval
TW = Treatment Week
EVR: Early Virologic Response
a: Sensitivity Analysis Week 12 PPV: Patients with missing data at FW 24 were included in the analysis if TW 12 and TW 48 were undetectable: PPVs at TW 12 is 82 %, 84 %, and 76 % for PEG2b 1.5/R, PEG2b 1.0/R, PEG2a/R.
Note: TW 4 and TW 12 HCV-RNA results are independent of one another.
Study 3 (EPIC): Retreatment of Prior Treatment Failures (Relapser and Non-responder Patients)
Study Demographics and Trial Design
In a single-arm trial, adult patients with moderate to severe fibrosis who failed previous treatment with combination of alpha interferon (pegylated or non-pegylated) and ribavirin, including non-responders and relapsers, were subsequently retreated with peginterferon alfa-2b, 1.5 mcg/kg subcutaneously, once weekly, in combination with body weight-adjusted ribavirin (800-1,400 mg/day, p.o.). Prior non-responders (n = 1,401) were defined as patients who were HCV-RNA positive at the end of a minimum 12 weeks of treatment and prior relapsers (n = 647) were defined as patients who were HCV-RNA negative at the end of a minimum 12 weeks of treatment and subsequently relapsed after post-treatment follow-up.
A total of 2,312 patients were eligible for safety analysis, while 2,293 patients were included in efficacy analysis. 943 patients (41 %) completed dosing of combination therapy and were treated for 48 weeks. 1,061 patients (46 %) were identified as virologic treatment failures after 12 weeks of treatment, were discontinued from the study by Treatment Week 18 and were eligible for other studies; 308 patients (13 %) were discontinued from the study due to other reasons.
Table 21 - Summary of Patient Demographics and Trial Design for EPIC Study
| Study # | Study design | Dosage, route of administration and duration | Study subjects | Mean age | Gender | METAVIR fibrosis category |
| P02370 | Open-label | Dosage: PEG2b 1.5 mcg/kg once weekly in combination with R 800 to 1,400 mg daily Route of administration: PEG2b: subcutaneously R: p.o. Duration: up to 48 weeks | n = 2,312 | 49.2 years | Men: 1,650 Women: 662 | F2: 658 F3: 676 F4: 974 |
PEG2b 1.5/R = peginterferon alfa- 2b 1.5 mcg/kg/week plus ribavirin
R = ribavirin
Study Results
Response to treatment was defined as undetectable HCV- RNA at 24 weeks post-treatment (Table 22).
Table 22 - Rates of Response to Retreatment in Prior Treatment Failures
PEG2b 1.5 mcg/kg once weekly ribavirin 800-1,400 mg daily | 99 % Confidence Interval % | |
| Overall response1,2 | 21.7 % (497/2,293) | 19.5, 23.9 |
| Genotype 1 | 14.6 % (270/1,846) | 12.5, 16.7 |
| Genotype 2 | 58.7 % (44/75) | 44.0, 73.3 |
| Genotype 3 | 54.5 % (159/292) | 46.9,62.0 |
| Genotype 4 | 28.4 % (19/67) | 14.2, 42.5 |
PEG2b = peginterferon alfa-2b
1: Plasma HCV RNA is measured with a research-based quantitative polymerase chain reaction assay by a central laboratory.
2: Nine subjects had missing/other genotypes.
Table 23 - SVR rates by baseline characteristics of prior treatment failures
| HCV Genotype/Metavir Fibrosis Score | SVR by Previous Response and Treatment for Overall Efficacy Population excluding subjects classified as “Treatment Failure” and Monotherapy Patients | ||||||||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Non-responder | Relapser | ||||||||||||||||||||
alpha interferon / ribavirin % (number of patients) | PEG2a / ribavirin % (number of patients) | PEG2b / ribavirin % (number of patients) | alpha interferon / ribavirin % (number of patients) | PEG2a / ribavirin % (number of patients) | PEG2b / ribavirin % (number of patients) | ||||||||||||||||
| Overall | 17.5 (158/903) | 5.6 (11/196) | 6.8 (19/280) | 43.3 (130/300) | 33.5 (55/164) | 32.2 (58/180) | |||||||||||||||
| HCV 1 | 12.9 (98/761) | 2.8 (5/178) | 5.5 (14/253) | 32.2 (67/208) | 19.2 (20/104) | 25.9 (36/139) | |||||||||||||||
| F2 | 17.8 (36/202) | 3.8 (2/52) | 7.7 (5/65) | 41.8 (33/79) | 26.5 (9/34) | 36.8 (14/38) | |||||||||||||||
| F3 | 16.3 (38/233) | 2.4 (1/42) | 4.3 (3/70) | 27.6 (16/58) | 10.3 (3/29) | 28.9 (11/38) | |||||||||||||||
| F4 | 7.4 (24/325) | 2.4 (2/84) | 5.1 (6/118) | 25.7 (18/70) | 19.5 (8/41) | 17.5 (11/63) | |||||||||||||||
| HCV 2/3 | 48.6 (53/109) | 35.7 (5/14) | 35.7 (5/14) | 66.7 (54/81) | 57.4 (31/54) | 55.3 (21/38) | |||||||||||||||
| F2 | 67.6 (23/34) | 50 (1/2) | 57.1 (4/7) | 76 (19/25) | 50.0 (5/10) | 75 (6/8) | |||||||||||||||
| F3 | 39.3 (11/28) | 33.3 (2/6) | 50 (1/2) | 66.7 (18/27) | 61.5 (8/13) | 62.5 (10/16) | |||||||||||||||
| F4 | 40.4 (19/47) | 33.3 (2/6) | 0 (0/5) | 58.6 (17/29) | 58.1 (18/31) | 35.7 (5/14) | |||||||||||||||
| HCV 4 | 17.2 (5/29) | 33.3 (1/3) | 0 (0/12) | 87.5 (7/8) | 60 (3/5) | 33.3 (1/3) | |||||||||||||||
PEG2a = peginterferon alfa-2a
PEG2b = peginterferon alfa-2b
SVR was higher among those with easy to treat baseline characteristics (HCV 2/3, F2) versus those with difficult to treat characteristics (HCV 1, F4). Patients with the following characteristics are less likely to benefit from retreatment after failing a course of combination therapy: previous non-response, previously treated with pegylated interferon therapy, significant bridging fibrosis or cirrhosis, or infection with HCV genotype 1.
Overall, approximately 36 % of interferon alpha (pegylated or non-pegylated) / ribavirin combination therapy subjects had undetectable plasma HCV-RNA levels at Week 12 of therapy. In this subgroup, there was an approximately 56 % SVR rate. The predictors of response in this subgroup were fibrosis score, baseline viral load and genotype. Patients with lower fibrosis scores, lower baseline viral load, or who were genotype 2 or genotype 3 were more likely to achieve a sustained response. Patients with undetectable HCV-RNA at TW12 who were previously treated with peginterferon alfa-2b/ribavirin attained similar rates of SVR to patients previously treated with peginterferon alfa-2a/ribavirin [50.7 % (76/150), 99 % CI 40.2, 61.2 and 50.0 % (61/122), 99 % CI 38.3, 61.7, respectively].
Patients with undetectable HCV-RNA at treatment Week 12 and SVR upon retreatment presented by baseline characteristics are summarized in Table 24.
Table 24 - Rates of Response to Retreatment in Prior Treatment Failures
| Patients with undetectable HCV–RNA at treatment Week 12 and SVR upon retreatment | |||||
|---|---|---|---|---|---|
| interferon alpha/ribavirin | peginterferon alpha/ribavirin | Overall Population* | |||
Response Week 12 % (n/N) | SVR % (n/N) 99 % CI | Response Week 12 % (n/N) | SVR % (n/N) 99 % CI | SVR % (n/N) 99 % CI | |
| Overall | 38.6 (549/1,423) | 59.4 (326/549) 54.0,64.8 | 31.5 (272/863) | 50.4 (137/272) 42.6, 58.2 | 21.7 (497/2,293) 19.5, 23.9 |
| Prior Response | |||||
| Relapse | 67.7 (203/300) | 59.6 (121/203) 50.7, 68.5 | 58.1 (200/344) | 52.5 (105/200) 43.4, 61.6 | 37.7 (243/645) 32.8, 42.6 |
| Genotype 1/4 | 59.7 (129/216) | 51.2 (66/129) 39.8, 62.5 | 48.6 (122/251) | 44.3 (54/122) 32.7, 55.8 | 28.6 (134/468) 23.3, 34.0 |
| Genotype 2/3 | 88.9 (72/81) | 73.6 (53/72) (60.2, 87.0) | 83.7 (77/92) | 64.9 (50/77) 50.9, 78.9 | 61.3 (106/173) 51.7, 70.8 |
| Non-responder | 28.6 (258/903) | 57.0 (147/258) 49.0, 64.9 | 12.4 (59/476) | 44.1 (26/59) 27.4, 60.7 | 13.6 (188/1,385) 11.2, 15.9 |
| Genotype 1/4 | 23.0 (182/790) | 51.6 (94/182) 42.1, 61.2 | 9.9 (44/446) | 38.6 (17/44) 19.7, 57.5 | 9.9 (123/1,242) 7.7, 12.1 |
| Genotype 2/3 | 67.9 (74/109) | 70.3 (52/74) 56.6, 84.0 | 53.6 (15/28) | 60.0 (9/15) 27.4, 92.6 | 46.0 (63/137) 35.0, 57.0 |
| Genotype | |||||
| 1 | 30.2 (343/1,135) | 51.3 (176/343) 44.4, 58.3 | 23.0 (162/704) | 42.6 (69/162) 32.6, 52.6 | 14.6 (270/1,846) 12.5, 16.7 |
| 2/3 | 77.1 (185/240) | 73.0 (135/185) 64.6, 81.4 | 75.6 (96/127) | 63.5 (61/96) 50.9, 76.2 | 55.3 (203/367) 48.6, 62.0 |
| 4 | 42.5 (17/40) | 70.6 (12/17) 42.1, 99.1 | 44.4 (12/27) | 50.0 (6/12) 12.8, 87.2 | 28.4 (19/67) 14.2, 42.5 |
| METAVIR Fibrosis Score | |||||
| Patients with undetectable HCV–RNA at treatment Week 12 and SVR upon retreatment |
|---|
| interferon alpha/ribavirin | peginterferon alpha/ribavirin | Overall Population* |
|---|
Response Week 12 % (n/N) | SVR % (n/N) 99 % CI | Response Week 12 % (n/N) | SVR % (n/N) 99 % CI | SVR % (n/N) 99 % CI | |
|---|---|---|---|---|---|
| F2 | 46.0 (193/420) | 66.8 (129/193) 58.1, 75.6 | 33.6 (78/232) | 57.7 (45/78) 43.3, 72.1 | 29.2 (191/653) 24.7, 33.8 |
| F3 | 38.0 (163/429) | 62.6 (102/163) 52.8, 72.3 | 32.4 (78/241) | 51.3 (40/78) 36.7, 65.9 | 21.9 (147/672) 17.8, 26.0 |
| F4 | 33.6 (192/572) | 49.5 (95/192) 40.2, 58.8 | 29.7 (116/390) | 44.8 (52/116) 32.9, 56.7 | 16.5 (159/966) 13.4, 19.5 |
| Baseline Viral Load | |||||
| High Viral Load (> 600,000 IU/mL) | 32.4 (280/864) | 56.1 (157/280) 48.4, 63.7 | 26.5 (152/573) | 41.4 (63/152) 31.2, 51.7 | 16.6 (239/1,441) 14.1, 19.1 |
| Low Viral Load (≤ 600,000 IU/mL) | 48.3 (269/557) | 62.8 (169/269) 55.2, 70.4 | 41.0 (118/288) | 61.0 (72/118) 49.5, 72.6 | 30.2 (256/848) 26.1, 34.2 |
NR = Non-responder defined as serum/plasma HCV-RNA positive at the end of a minimum of 12 weeks of treatment.
Plasma HCV-RNA is measured with a research-based quantitative polymerase chain reaction assay by a central laboratory.
*Intent to treat population includes 7 patients for whom at least 12 weeks of prior therapy could not be confirmed.
DETAILED PHARMACOLOGY
Pharmacodynamics
Ribavirin: Ribavirin is a synthetic nucleoside analog, which has shown in vitro activity against some, but not all, RNA and DNA viruses. Neither ribavirin nor its intracellular nucleotide metabolites at physiologic concentrations have been shown to inhibit HCV-specific enzymes or HCV replication. Ribavirin is not incorporated into either RNA or DNA, and ribavirin treatment per se does not induce endogenous synthesis of alpha interferons.
Peginterferon alfa-2b: In a rising single-dose study, interferon pharmacodynamics were assessed by examining changes in oral temperature, concentrations of effector proteins such as serum neopterin and 2’5’-oligoadenylate synthetase (2’5’-OAS), and white cell and neutrophil counts. Subjects treated with peginterferon alfa-2b showed mild dose-related elevations in body temperature with the maximum temperature and change (38.0°C and 2.0°C, respectively) occurring in the 0.7 mcg/kg dose group. In comparison, subjects treated with interferon alfa-2b (10 MIU) had average maximum body temperature and change from baseline values of 38.6°C and 2.7°C, respectively.
Peginterferon alfa-2b increased serum neopterin concentrations in a dose-dependent manner, and also increased 2’5’-OAS concentrations (although with no clear dose-relationship). Interferon alfa-2b increased concentrations of both effector proteins. Similar effects of peginterferon alfa-2b and interferon alfa-2b on hematological variables (white cell, neutrophil and platelet counts) were likewise observed. In the rising multiple-dose study, reductions in serum HCV-RNA levels were observed after administration of peginterferon alfa-2b.
Ribavirin plus peginterferon alfa-2b: Studies to date have not elucidated a mechanism of antiviral synergy between ribavirin and peginterferon alfa-2b that explains the increased efficacy of the combination in the treatment of chronic hepatitis C relative to either treatment alone.
Pharmacokinetics
Ribavirin: Ribavirin is rapidly absorbed following oral administration (mean Tmax = 1.5 hours), followed by rapid distribution and prolonged elimination phases (single dose half-lives of absorption, distribution and elimination are 0.05, 3.73 and 79 hours respectively). Absorption is extensive, with approximately 10 % of a radiolabeled dose excreted in the feces. However, absolute bioavailability is approximately 33-64 %, due to first pass metabolism. Apparent volume of distribution is approximately 5,000 L, which reflects the extensive distribution of ribavirin.
Ribavirin accumulation in non-plasma compartments has been most extensively studied in red cells, and has been identified as primarily via an es-type equilibrative nucleoside transporter. This type of transporter is present on virtually all cell types, and may account for the high volume of distribution. Ribavirin has two pathways of metabolism: (i) a reversible phosphorylation pathway; and (ii) a degradative pathway involving deribosylation and amide hydrolysis to yield a triazole carboxamide metabolite. Both ribavirin and its triazole carboxamide and triazole carboxylic acid metabolites are also excreted renally. Ribavirin does not bind to plasma proteins.
Based upon Cmax from single dose to 6 weeks, accumulation of ribavirin in plasma is approximately 4.7 fold, although steady state may not have been achieved at 6 weeks. Following oral dosing with 600 mg ribavirin BID, mean plasma concentrations of 2,200 (37 %) ng/mL were achieved. Upon discontinuation of dosing there was a washout half-life of approximately 298 hours, which probably reflects slow elimination from non-plasma compartments.
Population pharmacokinetic analysis was performed using sparsely sampled serum concentration values from the clinical efficacy studies. The clearance model developed showed that body weight, gender, age and serum creatinine were the main covariates. The estimates of ribavirin clearance developed by the final model were 21.1 L/hr for males, and 17.7 L/hr for females. These estimates are close to those obtained from intensively sampled multiple dose plasma pharmacokinetic data (approximately 23 L/hr). For males, clearance was approximately 20 % higher than for females. Clearance increased as a function of body weight and was reduced at ages greater than 40 years. Effects of covariates on ribavirin clearance appear to be of limited clinical significance, due to the substantial residual variability not accounted for by the model. Comparison of concentration data with pharmacodynamic variables showed a positive relationship with nadir hemoglobin values or percent change in hemoglobin from baseline, although these data were highly variable. Mean concentration values between treatment responders and non-responders were generally similar, although these data were also highly variable.
The bioavailability of ribavirin was increased by co-administration of a high fat meal (AUCt and Cmax both increased by 70 %).
Ribavirin is not a substrate for, nor does it inhibit or induce any cytochrome P450 enzymes. The pharmacokinetics of ribavirin was not assessed in elderly or pediatric subjects.
Peginterferon alfa-2b: The pharmacokinetic profile of peginterferon alfa-2b following subcutaneous injection, based on a single study, is summarized in Table 25 below. In addition, the pharmacokinetics of non-pegylated interferon alfa-2b (INTRON A®) is described for comparative purposes.
Table 25 - Mean (% CV) Pharmacokinetic Parameters in Humans Following Single Dose Administration of peginterferon alfa-2b
| Compound | Dose (mcg/kg) | Cmax (pg/mL) | Tmax (hr) | AUCtf (pg×hr/mL) | t½ (hr) | Cl/F (mL/hr×kg) | Vd/F (L/kg) |
| PEG2ba | 0.5 | 295 (26) | 37 (46) | 16,000 (32) | 27.2b | 23.0b | 0.89b |
| 1 | 554 (38) | 31 (45) | 41,400 (25) | 33.4 (33) | 21.9 (17) | 1.07 (39) | |
| 1.5 | 785 (47) | 44 (22) | 63,300 (43) | 28.2 (27) | 25.0 (40) | 1.08 (57) | |
| 2 | 1,710 (39) | 15 (35) | 105,000 (26) | 31.6 (17) | 18.8 (29) | 0.86 (31) | |
| Mean | - | - | 30.7 | 22 | 0.99 | ||
| Range | - | - | - | - | 27.2-33.4 | 18.8-25.0 | 0.86-1.08 |
| interferon alfa-2bc | Dose (MIU) | Cmax (IU/mL) | Tmax (hr) | AUCtf (IU×hr/mL) | t½ (hr) | CL/F (mL/hr×kg) | Vd/F (L/kg) |
| 3 MIU TIW | 14.4 (30) | 8 (27) | 134 (31) | 4.28 (24)d | 231.2 (22)d | 1.40 (35)d |
PEG2b = peginterferon alfa-2b
a: n = 6, except
b: n = 2
c: n = 16, except
d: n = 6
As shown, t½ for peginterferon alfa-2b is significantly longer than interferon alfa-2b (30.7 hours versus 4.28 hours respectively). The significantly lower clearance of peginterferon alfa-2b (22.0 mL/hr×kg) relative to interferon alfa-2b (231.2 mL/hr×kg) is reflective of the longer t½ for the former compound.
Both peginterferon alfa-2b and interferon alfa-2b are rapidly absorbed following subcutaneous administration with mean absorption half-lives (t½ka) of 4.6 hours and 2.3 hours respectively. However, due to sustained maximal concentrations, peginterferon alfa-2b Tmax is later (range 15-44 hours) compared with interferon alfa-2b (mean 8 hours).
Following absorption, peginterferon alfa-2b displays sustained maximal serum concentrations for 48 to 72 hours post-dose. In contrast, mean serum interferon alfa-2b concentrations decline rapidly after reaching peak concentrations.
Peginterferon alfa-2b Cmax and AUC increase in a dose-related manner. Mean apparent volume of distribution is slightly higher for interferon alfa-2b (1.4L/kg) than for peginterferon alfa-2b (0.99L/kg), which is not anticipated to be of clinical significance.
Upon multiple dosing, there is accumulation of immunoreactive interferons. There is however, only a modest increase in biologic activity as measured by bioassay.
The mechanisms involved in clearance of interferons in man have not yet been fully elucidated. Renal clearance appears to be an important route of elimination for interferon alfa-2b, accounting for approximately 80 % of apparent clearance. Based on a retrospective regression analysis of peginterferon alfa-2b Cl/F and creatinine clearance, from an expanded database, it is estimated that renal clearance of peginterferon alfa-2b may account for approximately 30 % of the apparent clearance.
Ribavirin plus peginterferon alfa-2b: No pharmacokinetic interactions were noted between peginterferon alfa-2b and ribavirin in a multiple-dose pharmacokinetic study.
TOXICOLOGY
Acute Toxicity
Ribavirin
Table 26
a: Except at the 6,310 mg/kg oral dose; there were 0 males and 5 females.
Ribavirin has a low level of toxicity after single doses in animals. Depression, hunched posture, rough coat, ataxia, prostration, tremors and labored respiration were observed following acute toxic doses in mice and rats. The presence of dark red material in the gastro-intestinal tract of non-surviving rats in the higher dose groups is suggestive of ribavirin-related hemorrhage. Similar drug-related findings were observed in guinea pigs. Soft, mucoid stools and/or diarrhea were observed in dogs administered single doses up to 480 mg/kg. Emesis and transient body weight loss were seen in select dogs at the intermediate doses. Ulcer-like areas in the upper portion of the duodenum were observed in dogs treated with the 60/480 mg/kg dose.
Peginterferon alfa-2b: Volume limited single subcutaneous doses of peginterferon alfa-2b (56,850 mcg/m2 in rats and 60,410 mcg/m2 in mice) failed to produce any toxic effects. Single dose studies in primates showed a no-observed adverse effect level of 58,861 mcg/m2 for males and 29,435 mcg/m2 for females. These single dose no-observed adverse event levels correspond with approximately 2,943 (for male monkeys) and 1,472 (for female monkeys) times the weekly human dose of INTRON A® (20 mcg/m2 or 9 MIU) utilized in the treatment of chronic hepatitis C. Two of four monkeys given a single dose of 117,721 mcg/m2 either died or was sacrificed in moribund condition. One death was the result of myocarditis and pleural effusion that was most likely present prior to dosing. The cause of death in the other monkey was not determined. Adverse events noted in survivors at the high-dose included loss of appetite, lower body temperature and reduction of blood pressure.
| Species | Sex | Route | LD50 +(mg/kg) | 95 % CI (mg/kg) |
| Mouse (CD-1) | M | p.o. | > 10,000 | - |
| M | ip | 1,268 | 1,032 - 1,504 | |
| Rat (Sprague-Dawley) | M/Fa | p.o. | 5,006 | 4,100 - 5,913 |
| M/F | ip | 1,655 | 1,513 - 1,796 | |
| Rat (Sprague-Dawley) | M/F | p.o. | 6,030 | - |
| M/F | im | 1,700 | 1,510 - 1,870 | |
| M/F | iv | 1,830 | 1,620 - 2,010 | |
| Guinea pig (Hartley) | M | p.o. | 2,313 | 1,768 - 2,858 |
| M | ip | 823 | 706 - 941 | |
| Dog (Beagle) | M | p.o. | > 480 | - |
Long-term (subacute and chronic) Toxicity
Ribavirin: Repeated dose toxicity studies were conducted in mice, rats, dogs and monkeys. In mice administered oral doses up to 600 mg/kg for 90 days, dose-related mortality was observed in the highest dose groups (300 and 600 mg/kg/day). Dose-related decreases in hemoglobin, hematocrit and/or erythrocyte count were observed in all treated groups. Increases in mean corpuscular volume/hemoglobin (300 mg/kg), platelets (150, 300 mg/kg/day), reticulocyte values (300 mg/kg/day), neutrophils, nucleated RBCs and poikilocytes (300 mg/kg/day) were also observed. Treated animals had higher spleen weights and increased liver weight was observed in the 300 mg/kg group. Testes and epididymides of mice in the 150, 300 and 600 mg/kg dose groups had histological evidence of bilateral degeneration of the testicular germinal epithelium accompanied by bilateral epididymal oligospermia and accumulation of degenerated seminal product.
No ribavirin-related mortality or clinical observations were observed in rats administered oral ribavirin in doses up to 120 mg/kg for at least 28 days. Food consumption and body weights were decreased in the mid to high dose groups. A treatment-related decrease in circulating red cell mass characterized by decreased hematocrit, hemoglobin and erythrocyte counts was observed. Small thymus and lymphoid depletion in the thymus of high dose rats of both sexes was also observed.
In a ninety-day study in rats administered oral ribavirin (20 to 200 mg/kg/day); mortalities were observed in the 15 mg/kg/day (1F) and 200 mg/kg/day (1 F/3 M) dose groups. Increased circulating aspartate aminotransferase and alanine aminotransferase were observed in the highest dose group in addition to the treatment-related effects on hemoglobin, hematocrit, erythrocyte count, platelet and leukocyte count (40 – 200 mg/kg). Heart and spleen weights were elevated in rats in the highest dose group.
In a 30-day dietary study in rats receiving ribavirin up to 320 mg/kg/day, piloerection, abnormal breathing and/or subdued behavior was observed in animals that died or were sacrificed prematurely. Hunched posture, pale extremities, ataxia, thin build, hypothermia, body weight loss or reduced weight gain and reduced food consumption were observed in the 160 and 320 mg/kg dose groups. Hematological effects included reduced hemoglobin and hematocrit (40 and 160 mg/kg), reduced RBC and WBC counts (160 mg/kg), decreased mean corpuscular hemoglobin and mean corpuscular volume (10 and 40 mg/kg). Females in the 160 mg/kg dose group showed increases in AST and phosphate and decrease in total protein, albumin, creatine and calcium. Decreases in thymus weight and increases in heart and lung weights occurred at 160 mg/kg. Macroscopic changes occurred in the heart, liver, lungs, thorax, thymus and lymph nodes (160 mg/kg) with histological changes in the intestine, heart, liver, lungs, salivary glands, spleen, testes, thymus and lymph nodes. Similar findings were noted in a 52-week dietary study where rats were administered up to 90 mg/kg/day. In addition to the findings noted above, ALT levels were reduced (both sexes) and a reduction in albumin noted in females. Albumin was increased in males (90 mg/kg) between weeks 4 and 13 and reduced in weeks 26 to 52. Pathology findings revealed depletion in thymic cellularity with possible secondary findings in the skin, lung and submandibular lymph nodes.
In a 28-day study in dogs administered oral ribavirin doses of 15, 30 or 60 mg/kg/day, 5 of 6 dogs in the high dose group died or were sacrificed due to moribund condition. Enteritis was the principal effect noted in the low dose group whereas body weight and food consumption were decreased primarily in the mid and high dose groups. Severe cachexia was noted in the high dose group. There was evidence of non-regenerative anemia (decreased red cell mass and absence of reticulocytosis) and decreased white blood cells in the mid- and high-dose groups. Bone marrow hypoplasia, lymphoid depletion in the thymus, gastric cytoplasmic vacuolization, and increased brown granular pigment in the spleen were present in mid- and high-dose groups. Similar findings were noted in two additional studies where dogs were administered oral doses of 5 - 40 mg/kg/day for 30 days or 5 - 20 mg/kg/day for 52 weeks.
Ribavirin was well tolerated when administered to cynomolgus monkeys at a single daily oral (gavage) dose of 100 mg/kg for two weeks. Upon intramuscular administration (30 or 100 mg/kg) to rhesus monkeys for 10 days, reversible, dose-related decreases in circulating red blood cell mass was observed as well as an increase in megakaryocytes at day 10 in both groups.
Peginterferon alfa-2b: In a multiple dose study, doses of 1,414 mcg/m2 and 4,239 mcg/m2 administered every other day over one month to primates were also well tolerated. At the highest dose (14,126 mcg/m2 QOD) one female was sacrificed in moribund condition with abscesses at the injection site due to bacterial infection, bone marrow hypocellularity, anemia, hypoalbuminemia and lymphoid depletion in thymus, spleen and lymph nodes. In surviving monkeys, there were dose related decreases in platelets, neutrophils, lymphocytes, erythrocytes, serum proteins, calcium, phosphorus and potassium. These changes tended toward normal after Week 2, and returned to pre-test values in the high-dose monkeys retained for a 4-week recovery period. Test article-related histopathologic findings were restricted to the bone marrow and injection site. There was minimal to mild bone marrow hypercellularity, suggestive of a regenerative process, in some animals in the peginterferon alfa-2b and the interferon alfa-2b groups, and minimal to mild perivasculitis at injection sites in all groups, including vehicle controls. All of the changes that were seen in peginterferon alfa-2b-dosed monkeys were similar in nature to those seen in the interferon alfa-2b group of this study, or in previous studies in monkeys of interferon alfa-2b.
The table below (Table 27) illustrates the relationships between dose, general effects, and AUC for interferon alfa-2b after a single dose in the one-month study in monkeys.
The general toxicologic effects of a dose of 4,239 mcg/m2 of peginterferon alfa-2b are most similar to those of an interferon alfa-2b dose of 3,105 mcg/m2. Peginterferon alfa-2b was well tolerated but produced mild toxicity at the mid-dose of 4,239 mcg/m2, or 241.6 MIU/m2. Interferon alfa-2b was well tolerated but produced similar mild toxicity at a dose of 3,105g/m2, or 807.3 MIU/m2. These doses gave similar interferon alfa-2b plasma levels in terms of AUC (0.675 vs. 0.545 MIU-equiv.x hr/mL) after a single dose. However, peginterferon alfa-2b accumulates after multiple doses because of its long half-life. The plasma AUC for a peginterferon alfa-2b dose of 4,239 mcg/m2 would exceed that of an interferon alfa-2b dose of 3,105 mcg/m2 after multiple doses. This suggests that the severity of general toxicologic effects in monkeys may be somewhat less for peginterferon alfa-2b than for interferon alfa-2b at similar systemic exposure levels.
Table 27 - Correlation of Dose and General Effects
| Test Article | Dose (mcg/m2) | MIU/m2 | IFN AUC/(I)c MIU-equiv. x hr/mL (after one dose) | Effect |
| PEG2ba | 1414 | 80.6 | 0.284 | Well tolerated, mild toxicity |
| PEG2b | 4239 | 241.6 | 0.675 | Well tolerated, minimal effects |
| PEG2b | 14126 | 805.2 | 2.22 | Well tolerated, mild toxicity, moderate weight loss |
| interferon alfa-2bb | 3105 | 807.3 | 0.545 | One female sacrificed moribund Moderate effects in other animals |
PEG2b = peginterferon alfa-2b a: Based on a specific activity of 0.57 X 10⁸ IU/mg protein b: Based on a specific activity of 2.6 X 10⁸ IU/mg protein c: As measured by ELISA | ||||
Peginterferon alfa-2b plus ribavirin: A one-month toxicity study and a one-month toxicity and neutrophil function study investigating peginterferon alfa-2b in combination with ribavirin were conducted in cynomolgus monkeys. In each study, monkeys were dosed with subcutaneous injections of peginterferon alfa-2b every other day (5,494 mcg/m2) either alone or in combination with a daily oral (gavage) ribavirin (50 or 75 mg/kg).
The major effects observed in the one-month toxicity study (body weight loss related to inappetence, and decreased red and white blood cell parameters due to reversible bone marrow suppression) were those that were expected based on the known biologic effects of these two drugs. Five monkeys (one peginterferon monotherapy, one low-dose combination, and three high-dose combination) were sacrificed in moribund condition. The moribundity observed was not a direct test article-related effect but was due to opportunistic infections. Peginterferon alfa-2b’s effect on neutrophil counts supports the conclusion that lowered host resistance to infections was a contributing factor in the morbidity and mortality. In the follow-up study, a similar degree of morbidity due to opportunistic infections was not observed with similar combination dosing regimens.
In the one-month toxicity and neutrophil function study, administration of ribavirin (75 mg/kg) in combination with peginterferon alfa-2b (350, 1,400, or 5,500 mcg/m2) resulted in an exacerbation of biologic effects typically seen with either drug alone. These findings included body weight loss related to inappetence, and decreased red and white blood cell parameters due to reversible bone marrow suppression (peginterferon alfa-2b) or extravascular hemolysis (ribavirin). Bone marrow changes were noted for all three combination groups with the highest incidence occurring in the high-dose combination males. There were no drug-induced effects on neutrophil function. One monkey died of aspiration pneumonia most likely exacerbated by neutropenia.
Carcinogenicity
Ribavirin: An 18-month study in mice indicated that ribavirin was not oncogenic at oral gavage doses up to 75 mg/kg/day. Hematologic and splenic changes indicate that ribavirin was absorbed at sufficient levels to cause adverse effects, and that the severity of the effects was dose-related. A two-year study in rats indicated that ribavirin had no oncogenic effect at oral gavage doses up to 40 mg/kg/day.
Conventional carcinogenicity studies in rodents with low exposures compared to human exposure under therapeutic conditions (factor 0.1 in rats and 1 in mice) did not reveal tumorigenicity of ribavirin. In addition, in a 26 week carcinogenicity study using the heterozygous p53 (+/-) mouse model, ribavirin did not produce tumors at the maximally tolerated dose of 300 mg/kg (plasma exposure factor approximately 2.5 compared to human exposure).
Peginterferon alfa-2b: Studies with peginterferon alfa-2b have not been performed to determine carcinogenicity due to lack of biologic activity in rodents.
Mutagenicity
Ribavirin: Mutagenicity studies suggest that ribavirin may exert some mutagenic activity. Ribavirin induced an increase in transformed foci in two independent Balb/3T3 in vitro transformation assay trials. Mutagenic activity was observed in the mouse lymphoma forward mutation assay, and ribavirin induced micronuclei in polychromatic erythrocytes at doses of 20-200 mg/kg in a mouse micronucleus assay. A dominant lethal assay in rats was negative, indicating that if mutations occurred in rats they were not transmitted through male gametes.
Peginterferon alfa-2b: Mutagenicity studies with peginterferon alfa-2b revealed no mutagenic activity.
Reproduction and Teratology
Ribavirin: In a Segment I study with male rats administered 10, 40, or 160 mg/kg daily for 9 weeks prior to mating and female rats administered 0.3, 1.0 or 10.0 mg/kg daily (all doses lower than the recommended 24-hour human dose for ribavirin) from 2 weeks prior to mating until Day 5 of presumed pregnancy, there were no treatment-related effects on female mating performance or latent effects on in utero and postnatal development of the litter.
Rats were administered oral doses of 0.3, 1.0 and 10.0 mg/kg ribavirin from day 6 to day 15 of pregnancy. Despite a negligible maternal toxicity response, the 10.0 mg/kg dose resulted in embryonic death, reduced litter size, reduced fetal weight, visceral and skeletal abnormalities, and skeletal variants. Morphological changes were also observed in the 1.0 mg/kg dose group. In a second study, rats were administered oral doses of 0.1, 0.3 and 1.0 mg/kg ribavirin from day 6 to day 18 of pregnancy. The 1.0 mg/kg dose level was associated with a transient reduction in maternal weight gain, slight reduction in fetal weight and increased incidences of fetuses showing skeletal anomalies and variants.
Male mice were administered oral ribavirin (0, 35, 75, 150 mg/kg/day) for 3-6 months to evaluate the time course and reversibility of ribavirin-induced testicular degeneration. Moderate dose-dependent effects on spermatogenesis were observed including reduced testicular spermatid counts, reduced sperm motility, increased abnormal epididymal sperm, reduced testes weight, marginal reductions in seminiferous tubular diameter and increased incidences of vacuolization and reduced thickness of the germinal cell epithelium. Upon cessation of treatment, total recovery was observed within one to two spermatogenesis cycles. In a second study, ribavirin administered at daily oral doses of 1, 15, 35 or 75 mg/kg for 3 months to seven-week old mice resulted in dose-related decreases in testicular spermatid and caudal epididymal sperm counts and in the percentage of morphologically normal sperm. Morphological changes were the most sensitive endpoint observed with differences from control detected at 15 mg/kg ribavirin. The effects on spermatid count and sperm morphology were reversible upon cessation of dosing.
A toxicokinetic study was conducted in rabbits at oral doses of 0.3, 1.0 and 3.0 mg/kg from day 6 to day 18 of pregnancy. Effects on the developing conceptus included, at 3.0 mg/kg, a slight increase in in utero mortality, slight reduction in litter size, markedly lower litter and mean fetal weight and an increase in fetuses showing probable malformation upon gross examination. Rats administered ribavirin at doses up to 1.0 mg/kg from day 15 of pregnancy through day 21 postpartum produced little or no evidence of toxicity to either the pregnant female or her offspring.
Peginterferon alfa-2b: Interferon alfa-2b has been shown to have abortifacient effects in Macaca mulatta (rhesus monkeys) at 7.5, 15, and 30 million IU/kg (90, 180, and 360 times the intramuscular or subcutaneous dose of 2 million IU/m2). Although abortion was observed in all dose groups, it was only statistically significant at the mid- and high-dose groups. Peginterferon alfa-2b is likely to also cause these effects.
REFERENCES
- 1. Lindsay KL, Trepo C, Heintges T, Shiffman ML, Gordon SC, Hoefs JC, et al. A Randomized, Double-Blind Trial Comparing Pegylated Interferon Alfa-2b to Interferon Alfa-2b as Initial Treatment for Chronic Hepatitis C. Hepatology 2001;34 (2):395-403.
- 2. INTRON A® (interferon alfa-2b) Product Monograph March 24, 2011.
- 3. Davis GL, Esteban-Mur R, Rustgi V, Hoefs J, Gordon SD, Trepo C, et al. Interferon alfa-2b alone or in combination with ribavirin for the treatment of relapse of chronic hepatitis C. N Engl J Med 1998;339(21):1493-9.
- 4. Hoffmann RM, Diepolder HM, Zachoval R, Zwiebel F-M, Jung MC, Scholz S, et al. Mapping of immunodominant CD4+ T lymphocyte epitopes of hepatitis C virus antigens and their relevance during the course of chronic infection. Hepatology 1995;21(3):632-8.
- 5. Knodell RG, Ishak KG, Black WC, Chen TS, Craig R, Kaplowitz N, et al. Formulation and application of a numerical scoring system for assessing histological activity in asymptomatic chronic active hepatitis. Hepatology 1981;1(5): 431-5.
- 6. McHutchison JG, Gordon SC, Schiff ER, Shiffman ML, Lee WM, Rustgi VK, et al. Interferon alfa-2b alone or in combination with ribavirin as initial treatment for chronic hepatitis C. N Engl J Med 1998;339(21):1485-92.
- 7. Poynard T, Marcellin P, Lee SS, Niederau C, Minuk GS, Ideo G, et al. Randomised trial of interferon alfa-2b plus ribavirin for 48 weeks or for 24 weeks versus interferon alfa-2b plus placebo for 48 weeks for treatment of chronic infection with hepatitis C virus. Lancet 1998;352(9138):1426-32.
- 8. Vial T, Descotes J. Clinical toxicity of the interferons. Drug Saf 1994;10(2):115-50.
- 9. National Institutes of Health Consensus Development Conference Panel Statement: Management of Hepatitis C. Hepatology 1997;26(3 Suppl. 1):2-10.
- 10. Center for Disease Control (CDC): Recommendations for Prevention and Control of Hepatitis C Virus (HCV) Infection and HCV-Related Chronic Disease. MMWR Recomm 1998; 47(RR19): 1-39.
- 11. Manns MP, McHutchison JG, Gordon SC, Rustgi VK, Shiffman M, Reindollar R, et al. Peginterferon alfa-2b plus ribavirin compared with interferon alfa-2b plus ribavirin for initial treatment of chronic hepatitis C: a randomised trial. Lancet 2001; 358(9286):958-65.
- 12. McHutchison JG, Manns M, Patel K, Poynard T, Lindsay KL, Trepo C, et al. Adherence to Combination Therapy Enhances Sustained Response in Genotype-1-Infected Patients with Chronic Hepatitis C. Gastroenterology 2002; 123(4):1061-9.
- 13. Gupta SK, Glue P, Jacobs S, Belle D, Affrime M. Single-dose pharmacokinetics and tolerability of pegylated interferon-alpha 2b in young and elderly healthy subjects. Br J Clin Pharmacol 2003; 56(1):131-4.
- 14. M. Sherman, S. Shafran, K. Burak et al. Management of chronic hepatitis C: Consensus guidelines. Can. J. Gastroenterol. 2007; 21 (Suppl C): 25C - 34C.