


Product Monograph - Tysabri
RECENT MAJOR LABEL CHANGES
4 Dosage and Administration, 4.4 Administration 7 Warnings and Precautions 7 Warnings and Precautions, 7.1.1 Pregnant Women | 08/2023 |
|---|---|
| 7 Warnings and Precautions, 7.1.1 Pregnant Women | 09/2024 |
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
RECENT MAJOR LABEL CHANGES ............................................................................................. 2
TABLE OF CONTENTS ............................................................................................................... 2
PART I: HEALTH PROFESSIONAL INFORMATION ....................................................................... 4
1 INDICATIONS ................................................................................................................ 4
1.1 Pediatrics ............................................................................................................... 4
1.2 Geriatrics ............................................................................................................... 4
2 CONTRAINDICATIONS .................................................................................................. 4
3 SERIOUS WARNINGS AND PRECAUTIONS BOX ............................................................. 5
4 DOSAGE AND ADMINISTRATION .................................................................................. 5
4.1 Dosing Considerations ........................................................................................... 5
4.2 Recommended Dose and Dosage Adjustment ...................................................... 5
4.3 Reconstitution ....................................................................................................... 6
4.4 Administration ....................................................................................................... 6
4.5 Missed Dose .......................................................................................................... 7
5 OVERDOSAGE ............................................................................................................... 7
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING .................................. 7
7 WARNINGS AND PRECAUTIONS ................................................................................... 8
7.1 Special Populations .............................................................................................. 16
7.1.1 Pregnant Women ..................................................................................... 16
7.1.2 Breast-feeding ......................................................................................... 17
7.1.3 Pediatrics ................................................................................................. 17
7.1.4 Geriatrics ................................................................................................. 17
8 ADVERSE REACTIONS ................................................................................................. 17
8.1 Adverse Reaction Overview ................................................................................. 17
8.2 Clinical Trial Adverse Reactions ........................................................................... 18
8.3 Less Common Clinical Trial Adverse Reactions .................................................... 22
8.5 Post-Market Adverse Reactions .......................................................................... 23
9 DRUG INTERACTIONS ................................................................................................. 24
9.2 Drug Interactions Overview ................................................................................. 24
9.3 Drug-Behavioural Interactions ............................................................................. 25
9.4 Drug-Drug Interactions ........................................................................................ 25
9.5 Drug-Food Interactions ........................................................................................ 25
9.6 Drug-Herb Interactions ........................................................................................ 25
9.7 Drug-Laboratory Test Interactions ....................................................................... 25
10 CLINICAL PHARMACOLOGY ........................................................................................ 25
10.1 Mechanism of Action ........................................................................................... 25
10.2 Pharmacodynamics ............................................................................................. 26
10.3 Pharmacokinetics ................................................................................................ 26
11 STORAGE, STABILITY AND DISPOSAL .......................................................................... 28
12 SPECIAL HANDLING INSTRUCTIONS ............................................................................ 28
PART II: SCIENTIFIC INFORMATION ........................................................................................ 29
13 PHARMACEUTICAL INFORMATION ............................................................................. 29
14 CLINICAL TRIALS ......................................................................................................... 29
14.1 Clinical Trials by Indication .................................................................................. 29
Multiple Sclerosis (MS) ........................................................................................ 29
14.3 Immunogenicity ................................................................................................... 39
15 MICROBIOLOGY ......................................................................................................... 40
16 NON-CLINICAL TOXICOLOGY ...................................................................................... 40
PATIENT MEDICATION INFORMATION ................................................................................... 42
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
TYSABRI (natalizumab) is indicated:
- as monotherapy (i.e. single disease-modifying agent) for the treatment of patients with the relapsing-remitting form of multiple sclerosis (MS) to reduce the frequency of clinical exacerbations, to decrease the number and volume of active brain lesions identified on magnetic resonance imaging (MRI) scans and to delay the progression of physical disability. TYSABRI is generally recommended in MS patients who have had an inadequate response to, or are unable to tolerate, other therapies for multiple sclerosis.
Safety and efficacy in patients with chronic progressive multiple sclerosis, and in geriatric and pediatric patients, have not been established.
The efficacy of TYSABRI for a treatment duration beyond 2 years has not been determined.
TYSABRI should be used by physicians who have sufficient knowledge of multiple sclerosis and who have familiarized themselves with the efficacy/safety profile of TYSABRI.
TYSABRI is only available through a controlled distribution program called Biogen ONETM Support Program. Under this program, only prescribers and pharmacies registered with the program are able to prescribe and dispense the product. In addition, TYSABRI can only be dispensed to patients who are registered and meet all the conditions of the Biogen ONETM Support Program. Please call 1-855-676-6300 or log onto BiogenTherapies.ca.
1.1 Pediatrics
Pediatrics (<18 years of age): Safety and effectiveness of TYSABRI in pediatric patients with multiple sclerosis have not been established. Therefore, Health Canada has not authorized an indication for pediatric use.
1.2 Geriatrics
Geriatrics (>65 years of age): Clinical studies of TYSABRI did not include sufficient numbers of patients aged 65 years and over to determine whether they respond differently than younger patients.
2 CONTRAINDICATIONS
- TYSABRI is contraindicated in patients who are hypersensitive to this drug or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING.
- TYSABRI is contraindicated in patients who have or have had progressive multifocal leukoencephalopathy (PML). See 7 WARNINGS AND PRECAUTIONS.
- TYSABRI is contraindicated in patients who are immunocompromised, including those immunocompromised due to immunosuppressant or antineoplastic therapies, or immunodeficiencies (HIV, leukemias, lymphomas, etc.). See 7 WARNINGS AND
PRECAUTIONS
- .
3 SERIOUS WARNINGS AND PRECAUTIONS BOX
Serious Warnings and Precautions
|
|---|
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
TYSABRI (natalizumab) should be administered by a healthcare professional.
- Patients should be observed during the infusion and for 1 hour after the infusion is complete for signs and symptoms of infusion reactions. Promptly discontinue the infusion upon the first observation of any signs or symptoms consistent with a hypersensitivity reaction (see 7 WARNINGS AND PRECAUTIONS, Immune, Hypersensitivity Reactions).
- Dilute only with 0.9% Sodium Chloride Injection, USP.
- TYSABRI contains 52 mg sodium per vial. When diluted in 100 mL of 0.9% Sodium Chloride Injection, USP, TYSABRI contains 406 mg sodium per dose. This should be taken into consideration by patients on a controlled sodium diet.
4.2 Recommended Dose and Dosage Adjustment
The recommended dose of TYSABRI is 300 mg IV infusion every 4 weeks. Do not administer TYSABRI as an IV push or bolus injection.
Health Canada has not authorized an indication for pediatric use (see 1.1 Pediatrics).
Pharmacokinetics of natalizumab in patients with renal or hepatic insufficiency have not been studied.
4.3 Reconstitution
Parenteral Products:
Table 1 – Reconstitution
| Vial Size | Volume of Diluent | Approximate Volume for infusion | Concentration per mL |
| 15 mL | 100 mL 0.9% Sodium Chloride Injection, USP | 115 mL | 2.6 mg |
Intravenous infusion: If not used immediately, store the TYSABRI solution for infusion at 2°-8°C. TYSABRI solution for infusion must be administered within 72 hours of preparation. DO NOT FREEZE. See 11 STORAGE, STABILITY AND DISPOSAL.
4.4 Administration
Dilution:
Parenteral Products:
Use aseptic technique when preparing TYSABRI solution for IV infusion. Each vial contains a single dose and is intended for single patient use only.
TYSABRI is a colourless, clear to slightly opalescent concentrate. Inspect the TYSABRI vial for particulate material prior to dilution and administration. If visible particulates are observed and/or the liquid in the vial is discoloured, the vial must not be used. Do not use TYSABRI beyond the expiration date on the carton or vial.
To prepare the solution, withdraw 15 mL of TYSABRI concentrate from the vial using a sterile needle and syringe. Inject the concentrate into 100 mL 0.9% Sodium Chloride Injection, USP. No other IV diluents may be used to prepare the TYSABRI solution.
Gently invert the TYSABRI solution to mix completely. Do not shake. Inspect for particulate material prior to administration.
Infuse over approximately 1 hour. Observe patients during the infusion and for 1 hour after the infusion is completed for signs and symptoms of infusion reactions. After the first 12 TYSABRI doses, patients should continue to be observed during infusion. If patients have not experienced any infusion reactions including hypersensitivity, the post dose observation time may be adjusted for the 13th and subsequent infusions according to clinical judgement.
After the infusion is complete, flush with 0.9% Sodium Chloride Injection, USP. Other medications should not be injected into infusion set side ports or mixed with TYSABRI.
4.5 Missed Dose
If a dose of TYSABRI is missed, TYSABRI should be administered as soon as possible, and dosing should continue at the prescribed frequency.
5 OVERDOSAGE
Safety of doses higher than 300 mg has not been adequately evaluated. The maximum amount of TYSABRI (natalizumab) that can be safely administered has not been determined.
| For management of a suspected drug overdose, contact your regional poison control centre. |
|---|
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
To help ensure the traceability of biologic products, including biosimilars, health professionals should recognise the importance of recording both the brand name and the non-proprietary (active ingredient) name as well as other product-specific identifiers such as the Drug Identification Number (DIN) and the batch/lot number of the product supplied.
Table 2 – Dosage Forms, Strengths, Composition and Packaging
TYSABRI (natalizumab) concentrate is supplied as 300 mg natalizumab in a sterile, single-use vial free of preservatives.
Each package contains one vial.
Each 15 mL dose also contains (pH 6.1):
123 mg sodium chloride, USP/Ph.Eur
17.0 mg sodium phosphate, monobasic, monohydrate, USP
7.24 mg sodium phosphate, dibasic, heptahydrate, USP
3.0 mg polysorbate 80, USP/NF/Ph.Eur
Water for Injection, USP/Ph.Eur
| Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
| Intravenous infusion | Concentrate for solution / 300 mg per 15 mL | polysorbate 80; sodium chloride; sodium phosphate, dibasic, heptahydrate; sodium phosphate, monobasic, monohydrate; water for injection |
7 WARNINGS AND PRECAUTIONS
Please see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX.
General
Before initiation of treatment with TYSABRI (natalizumab), a recent magnetic resonance image (MRI) should be available. This MRI may be helpful in differentiating subsequent MS symptoms from PML. For diagnosis of PML, an evaluation that includes a magnetic resonance imaging (MRI) scan of the brain and, when indicated, cerebrospinal fluid analysis for JC viral DNA are recommended. See 7 WARNINGS AND PRECAUTIONS, Infections).
Patients who are prescribed TYSABRI are to be enrolled in the Biogen ONETM Support Program – a registry of Canadian patients. To enroll, physicians fax an enrollment form to 1-855-676-6301. Biogen ONETM Support Program is a comprehensive program associated with the prescribing, administration and monitoring of patients who receive TYSABRI treatment.
Educational Guidance: Prescribers and Biogen ONETM Support Program healthcare professionals are educated regarding the appropriate use of TYSABRI, and information is updated regularly. Prescribers are expected to educate patients on the benefits and risks of treatment, especially the risk of PML. Patients should remain under medical supervision while receiving TYSABRI and should be evaluated by the prescriber every six months.
At 24 months of treatment, physicians should inform patients again about the risks of TYSABRI, including that the risk of PML increases with longer treatment duration. Physicians should obtain consent from their patients for continuation of treatment. At 24 months of treatment, the patient, their partner and/or caregiver should be re-instructed about the early signs and symptoms of PML.
Carcinogenesis and Mutagenesis
No clastogenic or mutagenic effects of natalizumab were observed in the Ames human chromosomal aberration assays. Natalizumab showed no effects on in vitro assays of α4-integrin-positive human tumour line proliferation/cytotoxicity. Xenograft transplantation models in SCID and nude mice with two α4-integrin-positive human tumour lines (leukemia, melanoma) demonstrated no increase in tumour growth rates or metastasis resulting from natalizumab treatment (See 16 Non-Clinical Toxicology).
No differences in incidence rates or the nature of malignancies between TYSABRI and placebo-treated patients were observed over 2 years of treatment. However, observation over longer treatment periods is required before any effect of TYSABRI on malignancies can be excluded. Should a malignancy develop, TYSABRI therapy should be withheld at least until appropriate treatment has been initiated for the malignancy and the benefit and risks of resuming TYSABRI therapy have been deemed to be acceptable by the treating physician.
Driving and Operating Machinery
No studies on the effects on the ability to drive and use machines have been performed with
TYSABRI. However, given that dizziness has been very commonly reported, patients who experience this adverse reaction should be advised not to drive or use machines until it has resolved.
Hematologic
In clinical trials, TYSABRI was observed to induce increases in circulating lymphocytes, monocytes, eosinophils and nucleated red blood cells. During phase 3 clinical trials, cell counts were measured every 12 weeks. The largest cell increases were seen in lymphocytes, which were found to be elevated within 12 weeks after initiating TYSABRI treatment, reaching a plateau by 24 weeks. Although elevated, mean cell counts remained within the normal range. Observed increases persisted during TYSABRI exposure, but were reversible, returning to baseline levels usually within 16 weeks after the last dose. Elevations of neutrophils were not observed. TYSABRI may induce mild decreases in hemoglobin levels (mean decrease of 6.0 g/L) that are frequently transient. Hemoglobin levels returned to pretreatment values, usually within 16 weeks of last dose of TYSABRI and the changes were not associated with clinical symptoms.
In post-marketing experience, there have been reports of uncommon frequency of thrombocytopenia and immune thrombocytopenic purpura (ITP), some of which were serious. Symptoms of thrombocytopenia may include spontaneous bruising, abnormal bleeding, and petechiae. Delay in the diagnosis and treatment of thrombocytopenia may lead to serious and life-threatening sequelae. If thrombocytopenia is identified, discontinuation of natalizumab should be considered.
Hepatic
In post-marketing experience, there have been rare reports of clinically significant liver injury, including markedly elevated serum hepatic enzymes and elevated total bilirubin, as early as 6 days after the first dose; signs of liver injury have also been reported for the first time after multiple doses. In some patients, liver injury recurred upon rechallenge. Some cases occurred in patients with pre-existing liver disease or in the presence of other drugs that have been associated with hepatic injury. Patients with history of liver disease, alcohol abuse, and/or treatment with other therapies that are known to cause liver injury should be carefully evaluated prior to commencement of treatment with TYSABRI and closely monitored for possible liver damage during and after treatment. The combination of transaminase elevations and elevated bilirubin without evidence of obstruction is generally recognized as an important predictor of severe liver injury that may lead to death or the need for a liver transplant in some patients.
TYSABRI should be discontinued in patients who develop jaundice or other evidence of clinically significant liver injury, e.g., 5-fold or greater elevation in serum hepatic enzymes, and the patient should be fully evaluated. In cases with no other identifiable cause, TYSABRI should be permanently discontinued.
Immune
Hypersensitivity Reactions:
TYSABRI has been associated with hypersensitivity reactions, which occurred at an incidence of 4%, including serious systemic reactions (e.g. anaphylaxis), which occurred at an incidence of <1%. These reactions usually occurred within 2 hours of the start of the infusion. Symptoms associated with these reactions included urticaria, dizziness, fever, rash, rigors, pruritus, nausea, flushing, hypotension, dyspnea and chest pain. Generally, these reactions are associated with antibodies to TYSABRI. The risk for hypersensitivity was greatest with early infusions and in patients re-exposed to TYSABRI following an initial short exposure (up to three infusions) and extended period (three months or more) without treatment. If a hypersensitivity reaction occurs, discontinue administration of TYSABRI immediately and initiate appropriate therapy.
Physicians should inform patients about the importance of uninterrupted dosing, particularly in the early months of treatment.
Post-Marketing Experience: There have been reports of hypersensitivity reactions which have been associated with one or more of the following: hypotension, hypertension, chest pain, chest discomfort, and dyspnea.
Immunosuppression:
The safety and efficacy of TYSABRI in combination with antineoplastic or immunosuppressive agents have not been established. Concurrent use of these agents with TYSABRI may increase the risk of infections, including opportunistic infections, over the risk observed with use of TYSABRI alone. The risk of PML is also increased in patients who have been treated with an immunosuppressant prior to receiving TYSABRI (see Contraindications).
No studies have been performed to evaluate the efficacy and safety of TYSABRI when switching patients from disease-modifying therapies with an immunosuppressant effect to TYSABRI. It is unknown if patients switching from these therapies to TYSABRI have an increased risk of PML. Therefore, these patients should be monitored more frequently, similarly to patients switching from immunosuppressants to TYSABRI (see Warnings and Precautions, Infections, Magnetic Resonance Imaging Screening for PML).
In clinical studies for conditions other than MS, opportunistic infections (e.g. pneumocystis carinii pneumonia, pulmonary mycobacterium avium intracellulare, bronchopulmonary aspergillosis and burkholderia cepacia) have been uncommonly observed in patients receiving TYSABRI; some of these patients were receiving concurrent immunosuppressants (see Adverse Reactions). In pivotal clinical trials (1801 and 1802), concomitant treatment of relapses with a short course of corticosteroids was not associated with an increased rate of infection in patients treated with TYSABRI as compared with placebo.
Immunizations:
In a randomized, open label study of 60 patients with relapsing MS for tetanus antibody response, post-immunization antibody levels for TYSABRI-treated patients were lower compared to controls (analysis based on 40/60 (67%) subjects available for the primary analysis), and a slower and reduced humoral immune response to neoantigen (keyhole limpet haemocyanin) was observed (analysis based on 42/60 (70%) subjects available for the primary analysis). The clinical significance of this is unknown. Live vaccines have not been studied.
Infections
Progressive Multifocal Leukoencephalopathy:
Use of TYSABRI has been associated with an increased risk of progressive multifocal leukoencephalopathy (PML), an opportunistic infection caused by John Cunningham Virus (JC virus). PML can cause severe disability or death.
Risk of PML
Three factors that are known to increase the risk of PML in TYSABRI-treated patients have been identified:
- The presence of anti-JCV antibodies. Testing for the presence of anti-JCV antibodies should only be performed using the STRATIFY JCV assay;
- Longer treatment duration, especially beyond 24 months; and
- Prior treatment with an immunosuppressant (IS), which appears independent of TYSABRI treatment duration.
The PML Risk Estimates Algorithm (Figure 1) summarizes PML risk by anti-JCV antibody status, prior IS use and duration of treatment (by year of treatment) and stratifies this risk by anti-JCV antibody level (index value), as derived from the STRATIFY JCV assay. The risk estimates are forward-looking in yearly intervals (e.g., the risk estimate corresponding to the 25-36 month TYSABRI exposure period is the PML risk estimated for the next year for patients treated for 24 months with TYSABRI). The individual treatment length of each patient is taken into consideration accounted for dropouts (e.g., treatment discontinuations).
Patients who are anti-JCV antibody negative are at a significantly lower risk of developing PML. Patients who have all three factors (anti-JCV antibody positive and prior IS use and duration of TYSABRI treatment >2 years) are at higher risk of PML. In patients not previously treated with IS, the level of anti-JCV antibodies (index value) can further stratify risk for PML. Index values equal to or below 0.9 are associated with a PML incidence of less than 1 per 1000 patients; PML risk increases substantially at index values above 1.5. The risks and benefits of continuing treatment with TYSABRI should be carefully considered in patients who have all three risk factors for PML or who have no prior IS use and have an index value of greater than 1.5 and more than 2 years of treatment with TYSABRI.
Figure 1: PML Risk Estimates Algorithm
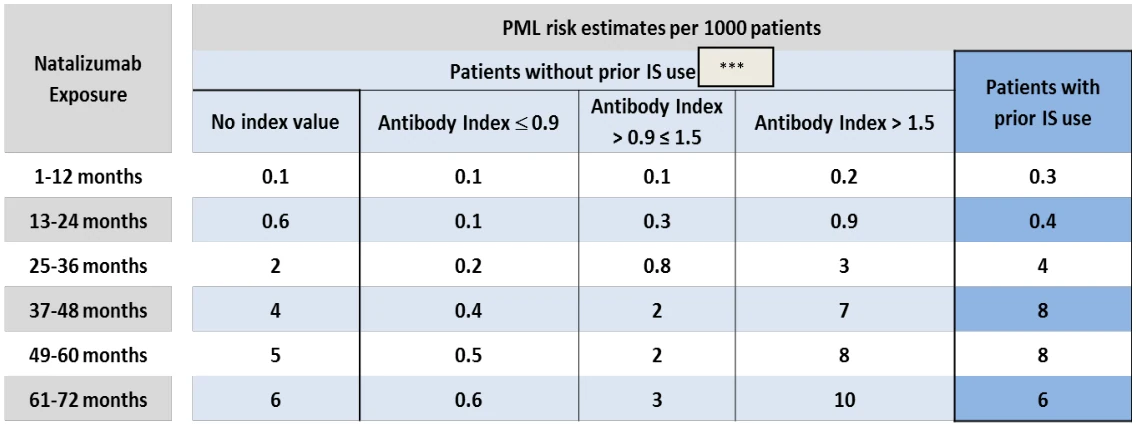
The estimates of PML risk as derived from clinical and observational trial data have been consistent with postmarketing data.
Testing for Anti-JCV Antibody
Infection by the JC virus is required for the development of PML. Anti-JCV antibody negative status indicates that exposure to the JC virus has not been detected; such patients are still at risk for the development of PML due to the potential for a new JCV infection, fluctuating
*The risk of PML in anti-JCV antibody negative patients were estimated based on post marketing data from approximately 125,000 TYSABRI exposed patients.
**PML risk estimates in anti-JCV antibody positive patients were based on the pooled cohort of 21,696 patients who participated in 3 observational studies (STRATIFY-2, TOP and TYGRIS) and 1 clinical study (STRATA).
***The majority of the prior IS use from these studies included the following 5 IS therapies: mitoxantrone, methotrexate, azathioprine, cyclophosphamide and mycophenolate.
Anti-JCV Antibody Status
Negative Antibody Status*
0.1 / 1000 patients
Positive Antibody Status**
***
antibody status or a false negative test result. For purposes of risk assessment, a patient with a positive anti-JCV antibody test at any time is considered anti-JCV antibody positive regardless of the results of any prior or subsequent anti-JCV antibody testing.
Testing for serum anti-JCV antibody status (using STRATIFY JCVTM assay) prior to initiating TYSABRI therapy or in patients receiving TYSABRI with an unknown antibody status is recommended. In addition, anti-JCV antibody retesting is recommended for patients with anti-JCV antibody negative status and for those anti-JCV antibody positive patients with lower index value, since the antibody status or index value may change. Retesting of patients who are anti-JCV antibody negative, every 6 months, is recommended. Patients with lower index values who have not had prior IS use should be retested periodically (e.g., every 6 months). Anti-JCV antibody negative patients may still be at risk of PML for reasons such as new JCV infection, fluctuating antibody status or a false negative test result. Based on a postmarketing study examining longitudinal antibody status over 18 months, there was approximately an 11% annual change in serostatus from anti-JCV antibody negative to positive. Testing should only be performed using an ELISA assay that has been validated for use in MS patients.
The anti-JCV antibody assay (ELISA) should not be used to diagnose PML. Use of plasmapheresis (PLEX) or intravenous immunoglobulin (IVIg) can affect meaningful interpretation of serum anti-JCV antibody testing. Anti-JCV antibody testing should not be performed during or for at least two weeks following PLEX due to the removal of antibodies from the serum or within 6 months of IVIg (i.e., 6 months = 5 x half-life for immunoglobulins).
Magnetic Resonance Imaging Screening for PML
Before initiation of treatment with TYSABRI, a recent magnetic resonance imaging (MRI) scan should be available. Pre-treatment investigations (e.g., MRI) may be helpful in the evaluation of patients who develop signs or symptoms suggestive of PML. More frequent monitoring (e.g., every 3-6 months) should be considered for patients at higher risk of PML. This includes:
- Patients who have all three risk factors for PML (i.e., are anti-JCV antibody positive and have received more than 2 years of TYSABRI therapy, and have received prior immunosuppressant therapy),
Or
- Patients with an anti-JCV antibody index value of greater than 1.5 without prior history of immunosuppressant therapy and more than 2 years of natalizumab treatment.
PML in the absence of symptoms can be detected on MRI and must be confirmed by presence of JCV DNA in CSF or brain biopsy.
Assessing for PML
Typical symptoms of PML are diverse, progress over days to weeks, and include progressive weakness on one side of the body or clumsiness of limbs, disturbance of vision, and changes in thinking, memory and orientation leading to confusion and personality changes. Withhold TYSABRI dosing immediately at the first sign or symptom suggestive of PML.
Healthcare professionals should be particularly alert to symptoms suggestive of PML that the patient may not notice (e.g. cognitive or psychiatric symptoms). Patients should also be advised to inform their partner or caregivers about their treatment, since they may notice symptoms that the patient doesn’t.
Monitoring for PML should continue while the patient is receiving TYSABRI therapy and for a period of 6 months following treatment. PML has been reported following discontinuation of TYSABRI in patients who did not have findings suggestive of PML at the time of discontinuation. Patients and healthcare professionals should continue to be vigilant for any new signs or symptoms that may be suggested of PML for approximately 6 months following discontinuation of TYSABRI (see 7 WARNINGS AND PRECAUTIONS, Stopping TYSABRI Therapy).
At 2 years of treatment, physicians should inform patients again about the risks of TYSABRI, including that the risk of PML increases with longer treatment duration. Physicians should obtain consent from their patients for continuation of treatment. At 2 years of treatment, the patient, their partner and/or caregiver should be re-instructed about the early signs and symptoms of PML.
TYSABRI should be suspended immediately at the first signs or symptoms suggestive of PML and an evaluation that includes a magnetic resonance imaging (MRI) scan of the brain should be performed. When indicated, cerebrospinal fluid analysis for JC viral DNA is recommended to confirm a diagnosis of PML. If initial investigations prove negative but clinical suspicion for PML still remains, TYSABRI should not be restarted and repeat investigations should be undertaken.
Patients being treated with TYSABRI should be instructed to report any new neurological signs or symptoms to their physician.
There are no known interventions that can reliably prevent PML or adequately treat PML if it occurs. It is not known whether early detection of PML and discontinuation of TYSABRI will mitigate the disease. In the post-marketing setting, early detection of PML and suspension of TYSABRI therapy may have contributed to improved survival rates from PML compared with the TYSABRI pre-approval clinical trial PML cases. Plasma exchange has been used to reduce the serum levels of TYSABRI. (See PML and IRIS (Immune Reconstitution Inflammatory Syndrome) below.)
It is unclear whether the risk of PML is increased in MS patients treated with TYSABRI in combination with interferon beta compared to TYSABRI alone. TYSABRI should not be used in combination with other immunosuppressive or immunomodulatory agents, regardless of their class.
PML and IRIS (Immune Reconstitution Inflammatory Syndrome)
In TYSABRI treated patients who developed PML, Immune Reconstitution Inflammatory Syndrome (IRIS) has been described following discontinuation or removal of TYSABRI (by plasma exchange); this can lead to serious neurological complications. In patients who have undergone plasma exchange, IRIS has occurred within days to several weeks. IRIS presents as a worsening in neurological status that may be rapid, as a result of the sudden reconstitution of immune function. It can lead to serious neurological complications and may be fatal. Monitoring for development of IRIS and appropriate treatment of the associated inflammatory reaction involving the brain should be undertaken.
JCV Granule Cell Neuronopathy (GCN):
JCV also causes granule cell neuronopathy (GCN) which has been reported in patients treated with TYSABRI. Symptoms of JCV GCN include progressive unsteadiness in walking (ataxia), slurred slow speech with loss of normal rhythm (dysarthria), and/or incoordination of movements, and diagnosis and management of JCV GCN should follow guidance provided for PML (see Adverse Reactions, Post Market Adverse Drug Reactions, Infections).
Herpes Infections:
TYSABRI increases the risk of developing encephalitis and meningitis caused by herpes simplex and varicella zoster viruses. Serious, life-threatening, and sometimes fatal cases have been reported in the postmarketing setting in multiple sclerosis patients receiving TYSABRI.
Laboratory confirmation in those cases was based on positive PCR for viral DNA in the cerebrospinal fluid. The duration of treatment with TYSABRI prior to onset ranged from a few months to several years. Monitor patients receiving TYSABRI for signs and symptoms of meningitis and encephalitis. If herpes encephalitis or meningitis occurs, TYSABRI should be discontinued, and appropriate treatment for herpes encephalitis/meningitis should be administered.
Acute retinal necrosis (ARN) is a fulminant viral infection of the retina caused by the family of herpes viruses (eg. varicella zoster). ARN has been observed in patients being administered TYSABRI and can be potentially blinding. Patients presenting with eye symptoms such as decreased visual acuity, redness and painful eye should be referred for retinal screening for ARN. Following clinical diagnosis of ARN, discontinuation of TYSABRI should be considered in these patients (see Adverse Reactions, Post Market Adverse Drug Reactions, Herpes).
Other Opportunistic Infections:
Physicians should be aware of the possibility that other opportunistic infections may occur during TYSABRI therapy (including patients without co-morbidities or concurrent therapy) and should include them in the differential diagnosis of infections that occur in TYSABRI treated patients. Serious, life-threatening and sometimes fatal cases have been reported. If an opportunistic infection is suspected, dosing with TYSABRI is to be suspended until such infections can be excluded through further evaluations. If a patient receiving TYSABRI is diagnosed with an opportunistic infection, TYSABRI should only be restarted after the infection has been treated and if the benefit and risks of resuming TYSABRI therapy have been deemed to be acceptable by the treating physician.
Stopping TYSABRI Therapy:
If a decision is made to discontinue treatment with natalizumab, the physician needs to be aware that natalizumab remains in the blood, and has pharmacodynamic effects (e.g increased lymphocyte counts) for approximately 12 weeks following the last dose. Starting other therapies during this interval will result in a concomitant exposure to natalizumab. For medicinal products such as interferon and glatiramer acetate, concomitant exposure of this duration was not associated with safety risks in clinical trials. No data are available in MS patients regarding concomitant exposure with immunosuppressant medication. Use of these medicinal products soon after the discontinuation of natalizumab may lead to an additive immunosuppressive effect. This should be carefully considered on a case-by-case basis, and a wash-out period of natalizumab might be appropriate. Short courses of steroids used to treat relapses were not associated with increased infections in clinical trials.
Reproductive Health: Female and Male Potential
It is not known whether TYSABRI can affect reproductive potential (See 7.1.1 Pregnant Women)
Fertility
See 16 Non-Clinical Toxicology.
7.1 Special Populations
7.1.1 Pregnant Women
There are no adequate and well-controlled studies of TYSABRI therapy in pregnant women. In premarketing clinical trials, the extent of exposure is very limited.
Thrombocytopenia and anaemia in infants born to women exposed to natalizumab during pregnancy were reported in the post-marketing setting. Monitoring for platelet counts, haemoglobin and hematocrit is recommended in neonates born to women exposed to natalizumab during pregnancy.
Because animal reproduction studies are not always predictive of human response, this drug should only be used during pregnancy if clearly needed. If a woman becomes pregnant while taking TYSABRI, discontinuation of TYSABRI should be considered.
In reproductive studies in monkeys and guinea pigs, there was no evidence of teratogenic effects or effects on survival or growth of offspring at doses up to 30 mg/kg (7 times the human clinical dose based on body weight comparison). In one of five studies that exposed monkeys or guinea pigs during pregnancy, the number of abortions in treated (30 mg/kg) monkeys was 33% vs. 17% in controls. No effects on abortion rates were noted in any other study. A study in pregnant cynomolgus monkeys treated at 2.3-fold the clinical dose demonstrated natalizumab-related changes in the fetus. These changes included mild anemia, reduced platelet count, increased spleen weights, and reduced liver and thymus weights associated with increased splenic extramedullary hematopoiesis, thymic atrophy and decreased hepatic hematopoiesis. In offspring born to mothers treated with natalizumab at 7-fold the clinical dose, platelet counts were also reduced. This effect was reversed upon clearance of natalizumab. There was no evidence of anemia in these offspring.
7.1.2 Breast-feeding
TYSABRI has been detected in human milk. Because of this and the potential for serious adverse reactions in nursing infants from TYSABRI, a decision should be made whether to discontinue nursing or to discontinue the drug, taking into account the importance of the drug to the mother.
7.1.3 Pediatrics
Pediatrics (<18 years): Safety and effectiveness of TYSABRI in pediatric MS patients have not been established. Therefore, Health Canada has not authorized an indication for pediatric use (see 1.1 Pediatrics).
7.1.4 Geriatrics
Geriatrics (>65 years): Clinical studies of TYSABRI did not include sufficient numbers of patients to determine whether they respond differently than younger patients.
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
Serious adverse drug reactions most frequently reported during treatment with TYSABRI (natalizumab) in clinical trials were infections (3.2% vs. 2.6% placebo, including urinary tract infection [0.8% vs. 0.3%] and pneumonia [0.6% vs. 0%]); acute hypersensitivity reactions (1.1% vs. 0.3%, including anaphylaxis/anaphylactoid reaction [0.8% vs. 0%]); depression (1.0% vs. 1.0%, including suicidal ideation [0.6% vs. 0.3%]); and cholelithiasis (1.0% vs. 0.3%). See 7 WARNINGS AND PRECAUTIONS, Immune, Hypersensitivity Reactions.
The most frequently reported adverse events leading to discontinuation of TYSABRI therapy were urticaria (1%) and other hypersensitivity reactions (1%). See 7 WARNINGS AND PRECAUTIONS, Immune, Hypersensitivity Reactions.
In clinical trials, cases of PML have been reported. PML can cause severe disability or death. See 7 WARNINGS AND PRECAUTIONS, Infections, Progressive Multifocal Leukoencephalopathy.
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
In placebo-controlled trials in 1617 patients with multiple sclerosis treated with TYSABRI, the incidence of common events was balanced between the TYSABRI-treated patients and those who received placebo. Adverse events leading to discontinuation of therapy occurred in 5.8% of patients receiving TYSABRI and in 4.8% of patients receiving placebo. Events are listed in Table 3 by body system and frequency of occurrence in the TYSABRI group.
Table 3 All Adverse Events in Placebo-Controlled Studies of MS Occurring with Incidence ≥1.0% in TYSABRI Group and > 0.5% in TYSABRI Group than Placebo Group
TYSABRI n = 1617 (%) | Placebo n = 1135 (%) | |
Blood and lymphatic system disorders Anemia | 30 (1.9%) | 14 (1.2%) |
Cardiovascular Tachycardia | 23 (1.4%) | 9 (0.8%) |
Gastrointestinal Abdominal pain | 75 (4.6%) | 43 (3.8%) |
General disorders and administration site conditions Fatigue Oedema Peripheral Chest Pain Rigors Weight decreased | 445 (27.5%) 62 (3.8%) 58 (3.6%) 55 (3.4%) 27 (1.7%) | 305 (26.9%) 25 (2.2%) 35 (3.1%) 12 (1.1%) 11 (1.0%) |
Injury, poisoning, procedural complications Limb injury Thermal burn | 38 (2.4%) 29 (1.8%) | 20 (1.8%) 12 (1.1%) |
Immune system disorders Seasonal allergy | 58 (3.6%) | 35 (3.1%) |
TYSABRI n = 1617 (%) | Placebo n = 1135 (%) | |
Infections and infestations Influenza Sinusitis Upper respiratory tract infection viral Pharyngitis Gastroenteritis Tonsillitis Bladder infection Herpes zoster Respiratory tract infection Gingival infection | 225 (13.9%) 184 (11.4%) 134 (8.3%) 125 (7.7%) 56 (3.5%) 51 (3.2%) 38 (2.4%) 33 (2.0%) 30 (1.9%) 18 (1.1%) | 146 (12.9%) 122 (10.7%) 88 (7.8%) 59 (5.2%) 21 (1.9%) 23 (2.0%) 16 (1.4%) 16 (1.4%) 15 (1.3%) 6 (0.5%) |
Musculoskeletal and connective tissue disorders Muscle Cramp Joint swelling | 82 (5.1%) 32 (2.0%) | 42 (3.7%) 13 (1.1%) |
Nervous system disorders Headache Dysesthesia Sinus headache | 634 (39.2%) 42 (2.6%) 38 (2.4%) | 436 (38.4%) 23 (2.0%) 19 (1.7%) |
Psychiatric disorders Depressed mood | 37 (2.3%) | 16 (1.4%) |
Reproductive system and breast disorders Menstruation irregular | 37 (2.3%) | 12 (1.1%) |
Respiratory, thoracic and mediastinal disorders Cough Sinus congestion Epistaxis | 130 (8.0%) 51 (3.2%) 28 (1.7%) | 81 (7.1%) 22 (1.9%) 13 (1.1%) |
Vascular disorders Hematoma | 17 (1.1%) | 6 (0.5%) |
Additional Information:
Hypersensitivity:
In post-marketing experience, there have been reports of hypersensitivity reactions with hypotension, hypertension, chest pain, chest discomfort, dyspnoea, and angioedema, in addition to more usual symptoms such as rash and urticaria.
The incidence of hypersensitivity reactions was based on the investigator assessment that the event was urticaria or an allergic reaction, which may have included terms such as urticaria, itch, flushing, hypersensitivity or anaphylactoid reaction. In controlled clinical trials in MS patients, hypersensitivity reactions occurred in up to 4% of patients. Serious systemic hypersensitivity reactions (e.g. anaphylactic/anaphylactoid) occurred in <1% (study 1801: 5/627) of MS patients. Hypersensitivity reactions usually occurred within two hours of the start of the infusion.
Immunogenicity:
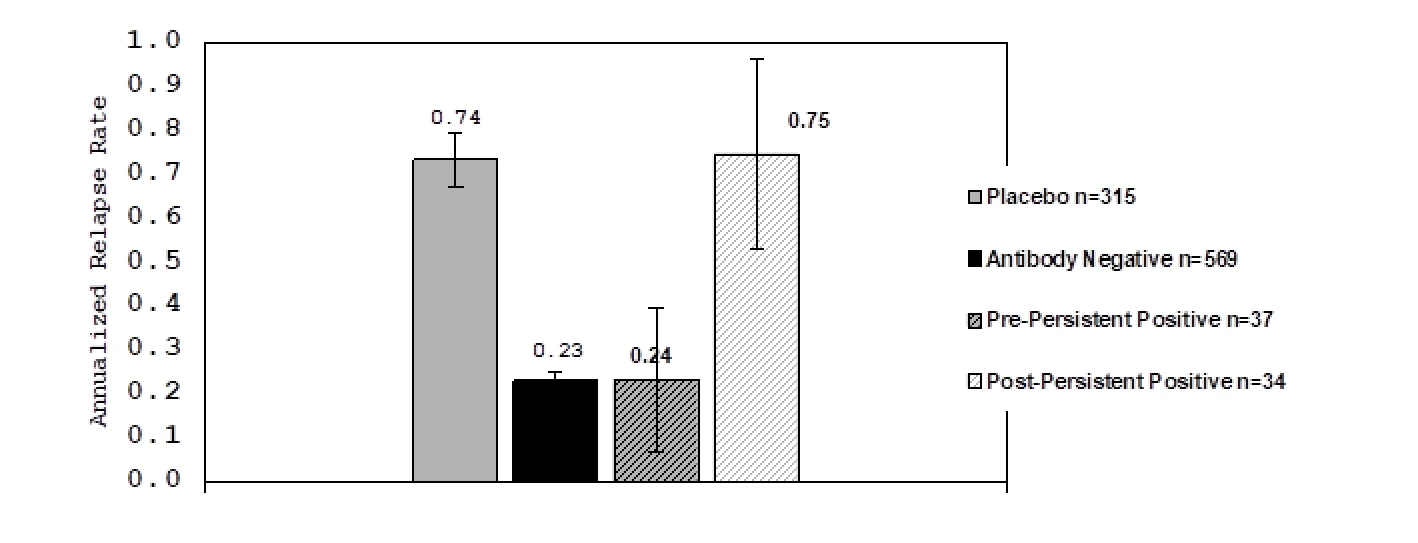
Persistent anti-natalizumab antibodies (detected on two occasions at least 6 weeks apart) were associated with decreased efficacy of TYSABRI and an increased incidence of hypersensitivity reactions. The majority of patients who became persistently antibody-positive had developed antibodies by 12 weeks.
In controlled clinical trials in MS patients, persistent anti-natalizumab antibodies developed in approximately 6% of patients. Antibodies were detected on only one occasion in 4% of patients. Additional infusion-related reactions associated with persistent antibodies included rigors, nausea, vomiting and flushing. Approximately 90% of patients who became persistently antibody-positive in 2-year clinical trials had developed antibodies by 12 weeks.
If, after 3 months of TYSABRI treatment, the presence of persistent antibodies is suspected, or in patients who have received an initial short exposure to TYSABRI and extended periods without treatment, antibody testing should be performed. Antibodies may be detected and confirmed with sequential serum antibody tests. Antibodies detected early in the treatment course (e.g. within 6 months) may be transient and disappear with continued dosing. Repeat testing between 6 weeks and 3 months after the initial positive result is recommended in patients in whom antibodies are detected to confirm that antibodies are persistent. In the presence of persistent antibodies, discontinuation of treatment with TYSABRI should be considered (see Figure 2).
Patients who receive TYSABRI for a short exposure (1-2 doses) followed by an extended period without treatment are at higher risk of developing anti-natalizumab antibodies and/or hypersensitivity reactions on re-exposure. Given that patients with persistent antibodies to TYSABRI experienced reduced efficacy and that hypersensitivity reactions were more common in such patients, consideration should be given to testing for the presence of persistent antibodies prior to redosing following a prolonged dose interruption.
Information regarding the availability and location of testing laboratories may be obtained by contacting Biogen Canada at 1-855-MSONE-00 (1-855-676-6300).
Figure 2: Subject Relapse Rate Prior to and After Antibody Detection – Persistent Positives – Study 1801.
Infections:
In controlled clinical trials in MS patients, the rate of infection was approximately 1.5 per patient year in both TYSABRI and placebo-treated patients. The nature of the infections was generally similar in TYSABRI and placebo-treated patients. The majority of patients did not interrupt TYSABRI therapy during infections, and recovery occurred with appropriate treatment.
In clinical trials, cases of PML have been reported (see Warnings and Precautions, Infections; Adverse Drug Reaction Overview).
In other clinical trials, cases of opportunistic infections have been reported, some of which were fatal. While a causal role for natalizumab cannot be excluded, it is reasonable to conclude that comorbidities and concomitant medications played an important role in these infections. Should a serious opportunistic infection develop, TYSABRI therapy should be withheld until the infection has been successfully treated.
TYSABRI should only be restarted after the infection has been treated and if the benefit and risks of resuming TYSABRI therapy have been deemed to be acceptable by the treating physician (see Warnings and Precautions, Infections, Other Opportunistic Infections).
In clinical trials, herpes infections occurred slightly more frequently in natalizumab-treated patients than in placebo-treated patients. During post-marketing experience, there have been rare reports of serious cases including encephalitis and meningitis; some cases have been life-threatening and sometimes fatal. Should a serious herpes infection occur, TYSABRI therapy should be withheld until the infection has been treated.
Short courses of corticosteroids can be used in combination with TYSABRI. In phase 3 MS clinical trials, concomitant treatment of relapses with a short course of corticosteroids was not associated with an increased rate of infection in patients treated with TYSABRI as compared with those on placebo.
Infusion-Related Reactions:
An infusion-related reaction was defined in clinical trials as any adverse event occurring within 2 hours of the start of an infusion. These events occurred in 23.1% of MS patients treated with TYSABRI (18.7% placebo). Events reported more commonly with TYSABRI than with placebo included headache, dizziness, fatigue, urticaria, pruritus and rigors.
Malignancies:
No differences in incidence rates or the nature of malignancies between TYSABRI and placebo-treated patients were observed over 2 years of treatment. However, observation over longer treatment periods is required before any effect of TYSABRI on malignancies can be excluded. Should a malignancy develop, TYSABRI therapy should be withheld at least until appropriate treatment has been initiated for the malignancy and the benefit and risks of resuming TYSABRI therapy have been deemed to be acceptable by the treating physician.
8.3 Less Common Clinical Trial Adverse Reactions
The incidence of adverse drug reactions experienced by <1% of subjects in natalizumab group and at least 0.1% higher in natalizumab compared to placebo are listed below:
Blood and lymphatic system disorders: Anemia, thrombocytopenia, leukocytosis
Cardiac disorders: Tachycardia, angina pectoris
Ear and labyrinth disorders: Vertigo
Gastrointestinal disorders: Flatulence, upper abdominal pain, abdominal distention, epigastric discomfort
General disorders and administration site conditions: Feeling hot, peripheral edema, lethargy, feeling abnormal, infusion site erythema, pain, thirst, hyperpyrexia, infusion site pruritus
Immune system disorders: Hypersensitivity, anaphylactoid reaction, anaphylactic reaction
Infections and infestations: Progressive multifocal leukoencephalopathy, pharyngitis, sinusitis, herpes simplex, herpes zoster, rhinitis infective, bronchial infection, gastroenteritis, skin and subcutaneous tissue abscess, furuncle, pharyngitis streptococcal, bladder infection, breast abscess, dermatitis infected, herpes viral infection, oral infection, pharyngitis viral, tooth infection, urinary tract infection
Injury, poisoning and procedural complications: Overdose
Investigations: Aspartate aminotransferase increased, neutrophil count increased, heart rate increased, neutrophil count decreased, white blood cell count increased, blood test abnormal
Musculoskeletal and connective tissue disorders: Myalgia, muscle cramp, muscle spasms, sensation of heaviness, joint stiffness, muscle tightness, muscle weakness
Neoplasms benign, malignant and unspecified (incl cysts and polyps): Cyst
Nervous system disorders: Tremor, paresthesia oral, sensory disturbance, paresis, psychomotor hyperactivity, syncope
Psychiatric disorders: Depression, agitation
Reproductive system and breast disorders: Irregular menstruation
Respiratory, thoracic and mediastinal disorders: Cough, sinus congestion, wheezing, throat irritation
Skin and subcutaneous tissue disorders: Erythema, rash pruritic, acne, pruritus, urticaria, dry skin, onychorrhexis, skin irritation
Vascular disorders: Petechiae, poor venous access, thrombophlebitis, vasodilatation
8.5 Post-Market Adverse Reactions
The following adverse reactions have been identified during post-marketing use of TYSABRI. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or to establish a causal relationship to drug exposure.
Hypersensitivity: There have been reports of hypersensitivity reactions which have been associated with one or more of the following: hypotension, hypertension, chest pain, chest discomfort, and dyspnea.
Hepatic: There have been rare reports of clinically significant liver injury, including markedly elevated serum hepatic enzymes and elevated total bilirubin, as early as 6 days after the first dose. In some patients, liver injury recurred upon rechallenge. Some cases occurred in patients with pre-existing liver disease or in the presence of other drugs that have been associated with hepatic injury.
Infections:
Progressive Multifocal Leukoencephalopathy:
There have been rare reports of progressive multifocal leukoencephalopathy (PML) in patients with MS receiving TYSABRI monotherapy, including cases with onset in the absence of clinical symptoms of PML. Some cases have been reported up to 6 months following discontinuation of TYSABRI monotherapy (see Warnings and Precautions, Infections, Progressive Multifocal Leukoencephalopathy).
Patients who have all three risk factors for PML (i.e. anti-JCV antibody positive AND have received more than 2 years of TYSABRI therapy AND have received prior immunosuppressant therapy) are at a higher risk of PML.
Anti-JCV antibody testing may provide supportive information for PML risk stratification prior to or during treatment with TYSABRI.
Cases of JCV GCN have also been reported during postmarketing use of TYSABRI.
Herpes: There have been rare reports of serious cases of herpes infections.
In post marketing experience, acute retinal necrosis (ARN) has been observed at a higher incidence in patients receiving natalizumab. Some cases have occurred in patients with central nervous system (CNS) herpes infections (eg. herpes meningitis and encephalitis). Serious cases of ARN, either affecting one or both eyes, led to blindness in some patients. The treatment reported in these cases included anti-viral therapy and in some cases, surgery.
Hematologic: In post-marketing experience, there have been reports of eosinophilia (eosinophil count > 1,500/mm3) without clinical findings. In cases where TYSABRI therapy was discontinued the elevated eosinophil levels resolved. Rare serious cases of anemia and hemolytic anemia have been reported in patients treated with TYSABRI in post-marketing observational studies.
Cases of thrombocytopenia, some of which were serious, in infants born to women exposed to TYSABRI during pregnancy were reported in the postmarketing setting. Cases of anemia were reported in infants born to women exposed to TYSABRI. Therefore, monitoring for hematological abnormalities is recommended in neonates who were exposed to TYSABRI in utero (see 7.1.1 Pregnant Women).
In post-marketing experience, there have been reports of uncommon frequency of thrombocytopenia and immune thrombocytopenic purpura (ITP), some of which were serious (see 7 WARNINGS AND PRECAUTIONS, Hematologic).
9 DRUG INTERACTIONS
9.2 Drug Interactions Overview
If a decision is made to discontinue treatment with TYSABRI, the physician needs to be aware that TYSABRI has pharmacodynamic effects (e.g. increased lymphocyte counts) for approximately 12 weeks following the last dose. For drugs such as interferon and glatiramer acetate, concomitant exposure of this duration was not associated with safety risks in clinical trials. This should be carefully considered on a case-by-case basis and a washout period of TYSABRI might be appropriate.
Should TYSABRI therapy be administered after treatment with another immunosuppressive drug, physicians should consider the half-life of the drug and the potential for persistent immunosuppressive effects of these products when considering if a washout period is needed and, if so, its duration.
TYSABRI should not be diluted with anything other than 0.9% Sodium Chloride Injection, USP.
9.3 Drug-Behavioural Interactions
Drug-Behavioural Interactions have not been established.
9.4 Drug-Drug Interactions
Interactions with other drugs have not been established.
9.5 Drug-Food Interactions
Interactions with food have not been established.
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
In clinical trials, TYSABRI was observed to induce increases in circulating lymphocytes, monocytes, eosinophils and nucleated red blood cells. Observed increases persisted during TYSABRI exposure, but were reversible, returning to baseline levels usually within 16 weeks after the last dose. Elevations of neutrophils were not observed.
TYSABRI may induce mild decreases in hemoglobin levels (mean decrease of 6.0 g/L). Hemoglobin levels returned to pretreatment values, usually within 16 weeks of last dose of TYSABRI and the changes were not associated with clinical symptoms.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
TYSABRI (natalizumab) is a selective adhesion molecule (SAM) inhibitor and binds to the α4-subunit of human integrin, which is highly expressed on the surface of all leukocytes, with the exception of neutrophils.
Specifically, natalizumab binds to the α4β1 integrin blocking the interaction with its cognate receptor, vascular cell adhesion molecule-1 (VCAM-1), and additional ligands such as osteopontin, and an alternatively spliced domain of fibronectin, connecting segment-1 (CS-1). Natalizumab blocks the interaction of α4β7 integrin with the mucosal addressin cell adhesion molecule-1 (MadCAM-1). Disruption of these molecular interactions prevents transmigration of mononuclear leukocytes across the endothelium into inflamed parenchymal tissue. A further mechanism of action of natalizumab may be to suppress ongoing inflammatory reactions in diseased tissues by inhibiting the interaction of α4-expressing leukocytes with their ligands in the extracellular matrix and on parenchymal cells. As such, natalizumab may act to suppress inflammatory activity present at the disease site, and inhibit further recruitment of immune cells into inflamed tissues.
In multiple sclerosis (MS), lesions are believed to occur when activated inflammatory cells, including T-lymphocytes, cross the blood-brain barrier (BBB). Leukocyte migration across the BBB involves interaction between adhesion molecules on inflammatory cells and endothelial cells of the vessel wall. The interaction between α4β1 and its targets is an important component of pathological inflammation in the brain, and disruption of these interactions leads to reduced inflammation. Under normal conditions, VCAM-1 is not expressed in the brain parenchyma. However, in the presence of pro-inflammatory cytokines, VCAM-1 is upregulated on endothelial cells, and possibly on glial cells near the sites of inflammation. In the setting of central nervous system (CNS) inflammation in MS, it is the interaction of α4β1 with VCAM-1, CS-1 and osteopontin that mediates the firm adhesion and transmigration of leukocytes into the brain parenchyma, and may perpetuate the inflammatory cascade in CNS tissue. Blockade of the molecular interactions of α4β1 with its targets reduces inflammatory activity present in the brain in MS and inhibits further recruitment of immune cells into inflamed tissue, thus reducing the formation or enlargement of MS lesions.
10.2 Pharmacodynamics
Treatment with TYSABRI (natalizumab) led to an increase in circulating white blood cells and total lymphocytes that was maintained throughout the treatment period. This is due to the ability of natalizumab to inhibit adhesion of leukocytes to endothelial cells and diminish transmigration of these cells from the vascular space into inflamed tissues. These increases were not clinically significant and once treatment was discontinued, counts returned to baseline levels. Consistent with the mechanism of action of natalizumab and the lack of α4 on the surface of this cell type, there was no change in the number of circulating neutrophils.
In study 101MS101, α4-integrin saturation levels were generally consistent with those observed in the phase 3 studies (C-1801 and C-1802). In these studies which demonstrated efficacy, α4-integrin saturation approximating 70% was observed, however there was a high degree of assay variability.
10.3 Pharmacokinetics
Pharmacokinetic values determined after a single 300 mg dose of TYSABRI in healthy subjects are provided in Table 4. Similar values observed in MS patients after a single dose and after 6 months of dosing as monotherapy are given in Table 5. Some accumulation occurs over the 6-month dosing period.
Table 4: Pharmacokinetic Parameters, Single-Dose 300 mg Natalizumab as Intravenous Infusion of 60 minutes
| Median Values of Parameter | Study 1805 | Study 1806 |
| AUCτ (μg/mL *hr) | 19900 | 21500 |
| Cmax (μg/mL) | 110 | 94 |
| Tmax (hrs) | 2.98 | 3.00 |
| t ½ (hr) | 224 | 249 |
| Vdis (mL/kg) | 66.6 | 67.4 |
| CL (mL/hr/kg) | 0.212 | 0.179 |
Table 5: Summary of Pharmacokinetic Parameters Following 60-Minute 300 mg Natalizumab Infusions Given Monthly in MS Patients (Mean +/- s.d.)
| Dose Numbe r | Study | Cmax (µg/mL) | Minimum (Trough) Conc. (µg/mL) | AUC(last) (µg×hr/mL) | Vd (mL/kg) | CL (mL/hr/kg ) | t½ (hr) |
| 1 | C-1801 | 84.8 ± 22.3 | none | 17884 ± 9165 | 77 ± 36 | 0.23 ± 0.09 | 249 ± 105 |
| 6 | C-1801 | 94.7 ± 34.2 | 21.3 ± 15.3* | 19609 ± 5701 | 81 ± 43 | 0.22 ± 0.06 | 265 ± 98 |
*Representative of concentration at the end of 6-months dosing (24-week measurement)
Clinical studies, 101MS101 and 101MS102, demonstrated that the pharmacokinetic, pharmacodynamic, immunogenicity and safety profiles of drug product produced from a high yield drug substance manufacturing process are comparable to the drug product produced from the original drug substance manufacturing process.
Special Populations and Conditions
- Pediatrics: The pharmacokinetics of TYSABRI in pediatric MS patients have not been established.
- Geriatrics: The pharmacokinetics of TYSABRI in MS patients over 65 years of age have not been established.
- Sex: Results of a population pharmacokinetic demonstrated that gender did not influence natalizumab pharmacokinetics.
- Ethnic Origin: The effects of race on the pharmacokinetics of TYSABRI have not been studied.
- Hepatic Insufficiency: The pharmacokinetics of TYSABRI in patients with hepatic insufficiency have not been studied.
- Renal Insufficiency: The pharmacokinetics of TYSABRI in patients with renal insufficiency have not been studied.
Duration of Effect:
TYSABRI has pharmacodynamic effects (e.g. increased lymphocyte counts) for approximately 12 weeks following the last dose.
11 STORAGE, STABILITY AND DISPOSAL
TYSABRI (natalizumab) single-use vials must be stored in a refrigerator between 2°C to 8°C. Do not use beyond the expiration date on the carton and vial label. Do not shake or freeze. Protect from light.
If not used immediately, store the TYSABRI solution for infusion at 2°C to 8°C. The administration of TYSABRI solution for infusion must be completed within 72 hours of dilution.
Any unused product or waste material should be disposed of in accordance with local requirements.
12 SPECIAL HANDLING INSTRUCTIONS
TYSABRI (natalizumab) is for single use only. One vial of TYSABRI should be diluted only with 0.9% Sodium Chloride Injection, USP before use.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: natalizumab
Chemical name: Recombinant, humanized, anti-α4–integrin monoclonal antibody
Molecular formula and molecular mass: Approximately 149 kilodaltons.
Physicochemical properties: Natalizumab is produced by recombinant DNA technology in a mouse NS/0 cell line. Natalizumab is of the IgG4 subclass and consists of two heavy and two light chains connected by four inter-chain disulfide bonds.
Product Characteristics:
TYSABRI (natalizumab) is a recombinant humanized IgG4κ monoclonal antibody selective for α4-integrin. Natalizumab is produced in murine myeloma cells. The molecular weight of natalizumab is 149 kilodaltons. TYSABRI is supplied as a sterile, colourless, clear to slightly opalescent concentrate for solution for intravenous (IV) infusion.
14 CLINICAL TRIALS
14.1 Clinical Trials by Indication
Multiple Sclerosis (MS):
Table 6 - Summary of patient demographics for clinical trials in MS
| Study # | Study design | Dosage, route of administration and duration | Study subjects (n) | Median age (Range) | Sex |
| Pivotal Studies | |||||
1801 AFFIRM | Randomized, double-blind, placebo-controlled study. MS patients who had experienced at least one clinical relapse during the prior year. EDSS score between 0.0 and 5.0 | 300 mg IV or placebo every 4 weeks for up to 30 infusions | 942 (627 TYSABRI and 315 placebo) | 37 (18-50) | F: 660 (70%) M: 282 (30%) |
1802 SENTINEL | Randomized, double-blind, placebo-controlled study. MS patients who had experienced at least one clinical relapse during the prior year on therapy with Avonex 30 μg intramuscularly (IM) once weekly. EDSS score between 0.0 and 5.0 | 300 mg IV or placebo in combination with Avonex 30 μg IM once weekly every 4 weeks for up to 30 infusions | 1171 (589 TYSABRI and 582 in combination with Avonex) | 39 (18-55) | F: 862 (74%) M: 309 (26%) |
| Supportive Studies | |||||
| MS-231 | Randomized, double-blind, placebo-controlled multicentre study in patients with relapsing remitting MS or secondary progressive MS | 3 mg/kg, 6 mg/kg or placebo every 28 days for 6 infusions | 213 (71 placebo, 68 TYSABRI 3 mg/kg, 74 TYSABRI 6 mg/kg) | 44 (22-66) | F: 152 (71.4%) M: 61 (28.6%) |
Study Results:
Table 7 - Results of study 1801 (AFFIRM) in MS
TYSABRI* n=627 | Placebo* n=315 | pvalue | |
| Clinical Endpoints | |||
Percentage with sustained progression of disability (increase in EDSS sustained for 12 weeks) Hazard ratio Risk reduction | 17% 29% 0.58, (95% CI 0.43, 0.77) 42% | p<0.001 | |
Percentage with sustained progression of disability (increase in EDSS sustained for 24 weeks) Hazard ratio Risk reduction | 11% 23% 0.46 (95% CI 0.33, 0.64) 54% | p<0.001 | |||
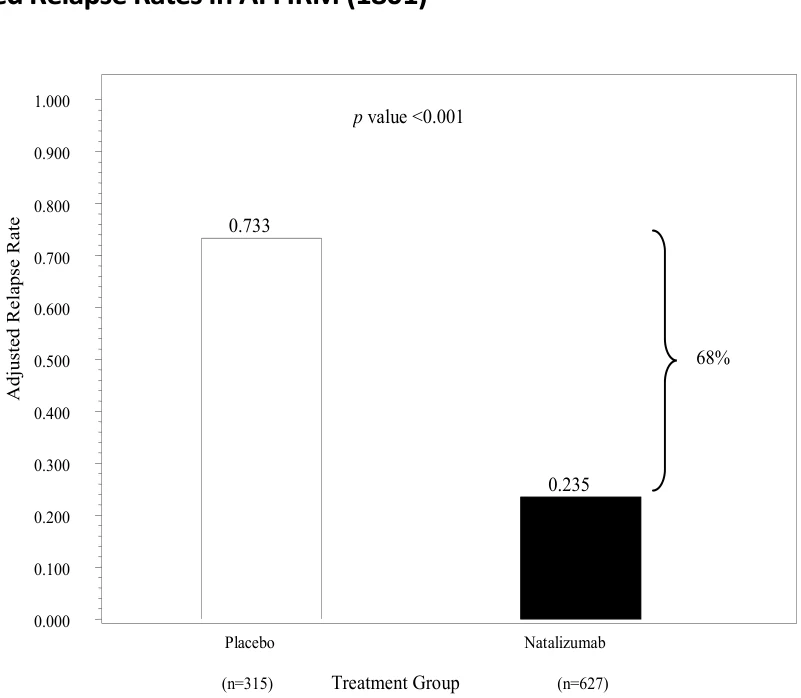
Annualized relapse rate (Percent reduction compared with placebo) | 0.24 0.73 (68%) | p<0.001 | |||
| Percentage of patients relapse-free after 2 years | 67% | 41% | p<0.001 | ||
| MRI Endpoints | |||||
| Median percentage change in volume of T2-hyperintense lesions | -9.4% | 8.8% | p<0.001 | ||
Number of new or newly-enlarging T2-hyperintense lesions Mean Percent reduction compared with placebo | |||||
- 1.9 11.0
| 83% | p<0.001 | |||
Median Percentage of patients with: 0 lesions 1 lesion 2 lesions 3 or more lesions | 0.0 57% 17% 8% 18% | 5.0 15% 10% 8% 68% | p<0.001 | |
Number of Gd-enhancing Lesions Mean Percent reduction compared with placebo | ||||
- 0.1 1.2
| 92% | p<0.001 | |||
Median Percentage of patients with: 0 lesions 1 lesion 2 or more lesions | 0.0 97% 2% 1% | 0.0 72% 12% 16% | p<0.001 | |
*All analyses were intent-to-treat.
Figure 3: Time to Sustained Progression of Disability as Measured by Increase in EDSS in AFFIRM (1801)
Figure 4: Annualized Relapse Rates in AFFIRM (1801)
Comparing studies 1801 and 1802, at baseline, those patients in 1802 had, on average, longer disease duration and higher EDSS scores than patients in study 1801.
The efficacy of TYSABRI alone was not compared with the efficacy of TYSABRI plus Avonex.
Other Clinical Endpoints:
Brain Atrophy:
Brain parenchymal fraction (BPF) is a marker of the destructive pathologic process ongoing in relapsing MS patients, with changes measuring a loss of brain tissue.
In the monotherapy study, 1801, the BPF interval changes at 1 year and 2 years suggests a pattern that differs between the placebo and treated groups. Although both groups exhibited a decrease in BPF from baseline to year 1, there was a relatively greater reduction in the natalizumab group compared to the placebo group (natalizumab vs. placebo: 0.56% vs. 0.40%, p=0.002). Between 1 and 2 years, the placebo group again demonstrated an equivalent reduction in brain volume (0.43%) comparable to year 1 while the reduction observed in the natalizumab-treated group decreased to 0.24% indicating a significant slowing of atrophy compared to the placebo group (p= 0.004).
From baseline to 1 year the placebo- and natalizumab-treated groups had a decreased BPF during the first year with a relatively greater reduction in the natalizumab treated groups. The disproportionate reduction in the natalizumab-treated groups during the first year is likely due to an acute reduction in inflammation and edema. The lower rate of atrophy seen in the
second year of each study likely reflects the significant anti-inflammatory treatment effects of natalizumab on atrophy progression.
Hospitalization:
The number of hospitalizations was recorded in phase 3 studies. Table 8 summarizes the number of hospitalizations whose primary reason was categorized as MS relapse, MS-related complication, elective surgery or “other”. The number of hospitalizations for MS-related or MS relapses, reported separately, followed a similar pattern to all hospitalizations.
Table 8: Rate of Hospitalization
| AFFIRM (1801) | ||||||||
| Placebo | TYSABRI | |||||||
| Number of subjects with a hospitalization (%) | 77 (24%) | 114 (18%) | ||||||
| Total number of hospitalizations | 125 | 156 | ||||||
| Annualized hospitalization rate (95% CI) | 0.183 (0.142, 0.236) | 0.112 (0.089, 0.140) | Rate ratio 0.612 (0.436, 0.858) p=0.005 | |||||
| Number of subjects with MS-related hospitalizations (%) | 41 (13%) | 37 (6%) | ||||||
| Total number of MS-related hospitalizations | 66 | 48 | ||||||
| Annualized MS-related hospitalization rate (95% CI) | 0.097 (0.070, 0.133) | 0.034 (0.024, 0.050) | Rate ratio 0.356 (0.218, 0.582) p<0.001 | |||||
Quality of Life (QOL):
The Multiple Sclerosis Quality of Life Index (MSQLI) consists of several scales to measure important symptoms experienced by MS patients as part of their disease. Patients treated with TYSABRI alone showed on average an increase in both the physical and mental component scores of the SF-36 indicating improvement, whereas those who received placebo showed worsening on average (p≤0.01). No statistically significant differences were observed between treatment groups on the non-SF-36 components. Indeed, there were minimal changes in either group on many of these measures.
Patients were asked how they were feeling during the study and to mark this on a 10 cm Visual Analogue Scale (VAS), with 0 as “poor” and 100 as “excellent”. On average, patients treated with TYSABRI had a significant effect on sense of well-being vs. patients treated with placebo using the VAS (p=0.007).
Subgroup Analyses of Efficacy:
Results for disability progression and clinical relapses have been tabulated by baseline EDSS (≤3.5, >3.5), the number of T2 lesions at baseline (<9, ≥9), presence or absence of Gd-lesions and age at baseline (<40, ≥40 years).
TYSABRI consistently delayed disability progression and reduced relapse rates in most clinical subpopulations, even those with the highest degree of disease activity. Although the subgroup of patients with fewer than 9 T2 lesions at baseline showed a treatment effect on the secondary MRI outcome measures, they did not show a similar effect on the primary clinical outcome measures; this may be due to the small numbers in this group. To the contrary, a significant effect was seen in those subjects with 9 or more T2 lesions at baseline. Patients with MS defined by McDonald diagnostic criteria 1 through 4 demonstrated consistent clinical responses to TYSABRI, although the subgroup defined by McDonald diagnostic criteria 1 or 2 appeared to have a greater response than criteria 3 or 4. These data indicate that the degree of MS disease activity should be a consideration when starting TYSABRI treatment.
There were twice as many women as men in study 1801. Treatment with TYSABRI was equally effective for both women and men across all 2-year endpoints.
Using the Multiple Sclerosis Functional Composite Score (Timed 25-Foot Walk [T25FW], 9 Hole Peg Test [9HPT], and the Paced Auditory Serial Addition Test 3 [PASAT3]), in study 1801, the group treated with TYSABRI showed statistically significant improvement in the overall score (p<0.0001), and on each parameter (T25FW: p<0.0001, 9HPT: p<0.0001, PASAT3: p=0.005) compared to the placebo-treated group.
In study 1801, there was a statistically significant relative reduction (69% p<0.001) in the rate of relapses treated with steroids (43% placebo-treated group vs. 13% of the TYSABRI-treated group experienced relapses).
Phase 2 Clinical Study
In a randomized, double-blind phase 2 trial (MS-231), a total of 213 patients with relapsing-remitting (RRMS, n=144) and relapsing secondary progressive (SPMS, n=69) multiple sclerosis received either placebo (n=71) or TYSABRI 3 mg/kg/body weight (n=68) or 6 mg/kg/body weight (n=74) every 28 days for 6 months. The primary endpoint was the number of new brain lesions on monthly gadolinium-enhanced magnetic resonance imaging during the 6-month treatment period. Clinical outcomes included relapses and self-reported well-being. The results indicated that both groups treated with TYSABRI had fewer enhancing lesions compared to the placebo-treated group. This difference was statistically significant (p<0.001). A similar result was noted for the number of patients with a relapse (p= 0.02), or with an objective relapse (p=0.004), or requiring corticosteroid treatment (p <0.001). Overall patients treated with TYSABRI had an improved sense of well-being using the Visual-Analog Score. During this study TYSABRI was well tolerated with a safety profile similar to that of placebo. Headache was the most common reported adverse event. The clinical significance of a trend toward an increased rate of infection in the TYSABRI-treated patients was unclear.
DETAILED PHARMACOLOGY
The pharmacokinetics and pharmacodynamics of TYSABRI (natalizumab) were evaluated in a total of three single-infusion studies in healthy volunteers and nine single- and repeat-infusion studies in MS patients. The intravenous infusion was given over 30 to 60 minutes. In the single-infusion studies, natalizumab was administered at doses ranging from 0.03 mg/kg to 6 mg/kg. In the repeat-infusion phase 2 studies, natalizumab was administered monthly at doses of 3 mg/kg and 6 mg/kg for up to 6 months. In the phase 3 studies, TYSABRI was administered monthly as a 300 mg fixed dose for a minimum of 6 months. Three studies evaluated the pharmacokinetics and pharmacodynamics of natalizumab when concurrently administered with other therapies including Avonex (interferon beta-1a) and glatiramer acetate.
Pharmacokinetic parameter estimates were derived using traditional methods. Serum concentration data profiles were analyzed noncompartmentally. Parameters describing the disposition of natalizumab included the maximum serum concentration (Cmax), area under the concentration-time curve (AUC 0-last and AUC 0-infinity), volume of distribution (Vd), clearance (CL) and elimination half-life (t ½).
Pharmacodynamic markers consistent with the mechanism of action of natalizumab were collected throughout the clinical studies. These markers included elevated peripheral white blood cell (WBC) and lymphocyte counts and the determination of α4-integrin receptor occupancy (% saturation) on peripheral blood mononuclear cells (PBMC). Since WBC counts include neutrophils, which are the only major leukocyte class that does not express α4-integrins, lymphocyte counts are considered a more sensitive pharmacodynamic marker of natalizumab activity.
All subjects were screened for the development of anti-natalizumab antibodies and the effect on the pharmacokinetics and pharmacodynamics of natalizumab was evaluated.
Pharmacokinetic Results
Following the single-infusion IV administration of natalizumab at doses ranging from 0.3 to 3 mg/kg and a fixed dose of 300 mg to healthy volunteers, Cmax values were proportional to the administered dose. At doses of 1 mg/kg and greater, mean CL, Vd and t½ values were relatively consistent and independent of actual administered dose.
When administered as a 300 mg fixed dose, the pharmacokinetics of natalizumab were consistent with that observed following weight-based dosing at 3 mg/kg.
Table 9. Summary of Pharmacokinetic Parameters Following a 30- to 60-Minute Single-Infusion Administration of Natalizumab in Healthy Volunteers (mean +/- s.d.)
| Study | Dose (mg/kg) | Cmax (µg/mL) | AUC(last) (µg×hr/mL) | Vd (mL/kg) | CL (mL/hr/kg) | t½ (hr) |
| 101 | 0.3 | 7.6 ± 1.9 | 342 ± 144 | 88 ± 30 | 1.01 ± 0.50 | 49 ± 13 |
| 101 | 1.0 | 22.4 ± 3.8 | 2272 ± 430 | 63 ± 8 | 0.44 ± 0.01 | 118 ± 23 |
| 101 | 3.0 | 71.8 ± 4.8 | 11044 ± 1157 | 53 ± 8 | 0.26 ± 0.04 | 202 ± 38 |
| C-1805 | 300 mg* | 114.3 ± 39.3 | 19625 ± 5539 | 72 ± 44 | 0.22 ± 0.06 | 234 ± 159 |
| C-1805 | 300 mg*b | 120.3 ± 44.2 | 20676 ± 6933 | 71 ± 32 | 0.22 ± 0.08 | 230 ± 86 |
| C-1806 | 300 mg* | 99.7 ± 29.2 | 22880 ± 9408 | 73 ± 34 | 0.20 ± 0.07 | 266 ± 154 |
| C-1806 | 300 mg* | 100.3 ± 30.3 | 23215 ± 8113 | 70 ± 30 | 0.19 ± 0.06 | 263 ± 127 |
*Fixed dose
Similar to healthy volunteers, following single-infusion IV administration of natalizumab at doses ranging from 0.3 to 6 mg/kg in MS patients, Cmax values were proportional to the administered dose. At doses of 1 mg/kg and greater, mean CL, Vd and t½ values were relatively consistent and independent of the actual administered dose, as noted in the following table. The Vd was consistent with plasma volume.
Table 10. Summary of Pharmacokinetic Parameters Following a 45- to 60-Minute Single-Infusion Administration of Natalizumab in MS Patients (Mean +/- s.d.)
Dose (mg/kg) | Study | Cmax (µg/mL) | AUC(last) (µg×hr/mL) | Vd (mL/kg) | CL (mL/hr/kg) | t½ (hr) |
| 0.3 | MS200 | 4.3 ± 0.5 | 204 ± 49 | 75 ± 12 | 1.45 ± 0.42 | 37 ± 4 |
| 1.0 | MS200 | 13.8 ± 2.5 | 1627 ± 386 | 81 ± 10 | 0.64 ± 0.17 | 92 ± 28 |
| 1.0 | MS202 | 23.5 ± 10.1 | 2044 ± 923 | 74 ± 91 | 0.57 ± 0.46 | 94 ± 30 |
| 1.0 | MS221 | 22.2 ± 5.0 | 1793 ± 897 | 72 ± 31 | 0.62 ± 0.38 | n.d.† |
| 3.0 | MS200 | 52.5 ± 12.0 | 9778 ± 1380 | 67 ± 17 | 0.31 ± 0.04 | 108 ± 30 |
| 3.0 | MS202 | 70.0 ± 27.1 | 8920 ± 3003 | 75 ± 30 | 0.35 ± 0.11 | 145 ± 49 |
| 3.0 | MS221 | 70.6 ± 18.6 | 8726 ± 3493 | 67 ± 20 | 0.39 ± 0.14 | 129 ± 46 |
| 6.0 | MS221 | 151.9 ± 31.7 | 22746 ± 6293 | 73 ± 21 | 0.28 ± 0.08 | 143 ± 32 |
a†Parameter not determined.
For multiple dose determinations, pharmacokinetic measurements were conducted after the first and sixth doses following monthly repeat-infusion IV administration of natalizumab to MS patients. Cmax values were proportional to the administered dose at 3 or 6 mg/kg or as a 300 mg fixed dose. As shown in Table 11, mean CL, Vd and t½ values were relatively consistent and independent of the administered dose.
When administered as a 300 mg fixed dose, the pharmacokinetics of natalizumab were consistent with that observed following weight-based dosing. Mean trough serum concentrations in the phase 3 studies were very consistent between studies and ranged from 15.3 to 25.9 μg/mL. These natalizumab concentrations were associated with mean α4-integrin saturation values in excess of 70% across studies.
Table 11. Summary of Pharmacokinetic Parameters Following 30- to 60-Minute Repeat-Infusion Administrations of Natalizumab in MS Patients (Mean +/- s.d.)
Dose (mg/kg) | Study | Cmax (µg/mL) | AUC(last) (µg×hr/mL) | Vd (mL/kg ) | CL (mL/hr/kg) | t½ (hr) |
| Dose 1 | ||||||
| 3.0 | MS201 | 64.1 ± 18.8 | 6848 ± 2631 | 86 ± 43 | 0.45 ± 0.17 | 143 ± 50 |
| 3.0 | MS231 | 73.7 ± 17.3 | 9870 ± 2503 | n.d.† | n.d. | 230 ± 69 |
| 6.0 | MS231 | 149.9 ± 18.2 | 20452 ± 3834 | n.d. | n.d. | 289 ± 112 |
| 300* | C-1801 | 84.8 ± 22.3 | 17884 ± 9165 | 77 ± 36 | 0.23 ± 0.09 | 249 ± 105 |
| Dose 6 | ||||||
| 3.0 | MS201 | 61.4 ± 15.8 | 12021 ± 4263 | 42 ± 17 | 0.27 ± 0.10 | 152 ± 38 |
| 3.0 | MS201 | 56.9 ± 14.1 | 14268 ± 4286 | 21 ± 5 | 0.22 ± 0.06 | 145 ± 42 |
| 3.0 | MS231 | 64.2 ± 25.4 | 11388 ± 6252 | n.d. | n.d. | 202 ± 57 |
| 6.0 | MS231 | 142.4 ± 54.9 | 31721 ± 13113 | n.d. | n.d. | 262 ± 44 |
| 300* | C-1801 | 94.7 ± 34.2 | 19609 ± 5701 | 81 ± 43 | 0.22 ± 0.06 | 265 ± 98 |
*Fixed dose
† Parameter not determined.
Pharmacodynamic Results
Results from studies where natalizumab was given as a 300 mg fixed dose in MS patients in large-scale clinical trials were considered to be most clinically relevant. The administration of 300 mg natalizumab resulted mean α4-integrin saturation that was in excess of 90% immediately post-infusion and maintained α4-integrin saturation levels of approximately 70% or greater during the entire 28-day dosing interval. Similar α4-integrin binding was observed after the first natalizumab dose and after the sixth dose, as shown in Figure 5. The reported ranges (minimum and maximum values) are represented by dotted lines.
Figure 5. Mean Alpha4-Integrin Percentage Saturation Over Time During Monthly Dose Administration in Antibody-Negative MS Patients (Studies C-1801)
| Dose 1 | Dose 6 |
| Mean +/- SEM Alpha-4 Integrin Saturation, Natalizumab 300 mg: Dose 1 Time, days 0 7 14 21 28 Alpha-4 Integrin, % Saturation 0 20 40 60 80 100 120 Placebo Natalizumab 300 mg | Mean +/- SEM Alpha-4 Integrin Saturation, Natalizumab 300 mg: Dose 6 Time, days 0 7 14 21 28 Alpha-4 Integrin, % Saturation 0 20 40 60 80 100 120 Placebo Natalizumab 300 mg |
Elevations in absolute lymphocyte counts were relatively consistent across studies. Lymphocyte counts in the natalizumab-treated subjects were elevated to approximately 3.0X10⁹ cells/L throughout the treatment periods. Following the cessation of dosing, lymphocyte counts remained elevated through Month 8 in the 3 mg/kg dose group and Month 9 in the 6 mg/kg dose group. Although elevated, the mean lymphocyte counts remained within the normal range throughout the observation period.
14.3 Immunogenicity
In the 2-year studies with monthly administration, continued measurements showed that the incidence of anti-TYSABRI antibodies at a single timepoint was 10%, 6% being persistent anti-natalizumab antibodies (detected on two occasions at least 6 weeks apart) and 4% transient.
Persistent anti-natalizumab antibodies were associated with a decreased efficacy of TYSABRI and an increased incidence of infusion-related reactions. The majority of patients who became persistently antibody-positive had developed antibodies by 12 weeks. Persistent antibody-positive subjects had trough natalizumab concentrations that were consistently below limit of quantitation. This level of natalizumab exposure was correlated with consistent reduction in α-4 integrin saturation on leukocytes in these persistently antibody-positive subjects. Patients who experienced transient anti-TYSABRI antibodies had a temporary reduction in natalizumab concentrations, but did not experience a long-term reduction in drug concentrations or activity.
15 MICROBIOLOGY
No microbiological information is required for this drug product
16 NON-CLINICAL TOXICOLOGY
General Toxicology: Natalizumab is a human IgG4 molecule and is therefore a foreign protein and immunogenic in the various species used in the toxicology program. The rate and incidence of detectable antibody formation varies with species, dose level and dosing regimen. The development of antibodies can affect the detection of natalizumab levels and can also reduce exposure to the drug through accelerated clearance. Therefore toxicokinetic sampling was performed in the majority of the chronic toxicology studies to allow for the monitoring of exposure over time.
Natalizumab treatment has been generally well tolerated in both adult and juvenile animals at cumulative exposures in the high-dose group (60 mg/kg) of up to 94-fold (mean 36, range 0.4-94) and 78-fold (mean 53, range 36-78), respectively, over anticipated human exposures (based on 6 months of dosing and a human dose of 300 mg).
In all species tested, increases in white blood cell count were associated with serum natalizumab levels above approximately 1-5μg/mL and returned to normal when natalizumab levels fell below these values. Increases were primarily the result of increases in lymphocyte counts, though increases in monocytes, eosinophils and basophils were also seen. These increases are the expected pharmacologic effect of the binding of natalizumab to α4-integrins, as α4 integrins are involved in the adhesion of leukocytes to endothelium and the subsequent trafficking of the leukocytes across the endothelium and into tissues.
Findings (some seen inconsistently across the studies) other than increased WBC counts included: increases in reticulocytes and/or nucleated red blood cells, increased spleen weights, mild to moderate follicular hyperplasia in the lymph node and spleen, and minimal to mild focal leukocyte infiltrates in the liver. Hyperplastic lymphoid follicles retained normal anatomic relationships and boundaries and were considered characteristic of follicles exhibiting polyclonal lymphocyte expansion and/or accumulation. Findings have been reversible following the discontinuation of natalizumab treatment.
Overall, natalizumab-related treatment findings seen in the toxicology program were generally related (e.g., hematology changes) or believed to be related (e.g., increased spleen weights) to the pharmacological activity of natalizumab. Treatment-related effects were not associated with overt toxicity in the affected animals, and were reversible following discontinuation of natalizumab treatment and clearance of natalizumab from circulation.
Genotoxicity: Natalizumab was not genotoxic in a human lymphocyte aberration assay, nor did it have any effect on the proliferation of α4-expressing human tumour cells lines in vitro. Growth and metastasis of two α4-expressing tumours (a leukemia and a melanoma) were not increased in the presence of natalizumab in nude and SCID mouse human tumour xenograft models.
Reproductive and Developmental Toxicology: Male fertility in guinea pigs was unaffected by natalizumab treatment at doses resulting in cumulative AUC exposures 38-fold times that in humans. Female fertility in guinea pigs demonstrated treatment-related effects (consisting of reduced fertility and reduced pup survival through post-natal day [PND] 14) at doses resulting in cumulative AUC exposures 40-fold times that in humans – effects were not observed at the next lowest dose level that resulted in cumulative AUC exposures 13-fold times that in humans. No teratogenic effects in guinea pigs or monkeys were seen as a result of natalizumab treatment. There was an apparent increased incidence of abortion in natalizumab-treated primates in only one of four studies that evaluated this effect, in guinea pigs and cynomolgus monkeys. Increases in nucleated red blood cells, changes in RBC parameters indicative of mild anemia, and some alterations in the distribution of immune cell populations in immune system organs were seen in the fetuses of guinea pigs and/or primates at high exposure levels (mean cumulative AUC 65-fold over human). Although no effects were noted at the lowest dose tested, exposure at this dose was only achieved through GD44. In offspring born to mothers treated with natalizumab at 7-fold the clinical dose, reduced platelet counts were observed and were reversed upon clearance of natalizumab. There was no evidence of anemia in these offspring. Offspring exposed in utero and via breast milk had no natalizumab-related changes in the lymphoid organs and had normal immune response to challenge with a T-cell dependent antigen.
Tissue cross-reactivity studies of natalizumab with normal adult human, cynomolgus and rhesus monkey and guinea pig tissues, and with fetal human and monkey tissues were consistent with staining patterns reported in the literature and did not result in the identification of any unexpected target tissues. Findings in the chronic and reproductive toxicology studies involved some of the lymphoid organs seen to stain in these studies, but did not reveal any findings associated with the less common, nonlymphoid staining patterns.