


Product Monograph - Tecvayli
Recent Major Label Changes
| 1 Indications | 2026-MM |
|---|---|
| 4 Dosage and Administration /4.2 Recommended Dose and Dosage Adjustment / 4.3 Administration / 4.4 Missed Dose | 2026-MM |
| 7 Warnings and Precautions, Hematologic / Immune / Hepatic / Neurologic | 2026-MM |
Table of Contents
Certain sections or subsections that are not applicable at the time of the preparation of the most recent authorized product monograph are not listed.
Recent Major Label Changes ................................................................................................... 2
Table of Contents ................................................................................................................... 2
Part 1: Healthcare Professional Information ........................................................................... 5
- 1.
Indications .................................................................................................................. 5
1.1. Pediatrics .............................................................................................................. 5
1.2. Geriatrics .............................................................................................................. 5
- 2. Contraindications ........................................................................................................ 5
- 3. Serious Warnings and Precautions Box ....................................................................... 5
- 4.
Dosage and Administration ......................................................................................... 6
4.1. Dosing Considerations .......................................................................................... 6
4.2. Recommended Dose and Dosage Adjustment ..................................................... 6
4.4. Administration .................................................................................................... 11
4.5. Missed Dose ....................................................................................................... 15
- 5. Overdosage ............................................................................................................... 16
- 6. Dosage Forms, Strengths, Composition and Packaging .............................................. 17
- 7.
Warnings and Precautions ......................................................................................... 17
Driving and Operating Machinery .................................................................................. 17
Hematologic ................................................................................................................... 17
Hepatic/Biliary/Pancreatic ............................................................................................. 18
Immune .......................................................................................................................... 18
Neurologic ...................................................................................................................... 21
Reproductive Health ...................................................................................................... 25
7.1. Special Populations ............................................................................................. 25
7.1.1. Pregnancy ....................................................................................................... 25
7.1.2. Breastfeeding ................................................................................................. 25
7.1.3. Pediatrics ........................................................................................................ 25
7.1.4. Geriatrics ........................................................................................................ 25
- 8.
Adverse Reactions ..................................................................................................... 26
8.1. Adverse Reaction Overview ................................................................................ 26
8.2. Clinical Trial Adverse Reactions .......................................................................... 27
8.3. Less Common Clinical Trial Adverse Reactions ................................................... 33
8.4. Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data ........................................................................................................... 33
8.5. Post-Market Adverse Reactions ......................................................................... 35
- 9.
Drug Interactions ...................................................................................................... 35
9.2. Drug Interactions Overview ................................................................................ 35
9.4. Drug-Drug Interactions ....................................................................................... 35
9.5. Drug-Food Interactions ....................................................................................... 35
9.6. Drug-Herb Interactions ....................................................................................... 35
9.7. Drug-Laboratory Test Interactions ...................................................................... 35
- 10.
Clinical Pharmacology ............................................................................................... 35
10.1. Mechanism of Action ...................................................................................... 35
10.2. Pharmacodynamics ........................................................................................ 36
10.3. Pharmacokinetics ........................................................................................... 36
10.4. Immunogenicity .............................................................................................. 38
- 11. Storage, Stability and Disposal .................................................................................. 38
- 12. Special Handling Instructions .................................................................................... 38
Part 2: Scientific Information ................................................................................................ 39
- 13. Pharmaceutical Information ...................................................................................... 39
- 14.
Clinical Trials ............................................................................................................. 40
14.1. Clinical Trials by Indication ............................................................................. 40
Multiple Myeloma After One to Three Prior Lines of Therapy ....................................... 40
Multiple Myeloma after Three or More Prior Lines of Therapy ...................................... 45
- 15. Microbiology ............................................................................................................. 47
- 16. Non-Clinical Toxicology ............................................................................................. 47
Patient Medication Information ........................................................................................... 48
Part 1: Healthcare Professional Information
1. Indications
TECVAYLI® (teclistamab injection) is indicated:
- in combination with daratumumab for the treatment of adults with relapsed or refractory multiple myeloma who have received one to three prior lines of therapy, including a proteasome inhibitor and an immunomodulatory agent.
- as a monotherapy for the treatment of adults with relapsed or refractory multiple myeloma who have received at least three prior lines of therapy, including a proteasome inhibitor, an immunomodulatory agent and an anti-CD38 monoclonal antibody, and who have demonstrated disease progression on the last therapy.
1.1. Pediatrics
Pediatrics (<18 years of age): No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use.
1.2. Geriatrics
Geriatrics (≥ 65 years of age): No overall differences in safety or effectiveness were observed between geriatric and younger patients, see 7.1.4 Geriatrics.
2. Contraindications
TECVAYLI is contraindicated in patients who are hypersensitive to this drug or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see 6. Dosage Forms, Strengths, Composition and Packaging.
- 3. Serious Warnings and Precautions Box
Serious Warnings and Precautions
|
|---|
4. Dosage and Administration
4.1. Dosing Considerations
- TECVAYLI should be administered by subcutaneous injection only.
- Pregnancy status for females of child-bearing potential should be verified prior to starting treatment with TECVAYLI.
- Monitor individuals for signs and symptoms of infections prior to and during treatment with TECVAYLI and treat appropriately. Administer prophylactic antimicrobials as per local institutional guidelines.
- For individuals receiving TECVAYLI in combination with daratumumab, consider initiating immunoglobulin replacement (IVIg or SCIg) as clinically appropriate and as per local institutional guidelines, including prophylactically. In the Phase 3 MajesTEC-3 Study, over 85% of participants treated with the combination therapy were administered at least one dose of intravenous or subcutaneous immunoglobulin replacement therapy.
- Do not administer TECVAYLI step-up dosing schedule in patients with active infection.
- Administer pre-treatment medications prior to each dose of the TECVAYLI step-up dosing schedule (see 4.4. Administration).
4.2. Recommended Dose and Dosage Adjustment
Administer TECVAYLI subcutaneously according to the step-up dosing schedule in Table 1 and Table 2 to reduce the incidence and severity of cytokine release syndrome (CRS).
Failure to follow the recommended doses or dosing schedule for initiation of therapy or re-initiation of therapy after dose delays may result in increased frequency and severity of adverse events related to mechanism of action, particularly CRS (see 7. Warnings and Precautions).
Recommended Dose
Combination with Daratumumab
The dosing schedule for TECVAYLI in combination therapy with daratumumab is in Table 1. TECVAYLI and daratumumab should be administered until disease progression or unacceptable toxicity.
Table 1: TECVAYLI Dosing Schedule for Combination Therapy with Daratumumab
| Dosing schedulea | Week/Day | TECVAYLI Dosage | Daratumumabi |
| Day 1 | N/A | Daratumumab 1800 mg | |
| Step-up dosing schedulec | Day 2d | Step-up dose 1 0.06 mg/kg | N/A |
| Day 4e | Step-up dose 2 0.3 mg/kg single dose | N/A | |
| Day 8f | First Treatment dose 1.5 mg/kg single dose | Daratumumab 1800 mg | |
| Weekly dosing schedulec | Weeks 3-8g | Subsequent treatment doses 1.5 mg/kg once weekly | Daratumumab 1800 mg once weekly |
| Biweekly (every two weeks) dosing schedulec | Weeks 9 to 24h | Subsequent treatment doses 3 mg/kg every two weeks | Daratumumab 1800 mg every two weeks |
| Q4W (every four weeks) dosing schedulec | Week 25 onwardsh | Subsequent treatment doses 3 mg/kg every four weeks | Daratumumab 1800 mg every four weeks |
a TECVAYLI must be administered at least 3 hours after daratumumab for the first treatment dose and thereafter, TECVAYLI must be administered at least 15 minutes after daratumumab. b Dose is based on actual body weight and must be administered subcutaneously. c See Table 8 for recommendations on restarting TECVAYLI after dose delays. d Step-up dose 1 must be administered 20 hours or more after daratumumab. e Step-up dose 2 may be given between 2 to 7 days after Step-up dose 1, f First treatment dose may be given between 2 to 7 days after Step-up dose 2. This is the first full treatment dose (1.5 mg/kg). g Maintain a minimum of 5 days between 1.5 mg/kg treatment doses. h Maintain a minimum of 12 days between 3 mg/kg treatment doses. i Daratumumab is to be administered subcutaneously and there must be ≥5 days between doses of daratumumab. | |||
For dosing and administration instructions of daratumumab subcutaneous, consult the DARZALEX SC Product Monograph.
Monotherapy
The recommended dose for TECVAYLI is 1.5 mg/kg actual body weight administered subcutaneously once weekly, preceded by step-up doses of 0.06 mg/kg and 0.3 mg/kg. TECVAYLI dosing schedule is provided in Table 2 for monotherapy.
In patients who have a complete response (CR) or better for a minimum of 6 months, a reduced dosing frequency of 1.5 mg/kg actual body weight administered every two weeks may be considered (see 14. Clinical Trials).
Table 2: TECVAYLI Dosing Schedule for Monotherapy
| Dosing schedule | Day | Dosea |
| Dosing schedule | Day | Dosea |
| All patients | ||
| Step-up dosing scheduleb | ||
| Day 1 | Step-up dose 1 | 0.06 mg/kg single dose |
| Day 3c | Step-up dose 2 | 0.3 mg/kg single dose |
| Day 5d | First treatment dose | 1.5 mg/kg single dose |
| Weekly dosing scheduleb | ||
| One week after first treatment dose and weekly thereaftere | Subsequent treatment doses | 1.5 mg/kg once weekly |
| Patients who have a complete response or better for a minimum of 6 months | ||
| Biweekly (every two weeks) dosing scheduleb | Consider reducing the dosing frequency to 1.5 mg/kg every two weeks | |
a Dose is based on actual body weight and should be administered subcutaneously. b See Table 8 for recommendations on restarting TECVAYLI after dose delays. c Step-up dose 2 may be given between 2 to 7 days after Step-up dose 1. d First treatment dose may be given between 2 to 7 days after Step-up dose 2. This is the first full treatment dose (1.5 mg/kg). e Maintain a minimum of five days between weekly treatment doses. | ||
Refer to Table 4, Table 5 and Table 6 to determine the dosage based on predetermined weight ranges.
Patients should be treated with TECVAYLI until disease progression or unacceptable toxicity.
For guidance regarding restarting therapy with TECVAYLI after dose delays, see 4.5. Missed Dose.
Dosage Adjustment
Do not skip step-up doses of TECVAYLI.
Combination therapy: Dose modifications of TECVAYLI during the step-up dosing and the first 1.5 mg/kg treatment dose are not recommended. Dose modifications from subsequent treatment dosing may be required to manage toxicities.
Refer to DARZALEX SC Product Monograph for information about dosage modifications for daratumumab.
Monotherapy: Dose reductions of TECVAYLI are not recommended.
Dose delays may be required to manage toxicities related to TECVAYLI (see 7. Warnings and Precautions and 4. Dosage and Administration).
See Table 3 for recommended actions for adverse reactions following administration of TECVAYLI.
Table 3: Recommended Actions for Adverse Reactions Following Administration of TECVAYLI
| Adverse Reactions | Grade | Actions | ||
| Adverse Reactions | Grade | Actions | ||
| Adverse Reactions | Grade | Actions | ||
Cytokine Release Syndrome (CRS)a (see 7. Warnings and Precautions) The presenting symptoms of CRS per grade are included in Table 10. | Grade 1 |
| ||
| ||||
Grade 2 Grade 3 (Duration: less than 48 hours) |
| |||
Grade 3 (Recurrent or duration: more than 48 hours) Grade 4 |
| |||
Immune Effector Cell-Associated Neurotoxicity Syndrome (ICANS)b (see 7. Warnings and Precautions) The presenting symptoms of ICANS outlined per grade are included in Table 11. | Grade 1 |
| ||
Grade 2 Grade 3 (First occurrence) |
| |||
Grade 3 (Recurrent) Grade 4 |
| |||
| Infections (see 7. Warnings and Precautions) | All Grades |
| ||
Grade 3 Grade 4 |
| |||
| Hematologic Toxicities (see 7. Warnings and Precautions and 8. Adverse Reactions) | Absolute neutrophil count less than 0.5 × 10⁹/L |
| ||
| Febrile neutropenia |
| |||
| Hemoglobin less than 8 g/dL |
| |||
Combination therapy: Platelet count less than 50000/µL Monotherapy: Platelet count less than 25000/µL Platelet count between 25000/µL and 50000/µL with bleeding | Combination therapy:
Monotherapy:
| |||
| Other Adverse Reactions (see 8. Adverse Reactions) | Grade 3 Grade 4 |
| ||
| a Based on American Society for Transplantation and Cellular Therapy (ASTCT) grading. | ||||
b Based on American Society for Transplantation and Cellular Therapy (ASTCT) 2019 grading for ICANS.
Renal impairment
No formal studies of TECVAYLI in patients with renal impairment have been conducted. Based on population pharmacokinetic analyses, no dose adjustment is required for patients with mild or moderate renal impairment (see 10.3. Pharmacokinetics). Limited data are available for patients with severe renal impairment.
Hepatic impairment
No formal studies of TECVAYLI in patients with hepatic impairment have been conducted. Based on population pharmacokinetic analyses, no dose adjustment is required for patients with mild hepatic impairment (see 10.3. Pharmacokinetics). Limited data are available in patients with moderate hepatic impairment and no data are available in patients with severe hepatic impairment.
Pediatric (<18 years)
Health Canada has not authorized an indication for pediatric use.
Geriatrics (≥65 years of age)
No dose adjustment is required in patients over 65 years of age (see 10. Clinical Pharmacology).
4.4. Administration
TECVAYLI should be administered by healthcare professionals at treatment centres with adequate medical equipment and personnel to manage severe reactions, including CRS and ICANS. Educational materials related to the risks of CRS and ICANS, are available for healthcare professionals through the manufacturer.
It is very important that the instructions for preparation and administration provided in this section are strictly followed to minimize potential dosing errors with TECVAYLI 30 mg/3 mL (10 mg/mL) vial and TECVAYLI 153 mg/1.7 mL (90 mg/mL) vial.
TECVAYLI should be administered via subcutaneous injection only. Do not administer TECVAYLI intravenously.
Pre-treatment Medications
Administer the following pre-treatment medications 1 to 3 hours before each dose of the TECVAYLI step-up dosing schedule, which includes step-up dose 1, step-up dose 2, and the first treatment dose (Error! Reference source not found. and Table 2) to reduce the risk of cytokine release syndrome (see 7. Warnings and Precautions).
- Corticosteroid (oral or intravenous dexamethasone, 16 mg)
- Antihistamine (oral or intravenous diphenhydramine, 50 mg or equivalent)
- Antipyretics (oral or intravenous acetaminophen, 650 mg to 1000 mg or equivalent)
Administration of pre-treatment medications may be required prior to the administration of subsequent doses of TECVAYLI in the following patients:
- Patients who repeat doses within the TECVAYLI step-up dosing schedule following a dose delay (see Table 8).
- Patients who experienced CRS following the prior dose of TECVAYLI (see Table 3).
For instructions on daratumumab subcutaneous, see 4.2 Recommended Dose and Dosage Adjustment, and consult the DARZALEX SC Product Monograph, except that dexamethasone (or equivalent) premedication should not be administered after the TECVAYLI step-up dosing schedule.
Preparation of TECVAYLI
- TECVAYLI is available in two strengths, 30 mg/3 mL (10 mg/mL) in a 3 mL glass vial with a blue colour cap, and 153 mg/1.7 mL (90 mg/mL) in a 1.7 mL glass vial with an orange colour cap (see 6. Dosage Forms, Strengths, Composition and Packaging). Use TECVAYLI 30 mg/3 mL (10 mg/mL) vial for Step-up dose 1 and Step-up dose 2, and TECVAYLI 153 mg/1.7 mL (90 mg/mL) vial for treatment dose.
- TECVAYLI 10 mg/mL and TECVAYLI 90 mg/mL are supplied as ready-to-use solutions for injection that do not need dilution prior to administration.
- TECVAYLI vials of different concentrations should not be combined to achieve treatment dose.
- Use aseptic technique to prepare and administer TECVAYLI.
- TECVAYLI solution for injection is clear to slightly opalescent, colourless to light yellow. Visually inspect TECVAYLI for particulate matter and discolouration prior to administration. Do not use if the solution is discoloured, or cloudy, or if foreign particles are present. Verify the prescribed dose for each TECVAYLI injection. To minimize errors, use the following tables to prepare TECVAYLI injection.
- Use Table 4 to determine total dose, injection volume, and number of vials required based on patient’s actual body weight for Step-up Dose 1 using TECVAYLI 30 mg/3 mL (10 mg/mL) vial.
Table 4: Step-up Dose 1 Injection Volumes Using TECVAYLI 30 mg/3 mL (10 mg/mL) Vial
| Step-Up Dose 1 (0.06 mg/kg) | Body Weight (kg) | Total Dose (mg) | Volume of Injection (mL) | Number of Vials (1 vial=3 mL) | |||||
| 35-39.9 | 2.2 | 0.22 | 1 | ||||||
| 40-44.9 | 2.5 | 0.25 | 1 | ||||||
| 45-49.9 | 2.8 | 0.28 | 1 | ||||||
| 50-59.9 | 3.3 | 0.33 | 1 | ||||||
| 60-69.9 | 3.9 | 0.39 | 1 | ||||||
| 70-79.9 | 4.5 | 0.45 | 1 | ||||||
| 80-89.9 | 5.1 | 0.51 | 1 | ||||||
| 90-99.9 | 5.7 | 0.57 | 1 | ||||||
| 100-109.9 | 6.3 | 0.63 | 1 | ||||||
| 110-119.9 | 6.9 | 0.69 | 1 | ||||||
| 120-129.9 | 7.5 | 0.75 | 1 | ||||||
| 130-139.9 | 8.1 | 0.81 | 1 | ||||||
| 140-149.9 | 8.7 | 0.87 | 1 | ||||||
| 150-160 | 9.3 | 0.93 | 1 | ||||||
- Use Table 5 to determine total dose, injection volume and number of vials required based on patient’s actual body weight for Step-up Dose 2 using TECVAYLI 30 mg/3 mL (10 mg/mL) vial.
Table 5: Step-up Dose 2 Injection Volumes Using TECVAYLI 30mg/3 mL (10 mg/mL) Vial
| Step-up Dose 2 (0.3 mg/kg) | Body Weight (kg) | Total Dose (mg) | Volume of Injection (mL) | Number of Vials (1 vial=3 mL) | ||||||
| 35-39.9 | 11 | 1.1 | 1 | |||||||
| 40-44.9 | 13 | 1.3 | 1 | |||||||
| 45-49.9 | 14 | 1.4 | 1 | |||||||
| 50-59.9 | 16 | 1.6 | 1 | |||||||
| 60-69.9 | 19 | 1.9 | 1 | |||||||
| 70-79.9 | 22 | 2.2 | 1 | |||||||
| 80-89.9 | 25 | 2.5 | 1 | |||||||
| 90-99.9 | 28 | 2.8 | 1 | |||||||
| 100-109.9 | 31 | 3.1 | 2 | |||||||
| 110-119.9 | 34 | 3.4 | 2 | |||||||
| 120-129.9 | 37 | 3.7 | 2 | |||||||
| 130-139.9 | 40 | 4 | 2 | |||||||
| 140-149.9 | 43 | 4.3 | 2 | |||||||
| 150-160 | 47 | 4.7 | 2 | |||||||
Use Table 6 to determine total dose, injection volume and number of vials required based on patient’s actual body weight for the 1.5 mg/kg Treatment Dose using TECVAYLI 153 mg/1.7 mL (90 mg/mL) vial.
Table 6: Treatment Dose (1.5 mg/kg) Injection Volumes Using TECVAYLI 153 mg/1.7 mL (90 mg/mL) Vial
| Treatment Dose (1.5 mg/kg) | Body Weight (kg) | Total Dose (mg) | Volume of Injection (mL) | Number of Vials (1 vial=1.7 mL) | |||||
| 35-39.9 | 56 | 0.62 | 1 | ||||||
| 40-44.9 | 64 | 0.71 | 1 | ||||||
| 45-49.9 | 71 | 0.79 | 1 | ||||||
| 50-59.9 | 83 | 0.92 | 1 | ||||||
| 60-69.9 | 99 | 1.1 | 1 | ||||||
| 70-79.9 | 108 | 1.2 | 1 | ||||||
| 80-89.9 | 126 | 1.4 | 1 | ||||||
| 90-99.9 | 144 | 1.6 | 1 | ||||||
| 100-109.9 | 153 | 1.7 | 1 | ||||||
| 110-119.9 | 171 | 1.9 | 2 | ||||||
| 120-129.9 | 189 | 2.1 | 2 | ||||||
| 130-139.9 | 198 | 2.2 | 2 | ||||||
| 140-149.9 | 216 | 2.4 | 2 | ||||||
| 150-160 | 234 | 2.6 | 2 | ||||||
Use Table 7 to determine total dose, injection volume and number of vials required based on patient’s actual body weight for the 3 mg/kg Treatment Dose using TECVAYLI 153 mg/1.7 mL (90 mg/mL) vial.
Table 7: Treatment Dose (3 mg/kg) Injection Volumes Using TECVAYLI 153 mg/1.7 mL (90 mg/mL) Vial
| Treatment Dose (3 mg/kg) | Body Weight (kg) | Total Dose (mg) | Volume of Injection (mL) | Number of Vials (1 vial=1.7 mL) | |||||
| 35-39.9 | 108 | 1.2 | 1 | ||||||
| 40-44.9 | 126 | 1.4 | 1 | ||||||
| 45-49.9 | 144 | 1.6 | 1 | ||||||
| 50-59.9 | 162 | 1.8 | 2 | ||||||
| 60-69.9 | 198 | 2.2 | 2 | ||||||
| 70-79.9 | 225 | 2.5 | 2 | ||||||
| 80-89.9 | 252 | 2.8 | 2 | ||||||
| 90-99.9 | 288 | 3.2 | 2 | ||||||
| 100-109.9 | 315 | 3.5 | 3 | ||||||
| 110-119.9 | 342 | 3.8 | 3 | ||||||
| 120-129.9 | 378 | 4.2 | 3 | ||||||
| 130-139.9 | 405 | 4.5 | 3 | ||||||
| 140-149.9 | 432 | 4.8 | 3 | ||||||
| 150-160 | 468 | 5.2 | 4 | ||||||
- Remove the appropriate strength TECVAYLI vial from refrigerated storage (2°C to 8°C) and equilibrate to ambient temperature (15°C to 30°C), as needed, for at least 15 minutes. Do not warm TECVAYLI in any other way.
- Once equilibrated, gently swirl the vial for approximately 10 seconds to mix. Do not shake.
Withdraw the required injection volume of TECVAYLI from the vial(s) into an appropriately sized syringe using a transfer needle.
- Each injection volume should not exceed 2.0 mL. Divide doses requiring greater than 2.0 mL equally into multiple syringes.
- TECVAYLI is compatible with stainless steel injection needles and polypropylene or polycarbonate syringe material.
- Replace the transfer needle with an appropriately sized needle for injection.
Administration of TECVAYLI
Inject the required volume of TECVAYLI into the subcutaneous tissue of the abdomen (preferred injection site). Alternatively, TECVAYLI may be injected into the subcutaneous tissue at other sites (e.g., thigh). If multiple injections are required
- (either as combination therapy or as monotherapy), TECVAYLI injections should be at least 2 cm apart.
- Do not inject into tattoos or scars or areas where the skin is red, bruised, tender, hard or not intact.
- If TECVAYLI is not used immediately, store at 2 to 8°C or at ambient temperature for a maximum of 20 hours. Discard after 20 hours, if not used.
- Any unused medicinal product or waste material should be disposed in accordance with local requirements.
Monitoring
Instruct the patients to remain within proximity of a healthcare facility and monitor daily for 48 hours for signs and symptoms of CRS after administration of all doses within the TECVAYLI initial step-up dosing schedule, or alternatively consider hospitalization for patients (see 4. Dosage and Administration and 7. Warnings and Precautions).
4.5. Missed Dose
Restarting TECVAYLI after dose delays
If a dose of TECVAYLI is delayed, restart therapy based on the recommendations listed in Table 8 and resume the treatment schedule accordingly (see 4.2. Recommended Dose and Dosage Adjustment). Administer pre-treatment medications as indicated (see 4.4. Administration).
Table 8: Recommendations for Restarting TECVAYLI after Dose Delay
| Last Dose Administered | Duration of Delay from the Last Dose Administered | Action | |
| Last Dose Administered | Duration of Delay from the Last Dose Administered | Action | |
| Step-up Dose 1 | 7 days or less | Resume TECVAYLI step-up dosing schedule at Step-up Dose 2 (0.3 mg/kg).a | |
| More than 7 days | Restart TECVAYLI step-up dosing schedule at Step-up Dose 1 (0.06 mg/kg).a | ||
| Step-up Dose 2 | 7 days or less | Resume TECVAYLI step-up dosing schedule at Treatment Dose (1.5 mg/kg).a | |
| 8 days to 28 days | Resume TECVAYLI step-up dosing schedule at Step-up Dose 2 (0.3 mg/kg).a | ||
| More than 28 days | Restart TECVAYLI step-up dosing schedule at Step-up Dose 1 (0.06 mg/kg).a | ||
| Any Treatment Dose | 63 days or less | Resume TECVAYLI at last Treatment Dose and schedule. | |
| 64 days to 112 days | Restart TECVAYLI step-up dosing schedule at Step-up Dose 2 (0.3 mg/kg) a | ||
| More than 112 days | Restart TECVAYLI step-up dosing schedule at Step-up Dose 1 (0.06 mg/kg).a | ||
| a Administer pre-treatment medications prior to TECVAYLI dose and monitor accordingly (see 4.4 Administration). | |||
5. Overdosage
The maximum tolerated dose of teclistamab has not been determined. In clinical trials, doses of up to 6 mg/kg have been administered.
In the event of an overdose, the patient should be monitored for any signs or symptoms of adverse effects and appropriate symptomatic treatment should be instituted immediately.
| For management of a suspected drug overdose, contact your regional poison control centre. |
|---|
6. Dosage Forms, Strengths, Composition and Packaging
Table 9: Dosage Forms, Strengths, Composition and Packaging
TECVAYLI is a clear to slightly opalescent, colourless to light yellow preservative-free solution for injection.
TECVAYLI is available in a 3 mL glass vial (10 mg teclistamab per mL) with a blue-coloured cap and a 1.7 mL glass vial (90 mg of teclistamab per mL) with an orange-coloured cap.
7. Warnings and Precautions
Please see 3. Serious Warnings and Precautions Box.
Driving and Operating Machinery
Due to the potential for ICANS, patients receiving TECVAYLI are at risk of a depressed level of consciousness. Patients should avoid driving or operating heavy or potentially dangerous machinery during and for 48 hours after completion of TECVAYLI step-up dosing schedule (Table 2) and in the event of new onset of any neurological symptoms (see 4. Dosage and Administration).
Hematologic
Hypogammaglobulinemia
Hypogammaglobulinemia is common in patients receiving TECVAYLI and higher incidences have been reported when TECVAYLI is used in combination with daratumumab (see 8. Adverse Reactions).
Monitor immunoglobulin levels during treatment with TECVAYLI and treat with subcutaneous or intravenous immunoglobin (IVIG) therapy to maintain the serum levels above 4g/L.
| Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
| Subcutaneous injection | Solution for injection 10 mg/mL strength: each 3 mL solution for injection contains 30 mg of teclistamab (10 mg teclistamab per mL) 90 mg/mL strength: each 1.7 mL solution for injection contains 153 mg of teclistamab (90 mg of teclistamab per mL) | EDTA disodium salt dihydrate Glacial acetic acid Polysorbate 20 Sodium acetate trihydrate Sucrose Water for injection |
Infection precautions, and antimicrobials, including antibiotic or antiviral prophylaxis, should be used according to local institutional guidelines.
Neutropenia
Neutropenia and febrile neutropenia have been reported in patients who received TECVAYLI (see 8. Adverse Reactions).
Monitor complete blood cell counts at baseline and periodically during treatment and provide supportive care per local institutional guidelines.
Patients with neutropenia should be monitored for signs of infection.
Withhold treatment with TECVAYLI based on severity as indicated in Table 3 (see 4. Dosage and Administration – Dosage Adjustment).
Hepatic/Biliary/Pancreatic
Hepatotoxicity
Higher incidences of hepatotoxicity have been observed when TECVAYLI is administered in combination with daratumumab compared to TECVAYLI monotherapy (see 8. Adverse Reactions). Grade 3 and 4 elevations in liver enzymes and/or bilirubin can occur with or without concurrent CRS.
Monitor liver enzymes and bilirubin at baseline and during TECVAYLI treatment as clinically indicated. Withhold TECVAYLI or consider permanent discontinuation of TECVAYLI based on severity (see Table 3 in 4. Dosage and Administration – Recommended Dose and Dosage Adjustment).
Immune
Cytokine release syndrome
Cytokine release syndrome (CRS), including life-threatening or fatal reactions, can occur in patients receiving TECVAYLI. The majority of CRS events observed following TECVAYLI administration were Grade 1 and Grade 2 (see 8. Adverse Reactions).
Clinical signs and symptoms of CRS may include, but are not limited to, fever, chills, hypotension, tachycardia, hypoxia, headache, and elevated liver enzymes. Potentially life-threatening complications of CRS may include cardiac dysfunction, adult respiratory distress syndrome, neurologic toxicity, renal and/or hepatic failure, and disseminated intravascular coagulation (DIC).
Initiate therapy according to TECVAYLI step-up dosing schedule to reduce risk of CRS (see and Table 2). Failure to follow the recommended doses or dosing schedule for initiation of therapy or re-initiation of therapy after dose delays may result in increased frequency and severity of adverse events related to mechanism of action. Administer pre-treatment medications (corticosteroids, antihistamine, and antipyretics) prior to each dose of the TECVAYLI step-up dosing schedule to reduce the risk of CRS and monitor patients following administration accordingly (see 4. Dosage and Administration). In patients who experienced CRS following their previous dose, administer pre-treatment medications prior to the next dose of TECVAYLI.
The use of myeloid growth factors, particularly granulocyte macrophage-colony stimulating factor (GM-CSF), should be avoided during CRS.
Identify CRS based on clinical presentation. Evaluate and treat other causes of fever, hypoxia, and hypotension. Counsel patients to seek medical attention should signs and symptoms of CRS occur. If CRS is suspected, immediately evaluate patients for hospitalization, administer supportive care (including but not limited to anti-pyretic agents, intravenous fluid support, vasopressors, supplemental oxygen, etc.) as appropriate, and treat CRS per institutional guidelines. Table 10 describes the CRS management in Study MajesTEC-1. Withhold TECVAYLI until CRS resolves (see Table 3). Consider laboratory testing to monitor for disseminated intravascular coagulation (DIC), hematology parameters, as well as pulmonary, cardiac, renal, and hepatic function.
Table 10: Recommendations for Management of Cytokine Release Syndrome
| Gradee | Presenting Symptoms | Tocilizumaba | Corticosteroidsb | |||
| Gradee | Presenting Symptoms | Tocilizumaba | Corticosteroidsb | |||
| Grade 1 | Temperature ≥ 38°C (100.4°F)c | May be considered. | May be considered. | |||
| Grade 2 | Temperature ≥ 38°C (100.4°F)c with either: Hypotension responsive to fluids and not requiring vasopressors. Or, oxygen requirement of low-flow nasal cannulad or blow-by. | Administer tocilizumabb 8 mg/kg intravenously over 1 hour (not to exceed 800 mg). Repeat tocilizumab every 8 hours as needed, if not responsive to intravenous fluids or increasing supplemental oxygen. Limit to a maximum of 3 doses in a 24-hour period; maximum total of 4 doses. | Manage per guidance below, if no improvement within 24 hours of starting tocilizumab. | |||
| Grade 3 | Temperature ≥ 38°C (100.4°F)c with either: Hypotension requiring one vasopressor, with or without vasopressin. Or, oxygen requirement of high-flow nasal cannulad, facemask, non-rebreather mask, or Venturi mask | Administer tocilizumab 8 mg/kg intravenously over 1 hour (not to exceed 800 mg). Repeat tocilizumab every 8 hours as needed if not responsive to intravenous fluids or increasing supplemental oxygen. Limit to a maximum of 3 doses in a 24-hour period; maximum total of 4 doses. | If no improvement, administer methylprednisolone 1 mg/kg intravenously twice daily or equivalent dexamethasone (e.g., 10 mg intravenously every 6 hours). Continue corticosteroids use until the event is Grade 1 or less, then taper over 3 days. | |||
| Grade 4 | Temperature ≥ 38°C (100.4°F)c with either: Hypotension requiring multiple vasopressors (excluding vasopressin). Or, oxygen requirement of positive pressure (e.g., continuous positive airway pressure (CPAP), bilevel positive airway pressure (BiPAP), intubation, and mechanical ventilation) | Administer tocilizumab 8 mg/kg intravenously over 1 hour (not to exceed 800 mg). Repeat tocilizumab every 8 hours as needed if not responsive to intravenous fluids or increasing supplemental oxygen. Limit to a maximum of 3 doses in a 24-hour period; maximum total of 4 doses. | As above or administer methylprednisolone 1000 mg intravenously per day for 3 days, per physician discretion. If no improvement or if condition worsens, consider alternate immunosuppressants.b | |||
a The recommendations describe the CRS management in Study MajesTEC-1. Treat CRS per institutional guidelines. b Treat unresponsive CRS per institutional guidelines. c Attributed to CRS. Fever may not always be present concurrently with hypotension or hypoxia as it may be masked by interventions such as antipyretics or anticytokine therapy (e.g., tocilizumab or steroids). d Low-flow nasal cannula is ≤6 L/min, and high-flow nasal cannula is >6 L/min. e Based on American Society for Transplantation and Cellular Therapy (ASTCT) grading (Lee et al 2019). | ||||||
Infections
Severe, life-threatening or fatal infections have occurred in patients receiving TECVAYLI (see 8. Adverse Reactions). New or reactivated viral infections and opportunistic infections occurred during therapy with TECVAYLI. Higher incidences have been reported when TECVAYLI is used in combination with daratumumab.
Monitor patients for signs and symptoms of infection prior to and during treatment with TECVAYLI and treat appropriately. Infection precautions, and antimicrobials, including antibiotic or antiviral prophylaxis, should be administered according to local institutional guidelines. For individuals receiving TECVAYLI in combination with daratumumab, consider initiating immunoglobulin replacement (IVIg or SCIg) as clinically appropriate and as per local institutional guidelines, including prophylactically. In the Phase 3 MajesTEC-3 Study, over 85% of participants treated with the combination therapy were administered at least one dose of intravenous or subcutaneous immunoglobulin replacement therapy.
Withhold treatment with TECVAYLI as indicated in Table 3 (see 4. Dosage and Administration).
Progressive Multifocal Leukoencephalopathy (PML), which can be fatal, has also been reported in patients receiving TECVAYLI (see 8. Adverse Reactions). Monitor any new onset of or changes in pre-existing neurological signs or symptoms. If PML is suspected, withhold treatment with TECVAYLI and initiate appropriate diagnostic testing. Discontinue TECVAYLI if PML is confirmed.
Hepatitis B Virus reactivation
Hepatitis B virus reactivation has been reported in patients treated with drugs directed against B-cells, and in some cases, may result in fulminant hepatitis, hepatic failure, and death.
Patients with evidence of positive HBV serology should be monitored for clinical and laboratory signs of HBV reactivation while receiving TECVAYLI, and for at least six months following the end of treatment.
In patients who develop reactivation of HBV while on TECVAYLI, withhold treatment with TECVAYLI as indicated in Table 3 and manage per local institutional guidelines (see 4. Dosage and Administration).
Vaccines
Immune response to vaccines may be reduced when taking TECVAYLI.
The safety of immunization with live viral vaccines during or following TECVAYLI treatment has not been studied. Vaccination with live virus vaccines is not recommended for at least 4 weeks prior to the start of treatment, during treatment, and at least 4 weeks after treatment.
Neurologic
Immune Effector Cell-Associated Neurotoxicity Syndrome (ICANS) Serious, life-threatening or fatal Immune Effector Cell-Associated Neurotoxicity Syndrome (ICANS) has occurred following treatment with TECVAYLI (see 8. Adverse Reactions). The onset of ICANS can be concurrent with CRS, following resolution of CRS, or in the absence of CRS.
Monitor patients for signs or symptoms of ICANS during treatment and treat promptly. Counsel patients to seek medical attention should signs or symptoms of ICANS occur.
At the first sign of ICANS, immediately evaluate patient (e.g., consider neurology evaluation, and rule out other causes of neurologic symptoms) and institute treatment based on severity per institutional guidelines. Table 11 describes the ICANS management in Studies MajesTEC-1 and MajesTEC-3. Provide intensive care and supportive therapy for severe or life-threatening ICANS. Withhold treatment with TECVAYLI as indicated in Table 3 (see 4. Dosage and
Administration).
Table 11: Recommendations for Management of Immune Effector Cell-Associated Neurotoxicity Syndrome
| Grade | Presenting Symptomsa | Concurrent CRSb | No Concurrent CRS | |||
| Grade | Presenting Symptomsa | Concurrent CRSb | No Concurrent CRS | |||
| Grade | Presenting Symptomsa | Concurrent CRSb | No Concurrent CRS | |||
| Grade 1 | ICE score 7-9c or depressed level of consciousnessd: awakens spontaneously. | Management of CRS (see Table 10). Monitor neurologic symptoms and consider neurology consultation and evaluation, per physician discretion. | Monitor neurologic symptoms and consider neurology consultation and evaluation, per physician discretion. | |||
| Consider non-sedating, anti-seizure medicines (e.g., levetiracetam) for seizure prophylaxis. | ||||||
| Grade 2 | ICE score 3-6c or depressed level of consciousnessd: awakens to voice. | Management of CRS (see Table 10). If no improvement after starting tocilizumab, administer dexamethasonee 10 mg intravenously every 6 hours if not already taking other corticosteroids. Continue dexamethasone use until resolution to Grade 1 or less, then taper. | Administer dexamethasonee 10 mg intravenously every 6 hours. Continue dexamethasone use until resolution to Grade 1 or less, then taper. | |||
| Consider non-sedating, anti-seizure medicines (e.g., levetiracetam) for seizure prophylaxis. Consider neurology consultation and other specialists for further evaluation, as needed. | ||||||
| Grade 3 | ICE score 0-2c or depressed level of consciousnessd: awakens only to tactile stimulus, or seizuresd, either:
| Management of CRS (see Table 10). In addition, administer dexamethasonee 10 mg intravenously with the first dose of tocilizumab and repeat dose every 6 hours. Continue dexamethasone use until resolution to Grade 1 or less, then taper. | Administer dexamethasonee 10 mg intravenously every 6 hours. Continue dexamethasone use until resolution to Grade 1 or less, then taper. | |||
| Consider non-sedating, anti-seizure medicines (e.g., levetiracetam) for seizure prophylaxis. Consider neurology consultation and other specialists for further evaluation, as needed. | ||||||
| Grade 4 | ICE score-0c or depressed level of consciousnessd either:
or seizuresd, either:
or motor findingsd:
or raised intracranial pressure/cerebral edemad, with signs/symptoms such as:
| Management of CRS (see Table 10). Administer dexamethasonee 10 mg intravenously with the first dose of tocilizumab and repeat dose every 6 hours. Continue dexamethasone use until resolution to Grade 1 or less, then taper. Alternatively, consider administration of methylprednisolone 1000 mg per day intravenously with first dose of tocilizumab, and continue methylprednisolone 1000 mg per day intravenously for 2 or more days. | Administer dexamethasonee 10 mg and repeat dose every 6 hours. Continue dexamethasone use until resolution to Grade 1 or less, then taper. Alternatively, consider administration of methylprednisolone 1000 mg per day intravenously for 3 days; if improves, then manage as above. | |||
| Consider non-sedating, anti-seizure medicines (e.g., levetiracetam) for seizure prophylaxis. Consider neurology consultation and other specialists for further evaluation, as needed. In case of raised intracranial pressure/cerebral edema, refer to local institutional guidelines for management. | ||||||
a Management is determined by the most severe event, not attributable to any other cause.
b The recommendations describe the ICANS management in Studies MajesTEC-1 and MajesTEC-3. Treat ICANS per institutional guidelines.
c If patient is arousable and able to perform Immune Effector Cell-Associated Encephalopathy (ICE) Assessment, assess: Orientation (oriented to year, month, city, hospital = 4 points); Naming (name 3 objects, e.g., point to clock, pen, button = 3 points); Following Commands (e.g., “show me 2 fingers” or “close your eyes and stick out your tongue” = 1 point); Writing (ability to write a standard sentence = 1 point; and Attention (count backwards from 100 by ten = 1 point). If patient is unarousable and unable to perform ICE Assessment (Grade 4 ICANS) = 0 points.
d Attributable to no other cause.
e All references to dexamethasone administration are dexamethasone or equivalent
Reproductive Health
Fertility
There are no data on the effect of TECVAYLI on fertility. Effects of TECVAYLI on male and female fertility have not been evaluated in animal studies.
7.1. Special Populations
7.1.1. Pregnancy
There are no available data on the use of TECVAYLI during pregnancy or animal data to assess the risk of TECVAYLI in pregnancy. Human IgG is known to cross the placenta after the first trimester of pregnancy. Therefore, teclistamab has the potential to be transmitted to the developing fetus. TECVAYLI should not be administered to individuals who are pregnant.
TECVAYLI is associated with hypogammaglobulinemia, therefore, assessment of immunoglobulin levels in newborns of individuals treated with TECVAYLI should be considered.
Contraception
Advise females of reproductive potential to use effective contraception during treatment and for five months after the final dose of TECVAYLI.
Advise male patients with a female partner of reproductive potential to use effective contraception during treatment and for three months after the last dose of TECVAYLI.
7.1.2. Breastfeeding
It is not known whether teclistamab is excreted in human or animal milk, affects infants receiving breastmilk, or affects milk production. Because of the potential for serious adverse reactions, advise individuals treated with TECVAYLI not to provide breastmilk (directly or from a bottle) to infants during treatment with TECVAYLI and for at least five months after the last dose.
7.1.3. Pediatrics
Pediatrics (<18 years of age): No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use.
7.1.4. Geriatrics
Geriatrics (≥ 65 years of age): Of the 165 patients treated with TECVAYLI in MajesTEC-1 at the recommended dose, 48% were 65 years of age or older, and 15% were 75 years of age or older.
Of the 291 patients treated with TECVAYLI in combination with daratumumab in MajesTEC-3 at the recommended dosage, 50% were 65 years of age or older, and 11% were 75 years of age or older.
No overall differences in safety or effectiveness were observed between these patients and younger patients. No dose adjustment is necessary.
8. Adverse Reactions
8.1. Adverse Reaction Overview
Combination therapy with daratumumab
The safety data of TECVAYLI in combination with daratumumab was evaluated in a Phase 3 clinical study, MajesTEC-3, which included 283 adults with relapsed or refractory multiple myeloma who received the recommended dose regimen of subcutaneous (SC) TECVAYLI in combination with SC daratumumab compared with either daratumumab, pomalidomide and dexamethasone (DPd) or daratumumab, bortezomib and dexamethasone (DVd). The median duration of treatment was 32 (range: 0.03 to 43) months for TECVAYLI in combination with daratumumab, and 16 (range: 0.03 to 45) months for DPd or DVd.
The most frequent adverse reactions of any grade (≥ 20%) in participants were hypogammaglobulinemia, cytokine release syndrome, upper respiratory tract infection, COVID-19, pneumonia, cough, diarrhea, nausea, musculoskeletal pain, fatigue, injection site reaction, pyrexia, pain, headache and weight decreased.
Serious adverse reactions were reported in 71% participants who received TECVAYLI in combination with daratumumab. Serious adverse reactions reported in ≥2% of participants included pneumonia (26%), COVID-19 (17%), upper respiratory tract infection (13%), cytokine release syndrome (10%), sepsis (6%), pyrexia (4.9%) and febrile neutropenia (4.6%).
Fatal adverse reactions occurring within 30 days of the last dose were reported in 2.5% of participants who received TECVAYLI in combination with daratumumab, and included sepsis (0.7%), pneumonia (0.4%), sudden death (0.4%), myocardial infarction (0.4%), enterovirus myocarditis (0.4%) and hemophagocytic lymphohistiocytosis (0.4%). Permanent discontinuation of TECVAYLI in combination with daratumumab due to adverse reactions occurred in 4.6% of participants. The most frequent adverse reactions leading to treatment discontinuation were pneumonia (1.1%), diarrhea (0.7%), fatigue (0.7%) and cough (0.7%).
Monotherapy
The safety data of TECVAYLI was evaluated in MajesTEC-1, which included 165 adult participants with relapsed or refractory multiple myeloma who received the recommended dose regimen of subcutaneous TECVAYLI as monotherapy. The median duration of TECVAYLI treatment was 8.5 (range: 0.2 to 24.4) months.
The most frequent adverse reactions of any grade (≥ 20%) in participants were hypogammaglobulinemia, cytokine release syndrome, neutropenia, anemia, musculoskeletal pain, fatigue, thrombocytopenia, injection site reaction, upper respiratory tract infection, lymphopenia, diarrhea, pneumonia, nausea, pyrexia, headache, cough, constipation, hypotension and pain.
Serious adverse reactions were reported in 65% participants who received TECVAYLI. Serious adverse reactions reported in ≥ 2% of participants included pneumonia (16%), COVID 19 (15%), cytokine release syndrome (8%), sepsis (7%), pyrexia (5%), musculoskeletal pain (5%), acute kidney injury (4.8%), diarrhea (3.0%), cellulitis (2.4%), hypoxia (2.4%), febrile neutropenia (2.4%), and encephalopathy (2.4%). Fatal adverse events were reported in 18 participants (10.9%), and the most commonly reported fatal adverse event was infection (15 participants [9.1%], including 12 participants [7.3%] with fatal COVID-19 infection).
Dose interruptions (dose delays and dose skips) of TECVAYLI due to adverse reactions occurred in 65% of participants. The most frequent adverse reactions (≥ 5%) leading to dose interruptions were neutropenia (26%), COVID-19 (12%), pneumonia (10%), cytokine release syndrome (8%), and pyrexia (7%).
Dose reduction of TECVAYLI due to adverse reaction occurred in one participant (0.6%) due to neutropenia.
Permanent discontinuation of TECVAYLI due to adverse reactions occurred in two participants (1.2%), both due to infections.
8.2. Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials; therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
Combination therapy with daratumumab
Table 12 lists adverse reactions reported in ≥10% of participants who received TECVAYLI in combination with daratumumab in MajesTEC-3.
Table 12: Adverse Reactions (>10%) in Adults with Multiple Myeloma who received TECVAYLI in combination with daratumumab in MajesTEC-3
MedDRA System Organ Class Adverse Reaction | TECVAYLI in combination with daratumumab (N=283) | DPd or DVd (N=290) | ||||||||||||||||||
MedDRA System Organ Class Adverse Reaction | TECVAYLI in combination with daratumumab (N=283) | DPd or DVd (N=290) | ||||||||||||||||||
MedDRA System Organ Class Adverse Reaction | TECVAYLI in combination with daratumumab (N=283) | DPd or DVd (N=290) | ||||||||||||||||||
| n (%) | n (%) | |||||||||||||||||||
| n (%) | n (%) | |||||||||||||||||||
| n (%) | n (%) | |||||||||||||||||||
| Any Grade | Grade 3 or 4 | Any Grade | Grade 3 or 4 | |||||||||||||||||
| Any Grade | Grade 3 or 4 | Any Grade | Grade 3 or 4 | |||||||||||||||||
| Any Grade | Grade 3 or 4 | Any Grade | Grade 3 or 4 | |||||||||||||||||
| Cardiac Disorders | ||||||||||||||||||||
| Cardiac arrhythmias1 | 32 (11%) | 3 (1.1%) | 21 (7%) | 6 (2.1%) | ||||||||||||||||
| Gastrointestinal disorders | ||||||||||||||||||||
| Diarrhea2 | 147 (52%) | 10 (3.5%) | 89 (31%) | 7 (2.4%) | ||||||||||||||||
| Nausea | 65 (23%) | 0 | 36 (12%) | 1 (0.3%) | ||||||||||||||||
| Vomiting | 49 (17%) | 0 | 20 (7%) | 0 | ||||||||||||||||
| Abdominal pain3 | 46 (16%) | 2 (0.7%) | 37 (13%) | 0 | ||||||||||||||||
| Constipation | 40 (14%) | 0 | 57 (20%) | 1 (0.3%) | ||||||||||||||||
| General disorders and administration site conditions | ||||||||||||||||||||
| Fatigue4 | 116 (41%) | 11 (3.9%) | 120 (41%) | 12 (4.1%) | ||||||||||||||||
| Injection site reaction5 | 108 (38%) | 0 | 0 | 0 | ||||||||||||||||
| Pyrexia | 104 (37%) | 4 (1.4%) | 55 (19%) | 1 (0.3%) | ||||||||||||||||
| Pain6 | 84 (30%) | 2 (0.7%) | 61 (21%) | 6 (2.1%) | ||||||||||||||||
| Edema7 | 37 (13%) | 1 (0.4%) | 64 (22%) | 1 (0.3%) | ||||||||||||||||
| Immune system disorders | ||||||||||||||||||||
| Hypogammaglobulinemia8 | 239 (84%) | 18 (6%) | 175 (60%) | 4 (1.4%) | ||||||||||||||||
| Cytokine release syndrome | 170 (60%) | 0 | 0 | 0 | ||||||||||||||||
| Infections and infestations | ||||||||||||||||||||
| Upper respiratory tract infection9 | 215 (76%) | 39 (14%) | 164 (57%) | 27 (9%) | ||||||||||||||||
| COVID-1910 | 130 (46%) | 42 (15%) | 106 (37%) | 13 (4.5%) | ||||||||||||||||
| Pneumonia11 | 100 (35%) | 74 (26%) | 89 (31%) | 75 (26%) | ||||||||||||||||
| Urinary tract infection12 | 46 (16%) | 8 (2.8%) | 39 (13%) | 3 (1%) | ||||||||||||||||
| Herpes virus infection13 | 32 (11%) | 6 (2.1%) | 17 (6%) | 1 (0.3%) | ||||||||||||||||
| Investigations | ||||||||||||||||||||
| Weight decreased | 57 (20%) | 8 (2.8%) | 20 (7%) | 4 (1.4%) | ||||||||||||||||
| Alanine aminotransferase increased | 56 (20%) | 7 (2.5%) | 22 (8%) | 2 (0.7%) | ||||||||||||||||
| Aspartate aminotransferase increased | 48 (17%) | 5 (1.8%) | 16 (6%) | 2 (0.7%) | ||||||||||||||||
| Lactate dehydrogenase increased | 32 (11%) | 0 | 11 (4%) | 0 | ||||||||||||||||
| Gamma-glutamyltransferase increased | 32 (11%) | 7 (2.5%) | 10 (3%) | 0 | ||||||||||||||||
| Metabolism and nutrition disorders | ||||||||||||||||||||
| Decreased appetite | 54 (19%) | 3 (1.1%) | 19 (7%) | 0 | ||||||||||||||||
| Musculoskeletal and connective tissue disorders | ||||||||||||||||||||
| Musculoskeletal pain14 | 137 (48%) | 4 (1.4%) | 145 (50%) | 12 (4.1%) | ||||||||||||||||
| Nervous system disorders | ||||||||||||||||||||
| Headache | 73 (26%) | 4 (1.4%) | 34 (12%) | 0 | ||||||||||||||||
| Respiratory, thoracic and mediastinal disorders | ||||||||||||||||||||
| Cough15 | 149 (53%) | 2 (0.7%) | 70 (24%) | 0 | ||||||||||||||||
| Dyspnea16 | 44 (16%) | 12 (4.2%) | 61 (21%) | 8 (2.8%) | ||||||||||||||||
| Vascular disorders | ||||||||||||||||||||
| Hypertension17 | 32 (11%) | 13 (4.6%) | 17 (6%) | 7 (2.4%) | ||||||||||||||||
Key: DVd = daratumumab-bortezomib-dexamethasone; DPd = daratumumab-pomalidomide-dexamethasone Note: Percentages calculated with the number of subjects in each treatment group as denominator. Note: Adverse events are graded according to the NCI-CTCAE Version 5.0, with the exception of ICANS and CRS, which were graded by ASTCT consensus grading system (Lee et al 2019).
| ||||||||||||||||||||
Monotherapy
Table 13 lists adverse reactions reported in ≥5% of participants who received TECVAYLI in MajesTEC-1.
Table 13: Adverse Reactions (≥5%) in Adults with Multiple Myeloma Treated with TECVAYLI in MajesTEC-1
System Organ Class Adverse Reaction | N=165 | ||||||||
System Organ Class Adverse Reaction | N=165 | ||||||||
| Incidence (%) | |||||||||
| Incidence (%) | |||||||||
| Any Grade | Grade 3 or 4 | ||||||||
| Any Grade | Grade 3 or 4 | ||||||||
| Blood and lymphatic system disorders | |||||||||
| Neutropenia | 117 (71%) | 106 (64%) | |||||||
| Anemia1 | 90 (55%) | 61 (37%) | |||||||
| Thrombocytopenia | 66 (40%) | 35 (21%) | |||||||
| Lymphopenia | 57 (35%) | 54 (33%) | |||||||
| Leukopenia | 29 (18%) | 12 (7%) | |||||||
| Cardiac disorders | |||||||||
| Cardiac arrhythmias2 | 29 (18%) | 4 (2.4%) | |||||||
| Gastrointestinal disorders | |||||||||
| Diarrhoea | 47 (28%) | 6 (3.6%) | |||||||
| Nausea | 46 (28%) | 1 (0.6%) | |||||||
| Constipation | 34 (21%) | 0 | |||||||
| Vomiting | 22 (13%) | 1 (0.6%) | |||||||
| General disorders and administration site conditions | |||||||||
| Pyrexia | 130 (79%) | 5 (3.0%) | |||||||
| Fatigue3 | 67 (41%) | 5 (3.0%) | |||||||
| Injection site reaction4 | 62 (38%) | 1 (0.6%) | |||||||
| Pain5 | 34 (21%) | 3 (1.8%) | |||||||
| Chills | 30 (18%) | 0 | |||||||
| Edema6 | 23 (14%) | 0 | |||||||
| Immune system disorders | |||||||||
| Hypogammaglobulinaemia7 | 123 (75%) | 3 (1.8%) | |||||||
| Cytokine release syndrome^ | 119 (72%) | 1 (0.6%) | |||||||
| Infections and infestations | |||||||||
| Upper respiratory tract infection8 | 61 (37%) | 4 (2.4%) | |||||||
| Pneumonia9* | 46 (28%) | 32 (19%) | |||||||
| COVID-1910* | 30 (18%) | 20 (12%) | |||||||
| Sepsis11 | 13 (8%) | 11 (7%) | |||||||
| Metabolism and nutrition disorders | |||||||||
| Decreased appetite | 20 (12%) | 1 (0.6%) | |||||||
| Musculoskeletal and connective tissue disorders | |||||||||
| Musculoskeletal pain12 | 86 (52%) | 14 (8%) | |||||||
| Nervous system disorders | |||||||||
| Headache | 44 (27%) | 1 (0.6%) | |||||||
| Motor dysfunction13 | 31 (19%) | 0 | |||||||
| Neuropathy peripheral14 | 26 (16%) | 1 (0.6%) | |||||||
| Encephalopathy15 | 17 (10%) | 0 | |||||||
| Renal and urinary disorders | |||||||||
| Acute kidney injury16 | 18 (11%) | 6 (3.6%) | |||||||
| Respiratory, thoracic and mediastinal disorders | |||||||||
| Cough17 | 39 (24%) | 0 | |||||||
| Hypoxia | 33 (20%) | 6 (3.6%) | |||||||
| Dyspnea18 | 22 (13%) | 3 (1.8%) | |||||||
| Vascular disorders | |||||||||
| Hypotension | 34 (21%) | 4 (2.4%) | |||||||
| Hypertension19 | 22 (13%) | 9 (5%) | |||||||
| Hemorrhage20* | 20 (12%) | 5 (3.0%) | |||||||
CRS = cytokine release syndrome.
CRS was graded by ASTCT consensus grading system (Lee et al 2019). Adverse events are coded using MedDRA Version 24.0.
* Includes fatal events
^ CRS-related symptoms reported in MajesTEC-1 include pyrexia, hypoxia, chills, hypertension, sinus tachycardia, headache, nausea, myalgia, fatigue, back pain, hypotension, vomiting.
1 Anemia includes Anaemia, Iron deficiency and Iron deficiency Anaemia.
2 Cardiac arrhythmias includes Atrial flutter, Cardiac arrest, Sinus bradycardia, Sinus tachycardia, Supraventricular tachycardia and Tachycardia.
3 Fatigue includes Asthenia, Fatigue and Malaise.
4 Injection site reaction includes Injection site bruising, Injection site cellulitis, Injection site discomfort, Injection site erythema, Injection site haematoma, Injection site induration, Injection site inflammation, Injection site oedema, Injection site pruritus, Injection site rash, Injection site reaction and Injection site swelling.
5 Pain includes Ear pain, Flank pain, Groin pain, Non-cardiac chest pain, Oropharyngeal pain, Pain, Pain in jaw, Toothache and Tumour pain.
6 Edema includes Face oedema, Fluid overload, Oedema peripheral and Peripheral swelling.
7 Hypogammaglobulinaemia includes participants with adverse events of hypogammaglobulinaemia, hypoglobulinaemia, immunoglobulins decreased; and/or participants with laboratory IgG levels below 500 mg/dL following treatment with Teclistamab.
8 Upper respiratory tract infection includes Bronchitis, Nasopharyngitis, Pharyngitis, Respiratory tract infection, Respiratory tract infection bacterial, Rhinitis, Rhinovirus infection, Sinusitis, Tracheitis, Upper respiratory tract infection and Viral upper respiratory tract infection.
9 Pneumonia includes Enterobacter pneumonia, Lower respiratory tract infection, Lower respiratory tract infection viral, Metapneumovirus pneumonia, Pneumocystis jirovecii pneumonia, Pneumonia, Pneumonia adenoviral, Pneumonia bacterial, Pneumonia klebsiella, Pneumonia moraxella, Pneumonia pneumococcal, Pneumonia pseudomonal, Pneumonia respiratory syncytial viral, Pneumonia staphylococcal and Pneumonia viral.
10 COVID-19 includes Asymptomatic COVID-19 and COVID-19.
11 Sepsis includes Bacteraemia, Meningococcal sepsis, Neutropenic sepsis, Pseudomonal bacteraemia, Pseudomonal sepsis, Sepsis and Staphylococcal bacteraemia.
12 Musculoskeletal pain includes Arthralgia, Back pain, Bone pain, Musculoskeletal chest pain, Musculoskeletal pain, Myalgia, Neck pain and Pain in extremity.
13 Motor dysfunction includes Cogwheel rigidity, Dysgraphia, Dysphonia, Gait disturbance, Hypokinesia, Muscle rigidity, Muscle spasms, Muscular weakness, Peroneal nerve palsy, Psychomotor hyperactivity, Tremor and VIth nerve paralysis.
14 Neuropathy peripheral includes Dysaesthesia, Hypoaesthesia, Hypoaesthesia oral, Neuralgia, Paraesthesia, Paraesthesia oral, Peripheral sensory neuropathy and Sciatica.
15 Encephalopathy includes Confusional state, Depressed level of consciousness, Lethargy, Memory impairment and Somnolence.
16 Acute kidney injury includes Acute kidney injury and Renal impairment.
17 Cough includes Allergic cough, Cough, Productive cough and Upper-airway cough syndrome.
18 Dyspnea includes Acute respiratory failure, Dyspnoea and Dyspnoea exertional
19 Hypertension includes Essential hypertension and Hypertension.
20 Hemorrhage includes Conjunctival haemorrhage, Epistaxis, Haematoma, Haematuria, Haemoperitoneum, Haemorrhoidal haemorrhage, Lower gastrointestinal haemorrhage, Melaena, Mouth haemorrhage and Subdural haematoma.
Description of Selected Adverse Reactions
Cytokine Release Syndrome
In clinical trials (combination therapy and monotherapy; N=448), CRS was reported in 65% of participants following treatment with TECVAYLI. Twenty seven percent (27%) of participants experienced more than one CRS event. Most participants experienced CRS during the initial step-up dosing schedule (Step-up Dose 1 (38%), Step-up Dose 2 (32%), or the initial treatment dose (20%)). Most CRS events were Grade 1 (46%) and Grade 2 (18%). Less than one percent (0.2%) of CRS events were Grade 3, and no Grade 4 or fatal events occurred. The median time to onset of CRS was 2 (range: 1 to 9) days after the most recent dose and the median duration of CRS was 2 (range: 1 to 22) days.
The most frequent (≥ 3%) signs and symptoms associated with CRS were fever (64%), hypotension (14%), chills (9%), hypoxia (8%), headache (5%) and sinus tachycardia (3.6%).
In clinical trials, tocilizumab, corticosteroids and tocilizumab in combination with corticosteroids were used to treat CRS in 33%, 5% and 1.9% of CRS events, respectively.
ICANS
In MajesTEC-1 (N=165), ICANS was reported in 3% of participants receiving TECVAYLI at the recommended dose. The most frequent clinical manifestations of ICANS reported were confusional state (1.2%) and dysgraphia (1.2%).
In MajesTEC-3 (N=283), ICANS was reported in 1.1% of participants receiving TECVAYLI in combination with daratumumab at the recommended dose. Grade 1 events occurred in 2 participants, and a Grade 4 event occurred in 1 participant. The clinical manifestations of ICANS reported were amnesia (0.4%), encephalopathy (0.4%) and delirium (0.4%).
Infection
In MajesTEC-3 (N=283), in participants who received TECVAYLI in combination with daratumumab at the recommended dose, serious infections occurred in 54% of participants, with Grade 3 or 4 infections in 54% of participants and fatal infections in 4.6%.
In MajesTEC-1 (N=165), in participants who received TECVAYLI at the recommended dose, serious infections occurred in 47% of participants, with Grade 3 or 4 infections in 55% of participants and fatal infections in 13%.
Longer-term Follow-up
In MajesTEC-1 (N=165), based on an updated safety analysis with a median follow-up of 30.4 months (median treatment duration of 9.3 months) additional adverse reactions occurring in ≥10% of participants were: abdominal pain (Any Grade: 12%, Grade 3 or 4: 1.2%), urinary tract infection (Any Grade: 14%, Grade 3 or 4: 6%), and hypoglycemia (Any Grade: 23%, Grade 3 or 4: 0%). Grade 5 treatment-emergent adverse events were reported in 8 additional participants (including COVID-19 in 6 participants and 1 participant each for Guillain Barré syndrome and influenza). Six additional participants discontinued study treatment due to adverse events (including 2 participants with COVID-19, and 1 participant each: sepsis, arthralgia, arthritis, and brain neoplasm).
8.3. Less Common Clinical Trial Adverse Reactions
Combination therapy with daratumumab
Clinically relevant adverse reactions reported in <10% of participants who received TECVAYLI in combination with daratumumab in MajesTEC-3 are summarized below:
Blood and lymphatic system disorders: Febrile neutropenia (7.4%)
Infections and infestations: Sepsis (9.9%)
Nervous system disorders: Immune effector cell-associated neurotoxicity syndrome (1.1%)
Monotherapy
Clinically relevant adverse reactions reported in less than 5% of participants who received TECVAYLI in MajesTEC-1 are summarized below:
Blood and lymphatic system disorders: Febrile neutropenia (3.6%)
Infections and infestations: Cellulitis (4.2%), herpes simplex (2.4%), herpes zoster (1.2%), hepatitis B reactivation (0.6%), adenovirus reactivation (0.6%), BK virus infection (0.6%), cytomegalovirus infection reactivation (0.6%), progressive multifocal leukoencephalopathy (0.6%)
Nervous system disorders: Immune effector cell-associated neurotoxicity syndrome (3%)
8.4. Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data
Clinical Trial Findings
Combination therapy with daratumumab
Table 14 lists laboratory abnormalities in participants who received TECVAYLI in combination with daratumumab in MajesTEC-3.
Table 14: Grade 3 or 4 Laboratory Abnormalities in ≥10% of Adults with Multiple Myeloma who received TECVAYLI in combination with daratumumab in MajesTEC-3
| Laboratory Abnormality | TECVAYLI in combination with daratumumab (N=283) | DPd or DVd (N=290) | |||||||||
| n (%) | n (%) | ||||||||||
| Any Grade (%) | Grade 3 or 4 (%) | Any Grade (%) | Grade 3 or 4 (%) | ||||||||
| Lymphocyte Count Decreased | 280 (99%) | 268 (95%) | 275 (95%) | 189 (65%) | |||||||
| White Blood Cell Decreased | 274 (97%) | 169 (60%) | 287 (99%) | 213 (73%) | |||||||
| Anemia | 271 (96%) | 55 (19%) | 282 (97%) | 55 (19%) | |||||||
| Neutrophil Count Decreased | 263 (93%) | 221 (78%) | 276 (95%) | 244 (84%) | |||||||
| Platelet Count Decreased | 249 (88%) | 58 (21%) | 247 (85%) | 72 (25%) | |||||||
| Hypokalemia | 154 (54%) | 43 (15%) | 111 (38%) | 25 (9%) | |||||||
| Hyponatremia | 152 (54%) | 29 (10%) | 125 (43%) | 18 (6%) | |||||||
Key: DVd = daratumumab-bortezomib-dexamethasone; DPd = daratumumab-pomalidomide-dexamethasone
Note: Percentages calculated with the number of subjects in each treatment group as denominator.
Note: The laboratory toxicity grades are derived based on the NCI CTCAE Version 5.0
Other clinically important Grade 3 or 4 laboratory abnormalities (based on laboratory data) reported in ≥2% and up to 10% of participants in the TECVAYLI-Dara arm, and reported at ≥1% higher incidence compared to DPd or DVd include alanine transaminase increased, aspartate transaminase increased, gamma-glutamyltransferase increased, hypercalcemia, hyperkalaemia, hypophosphatemia and serum amylase increase.
Monotherapy
Table 15 lists laboratory abnormalities that worsened from baseline in participants who received TECVAYLI in MajesTEC-1.
Table 15: Laboratory Abnormalities Worsening from Baseline in at least 20% of Adults with Multiple Myeloma Treated with TECVAYLI in MajesTEC-1
| Laboratory Abnormality | N=165 | |||||||
| n (%) | ||||||||
| Any Grade | Grade 3 or 4 | |||||||
| Lymphocyte count decreased | 151 (92%) | 137 (83%) | ||||||
| White blood cell decreased | 147 (89%) | 72 (44%) | ||||||
| Neutrophil count decreased | 143 (87%) | 104 (63%) | ||||||
| Platelet count decreased | 120 (73%) | 38 (23%) | ||||||
| Hypoalbuminemia | 118 (72%) | 10 (6%) | ||||||
| Anemia | 117 (71%) | 61 (37%) | ||||||
| Alkaline phosphatase increased | 71 (43%) | 5 (3.0%) | ||||||
| Hypophosphatemia | 71 (43%) | 24 (15%) | ||||||
| Aspartate aminotransferase increased | 67 (41%) | 5 (3.0%) | ||||||
| Gamma-glutamyltransferase increased | 63 (38%) | 15 (9%) | ||||||
| Hyponatremia | 59 (36%) | 20 (12%) | ||||||
| Alanine aminotransferase increased | 57 (35%) | 7 (4.2%) | ||||||
| Hypocalcemia (Corrected) | 57 (35%) | 3 (1.8%) | ||||||
| Creatinine increased | 56 (34%) | 5 (3.0%) | ||||||
| Hypokalemia | 51 (31%) | 8 (4.8%) | ||||||
| Hypomagnesemia | 47 (28%) | 0 | ||||||
| Hypercalcemia (Corrected) | 46 (28%) | 7 (4.2%) | ||||||
| Lipase increased | 42 (25%) | 9 (5%) | ||||||
| Serum amylase increased | 39 (24%) | 7 (4.2%) | ||||||
| Hyperkalemia | 33 (20%) | 3 (1.8%) | ||||||
| Laboratory toxicity grades are derived based on the NCI CTCAE (National Cancer Institute Common Terminology Criteria for Adverse Events) Version 4.03. | ||||||||
| Lipase Increased | 127 (45%) | 44 (16%) | 58 (20%) | 13 (4.5%) |
8.5. Post-Market Adverse Reactions
The following adverse reactions have been reported during post-marketing experience. As limited relevant information is available from voluntary reporting, meaningful estimates of frequency and a robust data review and analysis is not always possible.
Nervous system disorders: Immune effector cell-associated neurotoxicity syndrome (includes events with fatal outcome) (see 7. Warnings and Precautions)
9. Drug Interactions
9.2. Drug Interactions Overview
No drug interaction studies have been performed with TECVAYLI.
9.4. Drug-Drug Interactions
The initial release of cytokines associated with the start of TECVAYLI treatment could suppress CYP450 enzymes. Based on physiologically based pharmacokinetic (PBPK) modelling, the highest risk of drug-drug interaction is predicted to be from initiation of TECVAYLI step-up dosing schedule up to 7 days after the first Treatment Dose or during a CRS event. During this time period, monitor for toxicity or drug concentrations (e.g., cyclosporine) in patients who are receiving concomitant CYP450 substrates with a narrow therapeutic index. The dose of the concomitant drug should be adjusted as needed.
9.5. Drug-Food Interactions
Interactions with food have not been established.
9.6. Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7. Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10. Clinical Pharmacology
10.1. Mechanism of Action
Teclistamab is a full-size, IgG4-PAA bispecific antibody that targets the CD3 receptor expressed on the surface of T-cells and B-cell maturation antigen (BCMA) expressed on the surface of malignant multiple myeloma and healthy B-lineage cells and plasma cells. With its dual binding sites, teclistamab is able to draw CD3+ T-cells in close proximity to BCMA+ cells, resulting in T-cell activation and subsequent lysis and death of BCMA+ cells, which is mediated by secreted perforin and various granzymes stored in the secretory vesicles of cytotoxic T-cells. This effect occurs without regard to T-cell receptor specificity or reliance on major histocompatibility complex (MHC) Class 1 molecules on the surface of antigen presenting cells.
10.2. Pharmacodynamics
Within the first month of treatment with teclistamab, activation and redistribution of T-cells, reduction of B-cells and induction of serum cytokines were observed.
T-cell redistribution was demonstrated by reduction in peripheral CD4+ and CD8+ T-cells after the initial doses (step up and first full treatment dose) of teclistamab, followed by T-cell recovery beginning by C1D15. Reduction of CD19+ B-cells was observed in patients treated at pivotal recommended Phase II dose (RP2D) within the first cycle (beginning after the initial step-up doses) with persistent decreased levels observed at Cycle 3. Non-myeloma IgG had an initial decrease followed by a slight and gradual increase over time, which likely reflects increased use of IVIG during treatment. Induction of IL-10, IFN-g, TNF-α or IL-6 was observed following teclistamab administration. There was heterogeneity in the kinetics of cytokine increase, with considerable variability between patients when maximum induction occurred.
10.3. Pharmacokinetics
Teclistamab exhibited approximately dose-proportional pharmacokinetics following subcutaneous administration across a dose range of 0.08 mg/kg to 3 mg/kg in monotherapy. Following the recommended dose of teclistamab monotherapy, 90% of steady state exposure was achieved after 12 weekly treatment doses. The mean accumulation ratio between the first and 13th weekly maintenance dose of teclistamab 1.5 mg/kg was 4.2-fold for Cmax, 4.1-fold for Ctrough, and 5.3-fold for Cavg.
The pharmacokinetics of teclistamab were consistent whether used as monotherapy or in combination with daratumumab.
The Cmax, Ctrough, and Cavg of teclistamab are presented in Table 16.
Table 16: Pharmacokinetic Parameters of Teclistamab for the Recommended Dose in Adults with Relapsed or Refractory Multiple Myeloma
| Cmax (µg/mL) | Ctrough (µg/mL) | Cavg (µg/mL) | |||||
| Teclistamab Monotherapy | |||||||
| Steady state of 1.5 mg/kg weekly dosinga | 23.8 (55%) | 21.1 (63%) | 22.8 (57%) | ||||
| Teclistamab in Combination with Daratumumab | |||||||
| First 1.5 mg/kg dose | 6.36 (54%) | 5.79 (59%) | 4.96 (55%) | ||||
| End of 1.5 mg/kg weekly dosingb | 19.6 (54%) | 17.3 (62%) | 18.6 (56%) | ||||
| End of 3.0 mg/kg biweekly dosingc | 29.9 (55%) | 19.8 (85%) | 26.2 (62%) | ||||
| Steady state of 3.0 mg/kg Q4W dosingd | 20.2 (52%) | 5.82 (152%) | 13.7 (67%) | ||||
Cavg=average serum teclistamab concentration over a dosing interval; Cmax=maximum serum teclistamab concentration; Ctrough=serum teclistamab concentration prior to next dose; Q4W=every 4 weeks a steady-state exposure for the 13th weekly dose. b exposure for the 7th weekly dose. c exposure for the 8th biweekly dose. d steady-state exposure for the 5th Q4W dose. Note: Data are presented as geometric mean (CV %). | |||||||
Absorption
The mean bioavailability of teclistamab was 72% when administered subcutaneously. The median (range) Tmax of teclistamab after the first and 13th weekly maintenance doses in monotherapy were 139 (19 to 168) hours and 72 (24 to 168) hours, respectively.
Distribution
The mean volume of distribution was 5.63 L (29% coefficient of variation [CV]).
Elimination
Teclistamab clearance decreases over time, with a mean (CV%) maximal reduction from baseline to the 13th weekly treatment dose in monotherapy of 40.8% (56%). The geometric mean (CV%) clearance is 0.472 L/day (64%) at the 13th weekly treatment dose in monotherapy. Patients who discontinue teclistamab after the 13th weekly treatment dose in monotherapy are expected to have a 50% reduction from Cmax in teclistamab concentration at a median (5th to 95th percentile) time of 15 (7 to 33) days after Tmax and a 97% reduction from Cmax in teclistamab concentration at a median time of 69 (32 to 163) days after Tmax.
Population pharmacokinetic analysis showed that soluble BCMA did not impact teclistamab serum concentrations.
Special Populations and Conditions
- Pediatrics: The pharmacokinetics of teclistamab in pediatric patients have not been investigated.
- Geriatrics: Results of population pharmacokinetic analyses indicate that age (24 to 84 years) did not significantly influence the pharmacokinetics of teclistamab.
- Sex: Results of population pharmacokinetic analyses indicate that sex did not influence the pharmacokinetics of teclistamab.
Hepatic Insufficiency: No formal studies of TECVAYLI in patients with hepatic impairment have been conducted.
Results of population pharmacokinetic analyses indicate that mild hepatic impairment (total bilirubin less than or equal to upper limit of normal [ULN] with AST greater than ULN or total bilirubin greater than 1 to 1.5 times ULN with any AST) did not significantly influence the pharmacokinetics of teclistamab. Limited data are available from patients with moderate hepatic impairment, and no data are available in patients with severe hepatic impairment.
Renal Insufficiency: No formal studies of TECVAYLI in patients with renal impairment have been conducted.
Results of population pharmacokinetic analyses indicate that mild or moderate renal impairment (estimated glomerular filtration rate [eGFR] by Modification of Diet in Renal Disease [MDRD] method: 30 to 89 mL/min) did not significantly influence the pharmacokinetics of teclistamab.
10.4. Immunogenicity
All therapeutic proteins have the potential for immunogenicity.
The detection of antibody formation is highly dependent on the sensitivity and specificity of the assay. Additionally, the observed incidence of antibody (including neutralizing antibody) positivity in an assay may be influenced by several factors including assay methodology, sample handling, timing of sample collection, concomitant medications, and underlying disease. For these reasons, comparison of incidence of antibodies in the studies described below with the incidences of antibodies in other studies or to other products may be misleading.
Patients treated with subcutaneous TECVAYLI were evaluated for antibodies to teclistamab using an electrochemiluminescence-based immunoassay. One patient (0.4%) in TECVAYLI monotherapy (N=238) and two patients (0.5%) in TECVAYLI in combination with daratumumab (N=379) developed antibodies to teclistamab. One patient in TECVAYLI monotherapy and one patient in TECVAYLI in combination with daratumumab developed neutralizing antibodies to teclistamab.
11. Storage, Stability and Disposal
Store refrigerated at 2°C to 8°C. Do not freeze.
Store in the original carton in order to protect from light.
Keep out of the sight and reach of children.
12. Special Handling Instructions
Any unused medicinal product or waste material should be disposed of in accordance with local requirements.
Part 2: Scientific Information
13. Pharmaceutical Information
Drug Substance
Non-proprietary name of the drug substance: teclistamab
Molecular formula and molecular mass: approximately 146 kDa
Structure: TECVAYLI (teclistamab) is a humanized immunoglobulin G4-proline, alanine, alanine (IgG4-PAA) bispecific antibody targeting the B cell maturation antigen (BCMA) and cluster of differentiation 3 (CD3) receptors.
Physicochemical properties: TECVAYLI is a clear to slightly opalescent, colourless to light yellow preservative-free solution for injection.
Product Characteristics:
TECVAYLI is produced in a mammalian cell line (Chinese Hamster Ovary [CHO]) using recombinant DNA technology.
14. Clinical Trials
14.1. Clinical Trials by Indication
Multiple Myeloma after One to Three Prior Lines of Therapy
Table 17: Summary of participant demographics for clinical trials in adults with relapsed or refractory multiple myeloma who have received one to three prior lines of therapy, including a proteasome inhibitor and lenalidomide, and who are not refractory to a prior anti-CD38 monoclonal antibody
Study # Trial design | Dosage, route of administration and duration | Study subjects (n) | Median age (range) | Sex |
Study MMY3001 (MajesTEC-3) Phase 3, open-label, randomized, multicenter study in adults with relapsed or refractory multiple myeloma, who had previously received one to three prior lines of therapy including a proteasome inhibitor (PI) and lenalidomide, and who are not refractory to a prior anti-CD38 monoclonal antibody. | Initial step-up doses of 0.06 mg/kg and 0.3 mg/kg of TECVAYLI administered subcutaneously followed by the treatment dose of 1.5 mg/kg administered subcutaneously once weekly through Week 8, then 3 mg/kg once every two weeks through Week 24, and then 3 mg/kg once every four weeks until disease progression or unacceptable toxicity Daratumumab subcutaneous 1800 mg weekly in Week 1 to Week 8, then 1800 mg once every two weeks through Week 24, and then once very four weeks until disease progression or unacceptable toxicity. | N=587 TECVAYLI-Dara arm: 291 DPd or DVd arm: 296 | 64 years (range: 25-88 years) | 55% male, 45% female |
See Table 17 for a summary of study design and dosing.
The efficacy and safety of TECVAYLI in combination with daratumumab (TECVAYLI-Dara) versus the control arm of either daratumumab, pomalidomide and dexamethasone (DPd) or daratumumab, bortezomib and dexamethasone (DVd) in adults with relapsed or refractory multiple myeloma, was evaluated in a randomized, open-label, multi- regional study Phase 3 study (MajesTEC-3). The study included participants who had previously received one to three prior lines of therapy including a proteasome inhibitor (PI) and lenalidomide. Participants who had received only one prior line of therapy must have been refractory to lenalidomide. Individuals with multiple myeloma who had disease refractory to a prior anti-CD38 monoclonal antibody therapy, or who had received any prior BCMA-directed therapy, were excluded from participating in the clinical study.
- participants were randomized: 291 to the TECVAYLI-Dara arm and 296 to the control arm. Randomization was stratified by investigator’s choice of DPd or DVd, stage of disease at screening per International Staging System (ISS) (I vs II vs III), prior anti-CD38 monoclonal antibody exposure (yes vs no), and number of prior lines of therapy (1 vs 2 or 3). The baseline disease characteristics were similar between the TECVAYLI-Dara arm and the control arm. The median age was 64 (range: 25 to 88) years with 10% aged ≥75 years; 55% were male, 65% were White, 6% were Black or African American, and 22% were Asian. The ISS was 62.5% in Stage I, 29.5% in Stage II, and 8.0% in Stage III. High-risk cytogenetics (presence of del(17p). t(4;14) or t(14; 16)) were present in 35.9% of participants. Additionally, 14% of participants had soft tissue plasmacytomas.
The median number of prior lines of therapy was 2 (range: 1 to 3), with 37.8% of participants who received one prior line of the therapy. All participants were previously exposed to lenalidomide and a PI. There is limited data with TECVAYLI in combination with daratumumab in individuals who have received prior anti-CD38 monoclonal antibody therapy; five percent of participants in the Phase III study had received a prior anti-CD38 monoclonal antibody. Additionally, 85.3% of participants were refractory to their last line of therapy and 31.9% were double-class refractory (refractory to a PI, and an IMiD).
Study Results
With a median follow-up of 34.5 months in the Intent to treat (ITT) population in the MajesTEC-3 study, a statistically significant improvement in the primary efficacy outcome of progression free survival (PFS) and the secondary efficacy outcome of overall survival (OS) was established for the combination of TECVAYLI and daratumumab over the control treatment of DPd/DVd. The results are presented in Table 18 and Figure 1 and Figure 2, along with other key efficacy outcome measures included as part of the statistical hierarchical plan.
Subgroup analyses based on PFS hazard ratio were consistent across the pre-specified subgroups and showed improvement for participants in the TECVAYLI and daratumumab group versus participants in the DPd/DVd group.
Table 18: Efficacy results for MajesTEC-3
| TECVAYLI and Daratumumab Combination (N=291) | DPd/DVd (N=296) | |||||||||||
| Progression-free survival (PFS)a | ||||||||||||
| Number of events, n (%) | 44 (15.1) | 187 (63.2) | ||||||||||
| Median, months (95% CI) | NR (NE, NE) | 18.10 (14.6, 22.8) | ||||||||||
| Hazard ratio (95% CI)b ; p-valuec | 0.17 (0.12, 0.23); <0.0001 | |||||||||||
| Complete response or better (sCR+CR)a, n (%) | 238 (81.8) | 95 (32.1) | ||||||||||
| 95% CI (%) | (76.9, 86.0) | (26.8, 37.7) | ||||||||||
| Risk Differenced (95% CI)e; p-valuef | 49.6 (42.8, 56.6); <0.0001 | |||||||||||
| Overall response (sCR+CR+VGPR+PR)a, n (%) | 259 (89.0) | 223 (75.3) | ||||||||||
| 95% CI (%) | (84.8, 92.4) | (70.0, 80.1) | ||||||||||
| Risk Differenced (95% CI)e; p-valuef | 13.6 (7.6, 19.8); <0.0001 | |||||||||||
| Stringent complete response (sCR), n (%) | 225 (77.3) | 69 (23.3) | ||||||||||
| Complete response (CR), n (%) | 13 (4.5) | 26 (8.8) | ||||||||||
| Very good partial response (VGPR), n (%) | 14 (4.8) | 74 (25.0) | ||||||||||
| Partial response (PR), n (%) | 7 (2.4) | 54 (18.2) | ||||||||||
| MRD negativityg,h, n/N (%) | 153/262 (58.4) | 46/269 (17.1) | ||||||||||
| 95% CI (%) | (52.2, 64.4) | (12.8, 22.1) | ||||||||||
| Risk Differenced (95% CI)e; p-valuei | 41.4 (33.8, 48.8); <0.0001 | |||||||||||
| Overall survival (OS)a | ||||||||||||
| Number of events, n (%) | 46 (15.8) | 98 (33.1) | ||||||||||
| Median, months (95% CI) | NR (NE, NE) | NR (41.40, NE) | ||||||||||
| Hazard ratio (95% CI)b; p-valuec | 0.46 (0.32, 0.65); <0.0001 | |||||||||||
CI=confidence interval; NE=not estimable; NR=not reached; MRD = minimal residual disease; Control arm= DPd or DVd
Median duration of follow-up = 34.5 months
a Based on intent-to-treat analysis set
b Stratified Cox proportional hazard model. For all stratified analyses, stratification was based on ISS staging (I vs. II or III) and number of prior lines (1 vs. 2 or 3), as randomized
c Stratified log-rank test
d Mantel-Haenszel estimate of the risk difference for stratified tables is used. A risk difference > 0 indicates an advantage for the combination of TECVAYLI and daratumumab.
e Unstratified Miettinen-Nurminen 95% confidence interval.
f Cochran Mantel-Haenszel Chi-Squared test
g Based on MRD next-generation sequencing (NGS) primary analysis set, defined as all randomized participants in the study except for those recruited in China.
h Based on a threshold of 10-5 using a next generation sequencing assay (clonoSEQ).
i Fisher’s exact test.
Figure 1: Kaplan-Meier Curve of Progression Free Survival in MajesTEC-3
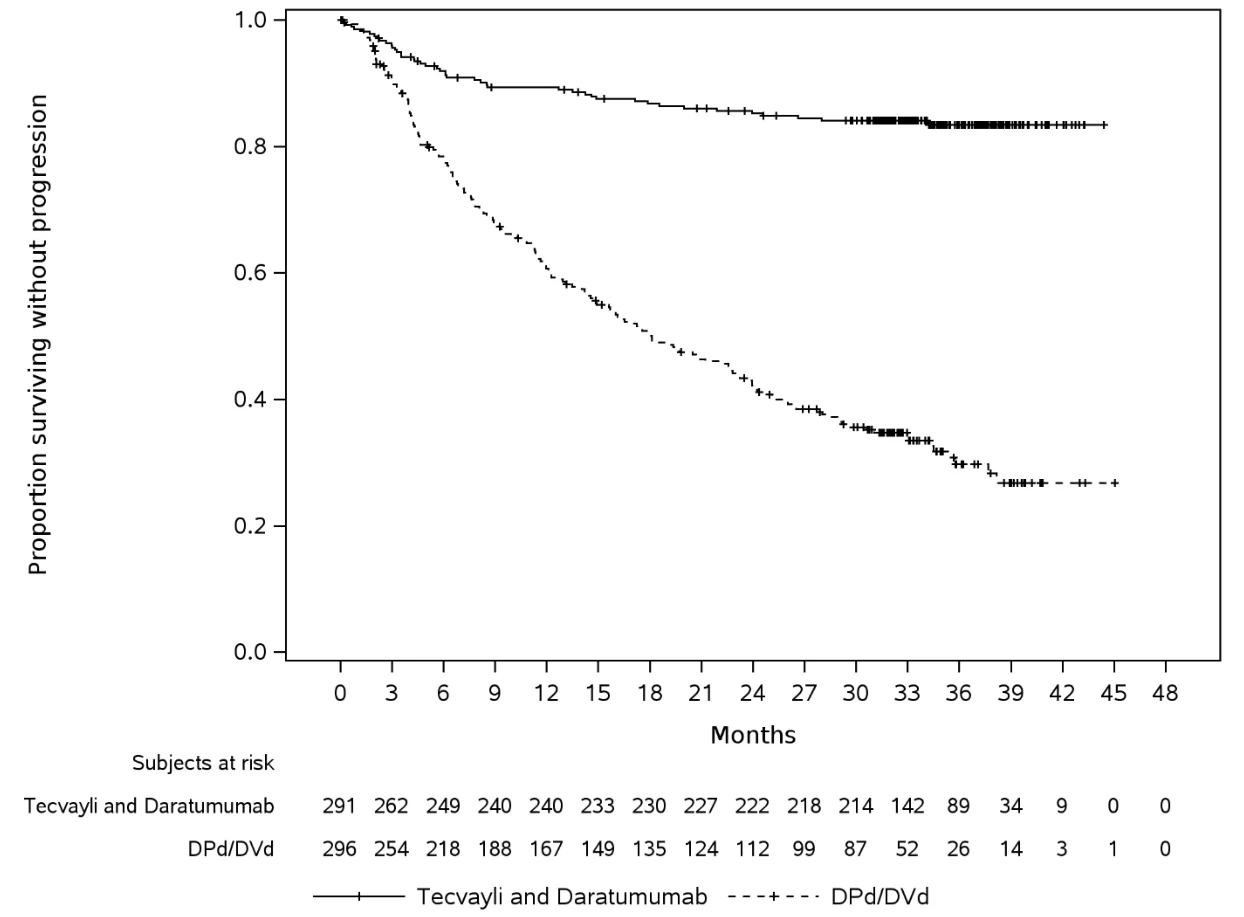
Key: DVd = daratumumab-bortezomib-dexamethasone; DPd = daratumumab-pomalidomide-dexamethasone
Figure 2: Kaplan-Meier Curve of Overall Survival in MajesTEC-3
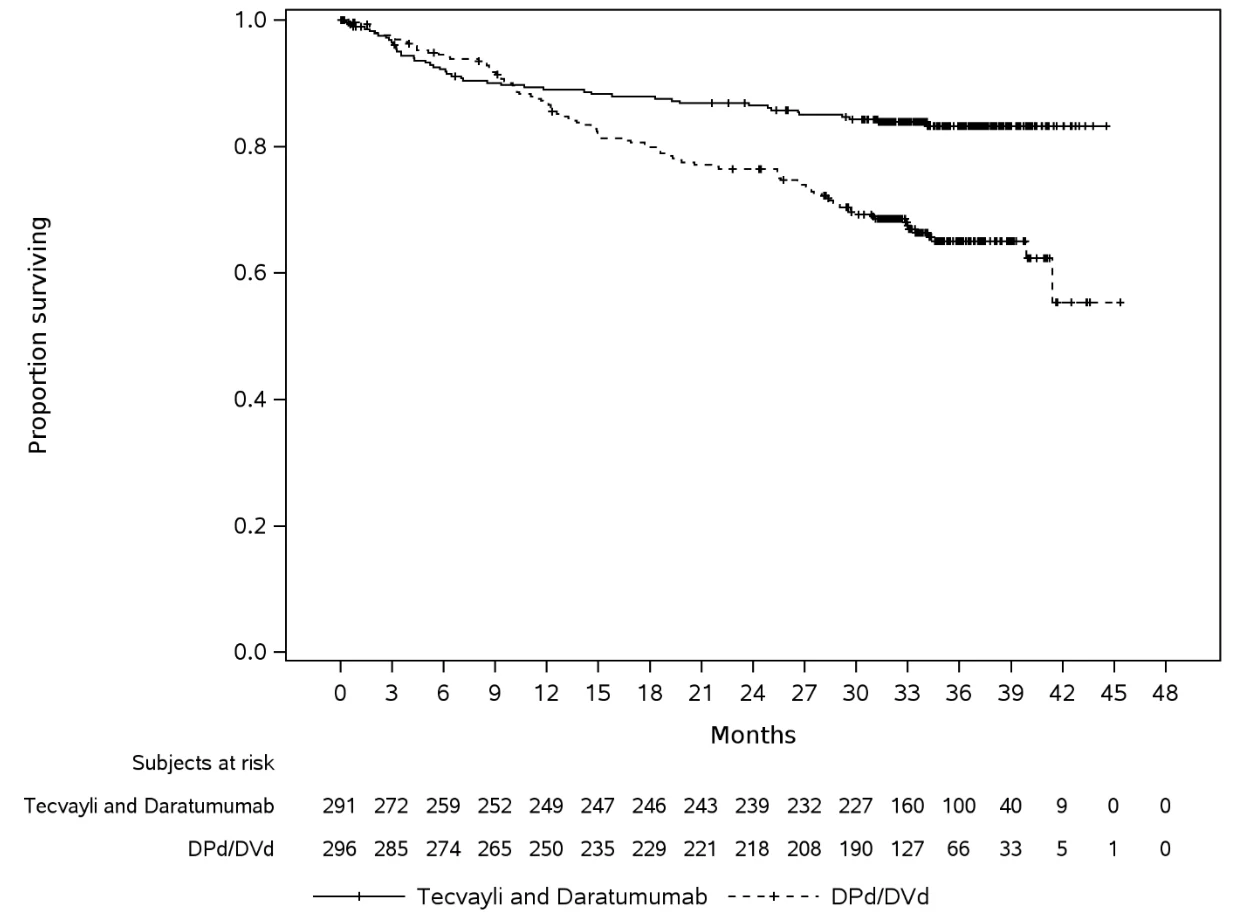
Key: DVd = daratumumab-bortezomib-dexamethasone; DPd = daratumumab-pomalidomide-dexamethasone
Multiple Myeloma after Three or More Prior Lines of Therapy
Table 19: Summary of participants demographics for clinical trials in adults with relapsed or refractory multiple myeloma who have received at least three prior lines of therapy, including a proteasome inhibitor, an immunomodulatory agent and an anti-CD38 monoclonal antibody.
Study # Trial design | Dosage, route of administration and duration | Study subjects (n) | Median age (range) | Sex |
Study MMY1001 (MajesTEC-1) Phase 1/2, open-label, multicenter study to evaluate the safety and efficacy of teclistamab in adults with relapsed or refractory multiple myeloma, including those who have received at least three prior lines of therapy, including a proteasome inhibitor, an immunomodulatory agent and an anti-CD38 monoclonal antibody | Initial step-up doses of 0.06 mg/kg and 0.3 mg/kg of TECVAYLI administered subcutaneously followed by the treatment dose of 1.5 mg/kg administered subcutaneously once weekly until disease progression or unacceptable toxicity Participants who had a complete response or better for a minimum of 6 months were eligible to reduce dosing frequency to once every two weeks | Efficacy population treated at the pivotal dose in Phase 2 (n = 110) | 66.0 years (range: 33-82 years) | 56% male, 44% female |
See Table 19 for a summary of study design and dosing.
MajesTEC-1 is a single-arm, open-label, multicenter, study that included adults with relapsed or refractory multiple myeloma. The study included participants who had received at least three prior therapies, including a proteasome inhibitor (PI), an immunomodulatory agent (IMiD) and an anti-CD38 monoclonal antibody. The study excluded individuals who had stroke, seizure, allogeneic stem cell transplant within the past 6 months, Eastern Cooperative Oncology Group (ECOG) performance status score 2 or higher, known central nervous system (CNS) involvement or clinical signs of meningeal involvement of multiple myeloma, and active or documented history of autoimmune disease (with the exception of vitiligo, Type 1 diabetes and prior autoimmune thyroiditis).
Participants received initial step-up doses of 0.06 mg/kg and 0.3 mg/kg of TECVAYLI administered subcutaneously, followed by the treatment dose of 1.5 mg/kg administered subcutaneously once weekly thereafter until disease progression or unacceptable toxicity (see 4.2. Recommended Dose and Dosage Adjustment).
Participants who had a complete response (CR) or better for a minimum of 6 months were eligible to reduce dosing frequency to 1.5 mg/kg subcutaneously every two weeks until disease progression or unacceptable toxicity (see 4.2. Recommended Dose and Dosage Adjustment).
The median duration between Step-up Dose 1 and Step-up Dose 2 was 2.9 (range: 2-7) days. The median duration between Step-up Dose 2 and the initial treatment dose was 3.9 (range: 2-9) days. Participants were hospitalized for monitoring for at least 48 hours after administration of each dose of the TECVAYLI step-up dosing schedule.
The efficacy population treated at the pivotal dose in Phase 2 included 110 participants. The median age was 66.0 (range: 33-82) years with: 16% of participants ≥ 75 years of age; 56% were male; 91% were White; 5% were Black; and 3% were Asian. The International Staging System (ISS) at study entry was 51% in Stage I, 38% in Stage II, and 12% in Stage III. High-risk cytogenetics (presence of del(17p). t(4;14) or t(14; 16)) were present in 25% of participants. Seventeen percent of participants had extramedullary plasmacytomas.
The median time since initial diagnosis of multiple myeloma to enrollment was 6.4 (range: 1.1-22.7) years. The median number of prior therapies was 5 (range: 2-14) with 20% of participants who received 3 prior lines of therapy. Eighty-one percent of participants received prior stem cell transplantation. All participants had received prior therapy with a proteasome inhibitor, an immunomodulatory agent and an anti-CD38 monoclonal antibody, and 76% were triple-class refractory (refractory to a PI, an IMiD and an anti-CD38 monoclonal antibody). Nine-two percent of participants were refractory to the last prior line of myeloma therapy.
Study Results
Efficacy results were based on overall response rate as determined by the Independent Review Committee (IRC) assessment using International Myeloma Working Group (IMWG) 2016 criteria (see Table 20).
Table 20: Efficacy results of study MajesTEC-1 in adults with relapsed or refractory multiple myeloma who have received at least three prior lines of therapy, including a proteasome inhibitor, an immunomodulatory agent and an anti-CD38 monoclonal antibody.
| N=110a | |
| Overall response rate (ORR: sCR+CR+VGPR+PR) n(%) | 68 (61.8%) |
| 95% CI (%) | (52.1%, 70.9%) |
| Stringent complete response (sCR) | 25 (22.7%) |
| Complete response (CR) | 6 (5.5%) |
| Very good partial response (VGPR) | 32 (29.1%) |
| Partial response (PR) | 5 (4.5%) |
Number of responders Duration of Response (Months): Median (95% CI) | 68 NE (9.0, NE) |
CI = confidence interval; NE = not estimable
a Efficacy population treated at the pivotal dose in Phase 2 with had a median duration of follow-up at the primary analysis: 8.8 months.
The median time to first response was 1.2 months (range 0.2 - 5.5 months) for responders treated at the pivotal dose in Phase 2 of the MajesTEC-1 study (N=68).
After a median follow-up of 29.5 months, the ORR was 62.4% (95% CI: 53.3%, 70.9%) for participants treated at the recommended dose in Phase 2 of MajesTEC-1 (N=125) with 36.8% of participants achieving sCR, 7.2% of participants achieving CR, 14.4% of participants achieving VGPR and 4.0% of participants achieving a PR. The median duration of response was 21.6 months (95% CI: 14.9 months, NE) for responders (N=78). Forty-three of the 78 responders (55.1%) switched from weekly to Q2W dosing during the study.
15. Microbiology
No microbiological information is required for this drug product.
16. Non-Clinical Toxicology
Carcinogenicity: No carcinogenicity studies have been performed to assess the carcinogenic potential of teclistamab.
Genotoxicity: No genotoxicity studies have been performed to assess the genotoxic potential of teclistamab.
Reproductive and Developmental Toxicology: No reproductive and developmental toxicity animal studies have been conducted to evaluate the potential effects of teclistamab.
No studies have been conducted to evaluate the effects of teclistamab on fertility in males or females. In the 5-week repeat-dose toxicity study in cynomolgus monkeys, there were no notable effects in the male and female reproductive organs at doses up to 30 mg/kg/week (approximately 22 times the maximum recommended human dose based on AUC exposure) intravenously for five weeks.