


Product Monograph - Columvi
Recent Major Label Changes
| 1 Indications | 2025-08 |
|---|---|
| 3 Serious Warnings and Precautions Box | 2026-07 |
| 4 Dosage and Administration, 4.1 Dosing Considerations | 2025-08 |
| 4 Dosage and Administration, 4.2 Recommended Dose and Dosage Adjustment | 2026-07 |
| 7 Warnings and Precautions, Driving and Operating Machinery | 2024-12 |
| 7 Warnings and Precautions, Immune | 2026-07 |
| 7 Warnings and Precautions, Neurologic | 2024-12 |
Table of Contents
Certain sections or subsections that are not applicable at the time of the preparation of the most recent authorized product monograph are not listed.
Recent Major Label Changes .................................................................................................... 2
Table of Contents .................................................................................................................... 2
Part 1: Health Professional Information ................................................................................... 4
1 Indications ................................................................................................................... 4
1.1 Pediatrics ............................................................................................................... 4
1.2 Geriatrics ............................................................................................................... 4
2 Contraindications ......................................................................................................... 4
3 Serious Warnings and Precautions Box ........................................................................ 4
4 Dosage and Administration .......................................................................................... 5
4.1 Dosing Considerations ........................................................................................... 5
4.2 Recommended Dose and Dosage Adjustment ...................................................... 6
4.3 Reconstitution ..................................................................................................... 12
4.4 Administration ..................................................................................................... 13
4.5 Missed Dose ........................................................................................................ 13
5 Overdose.................................................................................................................... 14
6 Dosage Forms, Strengths, Composition, and Packaging .............................................. 14
7 Warnings and Precautions .......................................................................................... 14
Driving and Operating Machinery ................................................................................... 14
Endocrine and Metabolism ............................................................................................. 15
Hepatic/Biliary/Pancreatic .............................................................................................. 15
Immune ........................................................................................................................... 15
Neurologic ....................................................................................................................... 17
Renal ............................................................................................................................... 18
Reproductive Health ....................................................................................................... 18
7.1 Special Populations .............................................................................................. 18
7.1.1 Pregnancy ........................................................................................................ 18
7.1.2 Breastfeeding .................................................................................................. 18
7.1.3 Pediatrics ......................................................................................................... 18
7.1.4 Geriatrics ......................................................................................................... 18
8 Adverse Reactions ...................................................................................................... 19
8.1 Adverse Reaction Overview ................................................................................. 19
8.2 Clinical Trial Adverse Reactions ........................................................................... 19
8.3 Less Common Clinical Trial Adverse Reactions .................................................... 27
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry, and Other Quantitative Data ............................................................................................................ 28
8.5 Post-Market Adverse Reactions .......................................................................... 30
9 Drug Interactions ....................................................................................................... 30
9.1 Drug Interactions Overview ................................................................................. 30
9.2 Drug-Behaviour Interactions ............................................................................... 30
9.3 Drug-Drug Interactions ........................................................................................ 30
9.4 Drug-Food Interactions ........................................................................................ 30
9.5 Drug-Herb Interactions ........................................................................................ 31
9.6 Drug-Laboratory Test Interactions ....................................................................... 31
10 Clinical Pharmacology ................................................................................................ 31
10.1 Mechanism of Action ........................................................................................... 31
10.2 Pharmacodynamics ............................................................................................. 31
10.3 Pharmacokinetics ................................................................................................ 31
10.4 Immunogenicity ................................................................................................... 34
11 Storage, Stability, and Disposal .................................................................................. 34
12 Special Handling Instructions ..................................................................................... 34
Part 2: Scientific Information ................................................................................................. 35
13 Pharmaceutical Information ....................................................................................... 35
14 Clinical Trials .............................................................................................................. 36
14.1 Clinical Trials by Indication .................................................................................. 36
Relapsed or Refractory DLBCL ......................................................................................... 36
14.2 Comparative Bioavailability Studies..................................................................... 42
15 Microbiology .............................................................................................................. 42
16 Non-Clinical Toxicology .............................................................................................. 42
Patient Medication Information ............................................................................................ 44
Part 1: Healthcare Professional Information
1 Indications
- COLUMVI (glofitamab for injection), as monotherapy, is indicated for the treatment of adult patients with relapsed or refractory diffuse large B-cell lymphoma (DLBCL) not otherwise specified, DLBCL arising from follicular lymphoma (trFL), or primary mediastinal B-cell lymphoma (PMBCL), who have received two or more lines of systemic therapy and are ineligible to receive or cannot receive CAR-T cell therapy or have previously received CAR-T cell therapy.
- COLUMVI, in combination with gemcitabine and oxaliplatin, is indicated for the treatment of adult patients with relapsed or refractory diffuse large B-cell lymphoma not otherwise specified (DLBCL NOS) who are not candidates for autologous stem cell transplant (ASCT).
1.1 Pediatrics
Pediatrics (< 18 years of age): Based on the data submitted and reviewed by Health Canada, the safety and efficacy of COLUMVI in pediatric patients has not been established; therefore, Health Canada has not authorized an indication for pediatric use (see 4.2 Recommended Dose and Dosage Adjustment; and 10.3 Pharmacokinetics, Special Populations and Conditions).
1.2 Geriatrics
Geriatrics (≥ 65 years of age): No differences in the safety or efficacy of COLUMVI were observed between patients ≥ 65 years of age and those under 65 years (see 7 Warnings and Precautions, 7.1.4 Geriatrics; and 10.3 Pharmacokinetics, Special Populations and Conditions).
2 Contraindications
COLUMVI is contraindicated in patients who are hypersensitive to this drug or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see 6 Dosage Forms, Strengths, Composition, and Packaging
- .
3 Serious Warnings and Precautions Box
|
|---|
|
4 Dosage and Administration
4.1 Dosing Considerations
COLUMVI therapy should only be administered under the supervision of a healthcare professional experienced in the treatment of cancer patients and who has access to appropriate medical support to manage severe reactions associated with cytokine release syndrome (CRS). At least 1 dose of tocilizumab, for use in the event of CRS, must be available prior to COLUMVI infusion at Cycles 1 and 2. Access to an additional dose of tocilizumab within 8 hours of use of the previous tocilizumab dose must be ensured (see 7 Warnings and Precautions).
COLUMVI must not be administered to patients with an active infection.
For information on dosing and timing of tocilizumab administration, refer to Table 4.
Pre-treatment with Obinutuzumab
All patients must receive a single 1 000 mg dose of obinutuzumab on Cycle 1 Day 1 (7 days prior to initiation of COLUMVI treatment); see Table 2, Table 3 and 4.5 Missed Dose. The purpose of obinutuzumab pre-treatment is to deplete circulating and lymphoid tissue B cells and minimize the risk of CRS.
Obinutuzumab should be administered as an intravenous infusion at 50 mg/h. The rate of infusion can be escalated in 50 mg/h increments every 30 minutes to a maximum of 400 mg/h.
Refer to the obinutuzumab Product Monograph for complete information on premedication, preparation, administration, warnings and precautions, and management of adverse reactions of obinutuzumab.
Premedication and Prophylactic Medications
Cytokine release syndrome prophylaxis
COLUMVI should be administered to well-hydrated patients. Premedication, to reduce the risk of CRS, (see 7 Warnings and Precautions) should be administered according to the guidance in Table 1.
Table 1 Premedication before COLUMVI Infusion to Reduce the Risk of Cytokine Release Syndrome
| Treatment Cycle (Day) | Patients requiring premedication | Premedication | Administration |
Cycle 1 (Day 8, Day 15); Cycle 2 (Day 1); Cycle 3 (Day 1) | All patients | 20 mg intravenous dexamethasone a | Completed at least 1 hour prior to COLUMVI infusion. |
| Oral analgesic / anti-pyreticb | At least 30 minutes before COLUMVI infusion. | ||
| Anti-histaminec | |||
| All subsequent infusions | All patients | Oral analgesic / anti-pyreticb | At least 30 minutes before COLUMVI infusion. |
| Anti-histaminec | |||
| Patients who experienced CRS with previous dose | 20 mg intravenous dexamethasone a | Completed at least 1 hour prior to COLUMVI infusion. | |
a If patient has an intolerance to dexamethasone or dexamethasone is unavailable, administer 100 mg prednisone/prednisolone or 80 mg methylprednisolone.
b For example, 1 000 mg acetaminophen.
c For example, 50 mg diphenhydramine.
Infection prophylaxis
Prophylaxis is recommended to reduce the risk of infection (see 7 Warnings and Precautions).
Consider prophylaxis for cytomegalovirus (CMV), herpes, pneumocystis jirovecii pneumonia, and other opportunistic infections in patients at increased risk (see 8.2 Clinical Trial Adverse Reactions, Description of selected adverse reactions).
4.2 Recommended Dose and Dosage Adjustment
COLUMVI dosing begins with a step-up dosing schedule to minimize the risk of CRS. The recommended dose after step-up is 30 mg.
COLUMVI Monotherapy Dose Step-up Schedule
Seven days after obinutuzumab pre-treatment (i.e., on Day 8), COLUMVI 2.5 mg is administered as an intravenous infusion. Subsequent doses are administered according to the step-up schedule, shown in Table 2, leading to the recommended dose of 30 mg. Each treatment cycle is 21 days.
Table 2 COLUMVI Monotherapy Dose Step-Up Schedule for Patients with Relapsed or Refractory DLBCL
| Treatment Cycle, Daya | Dose of COLUMVI | Duration of infusion |
Cycle 1 (Pre-treatment and step-up dose) | Day 1 | Pre-treatment with obinutuzumab 1 000 mgb |
| Day 8 | 2.5 mg | 4 hoursc |
| Day 15 | 10 mg | |
| Cycle 2 | Day 1 | 30 mg |
| Cycle 3 to 12 | ||
| Day 1 | 30 mg | 2 hoursd |
a Each treatment cycle is 21 days b Refer to Pre-treatment with obinutuzumab described above. c For patients who experience CRS with their previous dose of COLUMVI, the duration of infusion may be extended up to 8 hours (see Table 4 and Section 7 Warnings and Precautions). d At the discretion of the treating physician, if the previous infusion was well tolerated. If the patient experienced CRS with the previous dose, the duration of infusion should be maintained at 4 hours. | ||
COLUMVI Dose Step-up Schedule in Combination with Gemcitabine and Oxaliplatin
COLUMVI must be administered as an intravenous infusion according to the dose step-up schedule leading to the recommended dosage of 30 mg (as shown in Table 3), after completion of pre-treatment with obinutuzumab on Cycle 1 Day 1. Administer COLUMVI in combination with gemcitabine and oxaliplatin at Cycles 1-8 and as monotherapy at Cycles 9-12. Each cycle is 21 days.
The product monographs of the drugs used in combination with COLUMVI should be consulted before starting treatment.
Table 3 COLUMVI Dose Step-Up Schedule when administered in Combination with Gemcitabine and Oxaliplatin for Patients with Relapsed or Refractory DLBCL
| Treatment Cycle, Daya | Dose of COLUMVI (duration of infusion) | Dose of gemcitabine* | Dose of oxaliplatin* | |||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|
Cycle 1 (pre-treatment and step-up dose) | Day 1 | Pre-treatment with obinutuzumab 1 000 mgb | ||||||||||
| Day 2 | -- | 1 000 mg/m2 c | 100 mg/m2 c | |||||||||
| Day 8 | 2.5 mg (4 hours)d | -- | -- | |||||||||
| Day 15 | 10 mg (4 hours)d | -- | -- | |||||||||
| Cycle 2 | Day 1 | 30 mg (4 hours)d,e | 1 000 mg/m2 e | 100 mg/m2 e | ||||||||
| Cycle 3 to 8 | Day 1 | 30 mg (2 hours)e,f | 1 000 mg/m2 e | 100 mg/m2 e | ||||||||
| Cycle 9 to 12 | Day 1 | 30 mg (2 hours)e,f | N/A | N/A | ||||||||
N/A=not applicable.
a Each treatment cycle is 21 days.
b Refer to Pre-treatment with obinutuzumab described above.
c Cycles 1-8: administer gemcitabine before oxaliplatin.
d For patients who experience CRS with their previous dose of COLUMVI, the duration of infusion may be extended up to 8 hours (see Table 4 and Warnings and Precautions).
e Cycles 2-8: administer COLUMVI before gemcitabine, and oxaliplatin. Gemcitabine and oxaliplatin may be given on Day 1 or 2.
f Infusion time may be shortened to 2 hours at the discretion of the treating physician, if the previous infusion was well tolerated. If the patient experienced CRS with the previous dose, the duration of infusion should be maintained at 4 hours.
* Note: Dosing is based on the dosing used in Study GO41944. See 14 Clinical Trials.
Monitoring after infusion
- Patients must be monitored for signs and symptoms of potential CRS during infusion and for at least 10 hours after completion of the infusion of the first COLUMVI dose (2.5 mg on Cycle 1 Day 8).
- Patients who experienced Grade ≥ 2 CRS with their previous infusion should be monitored after completion of the infusion. See Table 4.
All patients must be monitored for signs and symptoms of CRS and/or neurologic toxicity, including immune effector cell-associated neurotoxicity syndrome (ICANS), following COLUMVI administration. Counsel patients on the risk, signs, and symptoms associated with CRS and/or neurologic toxicity, including ICANS, and on seeking immediate medical attention should signs and symptoms of CRS and/or neurologic toxicity, including ICANS, occur at any time.
Pediatric Use: Health Canada has not authorized an indication for pediatric use (see Indications, 1.1 Pediatrics).
Duration of Treatment
Treatment with COLUMVI monotherapy is recommended for a fixed duration of treatment for a maximum of 12 cycles or until disease progression or unmanageable toxicity, whichever occurs first.
Treatment with COLUMVI in combination with gemcitabine and oxaliplatin is recommended for a fixed duration of treatment of 8 cycles, followed by 4 cycles of COLUMVI monotherapy for a maximum of 12 cycles of COLUMVI in total or until disease progression or unmanageable toxicity, whichever occurs first.
Dose Modifications
No dose reductions of COLUMVI are recommended.
Management of Cytokine Release Syndrome
Cytokine release syndrome should be identified based on the clinical presentation (see
7 Warnings and Precautions). Patients should be evaluated for other causes of fever, hypoxia, and hypotension, such as infections or sepsis. If CRS is suspected, management should follow institutional guidelines based on American Society for Transplantation and Cellular Therapy [ASTCT] consensus grading, with consideration given to current consensus recommendations on management of CRS and the guidance outlined in Table 4. If CRS is refractory to management, consider other causes including hemophagocytic lymphohistiocytosis (HLH) and immune effector cell associated hemophagocytic lymphohistiocytosis-like syndrome (IEC-HS).
Table 4 ASTCT CRS Grading and CRS Management Guidancee
| Gradea | CRS Management | For Next Scheduled COLUMVI Infusion |
|---|---|---|
| Gradea | CRS Management | For Next Scheduled COLUMVI Infusion |
Grade 1 Fever ≥ 38°C | If CRS occurs during infusion:
If CRS occurs post-infusion:
If CRS lasts more than 48 h after symptomatic management:
|
|
Grade 2 Fever ≥ 38°C and/or hypotension not requiring vasopressors and/or hypoxia requiring low-flow oxygen by nasal cannula or blow-by | If CRS occurs during infusion:
If CRS occurs post-infusion:
|
|
For Grade 2: Tocilizumab use Do not exceed 3 doses of tocilizumabd in a period of 6 weeks. If no prior use of tocilizumab or if 1 dose of tocilizumab was used within the last 6 weeks:
If 2 doses of tocilizumab were used within the last 6 weeks:
| ||
Grade 3 Fever ≥ 38°C and/or hypotension requiring a vasopressor (with or without vasopressin) and/or hypoxia requiring high-flow oxygen by nasal cannula, face mask, non-rebreather mask, or Venturi mask | If CRS occurs during infusion:
If CRS occurs post-infusion:
|
|
Grade 4 Fever ≥ 38°C and/or hypotension requiring multiple vasopressors (excluding vasopressin) and/or hypoxia requiring oxygen by positive pressure (e.g., CPAP, BiPAP, intubation, and mechanical ventilation) | If CRS occurs during infusion or post-infusion:
| |
For Grade 3 and Grade 4: Tocilizumab use Do not exceed 3 doses of tocilizumabd in a period of 6 weeks. If no prior use of tocilizumab or if 1 dose of tocilizumab was used within the last 6 weeks:
If 2 doses of tocilizumab were used within the last 6 weeks:
| ||
a American Society for Transplantation and Cellular Therapy (ASTCT) consensus grading criteria. b Duration of infusion may be extended up to 8 hours (up to 50% slower infusion), as appropriate for that cycle (see Table 2). c Corticosteroids (e.g., 10 mg IV dexamethasone, 100 mg IV prednisolone, 1-2 mg/kg IV methylprednisolone per day, or equivalent). d Tocilizumab 8 mg/kg IV (not to exceed 800 mg). e The recommendations describe the CRS management in Study NP30179. Treat CRS per institutional guidelines. f See 8.2 Clinical Trial Adverse Reactions, for frequency and time to onset of Grade ≥ 2 CRS following COLUMVI 10 mg and 30 mg doses. | ||
Management of Neurologic Toxicity Including Immune Effector Cell-Associated Neurotoxicity Syndrome (ICANS)
Neurologic toxicity including ICANS should be identified based on the clinical presentation (see Section 7 Warnings and Precautions). At the first sign of neurologic toxicity, including ICANS, based on the type and severity of neurologic toxicity consider supportive therapy, neurology evaluation, and withholding COLUMVI per Table 5. Rule out other causes of neurologic symptoms. If ICANS is suspected, manage according to consensus recommendations and/or current institutional guidelines.
Table 5 Recommended Dosage Modification for Neurologic Toxicitya Including ICANSb
| Adverse Reaction | Severitya,b | Actions |
|---|---|---|
| Neurologic Toxicitya including ICANSbe | Grade 1 |
|
| Grade 2 |
| |
| Grade 3 |
| |
| Grade 4 |
|
a Neurologic toxicity grading per National Cancer Institute Common Terminology Criteria for Adverse Events (NCI CTCAE), version 4.03. The recommendations describe the neurologic toxicity management in Study NP30179 and GO41944. Treat ICANS per institutional guidelines.
b American Society for Transplantation and Cellular Therapy (ASTCT) 2019 grading for ICANS.
c Consider the type of neurologic toxicity before deciding to withhold COLUMVI.
d See 4.5 Missed Dose for guidance on restarting COLUMVI after dose delay.
e Evaluate benefit/risk before restarting COLUMVI.
Progressive Multifocal Leukoencephalopathy (PML)
If neurological symptoms suggestive of PML (all grades) occur during COLUMVI therapy, it should be withheld and appropriate diagnostic measures initiated. Discontinue COLUMVI if PML is confirmed (see 7 Warnings and Precautions, Serious Infections).
4.3 Reconstitution
Instructions for dilutions
- COLUMVI contains no preservative and is intended for single use only.
- COLUMVI must be diluted by a healthcare professional using aseptic technique, prior to intravenous administration.
- Visually inspect the COLUMVI vial for particulate matter or discolouration prior to administration. COLUMVI is a colourless, clear solution. Do not use COLUMVI if the solution is cloudy, discoloured, or contains visible particles.
- Withdraw and discard the required volume of 0.9% or 0.45% sodium chloride solution from the appropriately sized infusion bag (see Table 6) using a sterile needle and syringe.
- Withdraw the required volume of COLUMVI concentrate for the intended dose from the vial using a sterile needle and syringe and dilute into the infusion bag (see Table 6). Discard any unused portion left in the vial.
- The final drug concentration after dilution must be 0.1 mg/mL to 0.6 mg/mL.
- Gently invert the infusion bag to mix the solution in order to avoid excessive foaming. Do not shake.
- Inspect the infusion bag for particulates and discard if present.
- Prior to the start of the intravenous infusion, the content of the infusion bag should be brought to room temperature without exceeding 4 hours of hold time outside refrigerated conditions (see Section 11 Storage, Stability, and Disposal).
Table 6 Dilution of COLUMVI for Infusion
Vial Size (concentration) | Dose of COLUMVI to be administered | Number of vials to achieve required dose | Size of 0.9% or 0.45% sodium chloride solution infusion bag | Volume of 0.9% or 0.45% sodium chloride solution to be withdrawn and discarded | Volume of COLUMVI concentrate to be added |
2.5 mg/2.5 mL (1 mg/mL) | 2.5 mg | 1 | 50 mL | 27.5 mL | 2.5 mL |
| 1 | 100 mL | 77.5 mL | 2.5 mL | ||
10 mg/10 mL (1 mg/mL) | 10 mg | 1 | 50 mL | 10 mL | 10 mL |
| 1 | 100 mL | 10 mL | 10 mL | ||
10 mg/10 mL (1 mg/mL) | 30 mg | 3 | 50 mL | 30 mL | 30 mL |
| 3 | 100 mL | 30 mL | 30 mL |
Incompatibilities
Only 0.9% or 0.45% sodium chloride solution should be used to dilute COLUMVI, since other diluents have not been tested.
COLUMVI when diluted with 0.9% sodium chloride solution is compatible with intravenous infusion bags composed of polyvinyl chloride (PVC), polyethylene (PE), polypropylene (PP), or polyolefin. When diluted with 0.45% sodium chloride solution, COLUMVI is compatible with intravenous infusion bags composed of PVC.
No incompatibilities have been observed with infusion sets with product-contacting surfaces of polyurethane (PUR), PVC, or PE, and in-line filter membranes composed of polyethersulfone (PES) or polysulfone. The use of in-line filter membranes is optional.
4.4 Administration
- COLUMVI must be administered as an intravenous infusion through a dedicated infusion line, typically over a period of 2 hours to 4 hours (8 hours maximum).
- COLUMVI must not be administered as an intravenous push or bolus.
- COLUMVI must not be mixed with other drugs.
4.5 Missed Dose
During step-up dosing (weekly dosing):
- Following pre-treatment with obinutuzumab, if the COLUMVI 2.5 mg dose is delayed by more than 1 week, then repeat pre-treatment with obinutuzumab.
- Following COLUMVI 2.5 mg dose or 10 mg dose, if there is a COLUMVI treatment-free interval of 2 weeks to 6 weeks, then repeat the last tolerated COLUMVI dose and resume the planned step-up dosing.
- Following COLUMVI 2.5 mg dose or 10 mg dose, if there is a COLUMVI treatment-free interval of more than 6 weeks, then repeat pre-treatment with obinutuzumab and COLUMVI step-up dosing (see Cycle 1 in Table 2 and Table 3).
After Cycle 2 (30 mg dose):
- If there is a COLUMVI treatment-free interval of more than 6 weeks between cycles, then repeat pre-treatment with obinutuzumab and COLUMVI step-up dosing (see Cycle 1 in Table 2 and Table 3), and then resume the planned treatment cycle (30 mg dose).
5 Overdose
There is no experience with overdosage of COLUMVI in clinical trials.
| For the most recent information in the management of a suspected drug overdose, contact your regional poison control centre or Health Canada’s toll-free number, 1-844 POISON-X (1-844-764-7669). |
|---|
6 Dosage Forms, Strengths, Composition, and Packaging
To help ensure the traceability of biologic products, healthcare professionals should record the brand name, the non-proprietary (active ingredient) name, and other product-specific identifiers such as the Drug Identification Number (DIN) and the batch/lot number of the product supplied.
Table 7 Dosage Forms, Strengths, Composition and Packaging
Description
COLUMVI is a preservative-free, colourless, clear solution supplied in single-dose vials containing:
- 2.5 mg of glofitamab in 2.5 mL solution in a 6 mL single-use glass vial at a concentration of 1 mg/mL
- 10 mg of glofitamab in 10 mL solution in a 15 mL single-use glass vial at a concentration of 1 mg/mL
7 Warnings and Precautions
Driving and Operating Machinery
COLUMVI may have an influence on the ability to drive and use machines. Patients experiencing symptoms that might affect their ability to drive or use machines (e.g., symptoms of CRS, such as pyrexia, tachycardia, hypotension, chills, hypoxia and/or symptoms of neurologic toxicity including ICANS, such as somnolence, cognitive disorder, confusional state, delirium, disorientation) should be advised to refrain from driving and/or operating machinery until symptoms resolve.
| Route of Administration | Dosage Form/ Strength/Composition | Non-Medicinal Ingredients |
| Intravenous infusion | Concentrate for solution for infusion, 2.5 mg/2.5 mL vial and 10 mg/10 mL vial | L-histidine; L-histidine hydrochloride, monohydrate; L-methionine; polysorbate 20; D-sucrose; water for injection |
Endocrine and Metabolism
Tumour Lysis Syndrome
Tumour lysis syndrome (TLS) has been reported in patients receiving COLUMVI (see 8.2 Clinical Trial Adverse Reactions). Patients with high tumour burden, rapidly proliferative tumours, renal dysfunction, or dehydration are at greater risk of TLS.
Patients at risk should be monitored closely by appropriate clinical and laboratory tests for electrolyte status, hydration, and renal function. Appropriate prophylactic measures with anti-hyperuricemics (e.g., allopurinol or rasburicase) and adequate hydration should be considered prior to COLUMVI infusion.
Management of TLS may include aggressive hydration, correction of electrolyte abnormalities, anti-hyperuricemic therapy, and supportive care.
Hepatic/Biliary/Pancreatic
The safety and efficacy of COLUMVI in patients with moderate and severe hepatic impairment has not been studied (see 10.3 Pharmacokinetics, Special Populations and Conditions).
Immune
Cytokine Release Syndrome
CRS, including life-threatening reactions, has occurred in patients receiving COLUMVI.
The most common manifestations of CRS in relapsed or refractory DLBCL patients treated with COLUMVI monotherapy were pyrexia, tachycardia, hypotension, chills, and hypoxia. Infusion-related reactions may be clinically indistinguishable from manifestations of CRS and vice versa. Elevated liver function tests (AST and ALT ≥ 3x ULN and/or total bilirubin ≥ 2x ULN) concurrent with CRS have been reported after COLUMVI use. CRS events were most common following the first dose of COLUMVI, but were also frequently observed after the second and third doses (see 8.2 Clinical Trial Adverse Reactions).
To reduce the occurrence and/or severity of CRS, patients must be pre-treated with obinutuzumab, 7 days prior to initiation of COLUMVI, and should be premedicated with an anti-pyretic, anti-histamine, and a glucocorticoid (see 4.2 Recommended Dose and Dosage Adjustment, Management of Cytokine Release Syndrome).
In the event of CRS, treatment with supportive care, tocilizumab and/or corticosteroids should be instituted as indicated (see 4.2 Recommended Dose and Dosage Adjustment, Management of Cytokine Release Syndrome). At least 1 dose of tocilizumab, for use in the event of CRS, must be available prior to COLUMVI infusion at Cycles 1 and 2. In case CRS is not adequately controlled after 1 dose of tocilizumab, an additional dose of tocilizumab must be accessible for use within 8 hours of the first.
Patients must be monitored for signs and symptoms of potential CRS during COLUMVI infusion and for at least 10 hours after completion of the first COLUMVI dose (2.5 mg on Cycle 1 Day 8).
For complete information on monitoring, see 4.2 Recommended Dose and Dosage Adjustment. The healthcare professional must counsel patients to seek immediate medical attention should signs or symptoms of CRS occur at any time.
Patients should be evaluated for other causes of fever, hypoxia, and hypotension, such as infections or sepsis. CRS should be managed based on the patient’s clinical presentation and according to the CRS management guidance provided in Table 4 (see 4.2 Recommended Dose and Dosage Adjustment, Management of Cytokine Release Syndrome).
Hemophagocytic lymphohistiocytosis (HLH)/ Immune effector cell-associated HLH-like syndrome (IEC-HS)
Hemophagocytic lymphohistiocytosis/ IEC-HS, including fatal cases, have occurred in patients receiving COLUMVI. HLH/IEC-HS is a life-threatening syndrome, characterized by fever, elevated ferritin, hepato- and/or splenomegaly, cytopenias, elevated transaminases, elevated LDH, coagulation abnormalities, hypofibrinogenemia, renal insufficiency and pulmonary manifestations. HLH/IEC-HS should be considered when the presentation of CRS is atypical or prolonged. Patients should be monitored for clinical signs and symptoms of HLH/IEC-HS. For suspected HLH/IEC-HS, COLUMVI must be interrupted and treatment for HLH/IEC-HS initiated per current practice guidelines.
Infusion Related Reaction (IRR)
Infusion related reactions (IRRs) were reported with COLUMVI. IRRs may be clinically indistinguishable from manifestations of CRS. For all events with clinical presentation of IRR/CRS with onset during infusion or after from the end of COLUMVI infusion (e.g., fever, nausea, chills, headache, hypotension, hypoxia or organ toxicity), these events should be treated as signs or symptoms of CRS.
Serious Infections
Serious infections, including opportunistic infections, sometimes leading to death, have occurred in patients treated with COLUMVI (see 4.2 Recommended Dose and Dosage Adjustment).
COLUMVI must not be administered to patients with an active infection. Caution should be exercised when considering the use of COLUMVI in patients with a history of chronic or recurrent infection, those with underlying conditions that may predispose them to infections, or those who have had significant prior immunosuppressive treatment. Administer prophylactic antimicrobials, as appropriate. Patients should be monitored before and during COLUMVI treatment for the emergence of possible bacterial, fungal, and new or reactivated viral infections and treated appropriately.
COLUMVI should be temporarily withheld in the presence of an active infection until the infection has resolved. Patients should be instructed to seek medical advice if signs and symptoms suggestive of an infection occur.
Febrile neutropenia has been reported during treatment with COLUMVI. Patients with febrile neutropenia should be evaluated for infection and treated promptly.
Progressive multifocal leukoencephalopathy (PML), including fatal cases, has occurred in patients treated with COLUMVI. If neurological symptoms suggestive of PML occur during COLUMVI therapy, treatment with COLUMVI should be withheld and appropriate diagnostic measures initiated. Discontinue COLUMVI if PML is confirmed.
Tumour Flare
Tumour flare has been reported in patients receiving COLUMVI. Manifestations included localized pain and swelling at the sites of lymphoma lesions and tumour inflammation (see 8.2 Clinical Trial Adverse Reactions).
Consistent with the mechanism of action of COLUMVI, tumour flare is likely due to the influx of T cells into tumour sites following COLUMVI administration and may mimic progression of disease. Tumour flare does not imply treatment failure or represent tumour progression.
Specific risk factors for tumour flare have not been identified, however, there is a heightened risk of compromise and morbidity due to mass effect secondary to tumour flare in patients with bulky tumours located in close proximity to airways and/or a vital organ. Monitoring and evaluation of tumour flare at critical anatomical sites is recommended in patients treated with COLUMVI and managed as clinically indicated.
Immunisation
The safety of immunisation with live vaccines during or following COLUMVI therapy has not been studied. Immunisation with live vaccines is not recommended during COLUMVI therapy.
Neurologic
Neurological Adverse Events (NAEs) Including Immune Effector Cell-Associated Neurotoxicity Syndrome (ICANS)
Neurologic toxicity including ICANS has been reported in patients receiving COLUMVI, including serious and fatal reactions. Manifestations of ICANS included somnolence, cognitive disorder, confusional state, delirium, and disorientation. The majority of cases of ICANS occurred during Cycle 1 of COLUMVI treatment; however, some events occurred at later cycles (see 8.2 Clinical Trial Adverse Reactions).
Patients should be monitored for signs and symptoms of neurologic toxicity including ICANS following COLUMVI administration. The prescriber must counsel patients to seek immediate medical attention should signs or symptoms occur at any time.
At the first signs or symptoms of ICANS, manage according to the ICANS guidance provided in Table 5. Treatment with COLUMVI should be withheld or discontinued as recommended (see 4.2 Recommended Dose and Dosage Adjustment).
Renal
The safety and efficacy of COLUMVI in patients with severe renal impairment has not been studied (see 10.3 Pharmacokinetics, Special Populations and Conditions).
Reproductive Health
Contraception
Female patients of reproductive potential must use highly effective contraceptive methods during treatment and for at least 2 months following the last dose of COLUMVI (see 7.1.1 Pregnan).
Fertility
No fertility assessments in animals have been performed to evaluate the effect of COLUMVI.
7.1 Special Populations
7.1.1 Pregnancy
Female patients of reproductive potential must be advised to avoid pregnancy while receiving COLUMVI. There are no available data on the use of COLUMVI in pregnant women. COLUMVI is an immunoglobulin G (IgG). IgG is known to cross the placenta. Based on its mechanism of action, COLUMVI is likely to cause fetal B-cell depletion when administered to a pregnant woman. Female patients receiving COLUMVI should be advised of the potential harm to the fetus. Female patients should be advised to contact the treating physician, should pregnancy occur.
7.1.2 Breastfeeding
It is not known whether COLUMVI is excreted in human milk. No studies have been conducted to assess the impact of COLUMVI on milk production or its presence in human milk. Human IgG is known to be present in human milk. The potential for absorption of COLUMVI and the potential for adverse reactions in the nursing infant is unknown. Women should be advised to discontinue breastfeeding during treatment with COLUMVI and for 2 months after the last dose of COLUMVI.
7.1.3 Pediatrics
Pediatrics (<18 years of age): Based on the data submitted and reviewed by Health Canada, the safety and efficacy of COLUMVI in pediatric patients has not been established; therefore, Health Canada has not authorized an indication for pediatric use.
7.1.4 Geriatrics
No differences in safety or efficacy of COLUMVI were observed between patients ≥ 65 years of age and those under 65 years. No dose adjustment of COLUMVI is required in patients ≥ 65 years of age (see 10.3 Pharmacokinetics, Special Populations and Conditions).
8 Adverse Reactions
8.1 Adverse Reaction Overview
Study NP30179 – Third-Line Monotherapy
The adverse drug reactions described below were identified from 152 patients with relapsed or refractory DLBCL, who had received at least two prior lines of systemic therapy, including DLBCL NOS (73.0%), DLBCL arising from follicular lymphoma (18.4%), high-grade B-cell lymphoma (HGBCL) (4.6%), and PMBCL (3.9%), treated with COLUMVI monotherapy in Study NP30179, an open-label multicenter clinical trial. The most common serious adverse reactions (occurred in more than 5%) are Cytokine release syndrome and viral infections. All 152 patients received a single infusion of obinutuzumab 7 days prior to the first administration of glofitamab. Patients must have had an ECOG performance status of 0 or 1, and must not have had an ongoing infection or current or past CNS disease.
Study GO41944 (STARGLO) – Second-Line Combination Therapy
The safety of COLUMVI in combination with gemcitabine and oxaliplatin was evaluated in Study STARGLO, an open-label multicenter, randomized clinical trial in patients with relapsed or refractory diffuse large B-cell lymphoma not otherwise specified (DLBCL NOS) who had received at least one prior systemic treatment regimen. The adverse reactions described below and in
Table 9 were identified from 172 patients with relapsed or refractory DLBCL NOS who were administered at least one dose of COLUMVI.
The most common adverse reactions (≥ 20%) were thrombocytopenia, cytokine release syndrome, neutropenia, anaemia, nausea, peripheral neuropathy, diarrhoea, aspartate aminotransferase increase, alanine aminotransferase increased, rash, lymphopenia, pyrexia and vomiting.
The most common serious adverse reactions reported in ≥ 2% of patients were cytokine release syndrome (20.3%), pyrexia (6.4%), pneumonia (5.8%), COVID-19 (5.8%), thrombocytopenia (4.7%), respiratory tract infection (3.5%), sepsis (2.3%) febrile neutropenia (2.3%), and diarrhoea (2.3%).
Permanent discontinuation of COLUMVI due to an adverse reaction occurred in 20.9% of patients. The most common adverse reactions leading to permanent discontinuation of COLUMVI were COVID-19 (11.6%) and pneumonitis (1.2%).
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. Therefore, the frequencies of adverse reactions observed in the clinical trials may not reflect frequencies observed in clinical practice and should not be compared to frequencies reported in clinical trials of another drug.
Table 8 Adverse Drug Reactions Occurring in ≥ 5% of Patients with Relapsed or Refractory DLBCL Treated with COLUMVI Monotherapy in Study NP30179
System Organ Class (SOC) Adverse Drug Reaction | COLUMVI N=152 | |
|---|---|---|
System Organ Class (SOC) Adverse Drug Reaction | COLUMVI N=152 | |
All Grades n (%) | Grade 3−4 n (%) | |
All Grades n (%) | Grade 3−4 n (%) | |
| Blood and lymphatic system disorders | ||
| Neutropeniaa | 52 (34.2) | 36 (23.7) |
| Anaemiab | 43 (28.3) | 10 (6.6) |
| Thrombocytopeniac | 36 (23.7) | 9 (5.9) |
| Gastrointestinal disorders | ||
| Abdominal paind | 15 (9.9) | 0 |
| Constipation | 18 (11.8) | 0 |
| Diarrhoea | 15 (9.9) | 0 |
| Nausea | 14 (9.2) | 0 |
| General disorders and administration site conditions | ||
| Fatiguee | 27 (17.8) | 2 (1.3) |
| Pyrexia | 28 (18.4) | 0 |
| Oedemaf | 16 (10.5) | 1 (0.7) |
| Immune system disorders | ||
| Cytokine release syndromeg | 94 (61.8) | 6 (3.9) |
| Infections and infestations | ||
| Viral infectionsh | 16 (10.5) | 4 (2.6*) |
| Bacterial infectionsi | 14 (9.2) | 4 (2.6) |
| Upper respiratory tract infectionsj | 8 (5.3) | 0 |
| Investigations† | ||
| Alanine aminotransferase increased | 12 (7.9) | 4 (2.6) |
| Aspartate aminotransferase increased | 11 (7.2) | 4 (2.6) |
| Blood alkaline phosphatase increased | 11 (7.2) | 2 (1.3) |
| Gamma-glutamyltransferase increased | 9 (5.9) | 4 (2.6) |
| Metabolism and nutrition disorders | ||
| Hypophosphataemia | 27 (17.8) | 9 (5.9) |
| Hypomagnesaemia | 20 (13.2) | 0 |
| Hypocalcaemia | 19 (12.5) | 0 |
| Hypochloraemia | 9 (5.9) | 0 |
| Hypokalaemia | 16 (10.5) | 1 (0.7) |
| Hyponatraemia | 12 (7.9) | 1 (0.7) |
| Musculoskeletal and Connective Tissue Disorders SOC | ||
| Back Paink | 13 (8.6) | 2 (1.3) |
| Arthralgia | 9 (5.9) | 0 |
| Neoplasms benign, malignant and unspecified (incl cysts and polyps) | ||
| Tumour flare | 17 (11.2) | 4 (2.6) |
| Nervous system disorders | ||
| Headache | 14 (9.2) | 0 |
| Skin and subcutaneous tissue disorders | ||
| Rashl | 21 (13.8) | 2 (1.3) |
* Grade 5 reactions reported include sepsis (1.3%), COVID-19 pneumonia (2.0%), COVID-19 (0.7%) and delirium (0.7%). † The frequency of ADRs under Investigations are based on reported AEs by investigators and not based on evaluation of all reported laboratory results. a Includes neutropenia and neutrophil count decreased. b Includes anaemia, haemoglobin decreased, iron deficiency anaemia and anaemia of malignant disease. c Includes thrombocytopenia and platelet count decreased. d includes abdominal pain, abdominal discomfort and abdominal pain upper. e includes fatigue, asthenia and malaise. f includes oedema peripheral, oedema, localized oedema, face oedema, swelling, swelling face and peripheral swelling. g Based on ASTCT consensus grading. h Includes COVID-19, COVID-19 pneumonia, herpes zoster, ophthalmic herpes zoster, SARS-CoV-2 test positive and polymerase chain reaction positive. i Includes vascular device infection, bacterial infection, Campylobacter infection, biliary tract infection bacterial, urinary tract infection bacterial, Clostridium difficile infection, Escherichia infection, peritonitis, infection, localized infection, Clostridium difficile colitis and pneumococcal infection. j Includes upper respiratory tract infection, sinusitis, nasopharyngitis, chronic sinusitis, and rhinitis. k Includes back pain and spinal pain. l Includes rash, rash pruritic, rash maculo-papular, dermatitis, dermatitis acneiform, dermatitis exfoliative, erythema, and palmar erythema. | ||
Table 9 Adverse Drug Reactions Occurring in ≥ 5% of Patients with Relapsed or Refractory DLBCL Treated with COLUMVI in Combination with Gemcitabine and Oxaliplatin in Study STARGLO
| Adverse Reactions | COLUMVI+GemOx N=172 | R-GemOx N=88 | ||||||||||||||
| Adverse Reactions | COLUMVI+GemOx N=172 | R-GemOx N=88 | ||||||||||||||
All grades n (%) | Grade 3 to 4 n (%) | All grades n (%) | Grade 3 to 4 n (%) | |||||||||||||
All grades n (%) | Grade 3 to 4 n (%) | All grades n (%) | Grade 3 to 4 n (%) | |||||||||||||
| Blood and lymphatic system disorders | ||||||||||||||||
| Thrombocytopeniaa | 86 (50.0) | 46 (26.7) | 42 (47.7) | 15 (17.0) | ||||||||||||
| Neutropeniab | 76 (44.2) | 61 (35.5) | 27 (30.7) | 16 (18.2) | ||||||||||||
| Anaemia | 71 (41.3) | 29 (16.9) | 19 (21.6) | 8 (9.1) | ||||||||||||
| Lymphopeniac | 42 (24.4) | 21 (12.2) | 13 (14.8) | 3 (3.4) | ||||||||||||
| Gastrointestinal disorders | ||||||||||||||||
| Nausea | 71 (41.3) | 1 (0.6) | 35 (39.8) | 0 | ||||||||||||
| Diarrhoea | 60 (34.9) | 6 (3.5) | 24 (27.3) | 0 | ||||||||||||
| Vomiting | 41 (23.8) | 1 (0.6) | 19 (21.6) | 0 | ||||||||||||
| Abdominal paind | 32 (18.6) | 4 (2.3) | 4 (4.5) | 0 | ||||||||||||
| Constipation | 32 (18.6) | 0 | 14 (15.9) | 0 | ||||||||||||
| General disorders and administration site conditions | ||||||||||||||||
| Fatiguee | 62 (36.0) | 3 (1.7) | 26 (29.5) | 2 (2.3) | ||||||||||||
| Pyrexia | 42 (24.4) | 1 (0.6) | 5 (5.7) | 0 | ||||||||||||
| Immune system disorders | ||||||||||||||||
| Cytokine release syndrome | 76 (44.2) | 4 (2.3) | 0 | 0 | ||||||||||||
| Infections and infestations | ||||||||||||||||
| COVID-19f | 30 (17.4) | 6 (3.5) | 8 (9.1) | 2 (2.3) | ||||||||||||
| Respiratory infectionsg | 23 (13.4) | 3 (1.7) | 3 (3.4) | 1 (1.1) | ||||||||||||
| Pneumoniah | 22 (12.8) | 9 (5.2) | 5 (5.7) | 2 (2.3) | ||||||||||||
| Cytomegalovirus infectionsi | 11 (6.4) | 1 (0.6) | 1 (1.1) | 1 (1.1) | ||||||||||||
| Herpes viral infectionsj | 10 (5.8) | 1 (0.6) | 1 (1.1) | 1 (1.1) | ||||||||||||
| Sepsisk | 9 (5.2) | 6 (3.5) | 2 (2.3) | 1 (1.1) | ||||||||||||
| Investigations | ||||||||||||||||
| Aspartate aminotransferase increased | 59 (34.3) | 6 (3.5) | 17 (19.3) | 0 | ||||||||||||
| Alanine aminotransferase increased | 56 (32.6) | 5 (2.9) | 19 (21.6) | 3 (3.4) | ||||||||||||
| Blood alkaline phosphatase increased | 31 (18.0) | 1 (0.6) | 16 (18.2) | 0 | ||||||||||||
| Gamma-glutamyltransferase increasedl | 26 (15.1) | 4 (2.3) | 10 (11.4) | 2 (2.3) | ||||||||||||
| Blood lactate dehydrogenase increased | 20 (11.6) | 0 | 4 (4.5) | 0 | ||||||||||||
| Metabolism and nutrition disorders | ||||||||||||||||
| Hypokalaemia | 32 (18.6) | 5 (2.9) | 6 (6.8) | 1 (1.1) | ||||||||||||
| Hyponatraemia | 19 (11.0) | 1 (0.6) | 5 (5.7) | 0 | ||||||||||||
| Hypomagnesaemia | 13 (7.6) | 0 | 10 (11.4) | 1 (1.1) | ||||||||||||
| Hypocalcaemia | 11 (6.4) | 1 (0.6) | 5 (5.7) | 1 (1.1) | ||||||||||||
| Hypophosphataemia | 10 (5.8) | 3 (1.7) | 2 (2.3) | 0 | ||||||||||||
| Musculoskeletal and Connective Tissue Disorder | ||||||||||||||||
| Musculoskeletal painm | 32 (18.6) | 4 (2.3) | 17 (19) | 1 (1.1) | ||||||||||||
| Nervous system disorders | ||||||||||||||||
| Peripheral neuropathyn | 64 (37.2) | 2 (1.2) | 23 (26.1) | 0 | ||||||||||||
Adverse Reactions
COLUMVI+GemOx N=172 | R-GemOx N=88 | |||||||||||
All grades n (%) | Grade 3 to 4 n (%) | All grades n (%) | Grade 3 to 4 n (%) | |||||||||
| Headache | 15 (8.7) | 0 | 7 (8.0) | 0 | ||||||||
| Skin and subcutaneous tissue disorders | ||||||||||||
| Rasho | 46 (26.7) | 1 (0.6) | 13 (14.8) | 0 | ||||||||
The table includes a combination of grouped and ungrouped terms. Adverse reactions were graded using NCI CTCAE version 4.03, with the exception of CRS, which was graded per ASTCT consensus criteria in most cases. a Includes thrombocytopenia and platelet count decreased. b Includes neutropenia and neutrophil count decreased. c Includes lymphopenia and lymphocyte count decreased. d Includes abdominal pain, abdominal discomfort, abdominal pain upper, abdominal pain lower, and gastrointestinal pain. e Includes fatigue, asthenia and malaise. f Includes COVID-19, COVID-19 pneumonia, and SARS-CoV-2 test positive. Three subjects had a grade 5 COVID-19 event and one subject had a grade 5 acute respiratory distress event in the setting of COVID-19. g Includes upper respiratory tract infection, lower respiratory tract infection, respiratory tract infection, and respiratory tract infection bacterial. h Includes pneumonia, pneumonia bacterial, and pneumonia pneumococcal. i New onset or reactivation. Includes cytomegalovirus infection, cytomegalovirus test positive, cytomegalovirus infection reactivation and cytomegalovirus viraemia. j New onset or reactivation. Includes herpes zoster, herpes virus infection. k Includes sepsis, septic shock, bacteraemia, acinetobacter bacteraemia, enterococcal sepsis, escherichia bacteraemia, klebsiella bacteraemia, streptococcal sepsis, and neutropenic sepsis. l Includes gamma-glutamyltransferase increased and gamma-glutamyltransferase abnormal. m Includes arthralgia, musculoskeletal pain, back pain, bone pain, myalgia, neck pain, pain in extremity, musculoskeletal chest pain, and non-cardiac chest pain. n Includes neuropathy peripheral, peripheral sensory neuropathy, paraesthesia, hypoaesthesia, dysaesthesia, peripheral motor neuropathy, and polyneuropathy. o Includes rash, rash pruritic, rash maculo-papular, erythema, pruritus, rash erythematous, urticaria, and erythema multiforme. |
Description of selected adverse drug reactions from clinical trials
The descriptions below reflect information for significant adverse reactions for COLUMVI monotherapy. Details for the significant adverse reactions for COLUMVI when given in combination are presented if clinically relevant differences were noted in comparison to COLUMVI monotherapy. See 7 Warnings and Precautions, General for management of the following reactions:
Study NP30179 – Third-Line Monotherapy
Cytokine Release Syndrome
In Study NP30179, any grade CRS (by ASTCT criteria) occurred in 61.8% of patients, with Grade 1 CRS being reported in 45.4% of patients, Grade 2 CRS in 12.5% patients, Grade 3 CRS in 2.6% of patients, and Grade 4 CRS in 1.3% of patients. There were no fatal cases of CRS. CRS resolved in all patients except one. One patient discontinued COLUMVI due to CRS.
In patients with CRS, the most common manifestations of CRS included pyrexia (98.9%), tachycardia (27.7%), hypotension (25.5%), chills (13.8%), and hypoxia (12.8%). Grade 3 or higher events associated with CRS included hypotension (3.2%), hypoxia (3.2%), pyrexia (3.2%), and tachycardia (2.1%).
CRS of any grade occurred in 53.9% of patients following the 2.5 mg dose of COLUMVI at Cycle 1 Day 8 with median time to onset of 13.4 hours (range: 2.5 to 51.8 hours); in 32.5% of patients following the 10 mg dose at Cycle 1 Day 15 with median time to onset of 28.7 hours (range: 7.7 to 126.0 hours); and in 28.4% of patients following the 30 mg dose at Cycle 2 Day 1 with median time to onset of 29.1 hours (range: 15.9 to 45.1 hours). CRS was reported in 1.1% of patients at Cycle 3 and in 2.4% of patients beyond Cycle 3.
Grade ≥ 2 CRS occurred in 12.8% of patients following the first COLUMVI dose (2.5 mg), with median time to onset of 10.5 hours (range: 2.5 to 14 hours) and median duration of 40.8 hours (range: 6.5 to 316.7 hours). Following COLUMVI 10 mg dose at Cycle 1 Day 15, the incidence of Grade ≥ 2 CRS decreased to 5.6% of patients, with median time to onset of 27.2 hours (range: 7.7 to 145.2 hours) and median duration of 30.9 hours (range: 3.1 to 227.2 hours). Grade ≥ 2 CRS following COLUMVI 30 mg dose at Cycle 2 Day 1 occurred in one patient (0.9%) with time to onset of 16.0 hours and duration of 44.8 hours. No Grade ≥ 2 CRS was reported beyond Cycle 2.
Among the 25 patients who experienced Grade 2 or higher CRS after COLUMVI, 22 (88%) received tocilizumab, 15 (60%) received corticosteroids, and 14 (56%) received both tocilizumab and corticosteroids. Ten patients (40%) received oxygen. All 6 patients (24.0%) with Grade 3−4 CRS received a single vasopressor.
Immune Effector Cell-Associated Neurotoxicity Syndrome (ICANS)
In study NP30179 (cut-off date: 4 September 2023), neurologic toxicity was reported in 40.0% of patients (n=145). The most frequent neurologic toxicities of any grade were headache (10.3%), dizziness (5.5%), anxiety (4.1%), and paraesthesia (2.8%). Grade 3 or higher neurologic adverse reactions occurred in 2.1% of patients and included somnolence, delirium, and myelitis.
Seven patients (4.8%) experienced ICANS: 5 patients (3.4%) experienced Grade 1 events (2 patients with confusional state, and 1 patient each with somnolence, cognitive disorder, and disorientation), and 1 patient (0.7%) experienced Grade 3 somnolence. One patient (0.7%) experienced a fatal (Grade 5) event of delirium.
The median time to onset of the first ICANS event was 8 days (range: 1 to 106 days) from the first COLUMVI dose. The median time to resolution of ICANS was 1.5 days (range: 1 to 8 days). Of the 7 patients with ICANS, the onset of ICANS was concurrent with CRS in 5 patients and was non-concurrent with CRS in 2 patients.
Neutropenia
Neutropenia (including neutrophil count decreased) was reported in 34.2% of patients and severe neutropenia (Grade 3−4) was reported in 23.7% of patients who received COLUMVI monotherapy. The median time to onset of the first neutropenia event was 22.5 days (range: 1 to 183 days). Prolonged neutropenia (lasting longer than 30 days) occurred in 7.9% of patients. The majority of patients with neutropenia (82.7%) were treated with G-CSF. Febrile neutropenia was reported in 2.6% of patients.
Serious Infections
In Study NP30179, serious infections were reported in 17.1% of patients. The most frequent serious infections reported in ≥ 2% patients were sepsis (3.9%), COVID-19 pneumonia (3.3%), and COVID-19 (2%). Infection-related deaths were reported in 3.9% of patients (due to sepsis, COVID-19 pneumonia, and COVID-19). Three patients (2%) experienced serious infections concurrently with Grade 3−4 neutropenia.
Opportunistic Infections
CMV events were reported in 6/467 (1.3%) of patients who received COLUMVI monotherapy in study NP30179 (cut-off date: 17 May 2024), with one patient (0.2%) experiencing Grade 3 CMV chorioretinitis. Pneumocystis jirovecii pneumonia was reported in 4/467 patients (0.9%), 3 of whom (0.6%) had Grade 3 events in the same study.
Tumour Flare
Tumour flare was reported in 11.2% of patients who received COLUMVI monotherapy, including Grade 2 tumour flare in 4.6% of patients and Grade 3 tumour flare in 2.6% of patients. Tumour flare involved lymph nodes in the head and neck presenting with pain and lymph nodes in the thorax with symptoms of breathlessness due to development of pleural effusion. Most tumour flare events (16/17) occurred during Cycle 1, and no tumour flare events were reported beyond Cycle 2. The median time to onset of tumour flare of any grade was 2 days (range: 1 to 16 days), and the median duration was 3.5 days (range: 1 to 35 days). No patients discontinued COLUMVI due to tumour flare.
Tumour Lysis Syndrome TLS was reported in 2 patients (1.3%) who received COLUMVI monotherapy and was Grade 3 in severity in both cases. The median time to TLS onset was 2 days, and the median duration was 4 days (range: 3 to 5 days).
Colitis
Colitis (Grade 4) was reported in one patient who received COLUMVI monotherapy in study NP30179 (cut-off date: 04 September 2023), with time to onset from the first COLUMVI dose of 104 days.
Study GO41944 (STARGLO) – Second-Line Combination Therapy
Cytokine Release Syndrome
Any grade CRS (by ASTCT criteria) occurred in 44.2% of patients who received COLUMVI with gemcitabine and oxaliplatin, with Grade 1 CRS reported in 31.4% of patients, Grade 2 CRS in 10.5% of patients, and Grade 3 CRS in 2.3% of patients. There were no Grade 4 or fatal cases of CRS. CRS resolved in all patients except one who had a Grade 1 CRS and died due to disease progression on the same day. One patient discontinued COLUMVI due to CRS.
In patients with CRS, the most common manifestations of CRS included pyrexia (98.7%), hypotension (22.4%), chills (17.1%) and hypoxia (14.5%). Grade 3 or higher events associated with CRS included hypotension (6.6%), hypoxia (5.3%), pyrexia (3.9%), chills (1.3%), and diarrhea (1.3%).
CRS occurred in 35% of patients after the 2.5 mg dose of COLUMVI, 14% after the 10 mg dose, 9% after the initial 30 mg target dose, and 12% after subsequent doses. With the first step-up dose of COLUMVI, the median time to onset of CRS (from the start of infusion) was 13 hours (range: 4.4 to 55 hours). The majority (14/18) of patients who experienced Grade ≥ 2 CRS had onset of CRS within 8 hours of the start of the first COLUMVI dose (2.5 mg) or presented with a fever ≥ 1.5 hours before the onset of other symptoms of a Grade ≥ 2 CRS. CRS after any dose resolved in 99% of cases, with a median duration of first CRS of 2 days (range: 1 to 19 days). Recurrent CRS occurred in 22% of all patients. CRS can first occur with the 10 mg dose; of 167 patients treated with the 10 mg dose of COLUMVI, 5 patients (3%) experienced their first CRS event with the 10 mg dose, of which all 5 events were Grade 1.
At Cycle 1 after the 2.5 mg dose, 24.4% of patients experienced Grade 1 CRS, while 8.7% experienced Grade 2 CRS and 1.7% experienced Grade 3 CRS. At the 10 mg dose (Cycle 1, day 15), 12.6% of patients experienced grade 1 CRS, 1.2% experienced Grade 2 CRS and 0.6% experienced Grade 3 CRS. At the first dose of 30 mg (Cycle 2, day 1), 9.3% of patients experienced Grade 1 CRS. At Cycle 3, day 3 (30 mg), 6% of patients experienced Grade 1 CRS and 0.7% experienced Grade 2 CRS. From Cycle 4 to Cycle 12, 9.7% of patients experienced Grade 1 CRS and 1.4% experienced Grade 2 CRS. Among the 22 patients who experienced Grade 2 or higher CRS after COLUMVI, 16 (72.7%) received tocilizumab, 15 (68.2%) received corticosteroids, and 12 (54.5%) received both tocilizumab and corticosteroids. Eleven patients (50.0%) received oxygen. All 4 patients (18.2%) with Grade 3 CRS received a single vasopressor.
Immune Effector Cell-Associated Neurotoxicity Syndrome (ICANS)
In STARGLO, neurologic toxicity was reported in 59.3% of patients (n=172). The most frequent neurologic toxicities of any grade were peripheral neuropathy (37.2%), insomnia (11.6%), headache (8.7%), dizziness (7.0%) and dysgeusia (5.2%). Grade 3 or higher neurologic adverse reactions occurred in 5.8% of patients and included peripheral neuropathy, syncope, extrapyramidal disorder, confusional state, delirium, herpes zoster, meningitis aseptic, subdural haematoma and cerebral haemorrhage.
Four patients (2.3%) experienced ICANS: 1 patient (0.6%) experienced a Grade 1 event (confusional state), 2 patients (1.2%) experienced a Grade 2 event (1 patient with confusional state, and 1 patient with ICANS), and 1 patient (0.6%) experienced Grade 3 delirium.
The onset of the 4 events of ICANS was concurrent with CRS. The median time to resolution of ICANS was 1.5 days (range: 1 to 4 days).
Serious Infections
In STARGLO, serious infections were reported in 22.7% of patients who received COLUMVI with gemcitabine and oxaliplatin. The most frequent serious infections reported in ≥ 2% patients were pneumonia (5.8%), COVID-19 (4.7%), and lower respiratory tract infection (2.9%). Infection-related deaths were reported in 3.5% of patients (due to COVID-19, pneumonia, respiratory tract infection, and septic shock). One patient (0.6%) experienced a serious infection (pneumonia) concurrently with Grade 3 neutropenia.
Pneumonitis
Pneumonitis events (excluding pneumonia of infectious etiology) were reported in 2 patients (1.2%) who received COLUMVI with gemcitabine and oxaliplatin, both of which were fatal events. The median time to onset of pneumonitis from the first COLUMVI dose was 168 days (range: 102 to 255 days).
Colitis
Colitis events (excluding infectious etiology) were reported in 4 patients (2.3%) who received COLUMVI with gemcitabine and oxaliplatin. Two patients (1.2%) had Grade 3 events. The median time to onset of colitis from the first COLUMVI dose was 154 days (range: 115 to 187 days).
Opportunistic Infections
Cytomegalovirus (CMV) events were reported in 11 patients (6.4%) who received COLUMVI with gemcitabine and oxaliplatin, with 1 patient (0.6%) experiencing Grade 3 CMV viremia. Oral candidiasis was reported in 3 patients (1.7%), all of which were Grade 1-2 events. Pneumocystis jirovecii pneumonia (Grade 3) was reported in 1 patient (0.6%), the same patient with Grade 3 CMV viremia. Borellia meningitis (Grade 2) was reported in 1 patient (0.6%).
8.3 Less Common Clinical Trial Adverse Reactions
The ADRs which occurred in Study NP30179 with a frequency of < 5% were:
Blood and lymphatic system disorders: Lymphopenia, including lymphocyte count decreased (3.9%); febrile neutropenia, including neutropenic infection (3.3%).
Gastrointestinal disorders: Gastrointestinal haemorrhage, including large intestinal haemorrhage, and gastric haemorrhage (2.6%); vomiting (2.6%) and intestinal perforation (0.7%).
Immune system disorders: Hypogammaglobulinemia (1.3%)
Infections and infestations: Sepsis (3.9%); lower respiratory tract infections, including bronchitis (2.0%); pneumonia (2.6%); urinary tract infection (1.3%); Candida infections, including oesophageal candidiasis (0.7%).
Investigations: Blood bilirubin increased (3.3%); hepatic enzyme increased (1.3%).
Metabolism and nutrition disorders: Tumour lysis syndrome (1.3%).
Nervous system disorders: Somnolence (1.3%); tremor, myelitis, occurred concurrently with CRS (0.7%).
Psychiatric disorders: Confusional state (2.0%). The ADRs which occurred in STARGLO with a frequency of < 5% were:
Blood and lymphatic system disorders: Febrile neutropenia (2.9%).
Gastrointestinal disorders: Colitis, including colitis ischaemic, and enterocolitis (2.3%); pancreatitis including pancreatitis acute (1.7%).
Infections and Infestations: Urinary tract infection including urosepsis (3.5%); Candida infections including oral candidiasis (1.7%); Pneumocystis jirovecii pneumonia (0.6%).
Metabolism and nutrition disorders: Tumour lysis syndrome (1.7%).
Neoplasms benign, malignant and unspecified (incl cysts and polyps): Tumour flare including tumour pain (2.3%)
Nervous system disorders: ICANS including confusional state and delirium (2.3%); tremor (0.6%).
Respiratory, thoracic, and mediastinal disorders: Pneumonitis* (1.2%)
* Grade 5 reactions reported include COVID-19 (1.7%), pneumonitis (1.2%), septic shock (0.6%), pneumonia (0.6%), and respiratory tract infection (0.6%).
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry, and Other Quantitative Data
The following table summarizes treatment-emergent shifts from baseline in laboratory abnormalities in Study NP30179.
Table 10 Laboratory Abnormalities Worsening from Baseline, with Grade 3 to 4 Occurring in ≥ 10% of Patients with Relapsed or Refractory DLBCL Treated with COLUMVI Monotherapy
| Laboratory Abnormalitya | COLUMVI NCI CTCAE Grade | |||||
|---|---|---|---|---|---|---|
| All Grades (%)b | Grade 3 or 4 (%)b,c | |||||
| Hematology | ||||||
| Decreased lymphocytes | 88.1 | 80.4 | ||||
| Decreased neutrophils | 50.0 | 23.6 | ||||
| Decreased leukocytes | 66.2 | 11.7 | ||||
| Chemistry | ||||||
| Hypophosphatemia | 68.1 | 26.4 | ||||
| Hyperglycemia | 12.1 | 12.1 | ||||
| Hyperuricemia | 20.9 | 20.9 | ||||
a Percentages based on patients with a baseline and at least one post-baseline assessment for the specific laboratory parameter. b N=143 for decreased lymphocytes; N=144 for decreased neutrophils; N=145 for decreased leukocytes; N=144 for hypophosphatemia; N=141 for hyperglycemia; N=139 for hyperuricemia. c Includes shifts from Grade 0−2 at baseline to Grade ≥ 3 post-baseline, and shifts from Grade 3 at baseline to Grade 4 post-baseline. | ||||||
Table 11 Laboratory Abnormalities Worsening from Baseline, with Grade 3 to 4 Occurring in ≥ 5% of Patients with Relapsed or Refractory DLBCL Treated with COLUMVI in Combination with Gemcitabine and Oxaliplatin
| Laboratory Abnormalitya | COLUMVI+GemOx NCI CTCAE Grade | R-GemOx NCI CTCAE Grade | ||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|
| All Grades (%)b | Grade 3 or 4 (%)b,c | All Grades (%)d | Grade 3 or 4 (%)d,c | |||||||||
| Hematology | ||||||||||||
| Decreased platelets | 82.6 | 29.7 | 76.1 | 17 | ||||||||
| Decreased lymphocytes | 81.1 | 50.3 | 60.9 | 25 | ||||||||
| Decreased hemoglobin | 73.8 | 19.8 | 44.3 | 8 | ||||||||
| Decreased neutrophils | 65.3 | 39.5 | 45.5 | 19.7 | ||||||||
| Decreased leukocytes | 58.1 | 26.2 | 42 | 14.8 | ||||||||
| Chemistry | ||||||||||||
| Hyperuricemia | 21.9 | 21.9 | 12.2 | 12.2 | ||||||||
| Hypokalemia | 23.3 | 5.8 | 10.2 | 1.1 | ||||||||
a Percentages based on patients with a baseline and at least one post-baseline assessment for the specific laboratory parameter. b N=172 for decreased platelets; N=143 for decreased lymphocytes; N=172 for decreased hemoglobin; N=147 for decreased neutrophils; N=172 for decreased leukocytes; N=160 for hyperuricemia; N=172 for hypokalemia. c Includes shifts from Grade 0-2 at baseline to Grade ≥ 3 post-baseline, and shifts from Grade 3 at baseline to Grade 4 post-baseline. d N=88 for decreased platelets; N=64 for decreased lymphocytes; N=88 for decreased hemoglobin; N=66 for decreased neutrophils; N=88 for decreased leukocytes; N=82 for hyperuricemia; N=88 for hypokalemia. | ||||||||||||
8.5 Post-Market Adverse Reactions
The following adverse drug reactions have been identified from post-marketing experience with COLUMVI based on spontaneous case reports and literature cases. Adverse drug reactions are listed according to system organ classes in MedDRA.
Immune system disorders: Hemophagocytic lymphohistiocytosis1*(unknown frequency), Progressive multifocal leukoencephalopathy*(unknown frequency).
1Hemophagocytic lymphohistiocytosis (HLH) includes HLH and Immune Effector Cell Associated HLH-like Syndrome (IEC-HS).
*Incidence rate and frequency category cannot be estimated based on available data.
9 Drug Interactions
9.1 Drug Interactions Overview
No clinical drug-drug interaction studies have been performed with COLUMVI.
9.2 Drug-Behaviour Interactions
Female patients of reproductive potential must use highly effective contraceptive methods during treatment and for at least 2 months following the last dose of COLUMVI (see 7.1.1 Pregnan).
9.3 Drug-Drug Interactions
No drug interactions with COLUMVI are expected via the cytochrome P450 (CYP) enzymes, other metabolizing enzymes, or transporters.
A minimal physiologically-based pharmacokinetic model predicted some trends in the magnitude of potential drug interactions caused by the glofitamab-induced transient increase in interleukin-6 (IL-6) levels which may impact CYP activity. The modelling suggested it was feasible that the magnitude of the suppressive effect of transient IL-6 increase on CYP activities is < 50%. In addition, it was predicted that the changes in exposures to substrates of CYP3A4, CYP1A2, and CYP2C9 might be less than or equal to twofold.
Based on these data, on initiation of COLUMVI therapy in patients being treated with CYP450 substrates with a narrow therapeutic index, monitoring for toxicity (e.g., warfarin) or for drug concentrations (e.g., cyclosporine) of the concomitant drug should be considered.
Population pharmacokinetic modelling evaluated the effect of co-administered gemcitabine and oxaliplatin on the pharmacokinetics of COLUMVI. Co-administration had no statistically significant effect on any of the estimated pharmacokinetic parameters for COLUMVI.
9.4 Drug-Food Interactions
No drug−food interaction studies have been performed with COLUMVI.
9.5 Drug-Herb Interactions
No drug−herb interaction studies have been performed with COLUMVI.
9.6 Drug-Laboratory Test Interactions
No drug−laboratory test interaction studies have been performed with COLUMVI.
10 Clinical Pharmacology
10.1 Mechanism of Action
Glofitamab is a bispecific monoclonal antibody that binds bivalently (with high avidity) to CD20 expressed on the surface of B cells and monovalently to CD3 in the T-cell receptor complex expressed on the surface of T cells. By simultaneous binding to CD20 on the B cell and CD3 on the T cell, glofitamab mediates the formation of an immunological synapse with subsequent potent T-cell activation and proliferation, secretion of cytokines, and release of cytolytic proteins that results in the lysis of CD20-expressing B cells.
10.2 Pharmacodynamics
QT Prolongation: In Study NP30179, 10/152 patients who were exposed to glofitamab experienced a post-baseline QTc value > 450 ms. All but one were assessed as not of clinical significance by the investigator. No patients discontinued treatment due to QTc prolongation.
In study GO41944 (STARGLO), 16/172 patients who were exposed to glofitamab experienced a post-baseline QTc value > 450 ms. All but one were assessed as not of clinical significance by the investigator. No patients discontinued treatment due to QTc prolongation.
10.3 Pharmacokinetics
Non-compartmental analyses (NCA) of pharmacokinetics data from Study NP30179 (third-line monotherapy) indicate that glofitamab serum concentration reaches the maximal level (Cmax) at the end of infusion and declines in a bi-exponential fashion. Glofitamab exhibits linear and dose-proportional pharmacokinetics over the dose range studied (0.005 to 30 mg).
Table 12 Summary of Glofitamab Pharmacokinetic Parameters in r/r DBLC Patients calculated by Non-Compartmental Analysis after Single Dose of 10 mg
| Cmax (μg/mL) | Tmax (h) | Half-life (h) | AUCinf (h*μg/mL) | CL (mL/h) | Vz (mL) | |
|---|---|---|---|---|---|---|
| Single dose (10 mg) | 2.34 (46.1) | 8.05 (3.92-26.2) | 106 (23.9) | 244 (54.8) | 40.4 (54.3) | 6180 (44.9) |
All Parameters reported as Geometric Mean (Geo CV%) apart Tmax reported as Median (Min-Max) PK samples following the single dose of 10 mg were collected up to 336 h post dose.
Exposure metrics were estimated using population pharmacokinetics (popPK) modeling including concentration-time data from studies of glofitamab administered as monotherapy and in combination with GemOx. The predicted population means for exposure metrics over the step-up dosing regimen and after the first full dose at steady state are shown in Table 13 and
Table 14, respectively.
Table 13 Summary of Glofitamab Exposure Parameters in r/r DBLC Patients Estimated Using PopPK modeling – Step-up Dosing
| Dose\Exposure metric | CmaxD1 (µg/mL) | AUCD1 (µg.d/mL) | CmaxC1-C2 (µg/mL) | AUCC1-C2 (µg.d/mL) |
|---|---|---|---|---|
| 2.5/10/30 mg | 0.631 (0.245-1.14) | 0.450 (0.141-0.831) | 7.72 (0.656 – 15.1) | 46.6 (2.43 – 94.4) |
All Parameters reported as Geometric Mean (95% range); Cmaxd1 = peak concentration on Day 1 after 2.5 mg dose; AUC d1 = area under the curve on Day 1 after 2.5 mg dose; Cmaxc1-c2 = peak glofitamab concentration over the first two cycles of treatment; AUCC1-C2 = area under the curve over the first two cycles of treatment.
Table 14 Summary of Glofitamab Exposure Parameters in r/r DBLC Patients Estimated Using PopPK modeling – After first full (30 mg) dose
| Dose\Exposure metric | AUCtau (µg.d/mL) | Cmax (µg/mL) | Ctrough (µg/mL) |
|---|---|---|---|
| First full 30 mg dose | 44.5 [55%] | 9.41 [27%] | 0.52 [83%] |
| Steady state* 30 mg dose | 48.6 [33%] | 9.44 [26%] | 0.59 [67%] |
Data presented as geometric mean (%CV). AUCtau=area under the glofitamab concentration-time curve over 1 21-day cycle; Cmax=maximum glofitamab concentration; Ctrough=glofitamab concentration 30 minutes prior to next dose; CV=geometric coefficient of variation. * Steady state values are approximated at Cycle 6 (week 18). Absorption
COLUMVI is administered as an IV infusion. The PopPK Analysis with combined glofitamab monotherapy and glofitamab-GemOx data showed a peak geometric mean concentration of 0.631 µg/mL of glofitamab (Cmax) on Day 1 after the first infusion of 2.5 mg. The geometric mean Cmax at the end of Cycle 2 following the step-up dosing of 2.5, 10 and 30 mg, was estimated to be 7.72 µg/mL.
Distribution
Following IV administration, the PopPK model estimated the central volume of distribution parameter to be 3.34 L, and the peripheral volume of distribution parameter to be 2.35 L, with an intercompartmental clearance of 0.562 L/day.
Metabolism
The metabolism of glofitamab has not been directly studied. Antibodies are cleared principally by catabolism.
Elimination
The NCA analysis in glofitamab monotherapy estimated a half-life that ranged from 4 to 8 days across the doses tested. The glofitamab serum concentration−time data are described by a popPK model (combined glofitamab monotherapy and glofitamab-GemOx data) with two compartments and both time-independent and a time-varying clearance parameters.
Estimated PK parameters using PopPK in monotherapy and in combination with GemOx are stated below.
The time-independent clearance parameter was estimated as 0.633 L/day and the initial time-varying clearance parameter as 0.814 L/day, with an exponential decay over time (Kdes ~ 1.5/day). The estimated transition from the non-linear phase to the linear phase was estimated as 1.28 days, after which the effective half-life in the linear phase can be approximated to a typical linear effective half-life of 7.92 days (95% CI: 4.69 - 11.9) based on the empirical Bayes estimates in the current patient population.
Special populations and conditions
- Pediatrics No studies have been conducted to investigate the pharmacokinetics of glofitamab in pediatric patients.
- Geriatrics No differences in glofitamab exposure were noted in patients 65 years of age and older and those under 65 years based on population pharmacokinetic analysis.
- Hepatic Insufficiency No formal pharmacokinetic study has been conducted in patients with moderate and severe hepatic impairment.
- Renal Insufficiency Creatinine clearance is not associated with the linear or time varying clearance parameters in the model for glofitamab. The pharmacokinetic response of COLUMVI has not been studied in patients with severe renal impairment.
10.4 Immunogenicity
As with all therapeutic proteins, there is a potential for immunogenicity. The detection of an immune response is highly dependent on the sensitivity and specificity of the assays used, sample handling, timing of sample collection, concomitant medications, and underlying disease. For these reasons, comparison of the incidence of antibodies to COLUMVI with the incidence of antibodies to other products may be misleading.
No patients developed treatment-emergent anti-drug antibodies (ADAs) against COLUMVI. Across studies, the majority of patients (574/608 patients; 94.4%) who received COLUMVI were negative for ADAs at baseline and remained negative throughout treatment with COLUMVI. Four patients (0.7%) were ADA-negative at baseline and ADA-positive at one or more post-dose timepoints. Four patients (0.7%) were ADA-positive at baseline and at one or more post-dose timepoints.
11 Storage, Stability, and Disposal
Vials
Store at 2 °C to 8 °C. Keep the vial in the outer carton in order to protect it from light. Do not freeze. Do not shake.
Diluted solution for intravenous infusion
The prepared infusion solution should be used immediately. If not used immediately, the infusion solution can be stored in the refrigerator at 2°C to 8°C for up to 64 hours and at 25°C for up to 4 hours prior to administration, followed by a maximum infusion time of 8 hours.
Disposal of unused/expired medicines
The release of pharmaceuticals in the environment should be minimized. Medicines should not be disposed of via wastewater, and disposal through household waste should be avoided.
The following points should be strictly adhered to regarding the use and disposal of syringes and other medicinal sharps:
- Needles and syringes should never be reused.
- Place all used needles and syringes into a sharps container (puncture-proof disposable container).
Any unused medicinal product or waste material should be disposed of in accordance with local requirements.
12 Special Handling Instructions
Do not freeze. Do not shake.
Part 2: Scientific Information
13 Pharmaceutical Information
Drug Substance
Non-proprietary name of the drug substance(s): glofitamab
Chemical name: Recombinant anti-human CD20 and anti-human CD3 monoclonal antibody
Molecular formula and molecular mass: C8632H13326N2296O2701S58; Approx. 194 kDa (peptide chains only, without heavy chain C terminal lysine residues, with N terminal glutamines converted into pyroglutamates due to cyclization)
Structural formula:
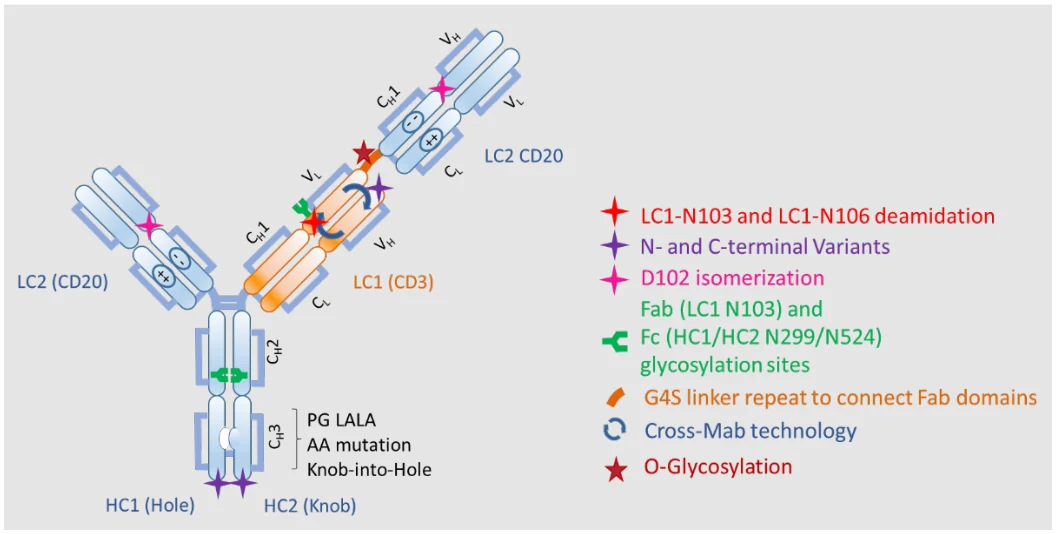
Physicochemical properties: COLUMVI is a sterile, preservative-free, colourless concentrate for solution for infusion.
Pharmaceutical standard: Professed
Product Characteristics:
Glofitamab is a heterogeneous protein having the intended primary structure, post-translational modifications, and other characteristics of a recombinant IgG1 derived from CHO cells.
14 Clinical Trials
14.1 Clinical Trials by Indication
Relapsed or Refractory DLBCL
Study NP30179 – relapsed or refractory diffuse large B-cell lymphoma (DLBCL) not otherwise specified, DLBCL arising from follicular lymphoma (trFL), or primary mediastinal B-cell lymphoma (PMBCL), who have received two or more lines of systemic therapy
An open-label, phase I/II, multicenter, multi-cohort trial (NP30179) was conducted to evaluate COLUMVI monotherapy in patients with relapsed or refractory B-cell lymphoma. In the single-arm DLBCL cohort (n=108), patients with relapsed or refractory DLBCL were required to have received at least two prior lines of systemic therapy, including an anti-CD20 monoclonal antibody and an anthracycline. Patients with FL3b and/or Richter’s transformation were not eligible. The study excluded patients with prior allogeneic hematopoietic stem cell transplant, previous or active central nervous system (CNS) lymphoma, active infections, previous history of active autoimmune disease requiring immunosuppressive therapy, Eastern Cooperative Oncology Group (ECOG) performance status ≥ 2, creatinine clearance (CrCL) < 50 mL/min, or hepatic transaminases > 3 × ULN.
Following pre-treatment with obinutuzumab 1 000 mg at Cycle 1 Day 1, patients received 2.5 mg of COLUMVI at Cycle 1 Day 8, 10 mg of COLUMVI at Cycle 1 Day 15, and 30 mg of COLUMVI at Cycle 2 Day 1 as per the step-up dosing schedule. Patients continued to receive 30 mg of COLUMVI on Day 1 of Cycles 3 to 12. Patients received premedication including an anti-pyretic, an anti-histamine and a glucocorticoid (see 4.1 Dosing Considerations). The duration of each cycle was 21 days. Patients received a median of 5 cycles of COLUMVI treatment (range: 1 to 12 cycles).
The baseline demographic and disease characteristics were: median age 66 years (range: 21 to 90 years); 69.4% male; 74.1% white, 5.6% Asian, and 0.9% Black or African American; 5.6% Hispanic or Latino; and ECOG performance status of 0 (47.2%) or 1 (50.0%). Most patients (73.1%) had DLBCL not otherwise specified, 15.7% had DLBCL arising from follicular lymphoma, 5.6% had high-grade B-cell lymphoma (HGBCL), and 5.6% had PMBCL.
The median number of prior lines of therapy was 3 (range: 2 to 7), with 40.7% of patients having received 2 prior lines and 59.3% having received 3 or more prior lines of therapy. Almost all patients (99.1%) had received prior chemotherapy and anti-CD20 monoclonal antibody therapy; 34.3% of patients had received prior CAR T-cell therapy; and 14.8% of patients had received autologous stem cell transplant. Most patients (90.7%) had refractory disease, 59.3% patients had primary refractory disease, and 84.3% of patients were refractory to their last prior therapy.
The overall median duration of follow-up was 9 months (range: 0 to 16 months). Median duration of follow-up from the date of first response (CR or ORR) per Independent Review Committee (IRC) assessment was 7.6 months (range: 0 to 14 months).
The primary efficacy outcome measure was complete response (CR) rate as assessed by the IRC using 2014 Lugano response criteria. The key secondary efficacy outcome measures included IRC assessed overall response rate (ORR), duration of response (DOR), and duration of complete response (DOCR). The primary and key secondary efficacy endpoints are shown in Table 15.
Table 15 Summary of efficacy in patients with relapsed or refractory DLBCL as assessed by an independent review committee (Study NP30179, Cohort D3)
| Efficacy Endpoints | COLUMVI N=108 | |||||
|---|---|---|---|---|---|---|
| Primary Endpoint | ||||||
| IRC-Assessed Complete Response | ||||||
| Patients with CR, n (%) | 38 (35.2) | |||||
| 95% CI | [26.24, 44.96] | |||||
| Secondary Endpoints | ||||||
| Overall Response Rate | ||||||
| Patients with CR or PR, n (%) | 54 (50.0) | |||||
| 95% CI | [40.22, 59.78] | |||||
| Partial Response (PR), n (%) | 16 (14.8) | |||||
| 95% CI | [8.71, 22.94] | |||||
| Duration of Complete Response | ||||||
| Median DOCR†, months [95% CI] | 14.4 [NE] a | |||||
| Range, months | 0b-14 | |||||
| 9-month DOCR, % [95% CI]c | 83.8 [68.92, 98.65] | |||||
| Duration of Response | ||||||
| Median DOR‡, months [95% CI] | 14.4 [7.3, NE] a | |||||
| Range, months | 0b-14 | |||||
| 9-month DOR, % [95% CI]c | 60.9 [46.49, 75.38] | |||||
CI=confidence interval; INV=Investigator; IRC=Independent Review Committee; N/A=not applicable; NE=not estimable. †DOCR is defined as the date of first complete response until disease progression or death due to any cause. ‡DOR is defined as the date of first response (PR or CR) until disease progression or death due to any cause. a IRC-assessed median DOCR and median DOR were immature at the time of analysis but were reached at 14.4 months when the last patient at risk experienced an event. b Censored observations. c Event-free rates based on Kaplan-Meier estimates. Note: 95% CI for response rates computed using the Clopper-Pearson method; 95% CI for median computed using the Brookmeyer and Crowley method. | ||||||
The time to first complete response was 42 days (95% CI: 41, 42).
Post CAR-T Subgroup
Among patients who have previously received CAR-T cell therapy, the complete response rate was 31.6% (12/38) and the overall response rate was 44.7% (17/38).
Study GO41944 (STARGLO) –relapsed or refractory diffuse large B-cell lymphoma not otherwise specified (DLBCL NOS) who are not candidates for autologous stem cell transplant (ASCT)
Table 16 Summary of patient demographics for Study GO41944 (STARGLO) in Relapsed or Refractory DLBCL Patients
| Study # | Study Design | Dosage, route of administration and duration | Study subjects (n) | Median age (Range) | Sex n (%) | ||
|---|---|---|---|---|---|---|---|
| GO41944 | Phase III, multicenter, randomized, double-blind, controlled study | COLUMVI + GemOx R-GemOx COLUMVI IV 2.5 mg at Cycle 1 Day 8, 10 mg at Cycle 1 Day 15, 30 mg on day 1 of Cycles 2-12 Duration: 12 cycles (21 days per cycle) Gemcitabine IV 1 000 mg/m2 and oxaliplatin IV 100 mg/m2 on Day 2 of Cycle 1 and then on Day 1 of subsequent cycles. Duration: 8 cycles (21 days per cycle) Rituximab IV 375 mg/m2 on Day 1 of Cycle 1 and then on Day 1 of subsequent cycles. Duration: 8 cycles (21 days per cycle) | Total: n = 274 COLUMVI+ GemOx: n = 183 R-GemOx: n = 91 | 68 years (range: 20-88) | M: 158 (57.7) F: 116 (42.3) | ||
| GemOx = Gemcitabine + Oxaliplatin; R = Rituximab | |||||||
The efficacy of COLUMVI in combination with gemcitabine and oxaliplatin (COLUMVI+GemOx) was investigated in study GO41944 (STARGLO), an open-label multicenter, randomized clinical trial that included 274 patients with relapsed or refractory DLBCL not otherwise specified (DLBCL NOS). The study excluded patients who received only one prior line of therapy, who were candidates for stem cell transplant, patients with HGBCL, PMBCL, history of transformation of indolent disease to DLBCL, prior allogeneic hematopoietic stem cell transplant, previous or active CNS lymphoma, ECOG performance status > 2, CrCL < 30 mL/min, or hepatic transaminases > 2.5 × ULN.
Patients were randomized 2:1 to receive COLUMVI+GemOx (N=183) or rituximab in combination with gemcitabine and oxaliplatin (R-GemOx; N=91) for 8 cycles, followed by 4 additional cycles of COLUMVI monotherapy for patients in the COLUMVI+GemOx arm.
Randomization was stratified by number of previous lines of systemic therapy for DLBCL (1 vs. ≥ 2) and outcome of last systemic therapy (relapsed vs. refractory).
In the COLUMVI+GemOx arm, following pre-treatment with obinutuzumab at Cycle 1 Day 1, patients received 2.5 mg of COLUMVI at Cycle 1 Day 8, 10 mg of COLUMVI at Cycle 1 Day 15, and 30 mg of COLUMVI at Cycle 2 Day 1 as per the step-up dosing schedule. Each cycle lasted 21 days. Patients continued to receive 30 mg of COLUMVI on Day 1 of Cycles 3 to 12. Patients received premedication including an anti-pyretic, an anti-histamine, and dexamethasone prior to being administered COLUMVI. For patients who were unable to receive dexamethasone, an alternate corticosteroid was used (see section 4 Dosage and Administration). Gemcitabine (1 000 mg/m2) and oxaliplatin (100 mg/m2) were administered intravenously on Day 2 of Cycle 1 and then on Day 1 of subsequent cycles, for a maximum of 8 cycles. The duration of each cycle was 21 days.
Patients received a median of 11 cycles of COLUMVI treatment (range: 1 to 13 cycles) compared to 4 cycles of rituximab (range: 1 to 8).
The baseline demographic and disease characteristics for the overall trial were: median age 68 years (range: 20 to 88 years); 57.7% males; 42.0% white, 50.0% Asian, and 1.1% Black or African American; 5.8% Hispanic or Latino; and ECOG performance status of 0 (43.3%), 1 (46.6%), or 2 (10.1%). The majority of patients (62.8%) had received 1 prior line of systemic therapy; 37.2% of patients received 2 or more prior lines. All patients had received prior chemotherapy and most (98.5%) had received anti-CD20 monoclonal antibody therapy; 7.7% of patients had received CAR T-cell therapy, and 4.0% had received autologous stem cell transplant. The majority of patients (66.8%) had refractory disease; 55.8% had primary refractory disease, and 60.6% of patients were refractory to their last prior therapy.
The primary efficacy outcome measure was overall survival (OS). Progression free survival (PFS) and complete response (CR) were the key secondary efficacy outcomes. PFS and CR rate were assessed by an independent review committee (IRC) based on the 2014 Lugano Response Criteria. At the time of the primary analysis, results for OS, PFS and CRR were statistically significant.
Efficacy results are summarized in
Table 17 and in Figure 1 and Figure 2.
Table 17 Efficacy in Patients with Relapsed or Refractory DLBCL Treated with COLUMVI in Combination with Gemcitabine and Oxaliplatin (ITT)
Primary Analysis Median observation time=11.3 months | ||||||||
|---|---|---|---|---|---|---|---|---|
| Columvi+GemOx (N=183) | R-GemOx (N=91) | |||||||
| Primary Endpoint | ||||||||
| Overall Survival | ||||||||
| Number (%) of deaths | 61 (33.3) | 40 (44.0) | ||||||
| Median [95% CI], months | NE [13.8, NE] | 9.0 [7.3, 14.4] | ||||||
| HR [95% CI] | 0.59 [0.40, 0.89] | |||||||
| p-value | 0.011 | |||||||
| Secondary Endpoints - IRC-assessed | ||||||||
| Progression-Free Survival | ||||||||
| Number (%) of patients with events | 68 (37.2) | 44 (48.4) | ||||||
| Median [95% CI], months | 12.1 [6.8, 18.3] | 3.3 [2.5, 5.6] | ||||||
| HR [95% CI] | 0.37 [0.25, 0.55] | |||||||
| p-value | <0.001 | |||||||
| Complete Response Rate | ||||||||
| Responders (%) | 92 (50.3) | 20 (22.0) | ||||||
| Difference in response rate (%) [95% CI] | 28.3 [16.3, 40.3] | |||||||
| p-value | <0.001 | |||||||
| CI=confidence interval; HR=hazard ratio; N/A=not applicable; NE=not estimable. | ||||||||
Figure 1 Kaplan-Meier Plot of Overall Survival in Study GO41944 (STARGLO, Primary Analysis; ITT)
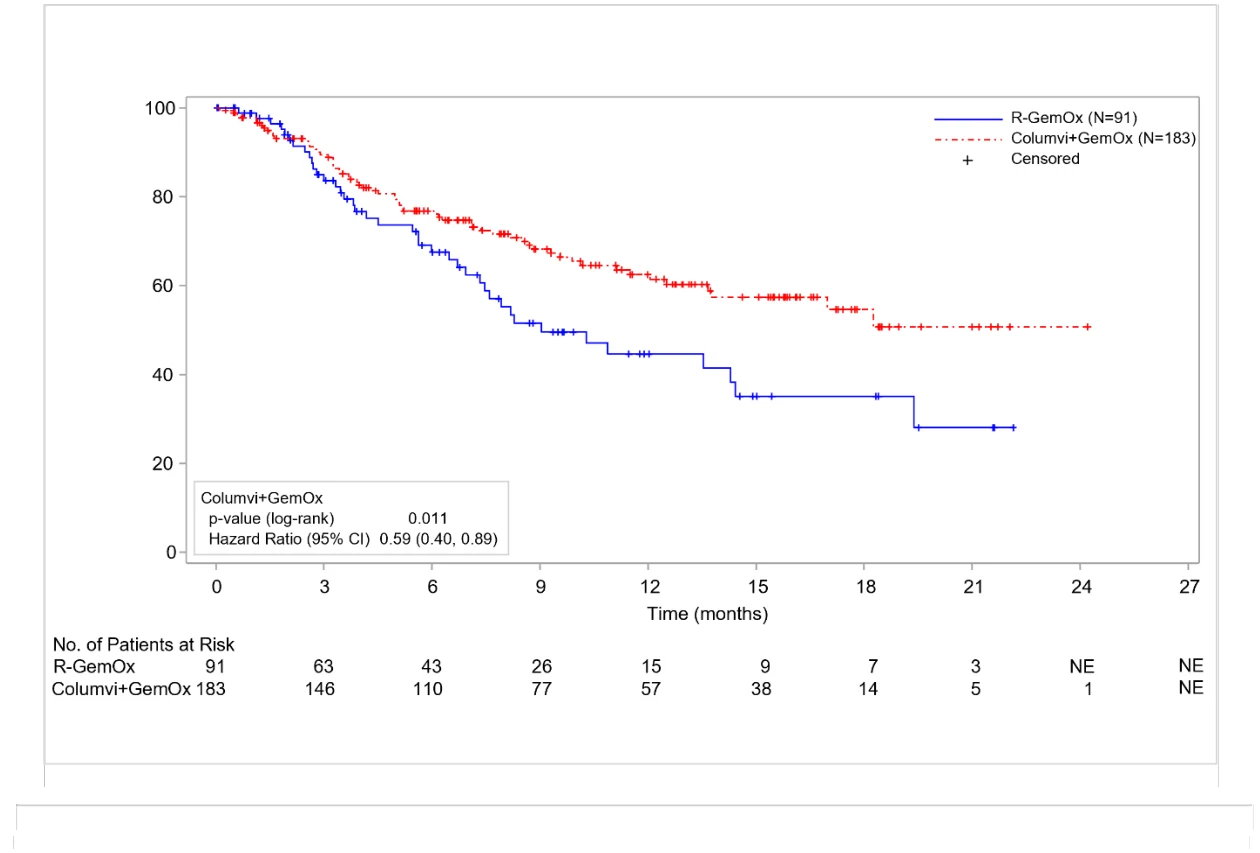
Figure 2 Kaplan-Meier Plot of IRC-Assessed Progression-Free Survival in Study GO41944 (STARGLO, Primary Analysis; ITT)
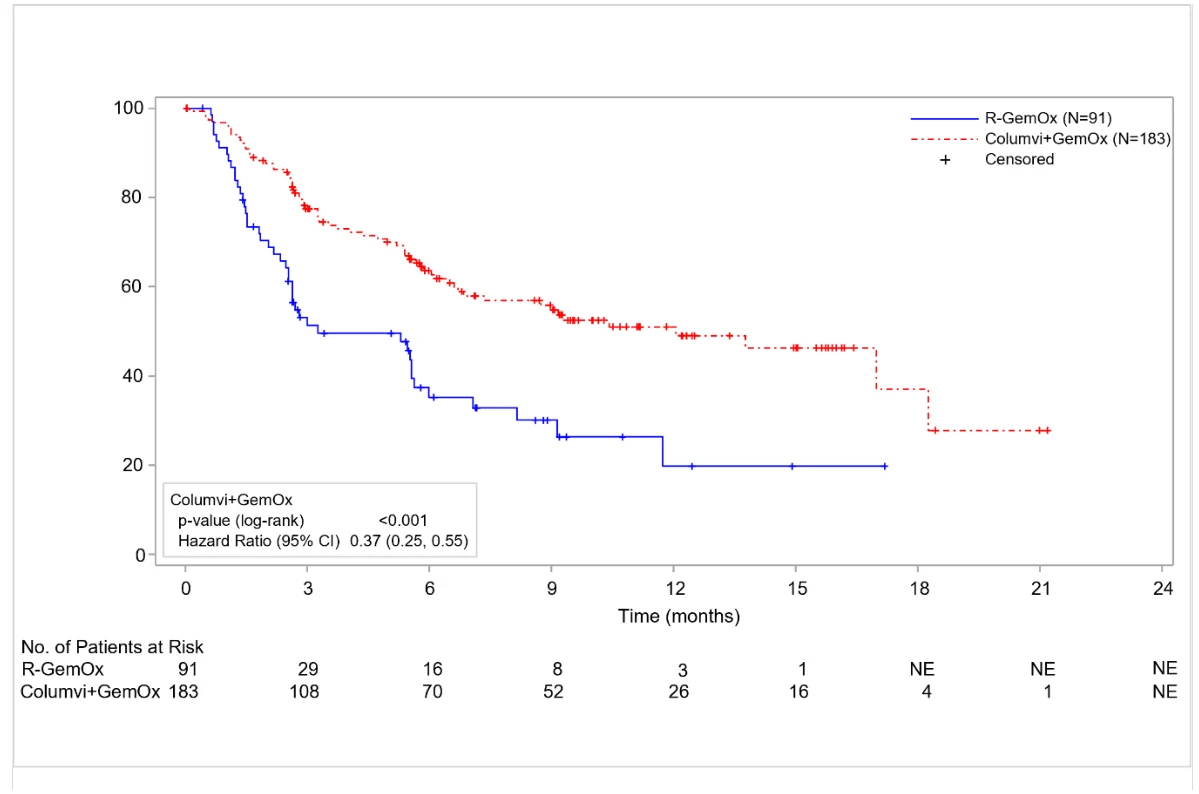
Overall survival, PFS, and CR results from an updated analysis conducted after an additional 10.5 months of follow-up (median observation time = 20.7 months) continued to demonstrate benefit of COLUMVI+GemOx over R-GemOx. Median OS was 25.5 months in the COLUMVI+GemOx arm compared with 12.9 months in the R-GemOx arm in the updated analysis. The Hazard Ratio for OS was 0.62 (95%CI: 0.43, 0.88) favouring COLUMVI+GemOx. The updated Hazard Ratio for PFS, which also favoured COLUMVI+GemOx, was 0.40 (95%CI: 0.28, 0.57). The updated CR rates were 58.5% for COLUMVI+GemOx and 25.3% for R-GemOx.
14.2 Comparative Bioavailability Studies
Not applicable.
15 Microbiology
No microbiological information is required for this drug product.
16 Non-Clinical Toxicology
General toxicology: A 2-week GLP repeat-dose toxicity study was conducted in cynomolgus monkeys to evaluate the toxicity of IV administration of glofitamab (0.01, 0.03 and 0.1 mg/kg/dose). Animals experiencing severe CRS after a single intravenous dose of glofitamab (0.1 mg/kg) without obinutuzumab pre-treatment had erosions in the gastrointestinal tract and inflammatory cell infiltrates in spleen and sinusoids of the liver and sporadically in some other organs. These inflammatory cell infiltrates were likely secondary to cytokine-induced immune cell activation.
In a 4-week repeat-dose toxicity study with step-up dosing 0.03/0.1/0.1 or 0.3 mg/kg and then dosing every other day, acute phase reactions (increased CRP, fibrinogen, triglycerides, and bilirubin; and mildly decreased albumin and cholesterol) and changes in leukocytes occurred and were considered secondary to cytokine release and activation-induced margination. Minimal to mild mononuclear cell infiltrates in some organs (heart, salivary gland, kidney, perivascular spaces of meninges, choroid plexus, and parenchyma of the brain - some with minimal gliosis) were increased in incidence among glofitamab-dosed animals as compared to controls.
Administration of glofitamab was also associated with sustained (beginning as early as 30 minutes post-dose up to 20 hours post-dose), dose-dependent increases in heart rate (decreased RR interval), with similar and rate-related decreases in PR and QT intervals. Effects were less pronounced after the second glofitamab dose. There were glofitamab-related increases in average body temperature 6 hours post-dose on Day 1 and 24 hours post-dose on Day 15 of the 4-week study. Increases in heart rate and body temperature are considered to be related to increases in cytokine levels following dosing. No test article-related findings on respiration, and no clinical signs specifically related to effects on CNS were identified.
In the absence of obinutuzumab, the maximum tolerated IV doses were 0.03 mg/kg on Day 1 followed by 0.1 mg/kg on Day 8 (step-up dosing). In the absence of obinutuzumab pretreatment and because of high clearance in monkeys, lower glofitamab exposures were achieved in repeat-dose toxicity studies compared to the clinical setting. Pre-treatment with obinutuzumab resulted in the attenuation of cytokine release and related adverse effects by depleting B cells in peripheral blood and lymphoid tissue. This allowed at least 10 times higher doses of glofitamab (1 mg/kg) in cynomolgus monkeys resulting in a Cmax of up to 3.74 times the human Cmax at the recommended 30 mg dose.
All findings with glofitamab were considered pharmacologically mediated effects and reversible. Studies longer than 4 weeks were not performed, as glofitamab was highly immunogenic in cynomolgus monkeys and led to loss of exposure and loss of the pharmacologic effect.
Genotoxicity: No studies have been performed to establish the mutagenic potential of COLUMVI.
Carcinogenicity: No carcinogenicity studies have been performed to establish the carcinogenic potential of COLUMVI.
Reproductive and developmental toxicology: No reproductive toxicity studies in animals have been performed to evaluate the effect of COLUMVI.
Based on low placental transfer of antibodies during the first trimester, the mechanism of action of glofitamab (B-cell depletion, target-dependent T-cell activation, and cytokine release), the available safety data with COLUMVI, and the data on other anti-CD20 antibodies, the risk for teratogenicity is low. Prolonged B-cell depletion can lead to increased risk of opportunistic infection, which may cause fetal loss. Transient CRS associated with COLUMVI administration may also be harmful to the fetus.
Impairment of Fertility: No fertility assessments in animals have been performed to evaluate the effect of COLUMVI.