


Product Monograph - Unituxin
Recent Major Label Changes
| None at the time of the most recent authorization |
|---|
Sections or subsections that are not applicable at the time of authorization are not listed.
Table of Contents
Table of Contents ................................................................................................................................. 2
Part 1: Healthcare Professional Information ......................................................................................... 4
- 1.
Indications ................................................................................................................................... 4
1.1. Pediatrics ............................................................................................................................ 4
1.2. Geriatrics ............................................................................................................................. 4
- 2. Contraindications ......................................................................................................................... 4
- 3. Serious Warnings and Precautions Box ......................................................................................... 4
- 4.
Dosage and Administration .......................................................................................................... 5
4.1. Dosing Considerations ........................................................................................................ 5
4.2. Recommended Dose and Dosage Adjustment ................................................................... 5
4.3. Reconstitution ..................................................................................................................... 8
4.4. Administration .................................................................................................................... 8
4.5. Missed Dose ........................................................................................................................ 8
- 5. Overdose ...................................................................................................................................... 8
- 6. Dosage Forms, Strengths, Composition, and Packaging ................................................................. 9
- 7.
Warnings and Precautions ............................................................................................................ 9
7.1. Special Populations ........................................................................................................... 12
- 8.
Adverse Reactions ...................................................................................................................... 13
8.1. Adverse Reaction Overview .............................................................................................. 13
8.2. Clinical Trial Adverse Reactions ........................................................................................ 13
8.3. Less Common Clinical Trial Adverse Reactions ................................................................. 18
8.5. Post-Market Adverse Reactions ........................................................................................ 18
- 9. Drug Interactions ........................................................................................................................ 19
- 10.
Clinical Pharmacology ................................................................................................................ 19
10.1. Mechanism of Action ........................................................................................................ 19
10.2. Pharmacodynamics ........................................................................................................... 19
10.3. Pharmacokinetics .............................................................................................................. 19
10.4. Immunogenicity ................................................................................................................ 20
- 11. Storage, Stability, and Disposal ................................................................................................... 21
- 12. Special Handling Instructions ...................................................................................................... 21
Part 2: Scientific Information ............................................................................................................. 22
- 13. Pharmaceutical Information ....................................................................................................... 22
- 14.
Clinical Trials .............................................................................................................................. 22
14.1. Clinical Trials by Indication................................................................................................ 22
- 15. Microbiology .............................................................................................................................. 29
- 16. Non-Clinical Toxicology ............................................................................................................... 29
Patient Medication Information ......................................................................................................... 30
Part 1: Healthcare Professional Information
1. Indications
UNITUXIN (Dinutuximab for injection) is indicated, in combination with granulocyte-macrophage colony-stimulating factor (GM-CSF), interleukin-2 (IL-2), and 13-cis-retinoic acid (RA), for the treatment of high-risk neuroblastoma in pediatric patients who achieve at least a partial response to prior first-line multiagent, multimodality therapy (see 14 Clinical Trials).
1.1. Pediatrics
Pediatrics (≤18 years old): Based on the data submitted and reviewed by Health Canada, the safety and efficacy of UNITUXIN as part of a multiagent, multimodality therapy have been established in pediatric patients with high-risk neuroblastoma. Therefore, Health Canada has authorized an indication for pediatric use (See 7.1.3 Pediatrics and 14 Clinical Trials).
1.2. Geriatrics
Geriatrics (≥65 years old): The safety and effectiveness of UNITUXIN in geriatric patients have not been established; therefore, Health Canada has not authorized an indication for geriatric use (see 7.1.4 Geriatrics).
2. Contraindications
UNITUXIN (Dinutuximab for injection) is contraindicated in patients with a history of anaphylaxis to dinutuximab, IL-2, GM-CSF, RA, or any excipients in the medicinal product. For a complete listing, see 6 Dosage Forms, Strengths, Composition, and Packaging.
- 3. Serious Warnings and Precautions Box
Serious Warnings and Precautions
Infusion Reactions
- UNITUXIN can cause serious and potentially life-threatening infusion reactions. Administer required prehydration and premedication, including antihistamines, prior to each UNITUXIN infusion. Monitor patients closely for signs and symptoms of an infusion reaction during and for at least 4 hours following completion of each UNITUXIN infusion. Immediately interrupt UNITUXIN for severe infusion reactions and permanently discontinue UNITUXIN for anaphylaxis (see 4 Dosage and Administration and 7 Warnings and Precautions, General).
Neurotoxicity
- UNITUXIN causes severe neuropathic pain. Administer intravenous opioid prior to, during, and for 2 hours following completion of the UNITUXIN infusion. Severe peripheral sensory neuropathy ranged from 2% to 9% in patients with neuroblastoma. Severe peripheral motor neuropathy has also been reported. Discontinue for severe unresponsive pain, severe sensory neuropathy, and moderate to severe peripheral motor neuropathy (see 4 Dosage and Administration and 7 Warnings and Precautions, Neurologic).
4. Dosage and Administration
4.1. Dosing Considerations
- Verify that patients have adequate hematologic, respiratory, hepatic, and renal function prior to initiating each course of UNITUXIN (see 14 Clinical Trials).
- Administer required premedication and hydration prior to initiation of each UNITUXIN infusion (see 4.2 Recommended Dose and Dosage Adjustment).
4.2. Recommended Dose and Dosage Adjustment
- The recommended dose of UNITUXIN is 17.5 mg/m2/day administered as an intravenous infusion over 10 to 20 hours for 4 consecutive days for a maximum of 5 cycles (Table 1 and Table 2) (see 14 Clinical Trials and 4.4 Administration).
- Initiate at an infusion rate of 0.875 mg/m2/hour for 30 minutes. The infusion rate can be gradually increased as tolerated to a maximum rate of 1.75 mg/m2/hour. Follow dose modification instructions for adverse reactions (see 4.2 Recommended Dose and Dosage Adjustment).
Table 1 Schedule of UNITUXIN Administration for Cycles 1, 3, and 5
| Cycle Day | 1 through 3 | 4 | 5 | 6 | 7 | 8 through 24a |
|---|---|---|---|---|---|---|
| UNITUXIN | X | X | X | X |
a Cycles 1, 3, and 5 are 24 days in duration.
Table 2 Schedule of UNITUXIN Administration for Cycles 2 and 4
| Cycle Day | 1 through 7 | 8 | 9 | 10 | 11 | 12 through 32a |
|---|---|---|---|---|---|---|
| UNITUXIN | X | X | X | X |
a Cycles 2 and 4 are 32 days in duration.
Required Pre-treatment and Guidelines for Pain Management and Infusion Reactions During all UNITUXIN-Administered Courses
Intravenous Hydration
- Administer 0.9% Sodium Chloride Injection as an intravenous infusion over 1 hour just prior to initiating each UNITUXIN infusion.
Analgesics
- Administer morphine sulfate at 50 mcg/kg intravenously immediately prior to initiation of UNITUXIN infusion and then continue as a morphine sulfate drip at an infusion rate of 20 to 50 mcg/kg/hour during and for 2 hours following completion of UNITUXIN infusion.
- Administer additional 25 to 50 mcg/kg intravenous doses of morphine sulfate up to every 2 hours as needed for pain, followed by a clinically appropriate increase in the morphine sulfate infusion rate in clinically stable patients.
- Other pain control should be considered as necessary. Consideration of using fentanyl or hydromorphone if morphine sulfate is not tolerated. Lidocaine or gabapentin can be considered as co-analgesics in conjunction with morphine infusion.
Antihistamines and Antipyretics
- Administer an antihistamine such as diphenhydramine (0.5 to 1 mg/kg; maximum dose 50 mg) intravenously over 10 to 15 minutes starting 20 minutes prior to initiation of UNITUXIN infusion and as tolerated every 4 to 6 hours during the UNITUXIN infusion.
- Administer an antipyretic such as acetaminophen (10 to 15 mg/kg; maximum dose 650 mg) 20 minutes prior to each UNITUXIN infusion and every 4 to 6 hours as needed for fever or pain. For persistent pain or fever despite acetaminophen and morphine sulfate, administer ibuprofen (5 to 10 mg/kg) every 6 hours as needed.
Required Pre-treatment and Guidelines for Pain Management and Infusion Reaction When IL-2 is Administered Alone (Courses 2 and 4, Course Days 0-3)
Antihistamines and Antipyretics
- Acetaminophen and ibuprofen should be administered as noted above. Acetaminophen is recommended before IL-2 administration and every 6 hours around the clock during IL-2 administration.
- Diphenhydramine is administered as needed for allergic reactions or nausea with dosing as described above. For nausea, it is recommended to start 10 minutes before IL-2 and continued every 4 to 6 hours as needed.
Dosage Modifications
Manage adverse reactions by infusion interruption, infusion rate reduction, dose reduction, or permanent discontinuation of UNITUXIN (Table 3 and Table 4) (see 7 Warnings and Precautions, 8 Adverse Reactions, and 14 Clinical Trials).
Table 3 Adverse Reactions Requiring Permanent Discontinuation of UNITUXIN
Grade 3 or 4 anaphylaxis or Grade 4 infusion reactions
Grade 3 or 4 serum sickness
Grade 3 pain unresponsive to maximum supportive measures
Grade 4 sensory neuropathy or Grade 3 sensory neuropathy that interferes with daily activities for more than 2 weeks
Grade 2 or greater peripheral motor neuropathy
Urinary retention that persists following discontinuation of opioids
Transverse myelitis
Reversible Posterior Leukoencephalopathy Syndrome (RPLS)
Subtotal or total vision loss
Grade 4 hyponatremia despite appropriate fluid management
Grade 4 hypokalemia despite interventions to correct deficiency
Atypical hemolytic uremic syndrome
Grade 4 capillary leak syndrome (if recurs after 50% dose reduction following Grade 4 reaction in previous cycle)
Table 4 Dose Modification for Selected UNITUXIN Adverse Reactions
Infusion-related reactions (see 7 Warnings and Precautions)
Mild to moderate adverse reactions, such as transient rash, fever, rigors, and localized urticaria, that respond promptly to symptomatic treatment
Onset of reaction:
Reduce UNITUXIN infusion rate to 50% of the previous rate and monitor closely.
After resolution:
Gradually increase infusion rate up to a maximum rate of 1.75 mg/m2/hour.
Prolonged or severe adverse reactions, such as mild bronchospasm without other symptoms, or angioedema that does not affect the airway
Onset of reaction:
Immediately interrupt UNITUXIN infusion.
After resolution:
If signs and symptoms resolve rapidly, resume UNITUXIN infusion at 50% of the previous rate and observe closely.
First recurrence:
Discontinue UNITUXIN infusion until the following day.
If symptoms resolve and continued treatment is warranted, premedicate with hydrocortisone 1 mg/kg (maximum dose 50 mg) intravenously and administer UNITUXIN at a rate of 0.875 mg/m2/hour in an intensive care unit.
Second recurrence:
Permanently discontinue UNITUXIN.
Neurological disorders of the eye (see 7 Warnings and Precautions)
Onset of reaction:
Discontinue UNITUXIN infusion and current UNITUXIN cycle until resolution.
After resolution:
In subsequent cycles, reduce the UNITUXIN dose by 50%.
First recurrence or if accompanied by visual impairment:
Permanently discontinue UNITUXIN.
Capillary leak syndrome (see 7 Warnings and Precautions)
Moderate to severe but not life-threatening capillary leak syndrome
Onset of reaction:
Immediately interrupt UNITUXIN infusion.
After resolution:
Resume UNITUXIN infusion at 50% of the previous rate.
Life-threatening capillary leak syndrome
Onset of reaction:
Discontinue UNITUXIN infusion for the current cycle.
After resolution:
In subsequent cycles, administer UNITUXIN infusion at 50% of the previous rate.
First recurrence:
Permanently discontinue UNITUXIN.
Hypotensiona requiring medical intervention (see 7 Warnings and Precautions)
Onset of reaction:
Interrupt UNITUXIN infusion.
After resolution:
Resume UNITUXIN infusion at 50% of the previous rate.
If blood pressure remains stable for at least 2 hours, increase the infusion rate as tolerated up to a maximum rate of 1.75 mg/m2/hour.
Severe systemic infection or sepsis
Onset of reaction:
Discontinue UNITUXIN until resolution of infection, and then proceed with subsequent cycles of therapy.
a Symptomatic hypotension, systolic blood pressure (SBP) less than lower limit of normal for age, or SBP decreased by more than 15% compared to baseline.
Special Populations
Renal Impairment: UNITUXIN has not been studied in patients with renal impairment.
Hepatic Impairment: UNITUXIN has not been studied in patients with hepatic impairment.
4.3. Reconstitution
Preparation for Intravenous Infusion
- Inspect visually for particulate matter and discoloration prior to administration. Do not administer UNITUXIN and discard the single-use vial if the solution is cloudy, has pronounced discoloration, or contains particulate matter.
- UNITUXIN is administered as a diluted intravenous infusion only. Aseptically withdraw the required volume of UNITUXIN from the single-use vial and inject into a 100 mL bag of 0.9% Sodium Chloride Injection, USP. Mix by gentle inversion. Do not shake.
- Discard unused contents of the vial (see 11 Storage, Stability, and Disposal).
Storage of Diluted Solution
- Store the diluted UNITUXIN solution under refrigeration (2°C to 8°C [36°F to 46°F]). Do not freeze.
- Discard diluted UNITUXIN solution 24 hours after preparation.
4.4. Administration
- Administer UNITUXIN only as an intravenous infusion diluted in 0.9% Sodium Chloride, USP (see 4.2 Recommended Dose and Dosage Adjustment). Do not administer UNITUXIN as an intravenous push or bolus.
- Once diluted, initiate infusion within 4 hours of preparation and discard 24 hours after preparation.
4.5. Missed Dose
If a dose of UNITUXIN is missed, the appointment should be rescheduled as soon as possible.
5. Overdose
UNITUXIN is only administered in a professional setting by experienced healthcare professionals. During clinical trials, no cases of UNITUXIN overdose have been reported. In clinical trials, scheduled UNITUXIN doses of up to 120 mg/m2 (60 mg/m2/day) have been administered with an adverse reaction profile similar to those described under 8 Adverse Reactions.
In case of overdose, patients should be closely monitored for signs or symptoms of adverse reactions and appropriate symptomatic treatment instituted.
For the most recent information in the management of a suspected drug overdose, contact your regional poison control centre or Health Canada’s toll-free number, 1-844 POISON-X (1-844-764-7669).
- 6. Dosage Forms, Strengths, Composition, and Packaging
To help ensure the traceability of biologic products, healthcare professionals should record both the brand name and the non-proprietary (active ingredient) name as well as other product-specific identifiers such as the Drug Identification Number (DIN) and the batch/lot number of the product supplied.
Table 5 Dosage Forms, Strengths, and Composition
Packaging
UNITUXIN is a sterile, preservative-free, clear and colorless to slightly opalescent solution, free from visible particles. UNITUXIN is supplied in a carton containing 1 (one) single-use vial.
7. Warnings and Precautions
See 3 Serious Warnings and Precautions Box.
General
UNITUXIN (Dinutuximab for injection) should be administered under the supervision of healthcare professionals experienced in the treatment of cancer.
Serious Infusion Reactions
Serious infusion reactions including anaphylaxis and serum sickness requiring urgent intervention, including blood pressure support, bronchodilator therapy, corticosteroids, infusion rate reduction, infusion interruption, or permanent discontinuation of UNITUXIN, included facial and upper airway edema, dyspnea, bronchospasm, stridor, urticaria, and hypotension. Infusion reactions generally occurred during or within 24 hours of completing the UNITUXIN infusion. Due to overlapping signs and symptoms, it was not possible to distinguish between infusion reactions and hypersensitivity reactions in some cases.
In study DIV-NB-301, severe (Grade 3 or 4) infusion reactions occurred in 35 (26%) patients in the UNITUXIN/13-cis-retinoic acid (RA) group compared to 1 (1%) patient receiving RA alone. Severe urticaria occurred in 17 (13%) patients in the UNITUXIN/RA group but did not occur in the RA group. Serious adverse reactions consistent with anaphylaxis and resulting in permanent discontinuation of UNITUXIN occurred in 2 (1%) patients in the UNITUXIN/RA group. Additionally, 1 (0.1%) patient had multiple cardiac arrests and died within 24 hours after having received UNITUXIN in study DIV-NB-302.
Prior to each UNITUXIN dose, administer required intravenous hydration and premedication with antihistamines, analgesics, and antipyretics (see 4.2 Recommended Dose and Dosage Adjustment). Monitor patients closely for signs and symptoms of infusion reactions during and for at least 4 hours following completion of each UNITUXIN infusion in a setting where cardiopulmonary resuscitation medication and equipment are available.
For mild to moderate infusion reactions, such as transient rash, fever, rigors, and localized urticaria, that respond promptly to antihistamines or antipyretics, decrease the UNITUXIN infusion rate and monitor
| Route of Administration | Dosage Form/ Strength/Composition | Non-Medicinal Ingredients |
| Intravenous infusion | solution / 17.5 mg dinutuximab per 5 mL (3.5 mg/mL) | histidine (20 mM), hydrochloric acid (to adjust pH), polysorbate 20 (0.05%), sodium chloride (150 mM), water for injection |
closely. Immediately interrupt the UNITUXIN infusion or permanently discontinue UNITUXIN and institute supportive management for severe or prolonged infusion reactions. Permanently discontinue UNITUXIN and institute supportive management for life-threatening infusion reactions (see 4.2 Recommended Dose and Dosage Adjustment).
Capillary Leak Syndrome
In study DIV-NB-301, severe (Grade 3 to 5) capillary leak syndrome occurred in 31 (23%) patients in the UNITUXIN/RA group and in no patients treated with RA alone. Additionally, capillary leak syndrome was reported as a serious adverse reaction in 9 (6%) patients in the UNITUXIN/RA group and in no patients treated with RA alone. Immediately interrupt the UNITUXIN infusion or discontinue UNITUXIN and institute supportive management in patients with symptomatic or severe capillary leak syndrome (see 4.2 Recommended Dose and Dosage Adjustment). Capillary leak syndrome is more likely when UNITUXIN is co-administered with interleukin-2 (IL-2). It is recommended to administer oral metolazone or intravenous furosemide every 6 to 12 hours as required. Supplemental oxygen, respiratory support, and albumin replacement therapy should be used as necessary according to clinical response.
Cardiovascular
Hypotension
In study DIV-NB-301, severe (Grade 3 or 4) hypotension occurred in 22 (16%) patients in the UNITUXIN/RA group compared to no patients in the RA group.
Prior to each UNITUXIN infusion, administer required intravenous hydration. Closely monitor blood pressure during UNITUXIN treatment. Immediately interrupt the UNITUXIN infusion or discontinue UNITUXIN and institute supportive management in patients with symptomatic hypotension, systolic blood pressure (SBP) less than lower limit of normal for age, or SBP that is decreased by more than 15% compared to baseline (see 4.2 Recommended Dose and Dosage Adjustment).
Endocrine and Metabolism
Electrolyte Abnormalities
Electrolyte abnormalities occurring in at least 25% of patients who received UNITUXIN/RA in study DIV-NB-301 included hyponatremia, hypokalemia, and hypocalcemia. Severe (Grade 3 or 4) hypokalemia and hyponatremia occurred in 37% and 23% of patients in the UNITUXIN/RA group, respectively, compared to 2% and 4% of patients in the RA group. In a study of a related anti-GD2 antibody conducted in 12 adult patients with metastatic melanoma, 2 (13%) patients developed syndrome of inappropriate antidiuretic hormone secretion resulting in severe hyponatremia. Monitor serum electrolytes daily during therapy with UNITUXIN.
Neurologic
Pain
In study DIV-NB-301, 114 (85%) patients treated in the UNITUXIN/RA group experienced pain despite pre-treatment with analgesics, including morphine sulfate infusion. Severe (Grade 3) pain occurred in 68 (51%) patients in the UNITUXIN/RA group compared to 5 (5%) patients in the RA group. Pain typically occurred during the UNITUXIN infusion and was most commonly reported as abdominal pain, generalized pain, extremity pain, back pain, neuralgia, musculoskeletal chest pain, and arthralgia.
Premedicate with analgesics, including intravenous opioids, prior to each dose of UNITUXIN and continue analgesics until 2 hours following completion of the UNITUXIN infusion (see 4.2 Recommended Dose and Dosage Adjustment).
For severe pain, decrease the UNITUXIN infusion rate to 0.875 mg/m2/hour. Discontinue UNITUXIN if pain is not adequately controlled despite infusion rate reduction and institution of maximum supportive measures (see 4.2 Recommended Dose and Dosage Adjustment).
Peripheral Neuropathy
In study DIV-NB-301, severe (Grade 3) peripheral sensory neuropathy occurred in 2 (1%) patients and severe peripheral motor neuropathy occurred in 2 (1%) patients in the UNITUXIN/RA group. No patients treated with RA alone experienced severe peripheral neuropathy. The duration and reversibility of peripheral neuropathy occurring in study DIV-NB-301 was not documented. In study DIV-NB-303, no patients experienced peripheral motor neuropathy. Among the 9 (9%) patients who experienced peripheral sensory neuropathy of any severity, the median (min, max) duration of peripheral sensory neuropathy was 9 (3, 163) days.
In a study of a related anti-GD2 antibody conducted in 12 adult patients with metastatic melanoma, 2 (13%) patients developed severe motor neuropathy. One patient developed lower extremity weakness and inability to ambulate that persisted for approximately 6 weeks. Another patient developed severe lower extremity weakness resulting in an inability to ambulate without assistance that lasted for approximately 16 weeks, and neurogenic bladder that lasted for approximately 3 weeks. Complete resolution of motor neuropathy was not documented in this case.
Permanently discontinue UNITUXIN in patients with peripheral motor neuropathy of Grade 2 or greater severity, Grade 3 sensory neuropathy that interferes with daily activities for more than 2 weeks, or Grade 4 sensory neuropathy (see 4.2 Recommended Dose and Dosage Adjustment).
Transverse Myelitis
Transverse myelitis has occurred in patients treated with UNITUXIN. Promptly evaluate any patient with signs or symptoms of transverse myelitis, such as weakness, paresthesia, sensory loss, or incontinence. Permanently discontinue UNITUXIN in patients who develop transverse myelitis (see 4.2 Recommended Dose and Dosage Adjustment and 8.5 Post-Market Adverse Reactions).
Reversible Posterior Leukoencephalopathy Syndrome
Reversible Posterior Leukoencephalopathy Syndrome (RPLS) has occurred in patients treated with UNITUXIN. Institute appropriate medical treatment and permanently discontinue UNITUXIN in patients with signs and symptoms of RPLS (eg, severe headache, hypertension, visual changes, lethargy, or seizures) (see 4.2 Recommended Dose and Dosage Adjustment and 8.5 Post-Market Adverse Reactions).
Ophthalmologic
Neurological Disorders of the Eye
Neurological disorders of the eye experienced by 2 or more patients treated with UNITUXIN in studies DIV-NB-301, DIV-NB-302, or DIV-NB-303 included blurred vision, photophobia, mydriasis, fixed or unequal pupils, optic nerve disorder, eyelid ptosis, and papilledema.
In study DIV-NB-301, 3 (2%) patients in the UNITUXIN/RA group experienced blurred vision, compared to no patients in the RA group. Diplopia, mydriasis, and unequal pupillary size occurred in 1 patient each in the UNITUXIN/RA group, compared to no patients in the RA group. The duration of eye disorders occurring in study DIV-NB-301 was not documented. In study DIV-NB-303, eye disorders occurred in 16 (15%) patients, and in 3 (3%) patients resolution of the eye disorder was not documented. Among the cases with documented resolution, the median (min, max) duration of eye disorders was 4 days (0, 221 days).
Interrupt UNITUXIN infusion in patients experiencing persistent dilated pupil with sluggish light reflex or other visual disturbances. Discontinue the current UNITUXIN cycle. Upon resolution, if continued treatment with UNITUXIN is warranted, then decrease the UNITUXIN infusion dose by 50% in future cycles. Permanently discontinue UNITUXIN in patients with recurrent signs or symptoms of an eye disorder following dose reduction and in patients who experience loss of vision (see 4.2 Recommended Dose and Dosage Adjustment).
Renal
Atypical Hemolytic Uremic Syndrome
Hemolytic uremic syndrome in the absence of documented infection and resulting in renal insufficiency, electrolyte abnormalities, anemia, and hypertension occurred in 2 patients enrolled in study DIV-NB-302 following receipt of the first cycle of UNITUXIN. Atypical hemolytic uremic syndrome recurred following rechallenge with UNITUXIN in 1 patient. Permanently discontinue UNITUXIN and institute supportive management for signs of hemolytic uremic syndrome (see 4.2 Recommended Dose and Dosage Adjustment and 8.5 Post-Market Adverse Reactions).
Prolonged Urinary Retention
Urinary retention that persists for weeks to months following discontinuation of opioids has occurred in patients treated with UNITUXIN. Permanently discontinue UNITUXIN in patients with urinary retention that does not resolve following discontinuation of opioids (see 4.2 Recommended Dose and Dosage Adjustment).
Reproductive Health: Female and Male Potential
Embryo-Fetal Toxicity
Based on its mechanism of action, UNITUXIN may cause fetal harm when administered to a pregnant woman. Advise pregnant women of the potential risk to a fetus.
Advise females of reproductive potential to use effective contraception during treatment, and for 2 months after the last dose of UNITUXIN (see 7.1 Special Populations and 10 Clinical Pharmacology).
Fertility
There are no data on the potential effects of UNITUXIN on fertility in humans.
7.1. Special Populations
7.1.1. Pregnancy
Based on its mechanism of action, UNITUXIN may cause fetal harm when administered to a pregnant woman (see 10 Clinical Pharmacology). There are no studies in pregnant women and no reproductive studies in animals to inform the drug-associated risk. Monoclonal antibodies are transported across the placenta in a linear fashion as pregnancy progresses, with the largest amount transferred during the third trimester. Advise pregnant women of the potential risk to a fetus. The background risk of major birth defects and miscarriage for the indicated population is unknown. However, the background risk in the general population of major congenital anomalies is ~4% and still births is <1% in Canada.
Females of Reproductive Potential: UNITUXIN may cause fetal harm. Advise females of reproductive potential to use effective contraception during treatment and for 2 months after the last dose of UNITUXIN (see 7 Warnings and Precautions, Reproductive Health and 10 Clinical Pharmacology).
7.1.2. Breastfeeding
There is no information available on the presence of dinutuximab in human breast milk, the effects of the drug on the breastfed infant, or the effects of the drug on breast milk production. However, human immunoglobulin G (IgG) is present in human breast milk. Because of the potential for serious adverse reactions in a breastfed infant, advise a nursing woman to discontinue breastfeeding during treatment with UNITUXIN.
7.1.3. Pediatrics
Pediatrics (≤18 years of age): The safety and effectiveness of UNITUXIN as part of multiagent, multimodality therapy have been established in pediatric patients with high-risk neuroblastoma. See 8 Adverse Reactions, 10 Clinical Pharmacology, and 14 Clinical Trials sections for details regarding supporting evidence.
7.1.4. Geriatrics
The safety and effectiveness of UNITUXIN in geriatric patients have not been established.
8. Adverse Reactions
8.1. Adverse Reaction Overview
The data described below reflect exposure to UNITUXIN at the recommended dose and schedule in 1021 patients with high-risk neuroblastoma enrolled in an open-label, randomized trial (study DIV-NB-301), or single-arm clinical trials (studies DIV-NB-302 and DIV-NB-303). Prior to enrollment, patients received therapy consisting of induction combination chemotherapy, maximum feasible surgical resection, myeloablative consolidation chemotherapy followed by autologous stem cell transplant, and radiation therapy to residual soft tissue disease. Patients received UNITUXIN in combination with GM-CSF, IL-2, and RA. Treatment commenced within 95 days post autologous stem cell transplant in study DIV-NB-301, within 210 days of autologous stem cell transplant in study DIV-NB-302, and within 110 days of autologous stem cell transplant in study DIV-NB-303.
UNITUXIN has been associated with neurologic adverse reactions thought to be resulting from the binding to GD2 not located at the tumor site (see 7 Warnings and Precautions for guidance). Most of these adverse reactions, including transverse myelitis, resolved following discontinuation of UNITUXIN and initiation of appropriate medical therapy.
8.2. Clinical Trial Adverse Reactions
Because clinical trials are conducted under very specific conditions, the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
8.2.1. Clinical Trial Adverse Reactions – Pediatrics
Study DIV-NB-301
In a randomized, open-label, multicenter study (DIV-NB-301), 134 patients received UNITUXIN in combination with GM-CSF, IL-2, and RA (UNITUXIN/RA group), including 109 randomized patients and 25 patients with biopsy-proven residual disease who were non-randomly assigned to receive UNITUXIN. A total of 106 randomized patients received RA alone (RA group) (see 4 Dosage and Administration and 14 Clinical Trials). Patients had a median age at enrollment of 3.8 years (range: 0.94 to 15.3 years), and were predominantly male (60%) and White (82%). In study DIV-NB-301, adverse reactions of Grade 3 or greater severity were comprehensively collected, but adverse reactions of Grade 1 or 2 severity were collected sporadically and laboratory data were not comprehensively collected.
Approximately 71% of patients in the UNITUXIN/RA group and 77% of patients in the RA group completed planned treatment. The most common reason for premature discontinuation of study therapy was adverse reactions in the UNITUXIN/RA group (19%) and progressive disease (17%) in the RA group.
The most common adverse drug reactions (≥25%) in the UNITUXIN/RA group were pain, pyrexia, thrombocytopenia, lymphopenia, infusion reactions, hypotension, hyponatremia, increased alanine aminotransferase, anemia, vomiting, diarrhea, hypokalemia, capillary leak syndrome, neutropenia, urticaria, hypoalbuminemia, increased aspartate aminotransferase, and hypocalcemia. The most common serious adverse reactions (≥5%) in the UNITUXIN/RA group were infections, infusion reactions, hypokalemia, hypotension, pain, fever, and capillary leak syndrome.
Study DIV-NB-302
Study DIV-NB-302 was a single-arm, multicenter expanded access trial that enrolled patients with high-risk neuroblastoma (N=783). The reported adverse event profile of UNITUXIN in study DIV-NB-302 was similar to that observed in study DIV-NB-301.
Study DIV-NB-303
Study DIV-NB-303 was a multicenter, single-arm safety study of UNITUXIN in combination with GM-CSF, IL-2, and RA. In study DIV-NB-303, adverse events of all Common Terminology Criteria for Adverse Events (CTCAE) grades and laboratory data were systematically and comprehensively collected. Of 104 patients enrolled and treated in study DIV-NB-303, 77% of patients completed study therapy. In general, the adverse reaction profile of UNITUXIN observed in study DIV-NB-303 was similar to that observed in studies DIV-NB-301 and DIV-NB-302. The following adverse reactions not previously reported in study DIV-NB-301 were reported in at least 10% of patients in study DIV-NB-303: nasal congestion (20%) and wheezing (15%).
Table 6 lists the adverse reactions, including laboratory values, reported in at least 2% of patients from study DIV-NB-301.
Table 6 Adverse Reactions Occurring in at Least 2% of Subjects in the Dinutuximab for injection Group
| Adverse Reaction | Dinutuximab for injection Group DIV-NB-301 Randomized (N=141) % | Control Group DIV-NB-301 Randomized (N=108) % |
|---|---|---|
| Adverse Reaction | Dinutuximab for injection Group DIV-NB-301 Randomized (N=141) % | Control Group DIV-NB-301 Randomized (N=108) % |
| Adverse Reaction | Dinutuximab for injection Group DIV-NB-301 Randomized (N=141) % | Control Group DIV-NB-301 Randomized (N=108) % |
| Adverse Reaction | Dinutuximab for injection Group DIV-NB-301 Randomized (N=141) % | Control Group DIV-NB-301 Randomized (N=108) % |
| Blood and Lymphatic System Disorders | ||
| Anemia | 53.9 | 21.3 |
| Febrile neutropenia | 3.5 | 0 |
| Cardiac Disorders | ||
| Sinus tachycardia | 15.6 | 0 |
| Tachycardia | 9.2 | 0.9 |
| Supraventricular tachycardia | 2.1 | 0 |
| Ear and Labyrinth Disorders | ||
| Hearing impaired | 5.7 | 5.6 |
| Endocrine Disorders | ||
| Hypothyroidism | 3.5 | 1.9 |
| Hyperthyroidism | 2.8 | 0 |
| Eye Disorders | ||
| Vision blurred | 2.1 | 0 |
| Photophobia | 2.8 | 1.9 |
| Gastrointestinal Disorders | ||
| Abdominal pain | 57.4 | 8.3 |
| Vomiting | 43.3 | 18.5 |
| Diarrhea | 44.0 | 14.8 |
| Nausea | 9.9 | 2.8 |
| Constipation | 7.1 | 1.9 |
| Cheilitis | 4.3 | 3.7 |
| Abdominal pain upper | 4.3 | 0.9 |
| Stomatitis | 3.5 | 0.9 |
| Lower gastrointestinal hemorrhage | 2.1 | 0 |
| General Disorders and Administration Site Conditions | ||
| Pyrexia | 73.0 | 26.9 |
| Pain | 51.8 | 5.6 |
| Face edema | 12.1 | 0 |
| Fatigue | 6.4 | 1.9 |
| Irritability | 4.3 | 0 |
| Edema peripheral | 6.4 | 0 |
| Chills | 7.8 | 0 |
| Injection site reaction | 4.3 | 0 |
| Edema | 6.4 | 0 |
| Non-cardiac chest pain | 4.3 | 0 |
| Immune System Disorders | ||
| Hypersensitivity | 56.7 | 7.4 |
| Anaphylactic reaction | 26.2 | 0.9 |
| Cytokine release syndrome | 4.3 | 0 |
| Infections and Infestations | ||
| Device related infection | 17.7 | 10.2 |
| Infection susceptibility increased | 9.9 | 5.6 |
| Enterocolitis infection | 7.1 | 1.9 |
| Urinary tract infection | 2.8 | 2.8 |
| Staphylococcal bacteremia | 10.6 | 3.7 |
| Upper respiratory tract infection | 2.1 | 2.8 |
| Lung infection | 2.1 | 1.9 |
| Otitis media | 3.5 | 1.9 |
| Bacteremia | 2.1 | 0.9 |
| Bacillus infection | 3.5 | 0.9 |
| Klebsiella bacteremia | 3.5 | 0.9 |
| Clostridium difficile colitis | 2.1 | 0.9 |
| Herpes zoster | 3.5 | 0.9 |
| Streptococcal bacteremia | 2.1 | 0 |
| Osteomyelitis | 2.1 | 0 |
| Wound infection | 2.1 | 0 |
| Escherichia urinary tract infection | 2.1 | 0 |
| Investigations | ||
| Platelet count decreased | 66.0 | 40.7 |
| Lymphocyte count decreased | 67.4 | 35.2 |
| Alanine aminotransferase increased | 53.9 | 30.6 |
| White blood cell count decreased | 37.6 | 14.8 |
| Neutrophil count decreased | 41.8 | 15.7 |
| Aspartate aminotransferase increased | 27.0 | 6.5 |
| Gamma-glutamyl transferase increased | 4.3 | 0 |
| Weight increased | 10.6 | 0 |
| Blood creatinine increased | 14.9 | 5.6 |
| Blood alkaline phosphatase increased | 6.4 | 6.5 |
| Blood bilirubin increased | 8.5 | 4.6 |
| Weight decreased | 2.8 | 0 |
| Blood culture positive | 2.8 | 0.9 |
| Metabolism and Nutrition Disorders | ||
| Hypoalbuminemia | 34.0 | 2.8 |
| Hyponatremia | 56.7 | 12.0 |
| Hypokalemia | 43.3 | 4.6 |
| Hypocalcemia | 25.5 | 0 |
| Hypertriglyceridemia | 17.0 | 11.1 |
| Hyperglycemia | 18.4 | 3.7 |
| Hypophosphatemia | 20.6 | 2.8 |
| Decreased appetite | 14.9 | 4.6 |
| Hypomagnesemia | 12.1 | 0.9 |
| Hyperkalemia | 5.7 | 3.7 |
| Hypoglycemia | 3.5 | 0 |
| Hypercalcemia | 7.8 | 7.4 |
| Acidosis | 5.7 | 0 |
| Hypermagnesemia | 3.5 | 0.9 |
| Dehydration | 3.5 | 1.9 |
| Hypernatremia | 2.8 | 0.9 |
| Musculoskeletal and Connective Tissue Disorders | ||
| Pain in extremity | 17.0 | 3.7 |
| Back pain | 12.1 | 0.9 |
| Neck pain | 4.3 | 0 |
| Musculoskeletal chest pain | 7.8 | 1.9 |
| Myalgia | 4.3 | 0.9 |
| Arthralgia | 6.4 | 1.9 |
| Bone pain | 4.3 | 0.9 |
| Nervous System Disorders | ||
| Neuralgia | 9.2 | 0 |
| Headache | 7.8 | 3.7 |
| Peripheral sensory neuropathy | 7.1 | 0.9 |
| Peripheral motor neuropathy | 6.4 | 3.7 |
| Psychiatric Disorders | ||
| Agitation | 4.3 | 1.9 |
| Psychotic disorder | 2.1 | 0 |
| Euphoric mood | 2.1 | 0 |
| Renal and Urinary Disorders | ||
| Proteinuria | 14.9 | 2.8 |
| Hematuria | 7.8 | 0.9 |
| Urinary retention | 7.1 | 0 |
| Urinary tract obstruction | 2.1 | 0 |
| Respiratory, Thoracic, and Mediastinal Disorders | ||
| Hypoxia | 26.2 | 1.9 |
| Cough | 9.9 | 1.9 |
| Dyspnea | 5.7 | 0.9 |
| Bronchospasm | 5.0 | 0 |
| Oropharyngeal pain | 3.5 | 0 |
| Rhinitis allergic | 2.1 | 0.9 |
| Epistaxis | 2.8 | 3.7 |
| Skin and Subcutaneous Tissue Disorders | ||
| Urticaria | 44.7 | 2.8 |
| Pruritus | 10.6 | 0.9 |
| Dry skin | 16.3 | 14.8 |
| Rash papular | 8.5 | 4.6 |
| Erythema multiforme | 5.0 | 5.6 |
| Vascular Disorders | ||
| Hypotension | 63.1 | 2.8 |
| Capillary leak syndrome | 41.8 | 0.9 |
| Hypertension | 13.5 | 6.5 |
| Flushing | 2.1 | 0 |
8.3. Less Common Clinical Trial Adverse Reactions
8.3.1. Less Common Clinical Trial Adverse Reactions – Pediatrics
The following events occur with a frequency below the cut-off for common and very common adverse reactions (<2%):
- Blood and Lymphatic: Atypical hemolytic uremic syndrome
- Eye: Mydriasis, Unequal pupils
- Immune System: Serum sickness
- Infections and Infestations: Sepsis
- Neurologic/Nervous System: Myelitis, Reversible Posterior Leukoencephalopathy Syndrome
- Hemorrhages, including gastrointestinal/gastric hemorrhage, hematochezia, rectal hemorrhage, hematemesis, upper gastrointestinal hemorrhage, hemorrhage urinary tract, renal hemorrhage, respiratory tract hemorrhage, disseminated intravascular coagulation, and catheter site hemorrhage
8.5. Post-Market Adverse Reactions
In addition to the adverse reactions discussed in the previous sections, the following adverse reactions have been identified during post-approval use of UNITUXIN. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure.
- Neurotoxicity, including transverse myelitis
- Reversible Posterior Leukoencephalopathy Syndrome
- Atypical hemolytic uremic syndrome
9. Drug Interactions
No drug-drug interaction studies have been conducted with dinutuximab.
10. Clinical Pharmacology
10.1. Mechanism of Action
Dinutuximab binds to the glycolipid GD2. This glycolipid is expressed on neuroblastoma cells and on normal cells of neuroectodermal origin, including the central nervous system and peripheral nerves. Dinutuximab binds to cell surface GD2 and induces cell lysis of GD2-expressing cells through antibody-dependent cell-mediated cytotoxicity (ADCC) and complement-dependent cytotoxicity (CDC).
This binding to normal cells of neuroectodermal origin has been proposed as an explanation for the pain and neurotoxicity observed in the clinic. Non-clinical studies suggest that dinutuximab-induced neuropathic pain is mediated by binding of the antibody to the GD2 antigen located on the surface of peripheral nerve fibers and myelin and subsequent induction of CDC and ADCC activity.
10.2. Pharmacodynamics
Non-clinical studies demonstrate that dinutuximab-induced neurotoxicity is likely due to the induction of mechanical allodynia that may be mediated by reactivity of dinutuximab with GD2 antigen located on the surface of peripheral nerve fibers and/or myelin.
Severe allergic reactions are more likely when dinutuximab is co-administered with IL-2. Therefore, caution should be taken when both medicinal products are combined.
Cardiovascular events, including increased heart rate and blood pressure, were observed in clinical studies; however, no effects on QTc interval or other cardiac monitoring parameters were identified in the cardiovascular sub-study of DIV-NB-302.
10.3. Pharmacokinetics
Table 7 Summary of UNITUXIN Pharmacokinetic Parameters in High-Risk Pediatric Neuroblastoma Patients
| Cmax | Tmax | t½ (h) | AUC0-∞ | CL | Vd | |
|---|---|---|---|---|---|---|
| Multiple Dose Mean | 11.45 mcg/mL | 74.72 h | 197.5 h | 1822 mcg.h/mL | 0.026 L/h | 7.2 L |
Absorption
No formal metabolism studies have been conducted. Absorption is considered to be 100% of the administered dose.
Distribution
The pharmacokinetics of dinutuximab were evaluated by a non-compartmental pharmacokinetic analysis in a clinical study of UNITUXIN in combination with GM-CSF, IL-2, and RA. In this study, 27 children with high-risk neuroblastoma (age: 3.9±1.9 years) received up to 5 cycles of UNITUXIN at 17.5 mg/m2/day as an intravenous infusion over 10 to 20 hours for 4 consecutive days every 28 days. The observed maximum plasma dinutuximab concentration (Cmax) was 11.45 mcg/mL (20%, coefficient of variation [CV]). The mean volume of distribution at steady state (Vdss) was 7.2 L (56%).
Metabolism
Dinutuximab is a protein for which the expected metabolic pathway is degradation to small peptides and individual amino acids by ubiquitous proteolytic enzymes. Classical biotransformation studies have not been performed.
Elimination
The clearance was 0.026 L/hour (0.63 L/day) and increased with body size. The terminal half-life was 197.5 hours (8.23 days). A covariate analysis with the population pharmacokinetic analysis conducted on all clinical data available suggests that the disposition of dinutuximab is not altered by age, race, gender, concomitant medications (IL-2, GM-CSF) and the presence of capillary leak syndrome, or renal or hepatic impairment. However, the presence of HACA appears to increase the clearance parameter in the model of dinutuximab by approximately 60%.
Special Populations and Conditions
- Pediatrics: Health Canada has authorized an indication for pediatric use (see 7.1.3 Pediatrics and 14 Clinical Trials).
- Geriatrics: No pharmacokinetic studies were conducted in geriatric patients (see 7.1.4 Geriatrics). The safety and effectiveness of UNITUXIN in geriatric patients have not been established.
- Pregnancy and Breastfeeding: No formal pharmacokinetic studies were conducted in patients who were pregnant or breastfeeding (see 7.1.1 Pregnancy and 7.1.2 Breastfeeding).
- Hepatic Insufficiency: No formal pharmacokinetic studies were conducted in patients with hepatic impairment.
- Renal Insufficiency: No formal pharmacokinetic studies were conducted in patients with renal impairment.
10.4. Immunogenicity
All therapeutic proteins have the potential for immunogenicity. The detection of antibody formation is highly dependent on the sensitivity and specificity of the assay. Additionally, the observed incidence of antibody (including neutralizing antibody) positivity in an assay may be influenced by several factors, including assay methodology, sample handling, timing of sample collection, concomitant medications, and underlying disease. For these reasons, comparison of the incidence of antibodies in the studies described below with the incidence of antibodies in other studies or to other products may be misleading.
In clinical studies of pediatric patients treated with dinutuximab, 86 of 418 (20.6%) tested positive for anti-dinutuximab binding antibodies (ADA). Of the 86 ADA positive patients, 45 (52.3%) tested positive for neutralizing antibodies. Plasma concentrations of dinutuximab, especially trough levels, tended to be lower in patients with human anti-chimeric antibodies (HACA). In light of insufficient data, it is unknown whether the presence of neutralizing antibodies impacts drug efficacy and/or safety.
- 11. Storage, Stability, and Disposal
Store UNITUXIN vials under refrigeration at 2°C to 8°C (36°F to 46°F) until time of use. DO NOT FREEZE OR SHAKE the vial. Keep the vial in the outer carton in order to protect from light. Discard unused contents of the vial.
Store the diluted UNITUXIN solution under refrigeration (2°C to 8°C [36°F to 46°F]). Discard diluted UNITUXIN solution 24 hours after preparation.
Any unused medicinal product or waste material should be disposed of in accordance with local requirements.
12. Special Handling Instructions
Avoid contact with skin or eyes. For skin contact, wash affected area immediately with soap and water and contact physician. For eye contact, flush eyes immediately with large amounts of water and contact physician.
Part 2: Scientific Information
13. Pharmaceutical Information
Drug Substance
Non-proprietary name of the drug substance: Dinutuximab
Chemical name: Immunoglobulin G1, anti-(ganglioside GD2) (human-Mus musculus
monoclonal ch14.18 heavy chain), disulfide with human-Mus musculus
monoclonal ch14.18 light chain, dimer
Molecular formula and molecular mass: The molecular weight of dinutuximab is in the range of 147,625 Da to 150,744 Da.
Structural formula: The heavy chain has 443 amino acids and 1 glycosylation site (Asn 293), molecular weight 49750 Da to 50075.4 Da. The light chain has 220 amino acids and a molecular weight of 24070.9 Da.
Physicochemical properties: Dinutuximab is a glycosylated chimeric IgG1 human/mouse monoclonal antibody (mAb), produced in a murine myeloma cell (SP2/0 hybridoma cell). It incorporates human constant regions for the heavy chain IgG1 and the kappa light chain, along with the murine variable regions targeted specifically against human disialoganglioside (GD2) to which dinutuximab binds. Dinutuximab is a clear, colorless, to slightly opalescent liquid.
Pharmaceutical standard: Professed
Product Characteristics:
UNITUXIN is a glycosylated chimeric IgG1 human/mouse monoclonal antibody and is produced in murine myeloma cells (SP2/0 hybridoma cell) by recombinant DNA technology.
14. Clinical Trials
14.1. Clinical Trials by Indication
The safety and effectiveness of UNITUXIN was evaluated in a randomized, open-label, multicenter trial conducted in pediatric patients with high-risk neuroblastoma (study DIV-NB-301). All patients had received prior therapy consisting of induction combination chemotherapy, maximum feasible surgical resection, myeloablative consolidation chemotherapy followed by autologous stem cell transplant, and radiation therapy to residual soft tissue disease. Patients were randomized between Day 50 and Day 77 post-autologous stem cell transplantation.
Trial Design and Study Demographics
Table 8 Summary of Patient Demographics for Pivotal and Main Supportive Clinical Trials in Pediatrics for Neuroblastoma
| Study # | Study design | Dosage, route of administration and duration | Study subjects (n) | Mean age in years (Range in years) |
|---|---|---|---|---|
| Study # | Study design | Dosage, route of administration and duration | Study subjects (n) | Mean age in years (Range in years) |
| DIV-NB-301 (ANBL-0032) | Phase III randomized study of chimeric antibody 14.18 UNITUXIN (Dinutuximab for injection) in high-risk neuroblastoma following myeloablative therapy and autologous stem cell rescue | UNITUXIN: 25 mg/m2/day IV over 5 to 20 hours x 4 days Courses 1-5 GM-CSF: 250 mcg/m2/day IV or SC over 2 hours x 14 days Courses 1, 3, and 5 IL-2: up to 4.5 MIU/m2/day IV x 8 days Courses 2 and 4 RA: 80 mg/m2/dose BID PO x 14 days, Courses 1-6 | Neuroblastoma: 251 enrolled, 226 randomized, of which 113 were assigned to dinutuximab immunotherapy + RA, 113 were assigned to RA only, and 25 were non-randomly assigned to dinutuximab immunotherapy (as of 13 January 2009 data cut) | 4.3 (0.94 to 15.29) |
| DIV-NB-302 (ANBL-0032) | Open-label, non-randomized, efficacy and safety study of UNITUXIN (Dinutuximab for injection) + GM-CSF + IL-2 + RA in patients with neuroblastoma | UNITUXIN: 25 mg/m2/day IV over 10 to 20 hours x 4 days Courses 1-5 GM-CSF: 250 mcg/m2/day IV or SC over 2 hours x 14 days Courses 1, 3, and 5 IL-2: up to 4.5 MIU/m2/day IV x 8 days Courses 2 and 4 RA: 80 mg/m2/dose BID PO x 14 days Courses 1-6 | 838 subjects enrolled per data cut from 31 December 2013 | 4.5 (0.75 to 29.4) |
| DIV-NB-303 (ANBL-0931) | Open-label, safety study of UNITUXIN (Dinutuximab for injection) + GM-CSF + IL-2 + RA in patients with neuroblastoma | UNITUXIN: 25 mg/m2/day IV over 10 to 20 hours x 4 days Courses 1-5 GM-CSF: 250 mcg/m2/day IV or SC over 2 hours x 14 days Courses 1, 3, and 5 IL-2: up to 4.5 MIU/m2/day IV x 8 days Courses 2 and 4 RA: 80 mg/m2/dose BID PO x 14 days Courses 1-6 | 105 enrolled, 104 treated | 4.8 (1 to 27) |
| DIV-NB-201 | Open-label randomized, comparative pharmacokinetic study in patients with neuroblastoma | UNITUXIN: 25 mg/m2/day or 17.5 mg/m2/day IV over 10 to 20 hours x 4 days Courses 1-5a GM-CSF: 250 mcg/m2/day IV or SC over 2 hours x 14 days Courses 1, 3, and 5 IL-2: up to 4.5 MIU/m2/day IV x 8 days Courses 2 and 4 RA: 80 mg/m2/dose BID PO x 14 days, Courses 1-6 | 28 | 3.9 (0.76 to 8.8) |
| BID, twice daily; CSR, clinical study report; GM-CSF, granulocyte-macrophage colony-stimulating factor; IL-2, interleukin-2; IV, intravenous(ly); PO, by mouth; RA, 13-cis-retinoic acid; SC, subcutaneous a Study DIV-NB-201 was designed to evaluate the comparability of 2 dinutuximab products: the product used in clinical trials at 25 mg/m2/day and the other intended for commercial production at 17.5 mg/m2/day. The results demonstrated comparability between the 2 products at these doses. | ||||
Table 9 Summary of Baseline Demographics for ITT Population of DIV-NB-301
| Characteristics | RA Alone (n=113) | Immunotherapy + RA (n=113) | Overall (n=226) |
|---|---|---|---|
| Characteristics | RA Alone (n=113) | Immunotherapy + RA (n=113) | Overall (n=226) |
Age at Enrollment (years): Mean (range) | 4.0 (0.94-13.29) | 4.3 (0.95-15.29) | 4.1 (0.94-15.29) |
| Age at Enrollment Category: n (%) | |||
| Adolescent (12-18 years) | 1 (0.9%) | 4 (3.5%) | 5 (2.2%) |
| Child (2-12 years) | 94 (83.2%) | 97 (85.8%) | 191 (84.5%) |
| Infant/Toddler (28 days to 2 years) | 18 (15.9%) | 12 (10.6%) | 30 (13.3%) |
| Gender: Male/Female (%) | 57/43 | 63/37 | 60/40 |
| Ethnicity: n (%) | |||
| Hispanic or Latino | 11 (10%) | 11 (10%) | 22 (10%) |
| Not Hispanic or Latino | 96 (85%) | 100 (89%) | 196 (87%) |
| Unknown | 6 (5%) | 2 (2%) | 8 (4%) |
| Race: n (%) | |||
| White | 90 (80%) | 95 (84%) | 185 (82%) |
| Black or African American | 8 (7%) | 8 (7%) | 16 (7%) |
| Asian | 4 (4%) | 2 (2%) | 6 (3%) |
| Native Hawaiian or Other Pacific Islander | 2 (2%) | 0 | 2 (1%) |
| Multiple | 2 (2%) | 1 (1%) | 3 (1%) |
| Other/Unknown | 7 (6%) | 7 (6%) | 14 (6%) |
| Pre-ASCT Response: n (%) | |||
| CR | 38 (34%) | 40 (35%) | 78 (35%) |
| VGPR | 49 (43%) | 47 (42%) | 96 (43%) |
| PR | 26 (23%) | 26 (23%) | 52 (23%) |
| Number of Days Post-Final ASCT: mean ± SD | 77 ± 12.0 | 75 ± 8.7 | 76 ± 10.5 |
| INSS Stage: n (%) | |||
| Stage 2a | 0 | 4 (4%) | 4 (2%) |
| Stage 3 | 16 (14%) | 10 (9%) | 26 (12%) |
| Stage 4 | 92 (81%) | 89 (79%) | 181 (80%) |
| Stage 4s | 0 | 2 (2%) | 2 (1%) |
| MYCN: n (%) | |||
| Amplified | 45 (40%) | 36 (32%) | 81 (36%) |
| Non-amplified | 51 (45%) | 52 (46%) | 103 (46%) |
| Missing | 17 (15%) | 25 (22%) | 42 (19%) |
| DNA ploidy: n (%) | |||
| Diploid | 46 (41%) | 35 (31%) | 81 (36%) |
| Hyperdiploid | 48 (43%) | 49 (43%) | 97 (43%) |
| Missing | 19 (17%) | 29 (26%) | 48 (21%) |
| Tumor Histology: n (%) | |||
| Favorable | 5 (4%) | 4 (4%) | 9 (4%) |
| Unfavorable | 81 (72%) | 68 (60%) | 149 (66%) |
| Missing | 27 (24%) | 41 (36%) | 68 (30%) |
Baseline Absolute Phagocyte Count (count/mcL): Mean ± SD | 17153 ± 74215 | 11767 ± 50411 | 14460 ± 63356 |
Patients were required to have achieved at least a partial response prior to autologous stem cell transplantation, have no evidence of disease progression following completion of front-line multimodality therapy, have adequate pulmonary function (no dyspnea at rest and peripheral arterial oxygen saturation of at least 94% on room air), adequate phagocyte count (≥1000 cells/mcL), adequate hepatic function (total bilirubin <1.5 x the upper limit of normal and alanine aminotransferase [ALT] <5 x the upper limit of normal), adequate cardiac function (shortening fraction of >30% by echocardiogram, or if shortening fraction abnormal, ejection fraction of 55% by gated radionuclide study), and adequate renal function (glomerular filtration rate at least 70 mL/min/1.73 m2). Patients with systemic infections or a requirement for concomitant systemic corticosteroids or immunosuppressant usage were not eligible for enrollment.
Patients randomized to the UNITUXIN/RA arm received up to 5 cycles of UNITUXIN in combination with GM-CSF (Table 10) or IL-2 (Table 11) plus RA, followed by 1 cycle of RA alone. Patients randomized to the RA arm received 6 cycles of RA. UNITUXIN was administered at a dose of 17.5 mg/m2/day (equivalent to 25 mg/m2/day of clinical trials material – see reference to this study and footnote “a” in Table 8) on 4 consecutive days. Patients in both treatment arms received 6 cycles of RA at a dose of 160 mg/m2/day orally (for patients weighing >12 kg) or 5.33 mg/kg/day (for patients weighing ≤12 kg) in 2 divided doses for 14 consecutive days.
Table 10 Dosage Regimen in the UNITUXIN/RA Arm for Cycles 1, 3, and 5
| Cycle Day | 1 | 2 | 3 | 4 | 5 | 6 | 7 | 8 | 9 | 10 | 11 | 12 | 13 | 14 | 15-24 |
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| GM-CSFa | X | X | X | X | X | X | X | X | X | X | X | X | X | X | |
| UNITUXINb | X | X | X | X | |||||||||||
| RAc | X | X | X | X | X |
GM-CSF, granulocyte-macrophage colony-stimulating factor; RA, 13-cis-retinoic acid
a GM-CSF: 250 µg/m2/day, administered by either subcutaneous injection (recommended) or IV infusion administered over 2 hours.
b UNITUXIN: 17.5 mg/m2/day, administered by diluted IV infusion over 10 to 20 hours.
c RA: for >12 kg body weight, 80 mg/m2 orally twice daily for a total dose of 160 mg/m2/day; for ≤12 kg body weight, 2.67 mg/kg orally twice daily for a total daily dose of 5.33 mg/kg/day (round dose up to nearest 10 mg).
Table 11 Dosage Regimen in the UNITUXIN/RA Arm for Cycles 2 and 4
Study Results
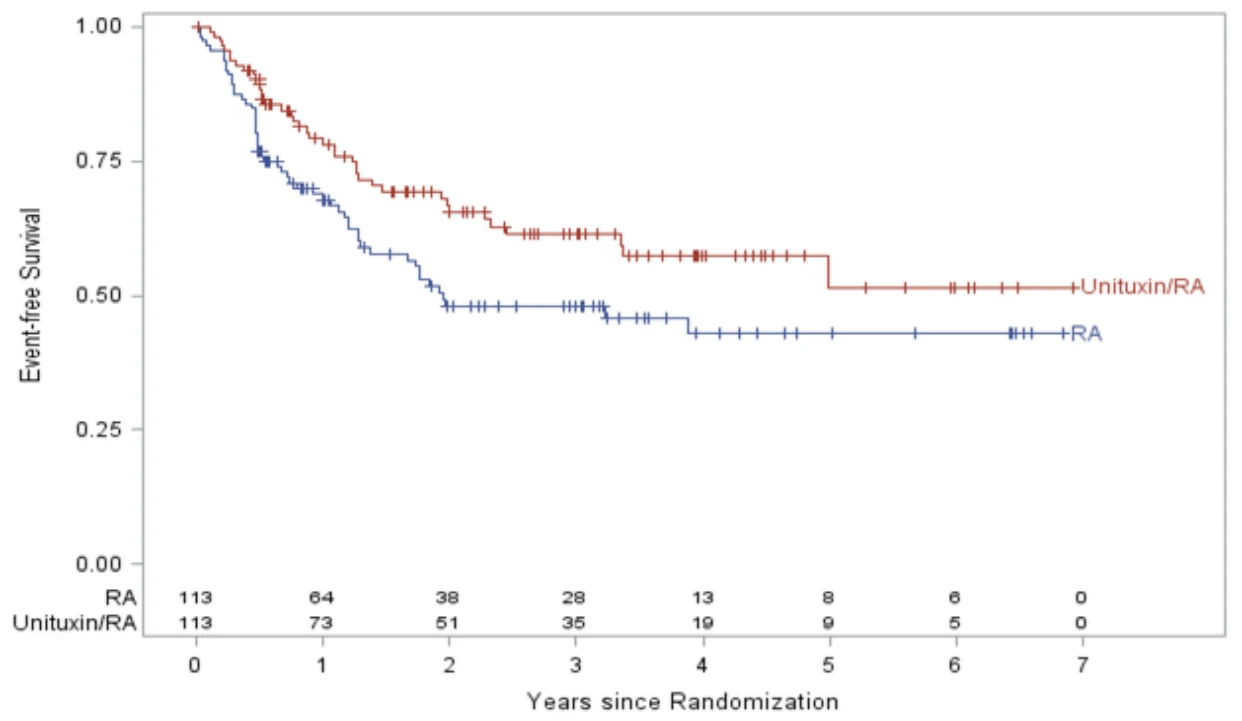
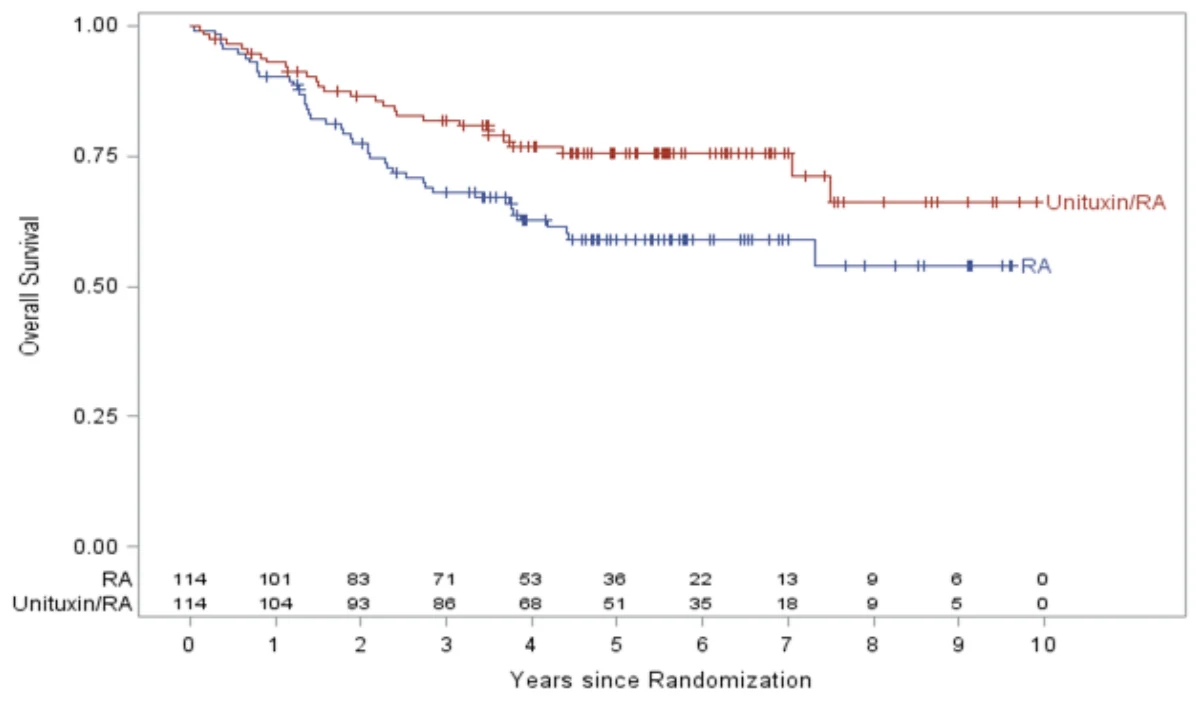
The major efficacy outcome measure was investigator-assessed event-free survival (EFS), defined as the time from randomization to the first occurrence of relapse, progressive disease, secondary malignancy, or death. Overall survival (OS) was also evaluated. Efficacy results on all randomized patients are shown in Table 12.
| Cycle Day | 1 | 2 | 3 | 4 | 5 | 6 | 7 | 8 | 9 | 10 | 11 | 12-14 | 15-28 | 29-32 | ||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| IL-2a | X | X | X | X | X | X | X | X | ||||||||
| UNITUXINb | X | X | X | X | ||||||||||||
| RAc | X | |||||||||||||||
IL-2, interleukin-2; RA, 13-cis-retinoic acid a IL-2: 3 MIU/m2/day administered by continuous IV infusion over 96 hours on Days 1-4 and 4.5 MIU/m2/day on Days 8-11. b UNITUXIN: 17.5 mg/m2/day, administered by diluted IV infusion over 10 to 20 hours. c RA: for >12 kg body weight, 80 mg/m2 orally twice daily for a total dose of 160 mg/m2/day; for ≤12 kg body weight, 2.67 mg/kg orally twice daily for a total daily dose of 5.33 mg/kg/day (round dose up to nearest 10 mg). | ||||||||||||||||
Table 12 Results of Study DIV-NB-301 in High-risk Neuroblastoma
| Efficacy Parameter | UNITUXIN/RA arm n=113 | RA arm n=113 |
| EFS | ||
| No. of Events (%) | 40 (35%) | 54 (48%) |
| Median (95% CI) (years) | NR (3.4, NR) | 2.0 (1.3, NR) |
| Hazard Ratio (95% CI)a | 0.59 (0.39, 0.89) | |
| p-value (log-rank test)a | 0.0124 | |
| Efficacy Parameter | UNITUXIN/RA arm n=114 | RA arm n=114 |
| OSb | ||
| No. of Events (%) | 28 (25%) | 44 (39%) |
| Median (95% CI) (years) | NR (7.5, NR) | NR (4.4, NR) |
| Hazard Ratio (95% CI)b | 0.60 (0.37, 0.96) | |
| p-valueb | 0.0351 | |
CI, confidence interval; EFS, event-free survival; INSS, International Neuroblastoma Staging System; NR, not reached; OS, overall survival; RA, 13-cis-retinoic acid a Hazard ratio and p-value were calculated using multivariate Cox proportional hazard regression model with treatment, age at diagnosis category, age at enrollment category, INSS stage, and pre-autologous stem cell transplantation (ASCT) response as explanatory variables. b Based on an additional 3 years of follow up. Hazard ratio and p-value were calculated using multivariate Cox proportional hazard regression model with treatment, DNA ploidy, and pre-ASCT response as explanatory variables. The p-value for OS is not adjusted for multiplicity. | ||
The Kaplan-Meier curve of EFS is shown in Figure 1. The Kaplan-Meier curve of OS is shown in Figure 2.
Figure 1 Kaplan-Meier Curve of Event-Free Survival
RA, 13-cis-retinoic acid
Figure 2 Kaplan-Meier Curve of Overall Survival
RA, 13-cis-retinoic acid
15. Microbiology
No microbiological information is required for this drug product.
16. Non-Clinical Toxicology
General Toxicology: Traditional animal studies were not conducted prior to the use of dinutuximab in the pivotal clinical trial, ANBL0032. Toxicology studies have been conducted in rats and non-human primates to investigate clinical findings observed in the clinical trial population. Overall, no new safety concerns have been identified through the non-clinical toxicology studies conducted; no mortality occurred during these studies despite higher exposure to the test agent, dinutuximab.
Genotoxicity: No studies have been conducted to evaluate the mutagenic potential of dinutuximab.
Carcinogenicity: No studies have been conducted to evaluate the carcinogenic potential of dinutuximab.
Reproductive and Developmental Toxicology: Dedicated studies examining the effects of dinutuximab on male and female fertility and early embryonic development, embryofetal development, or pre- and postnatal development have not been conducted. In repeat-dose toxicity studies, no clear effects on reproductive organs were observed in rats.
Juvenile Toxicity: A single-cycle IV tolerability study of dinutuximab in the juvenile cynomolgus monkey at doses of 0, 3, 10, or 30 mg/kg/day given for 4 consecutive days (total doses per 4-day cycle of 12, 40, and 120 mg/kg, respectively), was conducted. There was no mortality during the study. There was no dinutuximab-related effect on electrocardiology, neurological evaluation, nerve conduction velocity, or urinalysis parameters. An extensive peripheral neuropathy with nerve fiber degeneration extending into the dorsal funiculi of the spinal cord and further into the medulla oblongata was observed across doses without clear dose-relationship and was persistent beyond the cessation of dosing at the end of the 24-day recovery period. In addition, minimal degeneration and/or gliosis of the white matter in the cerebrum were observed at the high dose. A no-observed-adverse-effect level (NOAEL) could not be established for this study. However, it should be noted that these total per cycle doses are approximately 6-, 21-, and 63-fold higher than the human 1.9 mg/kg total cycle dose and lead to exposures approximately 20- to 70-fold higher than those observed in the clinical studies.
Special Toxicology: A combined cardiovascular and respiratory safety pharmacology study was conducted in 3 conscious male cynomolgus monkeys with 14 mg/kg dinutuximab administered via a 10-hour intravenous infusion. No respiratory system effects were noted. Cardiovascular system effects, including moderate increases in blood pressure (in 1 animal) and heart rate (in 2 animals), when compared with the control, were observed from 5 to 24 hours after the start of dosing. However, no statistically significant changes in group mean values were noted for blood pressure or heart rate at any time point. No change in QTc was observed, and the administration of dinutuximab had no direct effect on any ECG parameter.