


Product Monograph - Trodelvy
Recent Major Label Changes
| 1 Indications | 07/2023 |
|---|---|
| 1 Indications, 1.2 Geriatrics | 07/2023 |
| 3 Serious Warnings and Precautions Box | 03/2025 |
| 4 Dosage and Administration, 4.2 Recommended Dose and Dosage Adjustment | 03/2025 |
| 7 Warnings and Precautions, General | 07/2023 |
| 7 Warnings and Precautions, Endocrine and Metabolism | 07/2023 |
| 7 Warnings and Precautions, Gastrointestinal | 07/2023 |
| 7 Warnings and Precautions, Hematologic | 03/2025 |
| 7 Warnings and Precautions, Immune | 07/2023 |
| 7 Warnings and Precautions, 7.1.4 Geriatrics | 07/2023 |
Certain sections (as indicated in section 2.1. of the PM guidance) or subsections that are not applicable at the time of the preparation of the most recent authorized product monograph are not listed.
Table of Contents
Recent Major Label Changes ............................................................................................................ 2
Table of Contents ............................................................................................................................. 2
PART 1: Healthcare Professional Information .................................................................................... 4
1 Indications ........................................................................................................................... 4
1.1 Pediatrics .............................................................................................................................. 4
1.2 Geriatrics .............................................................................................................................. 4
2 contraindications ................................................................................................................. 4
3 Serious Warnings and Precautions Box ................................................................................. 4
4 Dosage and Administration .................................................................................................. 5
4.1 Dosing Considerations ......................................................................................................... 5
4.2 Recommended Dose and Dosage Adjustment .................................................................... 5
4.3 Reconstitution ...................................................................................................................... 7
4.4 Administration ..................................................................................................................... 8
5 Overdose ............................................................................................................................. 8
6 Dosage Forms, Strengths, Composition, and Packaging ......................................................... 9
7 Warnings and Precautions .................................................................................................... 9
7.1 Special Populations ............................................................................................................12
7.1.1 Pregnancy .........................................................................................................................12
7.1.2 Breastfeeding ...................................................................................................................12
7.1.3 Pediatrics ..........................................................................................................................12
7.1.4 Geriatrics ..........................................................................................................................12
8 Adverse Reactions ............................................................................................................. 13
8.1 Adverse Reaction Overview ...............................................................................................13
8.2 Clinical Trial Adverse Reactions .........................................................................................14
8.3 Less Common Clinical Trial Adverse Reactions ..................................................................23
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry, and Other Quantitative Data 24
9 DRUG INTERACTIONS ......................................................................................................... 25
9.2 Drug Interactions Overview ...............................................................................................25
9.3 Drug-Behavioural Interactions ...........................................................................................26
9.4 Drug-Drug Interactions ......................................................................................................26
9.5 Drug-Food Interactions ......................................................................................................26
9.6 Drug-Herb Interactions ......................................................................................................26
9.7 Drug-Laboratory Test Interactions .....................................................................................26
10 Clinical Pharmacology ........................................................................................................ 26
10.1 Mechanism of Action ...................................................................................................26
10.2 Pharmacodynamics .....................................................................................................27
10.3 Pharmacokinetics ........................................................................................................27
10.4 Immunogenicity ...........................................................................................................28
11 Storage, Stability, and Disposal .......................................................................................... 28
12 Special Handling Instructions.............................................................................................. 28
PART 2: Scientific Information ........................................................................................................ 29
13 Pharmaceutical Information ............................................................................................... 29
14 Clinical Trials ...................................................................................................................... 30
14.1 Clinical Trials by Indication ..........................................................................................30
Unresectable Locally Advanced or Metastatic Triple-Negative Breast Cancer (mTNBC) .............30
Unresectable Locally Advanced or Metastatic Hormone Receptor-Positive, Human Epidermal Growth Factor Receptor 2-Negative Breast Cancer (HR-positive/HER2-negative mBC) ..............33
15 Microbiology ..................................................................................................................... 36
16 Non-Clinical Toxicology ...................................................................................................... 36
Patient Medication Information ..................................................................................................... 38
PART 1: Healthcare Professional Information
1 Indications
TRODELVY (sacituzumab govitecan) is indicated for:
- the treatment of adult patients with unresectable locally advanced or metastatic triple-negative breast cancer (mTNBC) who have received two or more prior therapies, at least one of them for metastatic disease.
- the treatment of adult patients with unresectable locally advanced or metastatic hormone receptor (HR)-positive, human epidermal growth factor receptor 2 (HER2)-negative (IHC 0, IHC 1+ or IHC 2+/ISH-) breast cancer who have received endocrine-based therapy and at least two additional systemic therapies in the metastatic setting.
1.1 Pediatrics
Pediatrics (<18 years of age): No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use.
1.2 Geriatrics
Geriatrics (≥65 years of age): Evidence from clinical studies and experience suggests use in the geriatric population is not associated with differences in effectiveness. Evidence from clinical studies suggests the use in the geriatric population may be associated with differences in safety in the HR-positive/HER2-negative metastatic breast cancer population (see 7 Warnings and Precautions, Special Populations).
2 Contraindications
Sacituzumab govitecan is contraindicated in patients who are hypersensitive to this drug or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see 6 Dosage Forms, Strengths, Composition, and Packaging.
3 Serious Warnings and Precautions Box
Serious Warnings and Precautions
|
|---|
|
4 Dosage and Administration
4.1 Dosing Considerations
- Do NOT substitute Trodelvy for or use with other drugs containing irinotecan or its active metabolite SN-38.
- Patients homozygous for the uridine diphosphate-glucuronosyl transferase 1A1 (UGT1A1)*28 allele are at increased risk for neutropenia, febrile neutropenia, and anemia; and may be at increased risk for other adverse reactions when treated with Trodelvy [see 7 Warnings and Precautions, 10 Clinical Pharmacology].
- For intravenous infusion only. Do not administer as an intravenous push or bolus.
- The recommended dose is 10 mg/kg once weekly on Days 1 and 8 of continuous 21-day treatment cycles until disease progression or unacceptable toxicity [see 4.2 Recommended Dose and Dosage Adjustment].
- Premedication for prevention of infusion reactions is recommended [see 4.2 Recommended Dose and Dosage Adjustment, 7 Warnings and Precautions]. Have medications and emergency equipment to treat infusion-related reactions, including anaphylaxis, available for immediate use when administering Trodelvy.
- Premedication for prevention of chemotherapy-induced nausea and vomiting is recommended [see 4.2 Recommended Dose and Dosage Adjustment].
- Monitor patients during the infusion and for at least 30 minutes after completion of infusion. Treatment interruption and/or dose reduction may be needed to manage adverse reactions [see 4.2 Recommended Dose and Dosage Adjustment].
4.2 Recommended Dose and Dosage Adjustment
The recommended dose of Trodelvy is 10 mg/kg administered as an intravenous infusion once weekly on Days 1 and 8 of 21-day treatment cycles. Continue treatment until disease progression or unacceptable toxicity. Do not administer Trodelvy at doses greater than 10 mg/kg.
Administer Trodelvy as an intravenous infusion only. Do not administer as an intravenous push or bolus.
First infusion: Administer infusion over 3 hours. Observe patients during the infusion, and for at least 30 minutes following the initial dose, for signs or symptoms of infusion-related reactions [see 7 Warnings and Precautions].
Subsequent infusions: Administer infusion over 1 to 2 hours if prior infusions were tolerated. Observe patients during the infusion and for at least 30 minutes after infusion.
Premedication
Prior to each dose of Trodelvy, premedication for prevention of infusion reactions and prevention of chemotherapy-induced nausea and vomiting (CINV) is recommended.
- Premedicate with antipyretics and H1 and H2 blockers prior to infusion; corticosteroids may be used for patients who had prior infusion reactions.
- Premedicate with a two or three drug combination regimen (e.g., dexamethasone with either a 5-HT3 receptor antagonist or an NK-1 receptor antagonist, as well as other drugs as indicated).
Prophylaxis for Neutropenia
Primary prophylaxis with granulocyte colony-stimulating factor (G-CSF) is recommended starting in the first cycle in patients at increased risk of febrile neutropenia [see 7 Warnings and Precautions].
Dose Modifications for Adverse Reactions
Management of adverse reactions may require temporary interruption, dose reduction, or treatment discontinuation of Trodelvy as described in Table 1 and Table 2.
Do not re-escalate the Trodelvy dose after a dose reduction for adverse reactions has been made.
Table 1: Dosage Reduction Schedule
| Dose Reduction Schedule | Dose Level |
|---|---|
| Recommended starting dose | 10 mg/kg |
| First dose reduction | Reduce to 7.5 mg/kg |
| Second dose reduction | Reduce to 5 mg/kg |
| Requirement for further dose reduction | Discontinue treatment |
The recommended dosage modifications for adverse reactions are provided in Table 2.
Table 2: Dose Modifications for Adverse Reactions
| Adverse Reaction | Severity | Dose Modification |
|---|---|---|
| Adverse Reaction | Severity | Dose Modification |
| Neutropenia |
|
|
| Nausea/Vomiting/ Diarrhea |
|
|
| Infusion-Related Reaction |
|
|
|
| |
| Other Toxicities |
|
|
Pediatrics (<18 years of age): Health Canada has not authorized an indication for pediatric use [see 1 Indications, 1.1 Pediatrics].
Geriatrics (≥65 years of age): No dose adjustment is necessary in older patients [see 7 Warnings and Precautions, 7.1.4 Geriatrics].
Renal Impairment: There are no data on the use of sacituzumab govitecan in patients with severe renal impairment (creatinine clearance [CLcr] 15 to 29 mL/min) or end-stage renal disease (CLcr < 15 mL/min).
Hepatic Impairment: No dose adjustment is necessary in patients with mild hepatic impairment (total bilirubin ≤ ULN with AST ˃ ULN, or bilirubin >1.0 to ≤ 1.5 ULN with any AST) [see 10.3 Pharmacokinetics]. The safety and efficacy of Trodelvy in patients with moderate (total bilirubin ˃ 1.5 to 3.0 x ULN) or severe (total bilirubin ˃ 3.0 × ULN) hepatic impairment has not been established. The administration of Trodelvy in patients with severe hepatic impairment should be avoided.
4.3 Reconstitution
Parenteral Products:
Table 3: Reconstitution
| Vial Size | Volume of Diluent to be Added to Vial | Approximate Available Volume | Concentration per mL |
| 180 mg | 20 mL | 20 mL | 10 mg/mL |
Reconstitution
- Trodelvy is a cytotoxic drug.
- Follow applicable special handling and disposal procedures.
- Calculate the required dose (mg) of Trodelvy based on the patient’s body weight [see 4.2 Recommended Dose and Dosage Adjustment].
- Using a sterile syringe, slowly inject 20 mL of 0.9% Sodium Chloride Injection, USP, into each 180 mg Trodelvy vial. The resulting concentration will be 10 mg/mL.
- Gently swirl vials and allow to dissolve for up to 15 minutes. Do not shake. Parenteral drug products should be inspected visually for particulate matter and discolouration prior to administration, whenever solution and container permit. The solution should be free of visible particulates, clear, and yellow. Do not use the reconstituted solution if it is cloudy or discoloured.
- Use immediately to prepare a diluted Trodelvy infusion solution.
Dilution
- Calculate the required volume of the reconstituted Trodelvy solution needed to obtain the appropriate dose according to patient’s body weight. Withdraw this amount from the vial(s) using a syringe. Discard any unused portion remaining in the vial(s).
- Adjust the volume in the infusion bag as needed with 0.9% Sodium Chloride Injection, USP, to obtain a concentration of 1.1 mg/mL to 3.4 mg/mL.
- Slowly inject the required volume of reconstituted Trodelvy solution into a polyvinyl chloride, polyolefin (polypropylene and/or polyethylene) or ethylene vinyl acetate infusion bag to minimize foaming. Do not shake the contents.
- Only 0.9% Sodium Chloride Injection, USP should be used since the stability of the reconstituted product has not been determined with other infusion-based solutions. Use the diluted solution in the infusion bag immediately. If not used immediately, the infusion bag containing Trodelvy solution can be stored refrigerated at 2°C to 8°C for up to 24 hours protected from light. After refrigeration, administer diluted solution at room temperature up to 25°C within 8 hours (including infusion time).
Do not freeze or shake. Protect from light [see 11 Storage, Stability, and Disposal].
4.4 Administration
- Administer Trodelvy as an intravenous infusion [see 4.2 Recommended Dose and Dosage Adjustment]. Protect infusion bag from light.
- An infusion pump may be used.
- Do not mix Trodelvy, or administer as an infusion, with other medicinal products.
- Upon completion of the infusion, flush the intravenous line with 20 mL 0.9% Sodium Chloride Injection, USP.
5 Overdose
In a clinical trial, planned doses of up to 18 mg/kg (approximately 1.8 times the maximum recommended dose of 10 mg/kg) of Trodelvy were administered. In these patients, a higher incidence of severe neutropenia was observed.
| For the most recent information in the management of a suspected drug overdose, contact your regional poison control centre or Health Canada’s toll-free number, 1-844 POISON-X (1-844-764-7669). |
|---|
6 Dosage Forms, Strengths, Composition, and Packaging
To help ensure the traceability of biologic products, health professionals should recognise the importance of recording both the brand name and the non-proprietary (active ingredient) name as well as other product-specific identifiers such as the Drug Identification Number (DIN) and the batch/lot number of the product supplied.
Table 4: Dosage Forms, Strengths, Composition and Packaging
Trodelvy is supplied as a sterile, preservative-free, off-white to yellowish lyophilized powder for intravenous use in a 50 mL clear glass single-dose vial, with a rubber stopper and crimp-sealed with an aluminum flip-off cap.
7 Warnings and Precautions
Please see 3 .
General
Trodelvy should be administered under the supervision of healthcare professionals experienced in the treatment of cancer.
The pooled safety population (N=688) described in 7 Warnings and Precautions reflects exposure to Trodelvy as monotherapy at 10 mg/kg which included patients with locally advanced or metastatic HR-positive/HER2-negative breast cancer and patients with mTNBC from Study IMMU-132-01, Study IMMU-132-05 (ASCENT), and Study IMMU-132-09 (TROPiCS-02) unless otherwise noted.
Driving and Operating Machinery
Trodelvy has minor influence on the ability to drive and use machines. Dizziness has been reported. Advise patients to use caution when driving or using machines.
Endocrine and Metabolism
Genetic Polymorphism
Individuals who are homozygous for the uridine diphosphate-glucuronosyl transferase 1A1 (UGT1A1)*28 allele are potentially at increased risk for neutropenia, febrile neutropenia, and anemia and may be at increased risk for other adverse reactions following initiation of Trodelvy treatment.
Ninety-one percent (628/688) of patients who received Trodelvy (up to 10 mg/kg on Days 1 and 8 of a 21-day cycle) had retrospective UGT1A1 genotype results available. The incidence of Grade 3-4 neutropenia was 60.6% (43/71) in patients homozygous for the UGT1A1*28 allele, 52.9% (144/272) in patients heterozygous for the UGT1A1*28 allele, and 49.1% (140/285) in patients homozygous for the wild-type allele [see 10 Clinical Pharmacology]. The incidence of Grade 3-4 anemia was 15.5% (11/71) in patients homozygous for the UGT1A1*28 allele, 7.4% (20/272) in patients heterozygous for the
| Route of Administration | Dosage Form/ Strength/Composition | Non-medicinal Ingredients |
| Intravenous | Lyophilized powder for solution for injection: 180 mg/vial | Powder: 2-(N-morpholino) ethane sulfonic acid, polysorbate 80, trehalose dihydrate Solvent: sodium chloride, water |
UGT1A1*28 allele, and 8.1% (23/285) in patients homozygous for the wild-type allele.
The median time to first neutropenia including febrile neutropenia was 12 days in patients homozygous for the UGT1A1*28 allele, 14 days in patients heterozygous for the UGT1A1*28 allele, and 20 days in patients homozygous for the wild-type allele. The median time to first anemia was 22 days in patients homozygous for the UGT1A1*28 allele, 27 days in patients heterozygous for the UGT1A1*28 allele, and 29 days in patients homozygous for the wild-type allele.
Closely monitor patients with known reduced UGT1A1 activity for adverse reactions. Withhold or permanently discontinue Trodelvy based on clinical assessment of the onset, duration and severity of the observed adverse reactions in patients with evidence of acute early-onset or unusually severe adverse reactions, which may indicate reduced UGT1A1 enzyme activity [see 4.2 Recommended Dose and Dosage Adjustment].
Gastrointestinal
Diarrhea
Trodelvy can cause severe diarrhea. Diarrhea occurred in 62.5% (430/688) of all patients treated with Trodelvy. Grade 3-4 diarrhea occurred in 10.3% (71/688) of all patients treated with Trodelvy. Diarrhea in some cases was observed to have led to dehydration and subsequent acute kidney injury in 0.4% (3/688) of patients. In another clinical trial with Trodelvy, one patient had intestinal perforation following diarrhea.
Withhold Trodelvy for Grade 3-4 diarrhea at the time of scheduled treatment administration and resume when resolved to ≤ Grade 1 [see 3 Serious Warnings and Precautions Box, 4.2 Recommended Dose and Dosage Adjustment].
At the onset of diarrhea, evaluate for infectious causes and if negative, promptly initiate loperamide, 4 mg initially followed by 2 mg with every episode of diarrhea for a maximum of 16 mg daily. Discontinue loperamide 12 hours after diarrhea resolves. Additional supportive measures (e.g., fluid and electrolyte substitution) may also be employed as clinically indicated.
Patients who exhibit an excessive cholinergic response to treatment with Trodelvy (e.g., abdominal cramping, diarrhea, salivation, etc.) can receive appropriate premedication (e.g., atropine) for subsequent treatments.
Nausea and Vomiting
Trodelvy is emetogenic. Nausea occurred in 62.6% (431/688) of all patients treated with Trodelvy. Grade 3-4 nausea occurred in 2.8% (19/688) of all patients treated with Trodelvy.
Vomiting occurred in 33.6% (231/688) of all patients treated with Trodelvy. Grade 3-4 vomiting occurred in 2.5% (17/688) of all patients treated with Trodelvy.
Premedicate with a two or three drug combination regimen (e.g., dexamethasone with either a 5-HT3 receptor antagonist or an NK-1 receptor antagonist as well as other drugs as indicated) for prevention of chemotherapy-induced nausea and vomiting (CINV).
Withhold Trodelvy doses for Grade 3 nausea or Grade 3-4 vomiting at the time of scheduled treatment administration and resume with additional supportive measures when resolved to ≤ Grade 1 [see 4.2 Recommended Dose and Dosage Adjustment].
Additional antiemetics and other supportive measures may also be employed as clinically indicated. All patients should be given take-home medications with clear instructions for prevention and treatment of nausea and vomiting.
Hematologic
Neutropenia
Trodelvy can cause severe or life-threatening neutropenia. Fatal infections in the setting of neutropenia have been observed in clinical trials with Trodelvy, primarily in the first two cycles of treatment. Neutropenia occurred in 67.6% (465/688) of patients treated with Trodelvy. Grade 3-4 neutropenia occurred in 50.7% (349/688) of patients. Febrile neutropenia occurred in 6.1% (42/688) of patients. The median time to first onset of neutropenia (including febrile neutropenia) was 16 days and has occurred earlier in some patient populations [see Endocrine and Metabolism]. Neutropenic colitis occurred in 1% (7/688) of patients.
Monitor absolute neutrophil count (ANC) during treatment.
Primary prophylaxis with G-CSF is recommended starting in the first cycle of treatment in patients at increased risk of febrile neutropenia, e.g., older patients (in particular ≥ 65 years and older), patients with previous neutropenia, poor performance status, organ dysfunction (including renal, liver, or cardiovascular dysfunction), or multiple comorbid conditions.
Withhold Trodelvy for ANC below 1500/mm3 on Day 1 of any cycle or neutrophil count below 1000/mm3 on Day 8 of any cycle. Withhold Trodelvy for neutropenic fever. Dose modifications may be required due to neutropenia or febrile neutropenia. Treat neutropenia with G-CSF and use prophylaxis in subsequent cycles as clinically indicated [see 4.2 Recommended Dose and Dosage Adjustment].
Immune
Hypersensitivity
Serious hypersensitivity reactions including life-threatening anaphylactic reactions have occurred with Trodelvy treatment. Severe signs and symptoms included cardiac arrest, hypotension, wheezing, angioedema, swelling, pneumonitis, and skin reactions [see 2 contraindications].
Hypersensitivity reactions within 24 hours of dosing occurred in 33% (227/688) of patients treated with Trodelvy. Grade 3-4 hypersensitivity occurred in 1.7% (12/688) of patients treated with Trodelvy. The incidence of hypersensitivity reactions leading to permanent discontinuation of Trodelvy was 0.1% (1/688).
Premedication for patients receiving Trodelvy is recommended. Observe patients closely for infusion-related reactions during each Trodelvy infusion and for at least 30 minutes after completion of each infusion [see 4 Dosage and Administration]. Have medications and emergency equipment to treat infusion-related reactions, including anaphylaxis, available for immediate use when administering Trodelvy.
Reproductive Health
Fertility
Based on findings in animals, Trodelvy may impair fertility in females of reproductive potential [see 16 Non-Clinical Toxicology].
Teratogenic Risk
Based on its mechanism of action, Trodelvy can cause teratogenicity and/or embryo-fetal lethality when administered to a pregnant woman. Trodelvy contains a genotoxic component, SN-38, and targets rapidly dividing cells [see 10 Clinical Pharmacology and 16 Non-Clinical Toxicology]. Advise pregnant women and females of reproductive potential of the potential risk to a fetus. Advise females of reproductive potential to use effective contraception during treatment with Trodelvy and for 6 months after the last dose. Advise male patients with female partners of reproductive potential to use effective contraception during treatment with Trodelvy and for 3 months after the last dose [see 7.1 Special Populations].
7.1 Special Populations
7.1.1 Pregnancy
Based on its mechanism of action, Trodelvy can cause teratogenicity and/or embryo-fetal lethality when administered to a pregnant woman. Trodelvy contains a genotoxic component, SN-38, and is toxic to rapidly dividing cells [see 10 Clinical Pharmacology and 16 Non-Clinical Toxicology]. Advise pregnant women and females of reproductive potential of the potential risk to a fetus.
Verify the pregnancy status of females of reproductive potential prior to the initiation of Trodelvy.
Advise females of reproductive potential to use effective contraception during treatment with Trodelvy and for 6 months after the last dose.
Because of the potential for genotoxicity, advise male patients with female partners of reproductive potential to use effective contraception during treatment with Trodelvy and for 3 months after the last dose.
7.1.2 Breastfeeding
It is unknown if Trodelvy is excreted in human milk.
Because of the potential for serious adverse reactions in a breastfed child, advise women not to breastfeed during treatment and for 1 month after the last dose of Trodelvy.
7.1.3 Pediatrics
Pediatrics (<18 years of age): No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use.
7.1.4 Geriatrics
Geriatrics (≥65 years): Of the patients with mTNBC who received Trodelvy, 68/366 (18.6%) of patients were ≥65 years old and 3% were 75 years and older. Safety and efficacy were similar between these patients and younger patients.
Of the patients with HR-positive/HER2-negative breast cancer who received Trodelvy, 84/322 (26.1%) were ≥65 years old and 6% were 75 years and older. No overall differences in effectiveness were observed between these patients and younger patients. There was a higher discontinuation rate due to adverse reactions in patients aged 65 years or older (14%) compared with younger patients (3%). There was a higher dose reduction rate in patients aged 75 years and older (50.0%) compared with younger patients (32.5%). Also, there was a higher rate of treatment emergent serious adverse reactions in patients aged 65 years or older (42.9%) compared with younger patients (23.9%).
8 Adverse Reactions
8.1 Adverse Reaction Overview
The data described in the WARNINGS AND PRECAUTIONS section reflect exposure to Trodelvy as monotherapy in 688 patients from three studies, IMMU-132-01 (single-arm trial), IMMU-132-05 (randomized, active-controlled trial), and IMMU-132-09 (randomized, active-controlled trial) which included 366 patients with mTNBC who had received prior systemic chemotherapy for advanced disease and 322 patients with HR-positive/HER2-negative locally advanced or metastatic breast cancer, all of whom had received prior systemic chemotherapy for advanced disease.
Study IMMU-132-05 (ASCENT) in mTNBC
The data described below reflect exposure to Trodelvy as a monotherapy in 258 patients with mTNBC who had received prior systemic chemotherapy for advanced disease from pivotal Study IMMU-132-05 (ASCENT) [see 14 Clinical Trials]. The median duration of treatment was 4.4 months (range: 0 to 23 months).
Serious adverse reactions occurred in 26.9% of patients receiving Trodelvy. Serious adverse reactions in >1% of patients receiving Trodelvy were febrile neutropenia (5.0%), diarrhea (3.5%), neutropenia (2.7%), pneumonia (2.7%), anemia (1.2%), and abdominal pain (1.2%). Fatal adverse reactions occurred in 0.8% of patients who received Trodelvy, including respiratory failure (0.4%).
Adverse reactions leading to permanent discontinuation of Trodelvy occurred in 4.7% of patients. The most frequent adverse reactions leading to permanent discontinuation in patients who received Trodelvy were pneumonia (0.8%) and fatigue (0.8%).
Adverse reactions leading to a dose reduction of Trodelvy occurred in 21.7% of patients. The most frequent (≥1%) adverse reaction leading to a dose reduction was neutropenia (8.9%), diarrhea (4.7%), febrile neutropenia (2.7%), nausea (1.9%), fatigue (1.9%), anemia (1.2%). Adverse reactions leading to a treatment interruption of Trodelvy occurred in 63% of patients. The most frequent (≥4%) adverse reactions leading to a treatment interruption were neutropenia (46.1%), leukopenia (5.0%), and diarrhea (5.4%). Granulocyte-colony stimulating factor (G-CSF) was used in 47% (122/258) of patients who received Trodelvy.
The most common adverse reactions (incidence >25%) reported in patients receiving Trodelvy were: neutropenia (64.0%), diarrhea (65.1%), nausea (62.4%), fatigue (51.6%), alopecia (46.9%), anemia (39.5%), constipation (37.2%), vomiting (33.3%), and decreased appetite (27.5%).
Study IMMU-132-09 (TROPiCS-02) in HR-positive/HER2-negative locally advanced or metastatic BC
The data described below reflect exposure to Trodelvy as a monotherapy in 268 patients with HR-positive/HER2-negative locally advanced or metastatic BC whose disease has progressed after the following in any setting: a CDK 4/6 inhibitor, endocrine therapy, and a taxane, and received at least two prior chemotherapies in the metastatic setting (one of which could be in the neoadjuvant or adjuvant setting if progression or recurrence occurred within 12 months) from pivotal Study IMMU-132-09 (TROPiCS-02) [see 14 Clinical Trials]. The median duration of exposure to Trodelvy and treatment of physician’s choice was 4.1 months (range: 0.03 to 30.6 months) and 2.3 months (range: 0.03 to 22.3 months), respectively.
Serious adverse reactions occurred in 27.6% of the patients receiving Trodelvy. Serious adverse reactions in ˃1% of patients receiving Trodelvy included diarrhea (4.9%), febrile neutropenia (4.1%), neutropenia (3.0%), abdominal pain (2.2%), neutropenic colitis (1.9%), vomiting (1.9%), pneumonia (1.5%), colitis (1.5%), acute kidney injury (1.1%), pyrexia, urinary tract infection, and sepsis (each 1.1%).
Fatal adverse reactions occurred in 2.2% of patients who received Trodelvy including arrhythmia, pneumonia, COVID-19 pneumonia, nervous system disorder, pulmonary embolism, and septic shock (each 0.4%).
Adverse reactions leading to permanent discontinuation of Trodelvy occurred in 6.3% of patients. The most frequent (≥0.5%) adverse reactions leading to permanent discontinuation in patients who received Trodelvy were asthenia, general physical health deterioration, and neutropenia (each 0.7%).
Adverse reactions leading to a dose reduction of Trodelvy occurred in 33.6% of patients. The most frequent (≥1%) adverse reactions leading to dose reduction were neutropenia (16%), diarrhea (8%), fatigue (3%), febrile neutropenia (3%), vomiting (1.5%), anemia (1.1%), and asthenia (1.1%).
Adverse reactions leading to a treatment interruption of Trodelvy occurred in 66.4% of patients. The most frequent (≥4%) adverse reaction leading to treatment interruption was neutropenia (50%). G-CSF was used in 54.1% (145/268) of patients who received Trodelvy.
The most common adverse reactions (incidence >25%) reported in patients receiving Trodelvy were: neutropenia (70.5%), diarrhea (61.9%), nausea (58.6%), alopecia (47.8%), fatigue (39.2%), anemia (36.6%), and constipation (34.7%).
There was a higher incidence of both Grade 3 or higher and serious Grade 3 or higher adverse reactions in patients with mild hepatic impairment (81.1% [120/148] and 29.1% [43/148], respectively) compared to patients with normal hepatic function (64.4% [76/118] and 19.5% [23/118], respectively). Furthermore, adverse reactions leading to both dose reduction and drug interruption were more frequent (37.8% [56/148] and 70.9% [105/148], respectively) in patients with mild hepatic impairment compared with patients with normal hepatic function (28.8% [34/118] and 61.0% [72/118], respectively) (see 4.2 Recommended Dose and Dosage Adjustment and 10.3 Pharmacokinetics).
There was a higher rate of serious Grade 3 or higher adverse reactions in patients with moderate renal impairment (50.0% [11/22]) compared with those with mild (22.9% [24/105]) or normal renal function (22.1% [31/140]). Furthermore, adverse reactions leading to both drug interruption and discontinuation were more frequent (77.3% [17/22] and 13.6% [3/22], respectively) in patients with moderate renal impairment compared with those with mild (65.7% [69/105] and 4.8% [5/105], respectively) or normal renal function (65.7% [92/140] and 5.7% [8/140], respectively) (see 4.2 Recommended Dose and Dosage Adjustment and 10.3 Pharmacokinetics).
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials; therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
Unresectable locally advanced or metastatic triple-negative breast cancer (mTNBC)
The following group of patients were excluded: known history of Gilbert’s disease or bone-only disease, unstable angina, myocardial infarction, or congestive heart failure present within 6 months of randomization or a clinically significant cardiac arrhythmia (other than stable atrial fibrillation) requiring anti-arrhythmia therapy, active infection requiring IV antibiotic use within 1 week of treatment initiation, Human immunodeficiency virus (HIV), hepatitis B, or hepatitis C positive, active chronic inflammatory bowel disease (ulcerative colitis, Crohn’s disease), clinically significant bleeding, intestinal obstruction, or gastrointestinal perforation within 6 months of randomization, and clinically significant active chronic obstructive pulmonary disease or other moderate-to-severe chronic respiratory illness present within 6 months of randomization.
Table 5 lists Treatment Emergent Adverse Reactions (TEAR) from the pivotal ASCENT (IMMU-132-05) study, with incidences regardless of investigator assessment of causality, reported in this patient population.
Table 5: Adverse Reactions Reported in ≥1% of Patients with Metastatic Triple-negative Breast Cancer (mTNBC) in Study IMMU-132-05 (ASCENT)
| Adverse Reaction | Trodelvy (n=258) | Treatment of Physician’s Choice (n=224) | ||||||||||||||||||
| Adverse Reaction | Trodelvy (n=258) | Treatment of Physician’s Choice (n=224) | ||||||||||||||||||
| Adverse Reaction | Trodelvy (n=258) | Treatment of Physician’s Choice (n=224) | ||||||||||||||||||
| Adverse Reaction | Trodelvy (n=258) | Treatment of Physician’s Choice (n=224) | ||||||||||||||||||
All Grades n (%) | Grade 3 n (%) | Grade 4 n (%) | All Grades n (%) | Grade 3 n (%) | Grade 4 n (%) | |||||||||||||||
All Grades n (%) | Grade 3 n (%) | Grade 4 n (%) | All Grades n (%) | Grade 3 n (%) | Grade 4 n (%) | |||||||||||||||
All Grades n (%) | Grade 3 n (%) | Grade 4 n (%) | All Grades n (%) | Grade 3 n (%) | Grade 4 n (%) | |||||||||||||||
All Grades n (%) | Grade 3 n (%) | Grade 4 n (%) | All Grades n (%) | Grade 3 n (%) | Grade 4 n (%) | |||||||||||||||
| Blood and lymphatic system disorders | ||||||||||||||||||||
| Neutropenia | 165 (64) | 90 (35) | 44 (17) | 98 (44) | 46 (21) | 30 (13) | ||||||||||||||
| Anemia | 102 (40) | 24 (9) | 0 | 62 (28) | 13 (6) | 0 | ||||||||||||||
| Leukopenia | 43 (17) | 24 (9) | 3 (1) | 27 (12) | 11 (5) | 2 (1) | ||||||||||||||
| Lymphopenia | 25 (10) | 4 (2) | 1 (0.4) | 13 (6) | 5 (2) | 0 | ||||||||||||||
| Thrombocytopenia | 16 (6) | 2 (1) | 2 (1) | 28 (13) | 5 (2) | 0 | ||||||||||||||
| Febrile neutropenia | 15 (6) | 12 (5) | 3 (1) | 6 (3) | 5 (2) | 1 (0.4) | ||||||||||||||
| Cardiac disorders | ||||||||||||||||||||
| Palpitations | 5 (2) | 0 | 0 | 2 (1) | 0 | 0 | ||||||||||||||
| Eye disorders | ||||||||||||||||||||
| Dry eye | 10 (4) | 0 | 0 | 1 (0.4) | 0 | 0 | ||||||||||||||
| Vision blurred | 8 (3) | 0 | 0 | 1 (0.4) | 0 | 0 | ||||||||||||||
| Gastrointestinal disorders | ||||||||||||||||||||
| Diarrhea | 168 (65) | 29 (11) | 0 | 38 (17) | 2 (1) | 0 | ||||||||||||||
| Nausea | 161 (62) | 7 (3) | 1 (0.4) | 68 (30) | 1 (0.4) | 0 | ||||||||||||||
| Constipation | 96 (37) | 1 (0.4) | 0 | 52 (23) | 0 | 0 | ||||||||||||||
| Vomiting | 86 (33) | 3 (1) | 1 (0.4) | 36 (16) | 3 (1) | 0 | ||||||||||||||
| Abdominal pain | 55 (21) | 7 (3) | 0 | 18 (8) | 3 (1) | 0 | ||||||||||||||
| Stomatitis | 26 (10) | 2 (1) | 0 | 14 (6) | 0 | 0 | ||||||||||||||
| Abdominal pain upper | 24 (9) | 1 (0.4) | 0 | 8 (4) | 0 | 0 | ||||||||||||||
| Gastroesophageal reflux disease | 14 (5) | 0 | 0 | 7 (3) | 0 | 0 | ||||||||||||||
| Abdominal distension | 12 (5) | 0 | 0 | 7 (3) | 0 | 0 | ||||||||||||||
| Dyspepsia | 11 (4) | 0 | 0 | 8 (4) | 1 (0.4) | 0 | ||||||||||||||
| Colitis | 4 (2) | 1 (0.4) | 0 | 0 | 0 | 0 | ||||||||||||||
| Salivary hypersecretion | 4 (2) | 0 | 0 | 0 | 0 | 0 | ||||||||||||||
| General disorders and administration site conditions | ||||||||||||||||||||
| Fatigue | 133 (52) | 11 (4) | 0 | 89 (40) | 19 (8) | 0 | ||||||||||||||
| Asthenia | 40 (16) | 4 (2) | 0 | 29 (13) | 3 (1) | 0 | ||||||||||||||
| Pyrexia | 38 (15) | 1 (0.4) | 0 | 32 (14) | 5 (2) | 0 | ||||||||||||||
| Edema peripheral | 24 (9) | 0 | 0 | 24 (11) | 2 (1) | 0 | ||||||||||||||
| Mucosal inflammation | 20 (8) | 2 (1) | 0 | 14 (6) | 3 (1) | 0 | ||||||||||||||
| Pain | 19 (7) | 2 (1) | 0 | 11 (5) | 2 (1) | 0 | ||||||||||||||
| Chills | 14 (5) | 0 | 0 | 6 (3) | 0 | 0 | ||||||||||||||
| Immune System Disorders | ||||||||||||||||||||
| Hypersensitivity1 | 88 (34) | 3 (1) | 0 | 46 (21) | 3 (1) | 0 | ||||||||||||||
| Infections and infestations | ||||||||||||||||||||
| Urinary tract infection | 33 (13) | 1 (0.4) | 0 | 18 (8) | 1 (0.4) | 0 | ||||||||||||||
| Upper respiratory tract infection | 31 (12) | 0 | 0 | 7 (3) | 0 | 0 | ||||||||||||||
| Nasopharyngitis | 18 (7) | 0 | 0 | 5 (2) | 0 | 0 | ||||||||||||||
| Pneumonia | 13 (5) | 9 (3) | 0 | 11 (5) | 4 (2) | 2 (1) | ||||||||||||||
| Rash pustular | 3 (1) | 0 | 0 | 0 | 0 | 0 | ||||||||||||||
| Investigations | ||||||||||||||||||||
| Weight decreased | 22 (9) | 0 | 0 | 15 (7) | 0 | 0 | ||||||||||||||
| Aspartate aminotransferase increased | 29 (11) | 7 (3) | 0 | 27 (12) | 6 (3) | 0 | ||||||||||||||
| Alanine aminotransferase increased | 27 (10) | 3 (1) | 0 | 22 (10) | 2 (1) | 1 (0.4) | ||||||||||||||
| Blood alkaline phosphatase increased | 19 (7) | 3 (1) | 0 | 12 (5) | 2 (1) | 0 | ||||||||||||||
| Electrocardiogram QT prolonged | 12 (5) | 1 (0.4) | 0 | 3 (1) | 0 | 1 (0.4) | ||||||||||||||
| Blood creatinine increased | 7 (3) | 1 (0.4) | 0 | 0 | 0 | 0 | ||||||||||||||
| Metabolism and nutrition disorders | ||||||||||||||||||||
| Decreased appetite | 71 (28) | 4 (2) | 0 | 46 (21) | 2 (1) | 0 | ||||||||||||||
| Hypokalaemia | 41 (16) | 7 (3) | 0 | 29 (13) | 1 (0.4) | 0 | ||||||||||||||
| Hypomagnesemia | 32 (12) | 0 | 0 | 13 (6) | 0 | 0 | ||||||||||||||
| Hypophosphatemia | 15 (6) | 7 (3) | 2 (1) | 9 (4) | 3 (1) | 0 | ||||||||||||||
| Hyperglycaemia | 17 (7) | 2 (1) | 0 | 12 (5) | 3 (1) | 0 | ||||||||||||||
| Hypocalcaemia | 17 (7) | 3 (1) | 0 | 5 (2) | 1 (0.4) | 0 | ||||||||||||||
| Dehydration | 11 (4) | 1 (0.4) | 0 | 11 (5) | 0 | 0 | ||||||||||||||
| Hyponatraemia | 8 (3) | 2 (1) | 1 (0.4) | 6 (3) | 0 | 0 | ||||||||||||||
| Musculoskeletal and connective tissue disorders | ||||||||||||||||||||
| Back pain | 42 (16) | 3 (1) | 0 | 31 (14) | 4 (2) | 0 | ||||||||||||||
| Arthralgia | 32 (12) | 1 (0.4) | 0 | 16 (7) | 0 | 0 | ||||||||||||||
| Bone pain | 21 (8) | 1 (0.4) | 0 | 15 (7) | 0 | 0 | ||||||||||||||
| Pain in the extremity | 20 (8) | 6 (2) | 0 | 17 (8) | 2 (1) | 0 | ||||||||||||||
| Muscle spasms | 12 (5) | 0 | 0 | 5 (2) | 0 | 0 | ||||||||||||||
| Nervous system disorders | ||||||||||||||||||||
| Headache | 46 (18) | 2 (1) | 0 | 28 (13) | 1 (0.4) | 0 | ||||||||||||||
| Dizziness | 26 (10) | 0 | 0 | 16 (7) | 0 | 0 | ||||||||||||||
| Dysgeusia | 22 (9) | 0 | 0 | 6 (3) | 0 | 0 | ||||||||||||||
| Paraesthesia | 10 (4) | 0 | 0 | 6 (3) | 0 | 0 | ||||||||||||||
| Hypoaesthesia | 8 (3) | 0 | 0 | 3 (1) | 0 | 0 | ||||||||||||||
| Taste disorder | 4 (2) | 0 | 0 | 2 (1) | 0 | 0 | ||||||||||||||
| Tremor | 4 (2) | 0 | 0 | 1 (0.4) | 0 | 0 | ||||||||||||||
| Psychiatric disorders | ||||||||||||||||||||
| Insomnia | 29 (11) | 0 | 0 | 11 (5) | 0 | 0 | ||||||||||||||
| Respiratory, thoracic and mediastinal disorders | ||||||||||||||||||||
| Cough | 61 (24) | 0 | 0 | 40 (18) | 1 (0.4) | 0 | ||||||||||||||
| Dyspnea2 | 54 (21) | 9 (3) | 1 (0.4) | 50 (22) | 11 (5) | 1 (0.4) | ||||||||||||||
| Epistaxis | 13 (5) | 0 | 0 | 1 (0.4) | 0 | 0 | ||||||||||||||
| Nasal dryness | 3 (1) | 0 | 0 | 0 | 0 | 0 | ||||||||||||||
| Skin and subcutaneous tissue disorders | ||||||||||||||||||||
| Alopecia | 121 (47) | 0 | 0 | 36 (16) | 0 | 0 | ||||||||||||||
| Rash | 32 (12) | 1 (0.4) | 0 | 12 (5) | 1 (0.4) | 0 | ||||||||||||||
| Pruritus | 26 (10) | 0 | 0 | 7 (3) | 0 | 0 | ||||||||||||||
| Rash maculo-papular | 18 (7) | 0 | 0 | 3 (1) | 0 | 0 | ||||||||||||||
| Dry skin | 17 (7) | 0 | 0 | 3 (1) | 0 | 0 | ||||||||||||||
| Nail discolouration | 4 (2) | 0 | 0 | 0 | 0 | 0 | ||||||||||||||
| Dermatitis acneiform | 3 (1) | 0 | 0 | 0 | 0 | 0 | ||||||||||||||
| Vascular disorder | ||||||||||||||||||||
| Hypotension | 11 (4) | 0 | 0 | 9 (4) | 2 (1) | 0 | ||||||||||||||
| Hot flush | 6 (2) | 0 | 0 | 6 (3) | 0 | 0 | ||||||||||||||
Treatment of physician’s choice included one of the following single agents: eribulin (n=139), capecitabine (n=33), gemcitabine (n=38), or vinorelbine (except if patient had ≥ Grade 2 neuropathy, n=52).
Adverse events terms were coded using Medical Dictionary for Regulatory Activities (MedDRA) version 23.0.
‘Neutrophil count decreased', ‘Lymphocyte count decreased’, ‘Platelet count decreased’, 'White blood cell count decreased', 'Hemoglobin decreased', and 'Red blood cell count decreased' have been re-coded to Neutropenia, Lymphopenia, Thrombocytopenia, Leukopenia, and Anemia, correspondingly, for summary purposes. 1: Hypersensitivity events reported up to the end of the day after treatment was administered. Includes events coded to the following preferred terms: Cough; dyspnea; rash; pruritus; stomatitis; hypotension; rash maculopapular; flushing; erythema; chest discomfort; hypersensitivity; rhinitis allergic; wheezing; localized edema; dermatitis acneiform; conjunctivitis; rash pruritic; edema; rash macular; rash pustular; swelling; swelling face; urticaria; anaphylactic reaction; asthma; bronchospasm; conjunctivitis allergic; dermatitis; dermatitis contact; eye pruritus; mouth ulceration; periorbital edema; rash erythematous; scrotal edema; seasonal allergy; skin exfoliation; swollen tongue; tachypnoea; throat tightness; Type IV hypersensitivity reaction; choking.
2: Includes dyspnea exertional
Unresectable locally advanced or metastatic hormone receptor-positive/human epidermal growth factor receptor 2-negative breast cancer (HR-positive/HER2-negative mBC)
The following group of patients were excluded: history of significant cardiovascular disease (congestive heart failure greater than NYHA Class II, unstable angina or myocardial infarction within 6 months of enrollment, serious cardiac arrhythmia), clinically significant ECG abnormality, known active central nervous system metastases and/or carcinomatous meningitis, active hepatitis B or hepatitis C virus infection, active serious infection requiring antibiotics, and active chronic inflammatory bowel disease (ulcerative colitis, Crohn’s disease) and those with a history of bowel obstruction.
Table 6 lists Treatment Emergent Adverse Reactions (TEAR) from the pivotal TROPiCS-02 (IMMU-132-09) study, with incidences regardless of investigator assessment of causality, reported in this patient population.
Table 6: Adverse Reactions Reported in ≥1% of Patients with Metastatic HR-positive/HER2-negative Breast Cancer in Study IMMU-132-09 (TROPiCS-02)
| Adverse Reaction | Trodelvy (n=268) | Treatment of Physician’s Choice (n=249) | |||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Adverse Reaction | Trodelvy (n=268) | Treatment of Physician’s Choice (n=249) | |||||||||||||||
| Adverse Reaction | Trodelvy (n=268) | Treatment of Physician’s Choice (n=249) | |||||||||||||||
| Adverse Reaction | Trodelvy (n=268) | Treatment of Physician’s Choice (n=249) | |||||||||||||||
| Adverse Reaction | Trodelvy (n=268) | Treatment of Physician’s Choice (n=249) | |||||||||||||||
All Grades n (%) | Grade 3 n (%) | Grade 4 n (%) | All Grades n (%) | Grade 3 n (%) | Grade 4 n (%) | ||||||||||||
All Grades n (%) | Grade 3 n (%) | Grade 4 n (%) | All Grades n (%) | Grade 3 n (%) | Grade 4 n (%) | ||||||||||||
All Grades n (%) | Grade 3 n (%) | Grade 4 n (%) | All Grades n (%) | Grade 3 n (%) | Grade 4 n (%) | ||||||||||||
All Grades n (%) | Grade 3 n (%) | Grade 4 n (%) | All Grades n (%) | Grade 3 n (%) | Grade 4 n (%) | ||||||||||||
All Grades n (%) | Grade 3 n (%) | Grade 4 n (%) | All Grades n (%) | Grade 3 n (%) | Grade 4 n (%) | ||||||||||||
| Blood and lymphatic system disorders | |||||||||||||||||
| Neutropenia | 189 (70.5) | 86 (32.1) | 52 (19.4) | 136 (54.6) | 67 (26.9) | 30 (12.0) | |||||||||||
| Anemia | 98 (36.6) | 20 (7.5) | 0 | 69 (27.7) | 9 (3.6) | 0 | |||||||||||
| Leukopenia | 38 (14.2) | 14 (5.2) | 9 (3.4) | 25 (10.0) | 9 (3.6) | 6 (2.4) | |||||||||||
| Lymphopenia | 32 (11.9) | 9 (3.4) | 1 (0.4) | 29 (11.6) | 8 (3.2) | 1 (0.4) | |||||||||||
| Thrombocytopenia | 17 (6.3) | 0 | 1 (0.4) | 41 (16.5) | 3 (1.2) | 6 (2.4) | |||||||||||
| Febrile neutropenia | 16 (6.0) | 11 (4.1) | 5 (1.9) | 11 (4.4) | 10 (4.0) | 1 (0.4) | |||||||||||
| Ear and labyrinth disorders | |||||||||||||||||
| Vertigo | 9 (3.4) | 0 | 0 | 9 (3.6) | 1 (0.4) | 0 | |||||||||||
| Eye disorders | |||||||||||||||||
| Dry eye | 8 (3.0) | 0 | 0 | 4 (1.6) | 0 | 0 | |||||||||||
| Lacrimation increased | 4 (1.5) | 0 | 0 | 5 (2.0) | 0 | 0 | |||||||||||
| Vision blurred | 7 (2.6) | 0 | 0 | 2 (0.8) | 0 | 0 | |||||||||||
| Gastrointestinal disorders | |||||||||||||||||
| Diarrhea | 166 (61.9) | 25 (9.3) | 2 (0.7) | 57 (22.9) | 3 (1.2) | 0 | |||||||||||
| Nausea | 157 (58.6) | 2 (0.7) | 1 (0.4) | 87 (34.9) | 7 (2.8) | 0 | |||||||||||
| Constipation | 93 (34.7) | 1 (0.4) | 0 | 61 (24.5) | 0 | 0 | |||||||||||
| Vomiting | 64 (23.9) | 3 (1.1) | 0 | 39 (15.7) | 4 (1.6) | 0 | |||||||||||
| Abdominal pain | 53 (19.8) | 10 (3.7) | 0 | 34 (13.7) | 2 (0.8) | 0 | |||||||||||
| Abdominal pain upper | 26 (9.7) | 1 (0.4) | 0 | 15 (6.0) | 1 (0.4) | 0 | |||||||||||
| Stomatitis | 22 (8.2) | 1 (0.4) | 0 | 18 (7.2) | 3 (1.2) | 0 | |||||||||||
| Dyspepsia | 19 (7.1) | 0 | 0 | 7 (2.8) | 0 | 0 | |||||||||||
| Abdominal distension | 17 (6.3) | 0 | 0 | 8 (3.2) | 0 | 0 | |||||||||||
| Gastroesophageal reflux disease | 14 (5.2) | 0 | 0 | 9 (3.6) | 0 | 0 | |||||||||||
| Dry mouth | 16 (6.0) | 0 | 0 | 5 (2.0) | 0 | 0 | |||||||||||
| Hemorrhoids | 7 (2.6) | 0 | 0 | 3 (1.2) | 0 | 0 | |||||||||||
| Oral pain | 5 (1.9) | 0 | 0 | 6 (2.4) | 0 | 0 | |||||||||||
| Colitis | 6 (2.2) | 2 (0.7) | 1 (0.4) | 1 (0.4) | 1 (0.4) | 0 | |||||||||||
| Flatulence | 6 (2.2) | 0 | 0 | 1 (0.4) | 0 | 0 | |||||||||||
| Mouth ulceration | 5 (1.9) | 0 | 0 | 1 (0.4) | 1 (0.4) | 0 | |||||||||||
| Neutropenic colitis1 | 6 (2.2) | 2 (0.7) | 3 (1.1) | 0 | 0 | 0 | |||||||||||
| Gastritis | 4 (1.5) | 0 | 0 | 1 (0.4) | 0 | 0 | |||||||||||
| General disorders and administration site conditions | |||||||||||||||||
| Fatigue | 105 (39.2) | 16 (6.0) | 0 | 82 (32.9) | 9 (3.6) | 0 | |||||||||||
| Asthenia | 62 (23.1) | 6 (2.2) | 0 | 50 (20.1) | 5 (2.0) | 0 | |||||||||||
| Mucosal inflammation | 24 (9.0) | 1 (0.4) | 0 | 14 (5.6) | 0 | 0 | |||||||||||
| Chills | 10 (3.7) | 0 | 0 | 6 (2.4) | 0 | 0 | |||||||||||
| Malaise | 6 (2.2) | 0 | 0 | 3 (1.2) | 0 | 0 | |||||||||||
| Immune system disorders | |||||||||||||||||
| Hypersensitivity2 | 71 (26.5) | 4 (1.5) | 0 | 48 (19.3) | 1 (0.4) | 1 (0.4) | |||||||||||
| Infections and infestations | |||||||||||||||||
| Urinary tract infections | 26 (9.7) | 3 (1.1) | 0 | 24 (9.6) | 2 (0.8) | 0 | |||||||||||
| Upper respiratory tract infection | 7 (2.6) | 0 | 0 | 4 (1.6) | 0 | 0 | |||||||||||
| Pneumonia | 5 (1.9) | 3 (1.1) | 0 | 9 (3.6) | 5 (2.0) | 1 (0.4) | |||||||||||
| Sepsis | 4 (1.5) | 2 (0.7) | 2 (0.7) | 2 (0.8) | 1 (0.4) | 1 (0.4) | |||||||||||
| Candida infection | 3 (1.1) | 0 | 0 | 2 (0.8) | 0 | 0 | |||||||||||
| Investigations | |||||||||||||||||
| Blood alkaline phosphatase increased | 25 (9.3) | 1 (0.4) | 0 | 27 (10.8) | 2 (0.8) | 0 | |||||||||||
| Weight decreased | 15 (5.6) | 0 | 0 | 14 (5.6) | 0 | 0 | |||||||||||
| Gamma-glutamyltransferase increased | 12 (4.5) | 5 (1.9) | 1 (0.4) | 8 (3.2) | 2 (0.8) | 0 | |||||||||||
| Blood lactate dehydrogenase increased | 9 (3.4) | 0 | 0 | 13 (5.2) | 0 | 0 | |||||||||||
| Blood creatinine increased | 7 (2.6) | 1 (0.4) | 0 | 4 (1.6) | 2 (0.8) | 0 | |||||||||||
| Electrocardiogram QT prolonged | 3 (1.1) | 0 | 0 | 0 | 0 | 0 | |||||||||||
| Blood sodium decreased | 3 (1.1) | 1 (0.4) | 0 | 1 (0.4) | 0 | 0 | |||||||||||
| Bilirubin conjugated increased | 3 (1.1) | 1 (0.4) | 0 | 3 (1.2) | 0 | 1 (0.4) | |||||||||||
| Metabolism and nutrition disorders | |||||||||||||||||
| Decreased appetite | 57 (21.3) | 4 (1.5) | 0 | 52 (20.9) | 2 (0.8) | 0 | |||||||||||
| Hypokalemia | 29 (10.8) | 6 (2.2) | 0 | 9 (3.6) | 1 (0.4) | 0 | |||||||||||
| Hypomagnesemia | 16 (6.0) | 0 | 0 | 9 (3.6) | 0 | 0 | |||||||||||
| Hypoalbuminemia | 12 (4.5) | 0 | 0 | 7 (2.8) | 0 | 0 | |||||||||||
| Hypophosphatemia | 11 (4.1) | 1 (0.4) | 0 | 5 (2.0) | 1 (0.4) | 0 | |||||||||||
| Dehydration | 10 (3.7) | 4 (1.5) | 0 | 9 (3.6) | 3 (1.2) | 0 | |||||||||||
| Hypercalcemia | 10 (3.7) | 2 (0.7) | 2 (0.7) | 8 (3.2) | 2 (0.8) | 0 | |||||||||||
| Musculoskeletal and connective tissue disorders | |||||||||||||||||
| Arthralgia | 40 (14.9) | 1 (0.4) | 0 | 30 (12.0) | 1 (0.4) | 0 | |||||||||||
| Muscle spasms | 19 (7.1) | 0 | 0 | 11 (4.4) | 0 | 0 | |||||||||||
| Pain in extremity | 17 (6.3) | 0 | 0 | 13 (5.2) | 2 (0.8) | 0 | |||||||||||
| Nervous system disorders | |||||||||||||||||
| Headache | 44 (16.4) | 1 (0.4) | 0 | 36 (14.5) | 2 (0.8) | 0 | |||||||||||
| Dizziness | 22 (8.2) | 0 | 0 | 11 (4.4) | 1 (0.4) | 0 | |||||||||||
| Dysgeusia | 12 (4.5) | 0 | 0 | 12 (4.8) | 0 | 0 | |||||||||||
| Memory impairment | 4 (1.5) | 0 | 0 | 3 (1.2) | 0 | 0 | |||||||||||
| Psychiatric disorders | |||||||||||||||||
| Insomnia | 21 (7.8) | 0 | 0 | 19 (7.6) | 0 | 0 | |||||||||||
| Confusional state | 5 (1.9) | 0 | 0 | 3 (1.2) | 2 (0.8) | 0 | |||||||||||
| Renal and urinary disorders | |||||||||||||||||
| Dysuria | 9 (3.4) | 0 | 0 | 4 (1.6) | 0 | 0 | |||||||||||
| Proteinuria | 3 (1.1) | 0 | 0 | 0 | 0 | 0 | |||||||||||
| Respiratory, thoracic and mediastinal disorders | |||||||||||||||||
| Dyspnea | 49 (18.3) | 5 (1.9) | 0 | 39 (15.7) | 10 (4.0) | 1 (0.4) | |||||||||||
| Cough | 33 (12.3) | 0 | 0 | 18 (7.2) | 1 (0.4) | 0 | |||||||||||
| Epistaxis | 22 (8.2) | 0 | 0 | 6 (2.4) | 1 (0.4) | 0 | |||||||||||
| Rhinorrhea | 13 (4.9) | 0 | 0 | 4 (1.6) | 0 | 0 | |||||||||||
| Oropharyngeal pain | 10 (3.7) | 0 | 0 | 1 (0.4) | 0 | 0 | |||||||||||
| Dysphonia | 3 (1.1) | 0 | 0 | 1 (0.4) | 0 | 0 | |||||||||||
| Rhinitis allergic | 8 (3.0) | 0 | 0 | 1 (0.4) | 0 | 0 | |||||||||||
| Skin and subcutaneous tissue disorders | |||||||||||||||||
| Alopecia | 128 (47.8) | 0 | 0 | 46 (18.5) | 0 | 0 | |||||||||||
| Pruritus | 32 (11.9) | 1 (0.4) | 0 | 6 (2.4) | 0 | 0 | |||||||||||
| Rash | 24 (9.0) | 0 | 0 | 14 (5.6) | 2 (0.8) | 0 | |||||||||||
| Dry skin | 17 (6.3) | 0 | 0 | 8 (3.2) | 0 | 0 | |||||||||||
| Rash maculo-papular | 13 (4.9) | 2 (0.7) | 0 | 6 (2.4) | 1 (0.4) | 0 | |||||||||||
| Skin hyperpigmentation | 7 (2.6) | 0 | 0 | 3 (1.2) | 0 | 0 | |||||||||||
| Dermatitis acneiform | 7 (2.6) | 0 | 0 | 1 (0.4) | 0 | 0 | |||||||||||
| Pain of skin | 5 (1.9) | 0 | 0 | 2 (0.8) | 0 | 0 | |||||||||||
| Nail disorder | 4 (1.5) | 0 | 0 | 0 | 0 | 0 | |||||||||||
| Eczema | 4 (1.5) | 0 | 0 | 1 (0.4) | 0 | 0 | |||||||||||
| Vascular disorders | |||||||||||||||||
| Hypertension | 17 (6.3) | 5 (1.9) | 0 | 11 (4.4) | 1 (0.4) | 0 | |||||||||||
| Hypotension | 13 (4.9) | 1 (0.4) | 2 (0.7) | 8 (3.2) | 4 (1.6) | 0 | |||||||||||
| Hot flush | 9 (3.4) | 0 | 0 | 8 (3.2) | 0 | 0 | |||||||||||
| Flushing | 3 (1.1) | 0 | 0 | 1 (0.4) | 0 | 0 | |||||||||||
Treatment of physician’s choice included one of the following single agents: eribulin (n=130), capecitabine (n=22), gemcitabine (n=56), or vinorelbine (n=63).
Adverse events terms were coded using Medical Dictionary for Regulatory Activities (MedDRA) version 25.0.
‘Neutrophil count decreased’, ‘White blood cell count decreased’, ‘Lymphocyte count decreased’, ‘Platelet count decreased’, ‘Haemoglobin decreased’, and ‘Red blood cell count decreased’ have been re-coded to Neutropenia, Leukopenia, Lymphopenia, Thrombocytopenia, and Anemia, correspondingly.
1: Includes the preferred term of neutropenic colitis and events reported as typhlitis.
2: Hypersensitivity events include events with onset dates on day of or 1 day after dose. Includes events coded to the following preferred terms: cough; dyspnea; rash; pruritus; stomatitis; hypotension; rash maculopapular; flushing; erythema; mouth ulceration; dermatitis acneiform; eczema; rash erythematous; conjunctivitis; generalised edema; infusion relation reaction; rhinitis allergic; urticaria; blister; cheilitis; contrast media allergy; dermatitis; dermatitis exfoliative generalised; drug hypersensitivity; eye edema; edema; periorbital edema; rash pruritic; sneezing.
8.3 Less Common Clinical Trial Adverse Reactions
Less common clinical trial adverse reactions (<1%) in metastatic triple-negative breast cancer patients treated with Trodelvy in ASCENT included:
Ear and labyrinth disorders: ear pain, vertigo
Gastrointestinal disorders: neutropenic colitis, retching, glossodynia
General disorders and administration site conditions: chest pain, non-cardiac chest pain, xerosis
Immune system disorders: anaphylactic reaction
Infections and infestations: bronchitis, oral herpes, sepsis, diverticulitis, genital herpes
Injury, poisoning and procedural complications: infusion related reaction
Investigations: activated partial thromboplastin time prolonged, blood lactate dehydrogenase increased, weight increased
Metabolism and nutrition disorders: appetite disorder
Musculoskeletal and connective tissue disorders: musculoskeletal pain, neck pain, muscle fatigue
Psychiatric disorders: anxiety
Renal and urinary disorders: proteinuria
Reproductive system and breast disorders: vulvovaginal dryness
Respiratory, thoracic and mediastinal disorders: hypoxia, nasal congestion, rhinorrhea
Skin and subcutaneous tissue disorders: dermatitis, night sweats, skin discolouration, urticaria, eczema, macule, onychoclasis, skin hyperpigmentation
Vascular disorders: flushing, hypertension
Less common clinical trial adverse reactions (<1%) in HR-positive/HER2-negative metastatic breast cancer patients treated with Trodelvy in TROPiCS-02 included:
Ear and labyrinth disorders: tinnitus
Gastrointestinal disorders: oral dysesthesia, enteritis
General disorders and administration site conditions: xerosis
Hepatobiliary disorders: hypertransaminasemia
Infections and infestations: rash pustular, bacteremia
Injury, poisoning and procedural complications: infusion related reaction
Nervous system disorders: cholinergic syndrome
Respiratory, thoracic and mediastinal disorders: nasal ulcer
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry, and Other Quantitative Data
Clinical Trial Findings
Table 7: Most Common Hematologic Laboratory Abnormalities in ASCENT Study (≥10% in Either Group) in Patients with Metastatic Triple-negative Breast Cancer
| Hematologic Laboratory Abnormality | Trodelvy (n=258) | Treatment of Physician’s Choice (n=224) | |||||||||||
All Grades n (%) | Grade 3 n (%) | Grade 4 n (%) | All Grades n (%) | Grade 3 n (%) | Grade 4 n (%) | ||||||||
| Decreased hemoglobin | 242 (93.8) | 23 (8.9) | 0 | 189 (84.3) | 13 (5.8) | 0 | |||||||
| Decreased leukocytes | 226 (87.6) | 91 (35.3) | 15 (5.8) | 157 (70.1) | 45 (20.1) | 12 (5.4) | |||||||
| Decreased lymphocytes | 202 (78.3) | 71 (27.5) | 10 (3.9) | 152 (67.9) | 50 (22.3) | 4 (1.8) | |||||||
| Decreased neutrophils | 201 (77.9) | 82 (31.8) | 44 (17.1) | 134 (59.8) | 47 (21.0) | 33 (14.7) | |||||||
| Decreased platelets | 58 (22.5) | 2 (0.8) | 1 (0.4) | 72 (32.1) | 5 (2.2) | 1 (0.4) | |||||||
Table 8: Most Common Hematologic Laboratory Abnormalities in TROPiCS-02 Study (≥10% in Either Group) in Patients with HR-positive/HER2-negative Metastatic Breast Cancer
| Hematologic Laboratory Abnormality | Trodelvy (n=268) | Treatment of Physician’s Choice (n=249) | |||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Hematologic Laboratory Abnormality | Trodelvy (n=268) | Treatment of Physician’s Choice (n=249) | |||||||||||||
All Grades n (%) | Grade 3 n (%) | Grade 4 n (%) | All Grades n (%) | Grade 3 n (%) | Grade 4 n (%) | ||||||||||
All Grades n (%) | Grade 3 n (%) | Grade 4 n (%) | All Grades n (%) | Grade 3 n (%) | Grade 4 n (%) | ||||||||||
| Hematology | |||||||||||||||
| Decreased hemoglobin | 193 (72.8) | 20 (7.5) | 0 | 143 (59.3) | 12 (5.0) | 0 | |||||||||
| Decreased leukocytes | 235 (88.7) | 69 (26.0) | 32 (12.1) | 177 (73.4) | 51 (21.2) | 11 (4.6) | |||||||||
| Decreased lymphocytes | 174 (65.7) | 52 (19.6) | 4 (1.5) | 114 (47.3) | 30 (12.4) | 3 (1.2) | |||||||||
| Decreased neutrophils | 220 (83.0) | 84 (31.7) | 55 (20.8) | 163 (67.6) | 65 (27.0) | 32 (13.3) | |||||||||
| Decreased platelets | 57 (21.5) | 2 (0.8) | 3 (1.1) | 72 (29.9) | 4 (1.7) | 5 (2.1) | |||||||||
| Eosinophilia | 35 (13.2) | 0 | 0 | 11 (4.6) | 0 | 0 | |||||||||
| Chemistry | |||||||||||||||
| Increased glucose | 97 (37.0) | 0 | 0 | 73 (30.8) | 0 | 0 | |||||||||
| Decreased albumin | 83 (31.7) | 0 | 0 | 66 (28.0) | 1 (0.4) | 0 | |||||||||
| Decreased creatinine clearance | 64 (24.3) | 6 (2.3) | 0 | 46 (19.4) | 2 (0.8) | 1 (0.4) | |||||||||
| Increased alkaline phosphatase | 62 (23.6) | 0 | 0 | 56 (23.6) | 2 (0.8) | 0 | |||||||||
| Decreased potassium | 58 (22.1) | 10 (3.8) | 1 (0.4) | 29 (12.2) | 1 (0.4) | 0 | |||||||||
| Increased alanine aminotransferase | 56 (21.2) | 3 (1.1) | 0 | 74 (31.2) | 5 (2.1) | 0 | |||||||||
| Decreased sodium | 51 (19.4) | 2 (0.8) | 0 | 40 (16.9) | 0 | 1 (0.4) | |||||||||
| Decreased magnesium | 50 (19.2) | 0 | 2 (0.8) | 37 (15.9) | 0 | 0 | |||||||||
| Decreased phosphate | 45 (17.4) | 0 | 0 | 24 (10.4) | 0 | 0 | |||||||||
| Increased phosphate | 42 (16.2) | 0 | 0 | 39 (16.9) | 0 | 0 | |||||||||
| Increased lactate dehydrogenase | 44 (16.9) | 0 | 0 | 65 (28.0) | 0 | 0 | |||||||||
| Increase aspartate aminotransferase | 43 (16.3) | 4 (1.5) | 0 | 59 (24.9) | 3 (1.3) | 0 | |||||||||
| Increased potassium | 37 (14.1) | 3 (1.1) | 2 (0.8) | 22 (9.3) | 0 | 0 | |||||||||
9 DRUG INTERACTIONS
9.2 Drug Interactions Overview
No drug-drug interaction studies were conducted with sacituzumab govitecan or its components. Inhibitors or inducers of UGT1A1 may increase or decrease SN-38 exposure, respectively.
Concomitant administration of Trodelvy with inhibitors of UGT1A1 may increase the incidence of adverse reactions due to potential increase in systemic exposure to SN-38 [see 7 Warnings and Precautions and 10 Clinical Pharmacology]. Avoid administering UGT1A1 inhibitors with Trodelvy.
Exposure to SN-38 may be reduced in patients concomitantly receiving UGT1A1 enzyme inducers [see 7 Warnings and Precautions and 10 Clinical Pharmacology]. Avoid administering UGT1A1 inducers with Trodelvy.
9.3 Drug-Behavioural Interactions
Interactions with behavioural factors have not been established.
9.4 Drug-Drug Interactions
The drugs listed in Table 9 are based on either drug interaction case reports or studies, or potential interactions due to the expected magnitude and seriousness of the interaction (i.e., those identified as contraindicated).
Table 9: Potential Drug-Drug Interactions
| Proper/Common name | Source of Evidence | Effect | Clinical comment |
| UGT1A1 inhibitors | Theoretical | Increased SN-38 exposure | Avoid administering UGT1A1 inhibitors (e.g., propofol, ketoconazole, EGFR tyrosine kinase inhibitors) with Trodelvy |
| UGT1A1 inducers | Theoretical | Decreased SN-38 exposure | Avoid administering UGT1A1 inducers (e.g., carbamazepine, phenytoin, rifampicin, protease inhibitors) with Trodelvy |
SN-38 = the small molecule moiety of sacituzumab govitecan; UGT1A1 = uridine diphosphate-glucuronosyl transferase 1A1
9.5 Drug-Food Interactions
Interactions with food have not been established.
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10 Clinical Pharmacology
10.1 Mechanism of Action
Trodelvy (sacituzumab govitecan) is a Trop-2-directed antibody-drug conjugate (ADC) composed of three components: 1) sacituzumab is a humanized antibody that recognizes Trop-2, covalently linked to 2) a topoisomerase I inhibitor, SN-38, via 3) a hydrolysable linker (CL2A).
Pharmacology data suggest that sacituzumab govitecan binds to Trop-2-expressing cancer cells and is internalized with the subsequent release of SN-38 via hydrolysis of the linker. SN-38 interacts with topoisomerase I and prevents re-ligation of topoisomerase I-induced single strand breaks. The resulting DNA damage leads to apoptosis and cell death. Sacituzumab govitecan decreased tumor growth in mouse xenograft models of triple-negative breast cancer.
10.2 Pharmacodynamics
The Trodelvy exposure-response relationships and pharmacodynamic time course for efficacy have not been fully characterized.
Cardiac electrophysiology
The effect of Trodelvy on QTc interval prolongation was studied in Phase 3 ASCENT substudy (Study IMMU-132-05, n=17). The maximum mean change from baseline was 9.7 ms (90% CI 2.7, 16.8 ms). A positive exposure-response relationship was observed between QTcF increases and SN-38 concentrations.
10.3 Pharmacokinetics
The serum pharmacokinetics of sacituzumab govitecan and SN-38 were evaluated in patients with mBC who received sacituzumab govitecan as a single agent at a dose of 10 mg/kg. The pharmacokinetic parameters of sacituzumab govitecan and free SN-38 are presented in Table 10.
Table 10: Summary of Mean PK Parameters (CV%) of Sacituzumab Govitecan and Free SN-38*
| Sacituzumab govitecan (N=693) | Free SN-38 (N=681) | |
|---|---|---|
| Cmax[ng/mL] | 239000 (11%) | 98.0 (45%) |
| AUC0-168[ng*h/mL] | 5640000 (22%) | 3696 (56%) |
*Parameters are estimated based on the population PK analyses Cmax: maximum serum concentration from 0-168 hours after the first dose
AUC0-168: area under serum concentration curve through 168 hours after the first dose
Distribution:
Based on the population pharmacokinetic analysis, the apparent mean volume of distribution at steady state for sacituzumab govitecan was 3.6 L.
Metabolism:
No metabolism studies with sacituzumab govitecan have been conducted. SN-38 (the small molecule moiety of sacituzumab govitecan) is metabolized via UGT1A1. The glucuronide metabolite of SN-38 (SN-38G) was detectable in the serum of patients.
Elimination
The median elimination half-life (t1/2) of sacituzumab govitecan and free SN-38 in patients with metastatic triple negative breast cancer was 23.4 and 17.6 hours, respectively. Based on the population pharmacokinetic analysis, the estimated mean (%CV) clearance of the sacituzumab govitecan is 0.13L/h (12%).
Special Populations and Conditions
- Pediatrics: Sacituzumab govitecan was not studied in patients under 18 years of age.
- Genetic Polymorphism: SN-38 is metabolized via UGT1A1. Genetic variants of the UGT1A1 gene such as the UGT1A1*28 allele lead to reduced UGT1A1 enzyme activity. Individuals who are homozygous for the UGT1A1*28 allele are potentially at increased risk for neutropenia, febrile neutropenia, and anemia from Trodelvy [see 7 Warnings and Precautions]. Approximately 20% of the Black or African American population, 10% of the White population, and 2% of the East Asian population are homozygous for the UGT1A1*28 allele. Decreased function alleles other than UGT1A1*28 may be present in certain populations.
Hepatic Insufficiency: The exposure of sacituzumab govitecan is similar in patients with mild hepatic impairment (bilirubin ≤ ULN and AST > ULN, or bilirubin >1.0 to ≤1.5× ULN and AST of any level; n=257) to patients with normal hepatic function (bilirubin and AST ≤ ULN; n=526).
No dedicated moderate (total bilirubin >1.5 to 3.0 x ULN) or severe (total bilirubin >3.0 x ULN) hepatic impairment study was conducted, thus sacituzumab govitecan and free SN-38 exposures are unknown in these populations.
- Renal Insufficiency: Renal elimination is known to contribute minimally to the excretion of SN-38, the small molecule moiety of sacituzumab govitecan. No dedicated severe (CLcr 15 to 29 mL/min) renal impairment study was conducted, thus there are no data available for this population.
10.4 Immunogenicity
All therapeutic proteins have the potential for immunogenicity.
The detection of antibody formation is highly dependent on the sensitivity and specificity of the assay. Additionally, the observed incidence of anti-drug antibody (including neutralizing antibody) positivity in an assay may be influenced by several factors including assay methodology, sample handling, timing of sample collection, concomitant medications, and underlying disease. Any differences encountered preclude the comparison of the incidence of anti-drug antibodies in the studies described below with the incidence of anti-drug antibodies in other studies, including those of Trodelvy.
Across clinical studies in patients treated with Trodelvy, 9 (1.1%) of 785 patients developed antibodies to sacituzumab govitecan; 6 of these patients (0.8% of all patients treated with Trodelvy) had neutralizing antibodies against sacituzumab govitecan. Because of the low incidence of anti-drug antibodies, the effect of these antibodies on the pharmacokinetics, pharmacodynamics, safety and/or efficacy of sacituzumab govitecan is unknown.
11 Storage, Stability, and Disposal
Trodelvy (sacituzumab govitecan) for injection is a sterile, off-white to yellowish lyophilized powder in a single-dose vial. Each Trodelvy vial is individually boxed in a carton containing one 180 mg vial.
Store vials in a refrigerator at 2°C to 8°C in the original carton to protect from light until time of reconstitution. Do not freeze.
12 Special Handling Instructions
Trodelvy is a cytotoxic drug. Follow applicable special handling and disposal procedures.
PART 2: Scientific Information
13 Pharmaceutical Information
Drug Substance
Proper name: Sacituzumab govitecan
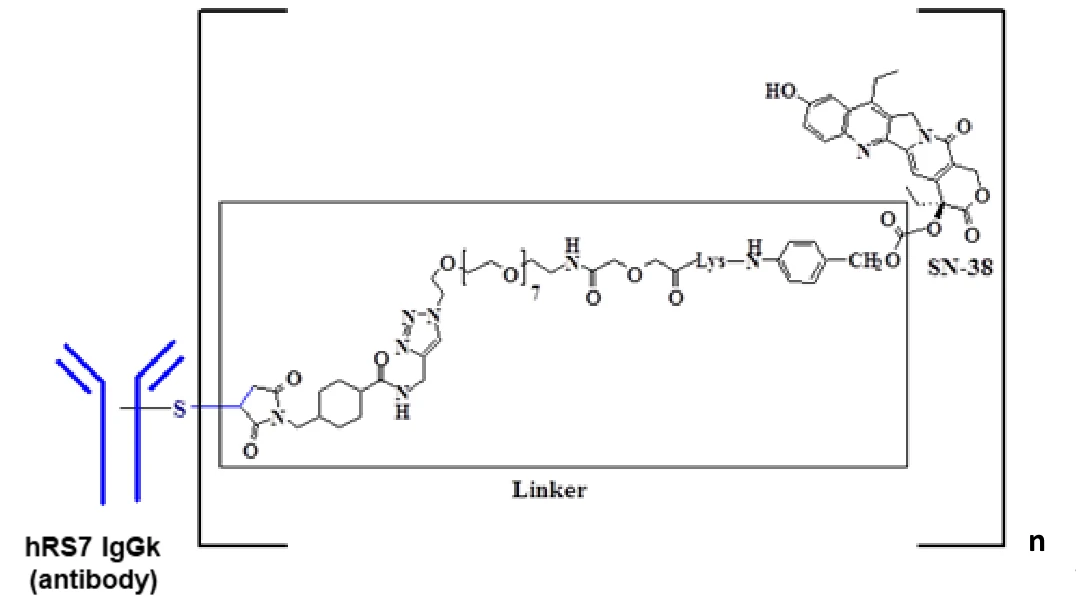
Chemical name: Sacituzumab govitecan is a Trop-2 directed antibody and topoisomerase inhibitor conjugate, composed of the following three components:
- The humanized monoclonal antibody, hRS7 IgG1κ (also called sacituzumab), which binds to Trop-2 (the trophoblast cell-surface antigen-2);
- The drug SN-38, a topoisomerase inhibitor; and
- A hydrolysable linker (called CL2A), which links the humanized monoclonal antibody to SN-38.
Molecular formula and molecular mass: approximately 160 kilodaltons
Structural formula: Sacituzumab govitecan contains on average 7 to 8 molecules of SN-38 per antibody molecule. Sacituzumab govitecan has the following chemical structure:
Physicochemical properties: Trodelvy (sacituzumab govitecan) for injection is a sterile, preservative-free, off-white to yellowish lyophilized powder.
Pharmaceutical standard: Manufacturer’s Standard
Product Characteristics:
The recombinant monoclonal antibody is produced by mammalian (murine myeloma) cells, while the small molecule components SN-38 and CL2A are produced by chemical synthesis.
14 Clinical Trials
14.1 Clinical Trials by Indication
Unresectable Locally Advanced or Metastatic Triple-Negative Breast Cancer (mTNBC)
The efficacy assessment of Trodelvy in the treatment of adult patients with unresectable locally advanced or metastatic triple-negative breast cancer (mTNBC) who have received at least two prior therapies was based on the pivotal ASCENT (IMMU-132-05) study. Table 11 summarizes the patient demographics for the ASCENT (IMMU-132-05) study.
Table 11: Summary of Patient Demographics for Clinical Trials in Metastatic Triple-negative Breast Cancer
| Study # | Study design | Dosage, route of administration and duration | Study subjects (n) | Median age (Range) | Sex |
| ASCENT (IMMU-132-05) | Phase 3, multicentre, open-label, randomized trial | 10 mg/kg IV on Days 1 and 8 of a 21-day cycle Trodelvy or Treatment of Physician’s Choice (TPC) of single agent chemotherapy | Total: 529 Trodelvy:267 TPC:262 | 54 (27-82) | 527 female 2 male |
ASCENT study was conducted in 529 patients with unresectable locally advanced or metastatic triple-negative breast cancer (mTNBC) who had relapsed after at least two prior chemotherapies for breast cancer (one of which could be in the neoadjuvant or adjuvant setting provided progression occurred within a 12 month period). All patients received previous taxane treatment in either the adjuvant, neoadjuvant, or advanced stage unless they had a contraindication or were intolerant to taxanes during or at the end of the first taxane cycle. Poly-ADP ribose polymerase (PARP) inhibitors were allowed as one of the two prior chemotherapies for patients with a documented germ-line BRCA1/BRCA2 mutation.
The median age of patients in the full population (n=529) was 54 years (range: 27–82 years); 99.6% were female; 79% were White, 12% were Black/African American; and 81% of patients were < 65 years of age. All patients had an ECOG performance status of 0 (43%) or 1 (57%). Forty-two percent of patients had hepatic metastases, 8% were BRCA1/BRCA2 mutational status positive, and 70% were TNBC at diagnosis.
Overall, 29% of patients had received prior PD-1/PD-L1 therapy. Thirteen percent of patients in the Trodelvy group in the full population received only 1 prior line of systemic therapy in the metastatic setting.
Patients with stable brain metastases were eligible. Magnetic resonance imaging (MRI) to determine brain metastases was required prior to enrollment for patients with known or suspected brain metastases. The study included a pre-defined maximum of 15% for patients with brain metastases. Twelve percent had baseline brain metastases previously treated and stable (n=61; 32 on Trodelvy arm and 29 on single agent chemotherapy arm).
The following group of patients were excluded from clinical study: known history of Gilbert’s disease or bone-only disease, unstable angina, myocardial infarction, or congestive heart failure present within 6 months of randomization or a clinically significant cardiac arrhythmia (other than stable atrial fibrillation) requiring anti-arrhythmia therapy, active infection requiring IV antibiotic use within 1 week of treatment initiation, Human immunodeficiency virus (HIV), hepatitis B, or hepatitis C positive, active chronic inflammatory bowel disease (ulcerative colitis, Crohn’s disease), clinically significant bleeding, intestinal obstruction, or gastrointestinal perforation within 6 months of randomization, and clinically significant active chronic obstructive pulmonary disease or other moderate-to-severe chronic respiratory illness present within 6 months of randomization.
Patients were randomized 1:1 to receive Trodelvy 10 mg/kg as an intravenous infusion on Days 1 and 8 of a 21-day (n=267) or TPC single agent chemotherapy per the authorised labeling (n=262). TPC was determined by the investigator before randomization from one of the following single-agent choices: eribulin (n=139), capecitabine (n=33), gemcitabine (n=38), or vinorelbine (except if patient had ≥ Grade 2 neuropathy, n=52).
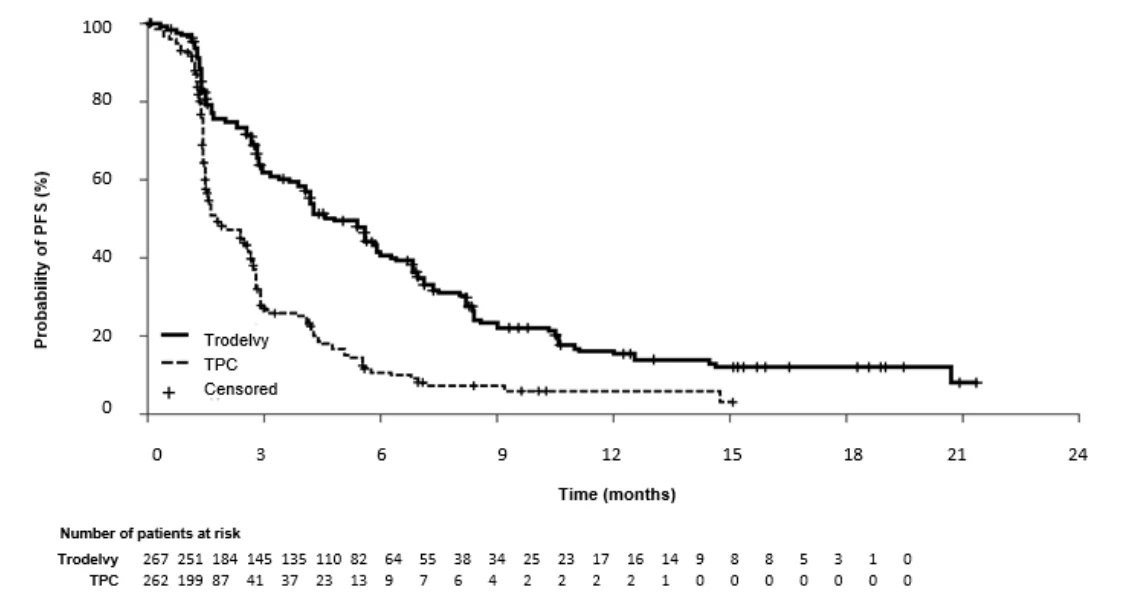
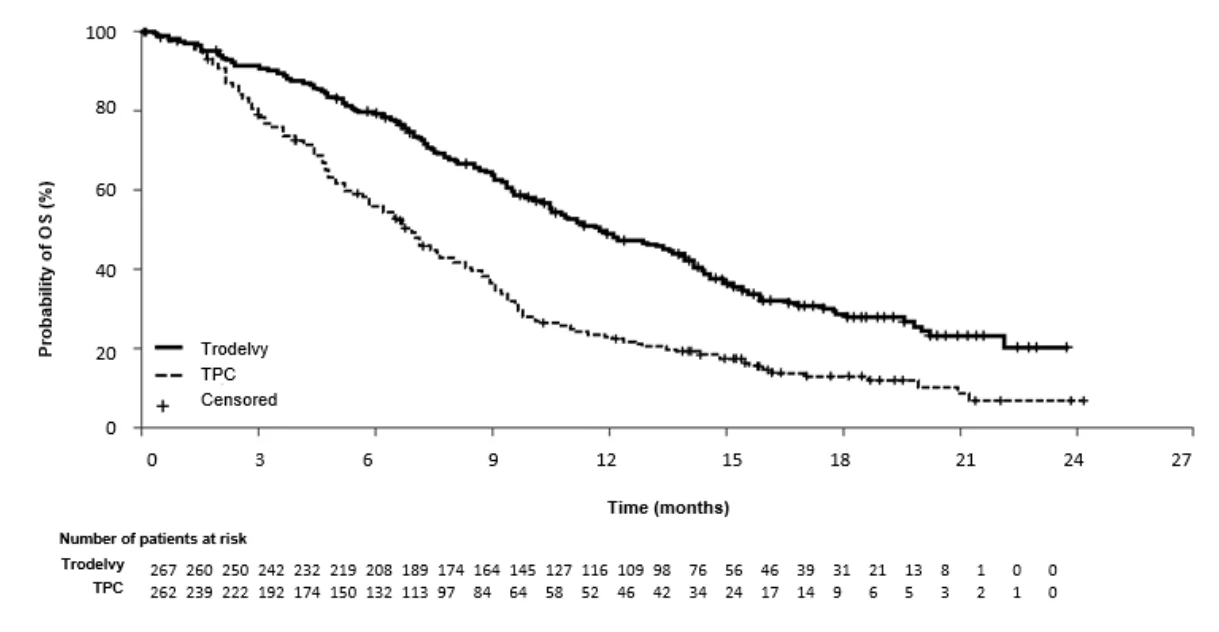
Patients were treated until disease progression or unacceptable toxicity. The major efficacy outcome was progression-free survival (PFS) as measured by a blinded, independent, centralized group of radiology experts using Response Evaluation Criteria in Solid Tumors (RECIST) v1.1 criteria. Major secondary outcomes included overall survival (OS), objective response rate (ORR), and duration of response (DOR). Results are shown in Table 12, Figure 1 and Figure 2.
Table 12: Efficacy Results from ASCENT (all randomized patients, ITT population)
Trodelvy n=267 | Treatment of physician’s choice (TPC) n=262 | ||||||
|---|---|---|---|---|---|---|---|
| Progression-free survival1 | |||||||
| Number of events (%) | 190 (71.2) | 171 (65.3) | |||||
| Median PFS in months (95% CI) | 4.8 (4.1, 5.8) | 1.7 (1.5, 2.5) | |||||
| Hazard ratio (95% CI) | 0.43 (0.35, 0.54) | ||||||
| p-value2 | <0.0001 | ||||||
| Overall Survival | |||||||
| Number of deaths (%) | 179 (67.0) | 206 (78.6) | |||||
| Median OS in months (95% CI) | 11.8 (10.5, 13.8) | 6.9 (5.9, 7.7) | |||||
| Hazard ratio (95% CI) | 0.51 (0.41, 0.62) | ||||||
| p-value2 | <0.0001 | ||||||
1 PFS is defined as the time from the date of randomization to the date of the first radiological disease progression or death due to any cause, whichever comes first.
2 Stratified log-rank test adjusted for stratification factors: number of prior chemotherapies, presence of known brain metastases at study entry, and region.
CI = Confidence Interval
Figure 1: Progression free survival (all randomized patients, ITT population) by BICR in ASCENT
Figure 2: Overall survival (all randomized patients, ITT population) in ASCENT
 |
|---|
For the ITT population, the number of responders was 83 (31%) in the Trodelvy arm and 11 (4%) in the control arm. The median duration of response was 6.3 months in the treatment arm and 3.6 months in the control arm.
In the BMNeg population (n=468), the median PFS in the Trodelvy arm was 5.6 months (95% CI: 4.3, 6.3) with an estimated HR of 0.41 (95% CI: 0.32, 0.52). In the brain metastases positive population (BMPos) (n=61), the median PFS in the Trodelvy arm was 2.8 months (95% CI: 1.5, 3.9) with an estimated HR of 0.65 (95% CI: 0.35, 1.22).
In the BMNeg population (n=468), the median OS in the Trodelvy arm was 12.1 months (95% CI: 10.7, 14.0) with an estimated HR of 0.48 (95% CI: 0.38, 0.59). In the BMPos population (n=61), the median OS in the Trodelvy arm was 6.8 months (95% CI: 4.7, 14.1) with an estimated HR of 0.87 (95% CI: 0.47, 1.63).
Unresectable Locally Advanced or Metastatic Hormone Receptor-Positive, Human Epidermal Growth Factor Receptor 2-Negative Breast Cancer (HR-positive/HER2-negative mBC)
The efficacy of Trodelvy in the treatment of adult patients with unresectable locally advanced or metastatic HR-positive/HER2-negative breast cancer was evaluated in the pivotal TROPiCS-02 (IMMU-132-09) study. Table 13 summarizes the patient demographics for the TROPiCS-02 (IMMU-132-09) study.
Table 13: Summary of Patient Demographics for Clinical Trials in Metastatic HR-positive/HER2-negative Breast Cancer
| Study # | Study design | Dosage, route of administration and duration | Study subjects (n) | Median age (Range) | Sex |
|---|---|---|---|---|---|
| TROPiCS-02 (IMMU-132-09) | Phase 3, multicentre, open-label, randomized trial | 10 mg/kg, intravenous, on Days 1 and 8 of a 21-day cycle Trodelvy or Treatment of Physician’s Choice (TPC) of single agent chemotherapy, intravenous or orally | Total: 543 Trodelvy: 272 TPC: 271 | 56 (27-86) | 538 female 5 male |
The TROPiCS-02 study, an open-label, multicentre, randomized trial, enrolled 543 patients with unresectable locally advanced or metastatic HR-positive/HER2-negative (IHC 0, IHC 1+ or IHC 2+/ISH-) breast cancer whose disease has progressed after the following in any setting: a CDK 4/6 inhibitor, endocrine therapy, and a taxane; patients received at least two prior chemotherapies in the metastatic setting (one of which could be in the neoadjuvant or adjuvant setting if progression or recurrence occurred within 12 months).
Patients were randomized (1:1) to receive either Trodelvy (n=272) or one of the following chemotherapies (n=271) as determined by the investigator before randomization: eribulin (n=130), vinorelbine (n=63), gemcitabine (n=56), or capecitabine (n=22). Randomization was stratified by the following factors: prior chemotherapy regimens for metastatic disease (2 vs. 3-4), visceral metastasis (Yes or No), and endocrine therapy in the metastatic setting for at least 6 months (Yes or No).
Patients were treated until disease progression or unacceptable toxicity. Administration of Trodelvy was permitted beyond RECIST-defined disease progression if the patient was clinically stable and considered by the investigator to be deriving clinical benefit. The primary efficacy outcome measure was PFS as determined by BICR per RECIST v1.1. Additional efficacy measures included OS, ORR by BICR, and DOR by BICR.
The median age of patients in the study population was 56 years (range: 27–86 years), and 26% of patients were 65 years or over. The majority of patients were female (99%); 67% were White, 4% were Black and 3% were Asian, and 26% were of unknown race. Patients received a median of 7 (range: 3 to 17) prior systemic regimens in any setting and 3 (range: 0 to 8) prior systemic chemotherapy regimens in the metastatic setting. Approximately 42% of patients had 2 prior chemotherapy regimens for treatment of metastatic disease compared to 58% of patients who had 3 to 4 prior chemotherapy regimens and all patients had an ECOG performance status of 0 (44%) or 1 (56%). Ninety-five percent of patients had visceral metastases. Most patients received endocrine therapy in the metastatic setting for ≥6 months (86%). The median follow-up duration was 12.5 months (range: 0.0-35.5).
The efficacy results are summarized in Table 14, Figure 3, and Figure 4.
Table 14: Efficacy Results from TROPiCS-02
Trodelvy n=272 | Treatment of Physician’s Choice (TPC) n=271 | |||||||
|---|---|---|---|---|---|---|---|---|
| Progression-free survival by BICR1 | ||||||||
| Median PFS in months (95% CI) | 5.5 (4.2, 7.0) | 4.0 (3.1, 4.4) | ||||||
| Hazard ratio (95% CI) | 0.661 (0.529, 0.826) | |||||||
| p-value2 | 0.0003 | |||||||
| Overall Survival3 | ||||||||
| Median OS in months (95% CI) | 14.4 (13.0, 15.7) | 11.2 (10.1, 12.7) | ||||||
| Hazard ratio (95% CI) | 0.789 (0.646, 0.964) | |||||||
| p-value2 | 0.0200 | |||||||
1 PFS is defined as the time from the date of randomization to the date of the first radiological disease progression or death due to any cause, whichever comes first. PFS was based on the primary analysis. 2 Stratified log-rank test adjusted for stratification factors: prior chemotherapy regimens for metastatic disease (2 vs. 3-4), visceral metastasis (Yes or No), and endocrine therapy in the metastatic setting for at least 6 months (Yes or No). 3 Second interim OS analysis (conducted when 390 OS events were observed) BICR = Blinded Independent Central Review; CI = Confidence Interval
For the ITT population, the number of responders was 57 (21%) in the Trodelvy arm and 38 (14%) in the TPC arm (Odds ratio [95% CI]: 1.625 [1.034, 2.555], p=0.0348). The median duration of response (DOR) was 8.1 months in the Trodelvy arm and 5.6 months in the TPC arm.
The PFS rate was 21.3% (95% CI: 15.2, 28.1) and 7.1% (95% CI: 2.8, 13.9) at 12 months in the Trodelvy and TPC arms, respectively. This was an exploratory analysis as formal statistical testing was not conducted.
Figure 3: Kaplan-Meier Plot of PFS by BICR in TROPiCS-02
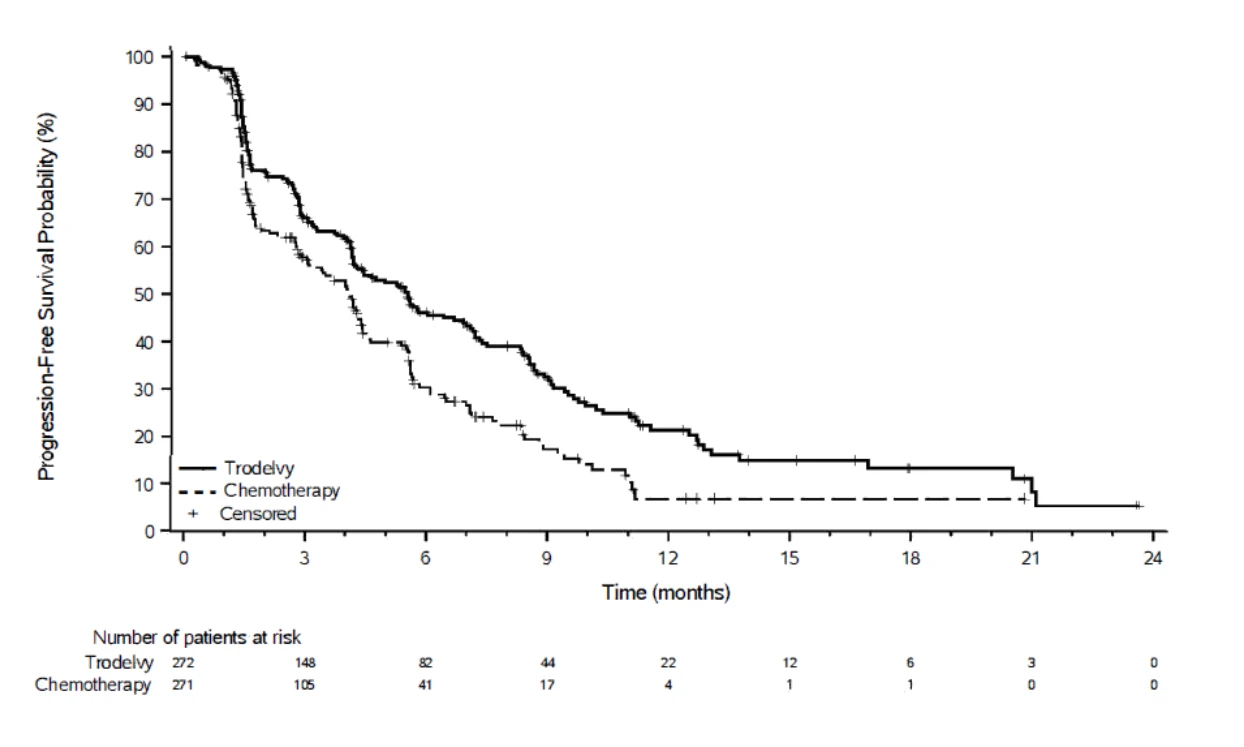
Figure 4: Kaplan-Meier Plot of OS in TROPiCS-02
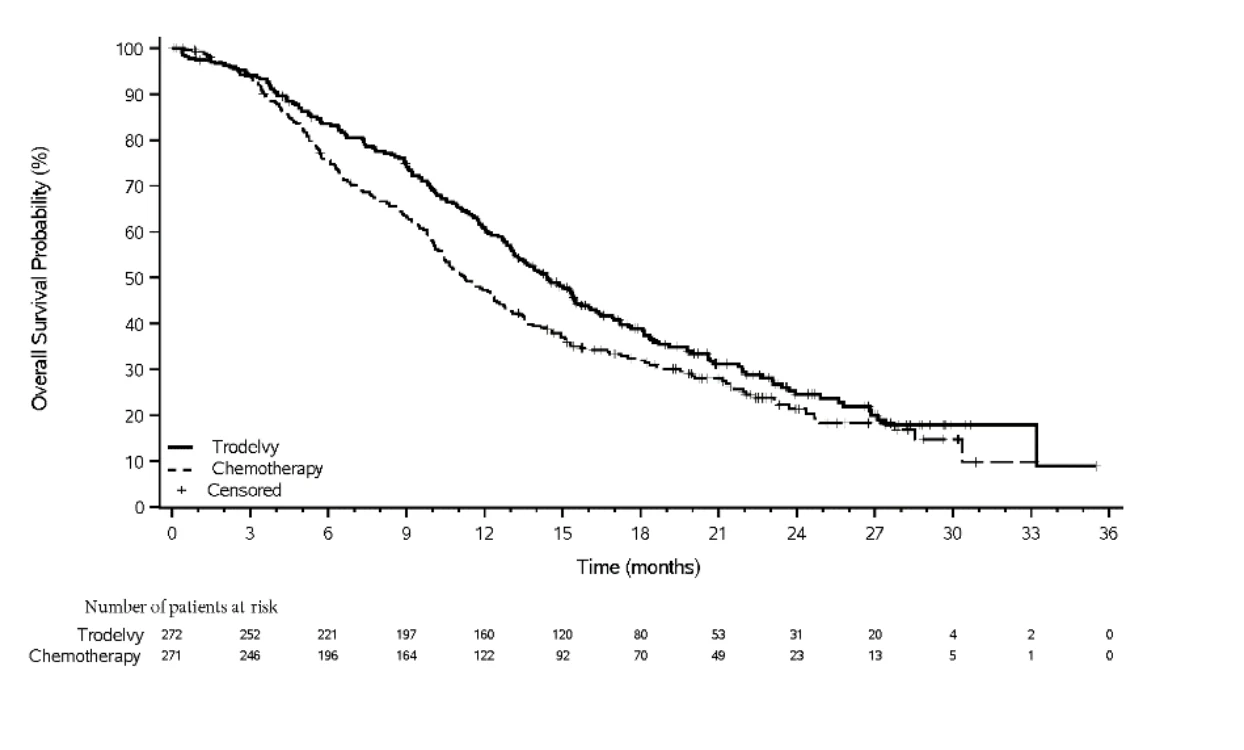
15 Microbiology
No microbiological information is required for this drug product.
16 Non-Clinical Toxicology
General Toxicology
Cynomolgus Monkeys
In Cynomolgus monkeys, sacituzumab govitecan administered up to 50 mg/kg/dose for four treatment cycles (days 1 and 8 of a 21-day cycle) was considered a NOAEL, and 120 mg/kg/dose administered 3 days apart was associated with lethality. Lethality was considered due to bone marrow suppression and gastrointestinal disturbances. Across studies, target organs also included the female reproductive tract, skin, kidney, and/or lymphoid organs.
Carcinogenicity and Mutagenicity
No long-term animal studies have been performed to evaluate carcinogenic or mutagenic potential of Trodelvy.
SN-38 was clastogenic in an in vitro mammalian cell micronucleus test in Chinese hamster ovary cells and was not mutagenic in an in vitro bacterial reverse mutation (Ames) assay.
Genotoxicity: The genotoxic potential of sacituzumab govitecan has not been fully evaluated. Sacituzumab govitecan contains the genotoxic topoisomerase I inhibitor component, SN-38, and is toxic to rapidly dividing cells, suggesting the potential for embryotoxicity and teratogenicity.
Reproductive and Developmental Toxicology
Impairment of Fertility
Dedicated fertility studies have not been conducted with sacituzumab govitecan. In a repeat-dose toxicity study in cynomolgus monkeys, intravenous administration of sacituzumab govitecan on Day 1 and Day 4 resulted in endometrial atrophy, uterine hemorrhage, increased follicular atresia of the ovary, and atrophy of vaginal epithelial cells at doses ≥60 mg/kg (≥6 times the human recommended dose of 10 mg/kg based on body weight).
Developmental Toxicity
There were no animal reproductive or developmental toxicity studies conducted with sacituzumab govitecan.
Juvenile Animal Studies
No juvenile toxicity studies have been conducted.