


Product Monograph - Polivy
Recent Major Label Changes
| 7 Warnings and Precautions, General | 2026-XX |
|---|
Table of Contents
Certain sections or subsections that are not applicable at the time of the preparation of the most recent authorized product monograph are not listed.
Recent Major Label Changes ..................................................................................................... 2
Table of Contents ........................................................................................................................ 2
Part 1: Health Professional Information ................................................................................... 4
1 Indications ....................................................................................................................... 4
Pediatrics ............................................................................................................... 4
Geriatrics ............................................................................................................... 4
- 2. Contraindications ............................................................................................................ 4
- 3. Serious Warnings and Precautions Box ....................................................................... 4
- 4. Dosage and Administration ........................................................................................... 5
Dosing Considerations .......................................................................................... 5
Recommended Dose and Dosage Adjustment ..................................................... 5
Reconstitution ...................................................................................................... 10
Administration ...................................................................................................... 11
Missed Dose ........................................................................................................ 11
- 5. Overdose ........................................................................................................................ 12
- 6. Dosage Forms, Strengths, Composition, and Packaging ......................................... 12
- 7.
Warnings and Precautions ........................................................................................... 12
General ........................................................................................................................... 12
Driving and Operating Machinery .................................................................................... 13
Endocrine and Metabolism .............................................................................................. 13
Hematologic .................................................................................................................... 13
Hepatic/Biliary/Pancreatic ............................................................................................... 13
Immune ........................................................................................................................... 14
Neurologic ....................................................................................................................... 14
Reproductive Health ........................................................................................................ 14
Special Populations ............................................................................................. 15
7.1.1 Pregnancy ....................................................................................................... 15
7.1.2 Breastfeeding .................................................................................................. 15
7.1.3 Pediatrics ......................................................................................................... 15
7.1.4 Geriatrics ......................................................................................................... 15
- 8. Adverse Reactions ........................................................................................................ 15
Adverse Reaction Overview ................................................................................ 15
Clinical Trial Adverse Reactions .......................................................................... 16
Less Common Clinical Trial Adverse Reactions .................................................. 24
Abnormal Laboratory Findings: Hematologic, Clinical Chemistry, and Other Quantitative Data ............................................................................................................ 24
Post-Market Adverse Reactions .......................................................................... 25
- 9. Drug Interactions .......................................................................................................... 25
Drug-Interactions Overview ................................................................................. 25
Drug-Drug Interactions ........................................................................................ 25
Drug-Food Interactions ........................................................................................ 26
Drug-Herb Interactions ........................................................................................ 26
Drug-Laboratory Test Interactions ....................................................................... 26
- 10. Clinical Pharmacology .................................................................................................. 26
 Mechanism of Action ........................................................................................... 26
 Pharmacodynamics ............................................................................................. 26
 Pharmacokinetics ................................................................................................ 27
 Immunogenicity ................................................................................................... 28
- 11. Storage, Stability, and Disposal .................................................................................. 28
- 12. Special Handling Instructions ...................................................................................... 29
Part 2: Scientific Information ................................................................................................... 30
- 13. Pharmaceutical Information ......................................................................................... 30
- 14. Clinical Trials ................................................................................................................. 30
 Clinical Trials by Indication .................................................................................. 30
- 15. Microbiology .................................................................................................................. 37
- 16. Non-Clinical Toxicology ............................................................................................... 37
Patient Medication Information ............................................................................................... 39
Part 1: Health Professional Information
1 Indications
POLIVY® (polatuzumab vedotin for injection) in combination with rituximab, cyclophosphamide, doxorubicin, and prednisone (R-CHP) is indicated for the treatment of adult patients with previously untreated large B-cell lymphoma (LBCL), including diffuse large B-cell lymphoma (DLBCL) not otherwise specified (NOS), high grade B-cell lymphoma, Epstein-Barr virus-positive (EBV+) DLBCL NOS, and T-cell/histiocyte rich LBCL.
POLIVY in combination with bendamustine and rituximab is indicated for the treatment of adult patients with relapsed or refractory diffuse large B-cell lymphoma (R/R DLBCL), not otherwise specified, who are not eligible for autologous stem cell transplant and have received at least one prior therapy.
Pediatrics
Pediatrics (< 18 years of age): Based on the data submitted and reviewed by Health Canada, the safety and efficacy of POLIVY in pediatric patients has not been established; therefore, Health Canada has not authorized an indication for pediatric use.
Geriatrics
Geriatrics (≥ 65 years of age): Evidence from clinical studies and experience suggests that POLIVY in combination with R-CHP in the geriatric population is associated with differences in safety compared to younger patients (see 7 Warnings and Precautions, 7.1.4 Geriatrics).
2. Contraindications
POLIVY is contraindicated in patients who are hypersensitive to this drug or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see 6 Dosage Forms, Strengths, Composition, and Packaging.
3. Serious Warnings and Precautions Box
Clinically significant and/or life-threatening adverse events include:
POLIVY should only be administered by a qualified healthcare professional experienced in the use of antineoplastic therapy. |
|---|
4. Dosage and Administration
Dosing Considerations
For information on rituximab, bendamustine, cyclophosphamide, doxorubicin, or prednisone, refer to their respective full Product Monographs. Refer to Table 3 for dose modification recommendations for neutropenia and thrombocytopenia.
If not already pre-medicated, administer premedication with an antihistamine and anti-pyretic to patients prior to administration of POLIVY .
Recommended Dose and Dosage Adjustment
Previously untreated LBCL and relapsed/refractory DLBCL patients:
The initial dose of POLIVY should be administered as a 90-minute intravenous infusion. Patients should be monitored for infusion-related reactions (IRRs) during the infusion and for at least 90 minutes following completion of the initial dose. If the prior infusion was well tolerated, the subsequent dose of POLIVY may be administered as a 30-minute infusion and patients should be monitored during the infusion and for at least 30 minutes after completion of the infusion.
Previously untreated LBCL patients:
The recommended dose of POLIVY is 1.8 mg/kg given as an intravenous infusion every 21 days for 6 cycles in combination with rituximab, cyclophosphamide, doxorubicin, and prednisone (R-CHP). POLIVY, rituximab, cyclophosphamide, and doxorubicin can be administered in any order on Day 1 after the administration of prednisone. Prednisone is administered on Days 1–5 of each cycle. Cycles 7 and 8 consist of rituximab as monotherapy.
Relapsed/refractory DLBCL patients:
The recommended dose of POLIVY is 1.8 mg/kg given as an intravenous infusion every 21 days in combination with bendamustine and rituximab for 6 cycles. POLIVY, bendamustine, and rituximab can be administered in any order on Day 1 of each cycle. The recommended dose of bendamustine is 90 mg/m2/day on Day 1 and 2 when administered with POLIVY and rituximab. The recommended dose of rituximab is 375 mg/m2 on Day 1 of each cycle.
Dose Modifications
The infusion rate of POLIVY should be slowed or interrupted if the patient develops an infusion-related reaction. POLIVY should be discontinued immediately and permanently if the patient experiences a life-threatening reaction. For dose modifications for infusion-related reactions see Table 1.
For peripheral neuropathy and myelosuppression, there are different possible dose modifications for POLIVY in patients with previously untreated LBCL and with R/R DLBCL (see Table 2 and Table 3, respectively).
Table 1 POLIVY Dose Modifications for Infusion-related reactions (IRRs)
| Indication | Severity on Day 1 of any cycle | Dose modification |
|---|---|---|
| Previously untreated LBCL and R/R DLBCL | Grade 1–3 IRRs | Interrupt POLIVY infusion and give supportive treatment. For the first instance of Grade 3 wheezing, bronchospasm, or generalized urticaria, permanently discontinue POLIVY. For recurrent Grade 2 wheezing or urticaria, or for recurrence of any Grade 3 symptoms, permanently discontinue POLIVY. Otherwise, upon complete resolution of symptoms, infusion may be resumed at 50% of the rate achieved prior to interruption. In the absence of infusion related symptoms, the rate of infusion may be escalated in increments of 50 mg/hour every 30 minutes. For the next cycle, infuse POLIVY over 90 minutes. If no infusion related reaction occurs, subsequent infusions may be administered over 30 minutes. Administer premedication for all cycles. |
Grade 4 IRRs | Stop POLIVY infusion immediately. Give supportive treatment. Permanently discontinue POLIVY. |
Peripheral Neuropathy
For dose modifications to manage peripheral neuropathy see Table 2.
Table 2 POLIVY Dose Modifications for Peripheral Neuropathy
| Indication | Severity on Day 1 of any cycle | Dose modification |
|---|---|---|
| Previously untreated LBCL | Grade 2a | Sensory neuropathy:
Motor neuropathy:
|
| Indication | Severity on Day 1 of any cycle | Dose modification |
|---|---|---|
If concurrent sensory and motor neuropathy occur, follow the most severe restriction recommendation above. | ||
| Grade 3a | Sensory neuropathy:
Motor neuropathy:
If concurrent sensory and motor neuropathy occur, follow the most severe restriction recommendation above. | |
| Grade 4a | Discontinue POLIVY | |
| R/R DLBCL | Grade 2-3 | Hold POLIVY dosing until improvement to ≤ Grade 1. If recovered to Grade ≤1 on or before Day 14, restart POLIVY at a permanently reduced dose of 1.4 mg/kg. If a prior dose reduction to 1.4 mg/kg has occurred, discontinue POLIVY. If not recovered to Grade ≤1 on or before Day 14, discontinue POLIVY. |
| Grade 4 | Discontinue POLIVY. |
aR-CHP may continue to be administered.
Myelosuppression
For dose modifications to manage myelosuppression see Table 3
Table 3 POLIVY, Chemotherapy, and Rituximab Dose Modifications for Myelosuppression
| Indication | Severity on Day 1 of any cycle | Dose modification |
|---|---|---|
| Previously untreated LBCL | Grade 3–4 Neutropenia | Hold all treatment until absolute neutrophil count (ANC) recovers to >1000/μL. If ANC recovers to >1000/μL on or before Day 7 of the treatment cycle, resume all treatment without any additional dose reductions. If ANC recovers to 1000/μL after Day 7:
|
| Grade 3–4 Thrombocytopenia | Hold all treatment until platelets recover to >75,000/μL. If platelets recover to >75,000/μL on or before Day 7, resume all treatment without any additional dose reductions. If platelets recover to >75,000/μL after Day 7:
| |
| R/R DLBCL | Grade 3-4 Neutropeniaa | Hold all treatment until ANC recovers to >1000/μL. If ANC recovers to >1000/μL on or before Day 7, resume all treatment without any additional dose reductions. Prophylactic use of granulocyte colony stimulating factor (G-CSF) should be considered for subsequent cycles, if not previously administered. If ANC recovers to >1000/μL after Day 7:
|
| |
|---|---|
| Grade 3-4 Thrombocytopeniaa | Hold all treatment until platelets recover to >75,000/μL. If platelets recover to >75,000/μL on or before Day 7, resume all treatment without any additional dose reductions. If platelets recover to >75,000/μL after Day 7:
|
ANC: absolute neutrophil count
aIf primary cause is due to lymphoma, the dose of bendamustine may not need to be reduced.
Dose Modifications for Special Populations
Pediatric use
The safety and efficacy of POLIVY in patients (<18 years) have not been established.
Geriatric use
No dose adjustment of POLIVY is required in patients ≥ 65 years of age (see 10 Clinical Pharmacology, 10.3 Pharmacokinetics, Special populations and conditions, Geriatrics).
Renal Impairment
No dose adjustment of POLIVY is required in patients with creatinine clearance (CrCL) ≥30mL/min. POLIVY has not been studied in patients with severe renal impairment (CrCL 15 to 29 mL/min, n=3). No data are available in patients with end-stage renal disease with or without dialysis. A recommended dose has not been determined for patients with CrCL <30mL/min. (see 10 Clinical Pharmacology, 10.3 Pharmacokinetics, Special populations and conditions, Renal Impairment).
Hepatic Impairment
The administration of POLIVY in patients with moderate or severe hepatic impairment (total bilirubin >1.5 × ULN) should be avoided. Patients with moderate or severe hepatic impairment are likely to have increased exposure to monomethyl auristatin E (MMAE), potentially increasing their risk of adverse reactions. POLIVY has not been studied in patients with moderate or severe hepatic impairment (see 10 Clinical Pharmacology, 10.3 Pharmacokinetics, Special populations and conditions, Hepatic Impairment).
No dose adjustment of POLIVY is required for patients with mild hepatic impairment (total bilirubin greater than ULN to less than or equal to 1.5 × ULN or aspartate transaminase [AST] greater than ULN).
Reconstitution
POLIVY must be reconstituted using sterile water for injection and diluted into an IV infusion bag containing 0.9% sodium chloride, 0.45% sodium chloride, or 5% dextrose by a healthcare professional prior to administration.
Use aseptic technique for reconstitution and dilution of POLIVY. Appropriate procedures for the preparation of antineoplastic products should be used.
- 1. Using a sterile syringe, slowly inject 1.8 mL of sterile water for injection into the 30 mg POLIVY vial or 7.2 mL of sterile water for injection into the 140 mg POLIVY vial to yield a single-dose solution containing 20 mg/mL polatuzumab vedotin. Direct the stream toward the wall of the vial and not directly on the lyophilized cake.
- 2. Swirl the vial gently until completely dissolved. Do not shake.
- 3. Inspect the reconstituted solution for discolouration and particulate matter. The reconstituted solution should appear colourless to slightly brown, clear to slightly opalescent, and free of visible particulates. Do not use if the reconstituted solution is discoloured, cloudy, or contains visible particulates.
From a microbiological point of view, the reconstituted solution should be used immediately. If not used immediately, in-use storage times and conditions prior to use are the responsibility of the user and would normally not be longer than 24 hours at 2°C to 8°C, unless reconstitution has taken place in controlled and validated aseptic conditions.
Chemical and physical in-use stability of the reconstituted solution has been demonstrated for up to 72 hours at 2°C to 8°C and up to 24 hours at room temperature (9°C to 25°C).
Dilution
- 1. Polatuzumab vedotin must be diluted to a final concentration of 0.72 – 2.7 mg/mL in an IV infusion bag with a minimum volume of 50mL containing 0.9% sodium chloride, 0.45% sodium chloride, or 5% dextrose.
- 2. Determine the volume of 20 mg/mL reconstituted solution needed based on the required dose:
| Volume = | POLIVY dose (1.8 or 1.4 mg/kg) X patient’s weight (kg) |
|---|---|
| Reconstituted vial concentration (20 mg/mL) |
- 3. Withdraw the required volume of reconstituted solution from the POLIVY vial using a sterile syringe and dilute into the IV infusion bag. Discard any unused portion left in the vial.
- 4. Gently mix the IV bag by slowly inverting the bag. Do not shake.
- 5. Inspect the IV bag for particulates and discard if present.
From a microbiological point of view, the prepared solution for infusion should be used immediately. If not used immediately, in-use storage times and conditions prior to use are the responsibility of the user and would normally not be longer than 24 hours at 2°C to 8°C, unless dilution has taken place in controlled and validated aseptic conditions. Acceptable chemical and physical stability of the prepared solution for infusion has been demonstrated for the durations listed in Table 4. Discard if storage time exceeds these limits. Do not freeze or expose to direct sunlight.
Table 4 Durations for which Acceptable Chemical and Physical Stability of the Prepared Solution for Infusion have been Demonstrated
| Diluent used to prepare solution for infusion | Solution for infusion storage conditions1 |
|---|---|
| 0.9% Sodium Chloride | Up to 72 hours at 2°C to 8°C or up to 4 hours at room temperature (9°C to 25°C) |
| 0.45% Sodium Chloride | Up to 72 hours at 2°C to 8°C or up to 8 hours at room temperature (9°C to 25°C) |
| 5% Dextrose | Up to 72 hours at 2°C to 8°C or up to 8 hours at room temperature (9°C to 25°C) |
| 1To ensure product stability, do not exceed specified storage durations. | |
Avoid transportation of the prepared solution for infusion as agitation stress can result in aggregation. If the prepared solution for infusion will be transported, remove air from the infusion bag and limit transportation to 30 minutes at 9°C to 25°C or 24 hours at 2°C to 8°C. If air is removed, an infusion set with a vented spike is required to ensure accurate dosing during the infusion.
Incompatibilities
- Do not mix POLIVY with, or administer through the same infusion line, as other medicinal products.
- No incompatibilities have been observed between POLIVY and IV infusion bags with product contacting materials of polyvinyl chloride (PVC), or polyolefins (PO) such as polyethylene (PE) and polypropylene (PP). In addition, no incompatibilities have been observed with infusion sets or infusion aids with product contacting materials of PVC, PE, polyurethane (PU), polybutadiene (PBD), acrylonitrile butadiene styrene (ABS), polycarbonate (PC), polyetherurethane (PEU), or fluorinated ethylene propylene (FEP), or polytetrafluorethylene (PTFE), or with filter membranes composed of polyether sulfone (PES) or polysulfone (PSU).
Administration
POLIVY is administered as an intravenous infusion only.
POLIVY should be reconstituted immediately before dilution.
The reconstituted product contains no preservative and is intended for single use only. Discard any unused portion.
A dedicated infusion line equipped with a sterile, non-pyrogenic, low-protein binding in-line or add-on filter (0.2 or 0.22 μm pore size) and catheter must be used to administer diluted POLIVY.
Missed Dose
If a planned dose of POLIVY is missed, it should be administered as soon as possible and the schedule of administration should be adjusted to maintain a 21-day interval between doses.
5. Overdose
There is no experience with overdose in human clinical trials. Patients who experience overdose should have immediate interruption of their infusion and be closely monitored.
- 6. Dosage Forms, Strengths, Composition, and Packaging
To help ensure the traceability of biologic products, health professionals should record both the brand name and the non-proprietary (active ingredient) name as well as other product-specific identifiers such as the Drug Identification Number (DIN) and the batch/lot number of the product supplied.
Table 5 Dosage Forms, Strengths, and Composition
POLIVY is a sterile, preservative-free, white to grayish-white, lyophilized cake supplied in single-use 6 mL vial containing 30 mg and 20 mL vial containing 140 mg of polatuzumab vedotin. Upon reconstitution POLIVY concentrate contains 20 mg/mL of polatuzumab vedotin for intravenous infusion only.
7. Warnings and Precautions
Please see 3 Serious Warnings and Precautions Box.
General
Infusion-Related Reactions (IRRs)
IRRs, including severe cases have been observed with POLIVY. IRRs can occur as late as 24 hours after receiving POLIVY. Patients should be administered premedication with an antihistamine and anti-pyretic to patients prior to administration of POLIVY. Patients should be monitored closely during administration for IRRs. Symptoms include fever, chills, flushing, dyspnea, hypotension, or urticaria. If an infusion-related reaction occurs, the infusion should be interrupted and appropriate management followed (see 4 Dosage and Administration, 4.2 Recommended Dose and Dosage Adjustment and 8 Adverse Reactions, 8.2 Clinical Trial Adverse Reactions, Description of Selected Adverse Drug Reactions from Clinical Trials, Infusion-Related Reactions).
Infusion Site Extravasation Injury
| For the most recent information in the management of a suspected drug overdose, contact your regional poison control centre or Health Canada’s toll-free number, 1-844 POISON-X (1-844-764-7669). |
|---|
| Route of Administration | Dosage Form/ Strength/Composition | Non-Medicinal Ingredients |
| Intravenous infusion | Powder for concentrate for solution for infusion / 20 mg per mL | polysorbate 20, sodium hydroxide, succinic acid, sucrose |
Cases of tissue damage following infusion site extravasation, including severe events, have occurred in patients treated with POLIVY. To minimize risk, ensure adequate venous access prior to initiating the infusion and closely monitor the infusion site throughout administration for any signs of extravasation. If extravasation is suspected, stop the infusion and monitor for adverse reactions (see 8.3 Less Common Clinical Trial Adverse Reactions).
For mild symptoms, the remaining dose may be administered in an alternate limb after establishing secure venous access. For moderate to severe symptoms, the infusion can be restarted in an alternate limb based on the clinical judgment of the treating physician.
Driving and Operating Machinery
Infusion-related reactions, peripheral neuropathy, fatigue, and dizziness may occur during treatment with POLIVY. Patients should avoid driving or operating a vehicle or potentially dangerous machinery if they experience these effects (see 8 Adverse Reactions).
Endocrine and Metabolism
Tumour Lysis Syndrome (TLS)
Tumour lysis syndrome has been reported in patients treated with POLIVY. Patients with high tumour burden and rapidly proliferative tumour may be at increased risk of tumour lysis syndrome. Appropriate measures in accordance with local guidelines should be taken prior to treatment with POLIVY. Patients should be monitored closely for tumour lysis syndrome during treatment with POLIVY.
Hematologic
Myelosuppression
Serious and severe neutropenia and febrile neutropenia have been reported in patients treated with POLIVY as early as the first cycle of treatment. Prophylactic G-CSF (granulocyte colony stimulating factor) administration should be considered. Grade 3 or 4 thrombocytopenia or anemia can also occur with POLIVY. Complete blood counts should be monitored prior to each dose of POLIVY. More frequent lab monitoring and/or POLIVY delays or discontinuation should be considered in patients with Grade 3 or Grade 4 neutropenia and thrombocytopenia (see 4 Dosage and Administration, 4.2 Recommended Dose and Dosage Adjustment and 8 Adverse Reactions, 8.2 Clinical Trial Adverse Reactions, Description of Selected Adverse Drug Reactions from Clinical Trials, Myelosuppression).
Hepatic/Biliary/Pancreatic
Hepatic Toxicity
Serious cases of hepatic toxicity that were consistent with hepatocellular injury, including elevations of transaminases (AST/ALT) and/or bilirubin, have occurred in patients treated with POLIVY (see section 8 Adverse Reactions). Pre-existing liver disease, elevated baseline liver enzymes, and concomitant medications may increase the risk of hepatotoxicity. Liver enzymes and bilirubin level should be monitored.
The administration of POLIVY in patients with moderate or severe hepatic impairment (total bilirubin greater than 1.5 x ULN) should be avoided (see 4.2 Recommended Dose and Dosage Adjustment and 10.3 Pharmacokinetics).
Immune
Infections
Fatal, life threatening, or serious infections, including opportunistic infections, such as pneumonia (including pneumocystis jirovecii and other fungal pneumonia), bacteremia, sepsis, herpes zoster infection, and cytomegalovirus infection have been reported in patients treated with POLIVY (see 8 Adverse Reactions). Patients should be closely monitored during treatment for signs of bacterial, fungal, or viral infections. Anti-infective prophylaxis and/or treatment should be considered. POLIVY and any concomitant chemotherapy should be discontinued in patients who develop serious infections.
Neurologic
Peripheral Neuropathy
Peripheral neuropathy has been reported in patients treated with POLIVY as early as the first cycle of treatment, and the risk increases with sequential doses (see 8 Adverse Reactions). Clinical studies of POLIVY excluded patients with Grade 2 or higher peripheral neuropathy and the benefits and risks of using POLIVY have not been established in these patients. Patients with pre-existing peripheral neuropathy may experience worsening of this condition.
Peripheral neuropathy reported with POLIVY treatment is predominantly sensory peripheral neuropathy; however, motor and sensorimotor peripheral neuropathy have also been reported. Patients should be monitored for symptoms of peripheral neuropathy such as hypoesthesia, hyperesthesia, paresthesia, dysesthesia, neuropathic pain, burning sensation, weakness, or gait disturbance. Patients experiencing new or worsening peripheral neuropathy may require a delay, dose reduction, or discontinuation of POLIVY (see 4 Dosage and Administration, 4.2 Recommended Dose and Dosage Adjustment).
Progressive Multifocal Leukoencephalopathy (PML)
PML has been reported with POLIVY treatment (see section 8 Adverse Reactions). Patients should be monitored closely for new or worsening neurological, cognitive, or behavioral changes suggestive of PML. POLIVY and any concomitant chemotherapy should be held if PML is suspected and permanently discontinued if the diagnosis is confirmed.
Reproductive Health
Pregnancy testing
The pregnancy status of female patients of reproductive potential should be verified prior to initiating POLIVY (see section 7 Warnings and Precautions, 7.1 Special Populations, 7.1.1 Pregnancy).
Contraception
Female patients of reproductive potential should be advised of the potential harm to the fetus. Female patients of reproductive potential should be advised to use effective contraception during treatment with POLIVY and for at least 9 months after the last dose (see sections 7 Warnings and Precautions, 7.1 Special Populations, 7.1.1 Pregnancy and 16 Non-Clinical Toxicology).
Based on genotoxicity findings, male patients with female partners of reproductive potential should be advised to use effective contraception during treatment with POLIVY and for at least 6 months after the last dose (see section 16 Non-Clinical Toxicology).
- Fertility
Based on findings from animal studies, POLIVY may impair male reproductive function and fertility (see 16 Non-Clinical Toxicology).
Special Populations
7.1.1 Pregnancy
There are no human data on the use of POLIVY during pregnancy. In animal studies, administration of MMAE to pregnant rats during organogenesis caused embryo-fetal death and fetal malformations at exposures below those occurring clinically at the recommended dose (see 16 Non-Clinical Toxicology). Based on the findings in animal studies and its mechanism of action, POLIVY can cause fetal harm when administered to a pregnant woman.
POLIVY should not be used in women who are pregnant. If POLIVY is used in pregnancy, or if the patient becomes pregnant while taking POLIVY, the patient should be apprised of potential hazard to the fetus.
7.1.2 Breastfeeding
It is not known whether polatuzumab vedotin is excreted in human breast milk. No studies have been conducted to assess the impact of POLIVY on milk production or its presence in breast milk. Since many drugs are excreted in human milk and because of the potential for serious adverse reactions in breastfeeding infants due to POLIVY, nursing women should be advised not to breastfeed during treatment with POLIVY and for at least 3 months after the last dose.
7.1.3 Pediatrics
Pediatrics (< 18 years of age): Based on the data submitted and reviewed by Health Canada, the safety and efficacy of POLIVY in pediatric patients has not been established; therefore, Health Canada has not authorized an indication for pediatric use.
7.1.4 Geriatrics
Geriatrics (≥ 65 years of age): Among 435 previously untreated LBCL patients treated with POLIVY in combination with R-CHP in Study GO39942, 227 (52.2%) were ≥ 65 years of age. Patients aged ≥ 65 years had an incidence of serious adverse events of 39.2% and patients aged < 65 years had an incidence of 28.4%. Incidences of adverse events leading to POLIVY discontinuations were 6.6% for patients ≥ 65 years vs. 1.9% for patients < 65 years, adverse events leading to POLIVY dose reduction were 4.8% for patients ≥ 65 years vs. 6.3% for patients < 65 years, and adverse events leading to POLIVY dose interruptions were 15.4% for patients ≥ 65 years vs. 12.5% for patients < 65 years.
8. Adverse Reactions
Adverse Reaction Overview
Previously untreated large B-cell lymphoma:
In the GO39942 study, the most frequently reported (≥30%) ADRs (all grades) in patients treated with POLIVY in combination with R-CHP for previously untreated LBCL were neuropathy peripheral, nausea, neutropenia, and diarrhea.
Serious adverse reactions were reported in 24.1% of POLIVY plus R-CHP treated patients which included the following that occurred in ≥5% of patients: febrile neutropenia (10.6%) and pneumonia (5.3%).
The ADR leading to treatment regimen discontinuation in ≥1% of patients treated with POLIVY in combination with R-CHP for previously untreated LBCL was pneumonia (1.1%).
Five patients (1.1%) experienced fatal ADRs, which included pneumonia (0.9%) and sepsis (0.2%).
Relapsed/refractory diffuse large B-cell lymphoma:
In the GO29365 study, the most frequently-reported (≥20%) adverse drug reactions (ADRs) in patients with DLBCL treated with POLIVY in combination with bendamustine (B) and rituximab (R) were anemia, thrombocytopenia, neutropenia, decreased appetite, neuropathy peripheral, fatigue, diarrhea, nausea, and pyrexia.
Serious adverse events were reported in 64.4% of POLIVY plus BR treated patients which included febrile neutropenia (11.1%), pyrexia (8.9%), pneumonia (8.9%), anemia (4.4%), duodenal ulcer hemorrhage (4.4%), sepsis (4.4%), and thrombocytopenia (4.4%).
Four patients (8.9%) experienced fatal ADRs which included pneumonia (6.7%) and meniningoencephalitis herpetic (2.2%).
ADRs leading to treatment regimen discontinuation in >5% of patients were thrombocytopenia (8.9%) and neutropenia (6.7%).
Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. Therefore, the frequencies of adverse reactions observed in the clinical trials may not reflect frequencies observed in clinical practice and should not be compared to frequencies reported in clinical trials of another drug.
Previously untreated large B-cell lymphoma
The adverse drug reactions (ADRs) described Table 6 were identified during treatment and follow-up of previously untreated adult LBCL patients from the pivotal Phase III clinical trial GO39942 (POLARIX), who received POLIVY plus R-CHP (n=435) or R-CHOP (n=438).
Table 6 Adverse Drug Reactions Reported in ≥ 1% of Patients with Previously Untreated LBCL Treated with POLIVY in Combination with R-CHP in Study GO39942
| Adverse drug reactions | POLIVY + R-CHP n=435 | R-CHOP n=438 | ||
|---|---|---|---|---|
| SOC | All grades (%) | Grade 3 or Higher (%) | All grades (%) | Grade 3 or Higher (%) |
| Blood and Lymphatic System Disorders | ||||
| Neutropeniaa | 38.4 | 34.5 | 39 | 36.5 |
| Anemiab | 28.7 | 12 | 26.9 | 8.7 |
| Febrile Neutropeniac | 14.9 | 14.5 | 8.7 | 8.7 |
| Leukopeniad | 14 | 9.7 | 13 | 9.8 |
| Thrombocytopeniae | 13.3 | 5.3 | 13.2 | 5 |
| Lymphopeniaf | 6.9 | 4.6 | 8.7 | 5.7 |
| Gastrointestinal Disorders | ||||
| Nausea | 41.6 | 1.1 | 37 | 0.5 |
| Diarrhea | 30.8 | 3.9 | 20.1 | 1.8 |
| Constipation | 28.7 | 1.1 | 29 | 0.2 |
| Abdominal Paing | 15.6 | 1.1 | 13.9 | 1.6 |
| Vomiting | 15.2 | 1.1 | 14.4 | 0.7 |
| General Disorders and Administration Site Conditions | ||||
| Fatigueh | 25.7 | 0.9 | 26.5 | 2.5 |
| Mucositisi | 21.8 | 1.4 | 19.4 | 0.5 |
| Pyrexia | 15.6 | 1.4 | 12.6 | 0 |
| Astheniaj | 12.2 | 1.6 | 12.1 | 0.5 |
| Peripheral Edema | 11 | 0.2 | 9.1 | 0.2 |
| Chills | 4.6 | 0.2 | 5.3 | 0.5 |
| Infections and Infestations | ||||
| Upper respiratory tract infection | 16.8 | 0.5 | 16 | 0.5 |
| Pneumonia | 8.7 | 5.1 | 7.3 | 5.5 |
| Urinary tract infection | 8.3 | 1.8 | 7.1 | 1.1 |
| Herpes virus infection | 3.4 | 0.2 | 3.2 | 0.5 |
| Sepsis | 2.1 | 2.1 | 3.4 | 3.4 |
| Injury, Poisoning, and Procedural | ||||
| Infusion related reactionk | 13.3 | 1.1 | 16 | 1.6 |
| Investigations | ||||
| Weight decreased | 12.6 | 0.9 | 12.1 | 0.2 |
| Adverse drug reactions | POLIVY + R-CHP n=435 | R-CHOP n=438 | ||
|---|---|---|---|---|
| SOC | All grades (%) | Grade 3 or Higher (%) | All grades (%) | Grade 3 or Higher (%) |
| Transaminases increasedl | 6.7 | 0.7 | 5.7 | 0.2 |
| Hypophosphataemia | 4.8 | 1.8 | 2.7 | 1.4 |
| Metabolism and Nutrition Disorders | ||||
| Decreased appetite | 16.6 | 1.1 | 14.2 | 0.7 |
| Hypokalemia | 8.3 | 1.8 | 8.9 | 1.8 |
| Hypoalbuminemia | 2.3 | 0.5 | 2.5 | 0 |
| Hypocalcemia | 1.6 | 0.2 | 2.3 | 0.5 |
| Musculoskeletal Disorders | ||||
| Myalgiam | 8.7 | 0.2 | 7.3 | 0.2 |
| Arthralgian | 6.2 | 0 | 8.4 | 0 |
| Nervous System Disorders | ||||
| Neuropathy Peripheral | 52.9 | 1.6 | 53.9 | 1.1 |
| Dizzinesso | 8.7 | 0.2 | 7.8 | 0.2 |
| Respiratory, Thoracic and Mediastinal Disorders | ||||
| Cough | 15.4 | 0 | 14.4 | 0 |
| Dyspnoea | 12.9 | 0.9 | 10 | 0.9 |
| Pneumonitis | 1.1 | 0.2 | 0.7 | 0 |
| Skin and Subcutaneous Tissue Disorders | ||||
| Alopecia | 24.4 | 0 | 24 | 0.2 |
| Rash | 13.3 | 0.9 | 11.2 | 0 |
| Pruritus | 8.3 | 0 | 6.4 | 0.2 |
| Skin infections | 6.9 | 1.1 | 3 | 0.7 |
| Dry skin | 6 | 0 | 2.7 | 0 |
a Neutropenia includes neutropenia and neutrophil count decreased.
b Anemia includes anemia, hemolytic anemia, hemoglobin decreased, hematocrit decreased, red blood cell decreased, erythropenia and aplasia.
c Febrile neutropenia includes febrile neutropenia, febrile bone marrow aplasia, neutropenic sepsis and neutropenic infection
d Leukopenia includes leukopenia and while blood count decreased
e Thrombocytopenia includes thrombocytopenia and platelet count decreased
f Lymphopenia includes lymphopenia, lymphocyte count decreased and lymphocyte percentage decreased.
g Abdominal pain includes abdominal pain, abdominal discomfort, gastrointestinal pain and epigastric discomfort h Fatigue includes fatigue
i Mucositis includes stomatitis, mucosal inflammation, mouth ulceration, tongue ulceration, aphthous ulcer, oropharyngeal pain, oral pain, odynophagia, oral mucosal erythema, tongue blistering, oral discomfort and oropharyngeal discomfort.
j Asthenia includes asthenia
k Infusion related reaction ADR is reflective of the combination regimen POLIVY plus R-CHP due to same day administration.
l Transaminases increased includes transaminases increased, hepatotoxicity, hepatic enzyme abnormal, hepatic enzyme increased, alanine aminotransferase increased, aspartate aminotransferase increased, hypertransaminasaemia, hepatotoxicity, hepatitis acute, hepatitis, acute hepatic failure, drug-induced liver injury, hepatocellular injury, hepatic cytolysis.
m Myalgia includes myalgia, musculoskeletal chest pain, musculoskeletal pain, limb discomfort, pain in the extremity.
n Arthralgia includes arthralgia and periarthritis
Relapsed/refractory diffuse large B-cell lymphoma
The adverse drug reactions (ADRs) described in this section were identified during treatment and follow-up of previously treated relapsed / refractory diffuse large B-cell lymphoma (DLBCL) adult patients from the pivotal Phase Ib/ II clinical trial GO29365. See Table 7 below.
In patients with relapsed or refractory DLBCL, the trial included a single-arm safety evaluation of POLIVY in combination with bendamustine and rituximab (BR) (n = 6), followed by an open-label randomization to POLIVY in combination with BR versus BR alone (n = 39 treated per arm).
Randomized patients in the POLIVY treatment arm received a median of 5 cycles of treatment while randomized patients in the comparator arm received a median of 3 cycles of treatment.
Following premedication with an antihistamine and antipyretic, POLIVY 1.8 mg/kg was administered by intravenous infusion on Day 2 of Cycle 1 and on Day 1 of Cycles 2–6, with a cycle length of 21 days. Bendamustine 90 mg/m2 daily was administered intravenously on Days 2 and 3 of Cycle 1 and on Days 1 and 2 of Cycles 2–6. Rituximab dosed at 375 mg/m2 was administered intravenously on Day 1 of each cycle.
In POLIVY treated patients (n = 45), the median age was 67 years (range 33 – 86) with 58% being ≥ age 65, 69% were male, 69% were white, and 87% had an Eastern Cooperative Oncology Group (ECOG) performance status of 0 or 1. The trial required an absolute neutrophil count ≥1500/μL, platelet count ≥75000/μL, creatinine clearance (CrCL) ≥40 mL/min, hepatic transaminases ≤2.5 times ULN, and bilirubin <1.5 times ULN, unless abnormalities were from the underlying disease. Patients with Grade 2 or higher peripheral neuropathy or prior allogeneic hematopoietic stem cell transplantation (HSCT) were excluded.
ADRs are listed by MedDRA system organ class in Table 7.
Table 7 Adverse Drug Reactions Reported in ≥5% of Relapsed or Refractory DLBCL Patients Treated with POLIVY in Combination with Bendamustine and Rituximab
Compared with Patients Treated with Bendamustine and Rituximab in Study GO29365
Adverse Drug Reactions System Organ Class Preferred Term | POLIVY + Bendamustine + Rituximab N = 45 | Bendamustine + Rituximab N = 39 | ||||||||||
All grades (%) | Grade 3 or Higher (%) | All grades (%) | Grade 3 or Higher (%) | |||||||||
| Blood and Lymphatic System Disorders | ||||||||||||
| Anemia | 46.7 | 24.4 | 25.6 | 17.9 | ||||||||
| Neutropenia | 46.7 | 40.0 | 38.5 | 33.3 | ||||||||
| Thrombocytopenia | 46.7 | 37.8 | 28.2 | 23.1 | ||||||||
| Febrile Neutropenia | 11.1 | 11.1 | 12.8 | 12.8 | ||||||||
| Leukopenia | 11.1 | 6.7 | 12.8 | 7.7 | ||||||||
| Lymphopenia | 11.1 | 11.1 | 0 | 0 | ||||||||
| Pancytopenia | 6.7 | 4.4 | 0 | 0 | ||||||||
| Cardiac Disorders | ||||||||||||
| Tachycardia | 8.9 | 2.2 | 5.1 | 0 | ||||||||
| Gastrointestinal Disorders | ||||||||||||
| Diarrhea | 37.8 | 4.4 | 28.2 | 5.1 | ||||||||
| Nausea | 33.3 | 0 | 41.0 | 0 | ||||||||
| Constipation | 17.8 | 0 | 20.5 | 2.6 | ||||||||
| Vomiting | 17.8 | 2.2 | 12.8 | 0 | ||||||||
| Abdominal Pain | 11.1 | 4.4 | 10.3 | 2.6 | ||||||||
| Abdominal Pain Upper | 11.1 | 2.2 | 5.1 | 0 | ||||||||
| Dyspepsia | 6.7 | 0 | 5.1 | 0 | ||||||||
| Gastroesophageal reflux disease | 6.7 | 0 | 0 | 0 | ||||||||
| Stomatitis | 6.7 | 0 | 10.3 | 0 | ||||||||
| General Disorders and Administration Site Conditions | ||||||||||||
| Fatigue | 40.0 | 4.4 | 35.9 | 2.6 | ||||||||
| Pyrexia | 33.3 | 2.2 | 23.1 | 0 | ||||||||
| Asthenia | 11.1 | 0 | 15.4 | 0 | ||||||||
| Chills | 11.1 | 0 | 7.7 | 0 | ||||||||
| Infections and Infestations | ||||||||||||
| Pneumonia a | 15.6 | 6.7 | 10.3 | 0 | ||||||||
| Upper respiratory tract infection | 8.9 | 0 | 2.6 | 0 | ||||||||
| Herpes virus infection | 6.7 | 2.2 | 0 | 0 | ||||||||
| Sepsis a | 4.4 | 4.4 | 5.1 | 5.1 | ||||||||
| Injury, Poisoning, and Procedural | ||||||||||||
| Infusion-related reaction b | 33.3 | 6.7 | 23.1 | 10.3 | ||||||||
| Investigations | ||||||||||||
| Weight decreased | 15.6 | 2.2 | 7.7 | 2.6 | ||||||||
| Hypophosphatemia | 9 | 4.4 | 2.6 | 2.6 | ||||||||
| Blood creatinine increased | 8.9 | 0 | 10.3 | 0 | ||||||||
| Transaminase elevation | 8.8. | 0 | 0 | 0 | ||||||||
| Lipase increase | 6.7 | 2.2 | 0 | 0 | ||||||||
| Metabolism and Nutrition Disorders | ||||||||||||
| Decreased appetite | 26.7 | 2.2 | 20.5 | 0 | ||||||||
| Hypokalemia | 15.6 | 6.7 | 7.7 | 2.6 | ||||||||
| Hypoalbuminemia | 13.3 | 2.2 | 5.1 | 0 | ||||||||
| Hypocalcemia | 11.1 | 2.2 | 2.6 | 0 | ||||||||
Adverse Drug Reactions System Organ Class Preferred Term | POLIVY + Bendamustine + Rituximab N = 45 | Bendamustine + Rituximab N = 39 | |||||||||
All grades (%) | Grade 3 or Higher (%) | All grades (%) | Grade 3 or Higher (%) | ||||||||
| Dehydration | 8.9 | 0 | 0 | 0 | |||||||
| Musculoskeletal and Connective Tissue Disorders | |||||||||||
| Arthralgia | 6.7 | 0 | 0 | 0 | |||||||
| Nervous System Disorders | |||||||||||
| Neuropathy Peripheral | 20.0 | 0 | 2.6 | 0 | |||||||
| Dizziness | 13.3 | 0 | 7.7 | 0 | |||||||
| Peripheral Sensory neuropathy | 13.3 | 0 | 0 | 0 | |||||||
| Headache | 8.9 | 2.2 | 5.1 | 0 | |||||||
| Dysgeusia | 6.7 | 0 | 0 | 0 | |||||||
| Hypoesthesia | 6.7 | 0 | 0 | 0 | |||||||
| Psychiatric disorders | |||||||||||
| Insomnia | 8.9 | 0 | 0 | 0 | |||||||
| Anxiety | 6.7 | 0 | 5.1 | 0 | |||||||
| Respiratory, Thoracic and Mediastinal Disorders | |||||||||||
| Cough | 15.6 | 0 | 20.5 | 0 | |||||||
| Productive cough | 8.9 | 0 | 5.1 | 0 | |||||||
| Dyspnea | 6.7 | 0 | 5.1 | 0 | |||||||
| Skin and Subcutaneous Tissue Disorders | |||||||||||
| Pruritis | 13.3 | 0 | 10.3 | 2.6 | |||||||
| Rash | 6.7 | 0 | 12.8 | 7.7 | |||||||
| Vascular Disorders | |||||||||||
| Hypotension | 8.9 | 4.4 | 12.8 | 0 | |||||||
a ADR associated with fatal outcome
b Defined as all adverse events reported as related to study treatment within 24 hours after treatment infusion
Description of Selected Adverse Drug Reactions from Clinical Trials
Myelosuppression
Previously untreated large B-cell lymphoma
Few patients (0.5%) in the POLIVY plus R-CHP arm discontinued study treatment due to neutropenia compared to no patients in the R-CHOP arm. Thrombocytopenia events led to discontinuation of treatment in 0.2% of patients in the POLIVY plus R-CHP arm and none discontinued treatment in the R-CHOP arm. No patients discontinued treatment due to anemia in either the POLIVY plus R-CHP arm or R-CHOP arm.
Relapsed/refractory diffuse large B-cell lymphoma
The incidence of Grade 3-4 neutropenia was higher in the POLIVY plus BR arm (40%) compared to the BR arm (33.3%). The incidence of febrile neutropenia was 11.1% in the POLIVY plus BR arm compared to 12.8% in the BR arm. 8.9% of patients in the POLIVY plus BR arm discontinued POLIVY due to neutropenia compared to 2.6% of patients in the BR arm who discontinued treatment due to neutropenia.
The incidence of Grade 3-4 thrombocytopenia was higher in the POLIVY plus BR arm (37.8%) compared to the BR arm (23.1%). Thrombocytopenia events led to discontinuation of treatment in 11.1% of patients in the POLIVY plus BR arm and 5.1% of patients in the BR arm.
The incidence of Grade 3-4 anemia was higher in the POLIVY plus BR arm (24.4%) compared to the BR arm (17.9%). No patients discontinued treatment due to anemia in either the POLIVY plus BR arm or BR arm.
Peripheral Neuropathy (PN)
Previously untreated large B-cell lymphoma
In the POLIVY plus R-CHP arm, Grade 1, 2, and 3 PN were reported in 39.1%, 12.2%, and 1.6% of patients, respectively. In the R-CHOP arm, Grade 1, 2, and 3 PN were reported in 37.2%, 15.5%, and 1.1% of patients, respectively. No Grade 4–5 PN were reported in either the POLIVY plus R-CHP arm or R-CHOP arm. Fewer patients (0.7%) discontinued study treatment in the POLIVY plus R-CHP compared to patients in the R-CHOP arm (2.3%). Likewise, fewer patients treated with POLIVY plus R-CHP (4.6%) had study treatment dose reduction due to PN compared to patients treated with R-CHOP (8.2%). In the POLIVY plus R-CHP arm, the median time to onset of first event of PN was 2.27 months compared to 1.87 months in the R-CHOP arm. 57.8% of patients with PN reported event resolution as of the clinical cut-off date compared to 66.9% in the R-CHOP arm. The median time to peripheral neuropathy resolution was 4.0 months compared to 4.6 months in the R-CHOP arm.
Relapsed/refractory diffuse large B-cell lymphoma
In the POLIVY plus BR arm, Grade 1 and 2 PN events were reported in 26.7% and 13.3% of patients, respectively. In the BR arm, Grade 1 and 2 PN events were reported in 2.6% and 5.1% of patients, respectively. No Grade 3-5 PN events were reported in either the POLIVY plus BR arm or BR arm. 2.2% of patients discontinued POLIVY treatment due to PN and 4.4% of patients had POLIVY dose reduction due to PN. No patients in the BR arm discontinued treatment or had dose reductions due to PN. In the POLIVY plus BR arm, the median onset to first event of PN was 1.8 months, and 61.1% of patients with PN events reported event resolution (see 7 Warnings and Precautions).
Infections
Previously untreated large B-cell lymphoma
Infections, including pneumonia and other types of infections, were reported in 49.7% of patients in the POLIVY plus R-CHP arm and 42.7% of patients in the R-CHOP arm. Grade 3-4 infections occurred in 14.0% of patients in the POLIVY plus R-CHP arm and 11.2% of patients in the R-CHOP arm. In the POLIVY plus R-CHP arm, serious infections were reported in 14.0% of patients and fatal infections were reported in 1.1% of patients. In the R-CHOP arm, serious infections were reported in 10.3% of patients and fatal infections were reported in 1.4% of patients. 7 patients (1.6%) in the POLIVY plus R-CHP arm discontinued treatment due to infection compared to 10 patients (2.3%) in the R-CHOP arm.
Relapsed/refractory diffuse large B-cell lymphoma
Infections, including pneumonia and other types of infections, were reported in 53.3% of patients in the POLIVY plus BR arm and 51.3% of patients in the BR arm. In the POLIVY plus BR arm, opportunistic infections were reported in 8.9% of patients, serious infections were reported in 28.9% of patients and fatal infections were reported in 8.9% of patients. In the BR arm, opportunistic infections were reported in 5.1% of patients, serious infections were reported in 30.8% of patients and fatal infections were reported in 10.3% of patients. One patient (2.2%) discontinued treatment in the POLIVY plus BR arm due to infection compared to 5.1% of patients in the BR arm (see section 7 Warnings and Precautions).
Progressive Multifocal Leukoencephalopathy (PML)
Previously untreated large B-cell lymphoma
No cases of PML were reported with POLIVY plus R-CHP or in the R-CHOP arm.
Relapsed/refractory diffuse large B-cell lymphoma
One case of PML, which was fatal, occurred in a patient treated with POLIVY plus bendamustine and obinutuzumab. This patient had three prior lines of therapy that included anti-CD20 antibodies (see section 7 Warnings and Precautions).
Hepatic Toxicity
Previously untreated large B-cell lymphoma
Hepatic toxicity was reported in 10.6% of patients in the POLIVY plus R-CHP arm and 7.3% of patients in the R-CHOP arm. In the POLIVY plus R-CHP arm, most events were Grade 1–2 (8.7%); Grade 3 events were reported in 1.8% of patients. There were no Grade 4 or 5 events. Serious hepatic toxicity events were reported in 1 patient (0.2%) and were reversible.
Relapsed/refractory diffuse large B-cell lymphoma
Hepatic toxicity events were reported in 20% of patients in the POLIVY plus BR arm and 12.8% of patients in the BR arm. Grade 3-4 were reported in 4.4% of patients in the POLIVY plus BR arm compared to 2.6% of patients in the BR arm. Most events were low grade laboratory abnormalities that were reversible. In another study, two cases of serious hepatic toxicity (hepatocellular injury and hepatic steatosis) were reported and were reversible (see 7 Warnings and Precautions).
Gastrointestinal Toxicity
Previously untreated large B-cell lymphoma
Gastrointestinal toxicity events were reported in 76.1% of patients in the POLIVY plus R-CHP arm compared to 71.9% of patients in the R-CHOP arm. Most events were Grade 1–2, and Grade ≥3 events were reported in 9.7% of patients in the POLIVY plus R-CHP arm compared to 8.2% of patients in the R-CHOP arm. The most common gastrointestinal toxicity events were nausea and diarrhea.
Relapsed/refractory diffuse large B-cell lymphoma
Gastrointestinal toxicity events were reported in 80.0% of patients in the POLIVY plus BR arm compared to 64.1% of patients in the BR arm. Most events were Grade 1-2, and Grade 3-4 events were reported in 22.2% of patients in the POLIVY plus BR arm compared to 12.8% of patients in the BR arm. The most common gastrointestinal toxicity events were diarrhea and nausea.
Less Common Clinical Trial Adverse Reactions
Other clinically relevant adverse reactions (all grades) in recipients of POLIVY plus R-CHP in patients with previously untreated LBCL included:
General Disorders and Administration Site Conditions: Infusion Site Extravasation (0.9%)
Blood and Lymphatic System Disorders: pancytopenia (0.2%)
Infections and infestations: cytomegalovirus infection (0.7%)
Metabolism and nutrition disorders: tumour lysis syndrome (0.5%)
Other clinically relevant adverse reactions in recipients of POLIVY plus BR included:
Infections and infestations: cytomegalovirus infection (2.2%)
Respiratory disorders: pneumonitis (4.4%)
Abnormal Laboratory Findings: Hematologic, Clinical Chemistry, and Other Quantitative Data
Table 8 Selected Laboratory Abnormalities (New and Worsening) from Baseline in Patients with Previously Untreated LBCL in Study GO39942
| Laboratory Parametera | POLIVY + R-CHP N = 435 | R-CHOP N = 438 | ||
|---|---|---|---|---|
All Grades (%) | Grades 3-4 (%) | All Grades (%) | Grades 3-4 (%) | |
| Hematologic | ||||
| Hemoglobin decreased | 62 | 10 | 63 | 8 |
| Lymphocyte count decreased | 79 | 43 | 77 | 43 |
| Neutrophil count decreased | 56 | 35 | 57 | 37 |
| Platelet count decreased | 31 | 7 | 30 | 6 |
| Chemistry | ||||
| Albumin decreased | 21 | 0.7 | 18 | 0.2 |
| Calcium decreased | 26 | 1.4 | 21 | 0.9 |
| Phosphorus decreased | 19 | 3.7 | 14 | 2.1 |
| Potassium decreased | 17 | 2.5 | 11 | 1.8 |
| SGPT/ALT increased | 24 | 0.9 | 26 | 0.5 |
| SGOT/AST increased | 24 | 0.5 | 22 | 1.1 |
aIncludes laboratory abnormalities that are new or worsening in grade or with worsening from baseline unknown.
Table 9 Significant Laboratory Abnormalities Worsening from Baseline in Patients with Relapsed or Refractory DLBCL and ≥ 5% More in the POLIVY Plus Bendamustine and Rituximab Product Group
| Laboratory Parametera | POLIVY + Bendamustine + Rituximab N = 45 | Bendamustine + Rituximab N = 39 | ||
|---|---|---|---|---|
All Grades (%) | Grades 3-4 (%) | All Grades (%) | Grades 3-4 (%) | |
| Hematologic | ||||
| Hemoglobin decreased | 78 | 18 | 62 | 10 |
| Lymphocyte count decreased | 87 | 87 | 90 | 82 |
| Neutrophil count decreased | 78 | 61 | 56 | 33 |
| Platelet count decreased | 76 | 31 | 64 | 26 |
| Chemistry | ||||
| Amylase increased | 24 | 0 | 18 | 2.6 |
| Calcium decreased | 44 | 9 | 26 | 0 |
| Creatinine increased | 87 | 4.4 | 77 | 5 |
| Lipase increased | 36 | 9 | 13 | 5 |
| Phosphorus decreased | 33 | 7 | 28 | 8 |
| Potassium decreased | 24 | 11 | 28 | 5 |
| SGPT/ALT increased | 38 | 0 | 8 | 2.6 |
| SGOT/AST increased | 36 | 0 | 26 | 2.6 |
aIncludes laboratory abnormalities that are new or worsening in grade or with worsening from baseline unknown.
Post-Market Adverse Reactions
Infusion site extravasation injury with POLIVY has been identified in the post-market setting based on spontaneous case reports and literature cases (see 7 Warnings and Precautions).
Cases of tissue damage following infusion site extravasation (including severe events) have occured in patients receiving POLIVY. The signs and symptoms of infusion site extravasation injury reported were sensation of burning, tingling, pain, discomfort, swelling and redness at site of injection, some of which progressed to more severe events like blistering, necrosis, ulceration, and tissue damage such as cellulitis.
9. Drug Interactions
Drug-Interactions Overview
No dedicated clinical drug-drug interaction studies with POLIVY in humans have been conducted.
Drug-Drug Interactions
Drug interactions with co-medications that are CYP3A inhibitors, inducers or substrates
Based on physiological-based pharmacokinetic (PBPK) model simulations of monomethyl auristatin E (MMAE) released from polatuzumab vedotin, strong CYP3A inhibitors (e.g., ketoconazole) may increase the area under the concentration-time curve (AUC) of unconjugated MMAE by 48%. Monitor patients receiving concomitant strong CYP3A inhibitors more closely for signs of toxicities. Strong CYP3A inducers (e.g., rifampin) may decrease the AUC of unconjugated MMAE.
Unconjugated MMAE is not predicted to alter the AUC of concomitant drugs that are CYP3A substrates (e.g., midazolam).
Drug interactions of rituximab, bendamustine, cyclophosphamide, and doxorubicin in combination with polatuzumab vedotin
The pharmacokinetics (PK) of rituximab, bendamustine, cyclophosphamide, and doxorubicin are not affected by co-administration with POLIVY. Concomitant rituximab is associated with increased antibody conjugated MMAE (acMMAE) plasma AUC by 24% and decreased unconjugated MMAE plasma AUC by 37%, based on population PK analysis. The plasma AUC of acMMAE and unconjugated MMAE for POLIVY plus R-CHP are in line with other studies of POLIVY. No dose adjustment is required.
Bendamustine does not affect acMMAE and unconjugated MMAE plasma AUC.
Drug-Food Interactions
Interactions with food have not been specifically studied with POLIVY. Grapefruit has CYP3A4 inhibitory activity. Therefore, ingestion of grapefruit while on POLIVY therapy may increase MMAE plasma concentrations. However, patients consuming grapefruit, grapefruit containing products, or other foods known to inhibit CYP3A4 should be monitored more closely for signs of toxicity during treatment with POLIVY.
Drug-Herb Interactions
Interactions with herbs have not been established.
Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10. Clinical Pharmacology
 Mechanism of Action
Polatuzumab vedotin is a CD79b-targeted antibody-drug conjugate that preferentially delivers an anti-mitotic agent (monomethyl auristatin E, or MMAE) to B-cells, which results in the killing of malignant B-cells. The polatuzumab vedotin molecule consists of MMAE covalently attached via a cleavable linker to a humanized immunoglobulin G1 (IgG1) monoclonal antibody, which is produced by recombinant DNA technology in Chinese hamster ovary (CHO) cells. The monoclonal antibody binds with nanomolar affinity and selectivity to CD79b, a cell surface component of the B-cell receptor. CD79b expression is restricted to normal cells within the B cell lineage (with the exception of plasma cells) and malignant B-cells; it is expressed in >95% of DLBCL. Upon binding CD79b, polatuzumab vedotin is rapidly internalized and the linker is cleaved by lysosomal proteases to enable intracellular delivery of MMAE. MMAE binds to microtubules and kills dividing cells by inhibiting cell division and inducing apoptosis.
 Pharmacodynamics
Cardiac Electrophysiology
The effect of polatuzumab vedotin on the QTc interval was evaluated based on triplicate ECG data from two open-label studies in 209 patients (102 patients at 1.8 mg/kg) with previously treated B-cell malignancies. Administration of polatuzumab vedotin did not prolong the mean
QTc interval >20 ms from baseline. Increases in the mean QTc interval of <10 ms cannot be excluded because this study did not include a placebo arm and a positive control arm.
 Pharmacokinetics
Antibody-conjugated MMAE (acMMAE) plasma exposure increased dose-proportionally over the 0.1 to 2.4 mg/kg polatuzumab vedotin dose range. After the first 1.8 mg/kg polatuzumab vedotin dose, the acMMAE mean maximum concentration (Cmax) was 803 (± 233) ng/mL and the area under the concentration-time curve from time zero to infinity (AUCinf) was 1860 (± 966) day*ng/mL. Based on the population PK analysis, Cycle 3 acMMAE AUC increased by approximately 30% over cycle 1 AUC, and achieved more than 90% of the Cycle 6 AUC. The terminal half-life at cycle 6 was approximately 12 days (95% CI of 8.1-19.5 days) for acMMAE.
Exposures of unconjugated MMAE, the cytotoxic component of polatuzumab vedotin, increased dose proportionally over the 0.1 to 2.4 mg/kg polatuzumab vedotin dose range. MMAE plasma concentrations followed formation rate limited kinetics. After the first 1.8 mg/kg polatuzumab vedotin dose, the Cmax was 6.82 (± 4.73) ng/mL, the time to maximum plasma concentration is approximately 2.5 days, and the terminal half-life is approximately 4 days. Plasma exposures of unconjugated MMAE are <3% of acMMAE exposures. Based on the population PK analysis, there is a decrease of plasma unconjugated MMAE exposure (AUC and Cmax) after repeated every-three-week dosing.
Absorption: POLIVY is administered as an IV infusion. There have been no studies performed with other routes of administration.
Distribution: The population estimate of central volume of distribution for acMMAE was 3.15 L, which approximated plasma volume. In vitro, MMAE is moderately bound (71% - 77%) to human plasma proteins. MMAE does not significantly partition into human red blood cells in vitro; the blood to plasma ratio is 0.79 to 0.98. In vitro data indicate that MMAE is a P-gp substrate but does not inhibit P-gp at clinically relevant concentrations.
Metabolism: Polatuzumab vedotin is expected to undergo catabolism in patients, resulting in the production of small peptides, amino acids, unconjugated MMAE, and unconjugated MMAE related catabolites. In vitro studies indicate that MMAE is a substrate for CYP 3A4/5 but does not induce major CYP enzymes. MMAE is a weak time-dependent inhibitor of CYP3A4/5 but does not competitively inhibit CYP3A4/5 at clinically relevant concentrations. MMAE does not inhibit CYP1A2, CYP2B6, CYP2C8, CYP2C9, CYP2C19, or CYP2D6.
Elimination: Based on a population pharmacokinetic analysis, the conjugate (acMMAE) is primarily eliminated by non-specific linear clearance pathway with a value of 0.9 L/day.
In vivo studies in rats dosed with polatuzumab vedotin (radiolabel on MMAE) demonstrate that the majority of radioactivity is excreted in feces and the minority of radioactivity is excreted in urine.
Special populations and conditions
- Pediatrics: No studies have been conducted to investigate the pharmacokinetics of POLIVY in pediatric patients (<18 years old).
- Geriatrics: Age did not have an effect on the pharmacokinetics of acMMAE and unconjugated MMAE based on population PK analyses with patients aged 19-89 years. No significant difference was observed in the pharmacokinetics of acMMAE and unconjugated MMAE among patients <65 years of age (n=394) and patients ≥65 years of age (n=495).
- Body Weight: Based on population PK analysis in patients with previously untreated LBCL, body weight > 100 kg resulted in mildly high acMMAE (increase of 14% in AUC and 8% in Cmax) compared to the exposures of lighter patients. However, unconjugated MMAE exposures were higher in patients weighing > 100 kg compared to lighter patients (54% for AUC and 48% for Cmax). Monitor patients weighing > 100 kg more closely for signs of toxicities.
- Hepatic Impairment: In patients with mild hepatic impairment [AST >1.0 - 2.5×ULN or ALT >1.0 - 2.5×ULN or total bilirubin >1.0 - 1.5×ULN, n=133], acMMAE exposures are similar whereas unconjugated MMAE AUC were up to 40% higher compared to patients with normal hepatic function (n=737), based on population pharmacokinetic analyses. Limited or no data are available in patients with moderate or severe hepatic impairment as Polivy should not be administered to these patients (see 7 Warnings and Precautions).
- Renal Impairment: In patients with mild (CrCL 60-89 mL/min, n=361) or moderate (CrCL 30-59 mL/min, n=163) renal impairment, acMMAE and unconjugated MMAE exposures are similar to patients with normal renal function (CrCL ≥ 90 mL/min, n=356), based on a population pharmacokinetic analysis. There are insufficient data to assess the impact of severe renal impairment (CrCL 15-29 mL/min, n=4) on PK. No data are available in patients with end-stage renal disease and/or who are on dialysis (see 4 Dosage and Administration).
 Immunogenicity
As with all therapeutic proteins, there is the potential for an immune response in patients treated with polatuzumab vedotin. In Studies GO39942 (POLARIX) and GO29365, 1.4% (6/427) and 5.2% (12/233) of patients tested positive for antibodies against polatuzumab vedotin, respectively, of which none were positive for neutralizing antibodies. Due to the limited number of anti-polatuzumab vedotin antibody positive patients, no conclusions can be drawn concerning a potential effect of immunogenicity on efficacy or safety.
Immunogenicity assay results are highly dependent on several factors including assay sensitivity and specificity, assay methodology, sample handling, timing of sample collection, concomitant medications and underlying disease. For these reasons, comparison of incidence of antibodies to polatuzumab vedotin with the incidence of antibodies to other products may be misleading.
- 11. Storage, Stability, and Disposal
Vials
Store unopened vials at 2°C to 8°C.
Keep vial in the outer carton in order to protect from light.
Do not freeze. Do not shake.
Shelf life
This medicine should not be used after the expiry date (EXP) shown on the pack.
Shelf life of reconstituted product and solution for infusion
See section 4 Dosage and Administration, 4.3 Reconstitution.
The reconstituted solution and solution for infusion should not be frozen or exposed to direct sunlight.
Disposal of unused/expired medicines
The release of pharmaceuticals in the environment should be minimized. Medicines should not be disposed of via wastewater and disposal through household waste should be avoided.
The following points should be strictly adhered to regarding the use and disposal of syringes and other medicinal sharps:
- Needles and syringes should never be reused.
- Place all used needles and syringes into a sharps container (puncture-proof disposable container).
Any unused medicinal product or waste material should be disposed of in accordance with local requirements.
12. Special Handling Instructions
Not applicable.
Part 2: Scientific Information
13. Pharmaceutical Information
Drug Substance
Proper name: polatuzumab vedotin
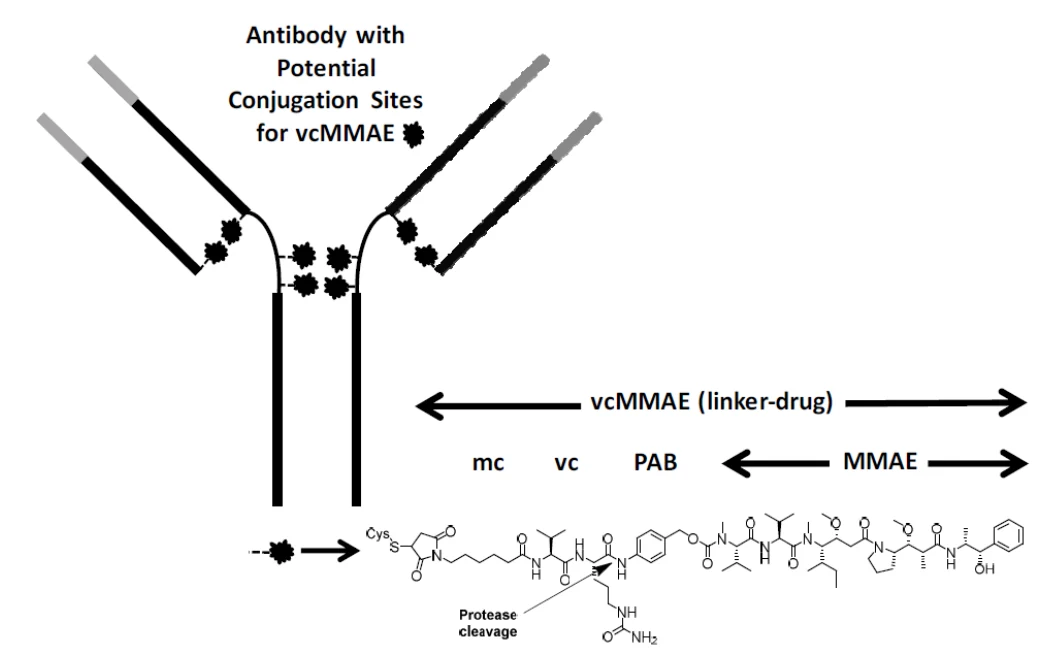
Chemical name: Immunoglobulin G1, anti-(human antigen CD79b) (human-Mus musculus monoclonal MCDS4409A heavy chain), disulfide with human-Mus musculus monoclonal MCDS4409A κ-chain, dimer, thioether with maleimidocaproyl-valine-citrulline- p-aminobenzyloxycarbonyl monomethylauristatin E
Molecular formula and molecular mass: C68H105N11O15
Polatuzumab vedotin has an average molecular mass of 1316.63 Da.
Structural formula:
14. Clinical Trials
 Clinical Trials by Indication
Previously Untreated LBCL
Trial Design and Study Demographics
Table 10 Summary of Patient Demographics for Clinical Trials in Previously Untreated LBCL
| Study # | Study Design | Dosage, Route of administration and duration | Study subjects (n) | Mean age (Range) | Sex |
|---|---|---|---|---|---|
GO39942 (POLARIX) | Phase 3, multicenter, randomized, double-blind, placebo-controlled | pola+R-CHP (investigational arm): pola was administered by IV infusion at 1.8mg/kg on Day 1 of each 21-day cycle for 6 cycles; R-CHP chemoimmunotherapy. Placebo for vincristine administered concurrently every 21 days for each 21-day cycle. R-CHOP (control arm): R-CHOP chemoimmunotherapy was administered on Day 1 of each 21-day cycle for 6 cycles; placebo for pola was administered concurrently every 21 days for each 21-day cycle. For both arms: Rituximab was administered as monotherapy in Cycle 7 and Cycle 8 | pola+R-CHP: 440 R-CHOP: 439 | pola+R-CHP: 63.11 (19.0-80.0) R-CHOP: 63.01 (19.0-80.0) | Male: 53.8% Female: 46.2% |
IV: intravenous; pola+R-CHP: polatuzumab vedotin, rituximab, cyclophosphamide, doxorubicin hydrochloride, prednisone; R-CHOP: rituximab, cyclophosphamide, doxorubicin hydrochloride, vincristine sulfate, prednisone.
The efficacy of POLIVY was evaluated in an international, multicenter, randomized, double-blind, placebo-controlled study (POLARIX, GO39942) in 879 patients with previously untreated LBCL. Patients were randomized 1:1 to receive POLIVY plus R-CHP (n=440) or R-CHOP (n=439) for six 21-day cycles followed by two additional cycles of rituximab alone in both arms. Patients were stratified by the International Prognostic Index (IPI) score (2 vs 3-5), presence or absence of bulky disease (lesion ≥7.5 cm), and geographical region.
Eligible patients were age 18–80 years, and had IPI score 2-5 and ECOG Performance Status 0–2. Histologies included DLBCL (NOS, ABC, GCB) (84.2%), high-grade B-cell lymphoma
(HGBL; NOS, double-hit, triple-hit) (10.6%), EBV positive DLBCL (2.0%), and T-cell rich/histiocyte rich LBCL (3.2%). Patients were excluded if they had follicular lymphoma grade 3B, B-cell lymphoma, unclassifiable, with features intermediate between DLBCL and classical Hodgkin lymphoma (grey-zone lymphoma), primary mediastinal (thymic) large B-cell lymphoma, Burkitt lymphoma, CNS lymphoma (primary or secondary involvement), primary effusion DLBCL, and primary cutaneous DLBCL. Patients were also excluded for peripheral neuropathy > Grade 1, an active infection, hepatic impairment (total bilirubin ≥ 1.5 x ULN or AST and ALT ≥ 2.5 x ULN), renal impairment (creatinine clearance <40 mL/min), and a known history of HIV seropositive status.
POLIVY was administered intravenously at 1.8 mg/kg on Day 1 of cycles 1–6. R-CHP or R-CHOP were administered starting on Day 1 of Cycles 1–6 followed by rituximab alone on Day 1 of Cycles 7–8. Dosing in each treatment arm was administered according to the following:
- POLIVY plus R-CHP arm: POLIVY 1.8 mg/kg, rituximab 375 mg/m², cyclophosphamide 750 mg/m², doxorubicin 50 mg/m², and prednisone 100 mg/day, on days 1-5 of every cycle, orally.
- R-CHOP arm: rituximab 375 mg/m², cyclophosphamide 750 mg/m², doxorubicin 50 mg/m², vincristine 1.4 mg/m², and prednisone 100 mg/day, on days 1-5 of every cycle, orally.
The two treatment groups were generally balanced with respect to baseline demographics and disease characteristics. The median age was 65 years (range 19 to 80 years), 53.6% of patients were white and 53.8% were male. 43.8% had bulky disease, 38.0% had IPI score 2, 62.0% had IPI score 3–5, and 88.7% had Stage 3 or 4 disease. The majority of patients (84.2%) had DLBCL (including NOS, ABC, and GCB). By gene expression profiling, 25.1% of patients had activated B-cell like (ABC) DLBCL and 40.0% of patients had germinal center B-cell like (GCB) DLBCL.
Study Results
In the POLIVY plus R-CHP group, 91.7% of patients received 6 cycles of POLIVY versus 88.5% of patients who received 6 cycles of vincristine in the R-CHOP group.
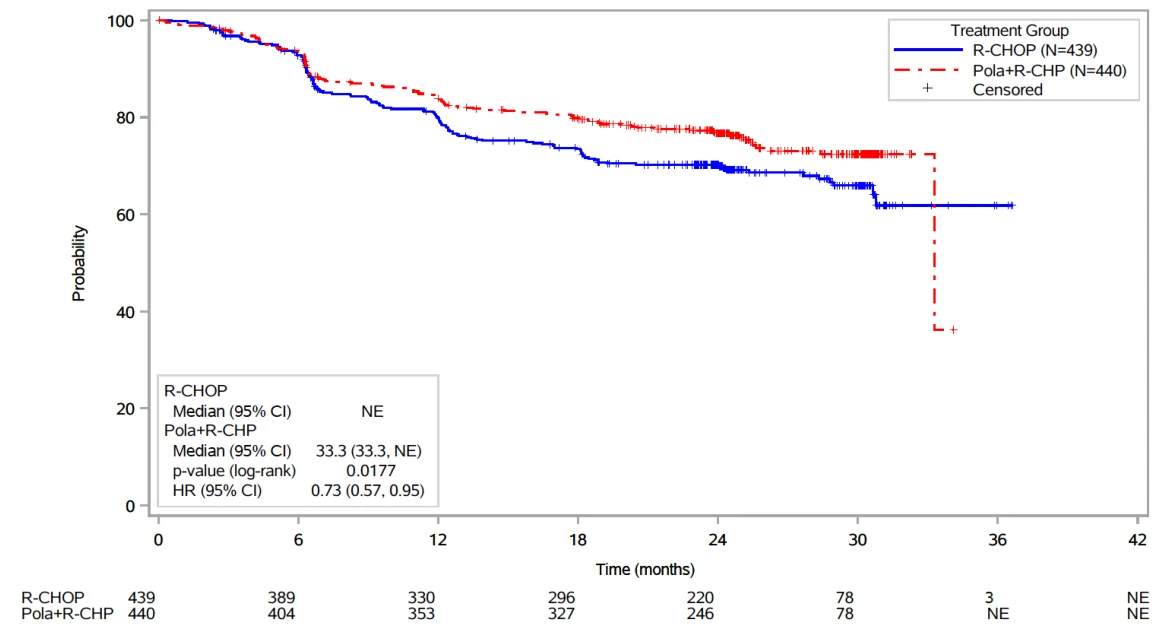
The primary endpoint of the study was investigator (INV)-assessed progression-free survival (PFS). The median duration of follow up was 28.2 months. Key secondary endpoints were event-free survival (EFS) based on INV assessments and complete response (CR) rates according to a blinded independent central review (BICR). The study was not powered to detect differences in overall survival between the two treatment arms. Efficacy results are summarized in Table 11, Table 12, and in Figure 1.
Table 11 Summary of Efficacy in Patients with Previously Untreated LBCL from Study GO39942 (POLARIX)
POLIVY + R-CHP N= 440 | R-CHOP N= 439 | ||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Primary Endpoint | |||||||||||||
| PFS1)* | |||||||||||||
| Number (%) of patients with events | 107 (24.3%) | 134 (30.5%) | |||||||||||
| HR (95% CI) | 0.73 [0.57, 0.95] | ||||||||||||
| p-value3)** | 0.018 | ||||||||||||
| 2-year PFS estimate | 76.7 | 70.2 | |||||||||||
| [95% CI] | [72.65, 80.76] | [65.80, 74.61] | |||||||||||
| Secondary Endpoints | |||||||||||||
| EFS 1) | |||||||||||||
| Number (%) of patients with event | 112 (25.5%) | 138 (31.4%) | |||||||||||
| HR [95% CI] | 0.75 [0.58, 0.96] | ||||||||||||
| p-value3)** | 0.02 | ||||||||||||
| CR Rate (%) 2)* | |||||||||||||
| Responders (%) | 343 (78.0%) | 325 (74.0%) | |||||||||||
| Difference in response rate (%) [95% CI] | 3.92 [-1.89, 9.70] | ||||||||||||
| p-value4)** | 0.16 | ||||||||||||
INV: Investigator; BICR: Blinded independent central review; CI: Confidence interval; HR: Hazard ratio; PFS: Progression free survival; EFS: Event free survival is defined as time from date of randomization to the earliest occurrence of any of the following: disease progression/relapse, death due to any cause, the primary efficacy reason determined by the investigator, other than disease progression/relapse, that led to initiation of any non-protocol specified anti-lymphoma treatment (NALT), if biopsy was obtained after treatment completion and was positive for residual disease regardless of whether NALT was initiated or not; CR: Complete Response; CMH: Cochran-Mantel-Haenszel.
- 1) INV-assessed
- 2) BICR-assessed
- 3) Log-rank text, stratified
- 4) CMH chi-squared test
*Per Lugano 2014 Response Criteria
**Stratified by IPI (2 vs 3-5), presence or absence of bulky disease, geography
Figure 1 Kaplan Meier curve of INV-assessed Progression Free Survival in Study GO39942 (POLARIX)
The results of a post-hoc exploratory analysis of PFS by both IPI and bulky disease (stratification factors) are presented in Table 12.
Table 12 Exploratory Analysis of PFS Results in Previously Untreated LBCL by IPI and Bulky Disease
| Bulky Disease Absent | Bulky Disease Present | |||||||||
|---|---|---|---|---|---|---|---|---|---|---|
| POLIVY + R-CHP | R-CHOP | POLIVY + R-CHP | R-CHOP | |||||||
| IPI 2 | N = 108 | N = 109 | N = 59 | N = 58 | ||||||
| HR (95% CI)a | 1.04 (0.54, 1.98) | 0.94 (0.49, 1.80) | ||||||||
| IPI 3-5 | N = 139 | N = 138 | N = 134 | N = 134 | ||||||
| HR (95% CI)a | 0.40 (0.25, 0.63) | 1.08 (0.70, 1.65) | ||||||||
a Based on an unstratified Cox proportional hazard model.
Relapsed/refractory DLBCL
Trial Design and Study Demographics
Table 13 Summary of Patient Demographics for Clinical Trials in Relapsed/Refractory DLBCL
| Study # | Study Design | Dosage, Route of administration and duration | Study subjects (n) | Median age (Range) | Sex |
|---|---|---|---|---|---|
| GO29365 | Phase Ib/II, Multicenter, Open-label | POLIVY was given intravenously at 1.8 mg/kg administered on Day 2 of Cycle 1 and on Day 1 of Cycles 2-6. Bendamustine was administered at 90 mg/m2 intravenously daily on Days 2 and 3 of Cycle 1 and on Days 1 and 2 of Cycles 2-6. Rituximab was administered at 375 mg/m2 intravenously on Day 1 of Cycles 1-6. | POLIVY plus BR: 40 BR: 40 | 69 (30-86) | Male: 66% Female: 34% |
The efficacy of POLIVY was evaluated in Study GO29365, an international, multicenter, open-label, Phase Ib/II trial which included a randomized cohort of 80 patients with previously treated DLBCL. Patients were randomized 1:1 to receive POLIVY plus bendamustine and rituximab (BR) or BR alone for six 21-day cycles. Patients were stratified by duration of response to last prior treatment of ≤12 months or >12 months.
Eligible patients were not candidates for autologous hematopoietic stem cell transplant (HSCT) at study entry, had relapsed or refractory disease after receiving at least one prior systemic chemotherapy regimen, and had an ECOG PS ≤2. The study excluded patients with prior allogeneic HSCT, central nervous system lymphoma, transformed follicular lymphoma (FL), grade 3b FL, Grade >1 peripheral neuropathy, significant cardiovascular or pulmonary disease, active infections. In addition, patients with abnormal creatinine >1.5×ULN (or CrCl < 40 mL/min), and AST or ALT >2.5×ULN or total bilirubin ≥1.5× ULN were also excluded, unless abnormal laboratory values were due to underlying lymphoma per the investigator.
In study GO29365, 80 patients were randomized to receive POLIVY plus BR (n=40) or BR alone (n=40). The median age was 69 years (range 30 to 86 years) and 71% of patients were white and 66% were male. The majority of patients (98%) had DLBCL not otherwise specified (NOS). Overall, 48% of patients had activated B-cell (ABC) DLBCL and 40% of patients had germinal center B-cell like (GCB) DLBCL. Primary reasons patients were not candidates for
HSCT included age (40%), insufficient response to salvage therapy (26%) and prior transplant failure (20%). The median number of prior therapies was 2 (range: 1-7) with 29% (n=23) receiving one prior therapy, 25% (n=20) receiving 2 prior therapies, and 46% (n=37) receiving 3 or more prior therapies. Eighty (80%) of patients had refractory disease.
Study Results
The primary endpoint of the study was complete response (CR) rate at end of treatment (6-8 weeks after day 1 of cycle 6 or last study treatment) as assessed by independent review committee (IRC). Efficacy was based on the primary endpoint, complete response (CR) rate at the end of treatment as assessed by IRC. Key supportive efficacy endpoints were objective response rate at the end of treatment and best overall response rate. Duration of response was also assessed in the study.
Table 14 Summary of Efficacy in Patients with Previously Treated DLBCL from study GO29365
POLIVY + Bendamustine + Rituximab N= 40 | Bendamustine + Rituximab N= 40 | ||||||
|---|---|---|---|---|---|---|---|
| Median observation time 22 months | |||||||
| Primary Endpoint | |||||||
| Complete Response Rate* (IRC-assessed) at End of treatment** | |||||||
| Responders (%) | 16 (40.0) | 7 (17.5) | |||||
| Difference in response rate (%) [95% CI] | 22.5 [2.6, 40.2] | ||||||
| Key Secondary Endpoints | |||||||
| Objective Response Rate* (IRC-assessed) at End of Treatment** | |||||||
| Responders (%) (CR, PR) | 18 (45.0) | 7 (17.5) | |||||
| Difference in response rate (%) [95% CI] | 27.5 [7.2, 45.0] | ||||||
| Best Overall Response Rate* (IRC-assessed) | |||||||
| Responders (%) [CR, PR] | 25 (62.5) | 10 (25.0) | |||||
| Complete Response (%) [CR]*** | 20 (50.0) | 9 (22.5) | |||||
IRC: Independent Review Committee; CI: Confidence Interval
*Per modified Lugano 2014 criteria: Bone marrow confirmation of PET-CT CR required. PET-CT PR required meeting both PET-CT criteria and CT criteria.
**6-8 weeks after day 1 of cycle 6 or last study treatment
***95% CI Clopper-Pearson: [33.8, 66.2] versus [10.8, 38.5]
In the POLIVY plus BR arm 25 patients achieved a complete or partial response versus 10 in the BR arm. The median duration of response was 12.6 months for patients in the POLIVY plus BR arm versus 7.7 months for patients in the BR arm.
15. Microbiology
No microbiological information is required for this product.
16. Non-Clinical Toxicology
General toxicology
Repeat dose toxicity
Repeat dose toxicity studies were conducted in rats (non-binding species) intravenously administered 2, 6, or 10 mg/kg polatuzumab vedotin, given once weekly (QW) for 4 total doses, followed by a 6-week recovery period. Bone marrow (decreased cellularity), thymus (decreased cellularity and increased apoptosis/mitoses), liver (focal necrosis and increased apoptosis/mitoses), and gastrointestinal tract (increased apoptosis/mitoses in the epithelium of the small and large intestines) toxicities were observed primarily at the 6 and 10 mg/kg dose levels. Testes toxicity was observed across all dose levels. All changes were reversible following a 6 week recovery period except for testes toxicity and residual histologic findings observed in single individual animals. The AUC for total antibody in rats at 2 mg/kg QW was similar to the AUC in patients at the recommended dose of 1.8 mg/kg every 21 days (Q3W). The AUC for unconjugated MMAE in rats at 2 mg/kg QW was below the exposure in patients at the recommended dose.
Repeat dose toxicity studies were also conducted in cynomolgus monkeys intravenously administered polatuzumab vedotin at 1, 3 or 5 mg/kg or a surrogate antibody-drug conjugate (ADC) at 3 or 5 mg/kg, given once every 3 weeks for 4 total doses, followed by a 9-week recovery period. The surrogate ADC binds to CD79b on monkey B-cells, whereas polatuzumab vedotin does not. Reversible, dose-dependent bone marrow hypocellularity was observed in both polatuzumab vedotin and surrogate ADC groups. Pharmacologically anticipated decreases in circulating B-lymphocytes and depletion of lymphoid follicular germinal centers in the spleen were observed in all animals administered the surrogate ADC. The AUC for total antibody in monkeys receiving 3 mg/kg Q3W of the surrogate ADC was 2.2-fold higher compared to patients at the 1.8 mg/kg Q3W dose. The AUC for unconjugated MMAE in monkeys receiving 3 mg/kg Q3W of the surrogate ADC was below the exposure in patients at the 1.8 mg/kg Q3W dose.
In both rats and monkeys, the predominant systemic toxicities associated with repeated administration of MMAE and polatuzumab vedotin included reversible bone marrow toxicity and associated peripheral blood cell effects.
Genotoxicity
No genotoxicity studies have been performed with polatuzumab vedotin. MMAE was genotoxic in the rat bone marrow micronucleus study through an aneugenic mechanism. This mechanism is consistent with the pharmacological effect of MMAE as a microtubule disrupting agent. MMAE was not mutagenic in vitro in the bacterial reverse mutation assay (Ames test) or the L5178Y mouse lymphoma forward mutation assay.
Carcinogenicity
No carcinogenicity studies in animals have been performed with polatuzumab vedotin or MMAE.
Reproductive and developmental toxicology
Impairment of Fertility
No dedicated fertility studies in animals have been performed with polatuzumab vedotin. However, results of repeat-dose toxicity in rats indicate the potential for polatuzumab vedotin to impair male reproductive function and fertility. In the 4-week repeat-dose toxicity study in rats with weekly dosing of 2, 6, or 10 mg/kg polatuzumab vedotin, dose-dependent testicular seminiferous tubule degeneration with abnormal lumen contents in the epididymis was observed. Findings in the testes and epididymis did not reverse and correlated with decreased testes weight and gross findings of small and/or soft testes at recovery necropsy in males given doses ≥ 2 mg/kg (below the exposure in patients at the recommended dose based on unconjugated MMAE AUC).
Developmental Toxicity
No teratogenicity studies in animals have been performed with polatuzumab vedotin. However, MMAE was evaluated in rats in an embryo-fetal developmental and toxicokinetic study, in which pregnant rats received 2 intravenous doses of 0.2 mg/kg MMAE during the period of organogenesis on gestational day 6 and 13. Treatment with MMAE at 0.2 mg/kg caused fetal external malformations including protruding tongue, malrotated limbs, gastroschisis, and agnathia. Systemic exposure (AUC) in rats at a dose of 0.2 mg/kg MMAE is approximately 50% of the AUC in patients who received the recommended dose of 1.8 mg/kg POLIVY every 21-days.