


Product Monograph - Rybrevant
Recent Major Label Changes
| 2025-01 |
|---|---|
| 2026-06 |
| 2026-06 |
| 2025-01 |
| 2025-11 |
| 2026-06 |
| 2025-01 |
| 2026-06 |
| 2025-11 |
| 2026-07 |
| 2025-01 |
| 2026-06 |
Table of Contents
Certain sections or subsections that are not applicable at the time of the preparation of the most recent authorized product monograph are not listed.
Recent Major Label Changes ................................................................................................. 4
Table of Contents ................................................................................................................. 4
Part 1: Healthcare Professional Information.......................................................................... 7
- 1.
Indications ................................................................................................................ 7
1.1. Pediatrics ................................................................................................................ 7
1.2. Geriatrics ................................................................................................................ 7
- 2. Contraindications ...................................................................................................... 8
- 4.
Dosage and Administration ....................................................................................... 8
4.1. Dosing Considerations ........................................................................................... 8
4.2. Recommended Dose and Dosage Adjustment ...................................................... 8
4.3. Reconstitution ...................................................................................................... 14
4.4. Administration ..................................................................................................... 14
4.5. Missed Dose ......................................................................................................... 17
- 5. Overdose ................................................................................................................ 17
- 6. Dosage Forms, Strengths, Composition, and Packaging ............................................ 18
- 7.
Warnings and Precautions ....................................................................................... 18
Carcinogenesis and Genotoxicity ..................................................................................... 18
Cardiovascular .................................................................................................................. 18
Driving and Operating Machinery .................................................................................... 19
Immune ............................................................................................................................ 19
Monitoring and Laboratory Tests .................................................................................... 20
Ophthalmologic ................................................................................................................ 20
Reproductive Health ........................................................................................................ 20
Respiratory ....................................................................................................................... 20
Skin ................................................................................................................................... 21
7.1. Special Populations .............................................................................................. 21
7.1.1. Pregnancy ......................................................................................................... 21
7.1.2. Breastfeeding ................................................................................................... 22
7.1.3. Pediatrics .......................................................................................................... 22
7.1.4. Geriatrics .......................................................................................................... 22
- 8.
Adverse Reactions ................................................................................................... 23
8.1. Adverse Reaction Overview ................................................................................. 23
8.2. Clinical Trial Adverse Reactions ........................................................................... 24
Select Adverse Reactions ................................................................................................. 36
8.3. Less Common Clinical Trial Adverse Reactions .................................................... 39
8.4. Abnormal Laboratory Findings: Hematologic, Clinical Chemistry, and Other Quantitative Data ............................................................................................................. 41
8.5. Post-Market Adverse Reactions ........................................................................... 44
- 9. Drug Interactions .................................................................................................... 44
- 10.
Clinical Pharmacology ............................................................................................. 44
10.1. Mechanism of Action ....................................................................................... 44
10.2. Pharmacodynamics .......................................................................................... 44
10.3. Pharmacokinetics ............................................................................................. 44
10.4. Immunogenicity ............................................................................................... 46
- 11. Storage, Stability, and Disposal ................................................................................ 46
- 12. Special Handling Instructions ................................................................................... 47
Part 2: Scientific Information .............................................................................................. 48
- 13. PHARMACEUTICAL INFORMATION .......................................................................... 48
- 14.
Clinical Trials ........................................................................................................... 48
14.1. Clinical Trials by Indication .............................................................................. 48
First-line Treatment of NSCLC with EGFR Exon 19 Deletion or Exon 21 L858R Substitution Mutation ...................................................................................................... 48
Previously Treated NSCLC with EGFR Exon 19 Deletions or Exon 21 L858R Substitution Mutations ......................................................................................................................... 53
First-line Treatment of NSCLC with EGFR Exon 20 Insertion Mutations ......................... 56
Previously Treated NSCLC with EGFR Exon 20 insertion mutations ................................ 59
- 15. Microbiology ........................................................................................................... 61
- 16. Non-Clinical Toxicology ........................................................................................... 61
Patient Medication Information ......................................................................................... 63
Part 1: Healthcare Professional Information
1. Indications
RYBREVANT® (amivantamab for injection) is indicated:
- in combination with lazertinib for the first-line treatment of adult patients with locally advanced (not amenable to curative therapy) or metastatic non-small cell lung cancer (NSCLC) with epidermal growth factor receptor (EGFR) Exon 19 deletions or Exon 21 L858R substitution mutations.
- in combination with carboplatin and pemetrexed for the treatment of adult patients with locally advanced (not amenable to curative therapy) or metastatic non-small cell lung cancer (NSCLC) with epidermal-growth factor receptor (EGFR) Exon 19 deletions or Exon 21 L858R substitution mutations, whose disease has progressed on or after treatment with osimertinib.
- in combination with carboplatin and pemetrexed for the first-line treatment of adult patients with locally advanced (not amenable to curative therapy) or metastatic NSCLC with activating EGFR Exon 20 insertion mutations.
as monotherapy for the treatment of adult patients with locally advanced or metastatic NSCLC with activating EGFR Exon 20 insertion mutations whose disease has progressed on or after platinum-based chemotherapy.
Clinical effectiveness of RYBREVANT monotherapy is based on overall response rate (ORR) and duration of response (DOR) from a single-arm trial in patients with activating epidermal-growth factor receptor (EGFR) Exon 20 insertion mutations.
1.1. Pediatrics
- Based on the data submitted and reviewed by Health Canada, the safety and efficacy of RYBREVANT in pediatric patients (<18 years of age) has not been established; therefore, Health Canada has not authorized an indication for pediatric use.
1.2. Geriatrics
- No clinically relevant differences in effectiveness were observed between elderly patients (≥65 years of age) and younger patients when treated with RYBREVANT as a monotherapy or in combination with carboplatin and pemetrexed. Evidence from the clinical studies suggests that the use in the geriatric population is associated with differences in safety (see 7.1.4. Geriatrics).
- Evidence from clinical studies suggests that use of RYBREVANT in combination with lazertinib in the geriatric population is associated with differences in safety. Differences were seen in subgroup analyses for efficacy in geriatrics patients; however no formal statistical testing of efficacy was planned for subgroup analyses by age and interpretation of these differences is non-conclusive (see 7.1.4. Geriatrics, 14.1. Clinical Trials by Indication, and 10.3. Pharmacokinetics).
2. Contraindications
RYBREVANT is contraindicated in:
- Patients who are hypersensitive to this drug or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see 6. Dosage Forms, Strengths, Composition, and Packaging.
4. Dosage and Administration
4.1. Dosing Considerations
- RYBREVANT should be administered by a healthcare professional with appropriate medical support to manage infusion related reactions (IRRs) if they occur (see 7. Warnings and Precautions).
- When considering the use of RYBREVANT, before treatment initiation the presence of an EGFR Exon 19 deletion, Exon 21 L858R substitution, or Exon 20 insertion mutation is required to be determined using a validated test (see 14. Clinical Trials).
- Administer pre-infusion medications (see 4.2. Recommended Dose and Dosage Adjustment, Table 4).
- Administer RYBREVANT via peripheral line for all Cycle 1 doses to reduce the risk of infusion related reactions (see 4.4. Administration).
- Administer diluted RYBREVANT intravenously according to the infusion rates in Table 1 and Table 3, with the initial dose as a split infusion in Week 1 on Day 1 and Day 2.
4.2. Recommended Dose and Dosage Adjustment
It is recommended that patients are treated with RYBREVANT until disease progression or unacceptable toxicity (see 4.4. Administration). Pre-medications should be administered before each RYBREVANT infusion as recommended (see Recommended Pre-infusion medications and Table 4).
RYBREVANT in combination with carboplatin and pemetrexed
The recommended dosage of RYBREVANT, when used in combination with carboplatin and pemetrexed is provided in Table 1 (see infusion rates in Table 7).
When used in combination with carboplatin and pemetrexed, RYBREVANT should be administered after carboplatin and pemetrexed in the following order: pemetrexed, carboplatin and then RYBREVANT (see Table 2).
Table 1: Recommended Dose and Dosing Schedule for RYBREVANT when in combination with carboplatin and pemetrexed
Body weight at Baselinea | Recommended Dose | Schedule | Number of 350 mg/7 mL RYBREVANT Vials/dose | |||
|---|---|---|---|---|---|---|
| Less than 80 kg | 1400 mg | Weekly (total of 4 doses) from Weeks 1 to 4
| 4 | |||
| 1750 mg | Every 3 weeks starting at Week 7 onwards | 5 | ||||
| Greater than or equal to 80 kg | 1750 mg | Weekly (total of 4 doses) for Weeks 1 to 4
| 5 | |||
| 2100 mg | Every 3 weeks starting at Week 7 onwards | 6 | ||||
| a Dose adjustments not required for subsequent body weight changes. | ||||||
Table 2: Recommended order of administration and regimen for RYBREVANT in combination with carboplatin and pemetrexed
| RYBREVANT in Combination with Carboplatin and Pemetrexed | ||
|---|---|---|
| Administer the regimen in the following order: pemetrexed first, carboplatin second and RYBREVANT last. | ||
| Drug | Dose | Duration/Timing of Treatment |
| Pemetrexed | Pemetrexed 500 mg/m2 intravenously Refer to the pemetrexed Product Monograph for complete information. | Every 3 weeks, continue until disease progression or unacceptable toxicity. |
| Carboplatin | Carboplatin AUC 5 intravenously Refer to the carboplatin Product Monograph for complete information. | Every 3 weeks for up to 12 weeks. |
| RYBREVANT | RYBREVANT intravenously See Table 1. | Every 3 weeks, continue until disease progression or unacceptable toxicity. |
RYBREVANT monotherapy or in combination with lazertinib
The recommended dosage of RYBREVANT monotherapy or in combination with lazertinib is provided in Table 3 (see infusion rates in Table 8).
The recommended dosage of lazertinib is 240 mg once daily, taken orally in combination with RYBREVANT. When used in combination with lazertinib, RYBREVANT should be administered anytime after lazertinib when given on the same day. For recommended dosing and administration instructions for lazertinib consult the lazertinib Product Monograph.
Table 3: Recommended Dose and Dosing Schedule for RYBREVANT monotherapy or in combination with lazertinib
Body weight at Baselinea | Recommended Dose | Dosing Schedule | Number of 350 mg/7 mL RYBREVANT Vials/dose | |||
|---|---|---|---|---|---|---|
| Less than 80 kg | 1050 mg | Weekly (total of 4 doses) from Weeks 1 to 4
| 3 | |||
| Every 2 weeks starting at Week 5 onwards | ||||||
| Greater than or equal to 80 kg | 1400 mg | Weekly (total of 4 doses) from Weeks 1 to 4
| 4 | |||
| Every 2 weeks starting at Week 5 onwards | ||||||
a Dose adjustments not required for subsequent body weight changes.
Recommended Pre-infusion medications
Two days before the first (initial) infusion only:
Oral dexamethasone or equivalent
Starting two days prior to the initial RYBREVANT infusion, patients should receive 8 mg dexamethasone orally, twice daily (total 16 mg per day). On the day of the initial infusion (Week 1, Day 1), patients should receive 8 mg dexamethasone orally, one hour prior to infusion in addition to intravenous dexamethasone to further reduce the risk of IRR.
Day of initial and subsequent infusions:
Prior to the initial infusion of RYBREVANT (Week 1, Days 1 and 2), administer pre-infusion medications as required and described in Table 4 to reduce the risk of IRRs. For subsequent infusions, administer both antihistamines and antipyretics prior to all infusions, and glucocorticoids as necessary. Administer antiemetics as needed. After prolonged dose interruptions of RYBREVANT, restart the premedications upon reinitiation of treatment: intravenous dexamethasone, diphenhydramine, and acetaminophen (see Table 4).
Table 4: Pre-Medications
| Medication | Dose | Route of Administration | Dosing Window Prior to RYBREVANT Administration |
|---|---|---|---|
| Medication | Dose | Route of Administration | Dosing Window Prior to RYBREVANT Administration |
| Antihistamine* | Diphenhydramine (25 to 50 mg) or equivalent | IV | 15 to 30 minutes |
| Oral | 30 to 60 minutes | ||
| Antipyretic* | Acetaminophen (650 to 1,000 mg) | IV | 15 to 30 minutes |
| Oral | 30 to 60 minutes | ||
| Glucocorticoid‡ | Dexamethasone (20 mg) or equivalent | IV | 60 to 120 minutes |
| Glucocorticoid+ | Dexamethasone (10 mg) or equivalent | IV | 45 to 60 minutes |
* Required at all doses.
‡ Required at initial dose (Week 1, Day 1)
+ Required at second dose (Week 1, Day 2); optional for subsequent doses
Dose Modifications
The recommended RYBREVANT dose reductions for adverse reactions (see Table 6) are outlined in Table 5.
Table 5: RYBREVANT Dose Reductions for Adverse Reactions
| Dose* | 1st Dose Reduction | 2nd Dose Reduction | 3rd Dose Modification |
|---|---|---|---|
| 1050 mg | 700 mg | 350 mg | Discontinue RYBREVANT |
| 1400 mg | 1050 mg | 700 mg | |
| 1750 mg | 1400 mg | 1050 mg | |
| 2100 mg | 1750 mg | 1400 mg | |
* Dose at which the adverse reaction occurred
Table 6: Recommended Dose Modifications for Adverse Reactions following administration of RYBREVANT
| Adverse Reaction | Severity | Dose Modification |
|---|---|---|
| Adverse Reaction | Severity | Dose Modification |
| Adverse Reaction | Severity | Dose Modification |
| Infusion Related Reactions (IRRs) (see 7. Warnings and Precautions, Immune) | Grade 1 to 3 |
|
| Recurrent Grade 3 or any Grade 4 | Permanently discontinue RYBREVANT | |
| Interstitial Lung Disease (ILD) / Pneumonitis (see 7. Warnings and Precautions, Respiratory) | Suspected ILD/ pneumonitis (any Grade) | Withhold RYBREVANT |
| Confirmed ILD/ pneumonitis (any Grade) | Permanently discontinue RYBREVANT | |
| Venous Thromboembolic (VTE) Events (applies to the combination with lazertinib, see 7. Warnings and Precautions, Cardiovascular) | Grade 2 or 3 |
|
| Grade 4 or recurrent Grade 2 or 3 despite therapeutic level of anticoagulation |
| |
| Skin and Nail Reactions (see 7. Warnings and Precautions, Skin) | Grade 1 |
|
| Grade 2 |
| |
| Grade 3 |
| |
| Grade 4, and severe bullous, blistering, or exfoliating skin conditions, | Permanently discontinue RYBREVANT | |
| including toxic epidermal necrolysis (TEN) | ||
| Other Adverse Reactions (see 8. Adverse Reactions) | Grade 3 |
|
| Grade 4 |
| |
Recommended Dose Modifications for Adverse Reactions for RYBREVANT in Combination with Carboplatin and Pemetrexed or in Combination with Lazertinib
When administering RYBREVANT in combination with carboplatin and pemetrexed, or in combination with lazertinib, follow the recommended dose modifications for adverse reactions for RYBREVANT as shown in Table 6. Refer to the Product Monographs for carboplatin, pemetrexed, and lazertinib for their dosage modification recommendations.
Renal impairment
No formal studies of RYBREVANT in patients with renal impairment have been conducted. Based on population pharmacokinetic (PK) analyses, no dosage adjustment is necessary for patients with mild (60 ≤ creatinine clearance [CrCl] < 90 mL/min) or moderate (29 ≤ CrCl < 60 mL/min) renal impairment. Data in patients with severe renal impairment are limited. No data are available in patients with end stage renal disease (15 ≤ CrCl < 29 mL/min) (see 10.3. Pharmacokinetics).
Hepatic impairment
No formal studies of RYBREVANT in patients with hepatic impairment have been conducted. Based on population PK analyses, no dosage adjustment is necessary for patients with mild hepatic impairment [(total bilirubin ≤ ULN and AST > ULN) or (ULN < total bilirubin ≤ 1.5 x ULN)]. Data in patients with moderate hepatic impairment are limited (1.5 x ULN < total bilirubin ≤ 3 x ULN and any AST)). No data are available in patients with severe hepatic impairment (total bilirubin >3 x ULN) (see 10.3. Pharmacokinetics).
Pediatrics (<18 years)
The safety and efficacy of RYBREVANT have not been established in pediatric patients.
Geriatrics (≥65 years)
No dose adjustment of RYBREVANT is required in patients aged 65 years or older (see 7.1.4. Geriatrics and 10.3. Pharmacokinetics).
4.3. Reconstitution
Parenteral Products: Dilution
RYBREVANT solution must be diluted and prepared for intravenous infusion by a healthcare professional using aseptic technique.
- Determine the dose required and number of RYBREVANT vials needed based on patient’s baseline weight (see 4.2. Recommended Dose and Dosage Adjustment). Each vial of RYBREVANT contains 350 mg of amivantamab.
- Check that the RYBREVANT solution is colorless to pale yellow. Do not use if discoloration or visible particles are present.
- Withdraw and then discard a volume of either 5% dextrose [glucose] solution USP or 0.9% sodium chloride solution USP from the 250 mL infusion bag equal to the volume of RYBREVANT to be added (i.e., discard 7 mL diluent from the infusion bag for each RYBREVANT vial). Infusion bags must be made of polyvinylchloride (PVC), polypropylene (PP), polyethylene (PE), or polyolefin blend (PP+PE).
- Withdraw 7 mL of RYBREVANT from each vial and add it to the infusion bag. The final volume in the infusion bag should be 250 mL. Each vial contains a 0.5 mL overfill to ensure sufficient extractable volume. Discard any unused portion left in the vial.
- Gently invert the bag to mix the solution. Do not shake.
- Visually inspect the diluted solution before administration. Do not use if discoloration or visible particles are observed.
- Diluted solutions should be administered within 10 hours (including infusion time of 2-5 hours, Table 7 and Table 8) at room temperature (15°C to 25°C) and in room light (see 11. Storage, Stability, and Disposal).
4.4. Administration
- Due to the frequency of infusion related reactions (IRRs; see 7. Warnings and Precautions) at the first dose, RYBREVANT must be infused via a peripheral line for all Cycle 1 doses (Week 1 to Week 4) to minimize drug exposure in the event of an IRR. If peripheral access is limiting, earlier use of a central line in Cycle 1 starting after Cycle 1 Day 8 may be considered if deemed medically acceptable.
- RYBREVANT via a central line may be considered for subsequent weeks.
- For the first dose, RYBREVANT should be diluted as close to administration as possible to allow for maximal flexibility for infusion time and allow for IRR management.
- Prior to administration, prime the infusion set with the diluent (either 5% dextrose solution or 0.9% sodium chloride solution).
- Administer the diluted solution by intravenous infusion using an infusion set fitted with a flow regulator and with an in-line, sterile, non-pyrogenic, low protein-binding polyethersulfone (PES) filter (pore size 0.2 micrometer), primed with diluent only. Administration sets must be made of either polyurethane (PU), polybutadiene (PBD), PVC, PP, or PE.
- Do not infuse RYBREVANT concomitantly in the same intravenous line with other agents.
- This medicinal product is for single use only. Any unused medicinal product should be disposed of in accordance with local requirements.
RYBREVANT in combination with carboplatin and pemetrexed
- Administer RYBREVANT, when used in combination with carboplatin and pemetrexed, intravenously at the recommended dose as per Table 1 and according to the infusion rates in Table 7.
- When used in combination with carboplatin and pemetrexed, RYBREVANT is administered weekly for the first four weeks. Patients do not receive RYBREVANT treatment in Week 5 or 6. RYBREVANT is administered at Week 7 and every 3 weeks thereafter.
- Administer treatment in the following order: pemetrexed infusion first, carboplatin infusion second, and the RYBREVANT infusion last according to Table 2.
Table 7: Infusion Rates for RYBREVANT when in combination with carboplatin and pemetrexed
| Body Weight Less than 80 kg | |||
|---|---|---|---|
| Body Weight Less than 80 kg | |||
| Week | Dose (per 250 mL bag) | Initial Infusion Rate | Subsequent Infusion Rate† |
| Week | Dose (per 250 mL bag) | Initial Infusion Rate | Subsequent Infusion Rate† |
| Week 1 (split dose infusion) | |||
| Week 1 Cycle 1 Day 1 | 350 mg | 50 mL/hr | 75 mL/hr |
| Week 1 Cycle 1 Day 2 | 1050 mg | 33 mL/hr | 50 mL/hr |
| Week 2 Cycle 1 Day 8 | 1400 mg | 65 mL/hr | |
| Week 3 Cycle 1 Day 15 | 1400 mg | 85 mL/hr | |
| Week 4 Cycle 2 Day 1 | 1400 mg | 125 mL/hr | |
| Week 5 and 6 | No dose | ||
| Week 7 Cycle 3 Day 1 and Subsequent weeks* | 1750 mg | 125 mL/hr | |
| Body Weight Greater Than or Equal to 80 kg | |||
| Week | Dose (per 250 mL bag) | Initial Infusion Rate | Subsequent Infusion Rate† |
| Week 1 (split dose infusion) | |||
| Week 1 Cycle 1 Day 1 | 350 mg | 50 mL/hr | 75 mL/hr |
| Week 1 Cycle 1 Day 2 | 1400 mg | 25 mL/hr | 50 mL/hr |
| Week 2 Cycle 1 Day 8 | 1750 mg | 65 mL/hr | |
| Week 3 Cycle 1 Day 15 | 1750 mg | 85 mL/hr | |
| Week 4 Cycle 2 Day 1 | 1750 mg | 125 mL/hr | |
| Week 5 and 6 | No dose | ||
| Week 7 Cycle 3 Day 1 and Subsequent weeks* | 2100 mg | 125 mL/hr | |
* Starting at Week 7 (start of Cycle 3), patients are dosed every 3 weeks. † Increase the initial infusion rate to the subsequent infusion rate after 2 hours in the absence of infusion related reactions. | |||
RYBREVANT monotherapy or in combination with lazertinib
- Administer RYBREVANT as a monotherapy or in combination with lazertinib at the recommended dose as per Table 3 and according to the infusion rates in Table 8.
- As a monotherapy or in combination with lazertinib, RYBREVANT is administered weekly for the first four weeks. RYBREVANT is then administered at Week 5 and every 2 weeks thereafter.
Table 8: Infusion Rates for RYBREVANT monotherapy or in combination with lazertinib
| Body Weight Less Than 80 kg | |||
|---|---|---|---|
| Body Weight Less Than 80 kg | |||
| Week | Dose (per 250 mL bag) | Initial Infusion Rate | Subsequent Infusion Rate† |
| Week | Dose (per 250 mL bag) | Initial Infusion Rate | Subsequent Infusion Rate† |
| Week 1 (split dose infusion) | |||
| Week 1 Cycle 1 Day 1 | 350 mg | 50 mL/hr | 75 mL/hr |
| Week 1 Cycle 1 Day 2 | 700 mg | 50 mL/hr | 75 mL/hr |
| Week 2 Cycle 1 Day 8 | 1050 mg | 85 mL/hr | |
| Week 3 Cycle 1 Day 15 | 1050 mg | 125 mL/hr | |
| Week 4 Cycle 1 Day 22 | 1050 mg | 125 mL/hr | |
| Week 5 Cycle 2 Day 1 and subsequent weeks/cycles* | 1050 mg | 125 mL/hr | |
| Body Weight Greater Than or Equal to 80 kg | |||
| Week | Dose (per 250 mL bag) | Initial Infusion Rate | Subsequent Infusion Rate† |
| Week 1 (split dose infusion) | |||
| Week 1 Day 1 Cycle 1 Day 1 | 350 mg | 50 mL/hr | 75 mL/hr |
| Week 1 Day 2 Cycle 1 Day 2 | 1050 mg | 35 mL/hr | 50 mL/hr |
| Week 2 Cycle 1 Day 8 | 1400 mg | 65 mL/hr | |
| Week 3 Cycle 1 Day 15 | 1400 mg | 85 mL/hr | |
| Week 4 Cycle 1 Day 22 | 1400 mg | 125 mL/hr | |
| Week 5 Cycle 2 Day 1 and subsequent weeks/cycles* | 1400 mg | 125 mL/hr | |
* Starting at week 5 (start of Cycle 2), patients are dosed every 2 weeks. † Increase the initial infusion rate to the subsequent infusion rate after 2 hours in the absence of infusion related reactions. | |||
4.5. Missed Dose
If a planned dose of RYBREVANT is missed, the dose should be administered as soon as possible and the dosing schedule should be adjusted accordingly, maintaining the treatment interval.
5. Overdose
There is no information on overdosage with RYBREVANT. There is no known specific antidote for RYBREVANT overdose. In the event of an overdose, stop RYBREVANT, monitor patient for any signs or symptom of adverse reactions and undertake general supportive measures until clinical toxicity has diminished or resolved.
| For the most recent information in the management of a suspected drug overdose, contact your regional poison control centre or Health Canada’s toll-free number, 1-844 POISON-X (1 844-764-7669). |
|---|
- 6. Dosage Forms, Strengths, Composition, and Packaging
To help ensure the traceability of biologic products, healthcare professionals should record both the brand name and the non-proprietary (active ingredient) name as well as other product-specific identifiers such as the Drug Identification Number (DIN) and the batch/lot number of the product supplied.
Table 9: Dosage Forms, Strengths, and Composition
RYBREVANT is available as a colourless to pale yellow preservative-free liquid concentrate for intravenous infusion after dilution.
Each single-use vial contains 350 mg of amivantamab per 7 mL (or 50 mg of amivantamab per mL). Each vial is individually packaged in a carton.
7. Warnings and Precautions
Carcinogenesis and Genotoxicity
No animal studies have been performed to evaluate the carcinogenic or mutagenic potential of amivantamab (see 16. Non-Clinical Toxicology).
Cardiovascular
Left Ventricular Dysfunction and Cardiomyopathy
In patients treated with RYBREVANT in combination with lazertinib, left ventricular ejection fraction (LVEF) reductions (>10 percentage points and a drop below lower limit of normal) and cardiomyopathy events (defined as cardiac failure, chronic cardiac failure, congestive cardiac failure, pulmonary edema, ejection fraction decreased, left ventricular dysfunction) have been reported. Refer to the lazertinib product monograph (see 7 Warnings and Precautions, Monitoring and Laboratory Tests and 8.2 Clinical Trial Adverse Reactions, Select Adverse Reactions).
| Route of Administration | Dosage Form/ Strength/Composition | Non-Medicinal Ingredients |
| Intravenous (IV) infusion | Liquid concentrate for IV infusion 350mg/7mL | EDTA disodium salt dihydrate, L-Histidine, L-Histidine hydrochloride monohydrate, L--Methionine, Polysorbate 80, Sucrose, Water for Injection |
Venous Thromboembolic (VTE) Events
In patients treated with RYBREVANT in combination with lazertinib, venous thromboembolic (VTE) events, including deep venous thrombosis (DVT) and pulmonary embolism (PE), including fatal events were reported. VTE events occurred predominantly in the first four months of therapy (see 8. Adverse Reactions and 8.2 Clinical Trial Adverse Reactions, Select Adverse Reactions).
Prophylactic anticoagulation is recommended to be used for the first four months of treatment to prevent VTE. Prophylactic anticoagulation beyond 4 months may be considered based on individual patient risk factors. Use of anticoagulants should align with clinical guidelines; use of Vitamin K antagonists is not recommended.
Monitor for signs and symptoms of VTE events. Treat patients with VTE events with anticoagulants as clinically indicated (see 4.2. Recommended Dose and Dosage Adjustment).
For patients with Grade 4 or recurrent Grade 2 or 3 VTE events despite therapeutic levels of anticoagulation, permanently discontinue RYBREVANT and withhold lazertinib. Administer anticoagulation treatment as clinically indicated. Once anticoagulation treatment has been initiated, treatment can continue with lazertinib at the same dose level at the discretion of the healthcare professional (see 4.2. Recommended Dose and Dosage Adjustment).
Driving and Operating Machinery
No studies on the effects on the ability to drive and use machines have been performed. Exercise caution when driving or operating a vehicle or potentially dangerous machinery.
If patients experience treatment-related symptoms affecting their ability to concentrate and react, it is recommended that they do not drive or use machines until the effect subsides.
Immune
Infusion related reactions may occur in patients treated with RYBREVANT. The most frequent signs and symptoms include chills, nausea, dyspnea, flushing, chest discomfort, hypotension, and vomiting (see 8. Adverse Reactions and 8.2. Clinical Trial Adverse Reactions, Select Adverse Reactions). Most infusion related reactions occur within a median time of 1 hr.
To reduce the risk of infusion related reactions, administer pre-infusion oral dexamethasone starting 2 days prior to the initial infusion followed by the recommended pre-infusion medications to be administered on the day of initial infusion (Table 4) (see 4. Dosage and Administration, Pre-infusion medications). The addition of oral dexamethasone demonstrated a reduction in incidence and severity of IRRs on the day of the initial infusion.
Prior to initial infusion (Week 1) of RYBREVANT, administer antihistamines, antipyretics, and glucocorticoids to reduce the risk of IRRs. For subsequent doses, administer antihistamines and antipyretics. Administer the initial infusion of RYBREVANT in split doses on Week 1, Day 1, and Day 2. Administer RYBREVANT via a peripheral line for all Cycle 1 doses (Week 1 to Week 4) (see 4. Dosage and Administration).
Treat patients with RYBREVANT in a setting with appropriate medical support necessary to treat IRRs. Interrupt RYBREVANT infusion at the first sign of IRRs and institute post-infusion medication as clinically indicated. Upon resolution of symptoms, resume the infusion at 50% of the previous rate. For recurrent Grade 3 or 4 IRRs, permanently discontinue RYBREVANT (see 4. Dosage and Administration).
Monitoring and Laboratory Tests
Prior to initiating therapy with RYBREVANT in combination with lazertinib, electrolyte levels (calcium, potassium, and magnesium) should be assessed. Refer to the lazertinib product monograph.
For patients with cardiac risk factors and those with conditions that can affect left ventricular ejection fraction (LVEF), refer to the lazertinib product monograph.
Ophthalmologic
Eye disorders may occur in patients treated with RYBREVANT. These include keratitis, dry eye, blurred vision, eye pruritus, visual impairment, lacrimation increased, ocular hyperemia, eyelid ptosis, aberrant eyelash growth, conjunctival hyperemia, blepharitis and uveitis (see 8. Adverse Reactions and 8.2 Clinical Trial Adverse Reactions, Select Adverse Reactions).
Refer patients presenting with worsening eye symptoms promptly to an ophthalmologist and advise discontinuation of contact lenses until symptoms are evaluated. Withhold, dose reduce or permanently discontinue RYBREVANT based on severity (see 4.2 Recommended Dose and Dosage Adjustment).
Reproductive Health
Due to the risk that RYBREVANT can cause fetal harm when administered to pregnant women, advise female patients of reproductive potential to use effective contraception during treatment and for 3 months after the last dose of RYBREVANT (see 7.1.1. Pregnancy). Male patients must use effective contraception (e.g., condom) and not donate or store semen during treatment and for 3 months after the last dose of RYBREVANT.
Fertility
No data are available to determine potential effects of RYBREVANT on fertility in males or females (see 7.1.1. Pregnancy).
Respiratory
Interstitial lung disease (ILD)/pneumonitis, including fatal events, may occur in patients treated with RYBREVANT (see 8. Adverse Reactions and 8.2. Clinical Trial Adverse Reactions, Select Adverse Reactions).
Patients with a medical history of ILD, drug-induced ILD, radiation pneumonitis that required steroid treatment, or any evidence of clinically active ILD were excluded from the clinical studies.
Monitor patients for symptoms indicative of ILD/pneumonitis (e.g., dyspnea, cough, fever). If symptoms develop, interrupt treatment with RYBREVANT pending investigation of these symptoms. Evaluate suspected ILD and initiate appropriate treatment as necessary. Discontinue RYBREVANT in patients with confirmed ILD (see 4. Dosage and Administration).
Skin
Skin and nail reactions may occur in patients treated with RYBREVANT.
This includes severe rash, dermatitis acneiform, palmar-plantar erythrodysesthesia, pruritus, dry skin and paronychia. Toxic epidermal necrolysis (TEN) has occurred with RYBREVANT treatment (see 8. Adverse Reactions and 8.2. Clinical Trial Adverse Reactions, Select Adverse Reactions)
When initiating treatment with RYBREVANT, consider prophylactic therapy to reduce the risk and severity of skin and nail reactions. This includes administration of an oral antibiotic (doxycycline or minocycline, 100 mg twice daily) starting on Day 1 for the first 12 weeks of treatment. After completion of oral antibiotic therapy, application of a topical antibiotic lotion to the scalp (clindamycin 1% once daily), should be used for the next 9 months of RYBREVANT treatment. Recommend a non-comedogenic skin moisturizer (ceramide based or other formulations that provide long-lasting skin hydration and exclude drying agents are preferred) on the face and whole body (except scalp) and 4% chlorhexidine solution to wash hands and feet, while on treatment. Instruct patients to limit sun exposure during and for 2 months after RYBREVANT therapy. Protective clothing and use of broad-spectrum UVA/UVB sunscreen are advisable. The prophylactic regimen demonstrated a reduction in dermatologic adverse events (Grade 2 and higher) compared to standard dermatologic management used in clinical practice.
If skin or nail reactions develop, administer supportive care, start topical corticosteroids and topical and/or oral antibiotics. For Grade 3 or poorly-tolerated Grade 2 events, add systemic antibiotics and oral steroids and consider dermatologic consultation. For Grade 4 skin reactions, permanently discontinue RYBREVANT. Promptly refer patients presenting with severe rash, atypical appearance or distribution, or lack of improvement within 2 weeks to a dermatologist. Withhold, dose reduce or permanently discontinue RYBREVANT based on severity (see 4. Dosage and Administration).
7.1. Special Populations
7.1.1. Pregnancy
There are no human or animal data to assess the risk of RYBREVANT in pregnancy. Administration of other EGFR and MET inhibitor molecules to pregnant animals has resulted in an increased incidence of impairment of embryo-fetal development, embryolethality, and abortion. Therefore, based on its mechanism of action and findings in animal models, RYBREVANT could cause fetal harm when administered to a pregnant woman.
RYBREVANT should not be used during pregnancy unless the benefit of treatment to the woman is considered to outweigh potential risks to the fetus. If the patient becomes pregnant while taking this drug, the patient should be informed of the potential risk to the fetus.
7.1.2. Breastfeeding
No studies have been conducted to determine if RYBREVANT is excreted in human or animal milk or affects milk production. RYBREVANT is a fully human, Immunoglobulin G1 (IgG1) based bispecific antibody. In general, human IgGs are known to be excreted in breast milk during the first few days after birth, which decreases to lower concentrations soon afterwards. Because of the potential for serious adverse reactions from RYBREVANT in breastfed infants, advise women not to breastfeed during treatment with RYBREVANT and for 3 months following the last dose of RYBREVANT.
7.1.3. Pediatrics
The efficacy and safety of RYBREVANT in pediatric patients has not been established; therefore, Health Canada has not authorized an indication for pediatric use.
7.1.4. Geriatrics
There are limited clinical data on the combination of RYBREVANT with lazertinib in patients 75 years or over. In MARIPOSA, older patients (≥65 years of age) reported more Grade 4 and Grade 5 adverse reactions compared to patients <65 years of age (21% vs. 7%). The incidence of serious adverse reactions was 62% in patients ≥65 years of age and 38% in patients <65 years of age. While the rates of drug interruptions and dose reductions were similar, the rate of adverse reactions leading to any treatment discontinuation was higher in patients ≥65 years of age compared to patients <65 years of age (47% vs. 25%).
Of the 281 patients treated with RYBREVANT in PAPILLON and MARIPOSA-2, 38% were 65 years of age or older, and 9% were 75 years of age or older. No clinically relevant differences in effectiveness were observed based on age. Adverse events that led to discontinuation of any study agent were reported for 13.8% of patients under 65 years old and 33.6% of patients aged 65 years or older.
Of the 302 patients treated with RYBREVANT in CHRYSALIS (EDI1001), 39.4% were 65 years of age or older, and 11.3% were 75 years of age or older. No clinically relevant differences in effectiveness were observed based on age. There was a higher incidence of serious adverse events observed in patients aged 65 years or older (39.5%) as compared to younger patients (25.1%). There was also a higher incidence of adverse events leading to dose interruptions observed in patients aged 65 years or older (44.5%) as compared to younger patients (28.4%).
8. Adverse Reactions
8.1. Adverse Reaction Overview
The following adverse reactions observed with RYBREVANT when used in combination with lazertinib or in combination with carboplatin and pemetrexed or when RYBREVANT is used alone as a monotherapy are discussed in the Warnings and Precautions section (7. Warnings and Precautions and 8.2. Clinical Trial Adverse Reactions, Select Adverse Reactions):
- Left Ventricular Dysfunction and Cardiomyopathy and Venous Thromboembolic Events (see 7. Warnings and Precautions, Cardiovascular and 8.2. Clinical Trial Adverse Reactions, Select Adverse Reactions)
- Infusion Related Reactions (see 7. Warnings and Precautions, Immune and 8.2. Clinical Trial Adverse Reactions, Select Adverse Reactions)
- Eye Disorders (see 7. Warnings and Precautions, Ophthalmologic and 8.2. Clinical Trial Adverse Reactions, Select Adverse Reactions)
- Interstitial Lung Disease (ILD)/Pneumonitis (see 7. Warnings and Precautions, Respiratory and 8.2. Clinical Trial Adverse Reactions, Select Adverse Reactions)
- Skin and Nail Reactions (see 7. Warnings and Precautions, Skin and 8.2. Clinical Trial Adverse Reactions, Select Adverse Reactions)
RYBREVANT in Combination with Lazertinib
First-line Treatment of NSCLC with EGFR Exon 19 Deletion or Exon 21 L858R Substitution Mutation
The safety of RYBREVANT in combination with lazertinib described in the Adverse Reactions section reflects the exposure of 421 patients enrolled in the MARIPOSA study. The most common adverse reactions (≥20%) of patients who received RYBREVANT in combination with lazertinib were paronychia, infusion related reaction (amivantamab-specific), rash, hypoalbuminemia (amivantamab-specific), alanine aminotransferase increased, edema peripheral, constipation, diarrhea, dermatitis acneiform, stomatitis, aspartate aminotransferase increased, COVID-19, decreased appetite, pruritus, anemia, nausea, and hypocalcemia. The most common Grade 3 to 4 laboratory abnormalities (≥2%) were decreased albumin, increased alanine aminotransferase, decreased sodium, decreased potassium, decreased hemoglobin, increased aspartate aminotransferase, increased magnesium, and increased gamma-glutamyltransferase.
RYBREVANT in Combination with Carboplatin and Pemetrexed
The pooled safety population described in the Adverse Reactions section also reflects exposure to RYBREVANT in combination with carboplatin and pemetrexed in 281 patients in two studies:
- MARIPOSA-2 (NSC3002) in 130 patients
- PAPILLON (NSC3001) in 151 patients
Among 281 patients who received RYBREVANT in combination with carboplatin and pemetrexed, 65% were exposed for 6 months or longer and 24% were exposed for greater than one year.
Two hundred and eighty-one patients were exposed to RYBREVANT with carboplatin and pemetrexed in PAPILLON (N=151) and MARIPOSA-2 (N=130) for a median duration of 7.75 months (range 0 to 26.9 months) and to carboplatin and pemetrexed (N=398) for a median duration of 4.86 (range 0 to 25.3 months).
The most common adverse reactions (≥20%) were rash, neutropenia, infusion related reactions, paronychia, fatigue, anemia, nausea, thrombocytopenia, stomatitis, constipation, edema, decreased appetite, leukopenia, hypoalbuminemia, alanine aminotransferase increased, aspartate aminotransferase increased, and vomiting.
The most common grade 3 to grade 4 laboratory abnormalities (≥2%) were decreased neutrophil count, decreased white blood cell count, decreased lymphocyte count, decreased platelet count, decreased hemoglobin, decreased potassium, decreased sodium, decreased albumin, increased alanine aminotransferase, and increased gamma glutamyl transferase.
RYBREVANT as a Monotherapy
Previously Treated NSCLC with EGFR Exon 20 Insertion Mutations (CHRYSALIS Study)
The safety of RYBREVANT described in the Adverse Reactions section reflects the exposure of 129 patients enrolled in the CHRYSALIS study. The most common adverse reactions (≥20%) were dermatitis acneiform, rash, infusion related reactions (IRRs), nausea, paronychia, fatigue, hypoalbuminemia, constipation, stomatitis, peripheral edema, and alanine aminotransferase increased. The most common Grade 3 to 4 laboratory abnormalities (≥2%) were decreased albumin, decreased phosphates, decreased potassium, increased alkaline phosphatase, increased glucose, increased gamma-glutamyltransferase, decreased sodium, increased alanine aminotransferase, decreases in lymphocytes, neutrophils, hemoglobin, and white blood cells.
8.2. Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. Therefore, the frequencies of adverse reactions observed in the clinical trials may not reflect frequencies observed in clinical practice and should not be compared to frequencies reported in clinical trials of another drug.
First-line Treatment of NSCLC with EGFR Exon 19 Deletion or Exon 21 L858R Substitution Mutation
The safety data described below reflect exposure to RYBREVANT in combination with lazertinib in 421 treatment-naïve patients with locally advanced or metastatic NSCLC whose tumors have EGFR exon 19 deletion or exon 21 L858R substitution mutation in the MARIPOSA study. Patients in MARIPOSA received lazertinib 240 mg orally once daily and RYBREVANT intravenously at 1,050 mg (for patients <80 kg) or 1,400 mg (for patients ≥80 kg) once weekly for 4 weeks, then every 2 weeks thereafter starting at week 5. Patients in the osimertinib arm received 80 mg osimertinib once daily.
The median treatment duration was 18.5 months (range 0.2 to 31.4 months) for the RYBREVANT + lazertinib arm and the median treatment duration was 18.0 months (range: 0.2 to 32.7 months) for the osimertinib arm. Among the 421 patients who received RYBREVANT in combination with lazertinib, 72.9% were exposed to RYBREVANT for ≥ 6 months and 59.1% were exposed to RYBREVANT for >1 year. For details on the study population, see 14. Clinical Trials by Indication.
The adverse reactions reported in ≥20% of patients who received RYBREVANT in combination with lazertinib were paronychia, infusion related reaction (amivantamab-specific), rash, hypoalbuminemia (amivantamab-specific), alanine aminotransferase increased, edema peripheral, constipation, diarrhea, dermatitis acneiform, stomatitis, aspartate aminotransferase increased, COVID-19, decreased appetite, pruritus, anemia, nausea, and hypocalcemia.
Dose interruptions of RYBREVANT in combination with lazertinib due to an adverse reaction occurred in 81% of patients. Adverse reactions requiring dose interruption in ≥5% of patients included infusion related reactions, rash, nail toxicity, venous thromboembolism, alanine aminotransferase increased, edema, hypoalbuminemia, fatigue, stomatitis, and aspartate aminotransferase increased.
Dose reductions of RYBREVANT in combination with lazertinib due to an adverse reaction occurred in 42% of patients. Adverse reactions requiring dose reductions in ≥5% of patients included rash and nail toxicity.
Permanent discontinuations of RYBREVANT due to an adverse reaction occurred in 22% of patients. Adverse reactions leading to RYBREVANT discontinuation in ≥1% of patients were rash, nail toxicity, infusion related reactions, ILD, venous thromboembolism, edema, fatigue, and hypoalbuminemia.
Serious adverse reactions occurred in 49% of patients who received RYBREVANT in combination with lazertinib. Serious adverse reactions in >2% of patients who received RYBREVANT in combination with lazertinib included pulmonary embolism (6.2%), pneumonia (4.0%), deep vein thrombosis (2.9%), ILD/pneumonitis (2.9%), COVID-19 (2.4%) infusion related reaction (2.1%; amivantamab-specific), rash (2.1%) and pleural effusion (2.1%).
Fatal adverse reactions occurred in 7% of patients who received RYBREVANT in combination with lazertinib, which included death not otherwise specified (1.2%); sepsis and respiratory failure (1% each); pneumonia, myocardial infarction, and sudden death (0.7% each); cerebral infarction, pulmonary embolism (PE), and COVID-19 infection (0.5% each); and ILD/pneumonitis, acute respiratory distress syndrome (ARDS), and cardiopulmonary arrest (0.2% each).
Table 10 summarizes the adverse reactions (≥ 10%) in MARIPOSA.
Table 10: Adverse Reactions (≥10%) in First-line Treatment of Patients with Locally Advanced or Metastatic NSCLC with EGFR Exon 19 Deletion or Exon 21 L858R Substitution Mutations in MARIPOSA
System Organ Class Adverse Reaction | RYBREVANT + Lazertinib n=421 | Osimertinib n=428 | |||||||||||
System Organ Class Adverse Reaction | RYBREVANT + Lazertinib n=421 | Osimertinib n=428 | |||||||||||
| All Grades (%) | Grade 3-4 (%) | All Grades (%) | Grade 3-4 (%) | ||||||||||
| All Grades (%) | Grade 3-4 (%) | All Grades (%) | Grade 3-4 (%) | ||||||||||
| Eye disorders | |||||||||||||
| Ocular infections, irritations and inflammationsa | 15 | 0.5 | 4 | 0 | |||||||||
| Gastrointestinal disorders | |||||||||||||
| Stomatitisb | 43 | 2 | 26 | 0.5 | |||||||||
| Constipation | 29 | 0 | 13 | 0 | |||||||||
| Diarrhea | 29 | 2 | 44 | 0.7 | |||||||||
| Nausea | 21 | 1 | 14 | 0.2 | |||||||||
| Vomiting | 12 | 0.5 | 5 | 0 | |||||||||
| Haemorrhoids | 10 | 0.2 | 2 | 0.2 | |||||||||
| General disorders and administration site conditions | |||||||||||||
| Edemac | 47 | 3 | 9 | 0 | |||||||||
| Fatigued | 32 | 4 | 20 | 2 | |||||||||
| Pyrexia | 12 | 0 | 9 | 0 | |||||||||
| Infections and Infestations | |||||||||||||
| Paronychia | 68 | 11 | 28 | 0.5 | |||||||||
| Injury, Poisoning and Procedural Complications | |||||||||||||
| Infusion related reactione | 63 | 6 | 0 | 0 | |||||||||
| Metabolism and nutrition disorders | |||||||||||||
| Decreased appetite | 24 | 1 | 18 | 1 | |||||||||
| Musculoskeletal and connective tissue disorders | |||||||||||||
| Muscle spasms | 17 | 0.5 | 7 | 0 | |||||||||
| Pain in extremity | 15 | 0.2 | 5 | 0 | |||||||||
| Myalgia | 13 | 0.7 | 4 | 0 | |||||||||
| Back pain | 11 | 0.2 | 11 | 0 | |||||||||
| Nervous system disorders | |||||||||||||
| Paresthesiaf | 34 | 2 | 10 | 0.2 | |||||||||
| Headache | 13 | 0.2 | 13 | 0 | |||||||||
| Dizziness | 12 | 0 | 7 | 0 | |||||||||
| Skin and subcutaneous tissue disorders | |||||||||||||
| Rashg | 88 | 26 | 47 | 0.7 | |||||||||
| Dry skinh | 26 | 1 | 20 | 0.5 | |||||||||
| Pruritus | 24 | 0.5 | 17 | 0.2 | |||||||||
| Vascular disorders | |||||||||||||
| Venous thromboembolismi | 36 | 11 | 8 | 3 | |||||||||
a Includes Blepharitis, Conjunctival hyperemia, Conjunctivitis, Episcleritis, Eye pruritus, Noninfective conjunctivitis, Ocular hyperemia b Includes Angular cheilitis, Aphthous ulcer, Mouth ulceration, Mucosal inflammation, Stomatitis | |||||||||||||
c Includes Eye edema, Eyelid edema, Face edema, Generalized edema, Localized edema, Edema, Edema peripheral, Periorbital edema, Periorbital swelling, Peripheral swelling, Swelling face d Includes Asthenia, Fatigue e Amivantamab specific adverse reactions f Includes Dysesthesia, Hypoesthesia, Neuropathy peripheral, Paresthesia, Peripheral motor neuropathy, Peripheral sensorimotor neuropathy, Peripheral sensory neuropathy, Polyneuropathy g Includes Acne, Dermatitis, Dermatitis acneiform, Erythema, Folliculitis, Rash, Rash erythematous, Rash macular, Rash maculo-papular, Rash pruritic, Rash pustular, Skin lesion h Includes Dry skin, Eczema, Eczema asteatotic, Skin fissures, Xeroderma, Xerosis i Includes Axillary vein thrombosis, Deep vein thrombosis, Embolism, Embolism venous, Jugular vein thrombosis, Portal vein thrombosis, Pulmonary embolism, Pulmonary infarction, Sigmoid sinus thrombosis, Superior sagittal sinus thrombosis, Thrombosis, Vena cava thrombosis, Venous thrombosis, Venous thrombosis limb | |||||||||||||
Previously Treated NSCLC with EGFR Exon 19 Deletions or Exon 21 L858R Substitution Mutations
The safety of RYBREVANT in combination with carboplatin and pemetrexed was evaluated in MARIPOSA-2 (NSC3002), which included patients with locally advanced or metastatic NSCLC with EGFR Exon 19 deletions or Exon 21 L858R substitution mutations whose disease has progressed on or after treatment with osimertinib. (see 14.1 Clinical Trials by Indication). Patients received RYBREVANT, 1400 mg (for patients <80 kg) or 1750 mg (for patients ≥80 kg) by intravenous infusion once weekly for 4 weeks, then every 3 weeks with a dose of 1750 mg (for patients <80 kg) or 2100 mg (for patients ≥80 kg) starting at Week 7 until disease progression or unacceptable toxicity.
Patients were exposed to RYBREVANT with carboplatin and pemetrexed (N=130) for a median treatment duration of 6.3 months (range: 0 to 14.7 months) and to carboplatin and pemetrexed (N=243) for a median treatment duration of 3.7 months (range: 0 to 15.9 months).
The most common TEAE (≥20%) in patients who received RYBREVANT in combination with carboplatin and pemetrexed were infusion related reactions, neutropenia, nausea, rash, thrombocytopenia, anemia, constipation, paronychia, edema peripheral, stomatitis, decreased appetite, leukopenia, fatigue, asthenia, vomiting, hypoalbuminemia, COVID-19, alanine aminotransferase increased, and dermatitis acneiform. The most common TEAE (≥20%) in patients who received carboplatin and pemetrexed were neutropenia, anemia, nausea, thrombocytopenia, constipation, leukopenia, alanine aminotransferase increased, aspartate aminotransferase increased, and decreased appetite.
Dose interruptions of RYBREVANT due to an adverse reaction occurred in 60% of patients. Infusion related reactions (IRRs) requiring infusion interruptions occurred in 52% of patients.
Adverse reactions requiring dose interruption in ≥5% of patients included neutropenia, thrombocytopenia, COVID-19, leukopenia, and rash. Dose reductions of RYBREVANT due to an adverse reaction occurred in 17% of patients. The most commonly reported adverse reactions requiring dose reductions in ≥2% of patients included neutropenia and rash.
Fifteen percent of patients permanently discontinued RYBREVANT due to adverse reactions. The most frequent adverse reactions leading to treatment discontinuation in ≥1% of patients were infusion related reactions.
The most common Grade 3 to 4 laboratory abnormalities (≥2%) were decreased albumin, increased alanine aminotransferase, increased gamma-glutamyl transferase, decreased sodium, decreased potassium, decreases in white blood cells, hemoglobin, neutrophils, platelets, and lymphocytes.
Serious adverse events occurred in 32.3% of patients who received RYBREVANT in combination with carboplatin and pemetrexed, and in 20.2% of patients treated with chemotherapy alone. In MARIPOSA-2 ACP arm, Grade ≥3 TEAEs were reported for 79.0% of Asians and in 64.1% of non-Asians. SAEs were reported for 40.3% of Asians and in 23.4% of non-Asians.
Serious adverse events in ≥2% of patients who received RYBREVANT in combination with carboplatin and pemetrexed included thrombocytopenia, dyspnea, sepsis, and pulmonary embolism. Serious adverse events in ≥2% who received chemotherapy alone included neutropenia, thrombocytopenia, febrile neutropenia, and pneumonia. Fatal adverse reactions, irrespective of relatedness to treatment occurred in 3 patients (2.3%) who received RYBREVANT in combination with carboplatin and pemetrexed. Fatal adverse reactions, irrespective of relatedness to treatment occurred in 3 patients (1.2%) who received chemotherapy alone. The fatal adverse events that occurred in patients treated with RYBREVANT in combination with carboplatin and pemetrexed included dyspnea, sepsis, and ventricular fibrillation. The fatal adverse reactions that occurred in patients treated with chemotherapy alone included dyspnea, pneumonia, and respiratory failure.
Table 11 summarizes TEAEs reported in ≥5% of patients in MARIPOSA-2.
Table 11: Treatment-Emergent Adverse Events (≥5%) in Previously Treated Patients with NSCLC with EGFR Exon 19 Deletions or Exon 21 L858R Substitution Mutations Treated with RYBREVANT in Combination with Carboplatin and Pemetrexed in MARIPOSA-2
System Organ Class Adverse Reaction | RYBREVANT + Carboplatin + Pemetrexed (N=130) | Carboplatin + Pemetrexed (N=243) | ||||||||||
System Organ Class Adverse Reaction | RYBREVANT + Carboplatin + Pemetrexed (N=130) | Carboplatin + Pemetrexed (N=243) | ||||||||||
System Organ Class Adverse Reaction | RYBREVANT + Carboplatin + Pemetrexed (N=130) | Carboplatin + Pemetrexed (N=243) | ||||||||||
| All Grades (%) | Grade 3-4 (%) | All Grades (%) | Grade 3-4 (%) | |||||||||
| Blood and lymphatic disorders | ||||||||||||
| Neutropenia | 57 | 45 | 42 | 21 | ||||||||
| Thrombocytopenia | 44 | 15 | 30 | 9.1 | ||||||||
| Anemia | 39 | 12 | 40 | 10 | ||||||||
| Leukopenia | 29 | 20 | 28 | 10 | ||||||||
| Eye disorders | ||||||||||||
| Eye disordersa | 13 | 0 | 5 | 0 | ||||||||
| Gastrointestinal disorders | ||||||||||||
| Nausea | 45 | 0.8 | 37 | 0.8 | ||||||||
| Constipation | 39 | 0.8 | 30 | 0 | ||||||||
| Stomatitisb | 35 | 2.3 | 11 | 0 | ||||||||
| Vomiting | 25 | 0.8 | 17 | 0.4 | ||||||||
| Diarrhea | 14 | 0.8 | 6.6 | 0.4 | ||||||||
| Abdominal painc | 9.2 | 0 | 6.6 | 0 | ||||||||
| Hemorrhoids | 5.4 | 0 | 0.4 | 0 | ||||||||
| General disorders and administration site conditions | ||||||||||||
| Fatigued | 51 | 3.8 | 35 | 3.7 | ||||||||
| Edemae | 36 | 1.5 | 11 | 0.4 | ||||||||
| Pyrexia | 12 | 0 | 10 | 0 | ||||||||
| Injury, poisoning and procedural complications | ||||||||||||
| Infusion related reaction | 59 | 5.4 | 0.4 | 0 | ||||||||
| Infections and infestations | ||||||||||||
| Paronychia | 37 | 2.3 | 0.4 | 0 | ||||||||
| COVID-19 | 21 | 1.5 | 10 | 0 | ||||||||
| Conjunctivitis | 7.7 | 0 | 2.1 | 0 | ||||||||
| Investigations | ||||||||||||
| Alanine aminotransferase increased | 20 | 5.4 | 28 | 4.1 | ||||||||
| Aspartate aminotransferase increased | 15 | 0.8 | 24 | 0 | ||||||||
| Weight decreased | 11 | 0 | 7.0 | 0.4 | ||||||||
| Blood alkaline phosphatase increased | 6.9 | 0 | 5.3 | 0 | ||||||||
| Gamma-glutamyl transferase increased | 5.4 | 2.3 | 10 | 0.4 | ||||||||
| Metabolism and nutrition disorders | ||||||||||||
| Decreased appetite | 31 | 0 | 21 | 1.2 | ||||||||
| Hypoalbuminemia | 22 | 2.3 | 8.6 | 0.4 | ||||||||
| Hypokalemia | 19 | 4.6 | 6.2 | 2.5 | ||||||||
| Hyperglycemia | 12 | 0.8 | 4.1 | 0 | ||||||||
| Hypocalcaemia | 12 | 0.8 | 3.7 | 0 | ||||||||
| Hypomagnesemia | 10 | 0.8 | 3.7 | 0 | ||||||||
| Hyponatremia | 10 | 3.8 | 6.6 | 0.8 | ||||||||
| Musculoskeletal and connective tissue disorders | ||||||||||||
| Musculoskeletal painf | 22 | 3.1 | 14 | 0.8 | ||||||||
| Nervous system disorders | ||||||||||||
| Dizzinessg | 9.2 | 0 | 6.6 | 0 | ||||||||
| Headache | 8.5 | 0 | 12 | 0.4 | ||||||||
| Psychiatric disorders | ||||||||||||
| Insomnia | 7.7 | 0 | 2.9 | 0 | ||||||||
| Respiratory, thoracic and mediastinal disorders | ||||||||||||
| Cough | 11 | 0 | 12 | 0.4 | ||||||||
| Dyspnea | 11 | 1.5 | 7.4 | 1.2 | ||||||||
| Epistaxis | 8.5 | 0 | 2.9 | 0 | ||||||||
| Skin and subcutaneous tissue disorders | ||||||||||||
| Rashh | 72 | 11 | 12 | 0 | ||||||||
| Nail toxicityi | 8.5 | 0 | 0 | 0 | ||||||||
| Pruritus | 15 | 0 | 7.0 | 0 | ||||||||
| Dry skinj | 15 | 0 | 2.5 | 0 | ||||||||
| Alopecia | 6.2 | 0 | 3.3 | 0 | ||||||||
| Vascular disorders | ||||||||||||
| Venous thromboembolismk | 6.9 | 2.3 | 3.3 | 2.5 | ||||||||
Adverse events are coded using MedDRA Version 25.0 a includes Blepharitis, Conjunctival hyperemia, Dry eye, Eye pruritus, Keratitis, Noninfective conjunctivitis, Ocular hyperaemia, Trichomegaly, Uveitis, Vision blurred, Visual acuity reduced, Visual impairment b includes Angular cheilitis, Aphthous ulcer, Cheilitis, Glossitis, Lip ulceration, Mouth ulceration, Mucosal inflammation, Stomatitis c includes Abdominal discomfort, Abdominal pain, Abdominal pain lower, Abdominal pain upper d includes Asthenia, Fatigue, Malaise e includes Eye edema, Eyelid edema, Face edema, Generalised edema, Localised edema, Edema, Edema peripheral, Periorbital edema, Peripheral swelling, Swelling face f includes Arthralgia, Back pain, Pain in extremity g includes Dizziness, Vertigo h includes Acne, Dermatitis, Dermatitis acneiform, Erythema, Folliculitis, Impetigo, Palmar-plantar erythrodysaesthesia syndrome, Perioral dermatitis, Pustule, Rash, Rash erythematous, Rash follicular, Rash macular, Rash maculo-papular, Rash papular, Rash pruritic, Rash pustular, Skin exfoliation, Skin lesion i includes Ingrowing nail, Nail bed disorder, Nail bed inflammation, Nail disorder, Nail dystrophy, Nail infection, Onychoclasis, Onycholysis, j includes Dry skin, Eczema, Skin fissures, Xeroderma, Xerosis k includes Deep vein thrombosis and Pulmonary embolism | ||||||||||||
First-line Treatment of Non-Small Cell Lung Cancer (NSCLC) with EGFR Exon 20 Insertion Mutations
The safety of RYBREVANT in combination with carboplatin and pemetrexed was evaluated in the PAPILLON study, a randomized, open-label trial in patients with locally advanced or metastatic NSCLC with EGFR exon 20 insertion mutations (see 14.1. Clinical Trials by Indication). In the PAPILLON study, 151 patients were treated with RYBREVANT in combination with carboplatin and pemetrexed at the recommended dosage and 155 patients were treated with carboplatin and pemetrexed (chemotherapy alone). Among patients who received RYBREVANT in combination with carboplatin and pemetrexed, the median exposure was
9.7 months (range: 0.1 to 26.9 months). The median exposure for patients who received chemotherapy alone was 6.7 months (range: 0.0 to 25.3 months). The median age was 62 years (range: 27 to 92 years); 57.8% were female; 61.4% were Asian, 36.0% were White and 84.4% had baseline body weight <80 kg.
The most common TEAE (≥20%) in patients who received RYBREVANT in combination with carboplatin and pemetrexed were rash, neutropenia, paronychia, anaemia, stomatitis, infusion related reactions, hypoalbuminaemia, edema, constipation, leukopenia, nausea, thrombocytopenia, decreased appetite, fatigue, ALT increased, AST increased, COVID-19, hypokalaemia, vomiting, and diarrhea. The most common TEAE (≥20%) in patients who received chemotherapy alone were anaemia, neutropenia, nausea, fatigue, ALT increased, AST increased, leukopenia, constipation, thrombocytopenia, and decreased appetite.
Serious adverse events occurred in 37.1% of patients who received RYBREVANT in combination with carboplatin and pemetrexed, and in 31.0% of patients treated with chemotherapy alone. Serious adverse events in ≥2% of patients who received RYBREVANT in combination with carboplatin and pemetrexed included pneumonia, COVID-19, pulmonary embolism, thrombocytopenia, rash, interstitial lung disease/pneumonitis, vomiting, and hypokalemia. Serious adverse events in ≥2% of patients who received chemotherapy alone included pneumonia, pulmonary embolism, dyspnoea, pleural effusion, thrombocytopenia, and anaemia. Fatal adverse events, irrespective of relatedness to treatment, occurred in 7 patients (4.6%) who received RYBREVANT in combination with carboplatin and pemetrexed and 4 (2.6%) patients who received chemotherapy alone. The fatal adverse events that occurred in patients who received RYBREVANT in combination with carboplatin and pemetrexed included pneumonia, cardiovascular accident, cardio-respiratory arrest, COVID-19, sepsis and death. The fatal adverse events that occurred in patients treated with chemotherapy alone included sepsis, acute myocardial infarction, dyspnoea and death.
Permanent discontinuation of RYBREVANT due to an adverse event occurred in 11.3% of patients. Adverse events resulting in permanent discontinuation of RYBREVANT in ≥1% of patients were rash and ILD/pneumonitis.
Dose interruptions of RYBREVANT due to an adverse event occurred in 64.2% of patients. Infusion related reactions (IRRs) requiring infusion interruptions occurred in 37.7% of patients. Adverse events requiring dose interruption in ≥5% of patients included rash, neutropenia, paronychia, COVID-19, thrombocytopenia, and hypokalemia.
Dose reductions of RYBREVANT due to an adverse event occurred in 35.8% of patients. Adverse events requiring dose reductions in ≥5% of patients included rash and paronychia.
The most common Grade 3 to 4 laboratory abnormalities (≥2%) observed in patients who received RYBREVANT in combination with carboplatin and pemetrexed were decreased albumin, increased alanine aminotransferase, increased gamma-glutamyltransferase, decreased sodium, decreased potassium, decreased magnesium and decreases in white blood cells, hemoglobin, neutrophils, platelets, and lymphocytes. The most common Grade 3 to 4 laboratory abnormalities (≥2%) observed in patients who received chemotherapy alone were decreased sodium, increased gamma-glutamyltransferase and decreases in white blood cells, hemoglobin, neutrophils, platelets, and lymphocytes.
Table 12 summarizes the TEAEs reported in ≥5% of patients in the PAPILLON study.
Table 12: Treatment-emergent Adverse Events (≥5%) in Patients with NSCLC with Exon 20 Insertion Mutations Treated with RYBREVANT in Combination with Carboplatin and Pemetrexed in PAPILLON
System Organ Class Adverse Reaction | RYBREVANT + Carboplatin + Pemetrexed (N=151) | Carboplatin + Pemetrexed (N=155) | ||
System Organ Class Adverse Reaction | RYBREVANT + Carboplatin + Pemetrexed (N=151) | Carboplatin + Pemetrexed (N=155) | ||
System Organ Class Adverse Reaction | RYBREVANT + Carboplatin + Pemetrexed (N=151) | Carboplatin + Pemetrexed (N=155) | ||
| All Grades (%) | Grade 3-4 (%) | All Grades (%) | Grade 3-4 (%) | |
| Blood and Lymphatic system disorders | ||||
| Neutropenia | 58.9 | 33.1 | 45.2 | 22.6 |
| Anaemia | 50.3 | 10.6 | 54.8 | 12.3 |
| Leukopenia | 37.7 | 11.3 | 32.3 | 3.2 |
| Thrombocytopenia | 36.4 | 9.9 | 29.7 | 10.3 |
| Eye Disorders | ||||
| Eye disordersa | 8.6 | 0 | 8.4 | 0 |
| Gastrointestinal disorders | ||||
| Stomatitisb | 43.0 | 4.0 | 11.0 | 0 |
| Constipation | 39.7 | 0 | 30.3 | 0.6 |
| Nausea | 36.4 | 0.7 | 41.9 | 0 |
| Vomiting | 21.2 | 3.3 | 18.7 | 0.6 |
| Diarrhea | 20.5 | 3.3 | 12.9 | 1.3 |
| Hemorrhoids | 11.9 | 1.3 | 1.3 | 0 |
| Abdominal painc | 10.6 | 0.7 | 8.4 | 0 |
| Gingival bleeding | 5.3 | 0 | 1.3 | 0 |
| Abdominal distension | 4.6 | 0 | 6.5 | 0 |
| General disorders and administration site conditions | ||||
| Edemad | 40.4 | 1.3 | 18.7 | 0 |
| Fatiguee | 33.8 | 6.0 | 37.4 | 3.9 |
| Pyrexia | 15.9 | 0 | 5.8 | 0 |
| Malaise | 10.6 | 0 | 7.7 | 0 |
| Hepatobiliary disorders | ||||
| Hyperbilirubinaemia | 9.9 | 0.7 | 3.9 | 0 |
| Infections and infestations | ||||
| Paronychia | 56.3 | 6.6 | 0 | 0 |
| COVID-19 | 23.8 | 1.3 | 13.5 | 0.6 |
| Pneumonia | 11.3 | 4.0 | 6.5 | 1.9 |
| Conjunctivitis | 6.0 | 0 | 4.5 | 0 |
| Injury, poisoning and procedural complications | ||||
| Infusion related reaction | 41.7 | 1.3 | 1.3 | 0 |
| Investigations | ||||
| Alanine aminotransferase increased | 33.1 | 4.0 | 36.1 | 1.3 |
| Aspartate aminotransferase increased | 31.1 | 0.7 | 32.9 | 0.6 |
| Gamma-glutamyltransferase increased | 13.9 | 2.6 | 16.8 | 3.9 |
| Weight decreased | 13.9 | 0.7 | 8.4 | 0 |
| Blood alkaline phosphatase increased | 12.6 | 0.7 | 7.7 | 0 |
| Blood lactate dehydrogenase increased | 8.6 | 0 | 5.2 | 0 |
| Blood creatinine increased | 7.3 | 1.3 | 9.7 | 0 |
| Metabolism and nutrition disorders | ||||
| Hypoalbuminaemia | 41.1 | 4.0 | 9.7 | 0 |
| Decreased appetite | 35.8 | 2.6 | 27.7 | 1.3 |
| Hypokalaemia | 21.2 | 8.6 | 8.4 | 1.3 |
| Hypomagnesaemia | 14.6 | 2.0 | 9.7 | 0.6 |
| Hypocalcaemia | 12.6 | 1.3 | 1.9 | 0 |
| Hyponatraemia | 12.6 | 2.0 | 7.7 | 0.6 |
| Hypophosphataemia | 6.6 | 0 | 1.3 | 0 |
| Hypoproteinaemia | 6.6 | 0 | 1.9 | 0 |
| Hyperglycaemia | 5.3 | 0 | 7.1 | 0.6 |
| Musculoskeletal and connective tissue disorders | ||||
| Myalgia | 5.3 | 1.3 | 3.2 | 0.6 |
| Nervous system disorders | ||||
| Dizzinessf | 9.9 | 0 | 11.6 | 0 |
| Dysgeusia | 6.0 | 0 | 6.5 | 0 |
| Respiratory, thoracic and mediastinal disorders | ||||
| Cough | 13.9 | 0 | 15.5 | 0 |
| Dyspnoea | 10.6 | 1.3 | 14.8 | 2.6 |
| Pulmonary embolism | 7.9 | 3.3 | 4.5 | 3.9 |
| Productive cough | 6.0 | 0 | 1.9 | 0 |
| Psychiatric disorders | ||||
| Insomnia | 10.6 | 0 | 12.9 | 0 |
| Skin and subcutaneous tissue disorders | ||||
| Rashg | 90.1 | 19.2 | 18.7 | 0 |
| Dry skinh | 16.6 | 0 | 5.8 | 0 |
| Alopecia | 8.6 | 0 | 5.2 | 0 |
| Nail toxicityi | 7.9 | 0 | 3.2 | 0 |
| Skin ulcer | 6.6 | 1.3 | 0.6 | 0 |
| Pruritus | 6.6 | 0 | 7.7 | 0 |
| Vascular disorders | ||||
| Deep vein thrombosis | 6.6 | 0 | 1.9 | 0 |
Adverse events are coded using MedDRA Version 25.0 a includes Blepharitis, Conjunctival hyperaemia, Dry eye, Eye pruritus, Keratitis, Vision blurred, Visual acuity reduced, Visual impairment | ||||
b includes Angular cheilitis, Aphthous ulcer, Cheilitis, Lip ulceration, Mouth ulceration, Mucosal inflammation, Stomatitis c includes Abdominal discomfort, Abdominal pain, Abdominal pain lower, Abdominal pain upper, Gastrointestinal pain d includes Eye edema, Eyelid edema, Face edema, Generalised edema, Localised edema, Edema, Edema peripheral, Periorbital edema, Peripheral swelling, Swelling face e includes Asthenia, Fatigue f includes Dizziness, Vertigo g includes Acne, Dermatitis, Dermatitis acneiform, Erythema, Folliculitis, Palmar-plantar erythrodysaesthesia syndrome, Pustule, Rash, Rash macular, Rash maculo-papular, Rash papular, Rash pruritic, Rash pustular, Skin lesion h includes Dry skin, Eczema, Skin fissures, Xeroderma, Xerosis i includes Ingrowing nail, Nail bed inflammation, Nail disorder, Nail dystrophy, Nail infection, Onychoclasis, Onycholysis | ||||
Previously Treated NSCLC with EGFR Exon 20 Insertion Mutations
The safety of RYBREVANT monotherapy in patients with locally advanced or metastatic NSCLC with EGFR exon 20 insertion mutations whose disease has progressed on or after platinum-based chemotherapy was evaluated in 129 patients enrolled in CHRYSALIS. Patients received RYBREVANT 1050 mg (for patients <80 kg) or 1400 mg (for patients ≥80 kg) by intravenous infusion once weekly for 4 weeks, then every 2 weeks starting at Week 5, until disease progression or unacceptable toxicity. The median treatment duration was 5.6 months (range: 0.03 to 23.9 months), with 44.2% of patients for at least 6 months. The median age was 62 years (range: 36 to 84 years) with 41.1% of patients 65 years of age or older, and 8.5% of patients 75 years of age or older; 61.2% were female; 55.0% were Asian, 2.3% were Black, and 34.9% were White. Eighty-two percent of patients (n=106) had baseline body weight <80 kg and 18% (n=23) had baseline body weight ≥80 kg.
The most common adverse reactions ≥20% were dermatitis acneiform, rash, infusion related reactions (IRRs), nausea, paronychia, fatigue, hypoalbuminemia, constipation, stomatitis, and peripheral edema, and alanine aminotransferase increased. Serious adverse reactions occurred in 30% of patients who received RYBREVANT. Serious adverse reactions in ≥2% of patients included pulmonary embolism, pneumonitis, dyspnea, back pain, and muscular weakness. Adverse reactions resulting in permanent discontinuation of RYBREVANT in ≥1% of patients were pneumonia, IRR, pneumonitis, and pleural effusion.
Dose reductions due to an adverse reaction occurred in 15% of patients who received RYBREVANT. Adverse reactions requiring dose reductions in ≥2% of patients included dermatitis acneiform, and paronychia.
Grade 5 treatment-emergent adverse events, irrespective of relatedness to RYBREVANT, were reported in 7.0% of patients. The most common events were pneumonia and dyspnea.
Table 13 presents adverse reactions reported in ≥5% of patients treated with RYBREVANT in CHRYSALIS. There were no new safety signals observed with longer term follow-up and additional patients, and therefore no meaningful changes occurred in the safety profile of RYBREVANT.
Table 13: Adverse reactions in CHRYSALIS Reported in ≥5% of Patients
System Organ Class Adverse Reaction | RYBREVANT Exon 20 Ins Prior Chemotherapy (RP2D) (N=129) | |
System Organ Class Adverse Reaction | RYBREVANT Exon 20 Ins Prior Chemotherapy (RP2D) (N=129) | |
| All Grades (%) | Grade 3-4* (%) | |
| All Grades (%) | Grade 3-4* (%) | |
| Eye disorders | ||
| Eye disorder a | 9.3 | 0 |
| Gastrointestinal disorders | ||
| Stomatitis b | 26.4 | 0.8 |
| Nausea | 24.0 | 0 |
| Constipation | 23.3 | 0 |
| Diarrhoea | 14.7 | 3.1 |
| Vomiting | 13.2 | 0 |
| Abdominal pain c | 9.3 | 0.8 |
| General disorders and administration site conditions | ||
| Fatigue d | 32.6 | 2.3 |
| Oedema e | 26.4 | 0.8 |
| Pyrexia | 13.2 | 0 |
| Infections and infestations | ||
| Paronychia | 49.6 | 3.1 |
| Pneumonia | 7.8 | 0.8 |
| Injury, poisoning and procedural complications | ||
| Infusion related reaction | 64.3 | 3.1 |
| Investigations | ||
| Alanine aminotransferase increased | 17.1 | 0.8 |
| Aspartate aminotransferase increased | 13.2 | 0 |
| Blood alkaline phosphatase increased | 9.3 | 0.8 |
| Gamma-glutamyltransferase increased | 6.2 | 0.8 |
| Metabolism and nutrition disorders | ||
| Hypoalbuminemia f | 32.6 | 3.1 |
| Decreased appetite | 14.7 | 0 |
| Musculoskeletal and connective tissue disorders | ||
| Musculoskeletal pain g | 45.0 | 0 |
| Nervous system disorders | ||
| Dizziness h | 10.1 | 0.8 |
| Paraesthesia | 8.5 | 0 |
| Headache | 6.2 | 0.8 |
| Respiratory, thoracic and mediastinal disorders | ||
| Dyspnea | 19.4 | 0.8 |
| Cough | 13.2 | 0 |
| Skin and subcutaneous tissue disorders | ||
| Rash i | 82.2 | 3.9 |
| Pruritus | 16.3 | 0 |
| Dry skin j | 15.5 | 0 |
| Skin fissures | 8.5 | 0 |
*No Grade 4 events observed RP2D (recommended phase 2 dose): 1050 mg if baseline weight <80 kg and 1400 mg if baseline weight ≥80 kg. Adverse events were coded using MedDRA version 23.0. Note: Patients are counted only once for any given event, regardless of the number of times they actually experienced the event. a includes Blepharitis, Conjunctival hyperaemia, Corneal irritation, Dry eye, Eye pruritus, Growth of eyelashes, Keratitis, Ocular hyperaemia, Uveitis, Vision blurred, Visual acuity reduced, Visual impairment b includes Aphthous ulcer, Cheilitis, Glossitis, Mouth ulceration, Mucosal inflammation, Stomatitis c includes Abdominal pain, Abdominal pain lower, Abdominal pain upper, Epigastric discomfort d includes Asthenia, Fatigue e includes Eyelid oedema, Face oedema, Generalised oedema, Oedema, Oedema peripheral, Periorbital oedema, Peripheral swelling f includes Blood albumin decreased, Hypoalbuminaemia g includes Arthralgia, Arthritis, Back pain, Bone pain, Musculoskeletal chest pain, Musculoskeletal discomfort, Musculoskeletal pain, Myalgia, Neck pain, Non-cardiac chest pain, Pain in extremity, Spinal pain. h includes Dizziness i includes Acne, Dermatitis, Dermatitis acneiform, Palmar-plantar erythrodysaesthesia syndrome, Perineal rash, Rash, Rash erythematous, Rash maculo-papular, Rash papular, Rash vesicular, Skin exfoliation j includes Dry skin, Eczema, Eczema asteatotic | ||
Select Adverse Reactions
The safety data presented under Select Adverse Reactions reflects the safety profile of 702 patients with locally advanced or metastatic NSCLC with EGFR Exon 19 deletions or Exon 21 L858R substitution mutations, this includes 421 patients who received RYBREVANT in combination with lazertinib in the MARIPOSA study and 281 who received RYBREVANT in combination with carboplatin and pemetrexed in the MARIPOSA-2 and PAPILLON studies. The safety data presented under Select Adverse Reactions also reflects the safety profile of 302 patients with locally advanced or metastatic NSCLC who received RYBREVANT as a monotherapy in the CHRYSALIS study. This includes 129 patients with locally advanced or metastatic NSCLC with EGFR Exon 20 insertion mutations whose disease has progressed on or after platinum-based chemotherapy.
Left Ventricular Dysfunction and Cardiomyopathy
RYBREVANT in combination with lazertinib
Left Ventricular Ejection Fraction (LVEF) reductions of >10 percentage points and a drop to below lower limit of normal occurred in 3.4% of patients treated with RYBREVANT in combination with lazertinib and who had a baseline LVEF assessment. A total of 7.4% of patients treated with RYBREVANT in combination with lazertinib reported cardiomyopathy events (defined as cardiac failure, chronic cardiac failure, congestive cardiac failure, pulmonary edema, ejection fraction decreased, left ventricular dysfunction).
Venous Thromboembolic (VTE) Events
RYBREVANT in combination with lazertinib
Venous thromboembolic events (VTE) occurred in 35.6% of patients treated with RYBREVANT. Most cases were Grade 1 or 2, with Grade 3-4 events occurring in 10.7% of patients. VTE events with a fatal outcome was reported in 0.5% of patients. The median time to onset was 83.5 days (range 6 to 777 days). The incidence of RYBREVANT dose reduction and dose interruption due to VTE was 1.0% and 9.0%, respectively and twelve patients (2.9%) permanently discontinued RYBREVANT due to VTE.
Infusion-Related Reactions (IRR)
RYBREVANT in combination with lazertinib
Infusion related reactions (IRRs) occurred in 62.9% of patients treated with RYBREVANT. Among patients receiving treatment on Week 1 Day 1, 52.5% experienced an IRR, while the incidence of IRR was 3.2% with the Day 2 infusion, 1.3% with the Week 2 infusion, and cumulatively 1.4% with the Week 3 and Week 4 infusions. The majority of reported IRRs were Grade 1-2 (93.5%). Grade 3 IRRs were reported in 5.5% of patients and Grade 4 IRRs were reported in 1.0% of patients. The median time to onset was 1.0 hours (range 0 to 52.5 hours) after start of infusion. The incidence of RYBREVANT dose reduction due to IRR was 0.7%, and 4.5% of patients permanently discontinued RYBREVANT due to IRR.
RYBREVANT in combination with carboplatin and pemetrexed
IRRs occurred in 49.5% of patients treated with RYBREVANT. Among patients receiving treatment on Week 1 Day 1, 45.7% experienced an IRR, while the incidence of IRR was 1.5% with the Day 2 infusion, 2.1% with the Week 2 infusion, and cumulatively 8.2% with subsequent infusions. Of the cases that reported IRRs, 93.5.% were Grade 1-2, 6.5% were Grade 3, and 0% were Grade 4. The median time to onset was 1.0 hours (range 0.0 to 7 hours) after start of infusion. The incidence of dose reduction due to IRR was 0.4%, and 2.8% of patients permanently discontinued RYBREVANT due to IRR.
RYBREVANT as monotherapy
IRRs occurred in 66% of patients treated with RYBREVANT. Among patients receiving treatment on Week 1 Day 1, 65% experienced an IRR, while the incidence of IRR was 3.4% with the Day 2 infusion, 0.4% with the Week 2 infusion, and cumulatively 1.1% with subsequent infusions. Of the cases that reported IRRs, 97% were Grade 1-2, 2.2% were Grade 3, and 0.4% were Grade 4. The median time to onset was 1 hour (range 0.1 to 18 hours) after start of infusion. The incidence of infusion modifications due to IRR was 62.3% and 1.3% of patients permanently discontinued RYBREVANT due to IRR.
Eye Disorders
RYBREVANT in combination with lazertinib
Eye disorders including keratitis (2.6%), occurred in 26.4% of patients treated with RYBREVANT. Reported adverse reactions included dry eye, blurred vision, eye pruritus, visual impairment, ocular hyperemia, aberrant eyelash growth, conjunctival hyperemia, blepharitis, conjunctivitis, episcleritis, visual acuity reduced, non-infective conjunctivitis, and eye disorder. The majority of events were Grade 1-2, with Grade 3-4 occurring in 1.0% of patients.
RYBREVANT in combination with carboplatin and pemetrexed
Eye disorders, including keratitis (0.4%), occurred in 10.7% of patients treated with RYBREVANT. Other reported adverse reactions included dry eye, blurred vision, eye pruritus, visual impairment, ocular hyperemia, aberrant eyelash growth, conjunctival hyperemia, blepharitis, and uveitis. All events were Grade 1-2.
RYBREVANT as monotherapy
Eye disorders, including keratitis (0.7%), occurred in 13.2% patients treated with RYBREVANT. Other reported adverse reactions included dry eye, blurred vision, eye pruritus, lacrimation increased, visual impairment, ocular hyperemia, eyelid ptosis, aberrant eyelash growth, and uveitis. All events were Grade 1-2.
Interstitial lung disease (ILD)/pneumonitis
RYBREVANT in combination with lazertinib
Interstitial lung disease (ILD) or ILD-like adverse reactions (e.g. pneumonitis) occurred in 3.1% of patients treated with RYBREVANT, with 1.2% of patients experiencing Grade 3-4 ILD. Twelve patients (2.9%) discontinued RYBREVANT due to ILD/pneumonitis.
RYBREVANT in combination with carboplatin and pemetrexed
ILD or ILD-like adverse reactions (e.g. pneumonitis) occurred in 2.1% of patients treated with RYBREVANT, with 1.8% of patients experiencing Grade 3 ILD. Six patients (2.1%) discontinued RYBREVANT due to ILD/pneumonitis.
RYBREVANT as monotherapy
ILD or ILD-like adverse reactions (e.g. pneumonitis) occurred in 3.3% of patients treated with RYBREVANT, with 0.7% of patients experiencing Grade 3 ILD. Three patients (1%) discontinued RYBREVANT due to ILD/pneumonitis.
Skin and Nail Reactions
RYBREVANT in combination with lazertinib
Rash (including dermatitis acneiform) (88.4%), pruritus (23.5%) and dry skin (26.1%) occurred in patients treated with RYBREVANT. Most cases were Grade 1 or 2, with Grade 3-4 events occurring in 26.4% of patients. Rash leading to dose reduction occurred in 23.5% of patients, and RYBREVANT discontinuation due to rash occurred in 5.0 % of patients. The median time to onset of rash was 14 days (range: 1 to 556 days). Nail toxicity occurred in patients treated with RYBREVANT. Most events were Grade 1 or 2, with Grade 3-4 nail toxicity occurring in 0.5% of patients.
RYBREVANT in combination with carboplatin and pemetrexed
Rash (including dermatitis acneiform) (81.9%), pruritus (10.7%) and dry skin (15.7%) occurred in patients treated with RYBREVANT. Most cases were Grade 1 or 2, with Grade 3 events occurring in 15.3% of patients. Rash leading to dose reduction occurred in 13.5% of patients, and RYBREVANT discontinuation due to rash occurred in 2.5% of patients. Rash usually developed within the first 4 weeks of therapy, with a median time to onset of 14 days (range: 1 to 311 days). Nail toxicity occurred in patients treated with RYBREVANT. All events were Grade 1 or 2, with Grade 3-4 nail toxicity occurring in 0% of patients.
RYBREVANT as monotherapy
Rash (including dermatitis acneiform) (73.5%), pruritis (17.9%) and dry skin (10.9%) occurred in patients treated with RYBREVANT. Most cases were Grade 1 or 2, with Grade 3 events occurring in 3.6% of patients. Rash leading to dose reduction occurred in 5% of patients and RYBREVANT discontinuation due to rash occurred in 0.7% of patients. Rash usually developed within the first 4 weeks of therapy, with a median time to onset of 14 days (range: 1 to 276 days). Paronychia occurred in patients treated with RYBREVANT. Most events were Grade 1 or 2, with Grade 3 paronychia occurring in 1.4% of patients.
Toxic epidermal necrolysis (TEN) occurred in one patient (0.2%) treated with RYBREVANT. Permanently discontinue RYBREVANT if TEN is confirmed.
8.3. Less Common Clinical Trial Adverse Reactions
First-line Treatment of NSCLC with EGFR Exon 19 Deletion or Exon 21 L858R Substitution Mutation
Clinically relevant adverse reactions in <10% of patients who received RYBREVANT in combination with lazertinib include:
Eye disorders: Dry eye (9%), vision blurred (3%), keratitis (3%), trichomegaly (1%), visual acuity reduced (1%), visual impairment (1%), eye disorders (1%), and growth of eyelashes (1%) (see 7. Warnings and Precautions, Ophthalmologic)
Hepatobiliary disorders: hyperbilirubinemia (7%)
Gastrointestinal disorders: gingival bleeding (5%)
Metabolism and nutrition disorders: Hypomagnesemia (5%)
Skin and subcutaneous tissue disorders: nail toxicity (8%, including ingrowing nail, nail disorder, nail infection, nail toxicity, onychoclasis, onycholysis, onychomadesis); palmar-plantar erythrodysesthesia syndrome (6%); skin ulcer (5%); alopecia (4%); and urticaria (1%) (see 7. Warnings and Precautions, Skin)
Renal and urinary disorders: hematuria (5%)
Respiratory, thoracic and mediastinal disorders: epistaxis (8%), interstitial lung disease (ILD) / pneumonitis (3%) (see 7. Warnings and Precautions, Respiratory)
Previously Treated NSCLC with EGFR Exon 19 Deletions or Exon 21 L858R Substitution Mutations
The following are clinically significant TEAEs reported in <5% of RYBREVANT-treated patients with NSCLC with EGFR Exon 19 Deletions or Exon 21 L858R Substitution Mutations in MARIPOSA-2:
Musculoskeletal and connective tissue disorders: myalgia
Respiratory, thoracic and mediastinal disorders: Interstitial lung disease/Pneumonitis (see 7. Warnings and Precautions, Respiratory)
First-line Treatment of NSCLC with EGFR Exon 20 Insertion Mutations
The following are clinically significant TEAEs reported in <5% of patients receiving RYBREVANT in the PAPILLON Study:
Infections and infestations: Skin infection
Respiratory, thoracic and mediastinal disorders: Interstitial lung disease/Pneumonitis (see 7. Warnings and Precautions, Respiratory); Epistaxis
Previously Treated NSCLC with EGFR Exon 20 Insertion Mutations
The following are clinically significant adverse reactions reported in <5% of patients receiving RYBREVANT in the CHRYSALIS Study:
Respiratory, thoracic and mediastinal disorders: Interstitial lung disease (ILD) (see 7. Warnings and Precautions, Respiratory).
Skin and subcutaneous tissue disorders: Toxic epidermal necrolysis (TEN) (see 7. Warnings and Precautions, Skin).
Interstitial lung disease or ILD-like adverse reactions have been reported with the use of RYBREVANT as well as with other EGFR inhibitors.
8.4. Abnormal Laboratory Findings: Hematologic, Clinical Chemistry, and Other Quantitative Data
First-line Treatment of NSCLC with EGFR Exon 19 Deletion or Exon 21 L858R Substitution Mutation
Table 14 summarizes the laboratory abnormalities in MARIPOSA.
Table 14: Select Laboratory Abnormalities (≥20%) That Worsened from Baseline in First-line Patients with Locally Advanced or Metastatic NSCLC with EGFR Exon 19 Deletion or Exon 21 L858R Substitution Mutations in MARIPOSA+
| Laboratory Abnormality | RYBREVANT + Lazertinib n=421 | Osimertinib n=428 | ||||||||||
All Grades (%) | Grades 3 or 4 (%) | All Grades (%) | Grades 3 or 4 (%) | |||||||||
| Chemistry | ||||||||||||
| Decreased Albumin | 89 | 8 | 22 | <1 | ||||||||
| Increased Alanine Aminotransferase | 65 | 7 | 29 | 3 | ||||||||
| Increased Aspartate Aminotransferase | 52 | 4 | 36 | 2 | ||||||||
| Increased alkaline phosphatase | 45 | 0.5 | 15 | 0.5 | ||||||||
| Decreased Calcium (Corrected) | 41 | 1 | 27 | 1 | ||||||||
| Increased Gamma Glutamyl Transferase | 39 | 3 | 24 | 2 | ||||||||
| Decreased Sodium | 38 | 7 | 35 | 5 | ||||||||
| Decreased potassium | 30 | 5 | 16 | 1.2 | ||||||||
| Increased Creatinine | 26 | 1 | 35 | 1 | ||||||||
| Decreased magnesium | 25 | 0.7 | 10 | 0.2 | ||||||||
| Increased Magnesium | 12 | 3 | 20 | 5 | ||||||||
| Hematology | ||||||||||||
| Decreased Platelet Count | 52 | 1 | 57 | 1 | ||||||||
| Decreased Hemoglobin | 47 | 4 | 56 | 2 | ||||||||
| Decreased White Blood Cell | 38 | 1 | 66 | 1 | ||||||||
| Decreased Neutrophil Count | 15 | 1 | 33 | 1 | ||||||||
| + The denominator used to calculate the rate is the number of patients with a baseline value and at least one post-treatment value for the specific lab test. | ||||||||||||
Previously Treated NSCLC with EGFR Exon 19 Deletions or Exon 21 L858R Substitution Mutations
Table 15 summarizes the laboratory abnormalities in MARIPOSA-2.
Table 15: Laboratory Abnormalities (≥20%) That Worsened from Baseline in Patients With NSCLC with EGFR Exon 19 Deletions or Exon 21 L858R Substitution Mutations Treated With RYBREVANT in Combination with Carboplatin and Pemetrexed in MARIPOSA-2
First-line Treatment of NSCLC with EGFR Exon 20 Insertion Mutations
Laboratory abnormalities in PAPILLON are summarized in Table 16.
Table 16: Laboratory Abnormalities (≥20%) That Worsened from Baseline in Patients With NSCLC with EGFR Exon 20 Insertion Mutations Treated with RYBREVANT in Combination with Carboplatin and Pemetrexed in PAPILLON
| Laboratory Abnormality | RYBREVANT + Carboplatin + Pemetrexed+ | Carboplatin + Pemetrexed | |||
All Grades (%) | Grade 3 or 4 (%) | All Grades (%) | Grade 3 or 4 (%) | ||
| Chemistry | |||||
| Laboratory Abnormality | RYBREVANT + Carboplatin + Pemetrexed (N=130) | Carboplatin + Pemetrexed (N=243) | |||||||
All Grades (%) | Grade 3 or 4 (%) | All Grades (%) | Grade 3 or 4 (%) | ||||||
| Chemistry | |||||||||
| Decreased Albumin | 73 | 4 | 26 | <1 | |||||
| Decreased Sodium | 48 | 11 | 30 | 6 | |||||
| Increased Aspartate Aminotransferase | 47 | 1 | 52 | 1 | |||||
| Increased Alkaline Phosphatase | 42 | 0 | 29 | <1 | |||||
| Increased alanine aminotransferase | 39 | 4 | 56 | 6 | |||||
| Decreased Magnesium | 38 | 1 | 17 | <1 | |||||
| Decreased Potassium | 37 | 11 | 12 | 3 | |||||
| Increased Gamma Glutamyl Transferase | 30 | 3 | 41 | 1 | |||||
| Decreased Calcium (Corrected) | 25 | 0 | 11 | 1 | |||||
| Hematology | |||||||||
| Decreased White Blood Cell | 90 | 42 | 85 | 19 | |||||
| Decreased Neutrophil Count | 74 | 49 | 64 | 25 | |||||
| Decreased Platelet Count | 74 | 17 | 58 | 9 | |||||
| Decreased Hemoglobin | 71 | 12 | 77 | 9 | |||||
| Decreased Lymphocyte Count | 69 | 28 | 58 | 18 | |||||
| Laboratory Abnormality | RYBREVANT + Carboplatin + Pemetrexed+ | Carboplatin + Pemetrexed | ||||||||
All Grades (%) | Grade 3 or 4 (%) | All Grades (%) | Grade 3 or 4 (%) | |||||||
| Albumin Decreased | 87 | 7 | 34 | 1 | ||||||
| Aspartate Aminotransferase Increased | 60 | 1 | 61 | 1 | ||||||
| Alanine Aminotransferase Increased | 57 | 4 | 54 | 1 | ||||||
| Sodium Decreased | 55 | 7 | 39 | 4 | ||||||
| Alkaline Phosphatase Increased | 51 | 1 | 28 | 0 | ||||||
| Potassium Decreased | 44 | 11 | 17 | 1 | ||||||
| Magnesium Decreased | 39 | 2 | 30 | 1 | ||||||
| Gamma-glutamyltransferase Increased | 38 | 4 | 43 | 4 | ||||||
| Calcium (Corrected) Decreased | 27 | 1 | 18 | 1 | ||||||
| Hematology | ||||||||||
| White Blood Cells Decreased | 89 | 17 | 76 | 10 | ||||||
| Hemoglobin Decreased | 79 | 11 | 85 | 13 | ||||||
| Neutrophils Decreased | 76 | 36 | 61 | 23 | ||||||
| Platelets Decreased | 70 | 10 | 54 | 12 | ||||||
| Lymphocytes Decreased | 61 | 11 | 49 | 13 | ||||||
Previously Treated NSCLC with EGFR Exon 20 Insertion Mutations
Laboratory abnormalities in CHRYSALIS are summarized in Table 17.
Table 17: Laboratory Abnormalities (≥10%) Worsening from Baseline in Patients Who Received RYBREVANT in CHRYSALIS
| Laboratory Abnormality | RYBREVANT (N=129) | |||||
| Laboratory Abnormality | RYBREVANT (N=129) | |||||
Change from Baseline All Grades (%) | Change from Baseline Grade 3 or 4 (%) | |||||
Change from Baseline All Grades (%) | Change from Baseline Grade 3 or 4 (%) | |||||
| Chemistry | ||||||
| Albumin Decreased | 79 | 8 | ||||
| Glucose Increased | 56 | 4 | ||||
| Alkaline Phosphatase Increased | 53 | 5 | ||||
| Creatinine Increased | 46 | 0 | ||||
| Alanine Aminotransferase Increased | 38 | 2 | ||||
| Phosphates Decreased | 33 | 8 | ||||
| Aspartate Aminotransferase Increased | 33 | 0 | ||||
| Gamma-glutamyltransferase Increased | 27 | 4 | ||||
| Magnesium Decreased | 27 | 0 | ||||
| Sodium Decreased | 27 | 4 | ||||
| Potassium Decreased | 26 | 6 | ||||
| Potassium Increased | 14 | 1 | ||||
| Glucose Decreased | 12 | 0 | ||||
| Hematology | ||||||
| Lymphocyte Count Decreased | 36 | 8 | ||||
| Hemoglobin Decreased | 18 | 2 | ||||
| Neutrophil Count Decreased | 18 | 3 | ||||
| Platelet Count Decreased | 17 | 1 | ||||
| White Blood Cell Decreased | 17 | 2 | ||||
| Note: Denominator used to calculate the rate is the number of patients with a baseline value and at least one post-treatment value for the specific lab test | ||||||
8.5. Post-Market Adverse Reactions
The following adverse reactions associated with the use of RYBREVANT were identified. Because some of these reactions were reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure.
Skin and subcutaneous tissue disorders: Skin ulcer
9. Drug Interactions
No formal drug interaction studies have been performed.
10. Clinical Pharmacology
10.1. Mechanism of Action
Amivantamab is a bispecific antibody that binds to the extracellular domains of the EGFR and MET receptors, disrupting EGFR and MET signaling functions through blocking ligand binding and enhancing degradation of these receptors. The presence of EGFR and MET on the surface of tumor cells also allows for targeting of these cells for destruction by immune effector cells, such as natural killer cells and macrophages, through antibody-dependent cellular cytotoxicity (ADCC) and trogocytosis mechanisms, respectively.
10.2. Pharmacodynamics
Pharmacodynamic responses of amivantamab in NSCLC patients with EGFR Exon 20 insertion, Exon 19 deletion, or Exon 21 substitution mutations have not been fully characterized.
10.3. Pharmacokinetics
Amivantamab pharmacokinetics (PK) as monotherapy or in combination with carboplatin and pemetrexed were assessed using non-compartmental analysis (NCA) and population PK. NCA PK parameters corresponding to 1050 mg (<80 kg) and 1400 mg (≥80 kg) are summarized in Table 18. Amivantamab exposure, based on amivantamab monotherapy data and assessed by area under the concentration-time curve (AUC1week), increases proportionally over a dose range from 350 to 1750 mg.
Based on the population pharmacokinetics of RYBREVANT, steady-state concentrations of RYBREVANT were reached by week 13 for both the recommended 3-week and 2-week dosing regimen and the systemic accumulation was 1.9-fold.
Table 18: Summary of Amivantamab Pharmacokinetic Parameters following Intravenous Administration as Monotherapy (1050 mg for <80 Kg or 1400 mg for ≥80 Kg)
| Parameter | Cmax (mcg/mL) Mean (SD) | Tmax (h) Median (Min – Max) | AUC0-168h (mcg.h/mL) Mean (SD) |
| Cycle 1 Day 1a,b | |||
| 1050 mg (<80 Kg) | 385 (89.2) | - | 33663 (9424) |
| 1400 mg (≥80 Kg) | 337 (74.8) | - | 28062 (5612) |
| Cycle 2 Day 1 c | |||
| 1050 mg (<80 Kg) | 836 (264) | 4.08 (2.03-8.33) | 94946 (35440) |
| 1400 mg (≥80 Kg) | 655 (109) | 5.72 (2.28-25.47) | 76946 (14557) |
a For 1050 (<80 Kg) mg, n=24 for AUC0-168h and n=23 for Cmax. For 1400 (≥80 Kg) mg, n=8 for AUC0-168h and Cmax. b Due to the split dose administration between Day 1 and Day 2, Tmax was not reported for at C1D1. c For 1050 (<80 Kg) mg, n=26 for Cmax and Tmax and n=25 for AUC0-168h. For 1400 (≥80 Kg) mg, n=13 for Cmax and Tmax and n=12 for AUC0-168h.
Distribution
Amivantamab mean ± SD volume of distribution estimated from population pharmacokinetic (PK) parameters was 5.34 ± 1.81 L.
Elimination
The geometric mean (% CV) linear clearance (CL) and terminal half-life associated with linear clearance estimated from population PK parameters were 0.266 L/day (30.4%), and 13.7 days (31.9%), respectively.
Special populations and conditions
No clinically meaningful differences in the pharmacokinetics of amivantamab were observed based on age (21-88 years). The clearance of amivantamab was 24% higher in males than in females. The population PK analysis estimated that amivantamab exposure was 35% higher in women than in men at steady state; however, no clinically meaningful differences were observed based on gender.
- Pediatrics (<18 years): The pharmacokinetics of amivantamab in pediatric patients have not been investigated.
Hepatic Insufficiency: No clinically meaningful difference in the pharmacokinetics of amivantamab was observed in patients with mild hepatic impairment [(total bilirubin ≤ ULN and AST > ULN) or (ULN < total bilirubin ≤ 1.5 x ULN and any AST)] or moderate hepatic impairment (1.5 x ULN < total bilirubin ≤ 3 x ULN and any AST). Data in patients with moderate hepatic impairment are limited (n=1). The pharmacokinetics of
- amivantamab have not been studied in patients with severe hepatic impairment (total bilirubin > 3 x ULN and any AST).
- Renal Insufficiency: No clinically meaningful difference in the pharmacokinetics of amivantamab was observed in patients with mild (60 ≤ creatinine clearance [CrCl] < 90 mL/min) and moderate (29 ≤ CrCl < 60 mL/min) or severe (15 ≤ CrCl < 29 mL/min) renal impairment. Data in patients with severe renal impairment are limited (n=1). The pharmacokinetics of amivantamab have not been studied in patients with end stage renal disease (CrCl <15 mL/min).
- Body Weight: Amivantamab volume of distribution and clearance increased with increasing body weight. Amivantamab exposures were 30-40% lower in patients who weighed ≥80 kg compared to patients with a body weight <80 kg when given the same dose. At the recommended dose of amivantamab, 1050 mg for patients with a body weight <80 kg and 1400 mg for patients with a body weight ≥80 kg, the amivantamab exposures were comparable.
10.4. Immunogenicity
All therapeutic proteins have the potential for immunogenicity.
The detection of antibody formation is highly dependent on the sensitivity and specificity of the assay. Additionally, the observed incidence of antibody (including neutralizing antibody) positivity in an assay may be influenced by several factors including assay methodology, sample handling, timing of sample collection, concomitant medications, and underlying disease. For these reasons, comparison of incidence of antibodies in the studies described below with the incidences of antibodies in other studies or to other products may be misleading.
In clinical trials of patients with locally advanced or metastatic NSCLC treated with RYBREVANT as monotherapy or as part of a combination therapy, 4 of the 1862 (0.2%) of participants who were treated with RYBREVANT and evaluable for the presence of anti-drug antibodies (ADA) tested positive for treatment emergent anti-amivantamab antibodies (one at 27 days, one at 59 days, one at 84 days, and one at 168 days after the first dose) with titers of 1:160 or less. Due to low immunogenicity observed with RYBREVANT, no meaningful conclusions can be made regarding the impact of ADAs on PK, safety (including IRRs), and efficacy.
- 11. Storage, Stability, and Disposal
Unopened vial:
Store in a refrigerator at 2°C to 8°C. Do not freeze. Store in the original carton in order to protect from light.
After dilution:
Since amivantamab solutions do not contain a preservative, unless the method of opening/dilution precludes the risk of microbial contamination, the product should be used immediately. Administer diluted solutions within 10 hours (including infusion time) at room temperature (15°C to 25°C) and in room light.
12. Special Handling Instructions
Do not freeze. Protect from light. This product contains no preservative. Any unused medicinal product should be disposed of in accordance with local requirements.
Part 2: Scientific Information
13. PHARMACEUTICAL INFORMATION
Drug Substance
Non-proprietary name of the drug substance: Amivantamab
Molecular mass: Approximately 148 kDa
Structure: Amivantamab is a low-fucose, fully human, bispecific Immunoglobulin G1 based bispecific antibody directed against the epidermal growth factor (EGF) and mesenchymal-epithelial transition (MET) receptors.
Physicochemical properties: RYBREVANT (amivantamab for injection) is available as a colorless to pale yellow preservative-free liquid concentrate for intravenous infusion after dilution.
Product Characteristics: Amivantamab is produced by a mammalian cell line (Chinese Hamster Ovary [CHO]) using recombinant DNA technology (see 10.1. Mechanism of Action).
14. Clinical Trials
14.1. Clinical Trials by Indication
Locally Advanced or Metastatic Non-Small Cell Lung Cancer (NSCLC) with EGFR Mutations
First-line Treatment of NSCLC with EGFR Exon 19 Deletion or Exon 21 L858R Substitution Mutation
Table 19: Description of the MARIPOSA study in patients with locally advanced or metastatic NSCLC with EGFR exon 19 deletions or exon 21 L858R substitution mutations
| Study # | Study design | Dosage, route of administration and duration | Study subjects (n) | Median age (range) | Sex |
| Study # | Study design | Dosage, route of administration and duration | Study subjects (n) | Median age (range) | Sex |
| MARIPOSA: NSC3003 | A Phase 3 randomized multicenter study to compare the efficacy and safety of the combination of RYBREVANT and lazertinib (Arm A) versus osimertinib monotherapy (Arm B) and | RYBREVANT + Lazertinib arm:
| RYBREVANT + Lazertinib arm: N=429 Osimertinib arm: N=429 Lazertinib arm: N=216 | 63 years (25-88) | Female: 61.6% Male: 38.4% |
| lazertinib monotherapy (Arm C) as first line treatment in patients with EGFRm NSCLC. |
Osimertinib arm:
Lazertinib arm:
| ||||
The MARIPOSA study is a randomized, active-controlled, multicenter Phase 3 study assessing the efficacy and safety of RYBREVANT in combination with lazertinib as compared to osimertinib monotherapy as first-line treatment in patients with EGFR-mutated locally advanced or metastatic NSCLC not amenable to curative therapy. Patient samples were required to have one of the two common EGFR mutations (exon 19 deletion or exon 21 L858R substitution mutation), as identified by local testing.
The primary efficacy endpoint for the MARIPOSA study was progression-free survival (PFS), defined as the time from randomization until the date of objective disease progression or death, whichever came first, based on blinded independent central review (BICR) using Response Evaluation Criteria in Solid Tumors (RECIST) v1.1. Key secondary endpoints were overall survival (OS), overall response rate (ORR) and duration of response (DOR).
A total of 1074 patients were randomized (2:2:1) to receive open label treatment with RYBREVANT in combination with lazertinib, and double-blinded treatment with osimertinib monotherapy, or lazertinib monotherapy (an unapproved regimen for NSCLC) until disease progression or unacceptable toxicity. Randomization was stratified by EGFR mutation type (exon 19 deletion or exon 21 L858R substitution mutation), race (Asian or non-Asian), and history of brain metastasis (yes or no). Evaluation of efficacy relied upon comparison between the RYBREVANT + lazertinib arm and the osimertinib arm.
Baseline demographics and disease characteristics were balanced across the treatment arms. The median age in the RYBREVANT + lazertinib arm was 64 (range: 25–88) years, and 63 (range 28-88) years in the osimertinib arm. In the RYBREVANT + lazertinib arm, 45% of patients were ≥65 years, 64% were female, 58% were Asian, and 38% were White. In the osimertinib arm, 45% of patients were ≥65 years, 59% were female, 59% were Asian and 38% were White. In the RYBREVANT + lazertinib arm, baseline Eastern Cooperative Oncology Group (ECOG)
performance status was 0 (33%) or 1 (67%); 70% never smoked; 41% had prior brain metastases; and 97% had Stage IV cancer at screening. In the osimertinib arm, baseline ECOG performance status was 0 (35%) or 1 (65%); 69% never smoked; 40% had prior brain metastases, and 97% had Stage IV cancer at screening. With regard to EGFR mutation status, 60% were exon 19 deletions and 40% were exon 21 L858R substitution mutations for both treatment arms.
Table 20, Figure 1, and Figure 2 summarize key efficacy results for RYBREVANT in combination with lazertinib.
Table 20: Efficacy Results in the MARIPOSA Study by BICR Assessment
| RYBREVANT + Lazertinib (N=429) | Osimertinib (N=429) | ||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|
| Progression-free survival (PFS)a | |||||||||||
| Number of events | 192 | 252 | |||||||||
| Median, months (95% CI) | 23.7 (19.12, 27.66) | 16.6 (14.78, 18.46) | |||||||||
| HR (95% CI); p-value | 0.70 (0.58, 0.85); p=0.0002 | ||||||||||
| Overall Survival (OS)b | |||||||||||
| Number of events | 173 | 217 | |||||||||
| Median, months (95% CI) | NE (42.9, NE) | 36.7 (33.4, 41.0) | |||||||||
| HR (95% CI); p-value | 0.75 (0.61, 0.92); p=0.0048 | ||||||||||
| Overall response rate (ORR)a,c | |||||||||||
| ORR % (95% CI) | 78% (71.4%, 82.1%) | 73% (69.0%, 77.5%) | |||||||||
| Complete response | 5.4% | 3.5% | |||||||||
| Partial response | 73.0% | 69.9% | |||||||||
| Duration of response (DOR)a,d | |||||||||||
| Median (95% CI), months | 25.8 (20.14, NE) | 16.7 (14.75, 18.53) | |||||||||
BICR – blinded independent central review; CI – confidence intervals; HR – hazard ratio; NE – not estimable a BICR by RECIST v.1.1
b Based on the results of the final analysis of OS with a median follow-up of 37.8 months
c Confirmed responses in ITT population
d In confirmed responders
Figure 1: Kaplan-Meier curve of PFS in previously untreated NSCLC patients by BICR assessment
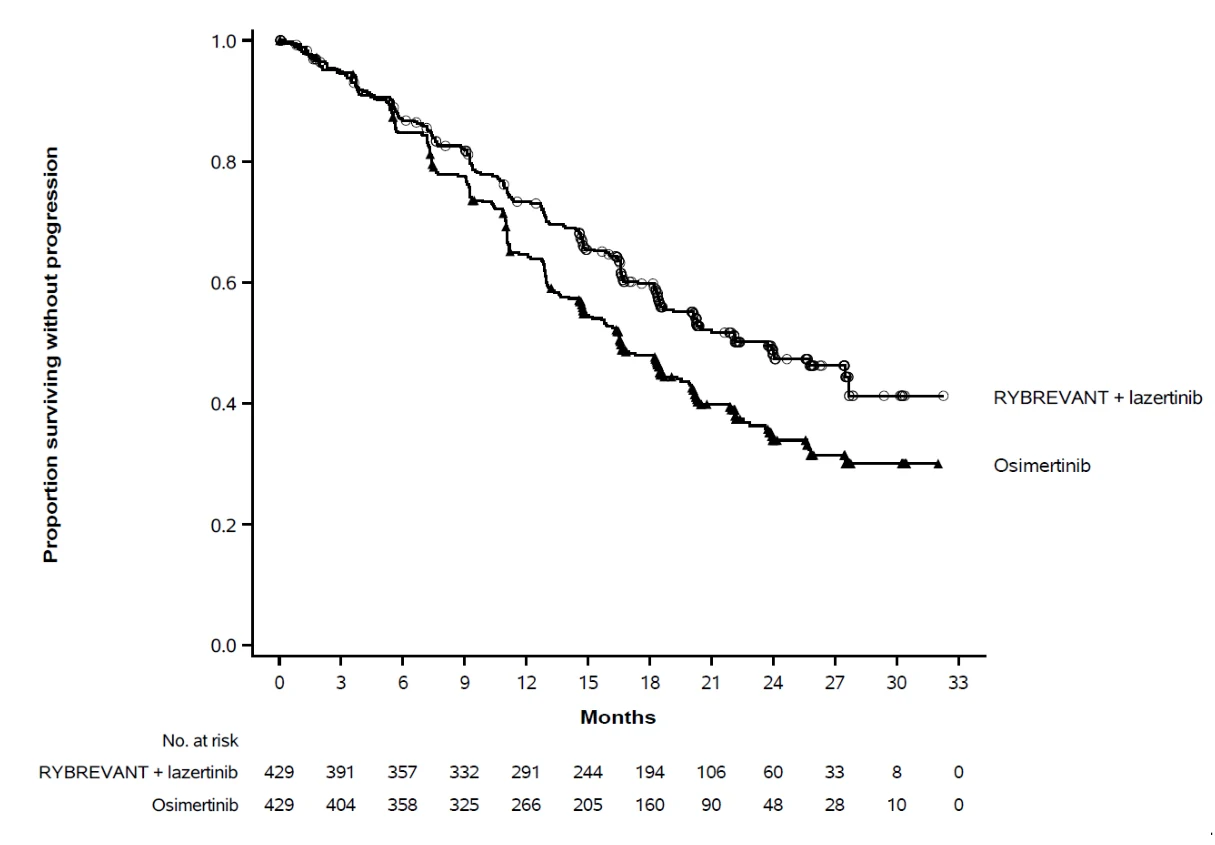
Figure 2: Kaplan-Meier curve of OS in previously untreated NSCLC patients
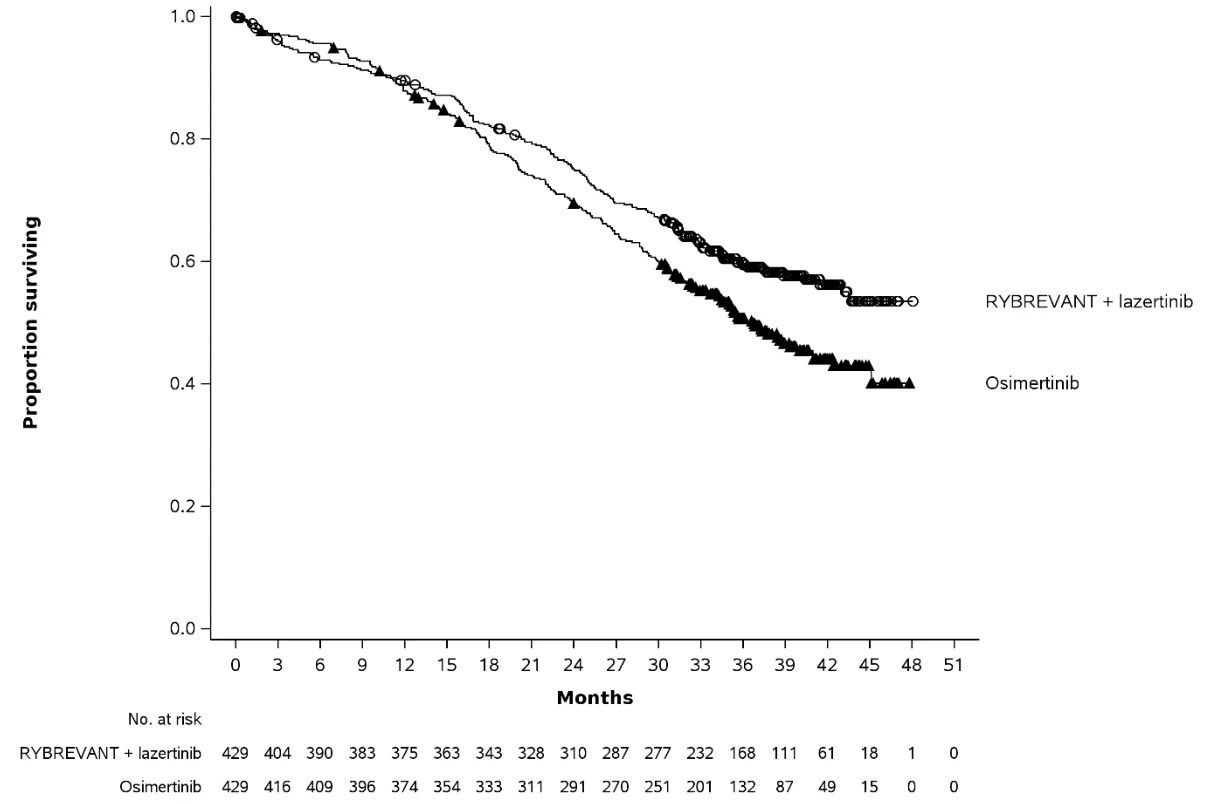
Results of pre-specified exploratory analyses of central nervous system (CNS) ORR by BICR in the subset of patients with measurable intracranial lesions at baseline for the combination of RYBREVANT and lazertinib demonstrated similar intracranial ORR to the control. Per protocol, all patients in MARIPOSA had serial brain MRIs to assess intracranial response and duration. Results are summarized in Table 21.
Table 21: Intracranial ORR by BICR assessment in subjects with measurable intracranial lesions at baseline
| RYBREVANT + lazertinib (N=180) | Osimertinib (N=187) | |||||
|---|---|---|---|---|---|---|
| Intracranial Tumor Response Assessment | ||||||
| Number of confirmed responders | 122 | 129 | ||||
| Intracranial ORR (CR+PR), % (95% CI) | 67.8 (60.4,74.5) | 69.0 (61.8,75.5) | ||||
| Complete response % | 55.0 | 52.4 | ||||
Subgroup Analyses
The outcomes of the subgroup analyses for PFS and OS were generally consistent across the prespecified subgroups; however, differences were seen in subgroups of geriatric patients. No formal statistical testing was planned for subgroup analyses and the clinical interpretation of the subgroup analyses is therefore limited (see Table 22 and Table 23).
Table 22: Progression-Free survival for pre-defined subgroups based on age in MARIPOSA study by BICR assessment
| Subgroups | HR (95% CI) | Events / N RYBREVANT + Lazertinib | Events / N Osimertinib | ||||||
|---|---|---|---|---|---|---|---|---|---|
| Age | |||||||||
| <65 | 0.50 (0.39, 0.65) | 94/235 | 153/237 | ||||||
| ≥65 | 1.06 (0.80, 1.41) | 98/194 | 99/192 | ||||||
| <75 | 0.70 (0.57, 0.85) | 165/378 | 220/376 | ||||||
| ≥75 | 0.77 (0.46, 1.30) | 27/51 | 32/53 | ||||||
BICR – blinded independent central review; HR – hazard ratio; CI – confidence interval
Table 23: Overall Survival for pre-defined subgroups based on age in MARIPOSA study
| Subgroups | HR (95% CI) | Events / N RYBREVANT + Lazertinib | Events / N Osimertinib | ||||||
|---|---|---|---|---|---|---|---|---|---|
| Age | |||||||||
| <65 | 0.53 (0.40, 0.70) | 76/235 | 123/237 | ||||||
| ≥65 | 1.11 (0.84, 1.48) | 97/194 | 94/192 | ||||||
| <75 | 0.75 (0.60, 0.93) | 147/378 | 185/376 | ||||||
| ≥75 | 0.79 (0.47, 1.33) | 26/51 | 32/53 | ||||||
Based on the results of the final analysis of OS with a median follow-up of 37.8 months
Previously Treated NSCLC with EGFR Exon 19 Deletions or Exon 21 L858R Substitution Mutations
Table 24: Summary of patient demographics for MARIPOSA-2 clinical trial (NSC3002) in patients with previously treated NSCLC with EGFR Exon 19 Deletions or Exon 21 L858R Substitution Mutations
| Study # | Study design | Dosage, route of administration and duration | Study subjects (n) | Median age (range) | Sex |
|---|---|---|---|---|---|
| Study # | Study design | Dosage, route of administration and duration | Study subjects (n) | Median age (range) | Sex |
NSC3002 (MARIPOSA-2) | Phase 3, randomized, open label, | RYBREVANT: 1400 mg, <80 kg body | N=394 RYBREVANT + carboplatin + pemetrexed | 62 years (31-85) | Female: 60.4% Male: 39.6% |
| multicentre study | weight, or 1750 mg, >80 kg body weight IV, once weekly through 4 weeks. Starting at Week 7 1,750 mg, <80 kg body weight, or 2,100 mg, ≥80 kg body weight IV, once every 3 weeks until disease progression or unacceptable toxicity. Carboplatin: AUC 5*, IV, once every 3 weeks for up to 12 weeks. Pemetrexed: 500 mg/m2, IV, once every 3 weeks until disease progression or unacceptable toxicity. | n=131 carboplatin+ pemetrexed n=263 | |||
*AUC5 = area under the concentration-time curve 5 mg/mL per minute
The efficacy of RYBREVANT was evaluated in patients with locally advanced or metastatic NSCLC with EGFR Exon 19 deletions or Exon 21 L858R substitution mutations (characterized by a validated test at or after the time of locally advanced or metastatic disease diagnosis, as identified by local or central testing) who had previously received osimertinib as first or second line therapy in MARIPOSA-2, an open-label, multicenter phase 3 clinical trial. In MARIPOSA-2, patients were randomised (2:2:1) to receive carboplatin and pemetrexed (CP, N=263), RYBREVANT in combination with carboplatin and pemetrexed (RYBREVANT-CP, N=131) and RYBREVANT in combination with lazertinib, carboplatin, and pemetrexed (N=263) in a separate arm of the study (an unapproved regimen for EGRFm NSCLC).
Patients were stratified by osimertinib line of therapy (first-line or second-line), prior brain metastases (yes or no), and Asian race (yes or no).
The primary efficacy endpoint was progression-free survival (PFS) as assessed by blinded independent central review (BICR) using RECIST 1.1. Secondary efficacy endpoints were overall response rate (ORR) and overall survival (OS). PFS and ORR were evaluated at the first interim analysis. There are two interim, and one final analysis planned for OS.
Of the 394 patients randomized to the RYBREVANT-CP arm or CP arm, the median age was 62 (range: 31–85) years, with 37.8% of the patients ≥ 65 years of age; 60.4% were female; and 48.2% were Asian and 46.4% were White. Baseline Eastern Cooperative Oncology Group (ECOG) performance status was 0 (39.6%) or 1 (60.4%); 65.5% never smoked; 45.2% had history of brain metastasis, and 91.6% had Stage IV cancer at initial diagnosis. Osimertinib had been given as first-line systemic therapy for 70.5% of participants and second-line therapy for 29.4% of participants.
Efficacy results are summarized in Table 25 and Figure 3.
Table 25: Efficacy results in MARIPOSA-2
RYBREVANT + Carboplatin + Pemetrexed (N=131) | Carboplatin + Pemetrexed (N=263) | |||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Progression-free survival (PFS)a | ||||||||||||
| Number of events (%) | 74 (56.5%) | 171 (65.0%) | ||||||||||
| Median, months (95% CI) | 6.28 (5.55, 8.41) | 4.17 (4.04, 4.44) | ||||||||||
| HR (95% CI); p-value | 0.48 (0.36, 0.64); p<0.0001 | |||||||||||
| Overall response ratea | ||||||||||||
| ORR, % (95% CI) | 63.8% (55.0, 72.1) | 36.2% (30.3, 42.3) | ||||||||||
| Complete response | 1.5% | 0.4% | ||||||||||
| Partial response | 62.3% | 35.8% | ||||||||||
CI = confidence interval NE = not estimatable a Blinded Independent Central Review by RECIST v1.1 | ||||||||||||
Figure 3: Kaplan-Meier curve of PFS in Previously Treated NSCLC Patients by BICR assessment - MARIPOSA-2
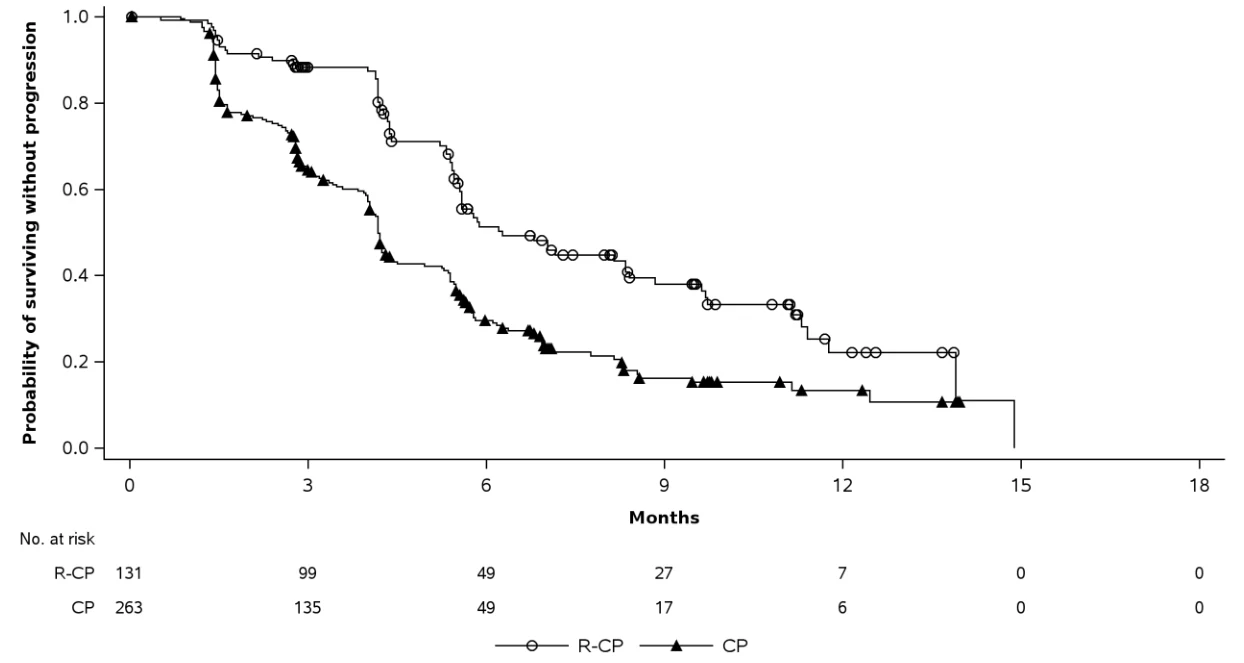
The median duration of response was 6.90 months (95% CI: 5.52, NE months) for patients who received RYBREVANT plus carboplatin and pemetrexed and 5.5 months (95% CI: 4.17, 9.56 months) for patients treated with carboplatin and pemetrexed alone.
The estimated OS HR at the first interim analysis was 0.77 [95% CI: 0.49, 1.21], however OS remains immature at the time of this analysis.
Patients with asymptomatic or previously treated and stable intracranial metastases were eligible to be randomized in MARIPOSA-2. In an exploratory sub-group analysis, in patients with stable intracranial metastases, the observed median intracranial PFS for RYBREVANT-CP was 12.45 months vs 8.31 months in the CP arm; HR=0.55 (95%CI 0.38, 0.79).
First-line Treatment of NSCLC with EGFR Exon 20 Insertion Mutations
Table 26: Summary of patient demographics for the PAPILLON clinical trial (NSC3001) in patients with previously untreated NSCLC with Exon 20ins mutations
| Study # | Study design | Dosage, route of administration and duration | Study subjects (n) | Median age (range) | Sex |
|---|---|---|---|---|---|
| Study # | Study design | Dosage, route of administration and duration | Study subjects (n) | Median age (range) | Sex |
| PAPILLON: NSC3001 | Phase 3, randomized, open label, | RYBREVANT: 1400 mg, <80 kg | N=308 RYBREVANT + carboplatin + | 62 years (27-92) | Female: |
| multicentre study | body weight, or 1750 mg, >80 kg body weight IV, once weekly through 4 weeks. Starting at Week 7 1,750 mg, <80 kg body weight, or 2,100 mg, ≥80 kg body weight IV, once every 3 weeks until disease progression or unacceptable toxicity. Carboplatin: AUC 5*, IV, once every 3 weeks for up to 12 weeks. Pemetrexed: 500 mg/m2, IV, once every 3 weeks until disease progression or unacceptable toxicity. | pemetrexed n=153 Carboplatin + pemetrexed n=155 | 58% Male: 42% | ||
*AUC5 = area under the concentration-time curve 5 mg/mL per minute
PAPILLON (NSC3001) is a randomized, open-label, multicenter phase 3 study comparing treatment with RYBREVANT in combination with carboplatin and pemetrexed to treatment as compared to chemotherapy alone (carboplatin and pemetrexed) in subjects with treatment-naïve, locally advanced or metastatic NSCLC with EGFR Exon 20 insertion mutations, as identified prospectively by local testing.
Patients with squamous NSCLC, untreated brain metastases, with a medical history of ILD, or any evidence of clinically active ILD were excluded from the clinical study.
Randomization was stratified by ECOG performance status and prior brain metastases.
The primary efficacy outcome measure was progression-free survival (PFS) as assessed by blinded independent central review (BICR) using RECIST 1.1. Secondary efficacy outcome measures were overall response rate (ORR) and overall survival (OS). Subjects randomized to the carboplatin and pemetrexed arm who had confirmed disease progression were permitted to cross over to receive RYBREVANT monotherapy.
A total of 308 subjects were randomized (1:1) to RYBREVANT in combination with carboplatin and pemetrexed (N=153) or carboplatin and pemetrexed (N=155). The median age was 62 (range: 27 to 92) years, with 39% of the subjects ≥65 years of age; 58% were female; and 61% were Asian and 36% were White. Baseline Eastern Cooperative Oncology Group (ECOG) performance status was 0 (35%) or 1 (65%); 58% never smoked; 23% had history of brain metastasis and 84% had Stage IV cancer at initial diagnosis (99% had Stage IV cancer at screening).
The median follow-up time at the time of the PFS analysis was 14.9 (range: 0.3 to 27.0) months.
Efficacy results for PAPILLON are summarized in Table 27 and Figure 4.
Table 27: Efficacy Results in PAPILLON
RYBREVANT+ carboplatin+ pemetrexed (N=153) | Carboplatin+ pemetrexed (N=155) | ||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|
| Progression-free survival (PFS) a | |||||||||||
| Number of events (%) | 84 (55%) | 132 (85%) | |||||||||
| Median, months (95% CI) | 11.4 (9.8, 13.7) | 6.7 (5.6, 7.3) | |||||||||
| HR (95% CI); p-valueb | 0.40 (0.30, 0.53); p<0.0001 | ||||||||||
| Overall response rate (ORR)a,c | |||||||||||
| ORR, % (95% CI) | 73% (65%, 80%) | 47% (39%, 56%) | |||||||||
| p-valued | p<0.0001 | ||||||||||
| Complete response | 3.9% | 0.7% | |||||||||
| Partial response | 69% | 47% | |||||||||
CI = confidence interval a Blinded Independent Central Review by RECIST v1.1 b p-value is from a log-rank test stratified by ECOG PS (0 or 1) and history of brain metastases (yes or no). c Including Unconfirmed Response. d p-value is from a logistic regression model stratified by ECOG PS (0 or 1) and history of brain metastases (yes or no). | |||||||||||
Figure 4: Kaplan-Meier Curve of PFS in Previously Untreated NSCLC Patients by BICR Assessment
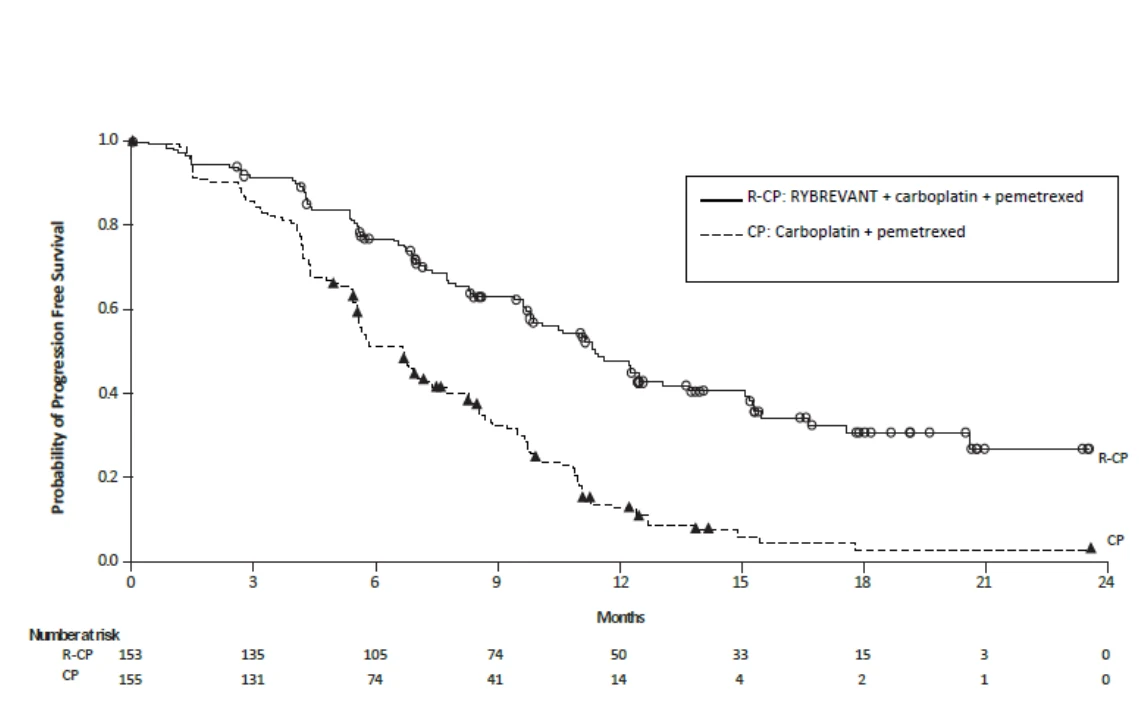
The overall response rate (ORR) for patients who had a confirmed response was 67.1% for patients who received RYBREVANT plus carboplatin and pemetrexed and 36.2% for patients treated with carboplatin and pemetrexed alone. For patients who achieved a confirmed overall response, the median duration of response was 10.1 months (range: 1.4 to 22.3 months) for patients who received RYBREVANT plus carboplatin and pemetrexed and 5.6 months (range: 1.3 to 22.4 months) for patients treated with carboplatin and pemetrexed alone.
At this PFS analysis, 65 (42%) patients who were randomized to the carboplatin and pemetrexed arm had crossed over to receive subsequent RYBREVANT monotherapy. At the prespecified first interim analysis for overall survival (OS), conducted at the time of the primary analysis of PFS, statistical significance had not been reached (HR=0.72 [95% CI: 0.44, 1.17]).
Previously Treated NSCLC with EGFR Exon 20 insertion mutations
Table 28: Summary of patient demographics for the CHRYSALIS clinical trial (EDI1001) in patients with previously treated NSCLC with Exon 20ins mutations
| Study # | Study design | Dosage, route of administration and duration | Study subjects (n) | Median age (range) | Sex |
| Study # | Study design | Dosage, route of administration and duration | Study subjects (n) | Median age (range) | Sex |
| CHRYSALIS: EDI1001 | Phase 1, open label, single | 1050 mg, <80 kg body weight | N=81 (efficacy | 62 years (42-84) | Female: 48 Male: 33 |
| arm, multi-cohort study | 1400 mg, >80 kg body weight IV, once weekly in cycle 1; bi-weekly thereafter | population) | |||
CHRYSALIS (EDI1001) was a multicenter, open-label, multi-cohort study conducted to assess the safety and efficacy of RYBREVANT in patients with locally advanced or metastatic NSCLC. Efficacy was evaluated in 81 patients with locally advanced or metastatic NSCLC who had EGFR Exon 20 insertion mutation, with measurable disease, whose disease had progressed on or after platinum-based chemotherapy. For enrollment, EGFR exon 20 insertion mutation status was determined prospectively by local testing using tissue and/or plasma samples. Patients with untreated brain metastases and patients with a history of ILD requiring treatment with prolonged steroids or other immunosuppressive agents within the last 2 years were not eligible for the study. The median follow-up for the efficacy population was 9.7 months.
RYBREVANT was administered intravenously at 1050 mg for patients <80 kg or 1400 mg for patients ≥80 kg once weekly for 4 weeks, then every 2 weeks starting at Week 5 until disease progression or unacceptable toxicity. The major efficacy outcome measure was overall response rate (ORR) according to Response Evaluation Criteria in Solid Tumors (RECIST v1.1) as evaluated by Blinded Independent Central Review (BICR). Duration of response (DOR) by BICR was assessed as an additional measure of efficacy.
The median age was 62 (range: 42–84) years, with 9% of the patients ≥75 years of age; 59% were female; and 49% were Asian and 37% were White; 74% had baseline body weight <80 kg; 95% had adenocarcinoma; and 46% had received prior immunotherapy. The median number of prior therapies was 2 (range: 1 to 7 therapies). At baseline, 99% had Eastern Cooperative Oncology Group (ECOG) performance status of 0 or 1; 53% never smoked; 75% had Stage IV cancer; and 22% had previous treatment for brain metastases. Insertions in Exon 20 were observed at 8 different residues; the most common residues were A767 (24%), S768 (16%), D770 (11%), and N771 (11%).
Efficacy results are summarized in Table 29.
Table 29: Results from CHRYSALIS: Patients with EGFR Exon 20 insertion mutations whose disease has progressed on or after platinum-based chemotherapy
Prior Platinum Chemotherapy Treated (N=81) | |
|---|---|
Prior Platinum Chemotherapy Treated (N=81) | |
| Overall Response Rate a,b (95% CI) | 40% (29%, 51%) |
| Complete response (%) | 3.7% |
| Partial response (%) | 35.8% |
| Duration of Response a (DOR) | |
| Median (95% CI), months c | 11.1 (6.9, NE) |
| Patients with DOR ≥6 months | 63% |
a Blinded Independent Central Review by RECIST v1.1
b Confirmed response.
c Based on Kaplan-Meier estimate.
NE=Not Estimable
15. Microbiology
No microbiological information is required for this product.
16. Non-Clinical Toxicology
General Toxicology: In repeat-dose toxicity studies in cynomolgus monkeys, amivantamab was well-tolerated at weekly doses up to 120 mg/kg intravenously for 3 months and up to 125 mg/kg subcutaneously for 2 weeks. There were no effects on cardiovascular, respiratory, and nervous system function. Clinical pathology demonstrated non-adverse elevations in serum alanine aminotransferase (ALT), aspartate aminotransferase (AST), and globulins, and non-adverse decreases in albumin when compared to the control group. All these values returned to normal ranges in recovery groups.
Genotoxicity: Routine genotoxicity studies are generally not applicable to biologic pharmaceuticals as large proteins cannot diffuse into cells and cannot interact with DNA or chromosomal material.
Carcinogenicity: No animal studies have been performed to establish the carcinogenic potential of amivantamab. Routine carcinogenicity studies are generally not applicable to biologic pharmaceuticals as large proteins cannot diffuse into cells and cannot interact with DNA or chromosomal material.
Reproductive and Developmental Toxicology: No long-term animal studies have been performed to evaluate whether amivantamab affects fertility in males or females or reproduction.
Based on its mechanism of action, amivantamab could cause fetal harm or developmental abnormalities when administered to a pregnant woman. Evidence from published literature showed that inhibition of EGFR and/or MET signaling pathways during pregnancy can cause impaired embryo-fetal development, embryo lethality and abortions in mice, rats and non-human primates. Therefore, it is reasonable to expect that amivantamab may cause adverse effects on embryo-fetal and postnatal development in humans.